Megaloblastic anemia is a macrocytic anemia (MCV above 100 fL) caused by impaired DNA synthesis, most often from vitamin B12 or folate deficiency: nuclei mature more slowly than the cytoplasm, producing macro-ovalocytes, hypersegmented neutrophils and ineffective hematopoiesis that can lower all three cell lines. Both deficiencies raise homocysteine, but only B12 deficiency raises methylmalonic acid (MMA) and causes subacute combined degeneration of the spinal cord and peripheral neuropathy, sometimes before any anemia appears. The acronym: B12 = BRAIN, folate = FOOD. The rule that protects patients: exclude B12 deficiency before giving folic acid alone, because folate can correct the blood count while neurologic damage progresses.
Why the cells get big
- Folate, as tetrahydrofolate (THF), carries the one-carbon units needed to build DNA (purines and thymidine). Review the pathways in de novo vs salvage nucleotide synthesis.
- B12 is the cofactor for two enzymes:
- Methionine synthase moves a methyl group from 5-methyl-THF onto homocysteine, making methionine and freeing THF. Without B12, folate is stuck as 5-methyl-THF (the "methyl-folate trap") and homocysteine builds up, so B12 deficiency starves DNA synthesis of usable folate.
- Methylmalonyl-CoA mutase converts methylmalonyl-CoA to succinyl-CoA. Only B12 deficiency blocks it, so MMA rises only in B12 deficiency.
- DNA synthesis slows while RNA synthesis continues, so precursors grow large with immature-looking nuclei (megaloblasts). Many die in the marrow (ineffective erythropoiesis): the reticulocyte count is low, and because every cell line is affected, leukopenia and thrombocytopenia can follow.
- Smear: macro-ovalocytes, hypersegmented neutrophils, Howell-Jolly bodies, variation in size and shape, and a high RDW.
The acronym trick: B12 = BRAIN, folate = FOOD
B12 deficiency hits the marrow and the brain; folate deficiency hits the marrow (and the developing fetal neural tube).
B12 = BRAIN
| Letter | Stands for | What to remember |
|---|---|---|
| B | Bad absorption | The usual cause: pernicious anemia, gastric or bariatric surgery, terminal ileal disease or resection (Crohn disease), fish tapeworm, bacterial overgrowth, chronic pancreatitis; drugs such as metformin, PPIs and H2 blockers |
| R | Reserves last years | Liver stores cover 3-5 years (months to a year if enterohepatic reabsorption is lost), so deficiency appears long after the cause; dietary deficiency hits vegans and breastfed infants of vegan mothers |
| A | Acid (methylmalonic) is up | MMA and homocysteine both rise; MMA is also raised by kidney failure |
| I | Intrinsic factor | Made by parietal cells and needed for absorption in the terminal ileum. Pernicious anemia (autoimmune metaplastic atrophic gastritis) shuts off its production; tests include intrinsic factor antibodies and serum gastrin, with a higher risk of stomach cancer |
| N | Nerves | Subacute combined degeneration: dorsal columns (lost vibration and position sense, ataxia) plus lateral corticospinal tracts (spasticity, extensor plantar responses); peripheral neuropathy; confusion, paranoia, depression. Repeated nitrous oxide exposure is another cause |
Folate = FOOD
| Letter | Stands for | What to remember |
|---|---|---|
| F | Fast to run out | Liver stores last only a few months |
| O | Out of the diet | Few raw green vegetables or enriched grains, prolonged cooking, and alcohol use disorder (impairs absorption, metabolism and reabsorption) |
| O | Overdrawn | Pregnancy, lactation and infancy raise demand; peritoneal dialysis and hemodialysis increase losses |
| D | Drugs and duodenum | Methotrexate and trimethoprim (dihydrofolate reductase inhibitors), phenytoin, metformin, triamterene; folate is absorbed in the duodenum and upper jejunum, so celiac disease and tropical sprue cause malabsorption |
The neuro picture is drawn out in the subacute combined degeneration flowchart and the spinal cord tracts visual hack.
B12 vs folate deficiency at a glance
| Feature | Vitamin B12 deficiency | Folate deficiency |
|---|---|---|
| Smear | Macro-ovalocytes, hypersegmented neutrophils | Same |
| Homocysteine | High | High |
| Methylmalonic acid | High | Normal |
| Nervous system | Subacute combined degeneration, neuropathy, cognitive changes; can precede anemia and become permanent | No myelopathy or neuropathy (classic exam rule); Merck lists depression and confusion |
| Other | Glossitis, weight loss | Glossitis, diarrhea; neural tube defects in pregnancy |
| Stores | Years | Months |
| Absorbed in | Terminal ileum, with intrinsic factor | Duodenum and upper jejunum |
| Serum level | Below 200 pg/mL is deficient; borderline values need MMA | Low serum or RBC folate |
| Treatment | IM or high-dose oral B12 (below) | Folic acid 400-1,000 mcg daily once B12 deficiency is excluded |
The "never folate alone" rule
Merck's wording is blunt: always exclude B12 deficiency before supplementing folate, because folate can mask a concomitant B12 deficiency by improving the anemia while neurologic complications progress. The same logic appears on the leucovorin label, which says leucovorin is not for pernicious anemia or other B12-deficient megaloblastic anemias "because of the risk of progression of neurologic manifestations despite hematologic remission." The reverse also happens: the cyanocobalamin nasal spray label warns that B12 doses above 10 mcg daily can produce a hematologic response in folate-deficient megaloblastic anemia, hiding that deficiency. If a smear says megaloblastic, measure both vitamins (and MMA when B12 is borderline) before treating.
Treatment and response
- Severe B12 deficiency or any neurologic signs: cyanocobalamin 1 mg IM, 1-4 times a week for several weeks until the blood count corrects, then monthly; pernicious anemia needs treatment for life (Merck).
- Mild to moderate deficiency without neurologic signs: oral B12 1,000-2,000 mcg daily works even without intrinsic factor, because large doses are absorbed by mass action (about 1-2% passively).
- Intranasal cyanocobalamin (500 mcg once weekly) is labeled for maintenance in pernicious anemia after remission on IM therapy, in patients without nervous system involvement.
- Expected response: reticulocytes rise within about 1 week and the blood count usually corrects within 6 weeks; nerves recover more slowly, and deficits present for months or years can be permanent.
- Watch potassium: the nasal B12 label warns that hypokalemia and sudden death can occur when severe megaloblastic anemia is treated intensively with B12.
- Folate: folic acid 400-1,000 mcg daily (Merck) after B12 deficiency is excluded. For prevention, USPSTF (2023) recommends 0.4-0.8 mg daily for anyone planning or able to become pregnant; after a pregnancy affected by a neural tube defect, Merck advises 4 mg daily, starting 3 months before conception.
- Methotrexate toxicity: leucovorin (folinic acid) is a reduced folate that bypasses the blocked dihydrofolate reductase.
How USMLE tests it
- Numb feet, lost vibration sense, positive Romberg sign + macrocytosis = B12, even when the hemoglobin is normal.
- Gastric bypass or ileal resection years ago = B12 (stores take years to run out).
- Alcohol use disorder, poor diet, no neuro signs = folate; alcohol also causes macrocytosis without megaloblasts, so look for hypersegmented neutrophils.
- Pregnancy or planning pregnancy = folic acid supplementation to prevent neural tube defects.
- Methotrexate, trimethoprim or phenytoin = folate antagonism or depletion.
- Anemia improved on folic acid but gait got worse = unmasked B12 deficiency.
- Macrocytosis without megaloblasts: chronic liver disease, alcohol (MCV usually about 100-105 fL), reticulocytosis, myelodysplasia, aplastic anemia, monoclonal gammopathies and post-splenectomy.
- The B12 mimic after bariatric surgery: copper deficiency (also caused by excess zinc) gives anemia, neutropenia and a myelopathy and neuropathy that resemble B12 deficiency, and it can sometimes cause megaloblastic changes.
- For more vignette practice, try the folate vs B12 question breakdown.
Practice question
A 58-year-old woman who had a Roux-en-Y gastric bypass 6 years ago and stopped taking her supplements has 4 months of fatigue, numb feet and unsteadiness that is worse in the dark. Vibration and position sense are reduced in both legs, Romberg sign is positive, knee reflexes are brisk and plantar responses are extensor. Hemoglobin is 9.8 g/dL, MCV is 112 fL, and the smear shows hypersegmented neutrophils. Which laboratory pattern is most likely?
A. Elevated methylmalonic acid and elevated homocysteine B. Normal methylmalonic acid and elevated homocysteine C. Normal methylmalonic acid and normal homocysteine D. Low ferritin and high total iron-binding capacity E. Elevated reticulocyte count
Answer: A. Gastric and bariatric surgery are classic causes of B12 malabsorption, and the deficiency appears years later, once the liver's stores run out. Dorsal column loss plus corticospinal signs is subacute combined degeneration. B12 is needed by both methionine synthase and methylmalonyl-CoA mutase, so both homocysteine and MMA rise. She needs IM vitamin B12 (neurologic signs), not folic acid alone.
- B: the folate deficiency pattern: homocysteine rises but MMA stays normal, and folate deficiency does not cause myelopathy.
- C: normal metabolites point away from a vitamin cause of macrocytosis (for example alcohol, liver disease or myelodysplasia).
- D: the iron deficiency pattern, which gives a microcytic anemia; review it in iron deficiency anemia. Bariatric patients can have both, but iron deficiency does not explain an MCV of 112 fL or the neurologic signs.
- E: megaloblastic anemia causes reticulocytopenia from ineffective erythropoiesis. A high reticulocyte count suggests hemolysis or blood loss; reticulocytosis itself can raise the MCV but does not produce hypersegmented neutrophils.
Key takeaways
- Megaloblastic anemia = impaired DNA synthesis: MCV above 100 fL, macro-ovalocytes, hypersegmented neutrophils, low reticulocytes, possible pancytopenia.
- B12 = BRAIN: Bad absorption, Reserves last years, Acid (MMA) up, Intrinsic factor, Nerves (subacute combined degeneration, nitrous oxide).
- Folate = FOOD: Fast to run out, Out of the diet (alcohol), Overdrawn (pregnancy), Drugs (methotrexate, trimethoprim, phenytoin) and duodenum (celiac disease).
- Homocysteine rises in both; MMA rises only in B12 deficiency.
- Never give folate alone until B12 deficiency is excluded; neurologic damage can progress and become permanent.
- B12 treatment: IM for severe deficiency or neurologic signs, high-dose oral otherwise; monitor potassium early in severe cases.
- Folic acid 0.4-0.8 mg daily for anyone who could become pregnant (USPSTF 2023); 4 mg after a prior neural tube defect.
Sources
- Megaloblastic Macrocytic Anemias — Merck Manual Professional Edition (2025)
- Vitamin B12 Deficiency — Merck Manual Professional Edition (2026)
- Folate Deficiency — Merck Manual Professional Edition (2026)
- Vitamin B12: Health Professional Fact Sheet — NIH Office of Dietary Supplements (2025)
- Folate: Health Professional Fact Sheet — NIH Office of Dietary Supplements (2026)
- Folic Acid for the Prevention of Neural Tube Defects: Preventive Medication — US Preventive Services Task Force (2023)
- Nascobal (cyanocobalamin) Nasal Spray Label — DailyMed (2024)
- Leucovorin Calcium Tablets Label — DailyMed (2026)
- Subacute Combined Degeneration of the Spinal Cord — StatPearls, NCBI Bookshelf (2024)
- Copper Deficiency — Merck Manual Professional Edition (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
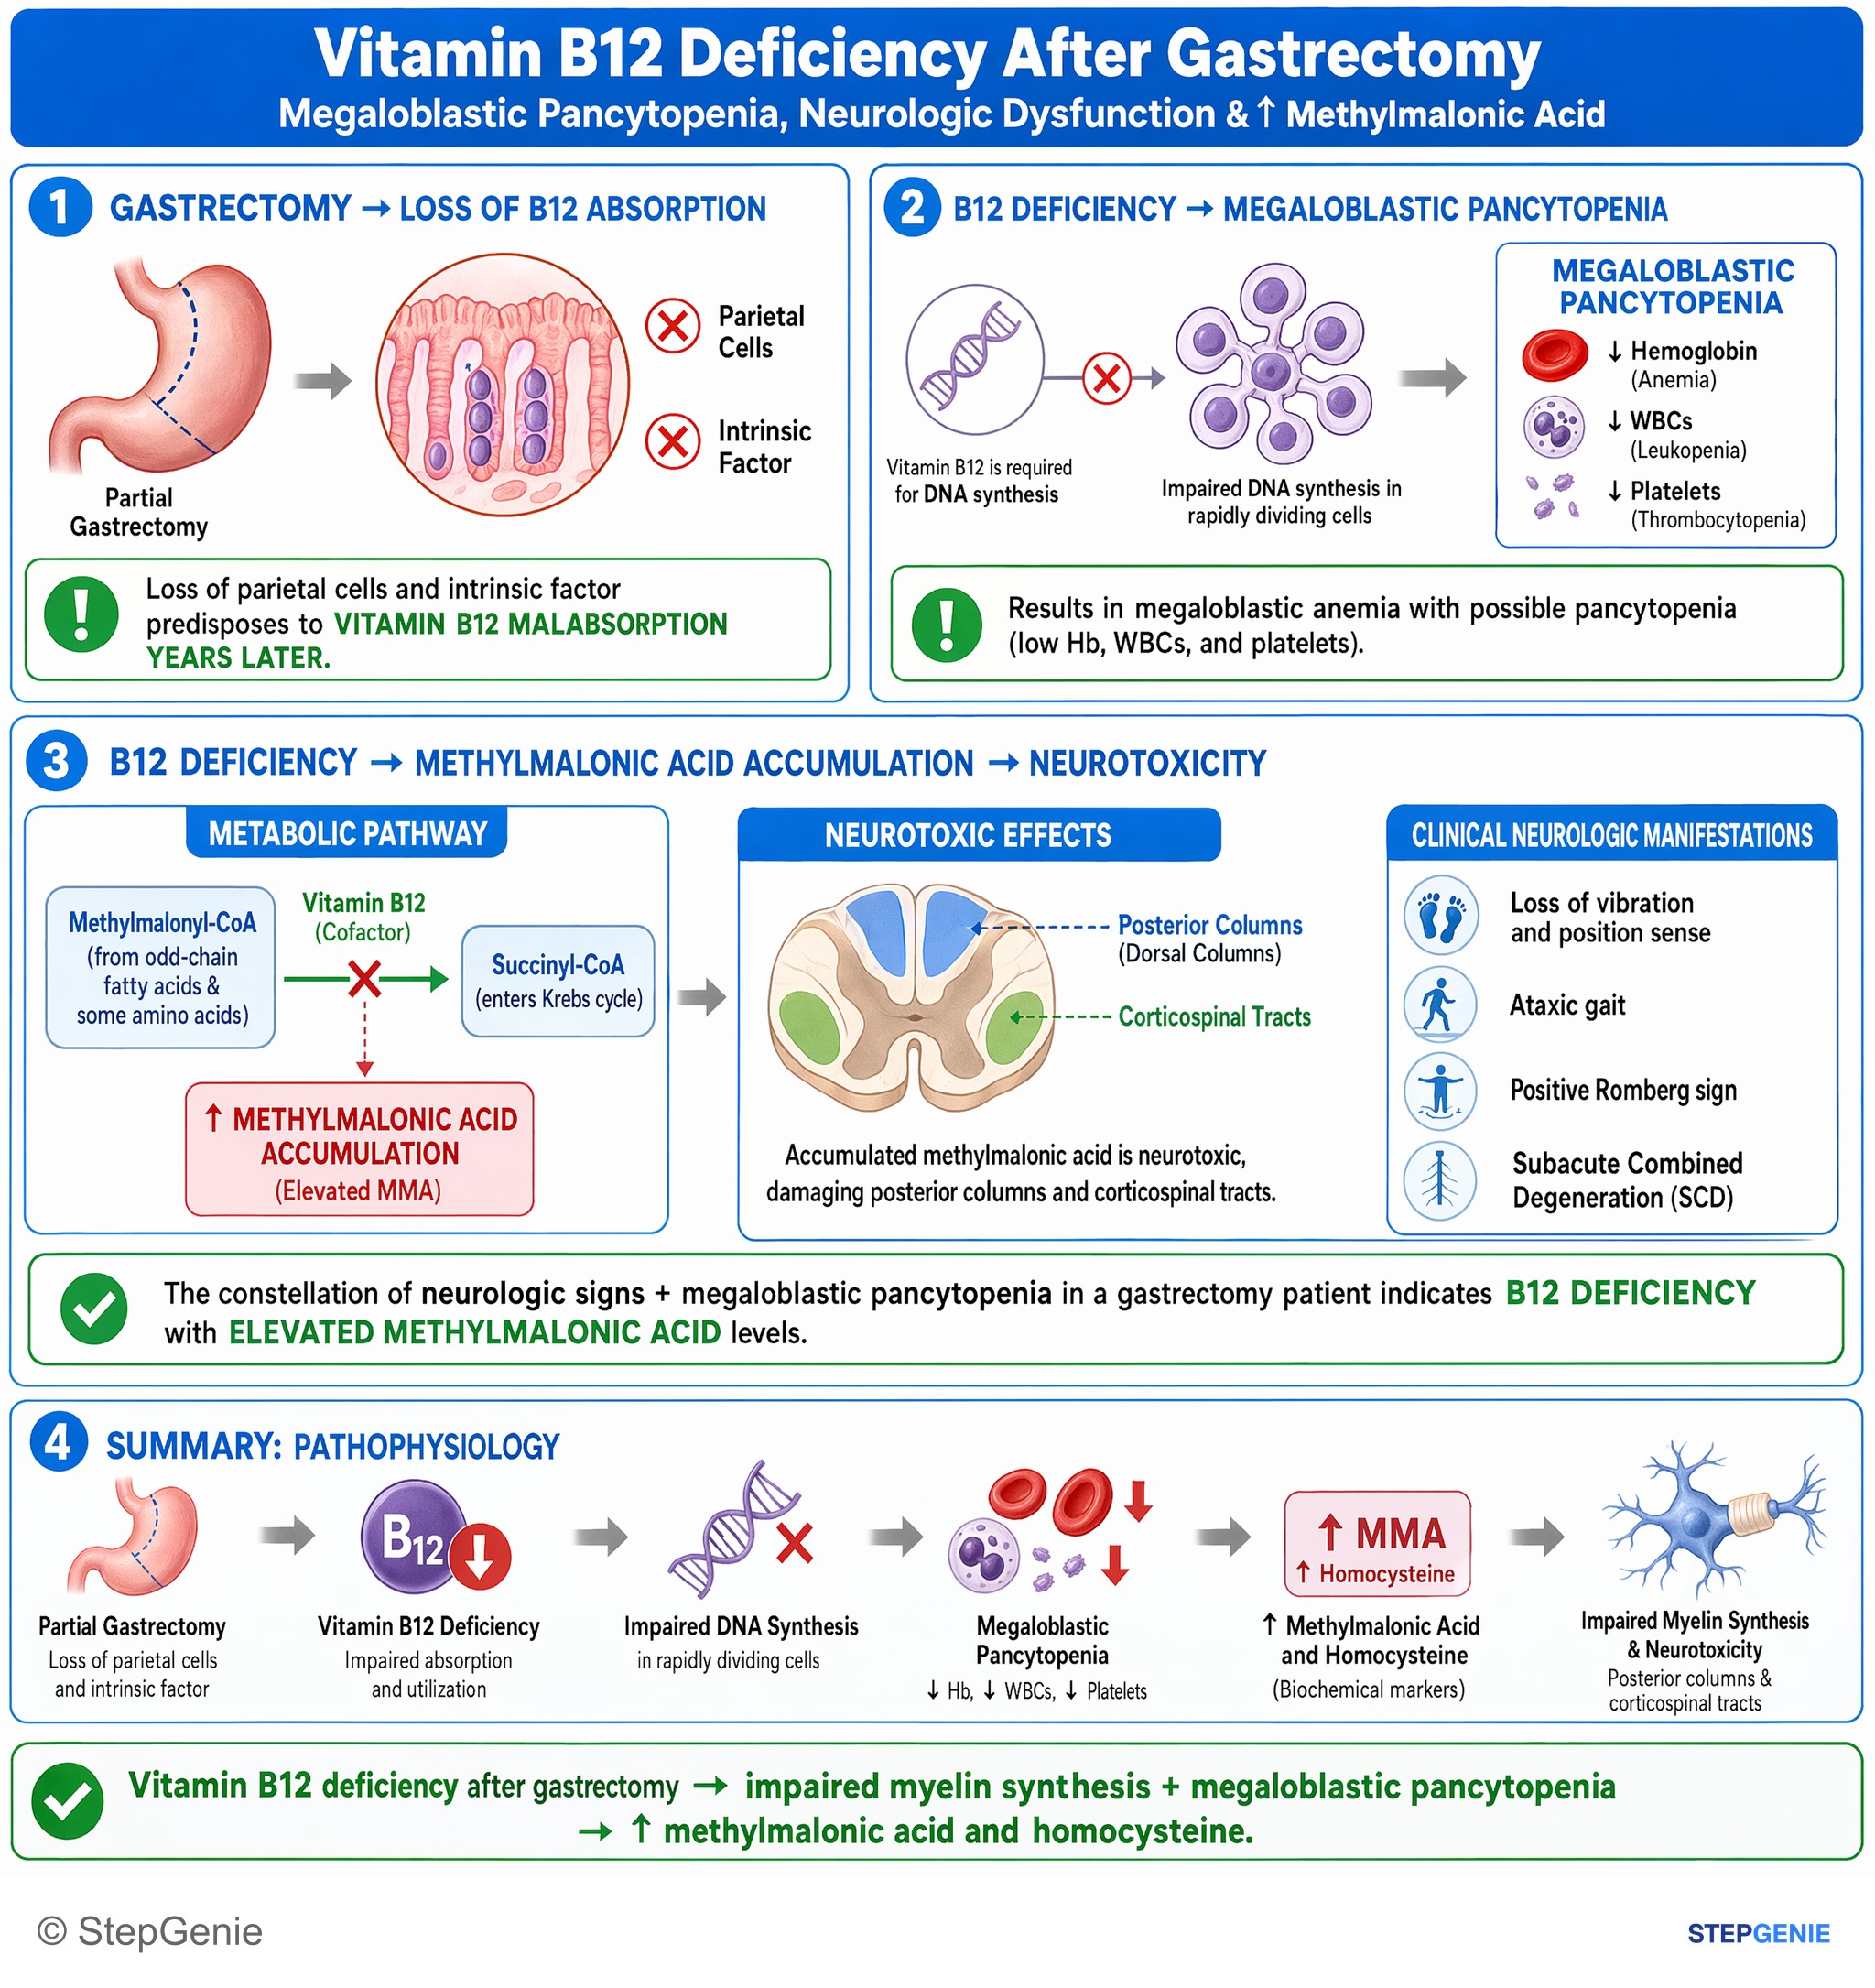
Vitamin B12 deficiency after gastrectomy → impaired myelin synthesis + megaloblastic pancytopenia → ↑ methylmalonic acid and homocysteine.
USMLE Step 1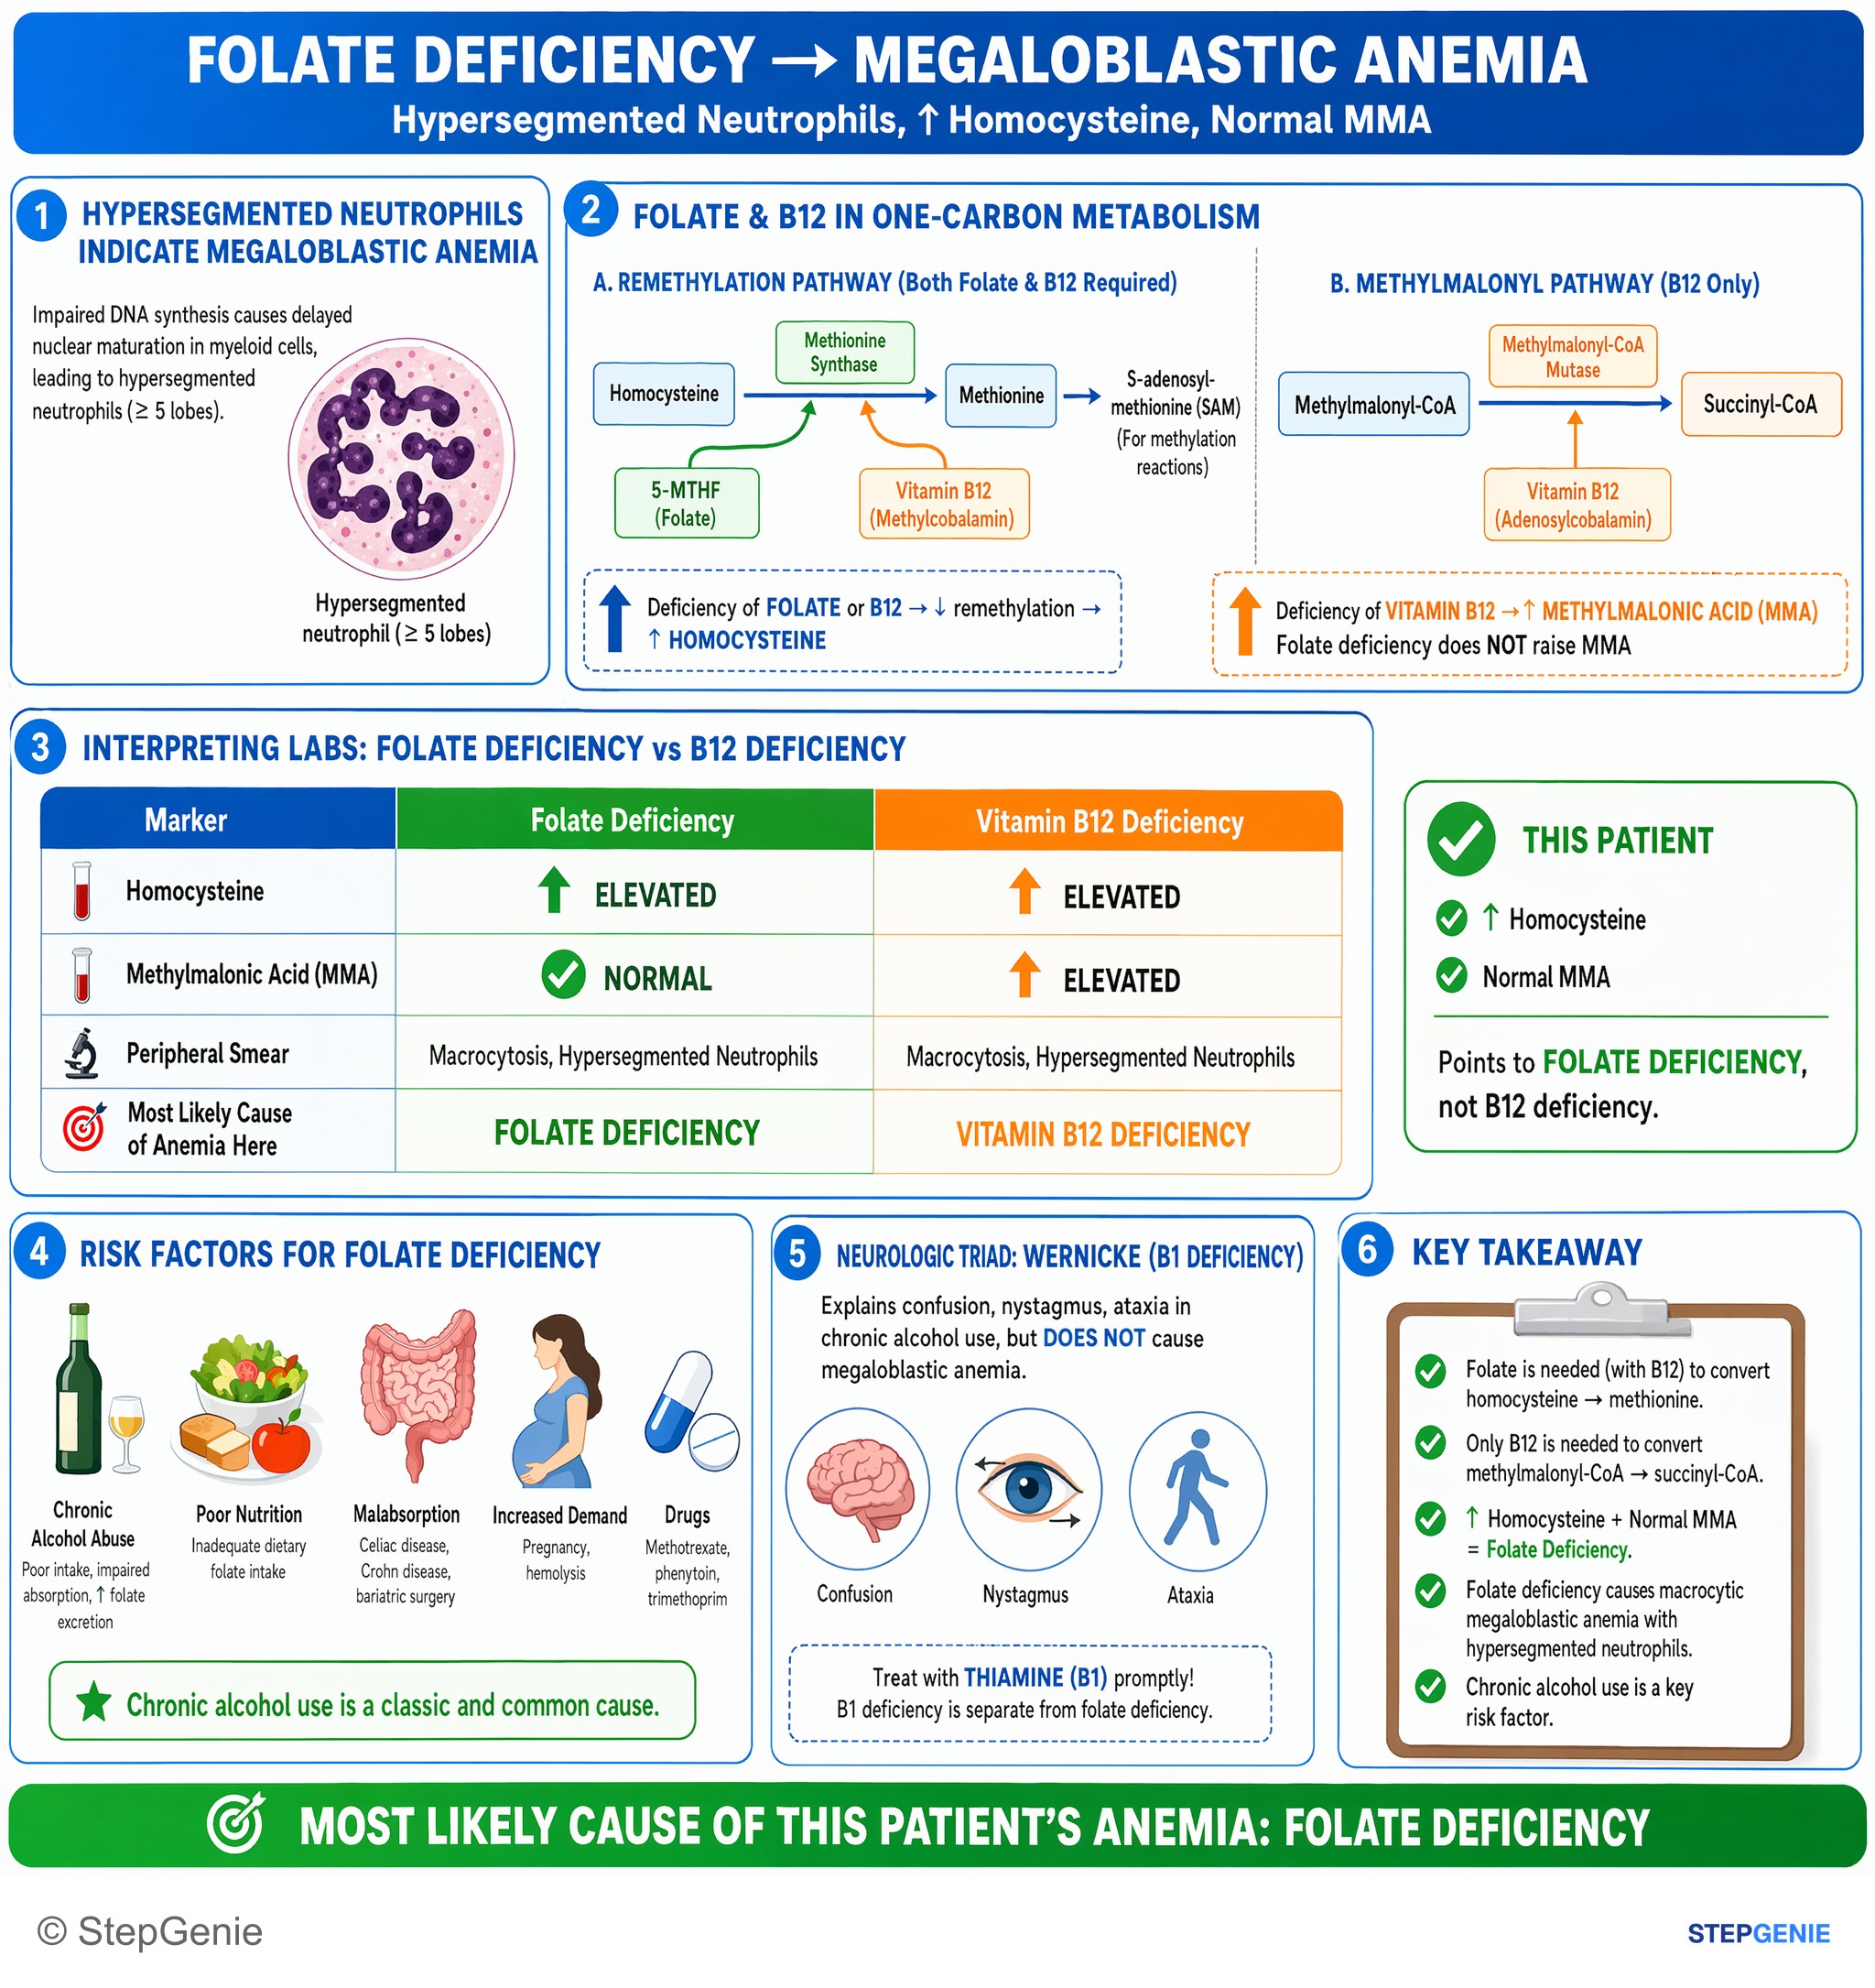
Folate deficiency causes macrocytic megaloblastic anemia with hypersegmented neutrophils, ↑homocysteine, normal methylmalonic acid…
USMLE Step 1Frequently Asked Questions
How do you tell vitamin B12 deficiency from folate deficiency?
Both cause the same megaloblastic blood picture: macrocytic anemia, macro-ovalocytes and hypersegmented neutrophils, with raised homocysteine. The separators are methylmalonic acid and the nervous system. Methylmalonic acid rises only in B12 deficiency, because B12 is the cofactor for methylmalonyl-CoA mutase. Only B12 deficiency causes subacute combined degeneration and peripheral neuropathy, which can appear before the anemia. Exposure clues help too: malabsorption or veganism for B12; alcohol, poor diet or pregnancy for folate.
Why does megaloblastic anemia cause macrocytes and hypersegmented neutrophils?
B12 and folate are both needed to make DNA. When either is lacking, DNA synthesis slows while RNA synthesis and cell growth continue, so blood cell precursors become large and their nuclei look immature compared with the cytoplasm. Many of these megaloblasts die in the bone marrow, so the reticulocyte count is low and white cells and platelets can fall as well. The peripheral smear shows macro-ovalocytes, hypersegmented neutrophils and a high red cell distribution width.
Why shouldn't you give folic acid alone for megaloblastic anemia?
If the real problem is B12 deficiency, folic acid can correct the anemia while the neurologic damage keeps progressing and may become permanent. That is why B12 deficiency must be excluded first, by measuring serum B12 and, when the level is borderline, methylmalonic acid. The leucovorin label carries the same warning for pernicious anemia. In the other direction, B12 doses above 10 mcg daily can produce a hematologic response in folate-deficient anemia and hide it.
What is subacute combined degeneration?
It is the spinal cord damage of vitamin B12 deficiency, affecting the dorsal columns and the lateral corticospinal tracts together. Patients lose vibration and position sense, become ataxic with a positive Romberg sign, and develop spasticity and extensor plantar responses, often with a peripheral neuropathy and sometimes confusion or depression. It can occur before anemia appears, and deficits that persist for months or years may not recover, so treatment with IM vitamin B12 should start promptly.
Can oral vitamin B12 treat pernicious anemia?
Yes, in many patients. High oral doses of 1,000 to 2,000 mcg daily are absorbed by mass action, about 1 to 2 percent by passive diffusion, even without intrinsic factor. Merck reserves oral treatment for patients without severe deficiency or neurologic signs. Those with severe deficiency or neurologic involvement get 1 mg intramuscularly one to four times a week until the blood count corrects, then monthly, and pernicious anemia needs treatment for life.
Why does folate deficiency develop faster than B12 deficiency?
The liver stores only a few months' supply of folate but enough vitamin B12 for about 3 to 5 years. Folate deficiency therefore appears within months of poor intake, alcohol use disorder, pregnancy or drugs such as methotrexate, trimethoprim and phenytoin. B12 deficiency typically appears years after its cause begins, for example years after gastric bypass or ileal resection, unless enterohepatic reabsorption is also lost, which shortens the timeline to months.