Iron deficiency anemia (IDA) is the classic “most common anemia” you’ll see in Step-style questions—and it’s also one of the most testable because the pathophysiology maps cleanly onto labs, smear findings, and clinical clues (diet, pregnancy, GI bleed). If you can connect low iron → low heme → impaired Hb synthesis → microcytosis + hypochromia, you’ll crush the diagnosis and the tricky differentials.
Where Iron Deficiency Anemia Fits (Big Picture)
Iron deficiency anemia = microcytic, hypochromic anemia due to decreased iron availability for hemoglobin synthesis.
Quick classification (Step 1 anchor)
Microcytic anemias are classically:
- Iron deficiency anemia
- Anemia of chronic disease (can be microcytic or normocytic)
- Thalassemias
- Sideroblastic anemia
- Lead poisoning
First Aid cross-reference: Anemias (microcytic), iron studies patterns, and RBC morphology (Heme/Onc section—varies by edition).
Definition (What “Iron Deficiency” Actually Means)
Iron deficiency = depleted total body iron stores leading to:
- Low serum iron
- Low ferritin (reflects low iron stores; most specific)
- Reduced heme production
- Reduced hemoglobin synthesis
- Smaller RBCs (microcytosis) and paler RBCs (hypochromia)
Pathophysiology (Why the Labs Look the Way They Do)
Stepwise physiology logic
- Iron is required for heme synthesis (protoporphyrin + Fe → heme via ferrochelatase).
- With insufficient iron, developing erythrocytes can’t load hemoglobin properly.
- Cells undergo extra divisions to try to reach target intracellular Hb concentration → smaller RBCs.
- The marrow response is limited by substrate deficiency → low reticulocyte response unless treated.
Core causes (think: “Not enough in / too much out”)
Most common etiologies to memorize:
- Chronic blood loss (especially GI in adults, menstrual in reproductive-age patients)
- Colon cancer is a board-favorite culprit in older adults.
- Increased requirement
- Pregnancy, infancy/childhood, adolescence
- Decreased absorption
- Celiac disease
- Gastrectomy/bariatric surgery
- Achlorhydria/PPI use (less common as a sole cause, but can contribute)
High-yield rule: Adult male or postmenopausal female with IDA = GI blood loss until proven otherwise.
Clinical Presentation (Clues You’re Supposed to Notice)
General anemia symptoms (shared across etiologies)
- Fatigue, weakness
- Dyspnea on exertion
- Pallor
- Tachycardia, palpitations
High-yield IDA-specific findings
- Pica (craving ice = pagophagia is classic)
- Koilonychia (spoon nails)
- Angular cheilitis
- Glossitis (smooth, sore tongue)
- Restless legs (commonly associated clinically)
The Step 1 “association” you must know
- Plummer-Vinson syndrome: IDA + esophageal webs + dysphagia
- Increased risk of squamous cell carcinoma of the esophagus
First Aid cross-reference: Koilonychia, pica, Plummer-Vinson are classic HY bullets in many editions.
Diagnosis (How to Nail It on a Vignette)
CBC and indices
- Low hemoglobin/hematocrit
- Low MCV (microcytosis) — often later; early IDA can be normocytic
- High RDW (anisocytosis) — very common in IDA
- Helps distinguish from thalassemia trait (often normal RDW)
Peripheral smear (visual testable clues)
- Microcytic, hypochromic RBCs
- Anisocytosis (variable sizes)
- Poikilocytosis (variable shapes)
- Pencil cells / elliptocytes (classically associated)
Iron studies (this is the exam table)
| Test | Iron deficiency anemia | Why |
|---|---|---|
| Serum iron | ↓ | Less circulating iron |
| Ferritin | ↓ | Depleted stores (most specific) |
| TIBC (transferrin) | ↑ | Liver makes more transferrin to scavenge iron |
| Transferrin saturation | ↓ | Less iron bound to more transferrin |
Helpful memory: IDA = low iron, low ferritin, high TIBC.
Bone marrow (rarely needed, but Step loves the concept)
- Absent iron stores on Prussian blue stain (gold standard historically)
Differentiation: IDA vs Anemia of Chronic Disease vs Thalassemia (Common Trap)
Pattern recognition table
| Feature | IDA | Anemia of chronic disease | Thalassemia trait |
|---|---|---|---|
| Ferritin | ↓ | ↑ (acute phase reactant) | Normal/↑ |
| TIBC | ↑ | ↓ | Normal |
| RDW | ↑ | Normal/↑ | Often normal |
| Smear | Pencil cells | Often nonspecific | Target cells (common) |
| MCV | ↓ | Normal or ↓ | ↓↓ (can be very low) |
| RBC count | Often low/normal | Low/normal | Often normal/high |
High-yield move: If the vignette says “microcytosis with normal RDW and normal/high RBC count,” think thalassemia trait, not IDA.
Workup Strategy (What the Question Writer Wants Next)
Adults (especially men and postmenopausal women)
- Confirm IDA on iron studies → search for bleeding source
- FOBT, colonoscopy ± EGD depending on scenario
Premenopausal women
- Consider menstrual loss, pregnancy, diet
- Still evaluate for GI loss if red flags (weight loss, abdominal pain, family history, refractory anemia)
Children
- Diet history (excess cow’s milk is a common real-world and board scenario)
- Consider lead exposure if indicated (can coexist and both are microcytic)
Treatment (Mechanism + Practical Points)
1) Treat the cause
- Stop/repair the bleed (e.g., peptic ulcer, colon cancer)
- Manage malabsorption (e.g., celiac)
- Address dietary deficiency
2) Replace iron
Oral iron (first-line if tolerated)
- Ferrous sulfate / gluconate / fumarate
- Best absorbed in acidic environment
- Vitamin C can enhance absorption
- PPIs, achlorhydria, and certain foods can reduce absorption
Side effects (common test + real life)
- GI upset, constipation, nausea
- Dark stools
Expected response (very Step-relevant)
- Reticulocytosis in ~7–10 days
- Hemoglobin rises over weeks; continue therapy for months to replete stores (ferritin)
IV iron
- For malabsorption, severe intolerance, ongoing blood loss, CKD with EPO therapy, etc.
3) Transfusion?
- Reserved for severe symptomatic anemia or hemodynamic instability
- Not the routine fix for uncomplicated IDA
First Aid cross-reference: Treatment pearls and iron studies patterns are frequently summarized in FA tables.
High-Yield Associations & Classic Vignette Patterns
“Classic” vignettes
- Older adult with fatigue + microcytosis + low ferritin → think colon cancer until proven otherwise
- Young woman with heavy menses + pica + koilonychia → IDA
- Pregnant patient with microcytosis → increased iron requirements
- Dysphagia + IDA → Plummer-Vinson (esophageal webs)
Common pitfalls
- Ferritin is an acute phase reactant: inflammation can raise ferritin and partially mask IDA.
- Early IDA may be normocytic—don’t overcommit to “MCV must be low.”
- Thalassemia trait can look “more microcytic” than IDA but with relatively preserved Hb and normal RDW.
Rapid-Fire Step 1 Checklist
- Most common anemia worldwide and common on USMLE.
- Microcytic, hypochromic; RDW often increased.
- Ferritin decreased (best single clue).
- TIBC increased.
- Smear: pencil cells/elliptocytes, anisopoikilocytosis.
- Symptoms: fatigue + pica, koilonychia, glossitis.
- Must evaluate GI blood loss in adult men/postmenopausal women.
- Treat with oral iron + fix underlying cause; expect reticulocytosis within ~1 week.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
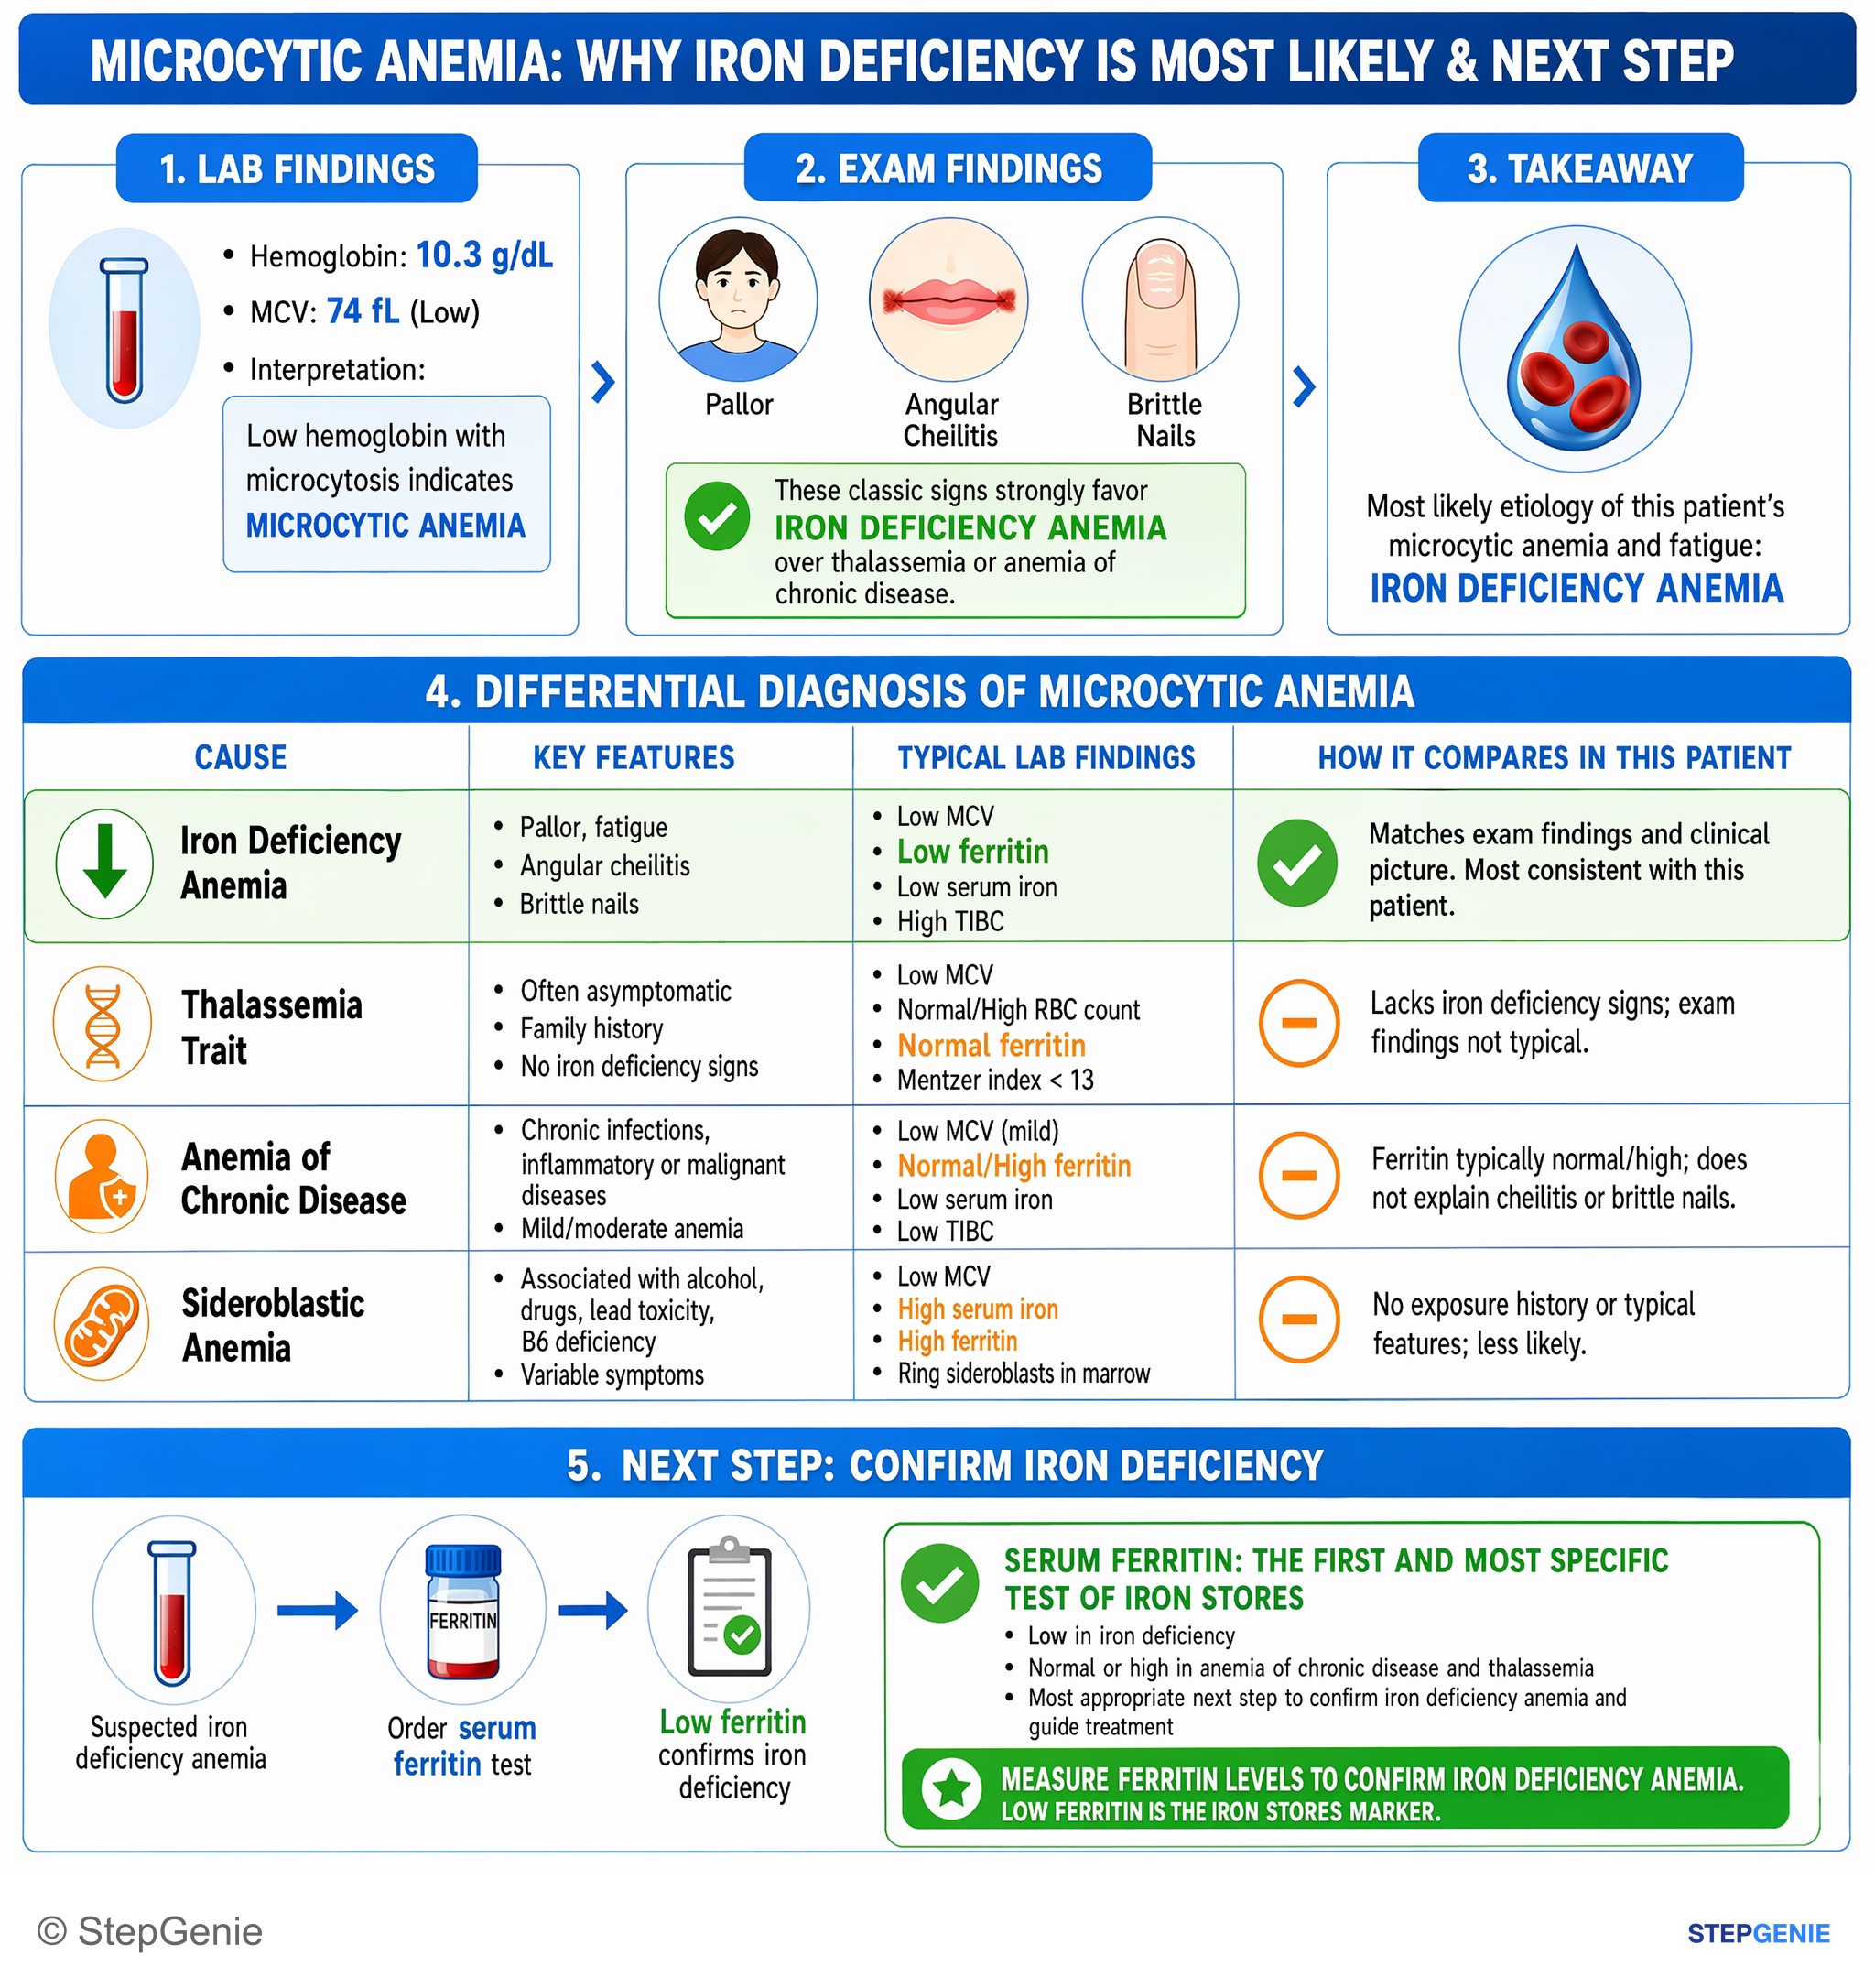
Iron deficiency anemia causing microcytic anemia and fatigue; first confirm with low ferritin as iron stores marker.
USMLE Step 2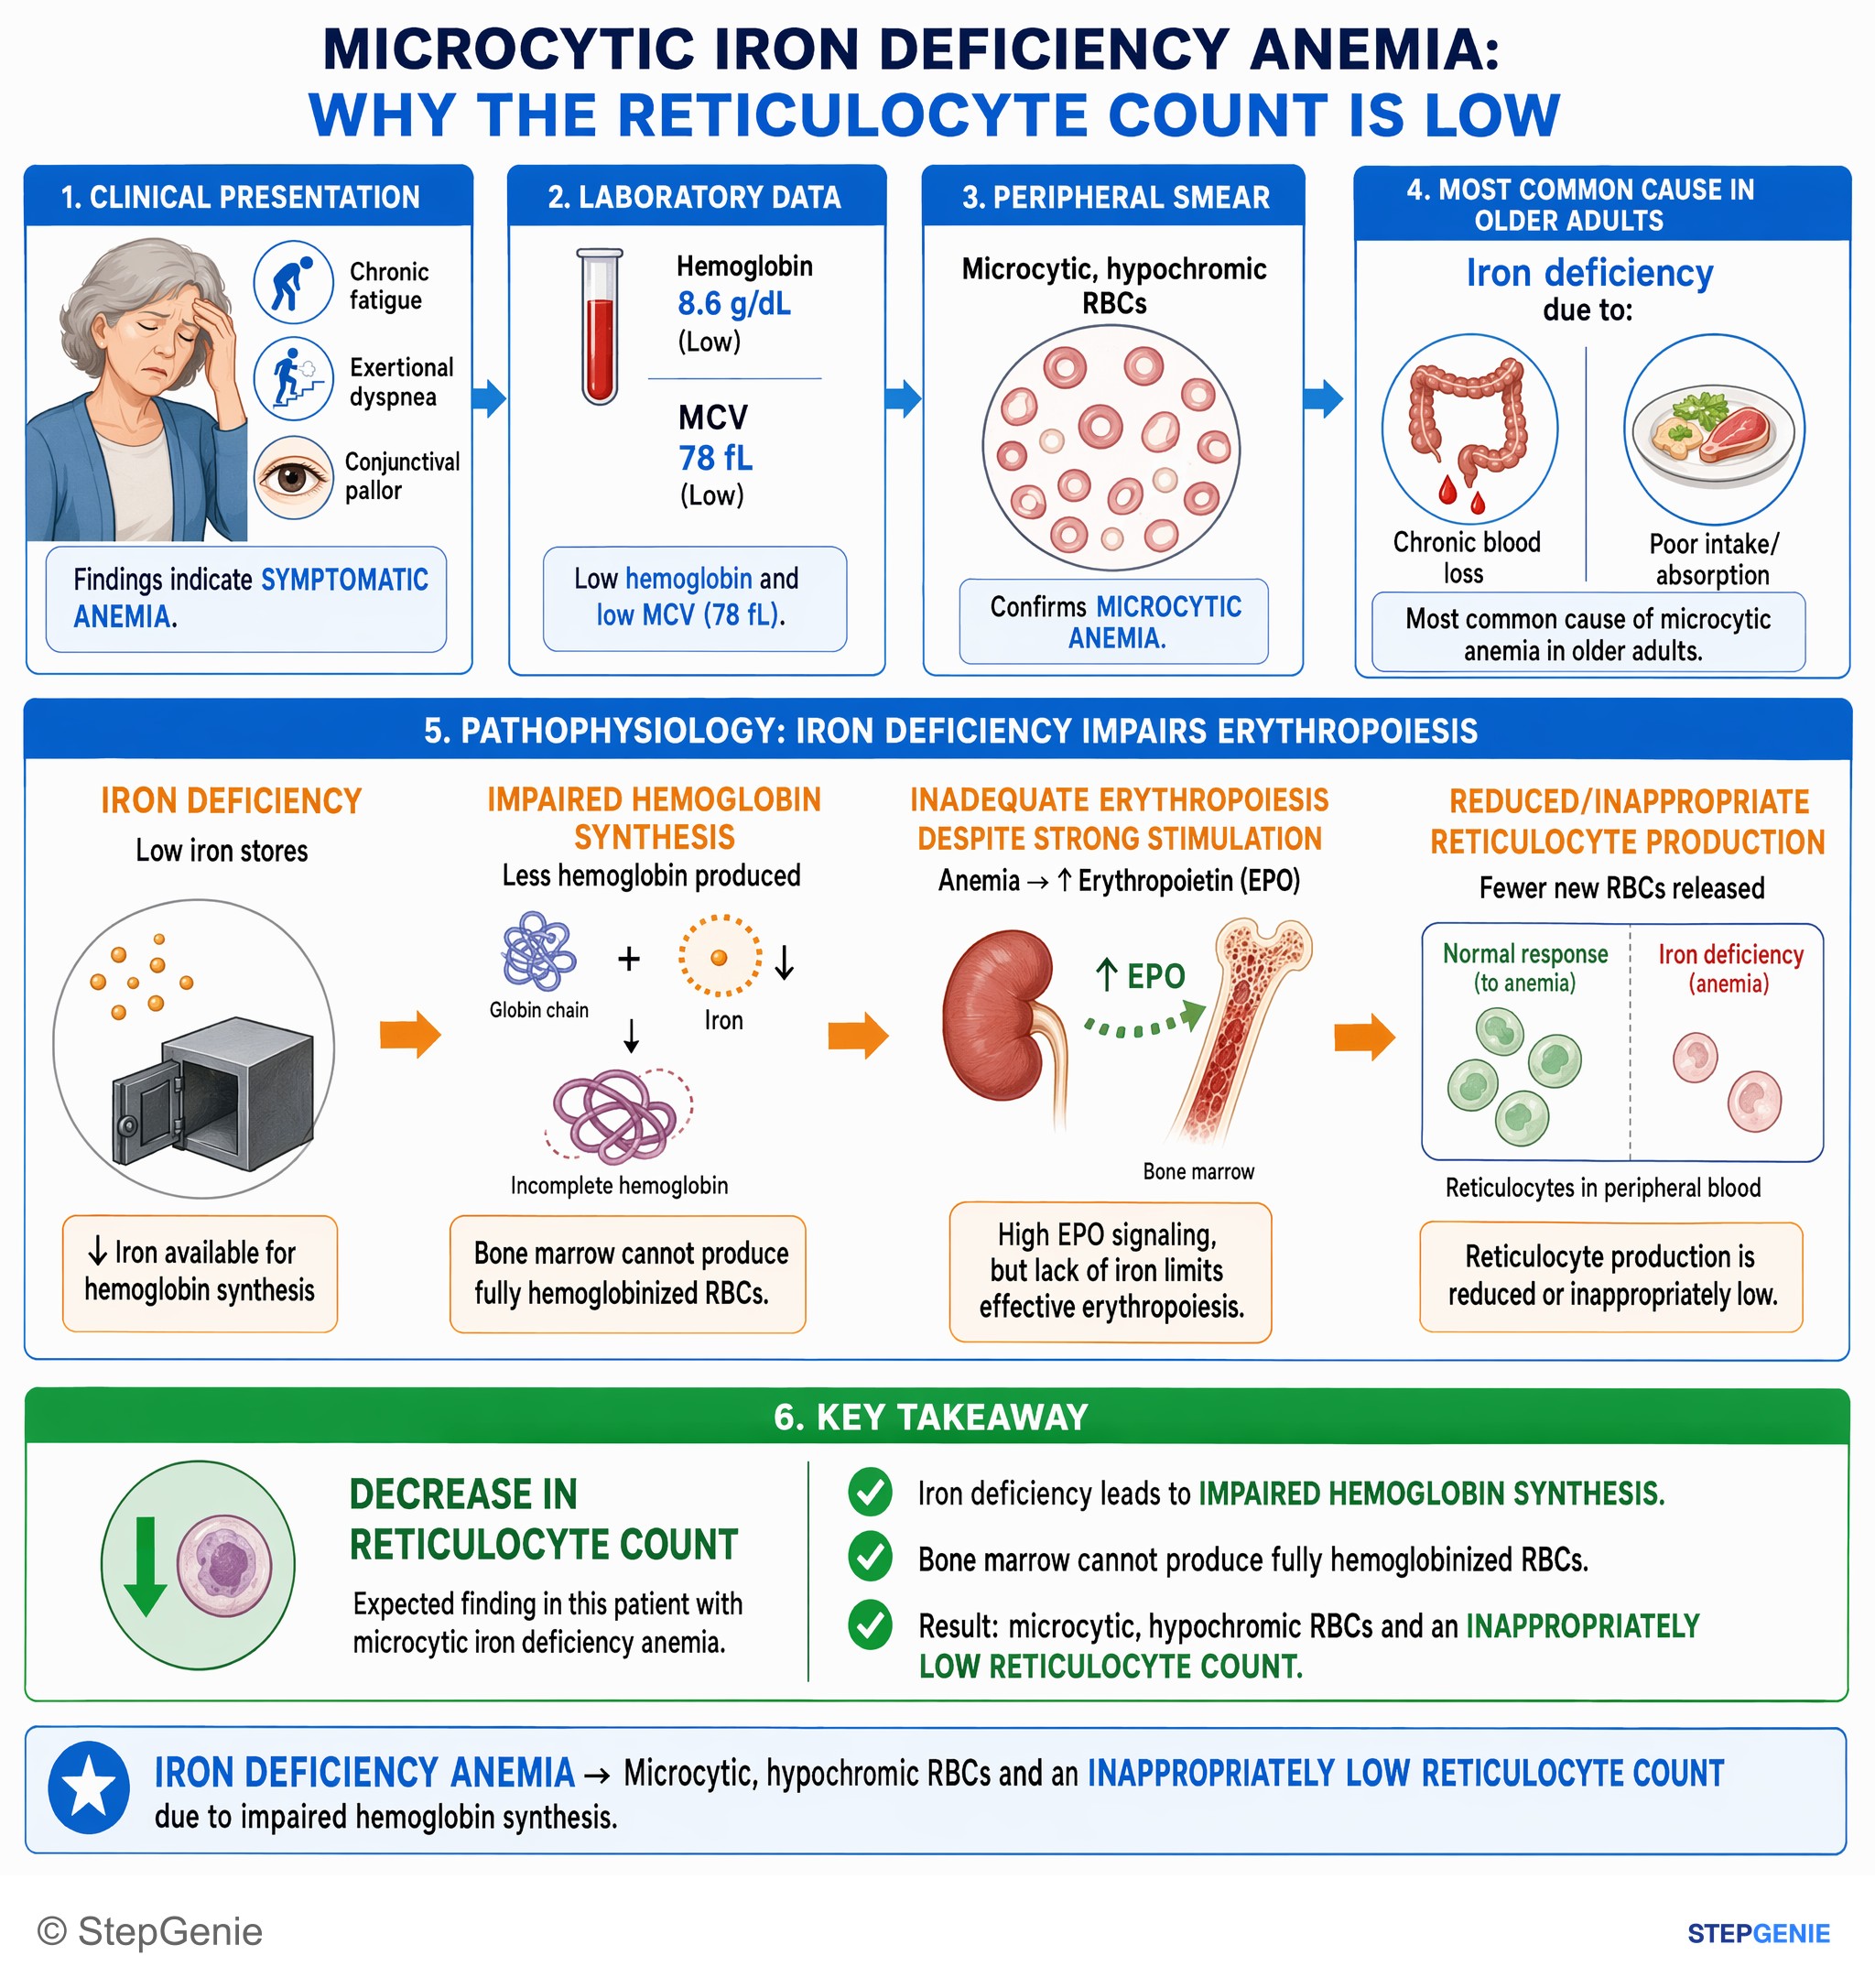
Iron deficiency anemia causes microcytic, hypochromic RBCs and an inappropriately low reticulocyte count due to impaired hemoglobin…
USMLE Step 1Frequently Asked Questions
Why does iron deficiency anemia cause microcytic, hypochromic red blood cells?
Iron deficiency anemia causes microcytic, hypochromic red blood cells because low iron reduces heme production and impairs hemoglobin synthesis. Developing erythrocytes cannot load enough hemoglobin, so they undergo extra divisions while trying to reach a target intracellular hemoglobin concentration. That process produces smaller cells with less hemoglobin, which appear microcytic and paler than normal on peripheral smear.
How do you tell iron deficiency anemia from thalassemia trait on a vignette?
Iron deficiency anemia is suggested by high RDW, low ferritin, high TIBC, and smear findings such as pencil cells, whereas thalassemia trait often has normal RDW, a normal or high RBC count, and target cells. A classic clue favoring thalassemia trait is microcytosis with normal RDW and a normal or elevated RBC count rather than the usual low or normal RBC count seen in iron deficiency anemia.
What are the classic iron study findings in iron deficiency anemia?
The classic iron study pattern in iron deficiency anemia is low serum iron, low ferritin, high TIBC, and low transferrin saturation. This reflects depleted total body iron stores, which lower ferritin, while the liver increases transferrin production to scavenge more iron, raising TIBC. Ferritin is especially useful because it is the most specific marker of low iron stores.
When should iron deficiency anemia make you think about gastrointestinal blood loss?
Iron deficiency anemia should make you think about gastrointestinal blood loss in adults, especially adult men and postmenopausal women. Chronic blood loss is a major cause of iron deficiency, and gastrointestinal bleeding should be assumed until proven otherwise in those groups. In older adults, colon cancer is a particularly high-yield cause to remember in a board-style vignette.
What is the first-line treatment for iron deficiency anemia, and what response should you expect?
First-line treatment for iron deficiency anemia is oral iron if the patient can tolerate it, such as ferrous sulfate, gluconate, or fumarate. Iron is absorbed best in an acidic environment, vitamin C can improve absorption, and PPIs, achlorhydria, and some foods can reduce it. You should also treat the underlying cause, and a classic expected response is reticulocytosis in about 7 to 10 days.