Subacute combined degeneration (SCD) is symmetric demyelination of the dorsal columns and the lateral columns (lateral corticospinal and spinocerebellar tracts) of the spinal cord, mostly the cervical and upper thoracic cord, and its classic cause is vitamin B12 deficiency. Suspect it when tingling, loss of vibration and position sense and a positive Romberg sign come with upper motor neuron signs such as spasticity and Babinski signs. Elevated methylmalonic acid (MMA) plus elevated homocysteine points to B12 deficiency; folate deficiency raises only homocysteine and rarely causes neurologic disease. Anemia can be absent, nitrous oxide can cause SCD with a normal B12 level, and copper deficiency produces a look-alike with normal B12 and MMA.
Subacute combined degeneration mnemonic for USMLE
The disease name is the mnemonic. SCD = Spinocerebellar, Corticospinal, Dorsal columns, the three tracts that degenerate. "Combined" means the sensory (dorsal) and motor (lateral) columns are damaged together.
For the labs, remember "B12 raises Both": B12 deficiency raises both MMA and homocysteine, while folate deficiency raises homocysteine alone. MMA is the more specific marker of B12 deficiency.
| Tract | Deficit | Bedside clue |
|---|---|---|
| Spinocerebellar tracts (lateral column) | Contribute to gait ataxia | Unsteady, clumsy gait |
| Lateral Corticospinal tracts (lateral column) | Spastic weakness | Hyperreflexia, ankle clonus, Babinski sign |
| Dorsal columns | Loss of vibration, joint position sense and fine touch; sensory ataxia | Positive Romberg; worse in the dark or with eyes closed |
| Peripheral nerves (often involved too) | Distal sensory loss | Ankle jerks often absent despite Babinski signs |
Pain and temperature pathways are involved less consistently, so preserved pinprick sensation does not argue against SCD.
Step-by-step flowchart: from symptoms to treatment
- Recognize the pattern. It usually starts with symmetric paresthesias (tingling or numbness) and loss of vibration and position sense in the legs. Then comes unsteadiness that is worse in the dark, a positive Romberg sign and, later, spasticity and extensor plantar responses. A mixed reflex picture (brisk knees, absent ankle jerks) is typical because a neuropathy often coexists. Lhermitte sign and cognitive change can also occur.
- Check the blood. A CBC may show macrocytic anemia (MCV above 100 fL) with hypersegmented neutrophils, but severe neurologic disease can occur without anemia or macrocytosis. A serum B12 below 200 pg/mL (145 pmol/L) indicates deficiency; 200–350 pg/mL is low-normal and needs confirmation.
- Confirm with MMA and homocysteine. Both high means B12 deficiency, absolute or functional. High homocysteine with normal MMA means folate deficiency. Both normal in a patient with an SCD picture sends you to step 6.
- Ask about nitrous oxide. Recreational use ("whippets" or balloons) is an increasingly recognized cause, especially in young patients. Nitrous oxide oxidizes the cobalt in cobalamin from the +1 to the +3 state, which inactivates B12 and blocks methionine synthase. Serum B12 and MCV can be normal, so MMA and homocysteine make the diagnosis. Nitrous oxide given as an anesthetic inactivates B12 too, so StatPearls advises preoperative B12 screening when it will be used.
- Find the cause of B12 deficiency. Pernicious anemia (autoimmune atrophic gastritis with loss of intrinsic factor; anti–intrinsic factor antibodies support it), gastrectomy or bariatric surgery, terminal ileal disease or resection (Crohn disease), long-term metformin or acid suppression, a strict vegan diet, chronic pancreatitis, small intestinal bacterial overgrowth and the fish tapeworm Diphyllobothrium latum.
- B12 and MMA normal? Check copper. Order serum copper, ceruloplasmin and zinc. Copper deficiency myelopathy follows bariatric or other upper GI surgery, excess zinc (supplements or zinc-containing denture cream) or malabsorption. Vitamin E deficiency is another mimic.
- Image the cord. MRI classically shows symmetric T2 hyperintensity in the dorsal columns of the cervical and upper thoracic cord, the "inverted V" (or "inverted rabbit ears") sign on axial images. A normal MRI does not exclude SCD.
- Treat immediately. Give parenteral B12 when there are neurologic signs; StatPearls suggests cyanocobalamin 1,000 mcg IM every other day for 2 weeks, then monthly. High-dose oral B12 (1,000–2,000 mcg daily) is an option once symptoms improve or when the cause is dietary. Continue for life if the cause persists (pernicious anemia), stop nitrous oxide, and never give folic acid alone.
Quick flow: symmetric dorsal column + UMN signs → CBC and B12 → MMA and homocysteine → both high: B12 deficiency (ask about nitrous oxide, then find the cause) → B12 and MMA normal: copper, ceruloplasmin, zinc → MRI for the inverted V → parenteral B12 without delay.
B12 vs folate vs copper deficiency vs nitrous oxide
| B12 deficiency | Folate deficiency | Copper deficiency | Nitrous oxide | |
|---|---|---|---|---|
| Neurologic picture | SCD, neuropathy, cognitive change | Neurologic findings rare | SCD-like myelopathy (sensory ataxia, spastic legs) plus polyneuropathy | SCD, often with neuropathy |
| Blood picture | Macrocytic anemia, may be absent | Macrocytic anemia | Anemia and/or neutropenia; can be mistaken for myelodysplasia | MCV may be normal |
| Key labs | Low or low-normal B12; high MMA and high homocysteine | Low folate; high homocysteine, normal MMA | Low copper and ceruloplasmin; normal B12 and MMA; zinc may be high | B12 may be normal; high MMA and homocysteine |
| Classic setting | Pernicious anemia, gastric or bariatric surgery, ileal disease, metformin, vegan diet | Chronic alcohol use, restrictive diet, anorexia, malabsorption | Bariatric or upper GI surgery, zinc excess, malabsorption | Recreational use; also anesthetic exposure in a patient with low B12 stores |
| Treatment | Parenteral B12, lifelong if the cause persists | Folic acid once B12 deficiency is excluded | Copper replacement; remove the zinc source | Stop nitrous oxide; parenteral B12 |
For more practice separating the two vitamins, see this folate vs B12 deficiency question breakdown.
Prognosis: why speed matters
Blood counts usually correct within about 6 weeks of B12 replacement, but nerve and cord recovery is slower, taking months, and deficits present for months to years can become permanent. StatPearls reports that 86% of patients show some clinical resolution with treatment, but only 14% recover completely. Younger age, shorter symptom duration, absent Romberg and Babinski signs and less extensive MRI involvement predict a better outcome. In copper deficiency, replacement normalizes the blood counts, but neurologic recovery is usually partial.
Exam traps
- Normal hemoglobin or MCV: does not rule out B12 deficiency; the neurologic and hematologic findings can dissociate.
- Folate alone: can correct the megaloblastic anemia while the neurologic deficits keep progressing.
- Borderline B12 (200–350 pg/mL): order MMA and homocysteine rather than stopping the workup.
- New sensory ataxia after surgery: consider nitrous oxide anesthesia inactivating B12 in a patient with low B12 stores.
- Tabes dorsalis also causes dorsal column loss and a positive Romberg sign, but it damages the dorsal roots, causes lancinating pains, reduced reflexes, Argyll Robertson pupils and Charcot joints, and spares motor function. UMN signs point to SCD instead; compare it in this tabes dorsalis question breakdown.
- Multiple sclerosis: asymmetric lesions separated in time; SCD is symmetric.
- Normal B12 and MMA with a classic SCD picture: check copper, ceruloplasmin and zinc.
Worked example
Vignette. A 22-year-old man has 4 weeks of numbness in both feet and hands and an unsteady gait that is worse at night. Vibration and position sense are reduced in the legs, the Romberg sign is positive, knee reflexes are brisk, ankle jerks are absent, and both plantar responses are extensor. Hemoglobin and MCV are normal. Serum B12 is 280 pg/mL; homocysteine and MMA are both elevated. MRI shows symmetric T2 hyperintensity in the cervical dorsal columns. He uses nitrous oxide canisters at parties most weekends. What is the mechanism, and what is the treatment?
Answer: Nitrous oxide–induced functional B12 deficiency causing subacute combined degeneration. Stop nitrous oxide and start parenteral B12.
Reasoning: Nitrous oxide oxidizes the cobalt in cobalamin and inactivates it, so the B12-dependent enzymes (methionine synthase and methylmalonyl-CoA mutase) stop working even though the serum B12 is only low-normal and there is no anemia. Raised MMA and homocysteine reveal the functional deficiency. Folate deficiency is excluded by the high MMA, and tabes dorsalis would not cause extensor plantar responses.
Key takeaways
- SCD = Spinocerebellar, Corticospinal, Dorsal columns, from B12 deficiency.
- Dorsal column loss plus UMN signs, often with absent ankle jerks, is the pattern.
- B12 raises Both MMA and homocysteine; folate raises homocysteine only.
- Anemia and macrocytosis can be absent; a low-normal B12 needs MMA.
- Nitrous oxide inactivates B12 and can cause SCD with a normal serum level.
- Normal B12 and MMA in an SCD picture: check copper, ceruloplasmin and zinc.
- Treat fast with parenteral B12; never give folate alone.
Sources
- Spinal Cord Subacute Combined Degeneration — StatPearls, NCBI Bookshelf
- Vitamin B12 Deficiency — StatPearls, NCBI Bookshelf
- Vitamin B12 Deficiency — Merck Manual Professional Edition
- McCormick JP, et al. Nitrous oxide-induced myeloneuropathy: an emerging public health issue — Irish Journal of Medical Science
- Jaiser SR, Winston GP. Copper deficiency myelopathy — Journal of Neurology, 2010
- Tabes Dorsalis — StatPearls, NCBI Bookshelf
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
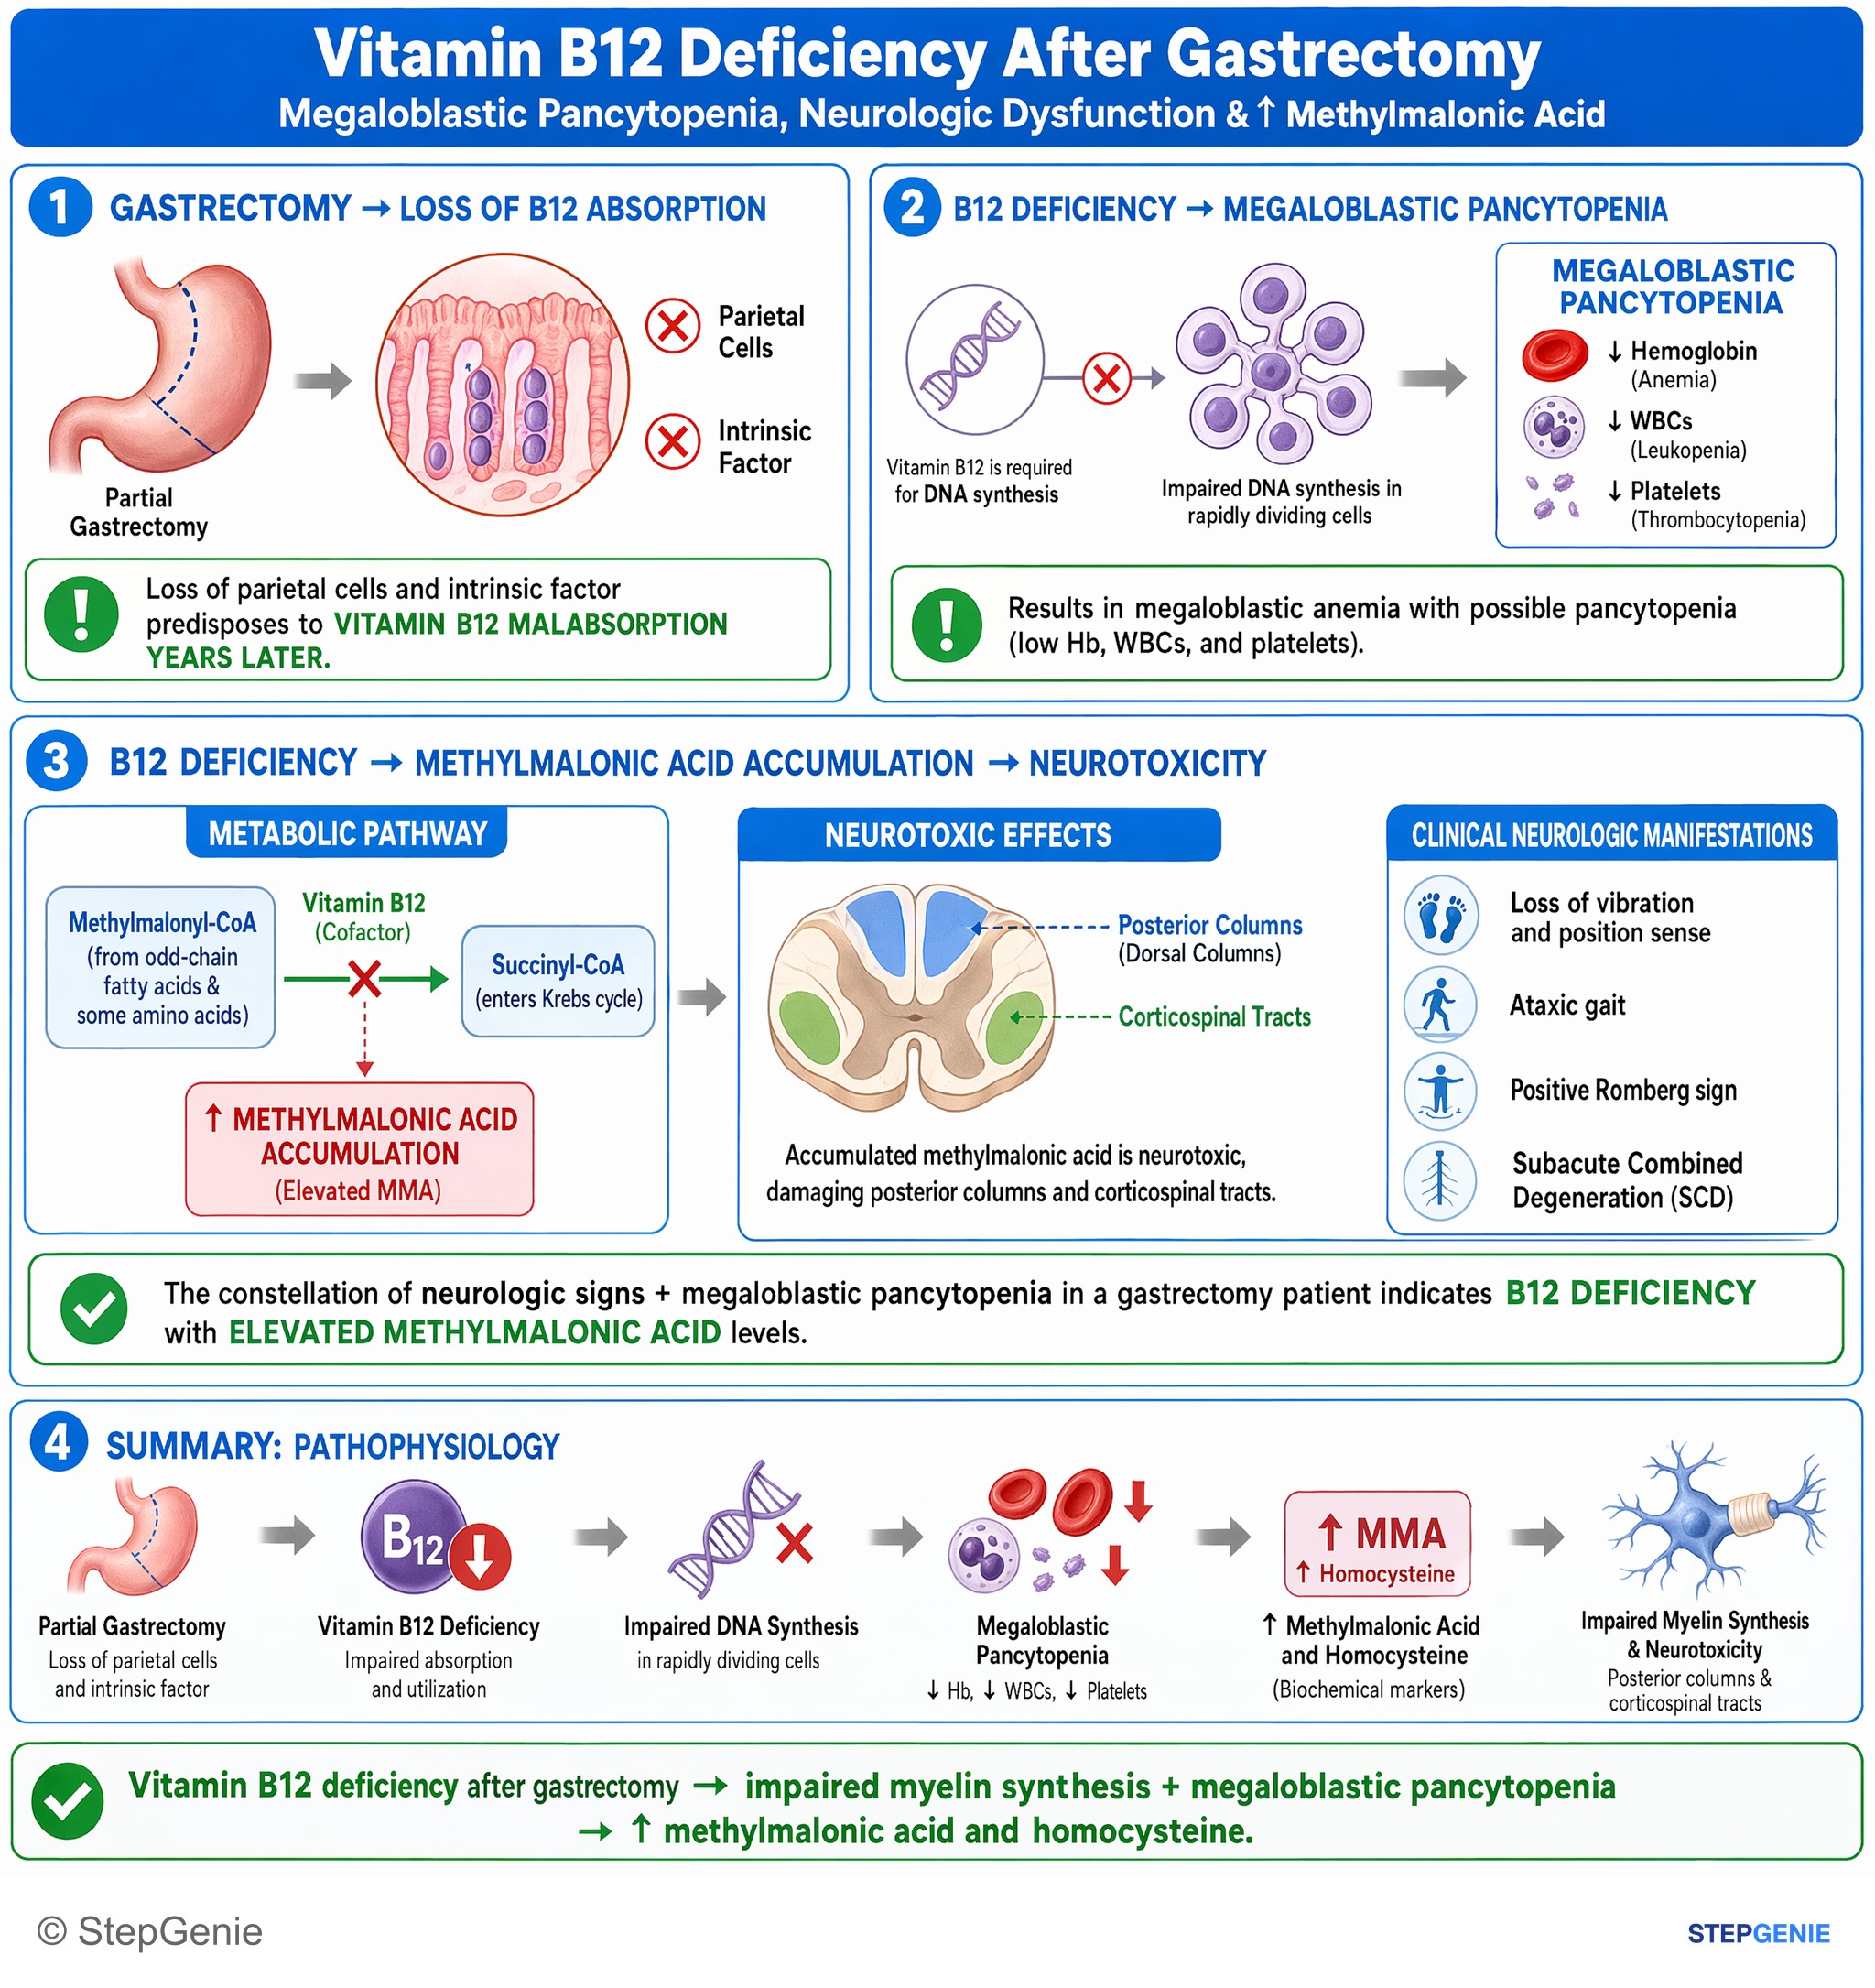
Vitamin B12 deficiency after gastrectomy → impaired myelin synthesis + megaloblastic pancytopenia → ↑ methylmalonic acid and homocysteine.
USMLE Step 1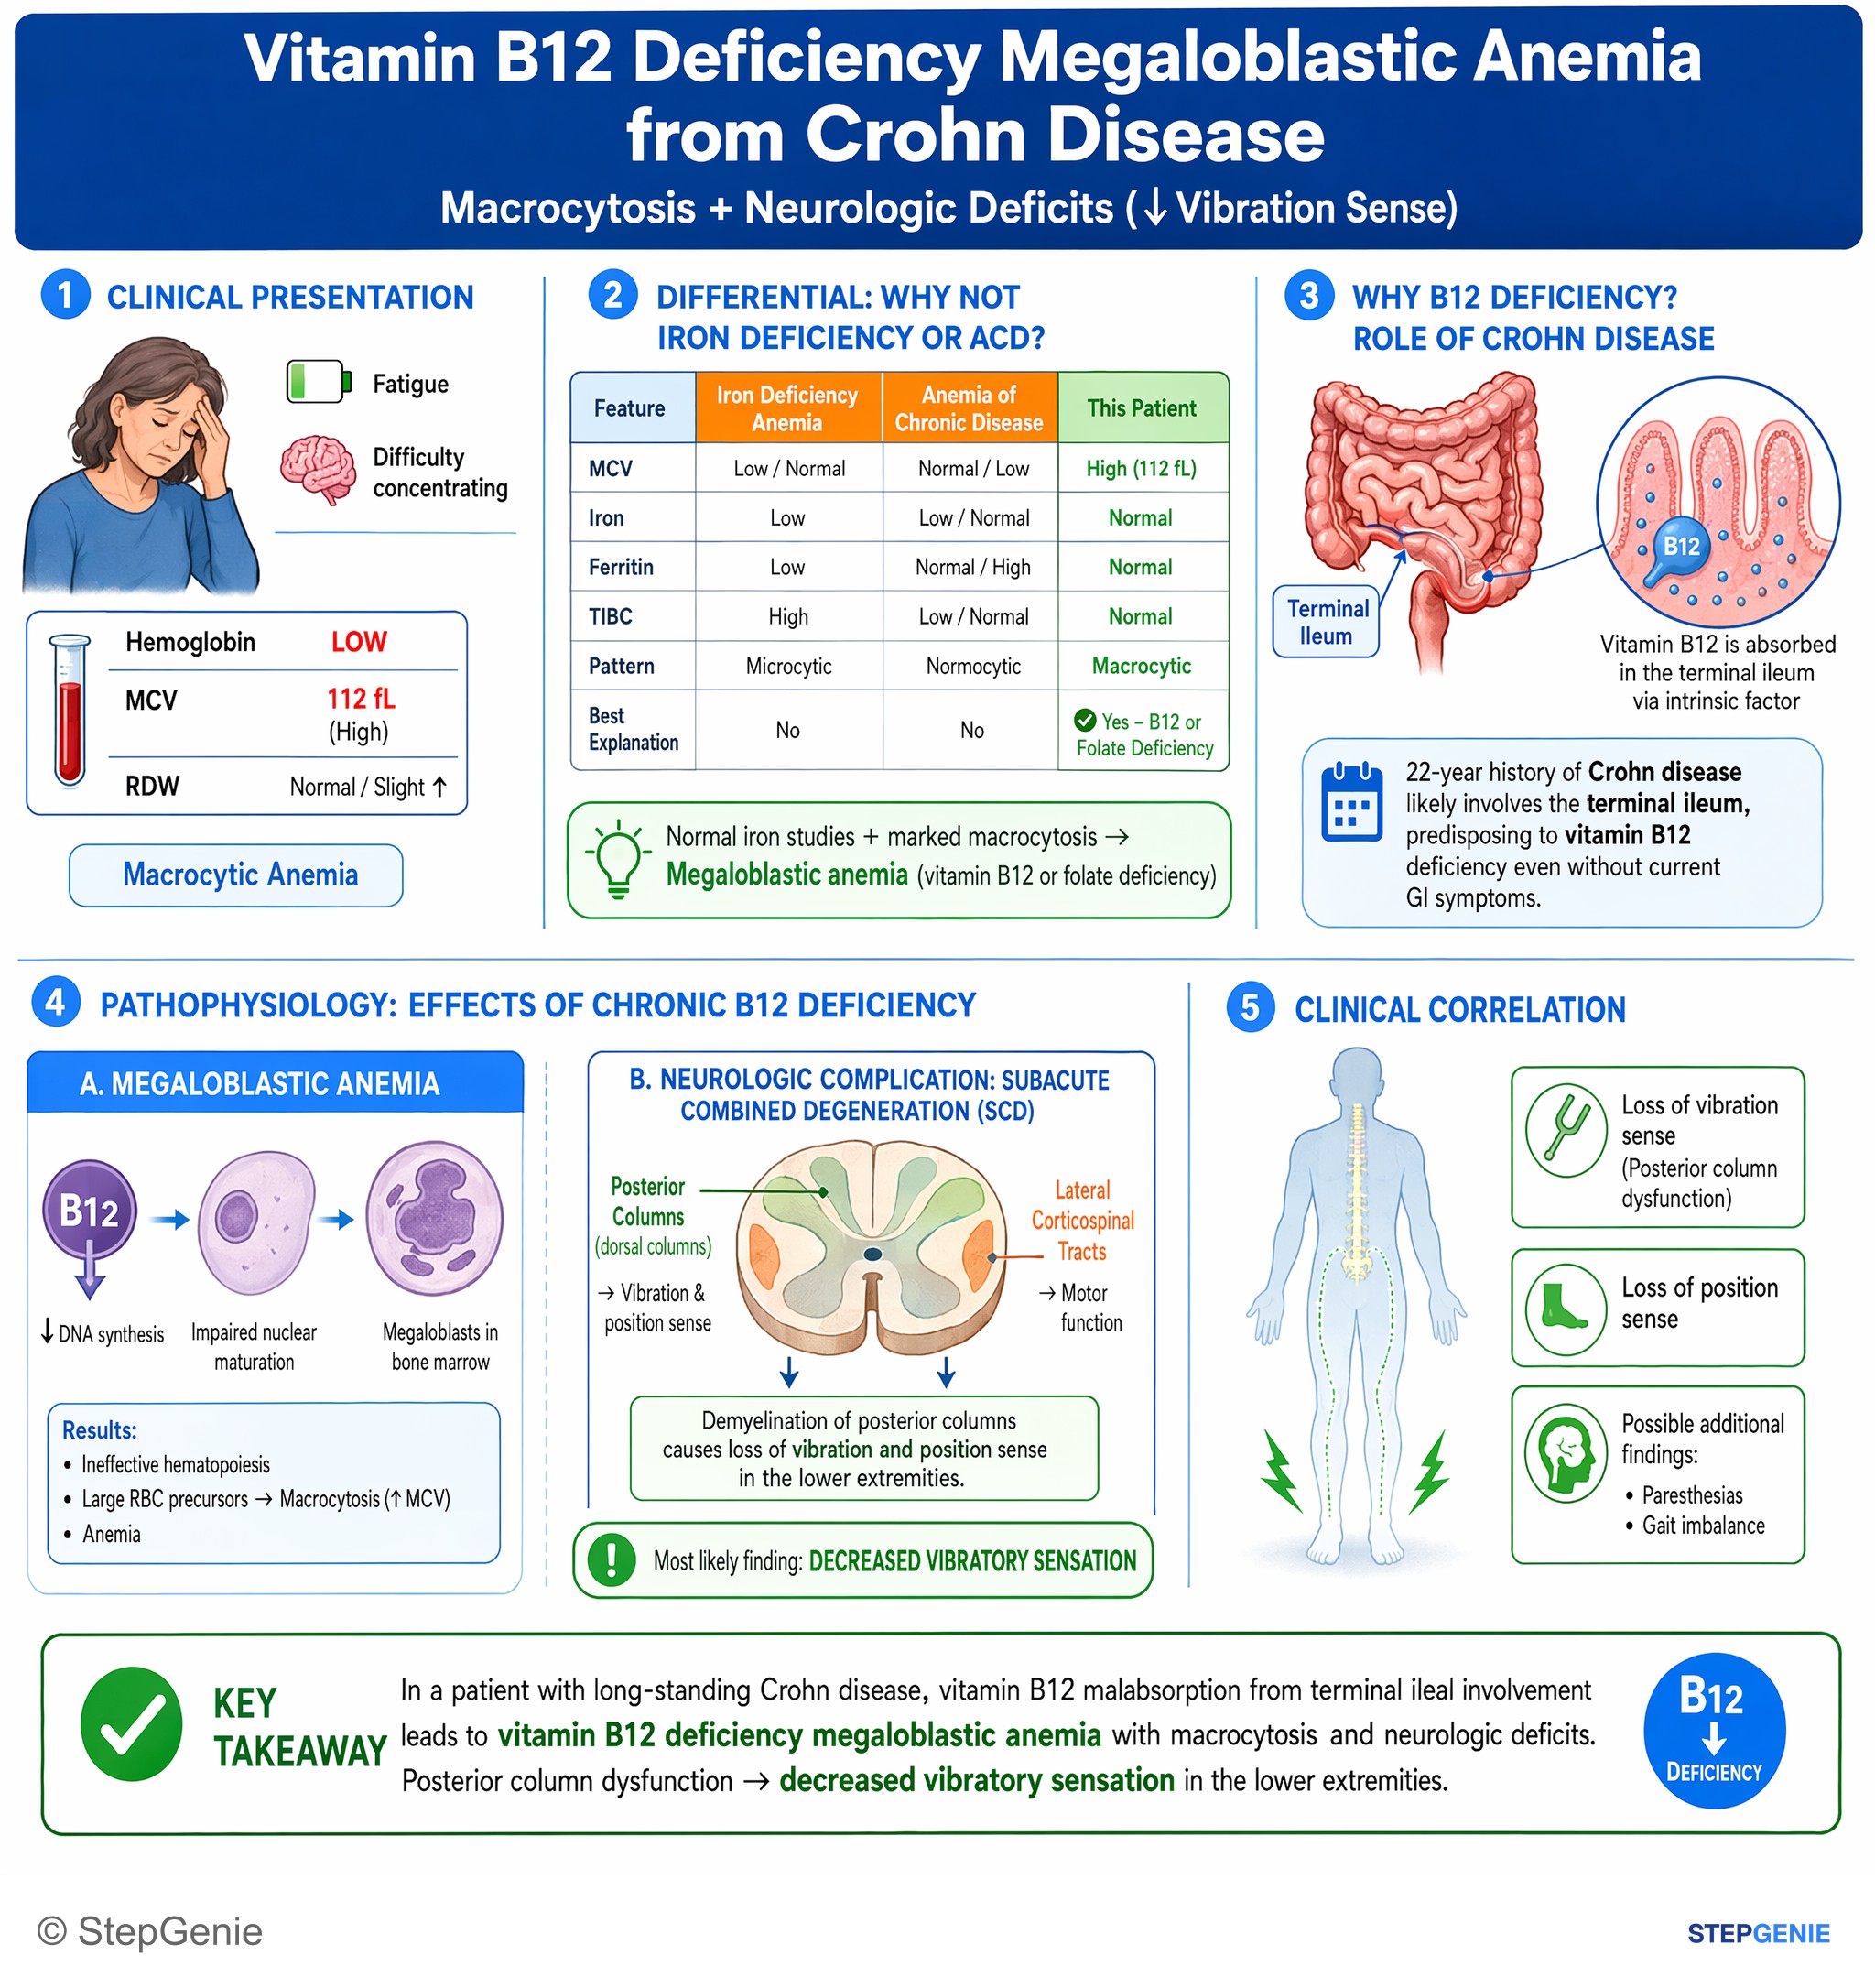
Vitamin B12 deficiency megaloblastic anemia from long-standing Crohn disease causes macrocytosis and neurologic deficits such as decreased…
USMLE Step 1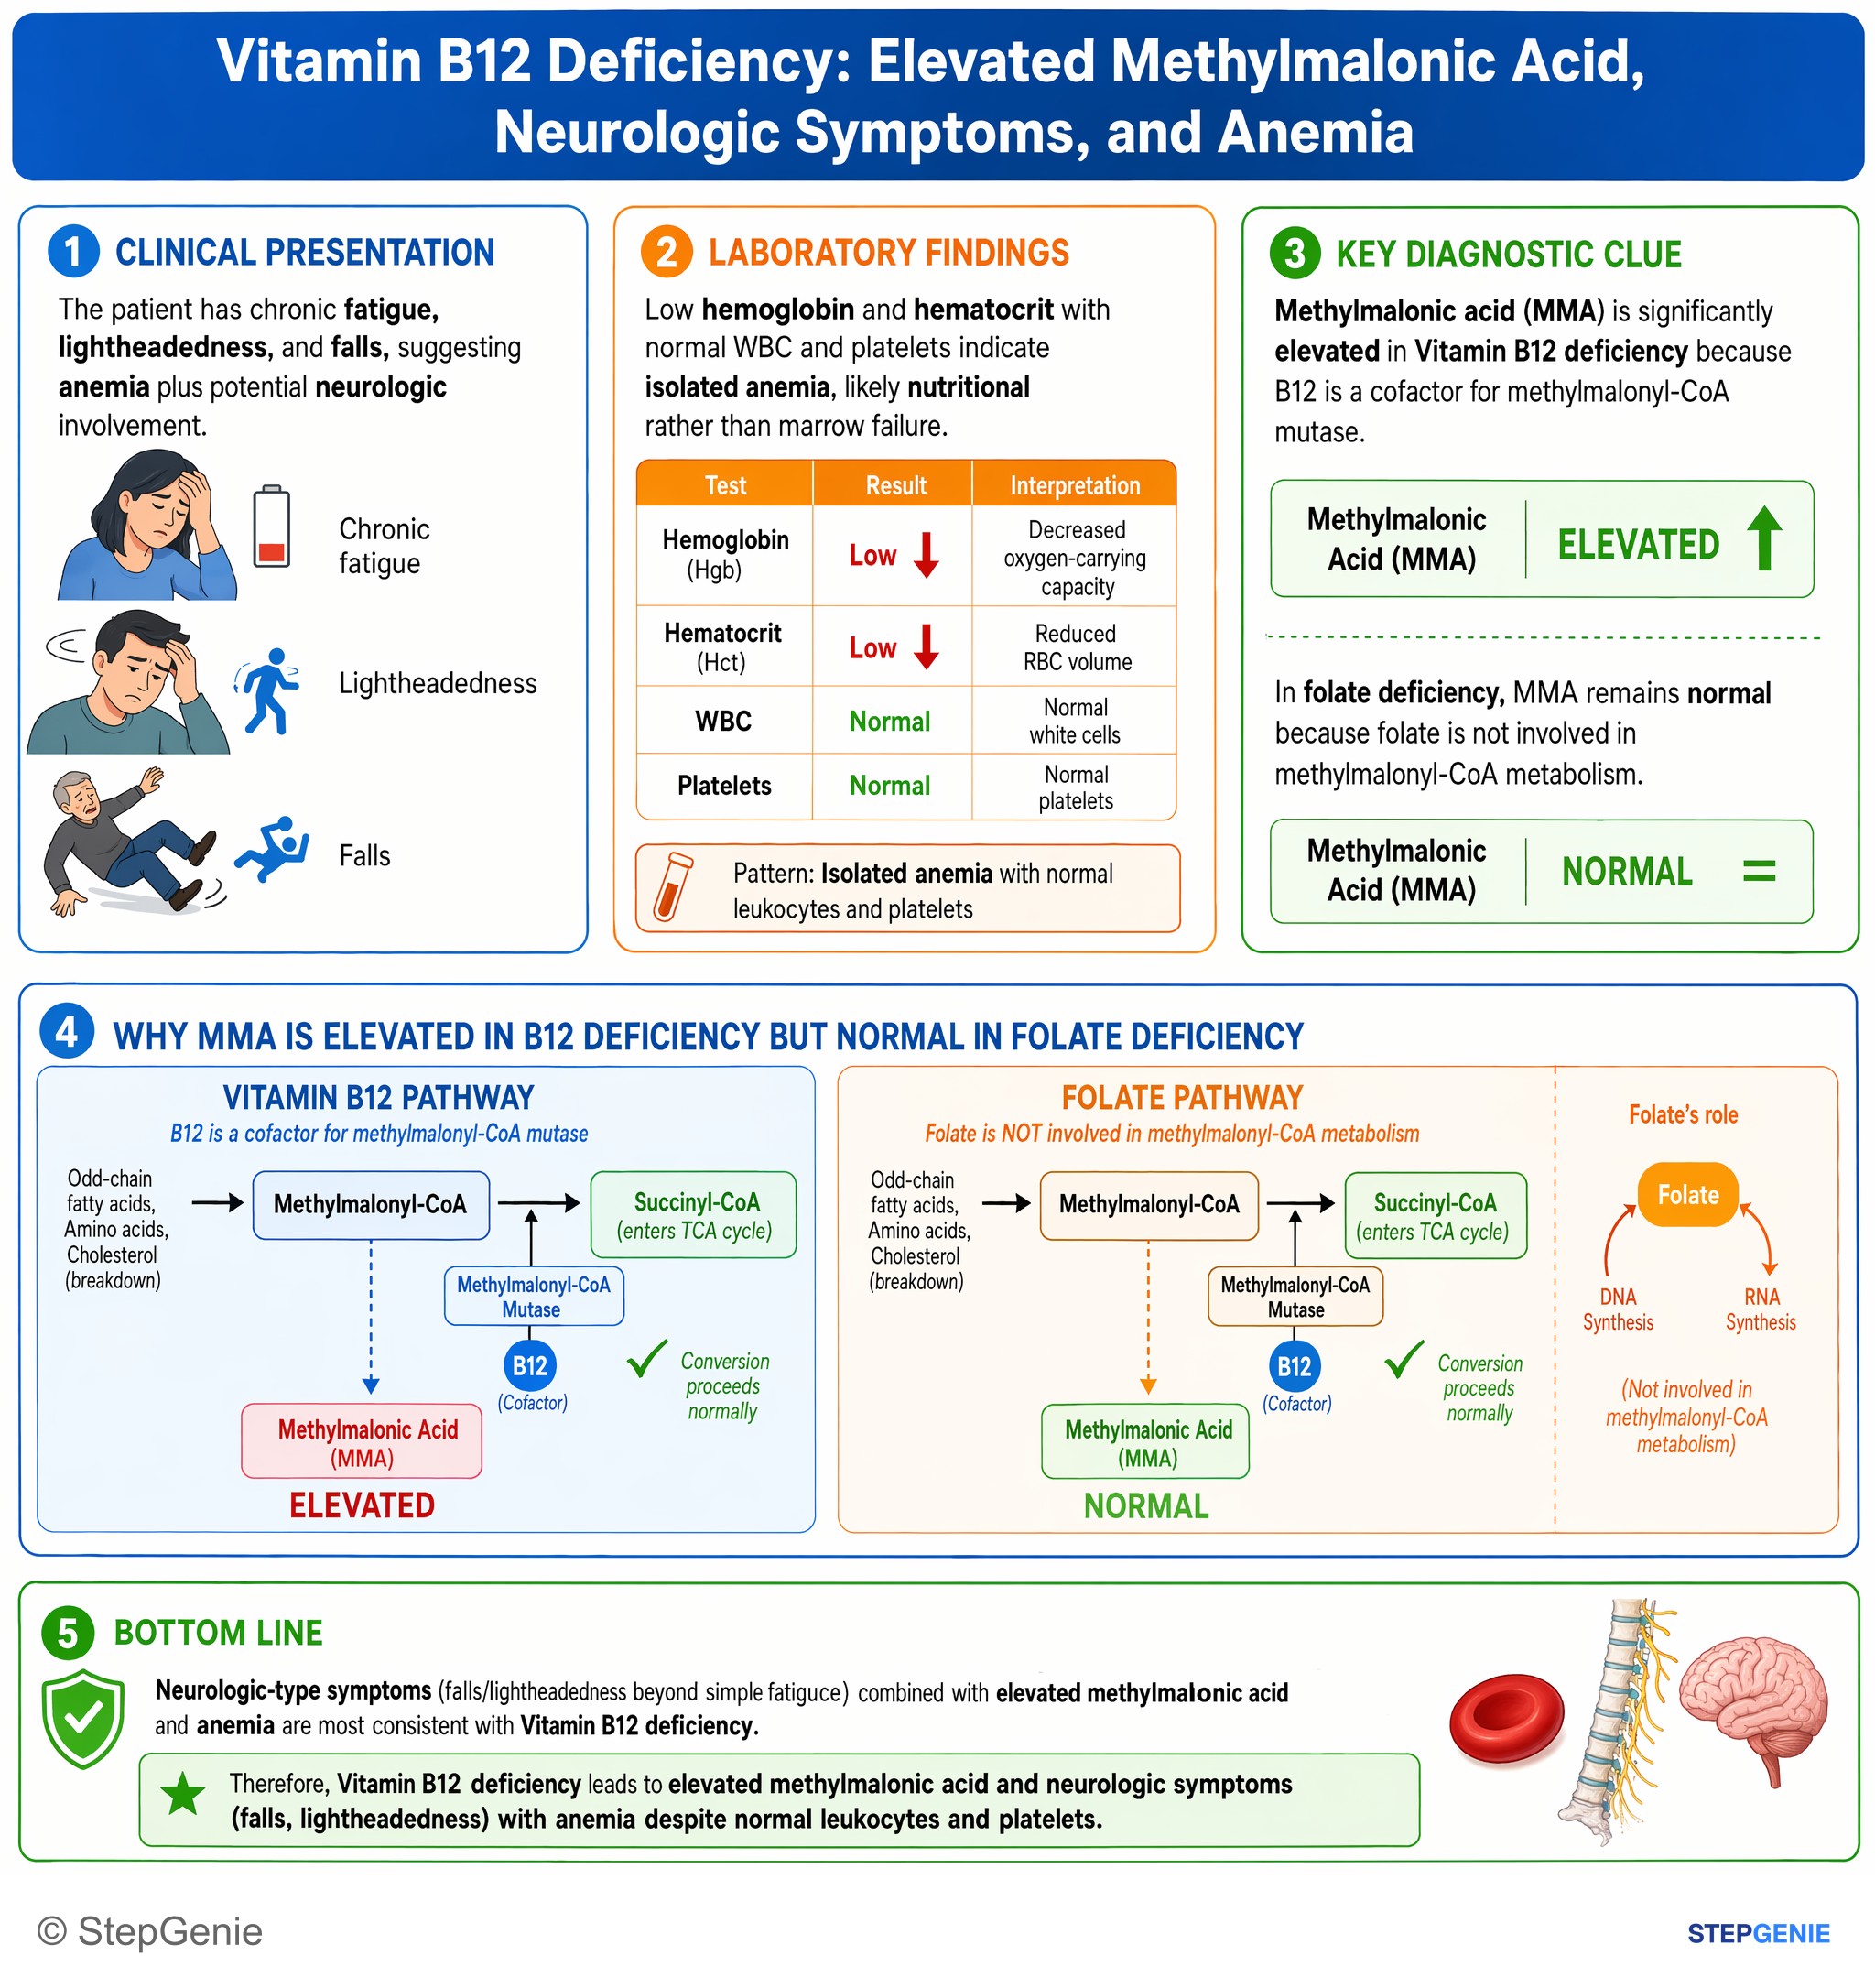
Vitamin B12 deficiency → elevated methylmalonic acid → neurologic symptoms (falls, lightheadedness) with anemia despite normal leukocytes…
USMLE Step 1Frequently Asked Questions
What is the mnemonic for subacute combined degeneration?
Use the letters of the name: SCD stands for the Spinocerebellar tracts, the lateral Corticospinal tracts and the Dorsal columns, the tracts damaged by vitamin B12 deficiency. Dorsal column damage causes loss of vibration and position sense with a positive Romberg sign, and corticospinal damage causes spasticity, hyperreflexia and Babinski signs. For the labs, B12 deficiency raises both methylmalonic acid and homocysteine, while folate deficiency raises only homocysteine.
Which spinal cord tracts are affected in subacute combined degeneration?
Subacute combined degeneration damages the dorsal (posterior) columns and the lateral columns, which contain the lateral corticospinal and spinocerebellar tracts. The changes are symmetric and are most prominent in the cervical and upper thoracic cord. On MRI they appear as T2 hyperintensity in the dorsal columns, called the inverted V sign.
Does folate deficiency cause subacute combined degeneration?
Folate deficiency causes the same megaloblastic anemia as B12 deficiency, but neurologic findings are rare. Labs separate the two: homocysteine is high in both, but methylmalonic acid is high only in B12 deficiency. Giving folic acid alone to a B12-deficient patient can correct the anemia while the neurologic damage progresses.
How does nitrous oxide cause subacute combined degeneration?
Nitrous oxide oxidizes the cobalt atom in vitamin B12, inactivating it and blocking B12-dependent enzymes such as methionine synthase. The result is a functional B12 deficiency, so serum B12 and MCV can be normal while methylmalonic acid and homocysteine are elevated. It is seen mainly with recreational use, and nitrous oxide given as an anesthetic can have the same effect in a patient with low B12 stores; treatment is stopping the exposure and giving parenteral B12.
Is subacute combined degeneration reversible?
Often only partly. Blood counts usually recover within about 6 weeks of B12 replacement, but neurologic recovery takes months, and deficits present for months to years may be permanent. Younger age, a short symptom duration and less extensive MRI involvement predict a better outcome, which is why treatment should start immediately.