The DCML (vibration, position sense, fine touch) and lateral corticospinal tract (movement) cross in the medulla; the spinothalamic tract (pain, temperature) crosses in the cord within 1–2 segments of entry. So a cord lesion causes same-side loss of vibration, position sense and strength but opposite-side loss of pain and temperature.
The visual hack: draw one big X at the bottom of the medulla, where DCML and corticospinal fibers cross, and a ladder of small x's down the cord, one per segment, where pain and temperature fibers cross. Below the big X (any cord lesion), weakness and vibration loss land on the lesion side and pinprick loss on the other; above it, all three land on the opposite side.
DCML vs spinothalamic vs corticospinal: side by side
| Feature | DCML | Spinothalamic (anterolateral system) | Lateral corticospinal |
|---|---|---|---|
| Carries | Vibration, conscious proprioception, fine touch, two-point discrimination | Pain and temperature (lateral part); crude touch, pressure (anterior part) | Voluntary movement, above all fine finger control |
| Starts in | Skin mechanoreceptors, muscle spindles, Golgi tendon organs | Free nerve endings: Aδ fibers (sharp pain, cold), C fibers (dull pain, warmth) | Precentral gyrus, plus secondary motor and somatosensory cortex |
| First neuron | Dorsal root ganglion cell; enters medially, climbs without synapsing | Dorsal root ganglion cell; enters laterally, runs 1–2 segments in Lissauer's tract | Upper motor neuron via internal capsule, cerebral peduncle, pons, pyramid |
| Synapses | Nucleus gracilis or cuneatus (caudal medulla), then VPL thalamus | Dorsal horn laminae I–II, then VPL thalamus | Anterior horn lower motor neuron, directly or via interneurons |
| Crosses | Caudal medulla (internal arcuate fibers) | Anterior white commissure, near entry | Pyramidal decussation (75–90% of fibers) |
| Runs in the cord | Dorsal columns, same side | Anterolateral cord, opposite side | Lateral funiculus, same side as its muscles |
| Legs sit | Medial (gracilis) | Lateral (sacral outermost) | Lateral, classically (disputed) |
| Cortex | Postcentral gyrus; leg in posterior paracentral lobule | Postcentral gyrus; insula and cingulate for slow pain | Leg area fed by the ACA, arm and face by the MCA |
| Cord lesion | Same-side loss below | Opposite-side loss from 1–2 segments below | Same-side UMN weakness below |
| Classic lesions | Tabes dorsalis, B12 deficiency | Syringomyelia, anterior spinal artery infarct | ALS, B12 deficiency |
DCML vs ALS: amyotrophic lateral sclerosis (ALS) destroys upper motor neurons (corticospinal tracts) and lower motor neurons (anterior horns, bulbar nuclei) but usually spares sensation, so vibration and position stay normal. Spastic weakness with vibration and position loss points to subacute combined degeneration (SCD).
The visual hack: where the DCML and spinothalamic tracts cross
Draw the nervous system as one vertical line from cortex to sacrum.
- Big X at the caudal medulla. DCML fibers synapse in the gracile and cuneate nuclei, and second-order axons cross as internal arcuate fibers to form the medial lemniscus. Corticospinal fibers cross at the pyramidal decussation, where medulla meets cord.
- Small x's down the cord. Second-order pain and temperature fibers cross in the anterior white commissure, just in front of the central canal, one small x per segment: the spinothalamic decussation.
Above the big X, corticospinal fibers are still uncrossed and sensory fibers already crossed, so body deficits land opposite the lesion; same-side cranial nerve signs mark a brainstem lesion.
| Right-sided lesion | Same side | Opposite side |
|---|---|---|
| Cord hemisection | UMN weakness, vibration and position loss below; LMN signs and all-modality loss at the level | Pain and temperature loss from 1–2 segments below |
| Medial medulla | Tongue deviates toward the lesion | Hemiparesis; vibration and position loss |
| Lateral medulla | Facial pain and temperature loss | Body pain and temperature loss |
| Thalamus (VPL) | None | All sensation; later, sometimes thalamic pain |
| Internal capsule lacune | None | Face, arm and leg weakness |
Brainstem versions are drilled in the brainstem syndromes mnemonic.
The DCML pathway, neuron by neuron
The dorsal column-medial lemniscus pathway carries discriminative touch and proprioception from the body (the face uses the trigeminal system).
- First-order neuron: a dorsal root ganglion cell. Its peripheral axon ends in Meissner corpuscles (light touch, low-frequency vibration), Merkel endings (pressure, texture), Ruffini endings (stretch), Pacinian corpuscles (high-frequency vibration), muscle spindles or Golgi tendon organs. The central axon enters the medial dorsal root entry zone, gives off reflex collaterals and climbs the ipsilateral dorsal column: fasciculus gracilis for roots up to T7, fasciculus cuneatus for T6 and above.
- Second-order neuron: nucleus gracilis or cuneatus in the caudal medulla; its axons sweep ventromedially as internal arcuate fibers, cross and ascend as the contralateral medial lemniscus.
- Third-order neuron: the VPL nucleus of the thalamus, projecting through the posterior limb of the internal capsule to the primary somatosensory cortex: postcentral gyrus for arm and trunk, posterior paracentral lobule for leg and foot.
At the bedside: dorsal column damage causes sensory ataxia with a positive Romberg sign (balance fails when the eyes close) and trouble recognizing numbers drawn on the skin, while simple touch suffers only modestly. The posterior spinal arteries supply the dorsal columns.
The spinothalamic tract (anterolateral system), neuron by neuron
The anterolateral system carries pain, temperature, crude touch and pressure; spinoreticular and spinomesencephalic fibers run with the spinothalamic tract to the brainstem.
- First-order neuron: a small dorsal root ganglion cell with free nerve endings: thinly myelinated Aδ fibers for sharp, well-localized pain and cold, unmyelinated C fibers for dull, burning pain and warmth. Central axons enter the lateral dorsal root and run up or down one or two segments in Lissauer's tract.
- Second-order neuron: in the dorsal horn. Aδ and C fibers end in laminae I (marginal zone) and II (substantia gelatinosa); projection neurons in laminae I and IV–VI cross in the anterior white commissure to the contralateral anterolateral quadrant, the lateral part carrying pain and temperature and the anterior part crude touch.
- Third-order neuron: the VPL nucleus, reached through the lateral medulla, projecting to the postcentral gyrus for sharp, localized pain. Dull, aching pain relays through the intralaminar nuclei to the insula and cingulate gyrus, which add its unpleasantness.
Why the pain level sits below the lesion: fibers entering just below a cut climb in Lissauer's tract and cross above it. Many references put the contralateral level 1–2 segments below the lesion; others say 2–3. The anterior spinal artery supplies the tract.
The lateral corticospinal tract and UMN vs LMN signs
- Upper motor neurons start mainly in the precentral gyrus and descend through the corona radiata, posterior limb of the internal capsule, cerebral peduncle, basis pontis and medullary pyramid.
- At the pyramidal decussation 75–90% of fibers cross (often quoted as about 90%) to form the lateral corticospinal tract, which drives the limbs and fine finger movements. Most uncrossed fibers form the anterior corticospinal tract, which crosses at its target segment, serves axial muscles and reaches only the thoracic cord.
- Lower motor neurons in the anterior horn receive the signal directly or, for most fibers, through interneurons.
| Finding | UMN lesion | LMN lesion (anterior horn, root, nerve) |
|---|---|---|
| Weakness pattern | Loss of fine finger movements | Individual muscles |
| Tone | Spastic: velocity-dependent, clasp-knife | Flaccid |
| Reflexes | Brisk, with clonus | Reduced or absent |
| Plantar response | Extensor (Babinski sign; normal in infants) | Normal (flexor) |
| Atrophy, fasciculations | Generally absent | Present |
Acute lesions mislead: right after a cord injury, UMN weakness is flaccid and areflexic (spinal shock); spasticity, brisk reflexes and Babinski signs appear over days to weeks. A cord lesion can show both: LMN signs at its level, where anterior horn cells die, and UMN signs below it.
Somatotopy: where the legs sit in each tract
- Dorsal columns, legs medial: the fasciculus gracilis (legs, lower trunk) is medial and the fasciculus cuneatus (arms, upper trunk, neck; T6 and above) lateral, so below T6 there is only gracilis.
- Spinothalamic tract, legs lateral: sacral fibers are outermost and cervical fibers innermost. A lesion expanding from the middle of the cord reaches arm fibers first and sacral fibers last, which is why central lesions can spare sacral sensation.
- Corticospinal tract, classic vs current: it is traditionally drawn the same way (arms medial, legs lateral) to explain why central cord syndrome weakens the arms more than the legs. Studies in humans and non-human primates found no such lamination, and current reviews blame diffuse injury to a tract densely packed with hand and arm fibers. Use the classic rule on exams, but know it is disputed.
Localize a spinal cord lesion in four steps
- Which modality? Vibration and position loss means dorsal columns; pinprick and temperature loss, spinothalamic tract; spasticity, brisk reflexes and Babinski signs, corticospinal tract; focal atrophy, fasciculations and areflexia, anterior horn or root.
- Which side? DCML and corticospinal deficits are on the lesion side, spinothalamic deficits on the other. Bilateral deficits point to a central, anterior, posterior or transverse lesion.
- Which level? The pinprick level sits 1–2 segments below a one-sided lesion, while LMN signs or a band of lost sensation mark the segment itself. Landmarks: C6 thumb, C7 middle finger, C8 little finger, T4 nipple line, T6 xiphoid, T10 umbilicus, T12 inguinal ligament, L4 medial malleolus, L5 dorsum of the foot, S1 lateral heel, S4–S5 perianal skin. Cord segments sit progressively higher than the vertebrae of the same number, and the cord ends at about L1–L2.
- What is spared? The spared tracts name the syndrome.
Classic spinal cord lesions compared
| Lesion | What is damaged | Vibration, position | Pain, temperature | Motor | Clues |
|---|---|---|---|---|---|
| Brown-Séquard | One half of the cord | Lost, same side | Lost, opposite side, from 1–2 segments below | Same-side UMN below, LMN at the level | Stab wound; Horner syndrome if cervical or upper thoracic |
| Anterior cord (anterior spinal artery) | Anterior two-thirds: corticospinal and spinothalamic tracts, anterior horns | Spared | Lost on both sides below | Bilateral, flaccid then spastic; bladder dysfunction | Aortic surgery or dissection, hypotension; sudden onset |
| Posterior cord | Both dorsal columns | Lost; positive Romberg | Spared | Normal | Tabes dorsalis, B12 or copper deficiency, compression, rare posterior spinal artery infarct |
| Central cord | Central cervical cord | Variable | Variable; sacral sparing | Arms and hands weaker than legs; bladder dysfunction | Older adult, cervical stenosis, hyperextension fall |
| Syringomyelia | Anterior white commissure, then anterior horns and lateral tracts | Spared | Lost on both sides in a cape (shoulders, arms) | Later hand wasting (LMN), spastic legs (UMN) | Chiari I, old trauma, tumor; painless burns |
| SCD | Dorsal columns, lateral corticospinal and spinocerebellar tracts | Lost; positive Romberg | Usually spared | Spastic paraparesis, Babinski; neuropathy may coexist | B12 deficiency, nitrous oxide, copper deficiency; anemia may be absent |
| Tabes dorsalis | Dorsal roots and dorsal columns | Lost; positive Romberg | Deep pain lost; lightning pains | Hypotonic, areflexic legs; sensory ataxia | Tertiary syphilis 10–30 years after infection; Argyll Robertson pupils |
| ALS | Corticospinal tracts, anterior horns, bulbar nuclei | Spared | Spared | Mixed UMN and LMN, often asymmetric hand onset | Eye movements and sphincters usually spared |
| Poliomyelitis | Anterior horn cells | Spared | Spared | Asymmetric flaccid paralysis, legs most often | Sudden weakness after fever or gastrointestinal illness |
| Spinal muscular atrophy | Anterior horn cells (SMN1, autosomal recessive) | Spared | Spared | Symmetric proximal weakness, hypotonia, reduced or absent reflexes | Floppy infant, tongue fasciculations |
| Conus medullaris | Cord tip, about T12–L2 | Perianal, symmetric | Perianal, symmetric | Milder distal weakness; UMN signs possible | Sudden; early bladder, bowel and sexual dysfunction |
| Cauda equina | Lumbosacral roots, not the cord | Saddle, often asymmetric | Saddle, often asymmetric | LMN only: flaccid, areflexic | Gradual; severe radicular pain; late urinary retention; disc herniation |
Deep dives: Brown-Séquard syndrome, anterior cord syndrome, posterior cord syndrome, syringomyelia, subacute combined degeneration, tabes dorsalis, ALS, poliomyelitis and cauda equina vs conus medullaris.
Other spinal tracts, briefly
| Tract | From | Crosses? | Job | Exam hook |
|---|---|---|---|---|
| Spinocerebellar | Clarke's nucleus, C8–L3 (dorsal tract) | Dorsal: no, via inferior cerebellar peduncle; ventral: twice, via superior peduncle | Unconscious proprioception (dorsal tract) to the cerebellum | Friedreich ataxia, with dorsal columns and corticospinal tracts |
| Rubrospinal | Red nucleus, midbrain | Immediately | Excites flexors, mainly of the arm | Decorticate posture: lesion above the red nucleus |
| Lateral vestibulospinal | Lateral vestibular nucleus | No | Excites antigravity extensors | Decerebrate posture: lesion below the red nucleus, above the vestibular nuclei |
| Reticulospinal | Pontine and medullary reticular formation | Mostly no | Posture, locomotion, gating of flexor reflexes | Major alternative route for cortical motor control |
Decorticate posture flexes the arms and extends the legs; decerebrate posture extends both.
USMLE traps
| Trap | What is true |
|---|---|
| Light touch tests the dorsal columns | Crude touch also runs in the anterolateral system; test vibration and position |
| The pinprick level is the lesion level | The lesion sits 1–2 segments higher (2–3 in some references) |
| Corticospinal fibers are laminated, legs lateral | The classic answer for central cord syndrome; human and primate studies found none |
| ALS causes dorsal column loss | Sensation is usually spared; vibration loss plus spasticity suggests SCD |
| A normal blood count or B12 level excludes B12 myelopathy | Neurologic disease can occur without anemia; normal B12 with high methylmalonic acid still fits B12 deficiency (ask about nitrous oxide); if both are normal, check copper |
| Cauda equina syndrome is a cord syndrome | It is a root (LMN) syndrome that mimics conus medullaris syndrome |
| Tabes dorsalis and SCD look alike | Both give a positive Romberg; tabes adds lightning pains, areflexia and Argyll Robertson pupils, SCD adds spasticity and Babinski signs |
More neuroanatomy walkthroughs are on the Neurology hub.
Worked USMLE-style vignettes
Vignette 1: the stab wound. Three weeks after a stab wound to the back, a 28-year-old man has a weak, hyperreflexic right leg with an extensor plantar response, no position sense in the right leg and no vibration sense on the right below the umbilicus. Pinprick and temperature sensation are lost on the left from about two dermatomes below the umbilicus. Where is the lesion?
A. Anterior white commissure at T10; B. Left half of the cord at T10; C. Right fasciculus gracilis at T10; D. Right half of the cord at T10; E. Right corticospinal tract above the pyramidal decussation
Answer: D, Brown-Séquard syndrome at T10 (umbilicus): the right dorsal column and corticospinal tract are cut before they cross, the right spinothalamic tract after, and fibers entering just below the cut cross above it. Why not the others: A gives a bilateral band of pinprick loss with normal strength (a syrinx); B is the mirror image; C misses the weakness and pinprick loss; E would weaken the left side, with no trunk sensory level.
Vignette 2: DCML vs ALS. A 58-year-old man has 8 months of weakness that began in his right hand. He has wasted hand muscles, fasciculations in the arms and tongue, spastic legs with brisk reflexes and extensor plantar responses. Vibration, position, pinprick and temperature sensation and bladder function are normal. Which structures are affected?
A. Dorsal columns and lateral corticospinal tracts; B. Anterior horn cells only; C. Corticospinal tracts and anterior horn cells; D. Anterior white commissure, anterior horns and lateral corticospinal tracts; E. Dorsal roots and dorsal columns
Answer: C, ALS: UMN plus LMN signs with normal sensation. Why not the others: A (SCD) removes vibration and position; B (polio, spinal muscular atrophy) gives no UMN signs; D (syrinx) causes cape-like pinprick loss; E (tabes dorsalis) causes sensory ataxia and areflexia.
Vignette 3: after aortic surgery. A 71-year-old woman wakes from thoracoabdominal aortic aneurysm repair with flaccid, areflexic legs and urinary retention. Pinprick and temperature sensation are lost below the umbilicus on both sides; vibration and position sense in the toes are normal. What is the most likely diagnosis?
A. Anterior spinal artery infarction; B. Posterior spinal artery infarction; C. Central cord syndrome; D. Cauda equina syndrome; E. Brown-Séquard syndrome
Answer: A. The anterior spinal artery feeds the anterior two-thirds of the cord and depends on feeders from the aorta, the largest being the artery of Adamkiewicz in the lower thoracic region; the posterior spinal arteries keep the dorsal columns alive. Flaccid areflexia is spinal shock. Why not the others: B removes vibration and position but spares strength; C weakens the arms more than the legs; D is a root lesion with saddle anesthesia and no dissociated sensory level; E is one-sided.
Vignette 4: the painless burns. A 34-year-old woman has burned her hands twice without feeling it and gets occipital headaches when she coughs. Pinprick and temperature sensation are lost over both shoulders and arms; light touch, vibration and position sense are normal. Her hand muscles are wasted and her leg reflexes brisk. Which structure was damaged first?
A. Anterior white commissure; B. Dorsal columns; C. Both lateral spinothalamic tracts; D. Anterior spinal artery territory; E. Right half of the cervical cord
Answer: A, cervical syringomyelia, with cough headache suggesting a Chiari I malformation. The syrinx first cuts the crossing spinothalamic fibers (a bilateral cape at its own segments), then reaches the anterior horns (hand wasting) and lateral corticospinal tracts (brisk leg reflexes). Why not the others: B removes vibration and position; C causes pinprick loss below the lesion, legs included; D is sudden, with weakness below the lesion; E is one-sided.
Key takeaways
- DCML vs spinothalamic: the DCML (vibration, position, fine touch) climbs uncrossed and crosses in the caudal medulla; the spinothalamic tract (pain, temperature, crude touch) crosses in the anterior white commissure within 1–2 segments of entry.
- Cord lesion: same-side vibration and position loss and UMN weakness below; opposite-side pinprick loss from 1–2 segments below; LMN signs at the level. Above the medulla, body deficits are contralateral.
- Somatotopy: the dorsal columns put the legs medial (gracilis) and the arms lateral (cuneatus, T6 and up); the spinothalamic tract puts sacral fibers lateral; legs-lateral corticospinal lamination is the classic but disputed exam answer.
- Spared tracts name the syndrome: anterior cord spares vibration and position, posterior cord spares strength and pinprick, a syrinx spares all but crossing pain fibers at its level, ALS spares sensation.
- UMN vs LMN: spasticity, brisk reflexes, Babinski signs vs atrophy, fasciculations, areflexia; the conus can mix both, cauda equina is pure LMN.
Sources
- Somatosensory Pathways (Neuroscience Online, Section 2, Chapter 4) — McGovern Medical School at UTHealth Houston (2026)
- Spinal Reflexes and Descending Motor Pathways (Neuroscience Online, Section 3, Chapter 2) — McGovern Medical School at UTHealth Houston (2026)
- Central Pain Pathways: The Spinothalamic Tract — Neuroscience, 2nd ed. (Purves et al.), NCBI Bookshelf (2001)
- The Dorsal Column-Medial Lemniscus System — Neuroscience, 2nd ed. (Purves et al.), NCBI Bookshelf (2001)
- The Upper Motor Neuron Syndrome — Neuroscience, 2nd ed. (Purves et al.), NCBI Bookshelf (2001)
- Neural Centers Responsible for Movement — Neuroscience, 2nd ed. (Purves et al.), NCBI Bookshelf (2001)
- Neuroanatomy, Spinothalamic Tract — StatPearls, NCBI Bookshelf (2023)
- Neuroanatomy, Posterior Column (Dorsal Column) — StatPearls, NCBI Bookshelf (2023)
- Neuroanatomy, Medial Lemniscus — StatPearls, NCBI Bookshelf (2025)
- Neuroanatomy, Lateral Corticospinal Tract — StatPearls, NCBI Bookshelf (2023)
- Neuroanatomy, Corticospinal Cord Tract — StatPearls, NCBI Bookshelf (2023)
- Corticospinal Tract Lesion — StatPearls, NCBI Bookshelf (2023)
- Neuroanatomy, Upper Motor Neuron Signs — StatPearls, NCBI Bookshelf (2026)
- Neuroanatomy, Lower Motor Neuron Lesion — StatPearls, NCBI Bookshelf (2023)
- Topographic and Functional Anatomy of the Spinal Cord — Medscape (2015)
- Overview of Spinal Cord Disorders — Merck Manual Professional Edition (2025)
- Spinal Cord Infarction — Merck Manual Professional Edition (2025)
- Brown-Séquard Syndrome — StatPearls, NCBI Bookshelf (2024)
- Anterior Cord Syndrome (Ventral Cord Syndrome) — StatPearls, NCBI Bookshelf (2025)
- Central Cord Syndrome — StatPearls, NCBI Bookshelf (2026)
- Shakil H, et al. Pathophysiology and Surgical Decision-Making in Central Cord Syndrome and Degenerative Cervical Myelopathy: Correcting the Somatotopic Fallacy — Front Neurol (2023)
- Syringomyelia — StatPearls, NCBI Bookshelf (2024)
- Spinal Cord Subacute Combined Degeneration — StatPearls, NCBI Bookshelf (2024)
- Tabes Dorsalis — StatPearls, NCBI Bookshelf (2024)
- Syphilis (tabes dorsalis) — Merck Manual Professional Edition (2025)
- Amyotrophic Lateral Sclerosis (ALS) and Other Motor Neuron Diseases — Merck Manual Professional Edition (2026)
- Poliomyelitis — StatPearls, NCBI Bookshelf (2024)
- Spinal Muscular Atrophy — GeneReviews, NCBI Bookshelf (2026)
- Cauda Equina and Conus Medullaris Syndromes — StatPearls, NCBI Bookshelf (2023)
- Cauda Equina and Conus Medullaris Syndromes — Medscape (2016)
- Neurological Examination in Spinal Cord Injury (key sensory points) — AOSpine (2017)
- Rupp R, et al. International Standards for Neurological Classification of Spinal Cord Injury: Revised 2019 — Top Spinal Cord Inj Rehabil (2021)
- Romberg Test — StatPearls, NCBI Bookshelf (2023)
- Neuroanatomy, Spinocerebellar Dorsal Tract — StatPearls, NCBI Bookshelf (2023)
- Decerebrate and Decorticate Posturing — StatPearls, NCBI Bookshelf (2023)
- Lateral Medullary Syndrome (Wallenberg Syndrome) — StatPearls, NCBI Bookshelf (2026)
- Medial Medullary Syndrome — StatPearls, NCBI Bookshelf (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
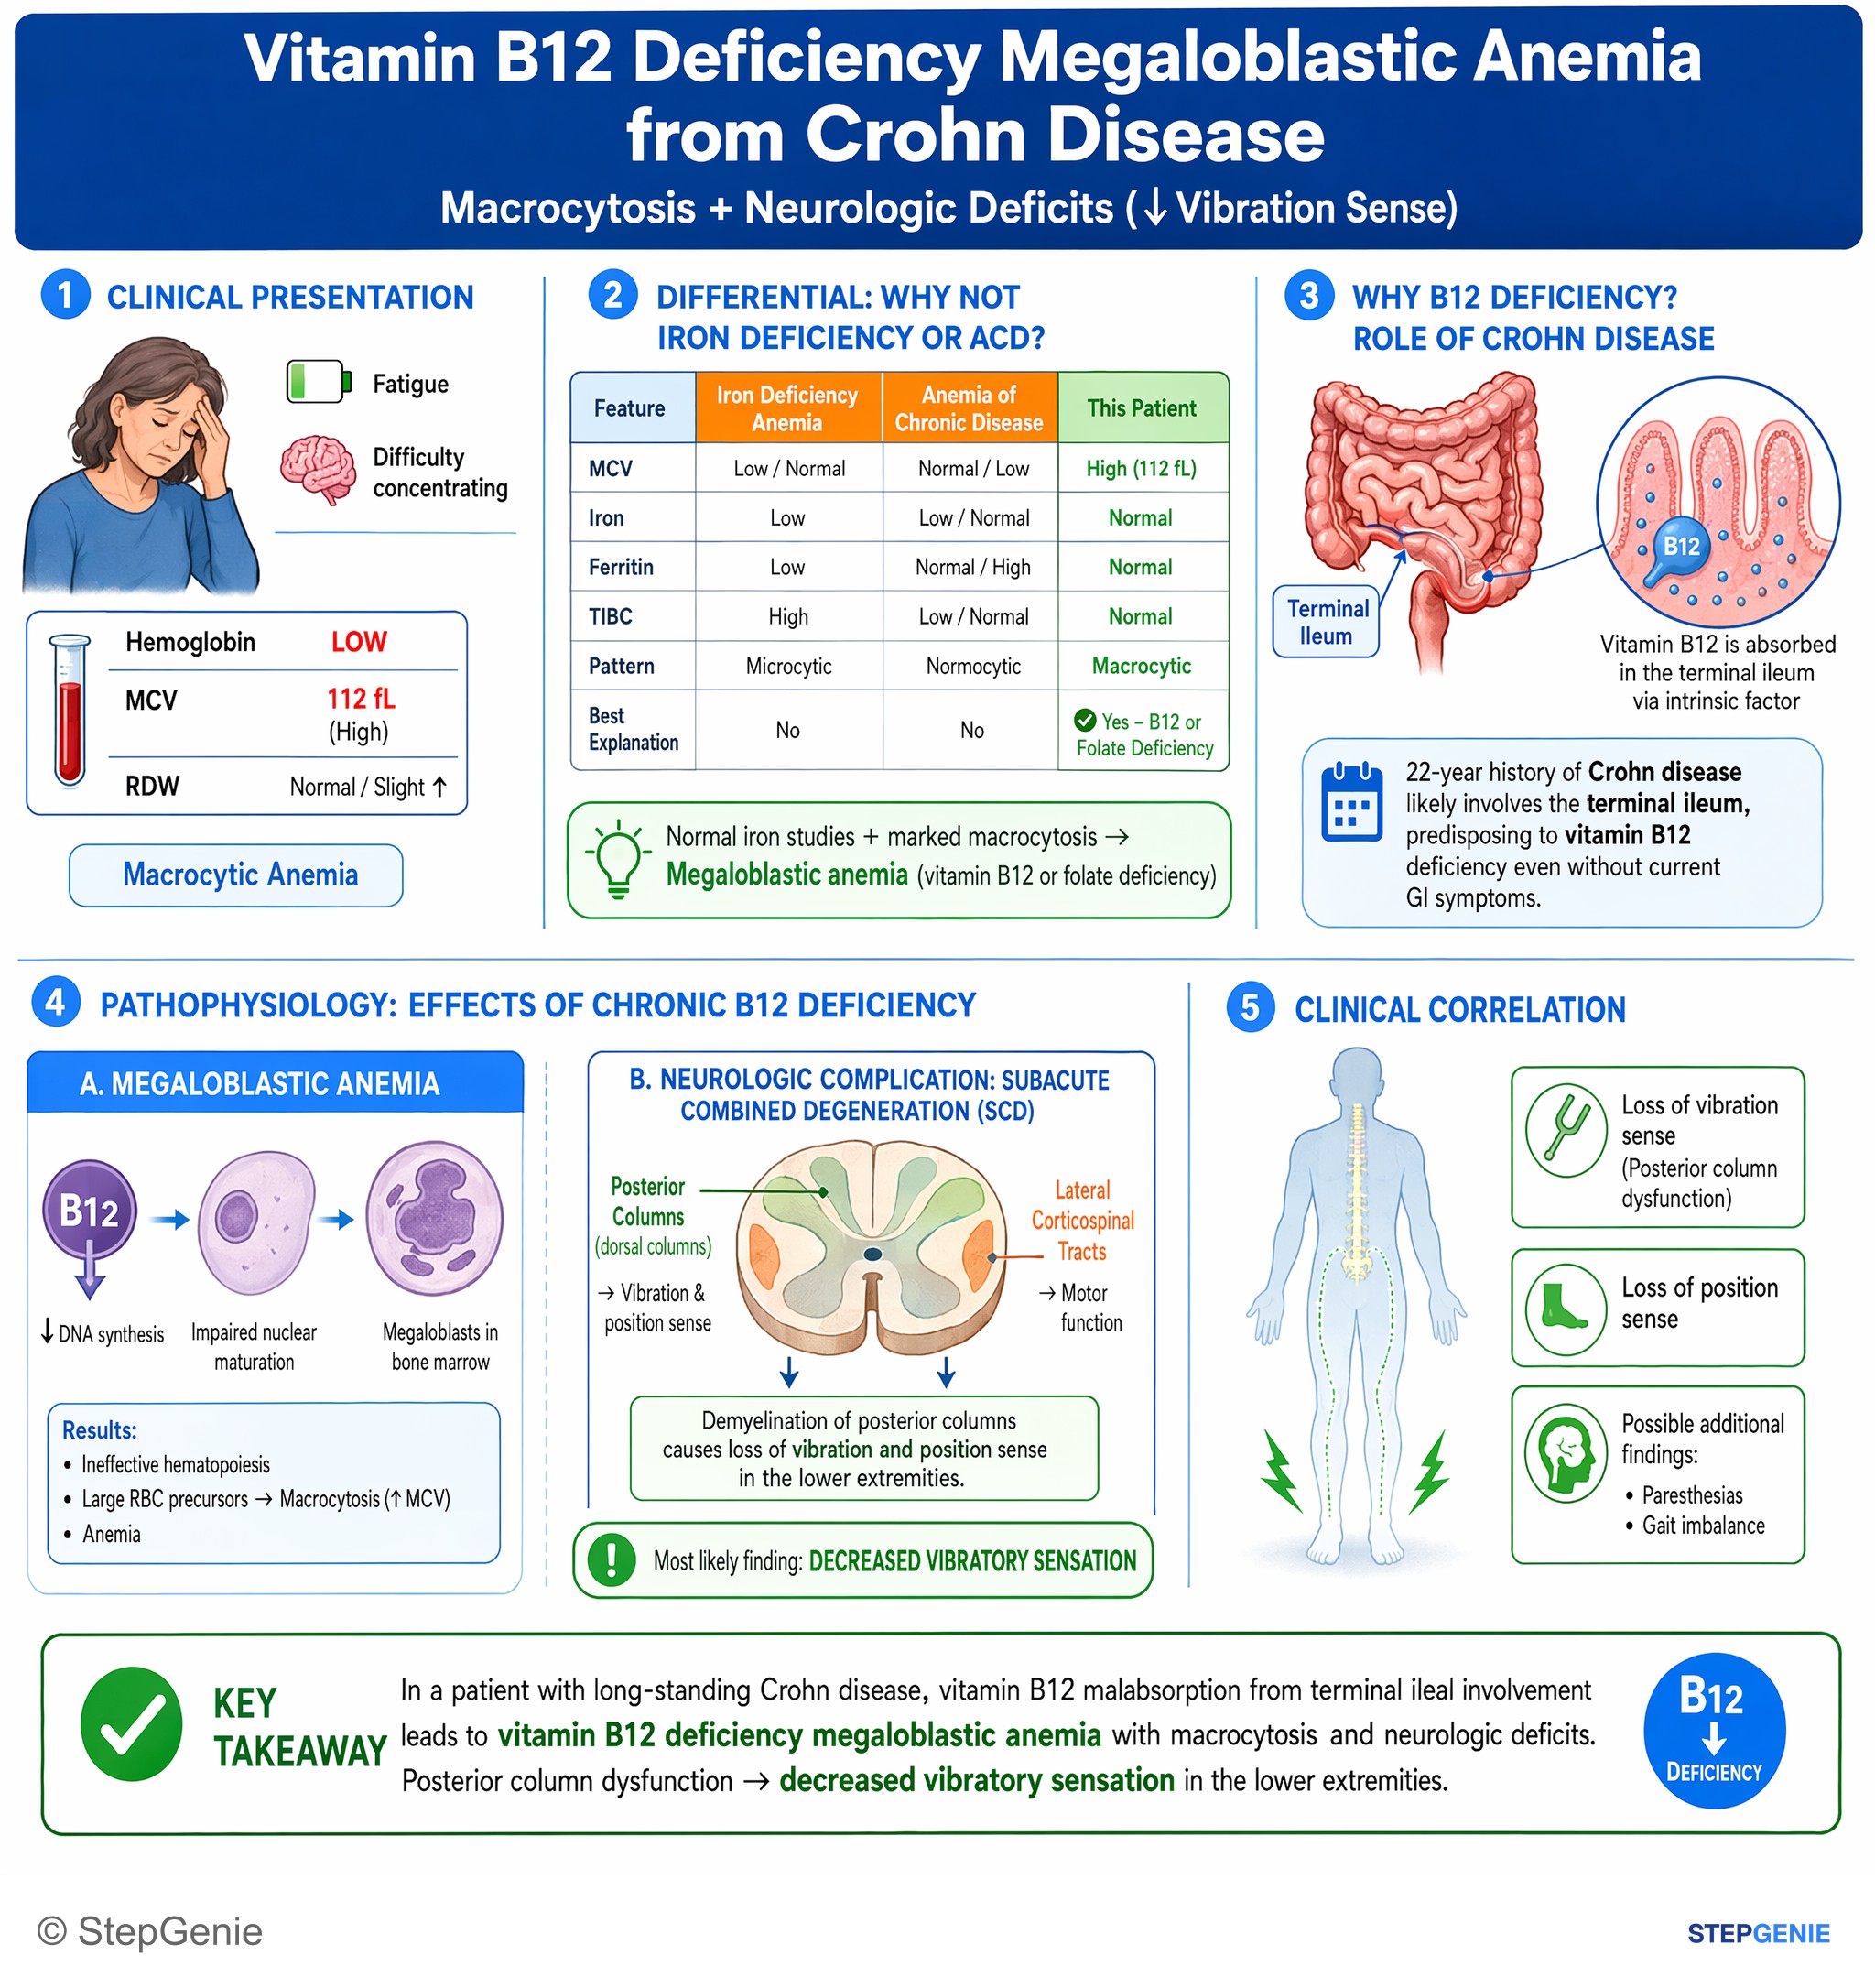
Vitamin B12 deficiency megaloblastic anemia from long-standing Crohn disease causes macrocytosis and neurologic deficits such as decreased…
USMLE Step 1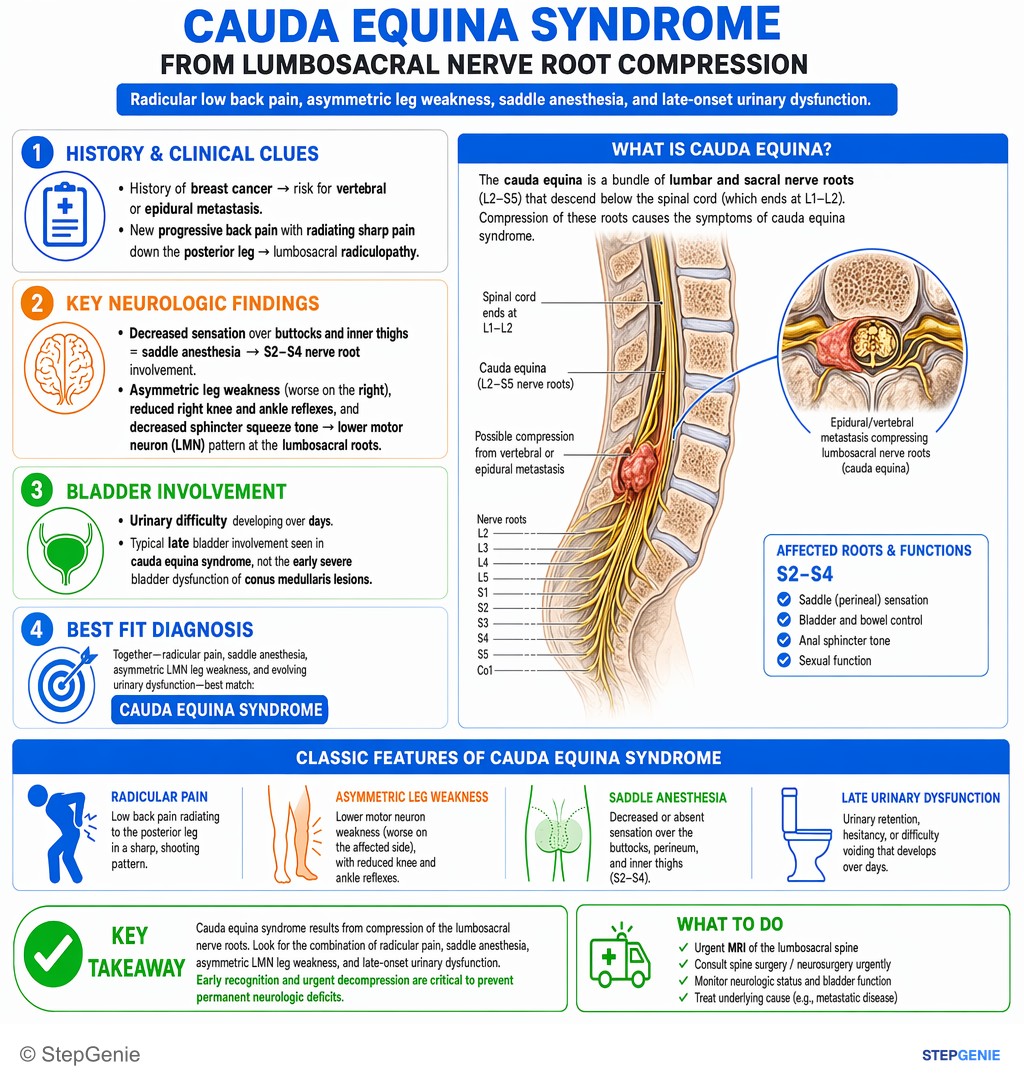
Cauda equina syndrome from lumbosacral nerve root compression: radicular low back pain, asymmetric leg weakness, saddle anesthesia, and…
USMLE Step 2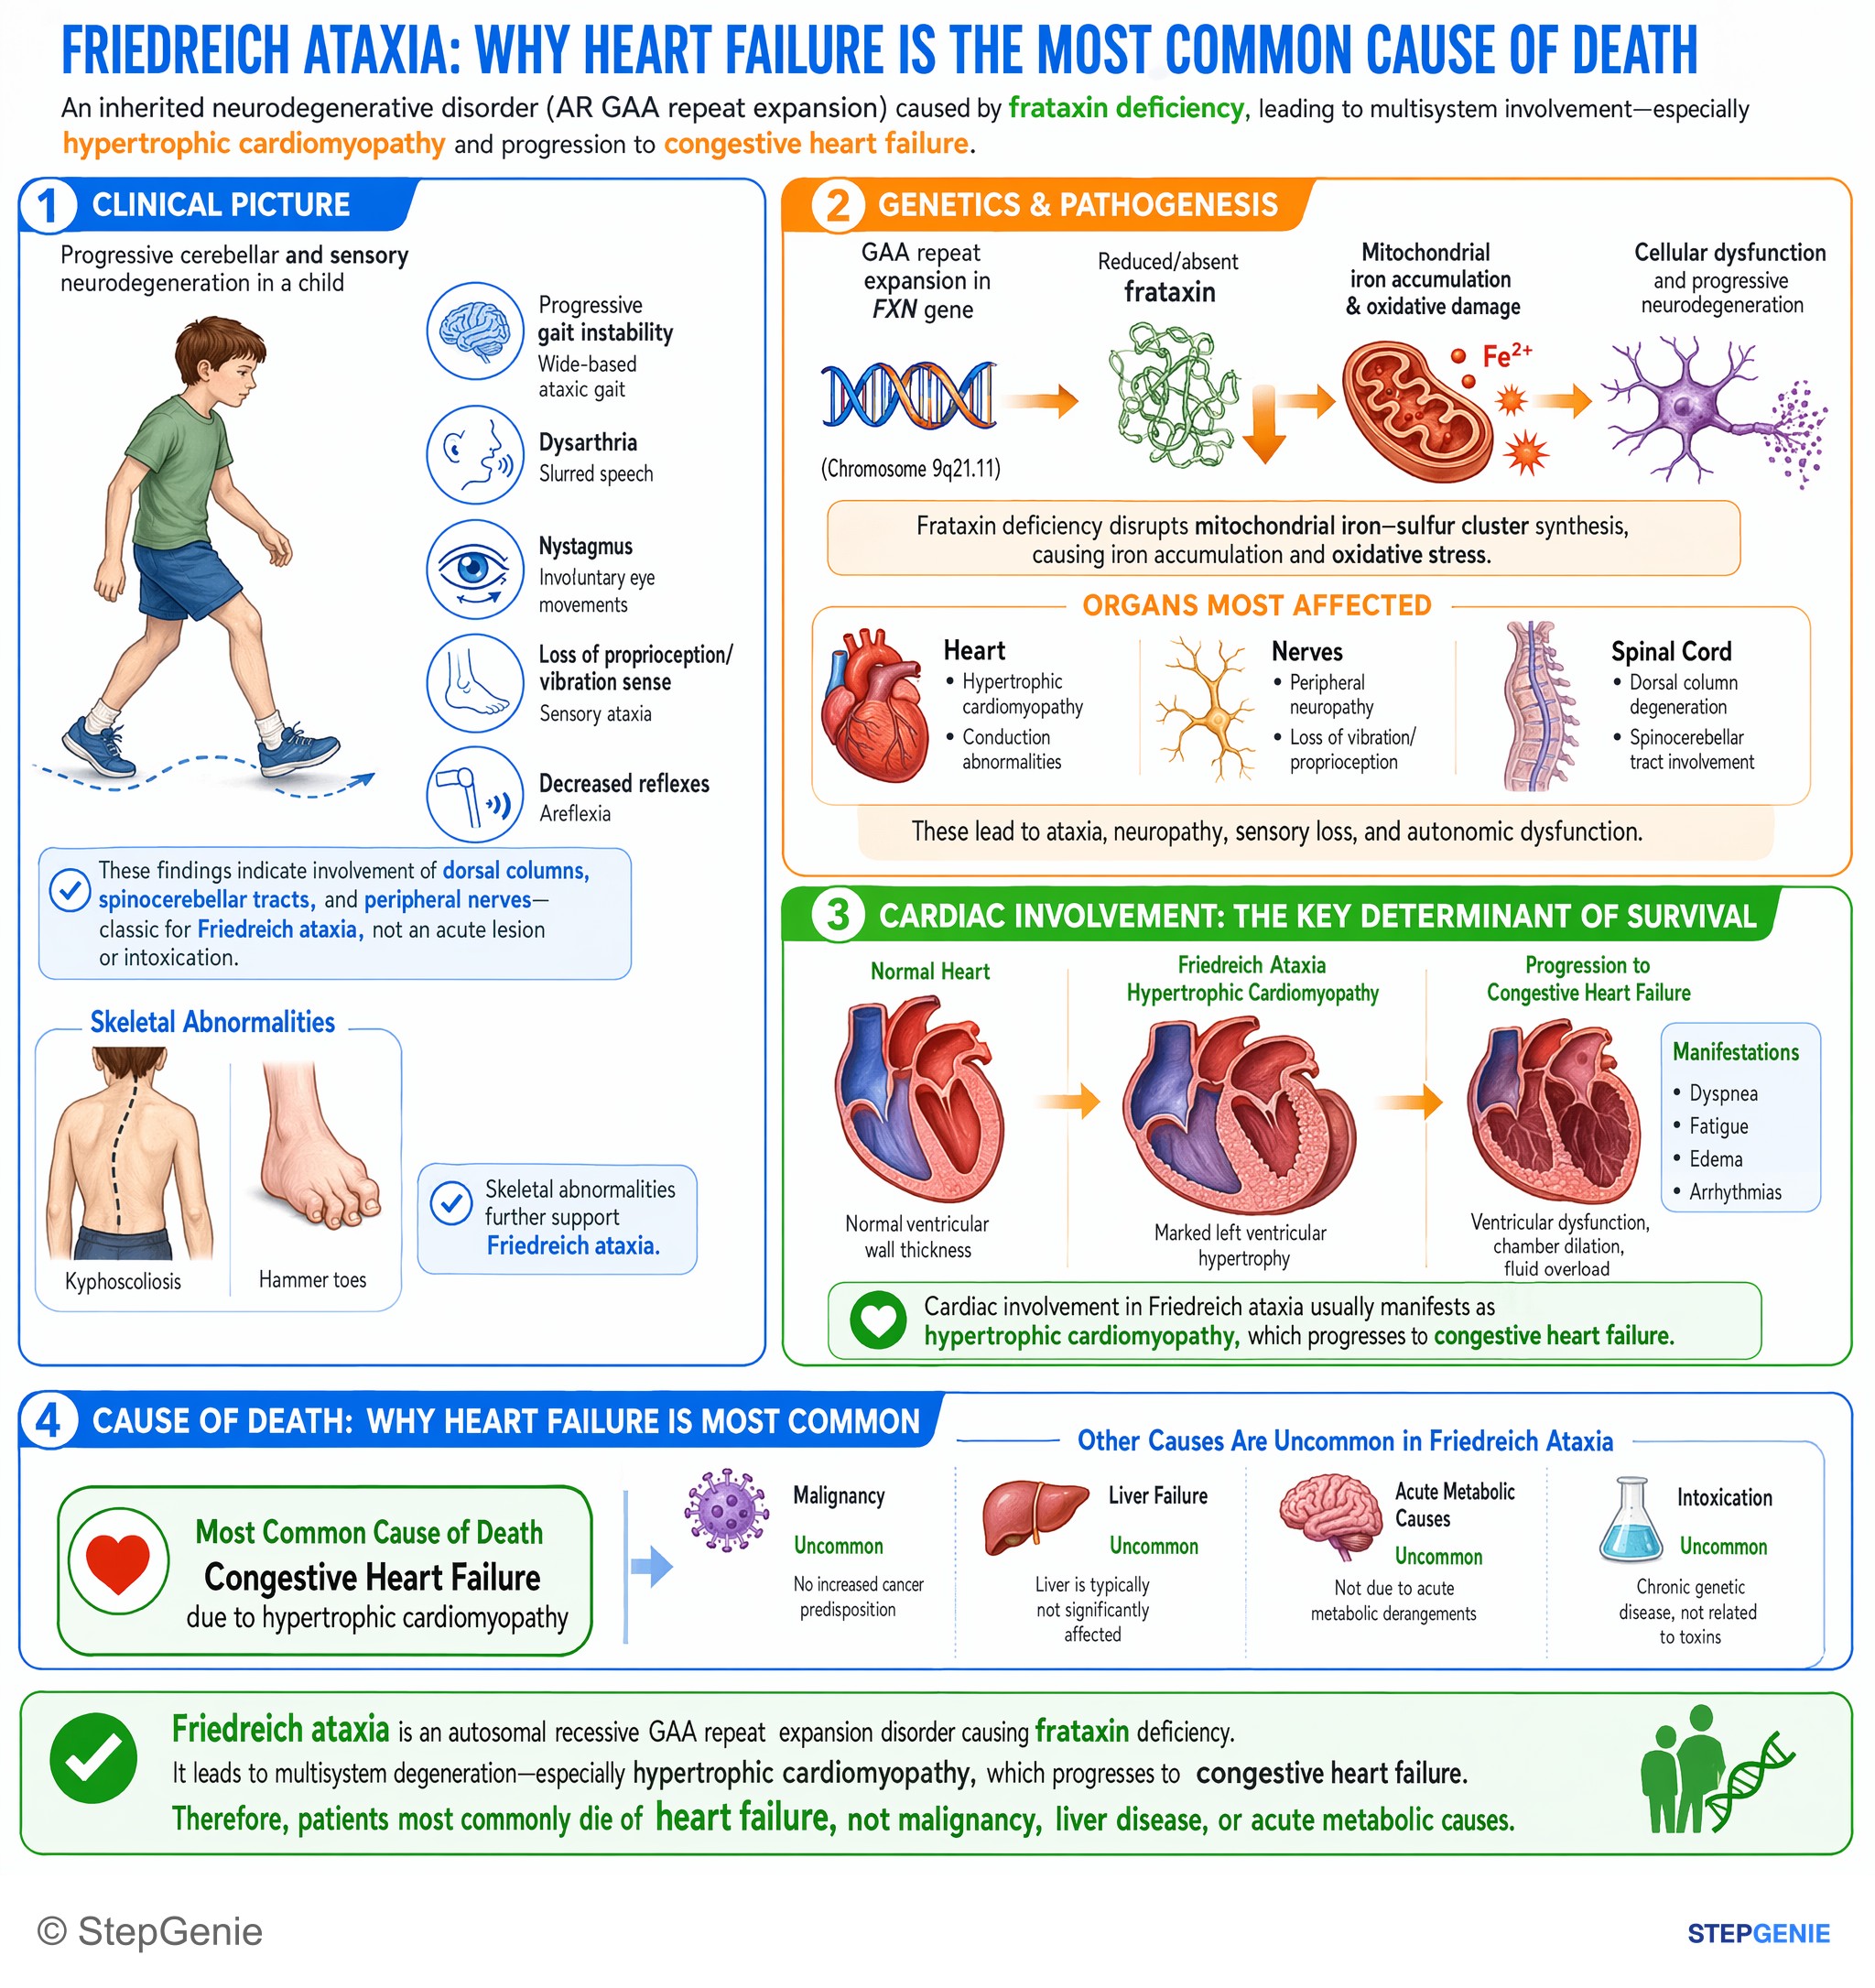
Friedreich ataxia (AR GAA repeat, frataxin deficiency) causes hypertrophic cardiomyopathy; patients most commonly die of congestive heart…
USMLE Step 1Frequently Asked Questions
What is the difference between the DCML and spinothalamic tracts?
The dorsal column-medial lemniscus (DCML) pathway carries vibration, conscious proprioception and fine touch; its first-order fibers climb the same side of the cord in the dorsal columns, and the pathway crosses in the caudal medulla. The spinothalamic tract carries pain, temperature and crude touch; its second-order fibers cross in the anterior white commissure within one or two segments of entry. A spinal cord lesion therefore causes same-side vibration loss but opposite-side pain loss.
Where does the DCML cross?
The DCML crosses in the caudal medulla. First-order axons ascend uncrossed in the fasciculus gracilis or cuneatus and synapse in the nucleus gracilis or cuneatus. The second-order axons then sweep ventromedially as internal arcuate fibers, cross the midline and ascend as the contralateral medial lemniscus to the VPL nucleus of the thalamus. So a cord lesion removes vibration and position sense on its own side, and a lesion above the medulla on the opposite side.
Where does the spinothalamic tract decussate?
Second-order spinothalamic axons decussate in the anterior white commissure, just in front of the central canal, close to the segment where their first-order fibers entered. Those first-order fibers first run up or down one or two segments in Lissauer's tract and synapse in the dorsal horn. That is why contralateral pain and temperature loss after a cord lesion begins about one to two segments below it; some clinical references say two to three.
What are the three neurons of the DCML pathway?
First-order neurons are dorsal root ganglion cells whose central axons ascend uncrossed in the fasciculus gracilis (legs, roots up to T7) or the fasciculus cuneatus (arms, T6 and above). Second-order neurons in the nucleus gracilis and cuneatus of the caudal medulla cross as internal arcuate fibers and form the medial lemniscus. Third-order neurons in the thalamic VPL nucleus project through the posterior limb of the internal capsule to the primary somatosensory cortex.
Does ALS affect the DCML?
No. Amyotrophic lateral sclerosis destroys upper motor neurons, whose axons form the corticospinal tracts, and lower motor neurons in the anterior horns and brainstem, so it mixes spasticity, brisk reflexes and Babinski signs with atrophy and fasciculations. Sensory systems are usually spared, so vibration and position sense stay normal. Vibration and position loss with spastic weakness points instead to subacute combined degeneration, which damages the dorsal columns and lateral corticospinal tracts.
What are the findings in Brown-Séquard syndrome?
A hemisection of the cord causes, below the lesion, same-side upper motor neuron weakness and same-side loss of vibration and position sense, plus opposite-side loss of pain and temperature starting about one to two segments below it. At the level of the lesion there can be same-side lower motor neuron signs and loss of all sensation, and a cervical or upper thoracic lesion can add a Horner syndrome. Stab wounds are the classic cause.