Acute lymphoblastic leukemia (ALL) is a cancer of lymphoid precursors (lymphoblasts) that replaces the marrow (at least 20% lymphoblasts) and causes anemia, bleeding and infections, often with bone pain; it is the most common childhood cancer, with a peak at ages 2-5. Blasts are TdT+: B-ALL (80-85% of childhood cases) is CD19+ and usually CD10+, while T-ALL is cytoplasmic CD3+ and CD7+ and classically presents as an adolescent boy with an anterior mediastinal mass. In children, high hyperdiploidy and t(12;21) ETV6::RUNX1 predict an excellent outcome, whereas t(9;22) BCR::ABL1 (the Philadelphia chromosome, in about 25% of adults) was once the worst lesion and is now treated with a tyrosine kinase inhibitor (TKI), increasingly combined with blinatumomab.
B-ALL vs T-ALL: the comparison table
| Feature | B-ALL | T-ALL |
|---|---|---|
| Share | 80-85% of childhood ALL; about 80% of adult ALL | Most of the rest; 10-15% of adult ALL |
| Typical patient | Young child (peak age 2-5) | Adolescent or young adult, usually male |
| Presentation | Pancytopenia, bone pain, hepatosplenomegaly, lymphadenopathy | Same, plus high WBC and an anterior mediastinal (thymic) mass: cough, dyspnea, SVC syndrome |
| Lineage markers | CD19 with CD79a, CD22 or CD10; CD10 in about 90% | Cytoplasmic CD3 (defining) with CD7 plus CD2 or CD5 |
| TdT | Positive | Positive |
| Genetics | Ploidy and fusion genes set the risk (table below) | NOTCH1 and/or FBXW7 activation in about 60%; hyperdiploidy rare |
| Prognosis notes | Age, WBC, genetics, MRD | Age not prognostic; a mediastinal mass is not prognostic; outcome now approaches B-ALL with intensive therapy |
| Subsets to know | Ph+ and Ph-like (BCR::ABL1-like): higher risk | Early T-precursor (ETP) ALL: CD1a−, CD8−, weak CD5, stem-cell or myeloid markers; slower early response, but not an independent adverse factor on current therapy |
| Extramedullary form | B-lymphoblastic lymphoma | T-lymphoblastic lymphoma |
Leukemia and lymphoblastic lymphoma are one disease: it is called leukemia when blasts fill blood and marrow, and lymphoma when they sit mainly outside the marrow, which is why the WHO name is "lymphoblastic leukemia/lymphoma".
Genetics and prognosis: the must-know list
| Lesion | WHO 2022 entity | Who gets it | Prognosis |
|---|---|---|---|
| High hyperdiploidy (51-65 chromosomes) | B-ALL with high hyperdiploidy | About 25% of children | Favorable |
| t(12;21) ETV6::RUNX1 | B-ALL with ETV6::RUNX1 fusion | 20-25% of children, mostly ages 2-9 | Favorable; cryptic, so found by FISH, not routine karyotype |
| t(9;22) BCR::ABL1 (Ph+) | B-ALL with BCR::ABL1 fusion | About 25% of adults, 2-5% of children | Historically poor; much improved with TKIs |
| BCR::ABL1-like (Ph-like) | B-ALL with BCR::ABL1-like features | All ages (10-20% of children, more with age) | Unfavorable; some kinase fusions (e.g., ABL-class) respond to TKIs |
| KMT2A rearranged, e.g. t(4;11) | B-ALL with KMT2A rearrangement | Up to 80% of infants | Poor: CD10-negative, very high WBC, CNS disease |
| Hypodiploidy (<44 chromosomes) | B-ALL with hypodiploidy | About 5% | Poor; linked to germline TP53 variants |
| iAMP21 | B-ALL with iAMP21 | Older children (median age about 10) | Poor on standard therapy, much better with intensified therapy |
The 2022 WHO (5th edition) names B-ALL by its genetic driver, upgraded BCR::ABL1-like ALL to a full entity, and added ETV6::RUNX1-like and TCF3::HLF types. The 2022 International Consensus Classification (ICC) uses parallel names and further splits BCR::ABL1-positive B-ALL into lymphoid-only and multilineage types (the latter arises in a multipotent progenitor). Both keep T-ALL and early T-precursor ALL; ICC adds provisional genetic T-ALL subtypes.
Children vs adults
| Children | Adults | |
|---|---|---|
| Share of cases | About 60% of all ALL | About 40%, with a second peak after age 50 |
| Ph+ ALL | 2-5% | About 25%, rising with age |
| Favorable genetics | Common (hyperdiploidy, ETV6::RUNX1) | Uncommon |
| Complete remission | 95% or more | 70-90% |
| Long-term outcome | 5-year survival about 90% under age 15 and over 75% at ages 15-19 | Lower: more high-risk genetics, comorbidities and less tolerance of intensive therapy |
| Risk grouping | NCI standard risk: age 1 to under 10 and WBC under 50,000/µL; high risk: age 10 or older and/or WBC 50,000/µL or more | Age, Ph status, KMT2A, karyotype, MRD |
In every age group, measurable (minimal) residual disease (MRD) after induction is the strongest predictor of relapse. Infants younger than 1 year, CNS3 status (5 or more WBC/µL in the CSF with blasts, or clinical CNS signs) and persistent MRD all add risk. Testicular involvement at diagnosis (about 2% of boys) no longer predicts a worse outcome with modern therapy.
How ALL presents and is diagnosed
- Marrow failure: anemia (fatigue, pallor), thrombocytopenia (petechiae, epistaxis, gum bleeding) and neutropenia (fever, infections). Infection risk stays high even with a huge WBC, because blasts do not fight infection.
- Infiltration: bone and joint pain (especially in children), hepatosplenomegaly, lymphadenopathy, CNS signs (headache, cranial nerve palsies) and painless testicular swelling.
- CBC and smear: pancytopenia with circulating blasts; the WBC can be very high. Auer rods are never seen in ALL.
- Bone marrow: lymphoblasts at least 20% of nucleated cells (Merck).
- Flow cytometry: TdT is elevated in about 95% of ALL but also in about 20% of AML, so lineage markers (CD19, CD22, CD79a for B; cytoplasmic CD3 for T; myeloperoxidase for myeloid) decide.
- Cytogenetics, FISH and molecular tests set the risk group; lumbar puncture defines CNS status.
- Tumor lysis labs (high uric acid, potassium and phosphate, low calcium, high LDH), chest imaging for a mediastinal mass, and an echocardiogram before anthracyclines.
Children with Down syndrome have a 20- to 30-fold higher risk of ALL (and over 100-fold higher risk of AML); see the Down syndrome breakdown.
ALL vs look-alikes
| Disorder | Biggest separator from ALL |
|---|---|
| AML | Myeloperoxidase+, CD13/CD33/CD117; Auer rods; t(15;17) APL presents with DIC (AML breakdown) |
| Burkitt leukemia (mature B-cell "ALL") | TdT-negative, surface immunoglobulin+, MYC translocation; treated as Burkitt lymphoma |
| CLL | Older adults; small mature CD5+, CD19+, CD20+, CD23+ B cells (CLL guide) |
| CML | t(9;22) with the larger p210 fusion (Ph+ ALL usually has p190) and maturing myeloid cells (CML guide) |
| Aplastic anemia, B12 or folate deficiency, viral infection | Pancytopenia without lymphoblasts |
Treatment, and how Ph+ ALL changed
- Phases over 2-3 years: induction (vincristine, a glucocorticoid and asparaginase in children, adding an anthracycline for high-risk B-ALL and all T-ALL; adult regimens are built around a glucocorticoid, vincristine and an anthracycline), consolidation and intensification, then maintenance with daily mercaptopurine, weekly methotrexate and periodic vincristine-glucocorticoid pulses (monthly in many regimens).
- CNS prophylaxis throughout: intrathecal methotrexate, with or without cytarabine and hydrocortisone, because the CNS (like the testes) is a sanctuary site; cranial irradiation is now used far less.
- Tumor lysis prevention: vigorous IV hydration plus allopurinol or rasburicase (contraindicated in G6PD deficiency), started before chemotherapy; urine alkalinization is optional at best, because it can promote calcium phosphate deposition.
- Pharmacogenomics: patients homozygous for low-activity TPMT (or NUDT15) variants tolerate only a fraction of the usual mercaptopurine dose, about 10% for TPMT.
- Ph+ ALL then vs now: it once meant allogeneic transplant in first remission. A BCR::ABL1 TKI (imatinib, dasatinib or ponatinib) is now added to therapy; in children, continuous imatinib plus intensive chemotherapy gave a 5-year disease-free survival of about 70%, at least as good as transplant, and ended routine transplant for good early responders. In adults, chemotherapy-free dasatinib plus a glucocorticoid, followed by blinatumomab, produced complete remission in 98% (GIMEMA D-ALBA), ponatinib has FDA accelerated approval with chemotherapy for newly diagnosed Ph+ ALL, and transplant is kept mainly for high-risk or resistant disease.
- Blinatumomab, a CD19-directed CD3 T-cell engager, is FDA-approved for MRD-positive B-ALL (MRD 0.1% or more), relapsed or refractory B-ALL, and consolidation of Ph-negative B-ALL in adults and children 1 month and older. In MRD-negative adults, adding it to consolidation raised 3-year survival from 68% to 85%. Watch for cytokine release syndrome and neurotoxicity.
- Relapse: inotuzumab ozogamicin (anti-CD22 antibody-drug conjugate; veno-occlusive disease), CD19 CAR T cells and allogeneic transplant.
Practice question
A 16-year-old boy has 2 weeks of cough, shortness of breath that worsens when he lies flat, and swelling of his face and neck. He also reports fatigue and easy bruising. He is pale, with petechiae, distended neck veins and cervical lymphadenopathy. CT of the chest shows a large anterior mediastinal mass. WBC count is 86,000/µL with 70% blasts, hemoglobin 8.6 g/dL and platelets 38,000/µL; uric acid and LDH are elevated. Flow cytometry of the circulating blasts is most likely to show which of the following?
A. TdT+, CD19+, CD10+, cytoplasmic CD3− B. TdT+, cytoplasmic CD3+, CD7+, CD19− C. Myeloperoxidase+, CD13+, CD33+ D. CD5+, CD19+, CD20+, CD23+ mature B cells E. TdT−, CD19+, surface immunoglobulin+, MYC rearranged
Answer: B. A teenage boy with an anterior mediastinal mass, SVC syndrome, a very high WBC and blasts has T-ALL; cytoplasmic CD3 defines T lineage, CD7 is typical, and TdT marks the cells as precursors.
- A: precursor B-ALL, the typical toddler with bone pain and pancytopenia; a mediastinal mass is not its pattern.
- C: AML; myeloperoxidase and Auer rods point to myeloid blasts.
- D: CLL; mature, TdT-negative cells in an older adult, not blasts in a teenager.
- E: Burkitt leukemia; mature B cells that are TdT-negative, carry surface immunoglobulin and need Burkitt-type treatment.
Next priorities: watch for airway compression from the mass, and start tumor lysis prevention before chemotherapy, because a high WBC and a bulky tumor mean rapid cell kill.
Key takeaways
- ALL is the most common childhood cancer (peak age 2-5): marrow failure plus bone pain, with lymphoblasts making up at least 20% of the marrow.
- TdT+ blasts; B-ALL is CD19+ and usually CD10+; T-ALL is cytoplasmic CD3+, CD7+.
- T-ALL: adolescent boy, high WBC, anterior mediastinal mass, SVC syndrome.
- Good in children: age 1 to under 10, WBC under 50,000/µL, high hyperdiploidy, t(12;21) ETV6::RUNX1, MRD-negative after induction.
- Bad: infant KMT2A (t(4;11)), hypodiploidy, Ph-like, CNS3, persistent MRD, older age; t(9;22) was the worst but now responds to TKIs, increasingly combined with blinatumomab.
- Treatment: multiphase chemotherapy for 2-3 years, intrathecal CNS prophylaxis, tumor lysis prevention, TPMT/NUDT15 testing before mercaptopurine.
- Burkitt leukemia is TdT-negative; Auer rods mean AML, never ALL.
Sources
- Childhood Acute Lymphoblastic Leukemia Treatment (PDQ), Health Professional Version — National Cancer Institute (2025)
- Acute Lymphoblastic Leukemia Treatment (PDQ), Health Professional Version — National Cancer Institute (2025)
- Acute Lymphoblastic Leukemia (ALL) — Merck Manual Professional Edition (2026)
- Acute Myeloid Leukemia (AML) — Merck Manual Professional Edition (2026)
- Management of Adverse Effects of Cancer Therapy (tumor lysis syndrome) — Merck Manual Professional Edition (2026)
- The 5th edition of the WHO Classification of Haematolymphoid Tumours: Lymphoid Neoplasms — Leukemia (2022)
- International Consensus Classification of acute lymphoblastic leukemia/lymphoma — Virchows Archiv (2023)
- Dasatinib-Blinatumomab for Ph-Positive Acute Lymphoblastic Leukemia in Adults (GIMEMA D-ALBA) — N Engl J Med, PubMed (2020)
- Blincyto (blinatumomab) prescribing information — DailyMed (2026)
- Iclusig (ponatinib) prescribing information — DailyMed (2025)
- Imatinib mesylate tablets prescribing information — DailyMed (2026)
- Sprycel (dasatinib) prescribing information — DailyMed (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
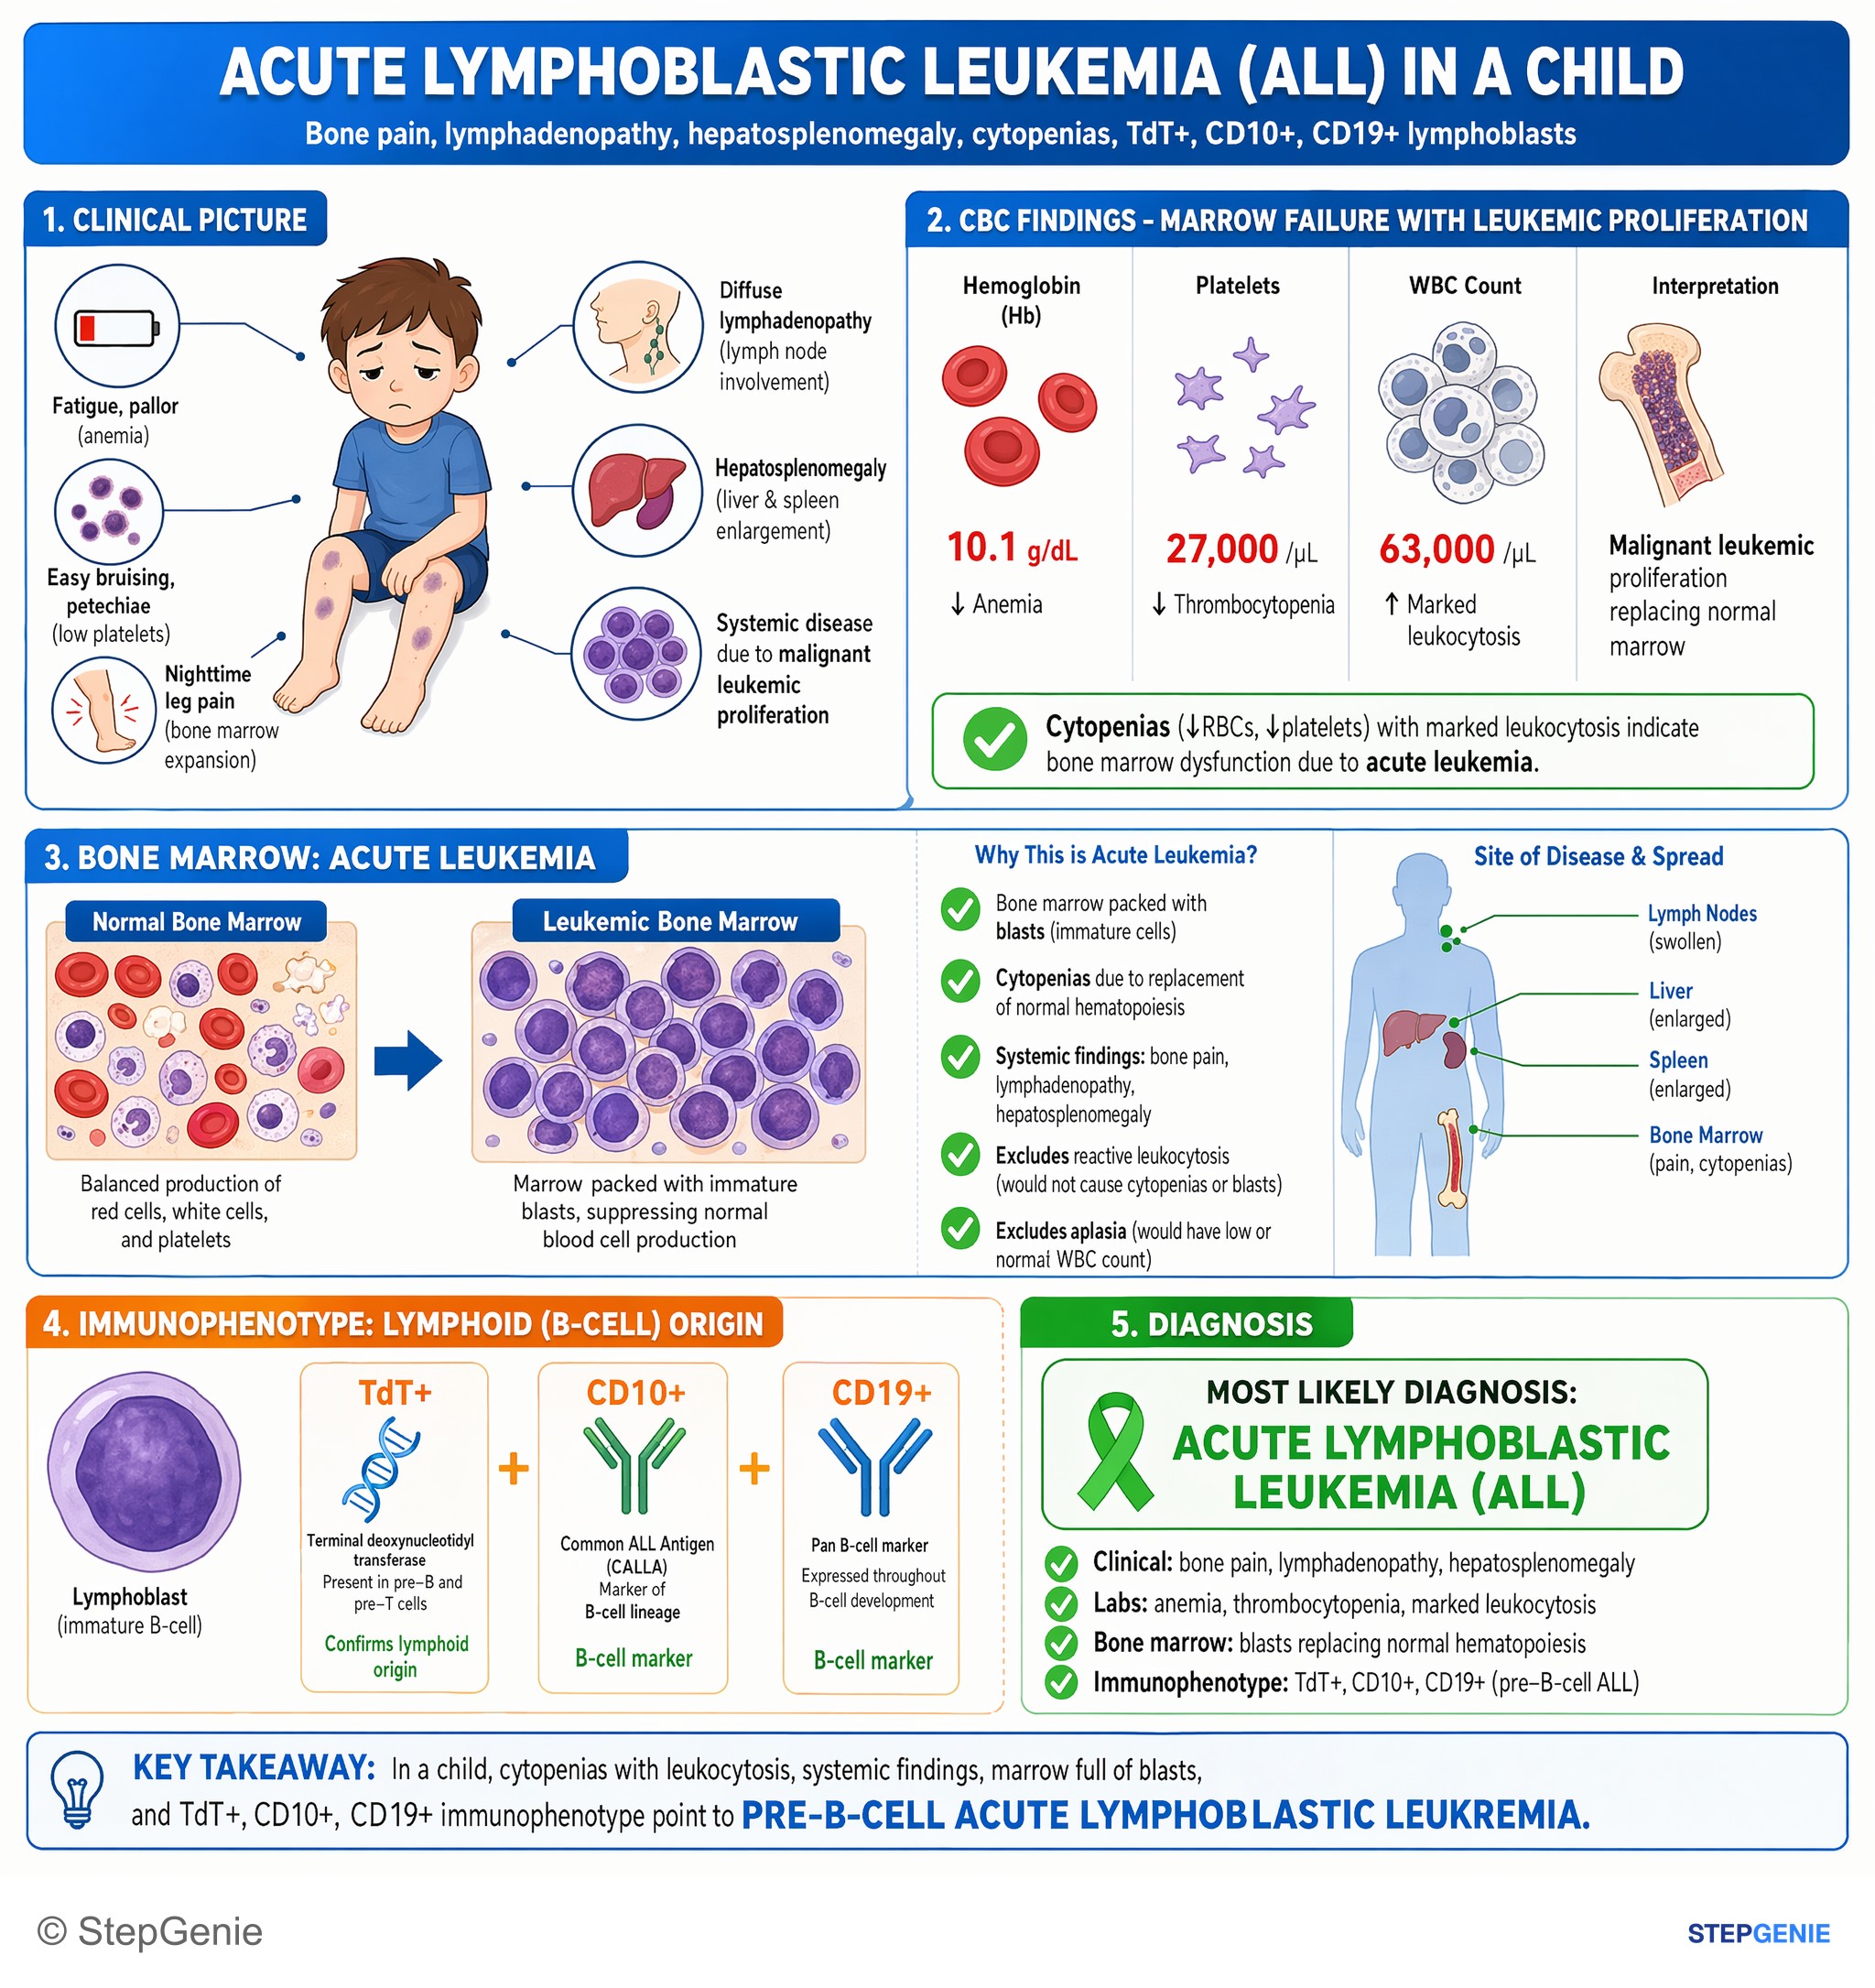
Acute lymphoblastic leukemia (ALL) in a child: bone pain, lymphadenopathy, hepatosplenomegaly, cytopenias, TdT+, CD10+, CD19+ lymphoblasts.
USMLE Step 2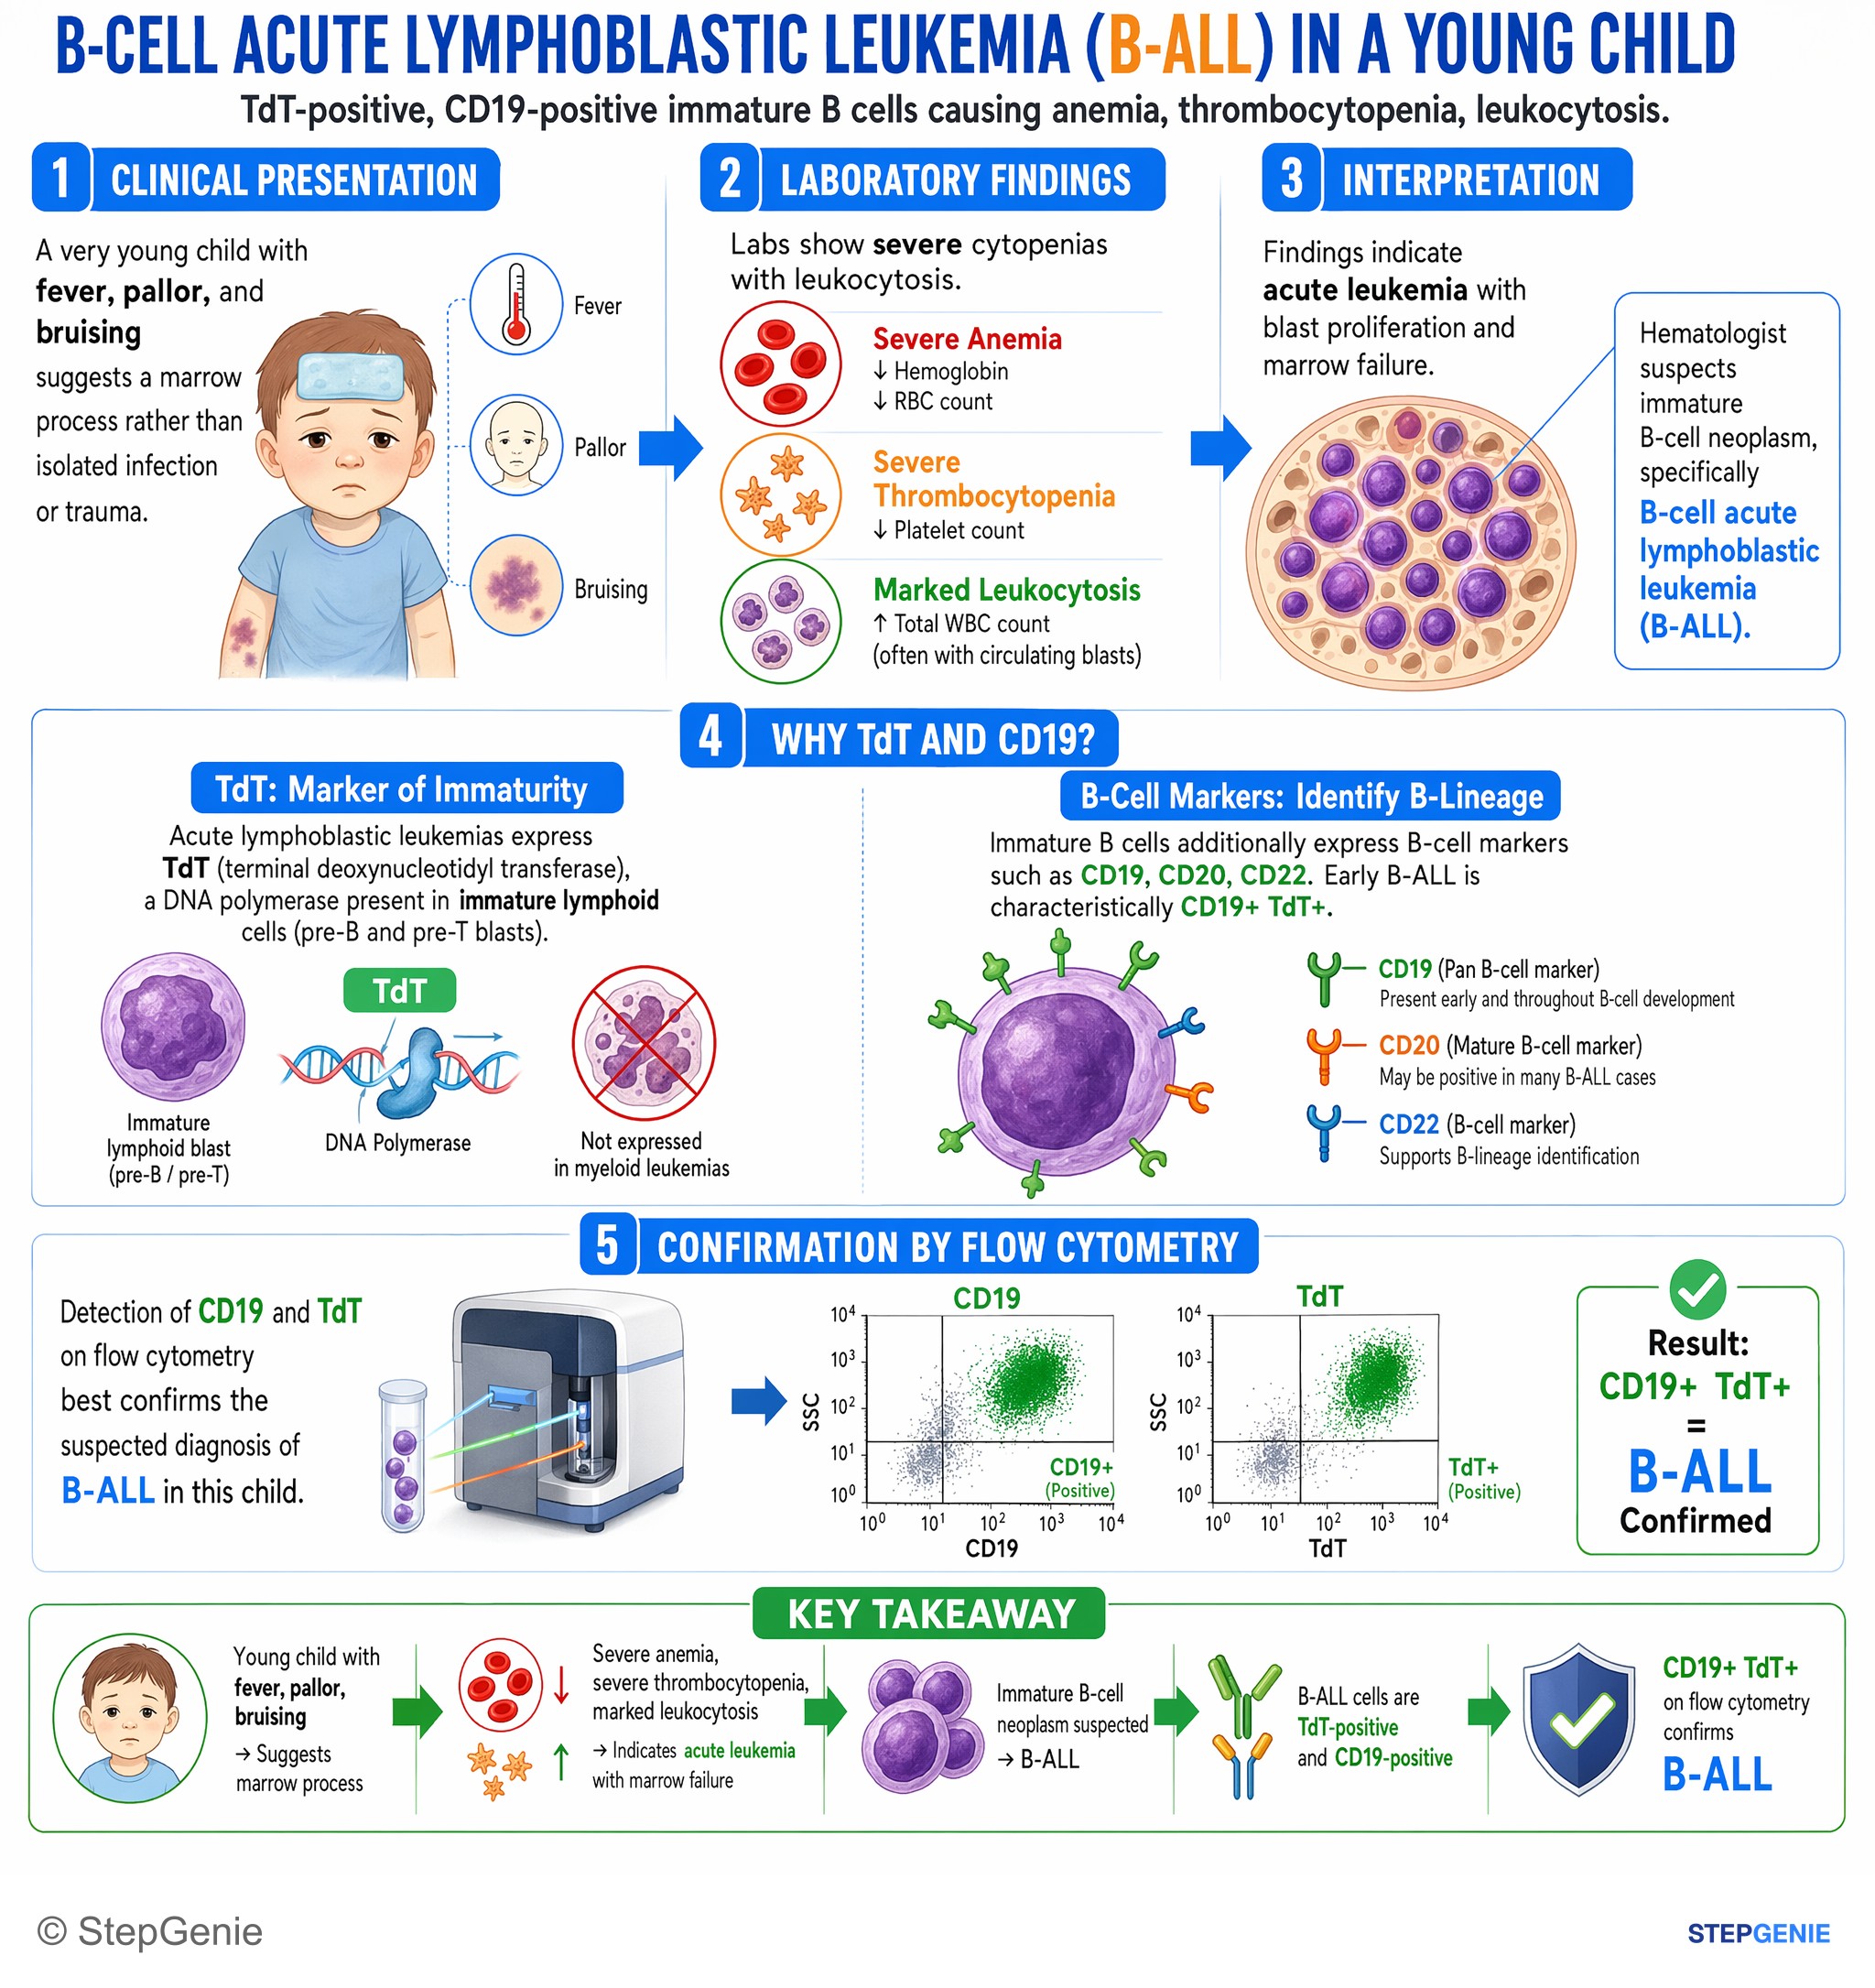
B-cell acute lymphoblastic leukemia (ALL) in a young child shows TdT-positive, CD19-positive immature B cells causing anemia…
USMLE Step 1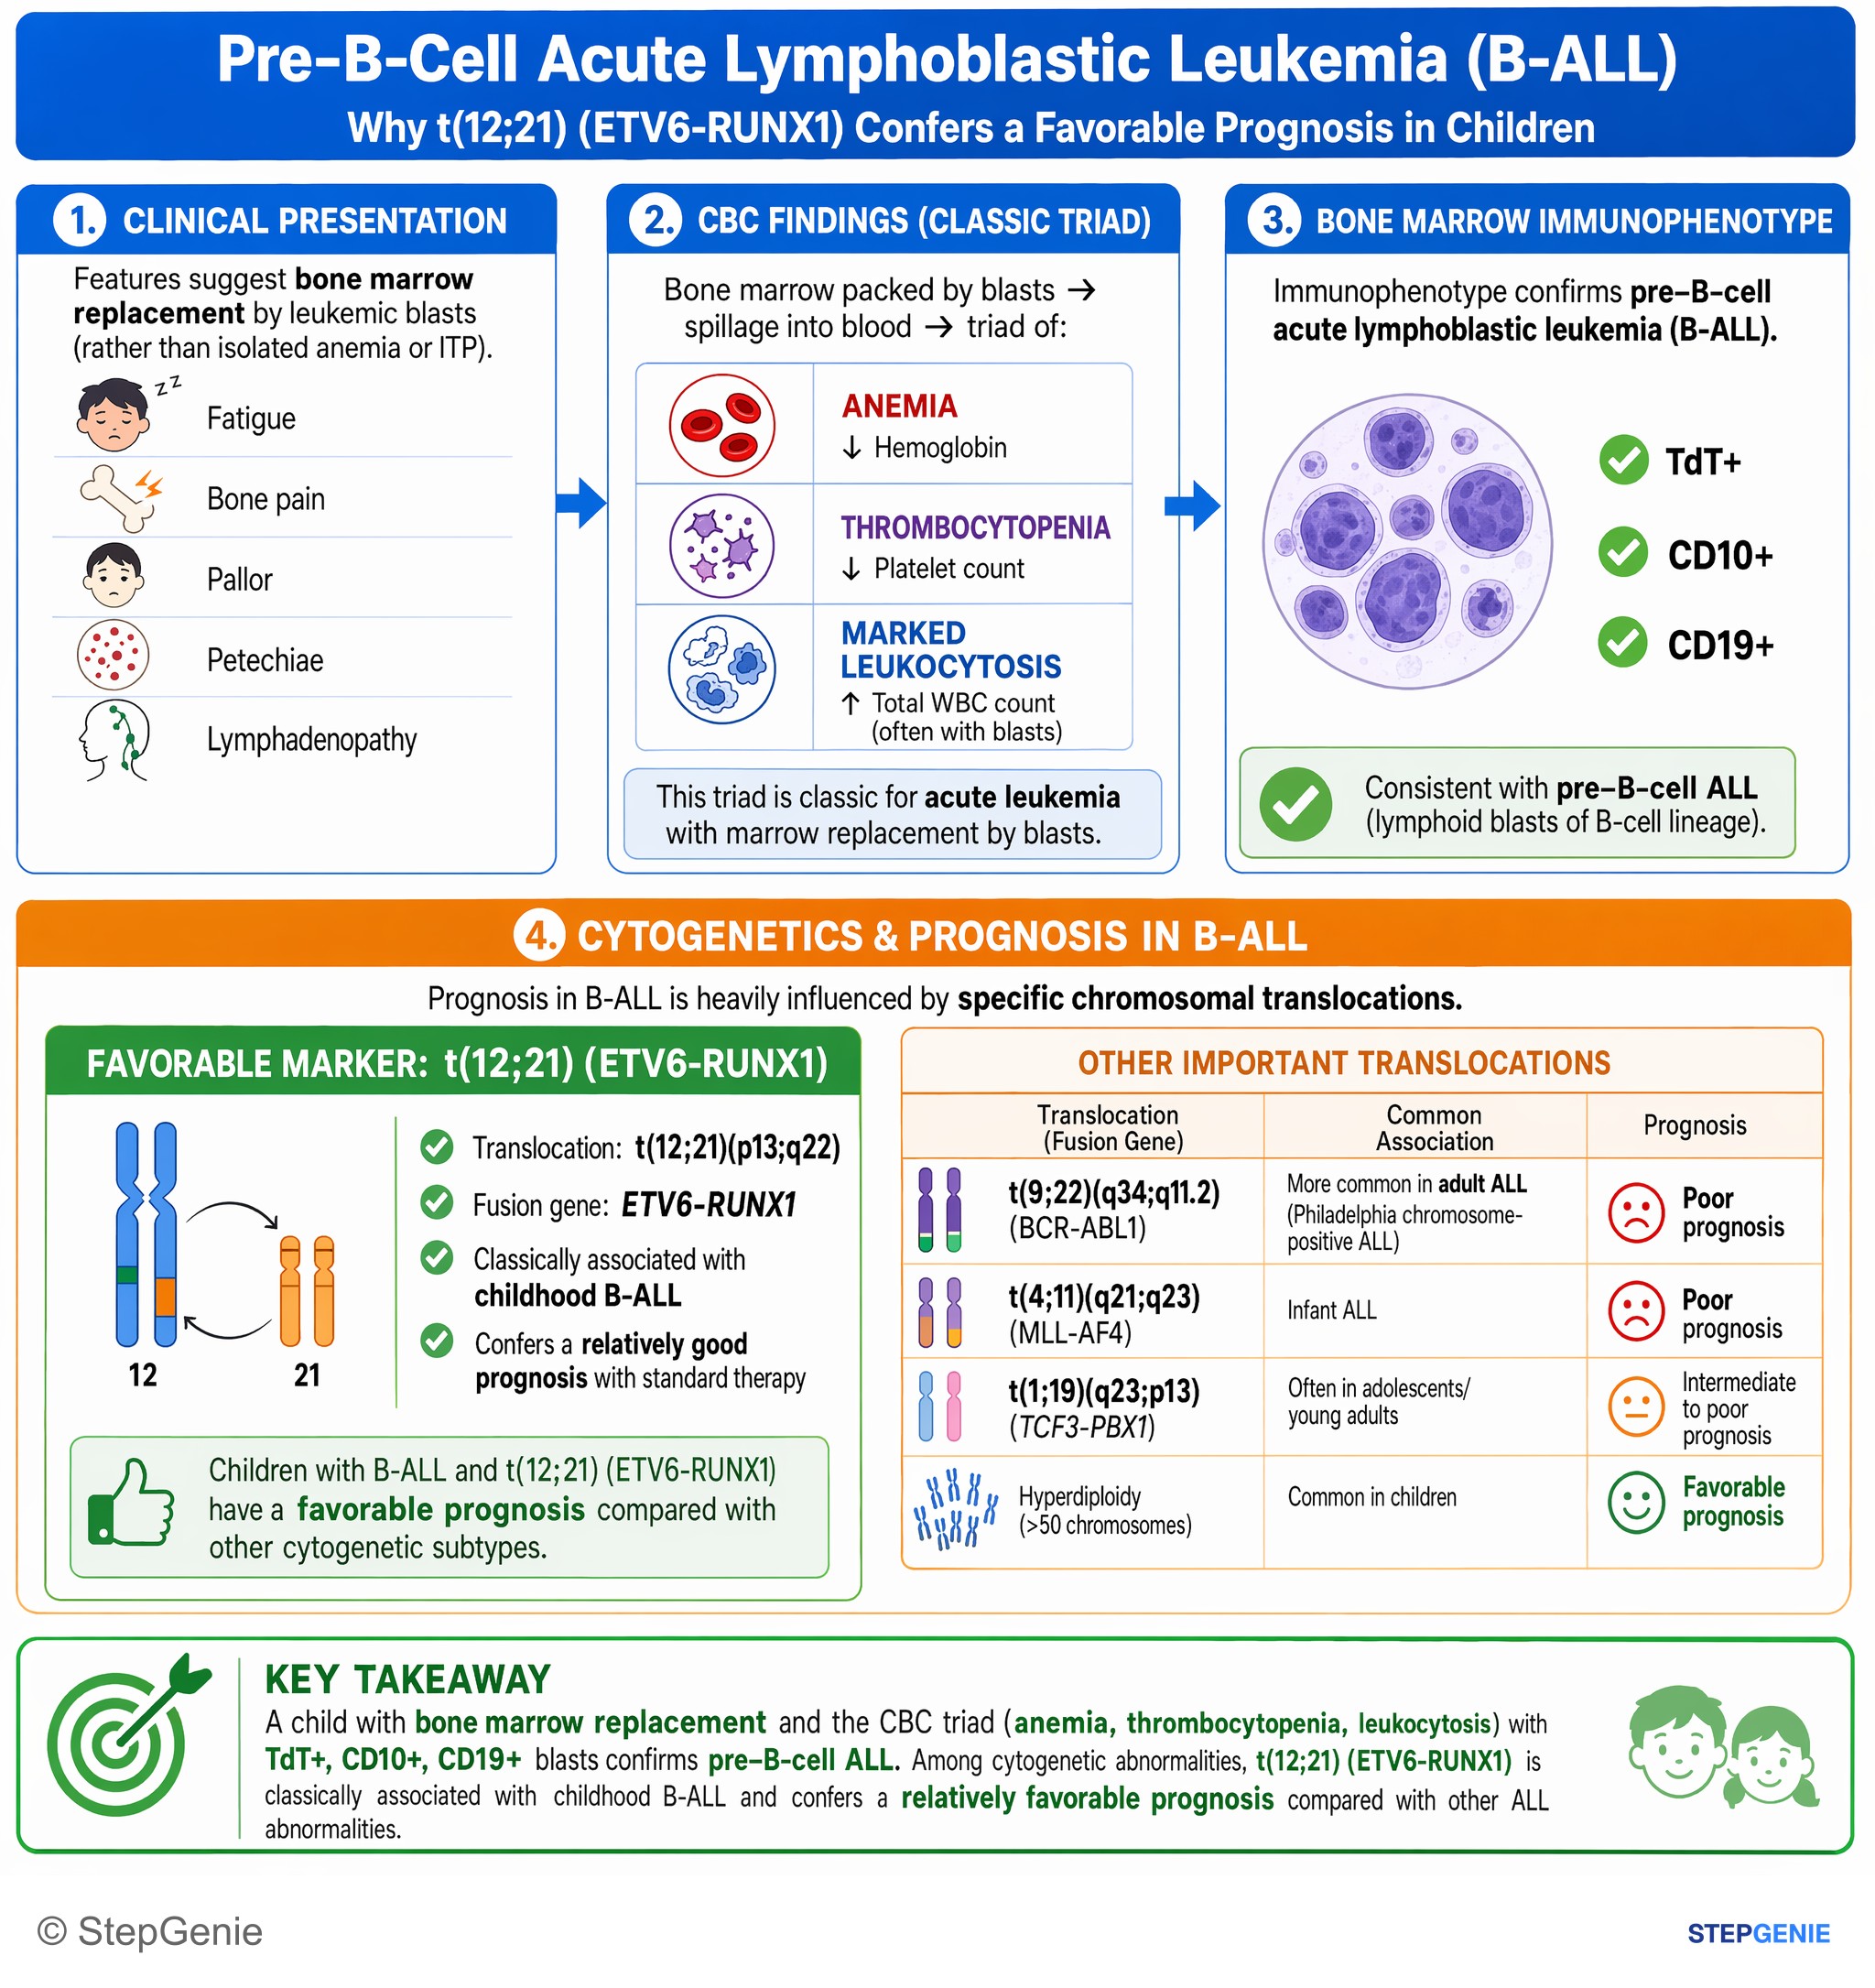
B-cell ALL in children with t(12;21) (ETV6-RUNX1) has a relatively favorable prognosis compared with other ALL cytogenetic abnormalities.
USMLE Step 1Frequently Asked Questions
What is the difference between B-ALL and T-ALL?
Both are cancers of TdT-positive lymphoblasts. B-ALL makes up 80 to 85% of childhood ALL, typically affects young children (peak age 2 to 5) and expresses CD19 with CD22 or CD79a, plus CD10 in about 90% of cases. T-ALL is defined by cytoplasmic CD3 with CD7 plus CD2 or CD5, and it is associated with male sex, older age, a high white cell count and an anterior mediastinal mass that can cause superior vena cava syndrome.
Which genetic findings in ALL are good or bad?
In children, high hyperdiploidy (51 to 65 chromosomes) and the t(12;21) ETV6::RUNX1 fusion are favorable. Unfavorable findings include KMT2A rearrangements such as t(4;11), which are common in infants, hypodiploidy (fewer than 44 chromosomes), BCR::ABL1-like (Ph-like) ALL, and iAMP21 when it is treated with standard therapy. The t(9;22) BCR::ABL1 Philadelphia chromosome was historically the worst lesion, but tyrosine kinase inhibitors have greatly improved outcomes. Persistent measurable residual disease after induction is the strongest adverse predictor.
Why is the prognosis of ALL worse in adults than in children?
About 95% or more of children reach complete remission and roughly 90% of those younger than 15 survive 5 years, while 70 to 90% of adults reach remission and fewer are cured. Adults more often have high-risk genetics, especially the Philadelphia chromosome, which is found in about a quarter of adult cases but in only 2 to 5% of children. Adults also have more comorbidities and tolerate intensive chemotherapy less well.
How is Philadelphia chromosome-positive ALL treated now?
A BCR::ABL1 tyrosine kinase inhibitor such as imatinib, dasatinib or ponatinib is added to treatment. In children, imatinib with intensive chemotherapy made routine stem cell transplant in first remission unnecessary for patients with a good early response. In adults, a chemotherapy-free regimen of dasatinib plus a glucocorticoid, followed by blinatumomab, produced complete remission in about 98% of patients, and allogeneic transplant is now kept mainly for high-risk or resistant disease.
What is TdT and is it specific for ALL?
Terminal deoxynucleotidyl transferase (TdT) is an enzyme of immature lymphoid cells, and it is elevated in about 95% of ALL, in both B and T types. It is not lineage-specific, because about 20% of AML cases also express it. Lineage is assigned with other markers, such as CD19, CD22 and CD79a for B cells, cytoplasmic CD3 for T cells and myeloperoxidase for myeloid cells. Burkitt leukemia, a mature B-cell cancer, is TdT-negative.
Why do patients with ALL get intrathecal chemotherapy?
Lymphoblasts often infiltrate the meninges and cerebrospinal fluid, and the central nervous system, like the testes, is a sanctuary site. Every ALL regimen therefore includes CNS prophylaxis from induction onward, usually intrathecal methotrexate, sometimes combined with cytarabine and hydrocortisone, and high-dose systemic methotrexate or cytarabine adds CNS coverage. Cranial irradiation, once common, is now used much less. Children with CNS3 disease at diagnosis have a higher risk of treatment failure.