Chronic lymphocytic leukemia (CLL) is a cancer of small, mature-looking but dysfunctional B cells that build up in the blood, bone marrow, lymph nodes and spleen. It is the most common leukemia in Western countries, with a median age at diagnosis of about 70. The diagnosis needs at least 5 × 10⁹/L (5,000/µL) clonal B cells in the blood for at least 3 months, with the classic flow cytometry profile CD5+, CD19+, CD20 dim, CD23+ and a single light chain; the smear shows smudge cells. The complications to know are warm autoimmune hemolytic anemia (AIHA), immune thrombocytopenia (ITP), hypogammaglobulinemia with infections, and Richter transformation to an aggressive lymphoma. Patients without symptoms or other iwCLL triggers are watched rather than treated, and treatment, when needed, is now targeted: BTK inhibitors or the BCL-2 inhibitor venetoclax.
Draw it out: the 6-panel CLL sketch
Six panels, left to right on scratch paper; each is a testable fact.
- The smear. A circle packed with small round lymphocytes (dense chromatin, thin rim of cytoplasm) plus two or three squashed blobs: smudge cells (Gumprecht nuclear shadows), fragile CLL cells that rupture when the slide is made.
- The flow badge. Write CD19, CD20 (dim), CD5, CD23, κ or λ (never both). CD5 is normally a T-cell antigen, so a B cell wearing CD5 is the tell, and a single light chain proves the cells are one clone. Surface immunoglobulin and CD79b are dim too.
- The 5,000 line. Draw a horizontal line labeled 5 × 10⁹/L clonal B cells for ≥3 months. Above it: CLL. Below it: monoclonal B lymphocytosis (MBL) if there are no enlarged nodes, organomegaly, cytopenias or symptoms, or small lymphocytic lymphoma (SLL) if nodes are enlarged.
- The Rai staircase. Five steps: 0 blood → I nodes → II spleen or liver → III anemia (Hb <11 g/dL) → IV platelets <100,000/µL. Write Binet A, B, C beside it.
- The complication ring. Around the cell, draw a cracked red cell (warm AIHA, Coombs positive), a few scattered dots (ITP), an empty "Y" antibody (hypogammaglobulinemia and infections) and a lightning bolt to a big ugly cell (Richter transformation, usually to DLBCL).
- The fork. No trigger → watch and wait. iwCLL trigger → treat with a BTK inhibitor or a fixed-duration venetoclax combination.
Diagnosis: CLL vs MBL vs SLL
| MBL | CLL | SLL | |
|---|---|---|---|
| Clonal B cells in blood | <5 × 10⁹/L | ≥5 × 10⁹/L for ≥3 months | <5 × 10⁹/L |
| Nodes, spleen, liver | None | Variable | Lymphadenopathy defines it |
| Cytopenias or symptoms | None | Variable | No cytopenias from marrow infiltration |
| Meaning | Precursor state; about 1-2% per year progress to CLL | The leukemia | Same disease, centered in nodes |
- CLL and SLL are one disease made of the same CD5+/CD23+ cells; the name depends on where the cells sit.
- Peripheral blood flow cytometry confirms clonality. A bone marrow biopsy is not required to diagnose CLL.
- Prognostic markers: unmutated IGHV and del(17p) or TP53 mutation predict a more aggressive course (del(17p)/TP53 is the worst); del(13q) as the sole abnormality is favorable; del(11q) and trisomy 12 are less favorable.
Staging: Rai and Binet
| Rai stage | Findings | Risk group |
|---|---|---|
| 0 | Lymphocytosis only | Low |
| I | Lymphocytosis + enlarged lymph nodes | Intermediate |
| II | + splenomegaly and/or hepatomegaly | Intermediate |
| III | + anemia, hemoglobin <11 g/dL | High |
| IV | + thrombocytopenia, platelets <100,000/µL | High |
Binet counts five lymphoid areas (cervical, axillary and inguinal nodes, liver, spleen):
- A: fewer than 3 areas enlarged, hemoglobin ≥10 g/dL and platelets ≥100,000/µL
- B: 3 or more areas enlarged, same blood counts
- C: hemoglobin <10 g/dL and/or platelets <100,000/µL, however many areas are involved
Watch the numbers: Rai III uses Hb <11 g/dL; Binet C and the iwCLL treatment trigger use <10 g/dL. All three use platelets <100,000/µL.
Only cytopenias caused by marrow infiltration should upstage CLL; immune cytopenias (AIHA, ITP) are complications with their own treatment.
Complications
- Warm AIHA: IgG-coated red cells are cleared in the spleen, giving anemia with spherocytes, high LDH and indirect bilirubin, low haptoglobin and a positive direct antiglobulin (Coombs) test. Corticosteroids come first; AIHA or ITP that responds poorly to steroids is itself an iwCLL reason to treat the CLL. More in the autoimmune hemolytic anemia guide.
- ITP, and rarely pure red cell aplasia: cytopenias caused by immune destruction or suppression rather than marrow crowding.
- Hypogammaglobulinemia develops in up to two-thirds of patients. It brings recurrent infections with Streptococcus pneumoniae, Haemophilus influenzae, Staphylococcus and herpesviruses. Consider immunoglobulin infusions for refractory infections or after 2 or more severe infections within 6 months.
- Richter transformation (2-10%): CLL turns into an aggressive lymphoma, usually diffuse large B-cell lymphoma (DLBCL) and rarely Hodgkin lymphoma. Suspect it when a previously stable patient develops rapidly enlarging nodes, fever or other B symptoms, or a sharply rising LDH; a biopsy confirms it. DLBCL that is clonally related to the CLL (60-70% of cases) does worse than de novo DLBCL. See the non-Hodgkin lymphoma breakdown.
When to treat: the iwCLL triggers
Asymptomatic early-stage CLL (Rai 0, Binet A) is monitored, because treating early-stage disease has not improved survival in controlled trials. Therapy starts only for active disease, meaning at least one of:
- Progressive marrow failure: new or worsening anemia or thrombocytopenia. iwCLL 2018 regards hemoglobin <10 g/dL or platelets <100,000/µL as the usual cutoffs, but a platelet count that stays stable below 100,000/µL does not automatically require treatment
- Massive (≥6 cm below the left costal margin), progressive or symptomatic splenomegaly
- Massive (≥10 cm in longest diameter), progressive or symptomatic lymphadenopathy
- Progressive lymphocytosis: a rise of ≥50% over 2 months, or a doubling time under 6 months
- Autoimmune anemia or thrombocytopenia that responds poorly to corticosteroids
- Symptomatic or functional extranodal disease (skin, kidney, lung, spine)
- Disease-related symptoms: weight loss ≥10% in 6 months, significant fatigue (ECOG 2 or worse), fever ≥38.0°C for 2 or more weeks, or night sweats for 1 month or more, without infection
Not triggers on their own: the absolute lymphocyte count, hypogammaglobulinemia, or a monoclonal or oligoclonal paraprotein.
Treatment in 2026: the drug classes
| Class | Drugs | Mechanism | Must-know points |
|---|---|---|---|
| Covalent BTK inhibitors | Ibrutinib, acalabrutinib, zanubrutinib | Bind BTK covalently (at C481) and block B-cell receptor signaling | Usually taken continuously until progression; atrial fibrillation, bleeding, hypertension and infections (fewer cardiac events with acalabrutinib and zanubrutinib than with ibrutinib) |
| Noncovalent BTK inhibitor | Pirtobrutinib | Binds BTK reversibly, including BTK with C481 mutations | Traditional FDA approval (December 2025) for relapsed or refractory CLL/SLL previously treated with a covalent BTK inhibitor |
| BCL-2 inhibitor | Venetoclax | Blocks the antiapoptotic protein BCL-2, so CLL cells die by apoptosis | Fixed duration: with obinutuzumab (ends after cycle 12), with acalabrutinib (FDA approved February 2026 for previously untreated CLL, based on the AMPLIFY trial; ends after cycle 14) or with rituximab (24 months). Risk of tumor lysis syndrome, so the dose is ramped up over 5 weeks |
| Anti-CD20 antibodies | Obinutuzumab, rituximab | Antibody-mediated killing of CD20+ B cells | Partners for venetoclax or a BTK inhibitor |
| Chemoimmunotherapy | FCR (fludarabine, cyclophosphamide, rituximab), bendamustine-rituximab | DNA damage plus anti-CD20 | Largely replaced by targeted therapy for most patients |
| Later-line options | Idelalisib (PI3K-delta inhibitor); lisocabtagene maraleucel (anti-CD19 CAR T cells) | For relapsed disease |
How each exam uses this: Step 1 asks the mechanism; BTK is the same enzyme that is mutated in X-linked (Bruton) agammaglobulinemia. Step 2 CK and Step 3 ask about timing and toxicity: new atrial fibrillation or bleeding on a BTK inhibitor, and tumor lysis (high potassium, phosphate and uric acid, low calcium) when venetoclax starts.
CLL vs mantle cell vs hairy cell
| Feature | CLL/SLL | Mantle cell lymphoma | Hairy cell leukemia |
|---|---|---|---|
| Typical patient | Older adult (median age 70), more men | Man aged 60-70 (3:1 male) | Adult with splenomegaly |
| Blood and marrow | Lymphocytosis with smudge cells | Nodes plus frequent spleen, marrow and GI involvement | Pancytopenia with monocytopenia; cells with hair-like projections; fibrotic marrow that is hard to aspirate ("dry tap") |
| Immunophenotype | CD5+, CD23+, dim CD20 and surface Ig | CD5+, CD23−, cyclin D1+, SOX11+ | CD11c+, CD25+, CD103+, very bright CD20 |
| Genetics | del(13q), trisomy 12, del(11q), del(17p)/TP53 | t(11;14) → cyclin D1 (CCND1) overexpression | BRAF V600E (disease-defining) |
| Treatment idea | Watch, or BTK inhibitor or venetoclax regimens | Chemoimmunotherapy with or without a BTK inhibitor; BTK inhibitors or CAR T cells at relapse | Cladribine with or without rituximab |
How USMLE tests CLL
- Older adult + incidental lymphocytosis + smudge cells = CLL until proven otherwise.
- CD5+ B cells: CD23+ means CLL; CD23− with cyclin D1 and t(11;14) means mantle cell lymphoma.
- Anemia in a CLL patient: check the reticulocyte count and Coombs test. Hemolysis with a positive DAT is warm AIHA, which is managed differently from marrow failure.
- Recurrent sinopulmonary infections with encapsulated bacteria in untreated CLL point to hypogammaglobulinemia.
- Sudden nodal growth and B symptoms in known CLL = Richter transformation; get a biopsy.
Practice question
A 72-year-old man is referred because a routine blood count showed a high white cell count. He feels well and is fully active. He has small (1-2 cm), painless cervical and axillary lymph nodes and no hepatosplenomegaly. WBC count is 34,000/µL with 80% lymphocytes, hemoglobin is 12.6 g/dL and platelets are 210,000/µL. The smear shows many small, mature-appearing lymphocytes and smudge cells. Flow cytometry shows a kappa-restricted B-cell population that is CD5+ and CD23+. Which is the most likely diagnosis?
A. Chronic lymphocytic leukemia B. Mantle cell lymphoma C. Hairy cell leukemia D. Chronic myeloid leukemia E. Infectious mononucleosis
Answer: A. An absolute lymphocytosis (about 27,000/µL) from a kappa-restricted CD5+/CD23+ B-cell clone, plus smudge cells, in an older adult is CLL.
- B: mantle cell lymphoma is also CD5+, but it is CD23-negative and cyclin D1-positive because of t(11;14).
- C: hairy cell leukemia causes pancytopenia with monocytopenia, splenomegaly and a dry tap, and its cells are CD11c+, CD25+ and CD103+ with BRAF V600E, not a CD5+ lymphocytosis.
- D: CML is a myeloproliferative neoplasm with neutrophilia, a left shift, basophilia and BCR::ABL1 from t(9;22); see the CML guide.
- E: mononucleosis affects teens and young adults with fever, pharyngitis and atypical reactive lymphocytes, and the lymphocytosis is polyclonal, not light-chain restricted.
What next? He is Rai stage I (nodes only; hemoglobin above 11 g/dL, platelets above 100,000/µL) and Binet A (two node areas), with no symptoms and no other iwCLL trigger, so the right plan is observation with periodic blood counts, not chemotherapy or a BTK inhibitor.
Key takeaways
- CLL = ≥5 × 10⁹/L clonal CD5+/CD23+ B cells for ≥3 months, with smudge cells on the smear.
- Below that count: MBL (no nodes; 1-2% per year progress) or SLL (nodes; same disease).
- Rai 0-IV: blood, nodes, spleen or liver, Hb <11 g/dL, platelets <100,000/µL. Binet A-C counts lymphoid areas.
- Complications: warm AIHA (DAT+), ITP, hypogammaglobulinemia with infections, Richter transformation to DLBCL (2-10%).
- Treat only active disease by iwCLL criteria; the lymphocyte count alone is not a trigger.
- 2026 therapy: continuous BTK inhibitors, or fixed-duration venetoclax with obinutuzumab or acalabrutinib; pirtobrutinib after a covalent BTK inhibitor; chemoimmunotherapy is largely replaced.
- CD5+ CD23− with cyclin D1 = mantle cell; CD11c/CD25/CD103 with BRAF V600E = hairy cell.
Sources
- Chronic Lymphocytic Leukemia Treatment (PDQ®)–Health Professional Version — National Cancer Institute (2025)
- Chronic Lymphocytic Leukemia (CLL) — Merck Manual Professional Edition (2026)
- Chronic Lymphocytic Leukemia: 2025 Update on the Epidemiology, Pathogenesis, Diagnosis, and Therapy — American Journal of Hematology (2025)
- iwCLL guidelines for diagnosis, indications for treatment, response assessment, and supportive management of CLL — Blood (2018)
- Chronic Lymphocytic Leukemia — StatPearls, NCBI Bookshelf (2023)
- CALQUENCE (acalabrutinib) prescribing information — DailyMed (2026)
- JAYPIRCA (pirtobrutinib) prescribing information — DailyMed (2025)
- VENCLEXTA (venetoclax) prescribing information — DailyMed (2026)
- FDA approves acalabrutinib with venetoclax for chronic lymphocytic leukemia or small lymphocytic lymphoma — U.S. Food and Drug Administration (2026)
- Hairy Cell Leukemia Treatment (PDQ®)–Health Professional Version — National Cancer Institute (2025)
- Mantle Cell Lymphoma — StatPearls, NCBI Bookshelf (2023)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
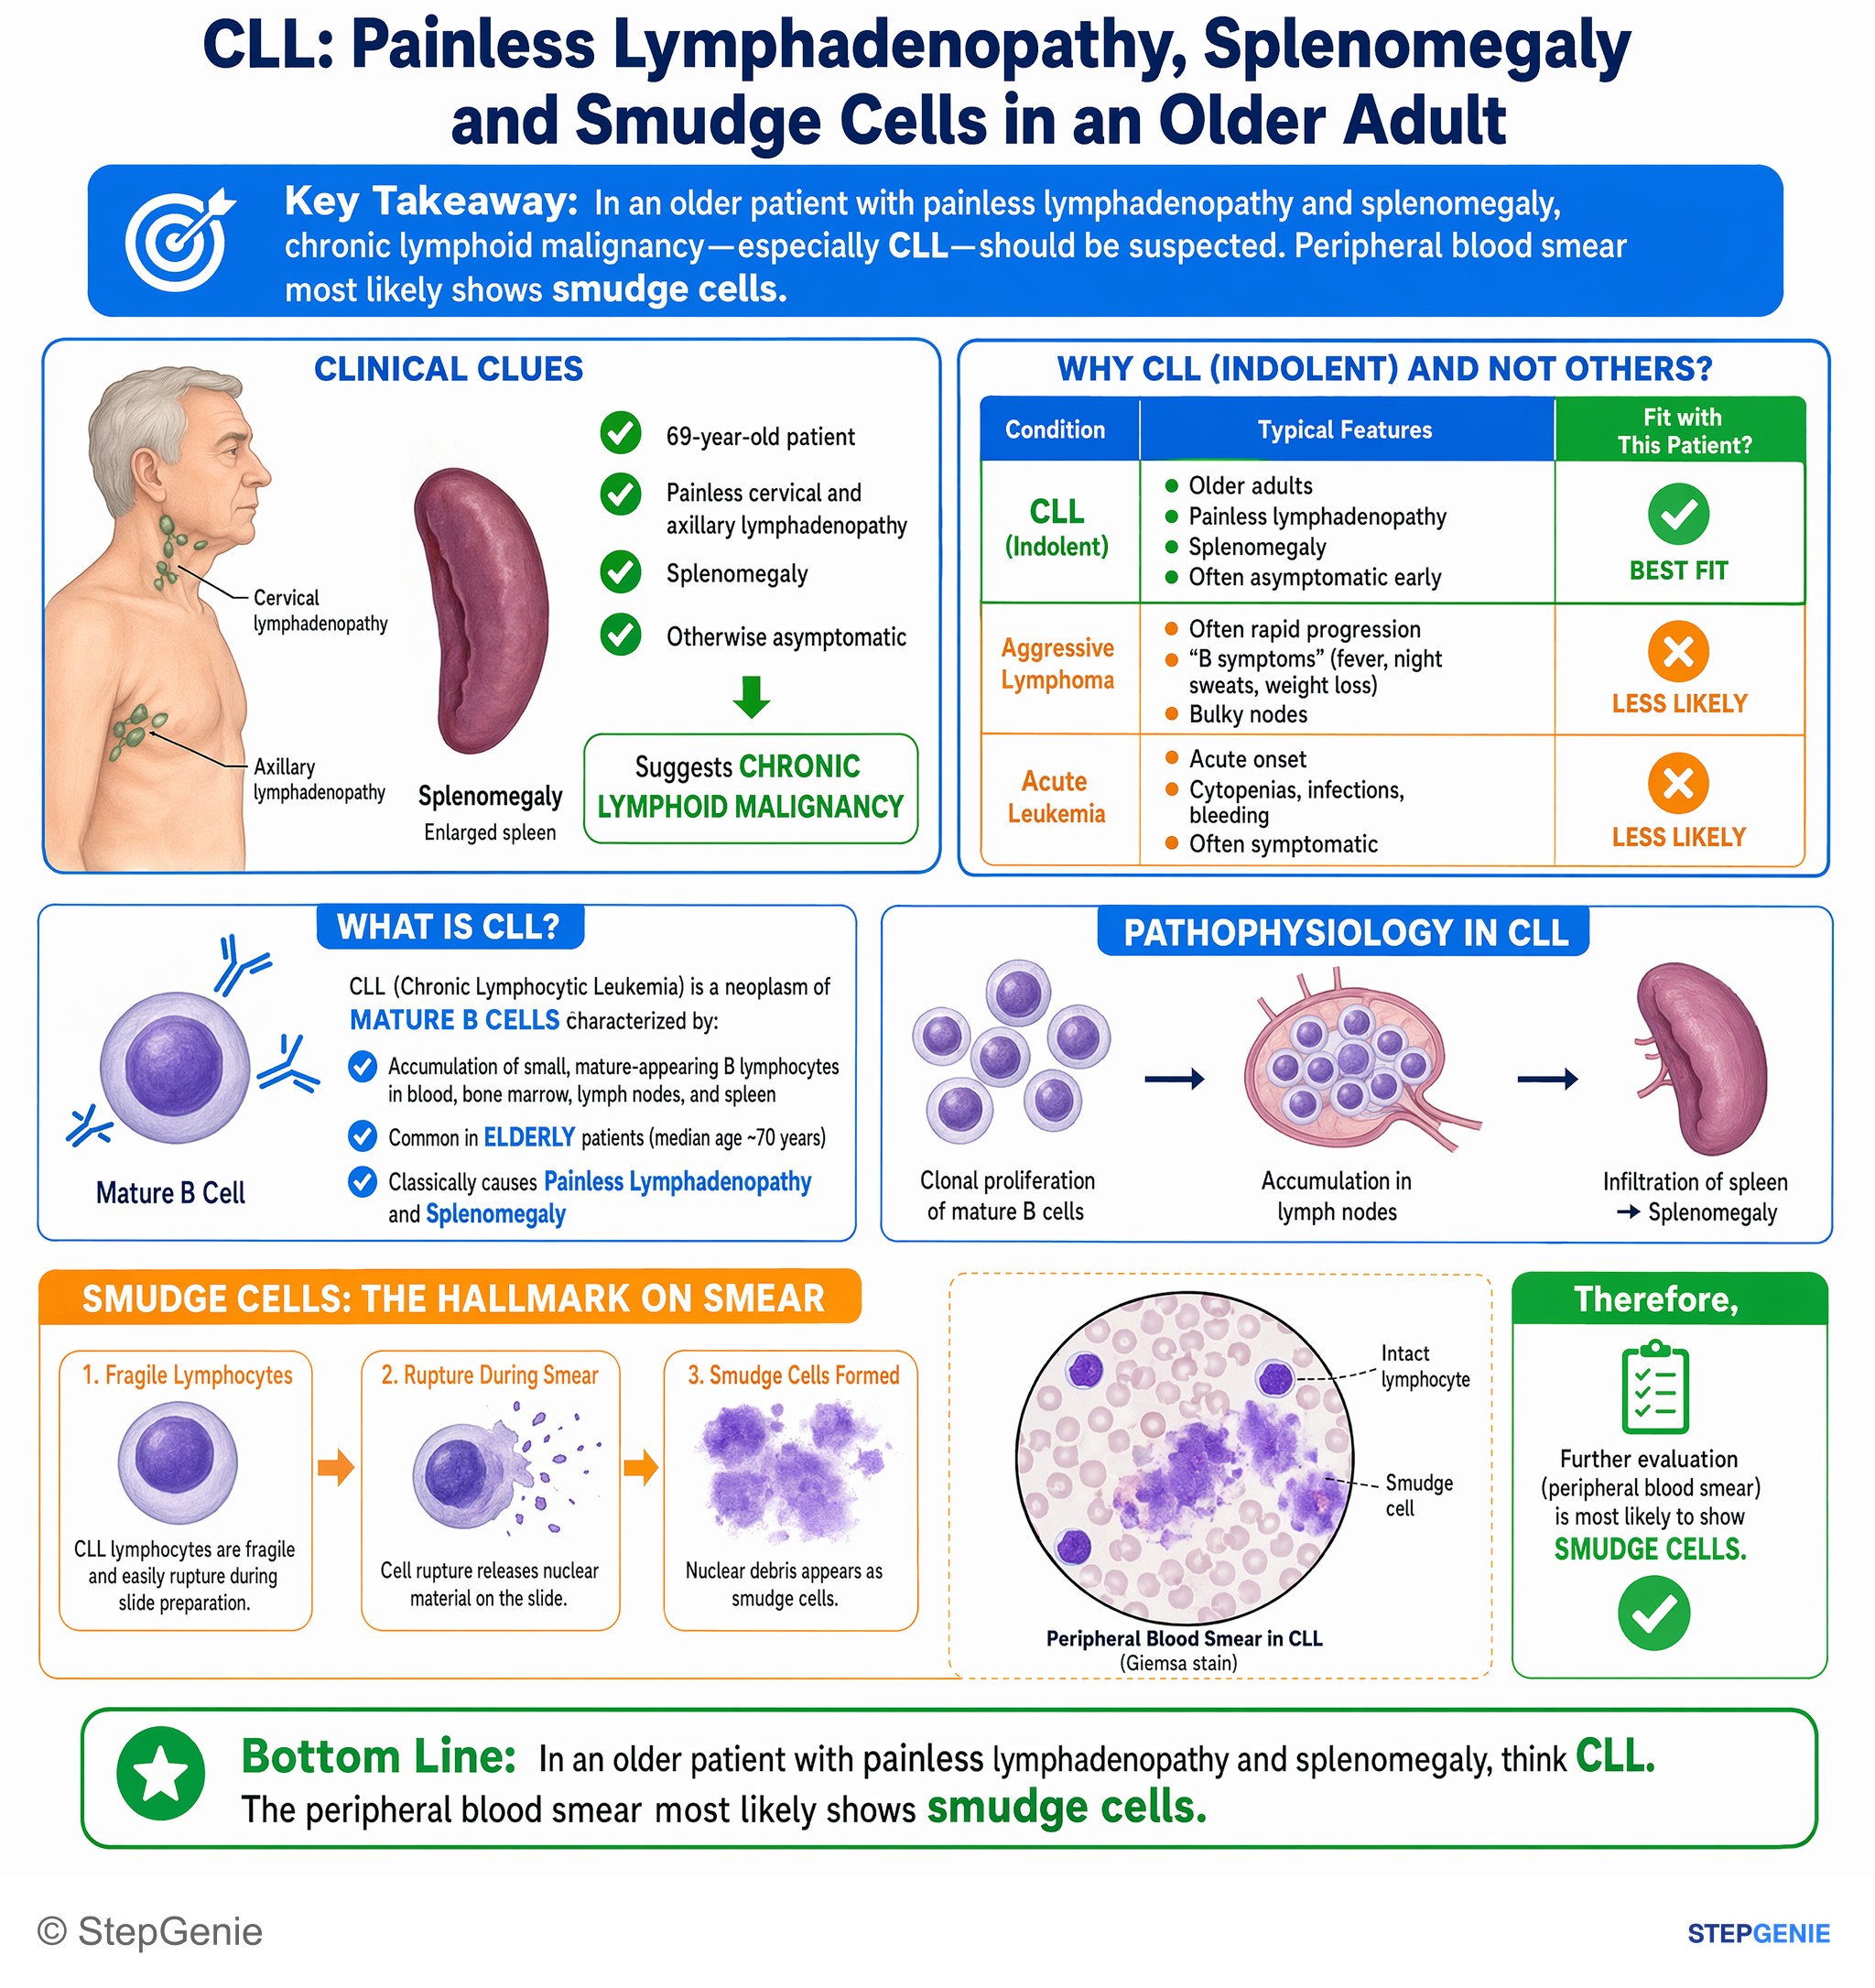
Chronic lymphocytic leukemia (CLL) causes painless lymphadenopathy and splenomegaly in older adults; smear shows fragile lymphocytes…
USMLE Step 1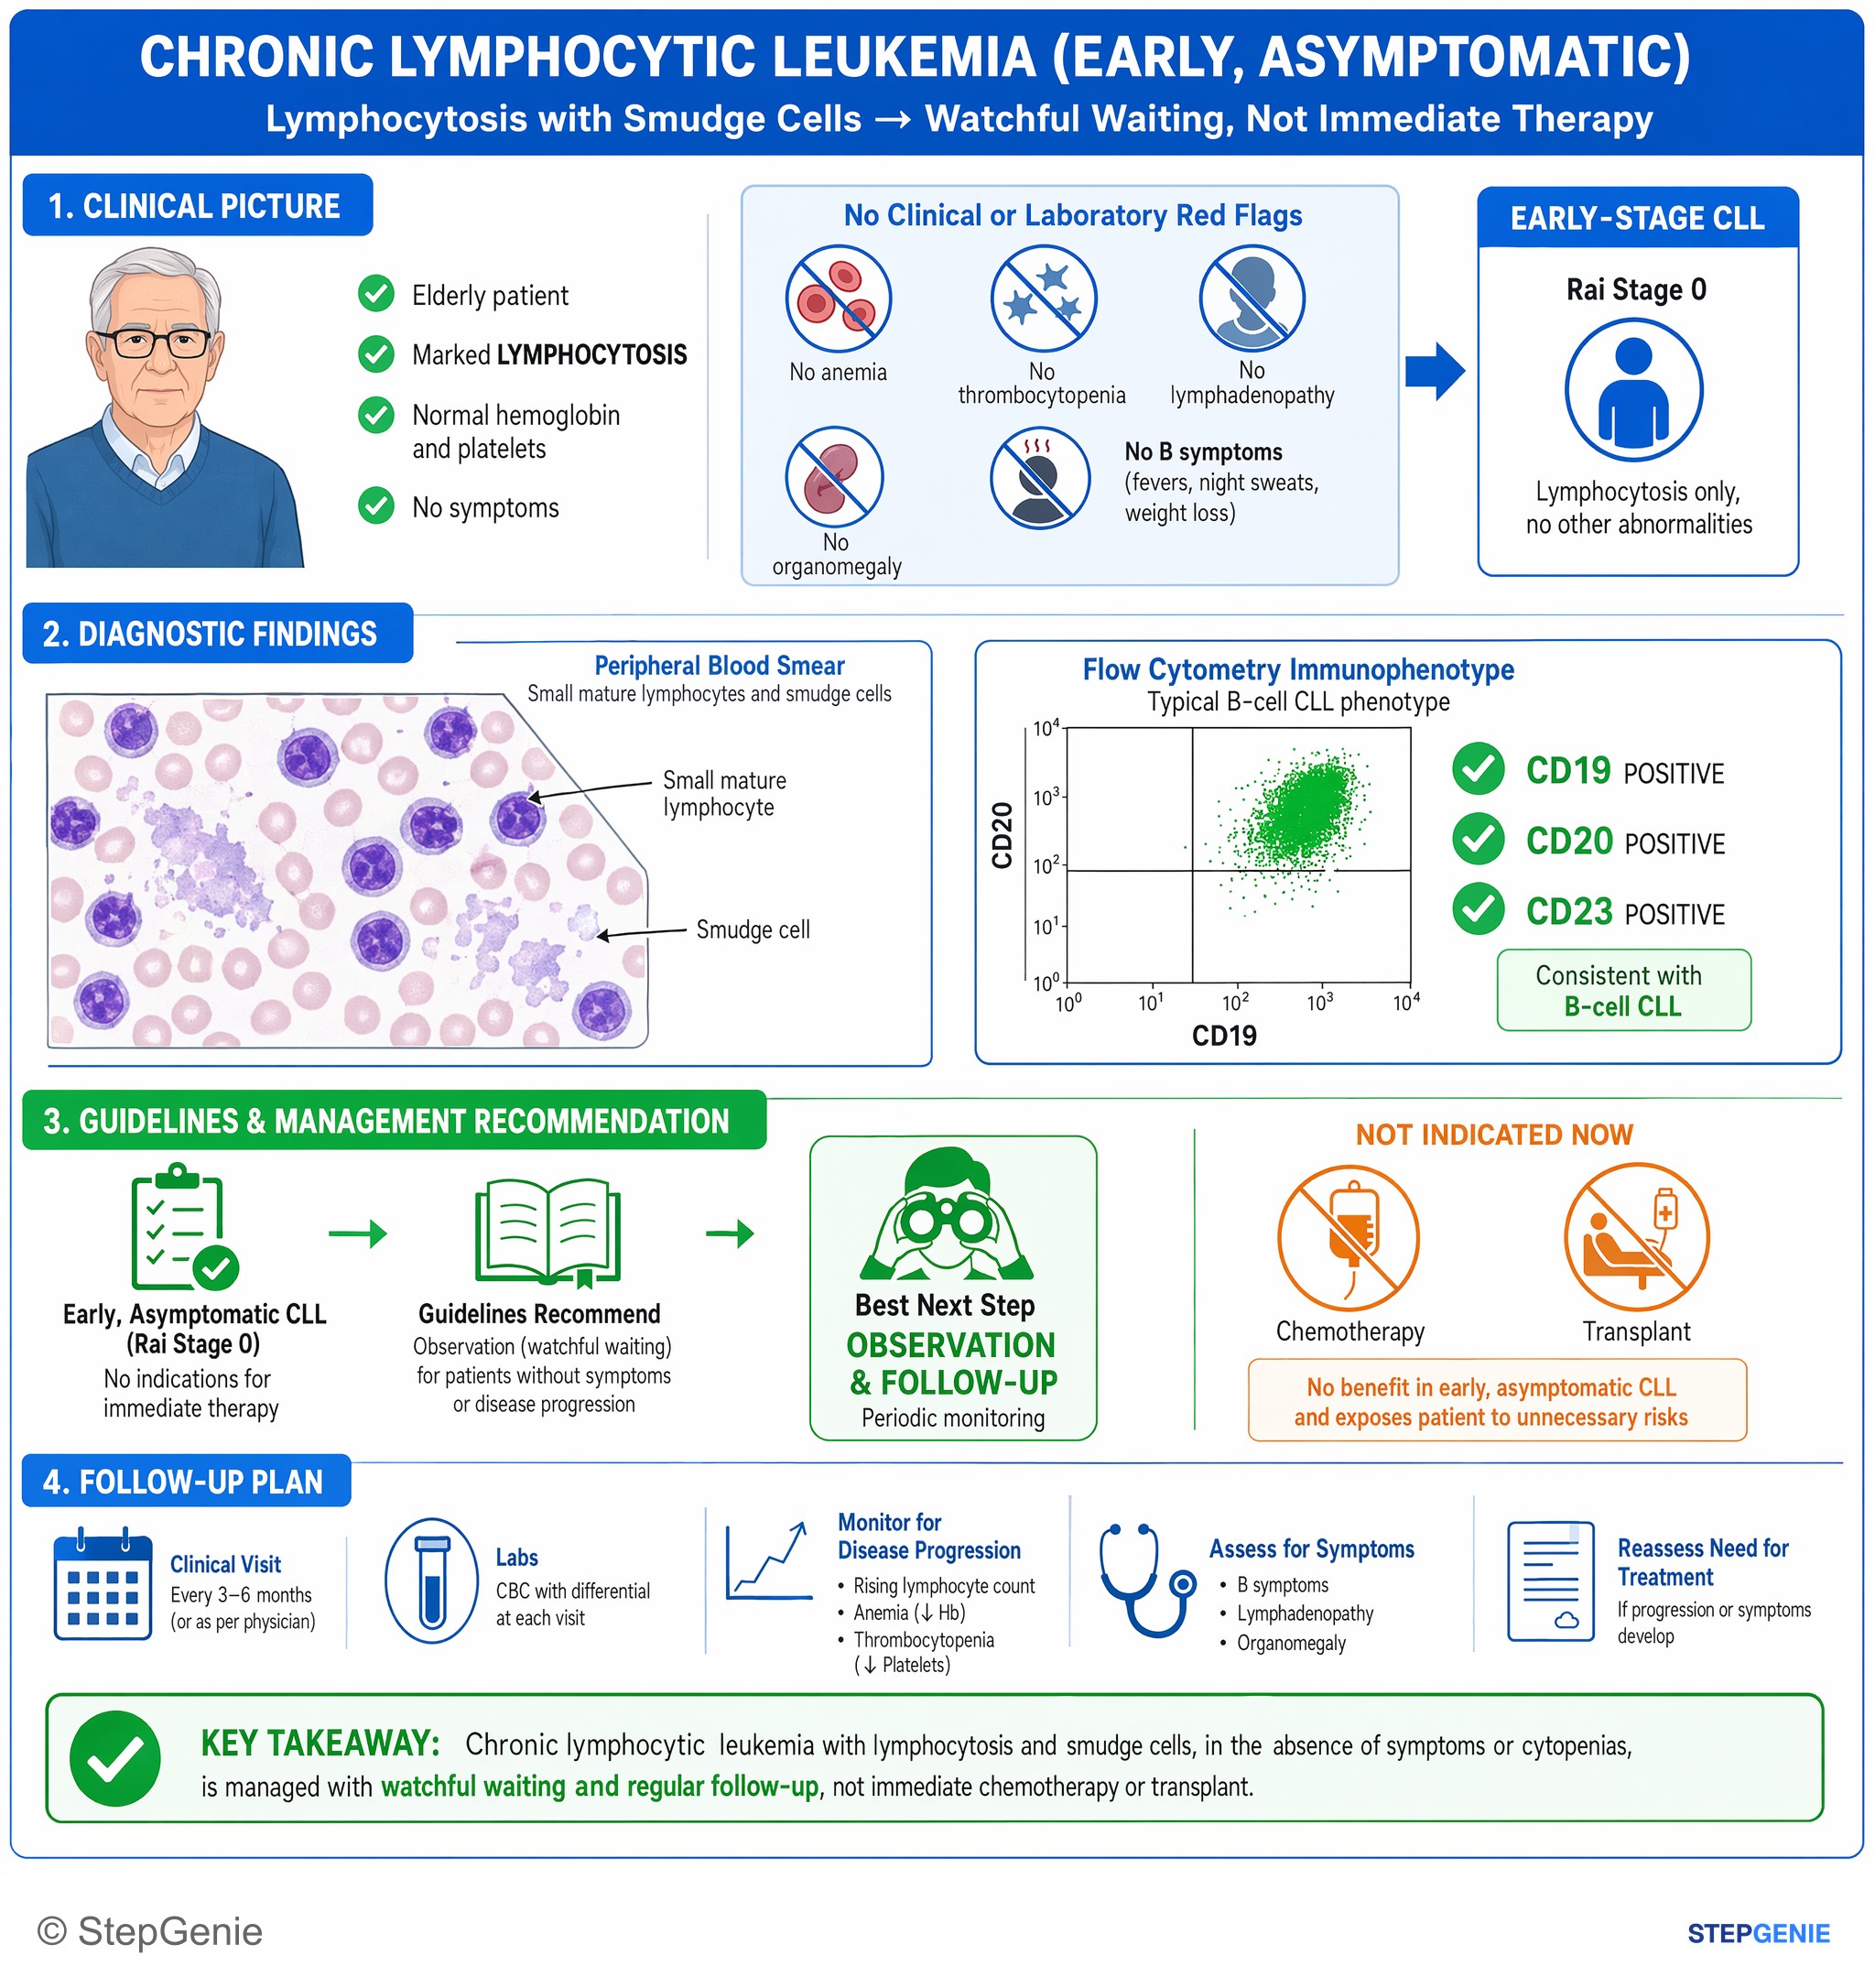
Chronic lymphocytic leukemia (early, asymptomatic) with lymphocytosis and smudge cells is managed with watchful waiting, not immediate…
USMLE Step 2Frequently Asked Questions
What are smudge cells in CLL?
Smudge cells, also called Gumprecht nuclear shadows, are the crushed remains of fragile CLL lymphocytes that break apart when a blood smear is made. They look like smeared nuclear material lying next to many small, mature-looking lymphocytes. They support the diagnosis but do not prove it: CLL is confirmed by flow cytometry showing at least 5 × 10⁹/L clonal B cells that are CD5+, CD19+, CD23+ and CD20 dim, with a single light chain.
How do you tell CLL from mantle cell lymphoma?
Both are CD5-positive B-cell cancers of older adults, which is why exams pair them. CLL cells are CD23-positive with dim CD20 and dim surface immunoglobulin, and the smear shows smudge cells. Mantle cell lymphoma is CD23-negative and cyclin D1-positive because of the t(11;14) translocation, which drives cyclin D1 overexpression. It is also SOX11-positive, is more common in men, and often involves the spleen, bone marrow and gastrointestinal tract.
What is the difference between CLL, SLL and monoclonal B lymphocytosis?
All three involve the same kind of clonal CD5-positive B cell. CLL is diagnosed when the blood contains at least 5 × 10⁹/L clonal B cells for at least 3 months. Small lymphocytic lymphoma (SLL) is the same disease centered in lymph nodes, with fewer than 5 × 10⁹/L clonal B cells in the blood and no cytopenias from marrow infiltration. Monoclonal B lymphocytosis is a smaller clone with no enlarged nodes, organomegaly, cytopenias or symptoms; about 1-2% per year progress to CLL.
What is the Rai staging system for CLL?
Rai staging uses physical findings and blood counts. Stage 0 is lymphocytosis alone; stage I adds enlarged lymph nodes; stage II adds an enlarged spleen or liver; stage III adds anemia with hemoglobin below 11 g/dL; and stage IV adds thrombocytopenia with platelets below 100,000/µL. Stage 0 is low risk, stages I and II are intermediate risk, and stages III and IV are high risk. The Binet system instead counts enlarged lymphoid areas and uses hemoglobin 10 g/dL and platelets 100,000/µL as cutoffs.
When does CLL need treatment?
Only when it is active by iwCLL criteria. Triggers include progressive marrow failure (worsening anemia or thrombocytopenia, for example hemoglobin below 10 g/dL), massive, progressive or symptomatic enlargement of the spleen or lymph nodes, a lymphocyte doubling time under 6 months, autoimmune anemia or thrombocytopenia that responds poorly to steroids, symptomatic extranodal disease, and disease-related symptoms such as major weight loss, fevers, night sweats or disabling fatigue. A high lymphocyte count or low immunoglobulins alone are not reasons to treat.
What is the treatment for CLL in 2026?
Most patients who need treatment now receive targeted drugs rather than chemotherapy. Options include continuous Bruton tyrosine kinase (BTK) inhibitors such as acalabrutinib, zanubrutinib or ibrutinib, or fixed-duration regimens built on the BCL-2 inhibitor venetoclax, given with obinutuzumab for about a year or with acalabrutinib (FDA approved in February 2026 for previously untreated CLL). Pirtobrutinib, a noncovalent BTK inhibitor, is approved for relapsed or refractory CLL after a covalent BTK inhibitor, and anti-CD19 CAR T-cell therapy is an option for relapsed disease.