ACE inhibitors (the -prils) block angiotensin-converting enzyme, the same enzyme as kininase II, which breaks down bradykinin; that is why they cause the two bradykinin side effects, dry cough and angioedema, while ARBs (the -sartans) block the AT₁ receptor and leave bradykinin alone. The mnemonic is ACE = Angioedema, Cough, Elevated K⁺: A and C belong to ACE inhibitors, but both classes lower aldosterone, so both raise K⁺. Both also raise creatinine (rises up to about 30% are expected), both carry a boxed warning for fetal toxicity, and they should never be combined; in HFrEF, the 2022 AHA/ACC/HFSA guideline prefers sacubitril/valsartan (an ARNI) to either.
ACE inhibitors vs ARBs at a glance
| Feature | ACE inhibitors (-pril) | ARBs (-sartan) |
|---|---|---|
| Examples | Lisinopril, enalapril, ramipril, captopril, benazepril | Losartan, valsartan, candesartan, telmisartan, irbesartan |
| What is blocked | ACE (kininase II): angiotensin I → II conversion and bradykinin breakdown | Angiotensin II at the AT₁ receptor; ACE keeps working |
| Angiotensin II | ↓ | ↑ (renin rises, but the receptor is blocked) |
| Bradykinin | ↑ | Unchanged |
| Dry cough | Reported in 5–35% of users | About the same as placebo |
| Angioedema | Under 1%; higher in Black patients | Rare |
| Hyperkalemia | Yes | Yes |
| Creatinine rise | Expected, usually ≤30% | Same |
| Pregnancy | Boxed warning: fetal toxicity | Same |
| Lithium levels | ↑ | ↑ |
| Use together? | No: more harm, no added benefit | No |
The mnemonic: ACE, then -PRIL
ACE is what sets ACE inhibitors apart, plus potassium. Keep the old "aches in the face" image, made accurate: swollen lips (A), a dry hack (C) and, on the monitor beside the face, peaked T waves (E).
- A, Angioedema: non-itchy swelling of the lips, tongue, face, larynx or bowel, from bradykinin.
- C, Cough: dry and tickly, hours to months after the first dose, from bradykinin and substance P.
- E, Elevated K⁺: less angiotensin II → less aldosterone → less K⁺ secretion.
A and C come from bradykinin, so ARBs largely lose them; E comes from aldosterone, so ARBs keep it. -PRIL is what both classes share:
- P, Pregnancy: boxed warning; fetotoxic in the second and third trimesters.
- R, Renal: creatinine rises from efferent arteriole dilation; acute kidney injury when GFR depends on angiotensin II (bilateral renal artery stenosis, volume depletion).
- I, Increased renin: angiotensin II no longer suppresses renin, so plasma renin activity rises.
- L, Low BP and Lithium: first-dose hypotension, especially with volume depletion; lithium levels rise.
Shortcut: an ARB is ACE-PRIL minus the C, with the A made rare.
How they work: RAAS, bradykinin and the efferent arteriole
In the renin–angiotensin–aldosterone system, juxtaglomerular cells release renin when renal perfusion or distal NaCl delivery falls or β₁ sympathetic tone rises. Renin turns angiotensinogen into angiotensin I, and ACE, on vascular endothelium (mostly in the lungs), converts that to angiotensin II. Via AT₁ receptors, angiotensin II constricts arterioles, releases aldosterone and vasopressin, boosts proximal tubular sodium reabsorption and sympathetic outflow, and suppresses renin.
- ACE inhibitors: angiotensin II falls; renin and angiotensin I rise; bradykinin, normally degraded by ACE, accumulates.
- ARBs: plasma renin activity doubles to triples and angiotensin II rises (losartan label), but AT₁ is blocked; ACE still clears bradykinin.
- Aliskiren, a direct renin inhibitor, lowers plasma renin activity, so angiotensin I and II both fall.
| Drug | Plasma renin activity | Angiotensin I | Angiotensin II | Aldosterone |
|---|---|---|---|---|
| ACE inhibitor | ↑ | ↑ | ↓ | ↓ |
| ARB | ↑ | ↑ | ↑ | ↓ |
| Aliskiren | ↓ | ↓ | ↓ | ↓ |
Why creatinine rises
Angiotensin II constricts the efferent arteriole, propping up glomerular pressure when renal perfusion is low. Remove it and glomerular pressure, GFR and albumin leak all fall: that is the kidney-protective effect in diabetic nephropathy and albuminuric CKD, and the reason creatinine creeps up. KDIGO 2024 calls rises below about 20–30% expected hemodynamic "dips", usually reversible and not drug toxicity. When GFR depends on angiotensin II (bilateral renal artery stenosis, stenosis to a solitary kidney, volume depletion, severe heart failure), the fall can cause acute kidney injury.
What current guidelines say
| Guideline | What it says about ACE inhibitors and ARBs |
|---|---|
| 2025 AHA/ACC high blood pressure | ACE inhibitors, ARBs, thiazide-type diuretics and long-acting dihydropyridine CCBs are the first-line classes; stage 2 hypertension starts with two first-line drugs of different classes, ideally in one pill. Hypertension plus CKD (eGFR <60 or albuminuria ≥30 mg/g), with or without diabetes: an ACE inhibitor or an ARB, not both (Class 1; the 2017 guideline rated ACE inhibitors 2a and ARBs 2b). Pregnant or planning pregnancy: do not use ACE inhibitors, ARBs, direct renin inhibitors, MRAs, atenolol or nitroprusside; labetalol and extended-release nifedipine are preferred. |
| 2022 AHA/ACC/HFSA heart failure | HFrEF with NYHA class II–III symptoms: ARNI recommended; ACE inhibitor if an ARNI is not feasible; ARB if an ACE inhibitor causes cough or angioedema and an ARNI is not feasible; switch patients who tolerate an ACE inhibitor or ARB to an ARNI (all Class 1). Harmful: an ARNI with an ACE inhibitor or within 36 hours of one, and an ARNI or ACE inhibitor after any angioedema. |
| KDIGO 2024 CKD | ACE inhibitor or ARB for CKD G1–G4 with A3 albuminuria (>300 mg/g) without diabetes (1B), suggested for A2 (30–300 mg/g) without diabetes (2C), and recommended for A2–A3 with diabetes (1B), even without high BP. Use the highest approved tolerated dose, continue below eGFR 30, and avoid any combination of ACE inhibitor, ARB and direct renin inhibitor (1B). |
| ADA Standards of Care 2026 | Diabetes plus hypertension: ACE inhibitor or ARB recommended for UACR 30–299 mg/g (B) and strongly recommended for UACR ≥300 mg/g and/or eGFR <60 (A), at the maximum tolerated dose; swap classes if one is not tolerated. Not for primary prevention of CKD when BP, UACR and eGFR are normal (A). First-line for hypertension with albuminuria or coronary artery disease; also recommended at age ≥55 with ASCVD or multiple risk factors (A). Avoid any combination of ACE inhibitor, ARB (including ARNI) and direct renin inhibitor. |
Labeled extras: lisinopril cuts mortality when started within 24 hours of an acute MI in hemodynamically stable patients; losartan reduces stroke in hypertension with left ventricular hypertrophy (its label cites evidence that this benefit does not apply to Black patients) and treats diabetic nephropathy. For the other HFrEF pillars, see HFrEF vs HFpEF.
Adverse effects, with the numbers
Cough (ACE inhibitors)
- How common: 5–35% in published reports (ACCP; StatPearls gives 10–20%). In ONTARGET, 4.2% of patients on ramipril stopped it permanently because of cough, vs 1.1% on telmisartan.
- Timing: hours to months after starting; it usually resolves 1–4 weeks after stopping, occasionally lingering up to 3 months.
- Fix: stopping is the only reliable cure, and it is a class effect, so do not switch to another -pril. In losartan rechallenge trials of patients with proven ACE-inhibitor cough, cough recurred in 62–69% on lisinopril vs 17–29% on losartan, similar to placebo or hydrochlorothiazide (25–35%).
Angioedema (mainly ACE inhibitors)
- How common: under 1% of users, yet ACE inhibitors cause about 30% of acute angioedema seen in emergency departments (Merck). The rate is higher in Black patients: on enalapril in PARADIGM-HF it was 0.5% in Black patients vs 0.2% overall.
- When: soon after starting or years later.
- What it looks like: swelling of the face, lips, tongue, glottis or larynx without hives or itch; intestinal angioedema causes abdominal pain, sometimes without facial swelling and with normal C1 esterase levels.
- Extra risk: prior angioedema of any cause, mTOR inhibitors (sirolimus, everolimus, temsirolimus) and neprilysin inhibitors.
- Treatment: airway first; stop the ACE inhibitor for good. Epinephrine, glucocorticoids and antihistamines have not been shown to work for bradykinin angioedema, which usually settles 24–48 hours after stopping (Merck still advises epinephrine for airway swelling unless the cause is clearly bradykinin-mediated). Severe or progressing cases can be tried on C1 inhibitor concentrate, fresh frozen plasma, and possibly ecallantide or icatibant.
Hyperkalemia (both)
In lisinopril trials, potassium above 5.7 mEq/L occurred in 2.2% of hypertension patients and 4.8% of heart failure patients. Risk climbs with CKD, diabetes, potassium-sparing diuretics, potassium supplements and potassium-containing salt substitutes. For the ECG and emergency treatment, see hyperkalemia.
Creatinine, acute kidney injury and when to stop (both)
- Usually small: reversible BUN and creatinine rises in about 2% of lisinopril-treated hypertension patients (more with diuretics or renal artery stenosis) and 11.6% of heart failure patients on diuretics.
- High-risk kidneys: renal artery stenosis, CKD, severe heart failure, post-MI and volume depletion. An NSAID, especially with a diuretic, can tip an ACE inhibitor or ARB into acute renal failure (the "triple whammy") and also blunts the BP effect.
- Check and continue: recheck BP, creatinine and K⁺ within 2–4 weeks of starting or raising the dose, and continue if creatinine rises ≤30% without volume depletion (KDIGO 2024, ADA 2026).
- Investigate a rise >30%: volume depletion, NSAIDs, diuretics, renal artery stenosis (an acute, sustained rise >30% is a classic renovascular clue). Reduce or stop the drug if the cause cannot be fixed.
- Hyperkalemia: lower the potassium first (dietary potassium, diuretics, sodium bicarbonate, potassium binders); reduce or stop the drug if it stays uncontrolled despite treatment, or for symptomatic hypotension.
Hypotension and fetal toxicity
- Hypotension: highest risk with heart failure and systolic BP <100, hyponatremia, high-dose diuretics, dialysis, or volume or salt depletion; start low and watch the first two weeks.
- Fetal toxicity (boxed warning on ACE inhibitors, ARBs and ARNI): second- and third-trimester exposure reduces fetal renal function; the resulting oligohydramnios can be associated with lung hypoplasia and skeletal deformities, and neonates can have skull hypoplasia, anuria, hypotension, renal failure or death. First-trimester risk is less well defined, but the drug is stopped as soon as pregnancy is detected; see preeclampsia and hypertension in pregnancy for alternatives.
Contraindications and interactions
- Pregnancy or planned pregnancy; ADA also says to avoid these drugs in sexually active people who could become pregnant and are not using reliable contraception.
- Angioedema: no ACE inhibitor after ACE-inhibitor angioedema or with hereditary or idiopathic angioedema; no sacubitril/valsartan after ACE-inhibitor or ARB angioedema, or with hereditary angioedema (the 2022 heart failure guideline calls an ARNI or ACE inhibitor after any angioedema harmful). An ARB remains an option, used cautiously: the same guideline recommends one in HFrEF when an ACE inhibitor caused cough or angioedema and an ARNI is not feasible, but the losartan label reports angioedema in some patients who had it on ACE inhibitors.
- Neprilysin inhibitors: never with an ACE inhibitor; leave 36 hours between the last ACE-inhibitor dose and sacubitril/valsartan, and vice versa. ACE and neprilysin both degrade bradykinin: in the OCTAVE trial, omapatrilat, which blocked both enzymes, caused angioedema in 2.17% vs 0.68% on enalapril. The label sets no washout for switching from an ARB.
- Aliskiren: contraindicated with an ACE inhibitor or ARB in diabetes; avoid the combination when GFR is <60.
- Bilateral renal artery stenosis (or stenosis to a solitary kidney): the classic exam contraindication. US labels list renal artery stenosis under warnings (monitor renal function), not contraindications, and StatPearls says a GFR fall with bilateral stenosis and poor renal perfusion mandates stopping the drug.
- Lithium: ACE inhibitors reduce renal lithium clearance, and lithium toxicity is reported with ACE inhibitors, ARBs and ARNI, so monitor levels.
Why not combine an ACE inhibitor with an ARB (or aliskiren)?
Dual blockade trims albuminuria a little more, but the kidneys and potassium pay for it.
- ONTARGET (2008): 25,620 patients with vascular disease or high-risk diabetes got ramipril, telmisartan or both. The primary outcome (cardiovascular death, MI, stroke or heart failure hospitalization) was 16.5%, 16.7% and 16.3%. Telmisartan matched ramipril, and fewer patients stopped it because of cough (1.1% vs 4.2%) or angioedema (0.1% vs 0.3%); the combination added hypotensive symptoms (4.8% vs 1.7%), syncope and renal dysfunction (13.5% vs 10.2%) without benefit.
- VA NEPHRON-D (2013): in 1,448 patients with type 2 diabetes, UACR ≥300 mg/g and eGFR 30–89.9, adding lisinopril to losartan gave no benefit; hyperkalemia rose from 2.6 to 6.3 and acute kidney injury from 6.7 to 12.2 events per 100 person-years, and the trial stopped early for safety.
- ALTITUDE (2012): aliskiren added to an ACE inhibitor or ARB in type 2 diabetes was stopped early with no benefit and more hyperkalemia and hypotension; the aliskiren label's diabetes contraindication cites it.
Hence the rule: one of ACE inhibitor, ARB or direct renin inhibitor, never two. Adding a mineralocorticoid receptor antagonist is different and evidence-based (an HFrEF pillar; ADA recommends a nonsteroidal MRA on top of a maximally dosed ACE inhibitor or ARB in type 2 diabetes with albuminuric CKD).
ACE inhibitor vs ARB vs ARNI
| Feature | ACE inhibitor | ARB | ARNI (sacubitril/valsartan) |
|---|---|---|---|
| Mechanism | Blocks ACE | Blocks AT₁ | Sacubitril blocks neprilysin (more natriuretic peptides); valsartan blocks AT₁ |
| Bradykinin | ↑ | Unchanged | ↑ (neprilysin also degrades it) |
| HFrEF role (2022 guideline) | When an ARNI is not feasible | When an ACE inhibitor is not tolerated and an ARNI is not feasible | First choice, NYHA II–III |
| Key evidence | Lower mortality in HFrEF and after MI | Telmisartan equal to ramipril (ONTARGET) | CV death or HF hospitalization 21.8% vs 26.5% on enalapril (HR 0.80, PARADIGM-HF) |
| Cough | Most | Placebo-like | 9% vs 13% on enalapril |
| Angioedema | Under 1% | Rare | 0.5% vs 0.2% on enalapril; 2.4% vs 0.5% in Black patients |
| Hypotension | Yes | Yes | More than enalapril (18% vs 12%) |
| Hyperkalemia, creatinine rise | Yes | Yes | Yes (hyperkalemia 12% vs 14% on enalapril) |
| Prior angioedema | Contraindicated | Use with caution | Contraindicated after ACE-inhibitor or ARB angioedema; avoid after any angioedema (2022 guideline) |
| Switching | 36-hour gap before an ARNI | No washout in the ARNI label | 36-hour gap before an ACE inhibitor |
| Pregnancy | Boxed warning | Boxed warning | Boxed warning |
How USMLE tests it
Name traps
| Ending | Class | Example | Trap |
|---|---|---|---|
| -pril | ACE inhibitor | Lisinopril, enalapril | Captopril and lisinopril are active drugs; enalapril, benazepril, fosinopril, quinapril and moexipril are prodrugs |
| -sartan | ARB | Losartan, valsartan | Similar benefits in most settings, no bradykinin rise |
| -kiren | Direct renin inhibitor | Aliskiren | Lowers plasma renin activity; never with an ACE inhibitor or ARB in diabetes |
| -tril, not -pril | Neprilysin inhibitor | Sacubitril | Given only with valsartan; raises bradykinin, hence the 36-hour gap |
| -sentan | Endothelin receptor antagonist | Bosentan | Pulmonary arterial hypertension, not an ARB |
Exam lore vs current sources
| Exam lore | What current sources say |
|---|---|
| ACE inhibitors are first-line for HFrEF | ARNI first; ACE inhibitor when an ARNI is not feasible (2022 guideline) |
| ARBs are only for ACE-inhibitor intolerance | First-line peers in hypertension, CKD and diabetes; in HFrEF the ranking is ARNI, then ACE inhibitor, then ARB |
| Stop the drug if creatinine rises | Continue unless the rise exceeds 30% (KDIGO 2024, ADA 2026) |
| Every patient with diabetes needs an ACE inhibitor | Not to prevent CKD when BP, UACR and eGFR are normal (ADA 2026) |
| Black patients: start a thiazide or CCB | Lisinopril monotherapy lowers BP less in Black patients, a gap that closes when a thiazide is added (label); the 2025 guideline dropped race-based drug choices |
For other drug classes in the same style, see high-yield drug side effects.
Worked vignettes
Vignette 1: cough. A 56-year-old woman with hypertension and type 2 diabetes (UACR 120 mg/g) started lisinopril 4 months ago. She now has a dry, tickly cough that keeps her awake; there is no fever, wheeze, heartburn or postnasal drip, and the chest x-ray is normal. What is the best next step?
Answer: Stop lisinopril and start an ARB such as losartan.
Reasoning: Bradykinin cough is a class effect, so another -pril would do the same. The ARB keeps the albuminuria protection ADA recommends for UACR 30–299 mg/g, with a placebo-like cough rate; the cough may take 1–4 weeks (occasionally 3 months) to fade. Adding the ARB to lisinopril would be dual blockade.
Vignette 2: angioedema. A 47-year-old Black man who has taken enalapril for 3 years wakes with a swollen tongue and lower lip, a muffled voice and drooling. He has no hives or itch and has eaten nothing new. What is the mechanism, and what comes first?
Answer: Bradykinin-mediated ACE-inhibitor angioedema; protect the airway (prepare for intubation) and stop enalapril permanently.
Reasoning: ACE is kininase II, so bradykinin accumulates; years of uneventful use do not exclude it, and risk is higher in Black patients. Epinephrine, steroids and antihistamines have not been shown to help; refractory cases can be tried on C1 inhibitor concentrate or fresh frozen plasma, and possibly ecallantide or icatibant. No hives or itch argues against mast-cell angioedema, and hereditary angioedema would show a low C4. Afterward: no ACE inhibitor or sacubitril/valsartan ever again; treat his BP with a thiazide or CCB.
Vignette 3: acute kidney injury after starting the drug. A 71-year-old smoker with peripheral artery disease has BP 168/94 mm Hg despite amlodipine and chlorthalidone. Lisinopril 10 mg is added. Ten days later creatinine has risen from 1.2 to 2.1 mg/dL and K⁺ is 5.8 mEq/L. He takes no NSAIDs, is not volume depleted, and has a periumbilical bruit. What is the most likely explanation?
Answer: Bilateral atherosclerotic renal artery stenosis, unmasked by loss of angiotensin II–dependent efferent constriction.
Reasoning: A 75% rise, (2.1 − 1.2)/1.2, is far above the 30% that KDIGO and ADA tolerate, and with NSAIDs and volume depletion excluded, renovascular disease is the classic cause. Stop lisinopril, treat the potassium and image the renal arteries (for example, duplex ultrasound). Had creatinine gone from 1.2 to 1.4 mg/dL (17%), the right move would be to continue and recheck.
Key takeaways
- ACE = Angioedema, Cough, Elevated K⁺. A and C come from bradykinin (ACE inhibitors only); E comes from low aldosterone (both classes).
- -PRIL is shared: Pregnancy boxed warning, Renal (creatinine rise, AKI with bilateral renal artery stenosis), Increased renin, Low BP and Lithium toxicity.
- ACE-inhibitor cough (5–35%) fades 1–4 weeks after stopping; switch to an ARB, not another -pril. Angioedema (under 1%, more in Black patients) can appear years in: airway first, stop the drug.
- Creatinine rises up to 30% are expected; above 30%, look for volume depletion, NSAIDs or renal artery stenosis.
- Never combine an ACE inhibitor with an ARB, or either with aliskiren in diabetes (ONTARGET, VA NEPHRON-D, ALTITUDE).
- In HFrEF, ARNI comes first; keep 36 hours between an ACE inhibitor and sacubitril/valsartan.
Sources
- ACE Inhibitors — StatPearls, NCBI Bookshelf (2025)
- Zestril (lisinopril) label — DailyMed (2025)
- Cozaar (losartan) label — DailyMed (2026)
- Entresto (sacubitril/valsartan) label — DailyMed (2026)
- Angioedema — Merck Manual Professional Edition (2026)
- KDIGO 2024 Clinical Practice Guideline for Chronic Kidney Disease — KDIGO (2024)
- Standards of Care in Diabetes—2026, all recommendations — American Diabetes Association (2025)
- The 2025 AHA/ACC Hypertension Guidelines: Key Updates, Historical Context, and Clinical Implications — Current Cardiology Reports (2026)
- Formulary Brief: Hypertension Guideline Update (review of the 2025 AHA/ACC guideline) — Indian Health Service National Pharmacy and Therapeutics Committee (2026)
- Overview of the 2025 Hypertension Guidelines — UIC Drug Information Group (2025)
- CMS135v14 heart failure ACEi/ARB/ARNI measure, quoting the 2022 AHA/ACC/HFSA guideline — eCQI Resource Center (2026)
- ACE inhibitor-induced cough: ACCP evidence-based clinical practice guidelines — Chest (2006)
- Telmisartan, ramipril, or both in patients at high risk for vascular events (ONTARGET) — N Engl J Med (2008)
- Combined angiotensin inhibition for the treatment of diabetic nephropathy (VA NEPHRON-D) — N Engl J Med (2013)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
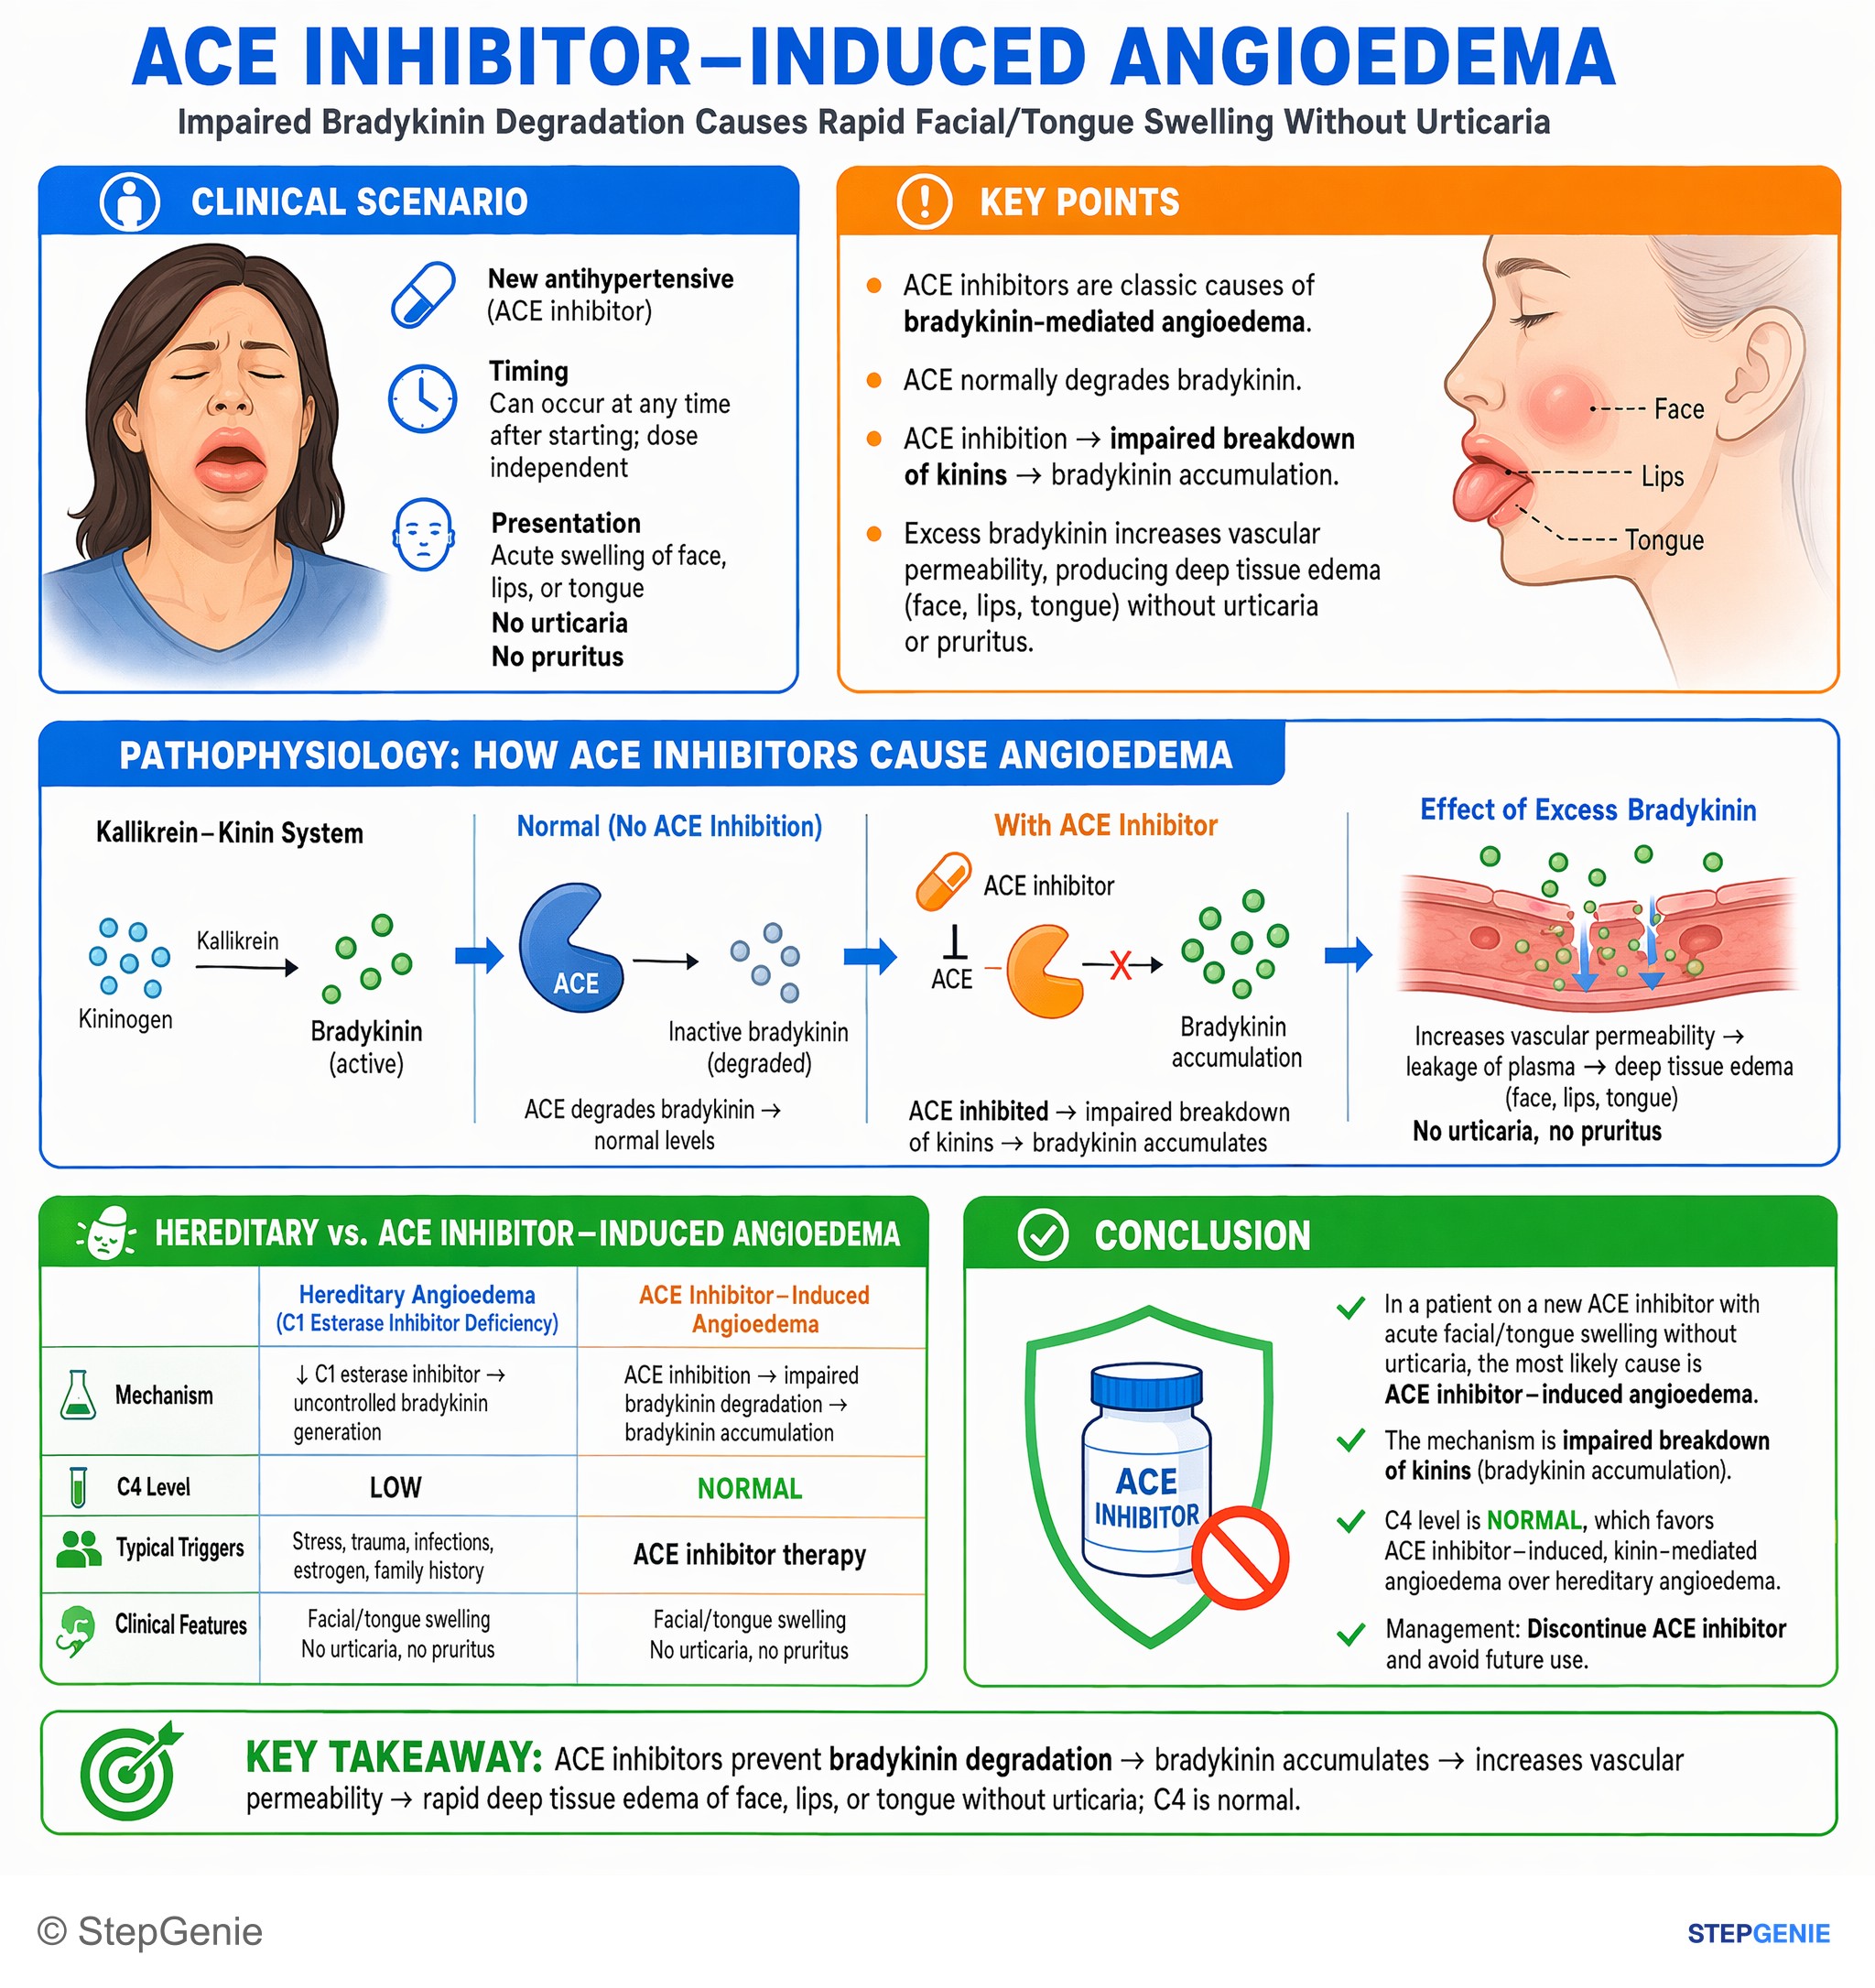
ACE inhibitor–induced angioedema from impaired bradykinin degradation causes rapid facial/tongue swelling without urticaria; C4 is normal…
USMLE Step 1Frequently Asked Questions
Why do ACE inhibitors cause a dry cough and angioedema but ARBs rarely do?
ACE is the same enzyme as kininase II, which breaks down bradykinin. ACE inhibitors therefore raise bradykinin and substance P while they lower angiotensin II, and bradykinin drives the dry cough and the non-itchy swelling of angioedema. ARBs block angiotensin II at the AT1 receptor and leave ACE working, so bradykinin is cleared normally. Cough with ARBs is similar to placebo and angioedema is rare, though not impossible, including in some people who had it before on an ACE inhibitor.
What does the ACE mnemonic for ACE inhibitor side effects stand for?
ACE stands for Angioedema, Cough and Elevated potassium. Angioedema and cough come from bradykinin build-up, so they belong mainly to ACE inhibitors. Elevated potassium comes from lower aldosterone, so ARBs share it. A second word, PRIL, covers what both classes share: Pregnancy (boxed warning for fetal toxicity), Renal effects (creatinine rise, and acute kidney injury in bilateral renal artery stenosis), Increased renin, and Low blood pressure plus Lithium toxicity.
How much can creatinine rise after starting an ACE inhibitor or ARB before you stop it?
A rise of up to about 30% is expected, because blocking angiotensin II dilates the efferent arteriole and lowers glomerular pressure. KDIGO 2024 advises checking blood pressure, creatinine and potassium within 2 to 4 weeks and continuing the drug unless creatinine rises more than 30% within 4 weeks; ADA 2026 says the same when there is no volume depletion. A larger rise should prompt a search for volume depletion, NSAIDs, diuretics or renal artery stenosis, then dose reduction or stopping if the cause cannot be corrected.
Can someone who had angioedema on an ACE inhibitor take an ARB or sacubitril/valsartan?
They should never take an ACE inhibitor again, and sacubitril/valsartan is contraindicated after angioedema from an ACE inhibitor or ARB. An ARB can be used with caution when the indication is strong: the 2022 heart failure guideline recommends an ARB in HFrEF when an ACE inhibitor causes cough or angioedema and an ARNI is not feasible, but the losartan label reports angioedema in some patients who had it before on ACE inhibitors. For hypertension alone, a thiazide or calcium channel blocker avoids the problem.
Why shouldn't an ACE inhibitor and an ARB be combined?
Dual blockade adds harm without benefit. In ONTARGET, ramipril plus telmisartan did not reduce cardiovascular events compared with ramipril alone but caused more hypotensive symptoms, syncope and renal dysfunction. In VA NEPHRON-D, adding lisinopril to losartan in diabetic kidney disease gave no kidney benefit, roughly doubled hyperkalemia and acute kidney injury, and the trial stopped early. Aliskiren with an ACE inhibitor or ARB is contraindicated in diabetes. The 2025 AHA/ACC, KDIGO 2024 and ADA 2026 guidelines all say to use one or the other.
Are ACE inhibitors and ARBs safe in pregnancy?
No. ACE inhibitors, ARBs and sacubitril/valsartan carry an FDA boxed warning for fetal toxicity. Exposure in the second and third trimesters reduces fetal kidney function; the resulting oligohydramnios can be associated with lung hypoplasia and skeletal deformities, and newborns can have skull hypoplasia, anuria, hypotension, renal failure or death. First-trimester risk is less clear, but the drug is stopped as soon as pregnancy is detected. The 2025 AHA/ACC guideline says not to use them during or when planning pregnancy and prefers labetalol or extended-release nifedipine.