Mitral valve prolapse (MVP) is systolic billowing of one or both mitral leaflets at least 2 mm above the mitral annular plane into the left atrium, usually from myxomatous degeneration; it affects about 2-3% of people and is linked to connective tissue disorders such as Marfan and Ehlers-Danlos syndromes, and to ADPKD. The classic sign is a midsystolic click, followed by a late systolic murmur when there is mitral regurgitation (MR), best heard at the apex: anything that shrinks the left ventricle (standing, Valsalva) moves the click toward S1 and lengthens the murmur, while squatting or handgrip delays the click and shortens it. Most patients need only reassurance; the complications that matter are progressive MR, chordal rupture with a flail leaflet, infective endocarditis, and arrhythmias with a small risk of sudden death. Echocardiography confirms the diagnosis, and under AHA guidance MVP alone no longer qualifies for endocarditis prophylaxis before dental work.
What MVP is: a floppy, myxomatous valve
- Pathology: proteoglycans accumulate in the valve's spongiosa layer, adding water and making the leaflets thick and redundant; structural collagen is degraded and disorganized, and the chordae weaken and elongate. The enlarged, rubbery leaflets bow back into the left atrium (LA) in systole.
- Two patterns: myxomatous degeneration (Barlow disease: thick, redundant leaflets, often involving both leaflets) and fibroelastic deficiency (thin leaflets with reduced collagen, elastin and proteoglycans; more often localized prolapse with chordal rupture and a flail segment).
- Primary MVP is idiopathic, the most common form; familial cases can carry autosomal dominant variants.
- Associations (Merck, StatPearls): Marfan syndrome, Ehlers-Danlos syndrome, ADPKD, Loeys-Dietz syndrome, osteogenesis imperfecta and pseudoxanthoma elasticum. See Marfan syndrome and the ADPKD vs ARPKD mnemonic.
- Epidemiology: prevalence about 2-3% (StatPearls; Merck gives 2.4%). StatPearls reports a slight female predominance, while Merck says men and women are affected equally.
Symptoms: usually none
Most people with MVP have no symptoms and are picked up by a click on routine exam or an incidental echo. Some report palpitations, atypical chest pain, exertional dyspnea, dizziness, near syncope or anxiety. The old "MVP syndrome" of autonomic symptoms is shaky: StatPearls notes that the latest guidelines dropped their dysautonomia advice because the link with MVP is unclear. Progressive dyspnea and fatigue suggest that MR has become significant.
The click and the murmur: why maneuvers move them
As the LV contracts, the redundant leaflet bulges into the LA until the leaflet and chordae snap taut: the crisp midsystolic click. If the leaflets then fail to meet, regurgitation starts after the click, giving a late systolic murmur at the apex.
The rule: a smaller LV makes the valve prolapse earlier in systole.
| Maneuver | LV size | Click | Murmur |
|---|---|---|---|
| Standing (or sitting up) | Smaller (less venous return) | Earlier, closer to S1 | Appears or gets louder, lasts longer |
| Valsalva (strain phase) | Smaller | Earlier | Louder, longer |
| Squatting | Larger | Later | Shorter |
| Isometric handgrip | Larger (higher afterload) | Later | Shorter |
MVP vs HCM vs aortic stenosis vs MR
Hypertrophic cardiomyopathy (HCM) is the classic trap because its murmur also grows when the LV shrinks; the click, the location and the pulse separate them.
| MVP | HCM (obstructive) | Aortic stenosis | Chronic MR | |
|---|---|---|---|---|
| Sound | Midsystolic click → late systolic murmur | Late-peaking systolic murmur, no click | Harsh crescendo-decrescendo ejection murmur | Holosystolic blowing murmur |
| Where | Apex | Left sternal border, 3rd-4th intercostal space | Upper sternal borders → both carotids | Apex → left axilla |
| Standing or Valsalva | Click earlier, murmur longer | Louder | Softer | Softer |
| Squatting or leg raise | Click later, murmur shorter | Softer | Louder | Louder with squatting |
| Handgrip | Click later, murmur shorter | Softer | Softer | Louder |
| Other clue | Young woman, palpitations, connective tissue disease | Brisk, bifid carotid upstroke; often an S4 | Blunted carotid upstroke | Enlarged LA and LV, atrial fibrillation |
More on each lesion: the HCM memory palace, the mitral regurgitation breakdown and the heart murmurs table.
Diagnosis: echo, in the right view
- Transthoracic echocardiography confirms MVP: systolic displacement of one or both leaflets ≥2 mm above the mitral annular plane in the parasternal long-axis view (StatPearls).
- Classic vs nonclassic: StatPearls defines classic MVP by leaflets >5 mm thick and nonclassic by thinner leaflets; Merck treats thick (≥5 mm), redundant leaflets as a sign of more extensive myxomatous change, with greater risk of endocarditis and MR.
- View trap: the annulus is saddle-shaped, so long-axis views (especially parasternal) are preferred; other views, classically the apical four-chamber, can overcall prolapse and give false-positive MVP.
- Doppler grades any MR; look for a flail segment and for mitral annular disjunction (MAD): partial detachment of the mitral annulus from the adjacent ventricular myocardium during systole, best seen at the posterolateral annulus. Merck links MAD to a higher risk of arrhythmic sudden death and recommends ambulatory rhythm monitoring.
- ECG is usually normal or nonspecific; inferior T-wave inversions and PVCs from the papillary muscles raise concern for arrhythmic MVP. StatPearls suggests Holter monitoring when risk features are present or the PVC burden may be ≥5%, and on cardiac MRI the extent of midwall late gadolinium enhancement (fibrosis) is the strongest predictor of arrhythmic MVP.
Complications
| Complication | What to know |
|---|---|
| Mitral regurgitation | The most common complication; MVP is the leading cause of primary MR. Rupture of a degenerated chorda lets a segment flail into the LA, typically causing severe MR |
| Infective endocarditis | About a 7-fold higher risk than the general population over 15 years (StatPearls), yet routine prophylaxis is not recommended (below) |
| Arrhythmias and sudden death | Severe ventricular arrhythmias or a high ectopic burden occur in <10% (Merck). Sudden cardiac death is rare: about 0.14% per year (StatPearls); <1% in Merck, most often with ruptured or abnormal chordae |
| Arrhythmic MVP | A high-risk phenotype, more common in young adult women and possible at any MR severity: bileaflet myxomatous prolapse, MAD, inferior T-wave inversions, papillary-muscle PVCs, and fibrosis (late gadolinium enhancement) on MRI |
| Stroke | Risk is low (<1% per year); the 2021 AHA/ASA stroke guideline notes that recent studies have not confirmed a link |
| Atrial fibrillation and heart failure | Follow severe chronic MR as the LA and LV enlarge |
With significant MR, Merck puts the rate of cardiac events (endocarditis, stroke, other embolic events) as high as 4% a year.
Management
- No significant MR: reassurance; no activity restriction unless high-risk features are present. Echo surveillance follows MR severity: every 3-5 years for mild MR and every 1-2 years for moderate MR.
- Palpitations from ectopy: beta-blockers (or verapamil) ease symptoms, but there is no evidence they improve prognosis (Merck).
- Anticoagulation: Merck recommends it only for atrial fibrillation or a prior TIA or stroke.
- Severe primary MR (2020 ACC/AHA criteria, as summarized by Merck): operate when symptoms appear or the LV starts to decompensate (LVEF ≤60% or LV end-systolic diameter ≥40 mm). Repair is preferred over replacement because it better preserves LV function and survival. Transcatheter edge-to-edge repair (TEER) is for NYHA class III-IV symptoms despite medical therapy when surgery is too risky.
- Arrhythmic features (MAD, papillary-muscle PVCs, inferior T-wave inversion): ambulatory monitoring and cardiac MRI.
Endocarditis prophylaxis: not for MVP alone
Under the 2021 AHA scientific statement (as listed by the ADA and AHA), antibiotics before dental procedures that manipulate the gums or the periapical region of the teeth, or perforate the oral mucosa, are only for the highest-risk patients:
- Prosthetic heart valves, including transcatheter valves and homografts, and prosthetic material used for valve repair (annuloplasty rings, chords)
- Previous infective endocarditis
- Certain congenital heart disease, for example unrepaired cyanotic disease, or a repair with a residual shunt or regurgitation at or next to prosthetic material
- Cardiac transplant with valve regurgitation from a structurally abnormal valve
MVP alone, even with MR, is not on the list. The trap: once a prolapsing valve has been repaired with an annuloplasty ring or artificial chords, or replaced, the patient does qualify. Review organisms and Duke criteria in the infective endocarditis breakdown.
How USMLE tests it
| Stem clue | Answer |
|---|---|
| Young woman with palpitations; apical midsystolic click that moves earlier on standing | MVP |
| Tall patient with long fingers and lens dislocation, plus a click | Marfan syndrome with MVP |
| Flank masses, hypertension and hematuria, plus a click | ADPKD with MVP |
| Known MVP, sudden severe dyspnea and pulmonary edema; the murmur may be soft or even absent | Chordal rupture → flail leaflet → acute severe MR |
| Systolic murmur louder with Valsalva, no click, left sternal border | HCM |
| Loud S1, opening snap, diastolic rumble at the apex | Rheumatic mitral stenosis |
| MVP before a dental cleaning | No antibiotic prophylaxis |
| Mitral repair with an annuloplasty ring, before a tooth extraction | Prophylaxis indicated |
Practice question
A 24-year-old woman has intermittent palpitations and brief episodes of sharp left-sided chest pain at rest. She has no exertional dyspnea, syncope, fever or drug use. Her mother "has a heart murmur." Vital signs are normal. At the apex there is a midsystolic click followed by a late systolic murmur. When she stands up from squatting, the click comes earlier and the murmur lasts longer. What is the most likely underlying abnormality?
A. Myxomatous degeneration of the mitral valve leaflets B. Calcific degeneration of the aortic valve cusps C. Asymmetric septal hypertrophy with systolic anterior motion of the mitral valve D. Rheumatic fusion of the mitral commissures E. Left ventricular dilation displacing the papillary muscles
Answer: A. A click and late systolic apical murmur that move earlier when the LV shrinks is MVP. Myxomatous, redundant leaflets and elongated chordae let the valve billow into the LA, and her family history fits a familial form.
- B (aortic stenosis): a harsh crescendo-decrescendo ejection murmur at the upper sternal borders radiating to both carotids, with a blunted carotid upstroke; it gets softer on standing or Valsalva and louder with squatting. No click at the apex.
- C (HCM): the trap, because this murmur also gets louder when the LV shrinks, and SAM can add an apical MR murmur. But HCM has no click; its outflow murmur peaks late at the left sternal border (3rd-4th intercostal space), softens with handgrip and squatting, and comes with a brisk, bifid carotid pulse.
- D (rheumatic mitral stenosis): loud S1, an early diastolic opening snap and a low-pitched diastolic rumble at the apex; a diastolic, not systolic, lesion.
- E (secondary MR): a dilated, failing LV pulls the papillary muscles outward and tethers otherwise normal leaflets, producing a holosystolic murmur radiating to the axilla in a patient with ischemic or dilated cardiomyopathy. No click.
Key takeaways
- MVP = leaflet displacement ≥2 mm above the annulus in the parasternal long-axis view, usually from myxomatous degeneration; about 2-3% of people.
- Associations: Marfan, Ehlers-Danlos, ADPKD, osteogenesis imperfecta, Loeys-Dietz.
- Midsystolic click ± late systolic murmur at the apex. Smaller LV (standing, Valsalva) → click earlier, murmur longer; bigger LV or higher afterload (squatting, handgrip) → click later, murmur shorter.
- vs HCM: both louder with Valsalva, but HCM has no click, sits at the left sternal border and softens with handgrip.
- Complications: MR (the most common; flail leaflet from chordal rupture), endocarditis, arrhythmias and rare sudden death (arrhythmic MVP: bileaflet prolapse, MAD, inferior T-wave inversion, fibrosis on MRI).
- Treatment: reassurance, beta-blockers for symptoms, valve repair for severe primary MR (symptoms, LVEF ≤60% or LVESD ≥40 mm).
- No endocarditis prophylaxis for MVP alone; yes after repair with prosthetic material or replacement.
Sources
- Mitral Valve Prolapse (MVP) — Merck Manual Professional Edition (2025)
- Mitral Valve Prolapse — StatPearls, NCBI Bookshelf (2026)
- Mitral Regurgitation — Merck Manual Professional Edition (2026)
- Hypertrophic Cardiomyopathy — Merck Manual Professional Edition (2026)
- Aortic Stenosis — Merck Manual Professional Edition (2025)
- Mitral Stenosis — Merck Manual Professional Edition (2025)
- Infective Endocarditis — American Heart Association (2026)
- Antibiotic Prophylaxis Prior to Dental Procedures — American Dental Association (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
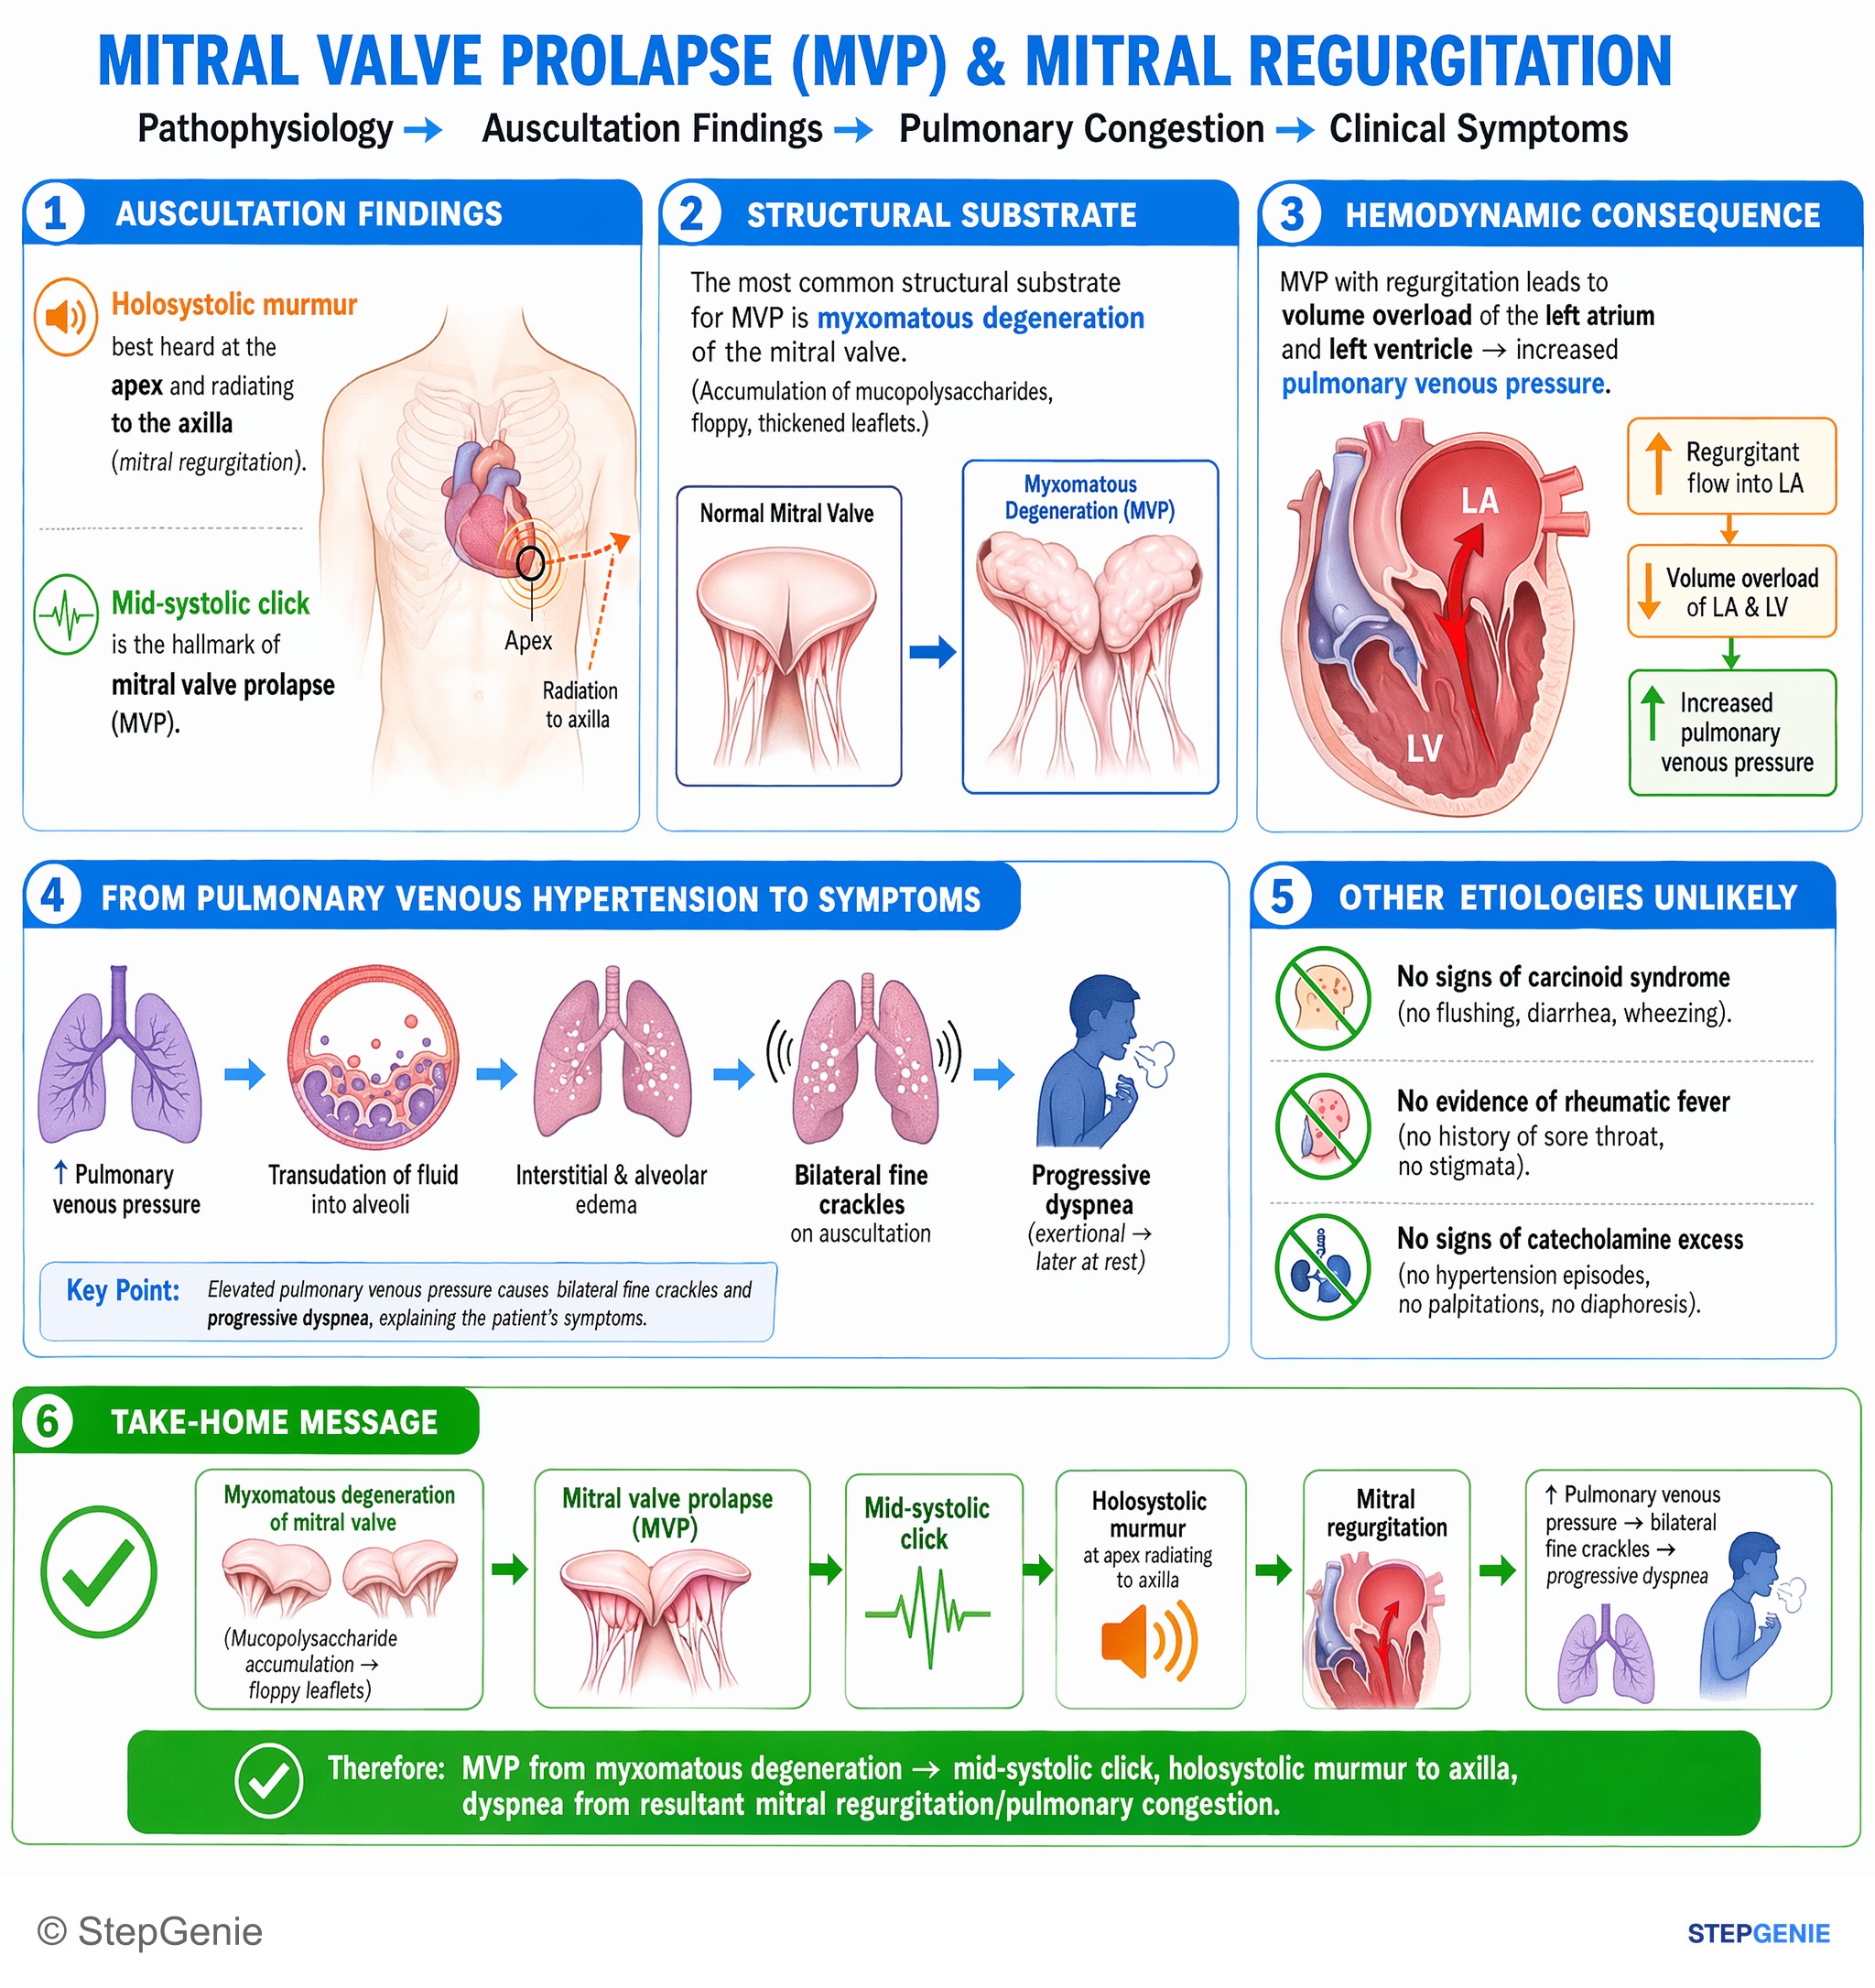
Mitral valve prolapse from myxomatous degeneration → mid-systolic click, holosystolic murmur to axilla, dyspnea from resultant mitral…
USMLE Step 1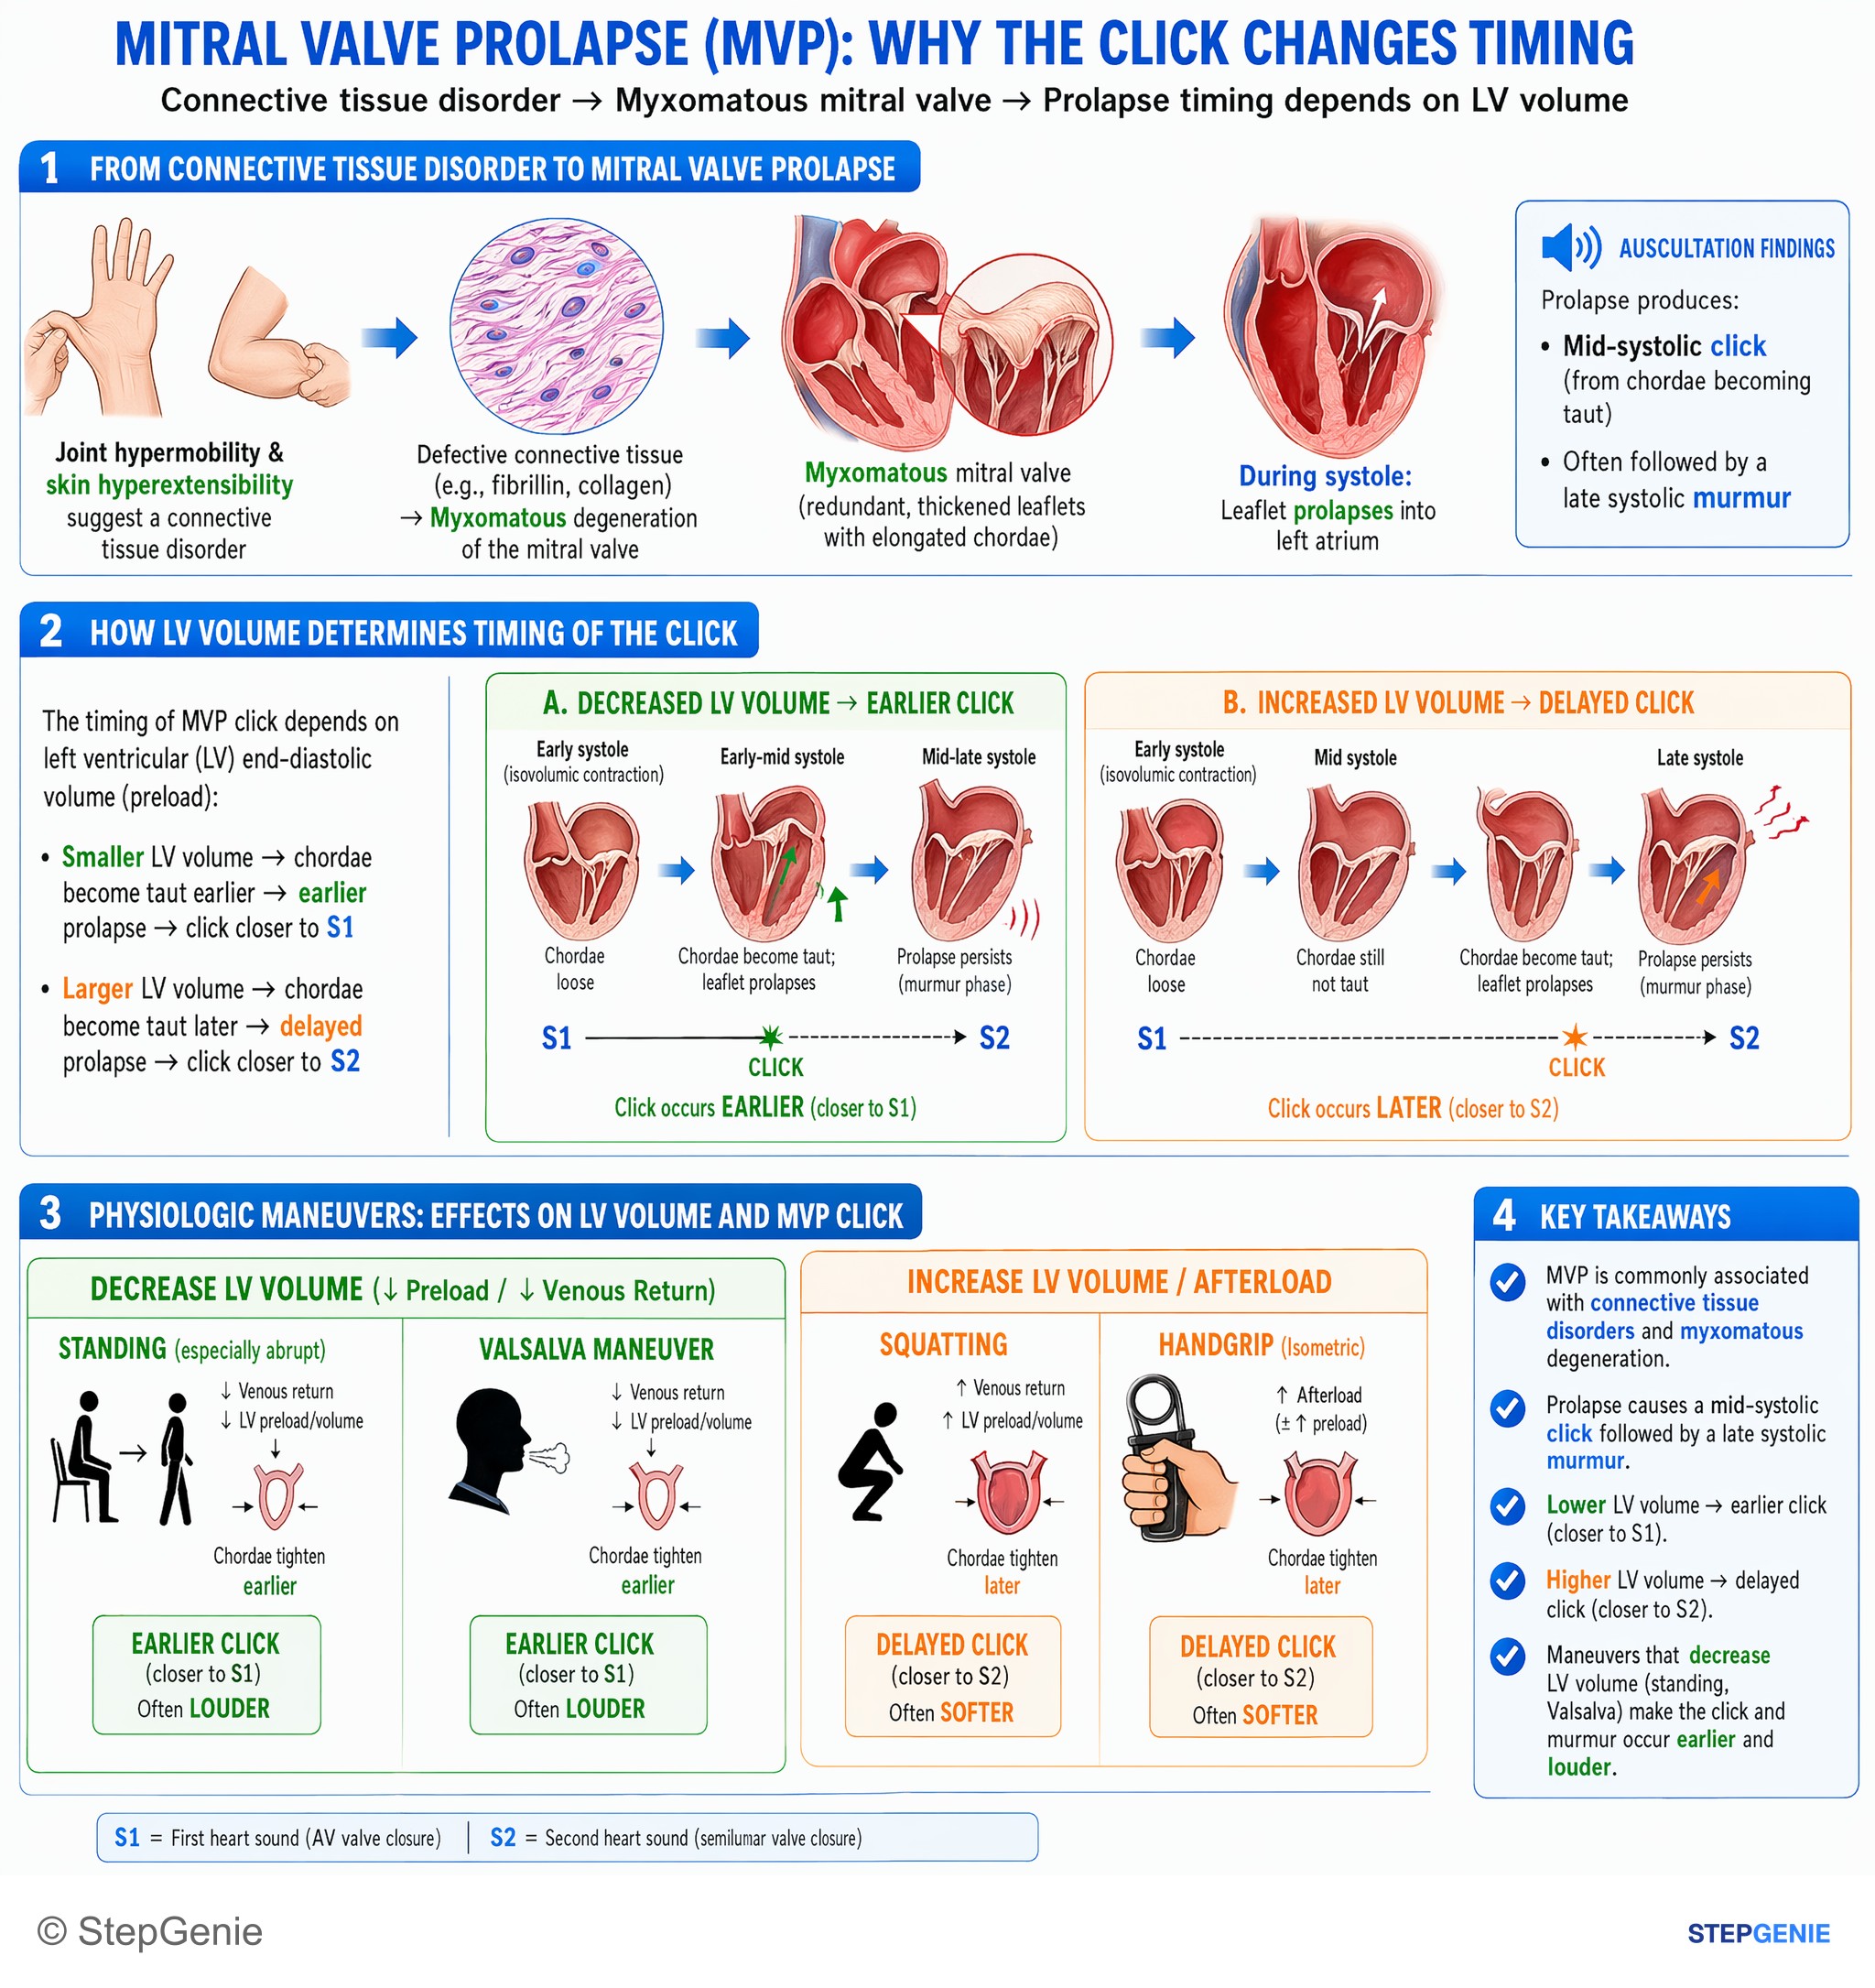
Mitral valve prolapse: myxomatous valve in connective tissue disorder; maneuvers that decrease LV volume (standing, Valsalva) make…
USMLE Step 1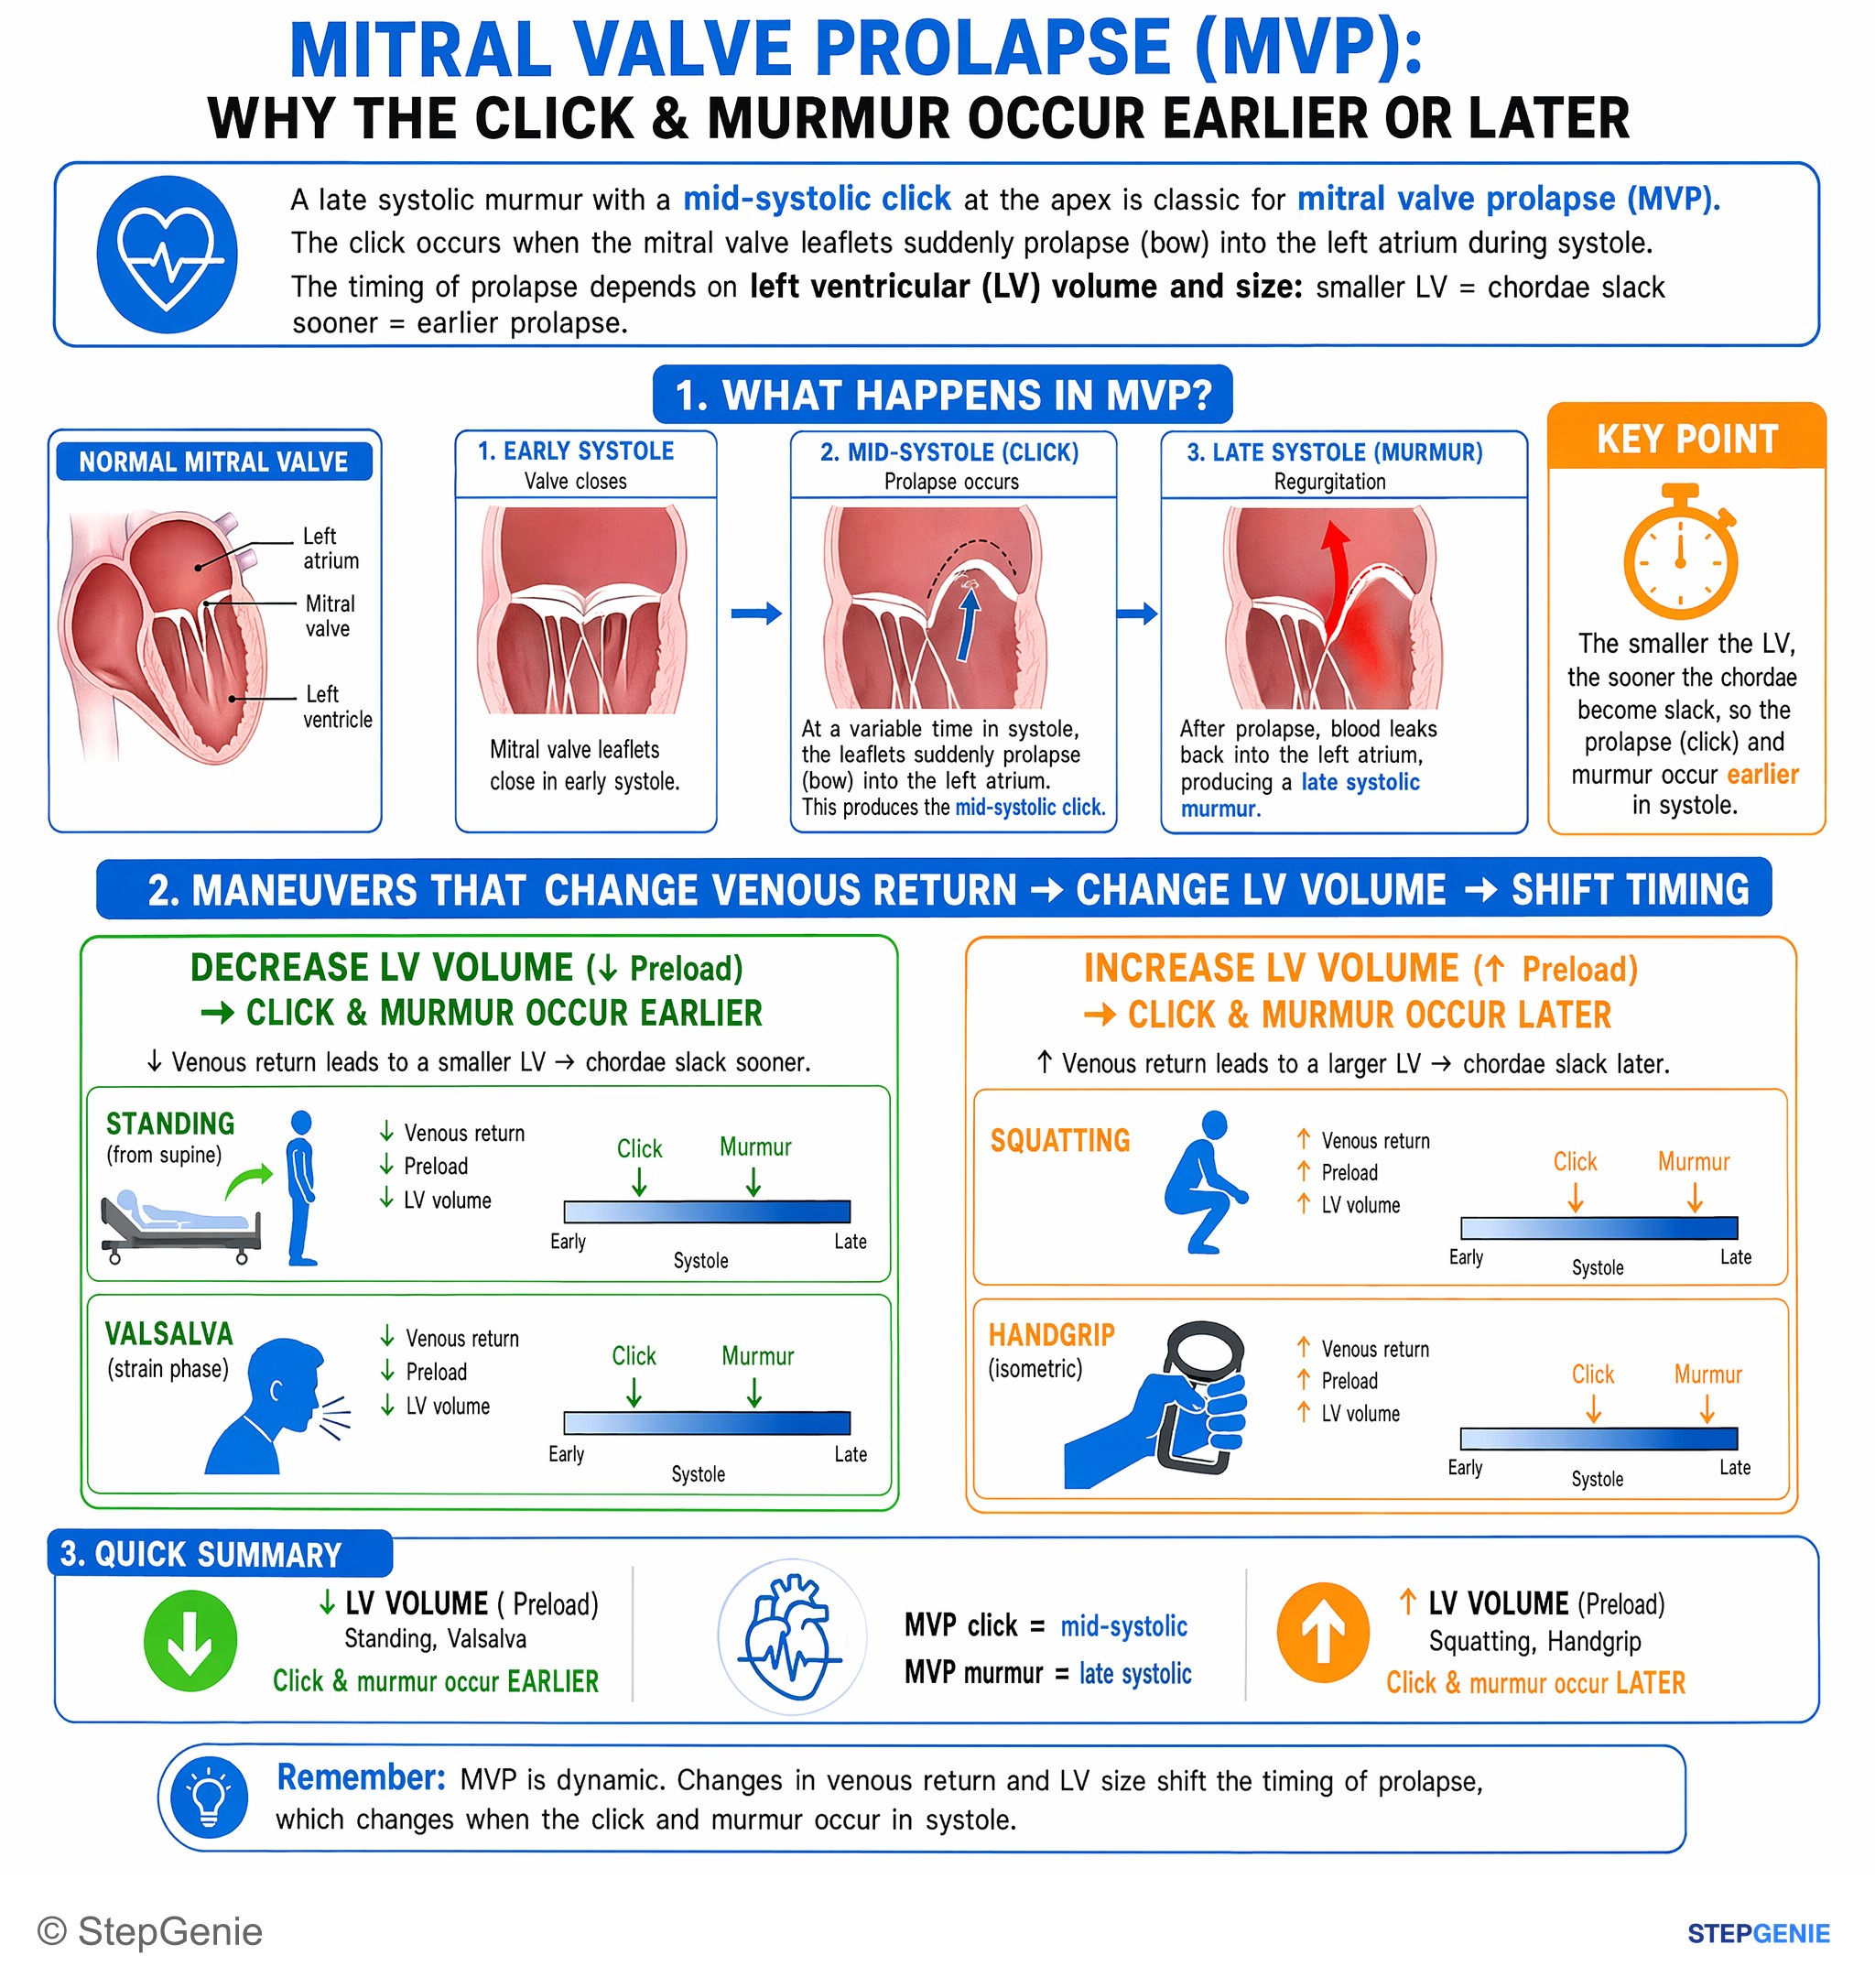
Mitral valve prolapse click/murmur occur earlier with maneuvers that ↓LV volume (standing, Valsalva) and later with maneuvers that ↑LV…
USMLE Step 1Frequently Asked Questions
What causes the midsystolic click in mitral valve prolapse?
In mitral valve prolapse, myxomatous degeneration makes the leaflets thick and redundant and the chordae long and thin. As the left ventricle contracts, the floppy leaflet billows into the left atrium until the leaflet and chordae suddenly tense, producing a crisp midsystolic click. If the leaflets then fail to meet, mitral regurgitation begins after the click, which creates the late systolic murmur heard best at the apex.
Why does standing or Valsalva make the mitral valve prolapse click earlier?
Standing and the strain phase of Valsalva reduce venous return, so the left ventricle is smaller. With a smaller ventricle the redundant leaflet prolapses earlier in systole, so the click moves toward the first heart sound and the murmur becomes longer and often louder. Squatting and isometric handgrip enlarge the ventricle or raise afterload, which delays the click and shortens the murmur.
How do you tell mitral valve prolapse from hypertrophic cardiomyopathy?
Both murmurs become more prominent with standing or Valsalva, which is the classic exam trap. Mitral valve prolapse has a midsystolic click followed by a late systolic murmur at the apex. Hypertrophic cardiomyopathy has no click; its late-peaking systolic murmur is loudest at the left sternal border, softens with handgrip, squatting or leg raise, and comes with a brisk, bifid carotid pulse and often an S4.
How is mitral valve prolapse diagnosed?
Transthoracic echocardiography confirms it by showing systolic displacement of one or both mitral leaflets at least 2 mm above the mitral annular plane in the parasternal long-axis view. StatPearls defines classic prolapse by leaflets thicker than 5 mm, and Merck flags leaflets 5 mm or thicker as more extensive myxomatous change. Other views, classically the apical four-chamber, can overcall prolapse. Doppler grades any mitral regurgitation, and the study also looks for a flail segment and mitral annular disjunction. The ECG is usually normal or nonspecific.
Does mitral valve prolapse require antibiotics before dental work?
No. Under the 2021 American Heart Association statement, antibiotic prophylaxis before qualifying dental procedures is limited to the highest-risk patients: prosthetic heart valves or prosthetic material used for valve repair, previous infective endocarditis, certain congenital heart disease, and heart transplant recipients with valve regurgitation from a structurally abnormal valve. Mitral valve prolapse alone, even with regurgitation, does not qualify, but a patient whose valve has been repaired with an annuloplasty ring or replaced does.
Is mitral valve prolapse dangerous?
Usually not; most people need only reassurance. Mitral regurgitation is the most common complication and can become severe if a degenerated chorda ruptures and a leaflet segment flails. Infective endocarditis and ventricular arrhythmias are less common, and sudden cardiac death is rare, estimated at about 0.14 percent per year. Higher-risk features include bileaflet prolapse, mitral annular disjunction, inferior T-wave inversions and myocardial fibrosis on cardiac MRI.