Cardiac biomarkers are one of those Step “make-or-break” topics: you’ll see chest pain, an EKG that’s “not definitive,” and you’ll need to decide what’s happening and when it happened. Troponin and CK-MB are the core players—learn their timelines, what they actually measure, and the classic traps (renal failure, myocarditis, reinfarction), and you’ll pick up easy points on both Step 1 and Step 2.
Where biomarkers fit in coronary & ischemic heart disease
In acute coronary syndrome (ACS), plaque rupture → thrombus → reduced coronary blood flow → ischemia (reversible) and potentially infarction (irreversible myocyte necrosis).
Biomarkers rise when myocardial cell membranes lose integrity, releasing intracellular proteins into the blood. This is why biomarkers diagnose MI/infarction, not just ischemia.
Key distinction (high-yield)
- Angina (stable/unstable) = ischemia without necrosis → biomarkers typically negative
- MI (NSTEMI/STEMI) = necrosis → biomarkers positive (especially troponin)
First Aid cross-reference: Cardiovascular → Ischemic heart disease / MI, the “markers over time” figure/table is a classic.
Pathophysiology: why troponin and CK-MB rise
Troponin (TnI and TnT)
Troponin is part of the contractile regulatory complex in striated muscle:
- TnC binds calcium (not cardiac-specific)
- TnI inhibits actin-myosin interaction (cardiac-specific isoform)
- TnT binds tropomyosin (cardiac isoform used clinically)
Injury mechanism: myocyte necrosis → cytosolic troponin release (early) + structural troponin release (sustained elevation).
CK-MB
Creatine kinase (CK) exists as isoenzymes:
- CK-MM (skeletal muscle)
- CK-BB (brain)
- CK-MB (relatively more cardiac; also present in skeletal muscle)
Injury mechanism: myocyte necrosis releases CK-MB. Because it clears faster than troponin, it’s useful for detecting reinfarction.
First Aid cross-reference: Biochemistry → muscle enzymes (CK) and Cardio → MI biomarkers timeline.
The Step-friendly timeline table (must memorize)
| Biomarker | Rises after MI | Peaks | Returns to normal | Classic use |
|---|---|---|---|---|
| Troponin I/T | 3–4 hours (can be 2–3h with high-sensitivity assays) | 24–48 hours | 7–10 days (sometimes up to ~14) | Most sensitive & specific for MI |
| CK-MB | 4–6 hours | 18–24 hours | 2–3 days | Reinfarction (new rise after it normalized) |
| (Historical) Myoglobin | 1–2 hours | 6–9 hours | <24 hours | Early but nonspecific (rarely tested now) |
High-yield pearl: Troponin stays elevated so long that it can “mask” a second MI occurring a few days later → CK-MB helps because it returns to baseline sooner.
Clinical presentation: when to suspect you need biomarkers
Typical ACS symptoms
- Substernal pressure (not sharp), may radiate to left arm/jaw
- Diaphoresis, nausea/vomiting
- Dyspnea
- Symptoms often last >20 minutes and can occur at rest (unstable angina/MI)
Atypical presentations (Step 2 favorite)
- Diabetics, elderly, women: more likely dyspnea, fatigue, nausea, epigastric discomfort
- “Silent MI” can happen—still get biomarkers if suspicion is high.
Diagnosis: how biomarkers are actually used (real-world + USMLE)
MI requires more than a positive troponin
Per the 2026 Fifth Universal Definition of MI, MI is diagnosed with:
- Rise/fall of troponin with at least one value above the sex-specific 99th percentile (this is acute myocardial injury), plus evidence of ischemia, such as:
- ischemic symptoms
- new ischemic EKG changes or new pathologic Q waves
- imaging evidence of new loss of viable myocardium or a new regional wall motion abnormality in an ischemic pattern
- imaging evidence of an acute coronary pathology (e.g., coronary thrombus, dissection, spasm or embolism)
Translation for exams: a single mildly elevated troponin isn’t automatically MI—context matters.
Serial troponins are key
If initial troponin is negative but suspicion remains:
- Repeat at 3–6 hours with conventional troponin assays (institution-dependent). With high-sensitivity troponin, validated pathways retest at 1 or 2 hours (0/1-h or 0/2-h algorithms) or at 3 hours (0/3-h pathways).
STEMI vs NSTEMI vs unstable angina (what biomarkers do)
- STEMI: ST elevations (or a STEMI-equivalent pattern of acute coronary occlusion, e.g., posterior MI, de Winter T waves, or a new LBBB/RBBB with other signs of ischemia) + positive troponin
- NSTEMI: no ST elevation but positive troponin
- Unstable angina: no ST elevation and troponin negative (or not above diagnostic threshold)
First Aid cross-reference: ST elevation MI vs NSTEMI vs unstable angina chart; treatment algorithms section.
Troponin: the nuance USMLE likes
When troponin is elevated without MI (common traps)
Troponin indicates myocardial injury, not necessarily a primary (type 1) plaque-rupture MI.
High-yield causes:
- Myocarditis (often post-viral; chest pain, maybe diffuse ST elevation; can mimic MI)
- Heart failure exacerbation
- Tachyarrhythmias (demand ischemia)
- Pulmonary embolism (RV strain can bump troponin)
- Sepsis/critical illness
- Renal failure (CKD/ESRD): especially troponin T can be chronically elevated
- Cardiac contusion (trauma)
- Takotsubo cardiomyopathy (stress-induced)
Step move: If you see elevated troponin + normal coronaries or clear alternative cause, think “injury” rather than classic MI.
Primary (type 1) vs secondary (type 2) MI (Step 2 framing)
The 2026 Fifth Universal Definition replaced the numbered types with primary, secondary and procedure-related MI; exams may still say type 1/type 2.
- Primary MI (formerly type 1): spontaneous MI from an acute coronary pathology—usually plaque rupture + thrombus (classic ACS), but also spontaneous coronary artery dissection, coronary embolism or vasospasm (all type 2 under the 2018 definition)
- Secondary MI (formerly type 2): supply-demand mismatch from another acute illness (anemia, tachycardia, hypotension, hypoxia); it can raise troponin, but it counts as MI only with ischemic features, and imaging confirms it by showing obstructive CAD (without an acute coronary lesion) or a new regional wall motion abnormality/loss of viable myocardium in an ischemic pattern—if imaging shows neither, it is acute myocardial injury, not MI
CK-MB: why it still matters
Reinfarction
If a patient had an MI and then has new chest pain 2 days later:
- Troponin may still be elevated from the first event.
- A second rise in CK-MB after it had begun to fall (or after normalization) supports reinfarction (the classic Step 1 answer).
- In current practice the Universal Definition uses serial troponin instead: a new rise suggests reinfarction, and the 2026 fifth edition says CK-MB “adds cost without providing diagnostic clarity.”
False positives / limitations
Because CK-MB exists in skeletal muscle too:
- Skeletal muscle injury (trauma, rhabdomyolysis) can elevate CK-MB
- Less specific than troponin overall
Treatment: what you do while biomarkers are pending
On exams, you treat suspected ACS based on clinical suspicion and EKG, not waiting for labs.
Immediate ACS management (high-yield scaffold)
Common Step mnemonic: MONA-B (not perfect, but helps structure)
- Morphine: for pain refractory to nitrates (use carefully; can mask symptoms)
- Oxygen: only if hypoxemic (modern practice; Step often still mentions O2)
- Nitrates: relieve ischemic pain (contraindicated with hypotension, RV infarct, PDE-5 inhibitors)
- Aspirin: reduces mortality (antiplatelet)
- Beta-blocker: decreases myocardial oxygen demand (avoid in acute decomp HF, bradycardia, shock)
Add:
- P2Y12 inhibitor (clopidogrel/ticagrelor) for ACS
- Anticoagulation (heparin) for NSTEMI/unstable angina; also used in many STEMI protocols pre-PCI
- High-intensity statin
- Reperfusion for STEMI: PCI preferred; thrombolysis if PCI unavailable within recommended time window and no contraindications
First Aid cross-reference: Pharm: antianginals, antiplatelets, anticoagulants; Cardio: MI management and complications.
High-yield associations & classic question stems
1) “Chest pain + normal EKG + early presentation”
- Troponin may be negative if very early.
- Repeat serial troponins; manage clinically if suspicion high.
2) “Troponin elevated + diffuse ST elevations”
- Think myocarditis or pericarditis (pericarditis classically has diffuse ST elevation + PR depression; troponin can be mildly elevated if myopericarditis).
3) “Kidney disease + chronically elevated troponin”
- Don’t anchor on a single value; look for dynamic change (rise/fall) and ischemic context.
4) “Second MI a few days later”
- Troponin still high from the first MI → use CK-MB (or look for a significant delta troponin depending on the question).
5) “Timing questions”
If they ask when it peaks/returns to normal:
- Troponin: peaks ~1–2 days, normal in 7–10 days
- CK-MB: normal in 2–3 days
Quick comparison: troponin vs CK-MB (Step 1-friendly)
| Feature | Troponin | CK-MB |
|---|---|---|
| Specificity for cardiac muscle | High (esp TnI) | Moderate |
| Sensitivity for MI | Highest | Lower than troponin |
| Duration of elevation | Long (days) | Short (2–3 days) |
| Reinfarction | Current method: a new rise on serial testing | Classic exam answer (normalizes in 2–3 days) |
| Common non-MI elevations | CKD, sepsis, PE, myocarditis, HF | Skeletal muscle injury, surgery/trauma |
Rapid-fire Step takeaways (memorize these)
- Troponin is the best overall biomarker for MI (sensitive + specific).
- CK-MB is the classic exam answer for reinfarction because it returns to baseline in 48–72 hours; current practice (2026 Universal Definition) looks for a new rise in serial troponin instead.
- Biomarkers diagnose necrosis, not mere ischemia—unstable angina usually has negative troponin.
- Elevated troponin ≠ always plaque rupture MI; think myocardial injury causes (CKD, myocarditis, PE, sepsis).
- If presentation is early and troponin is negative, repeat—don’t prematurely rule out MI.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
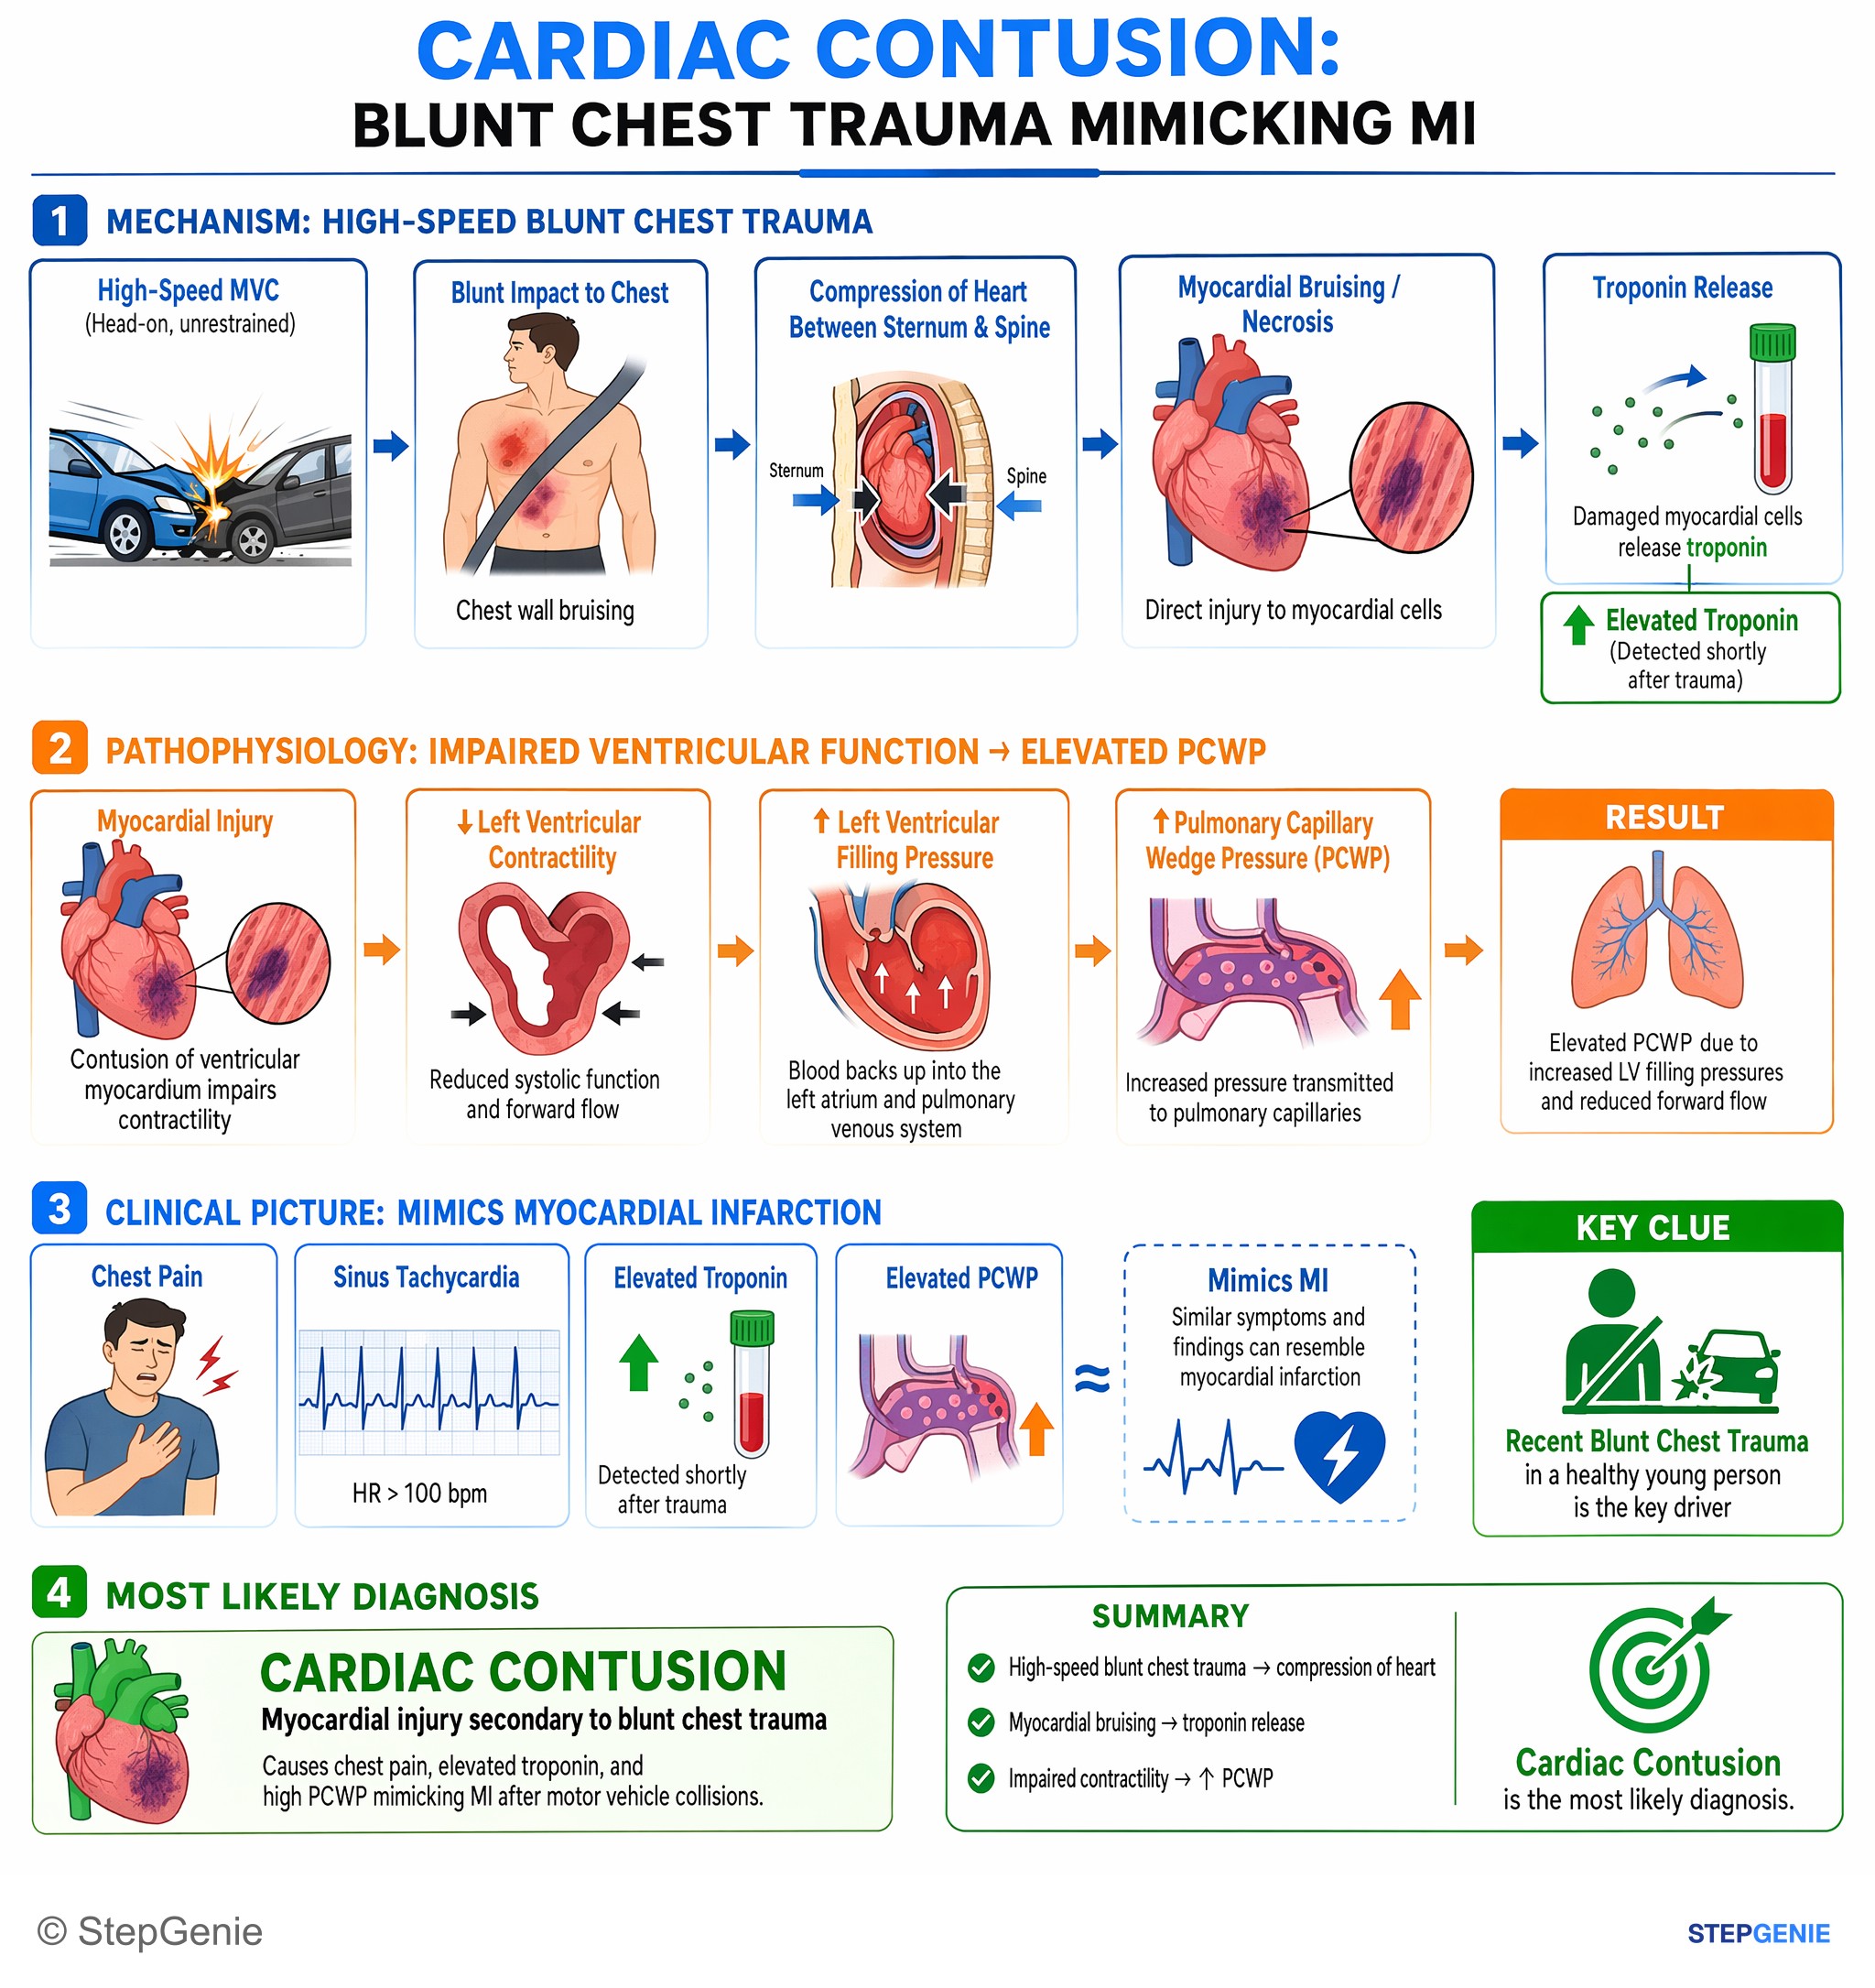
Cardiac contusion from blunt chest trauma causes chest pain, elevated troponin, and high PCWP mimicking MI after motor vehicle collisions.
USMLE Step 2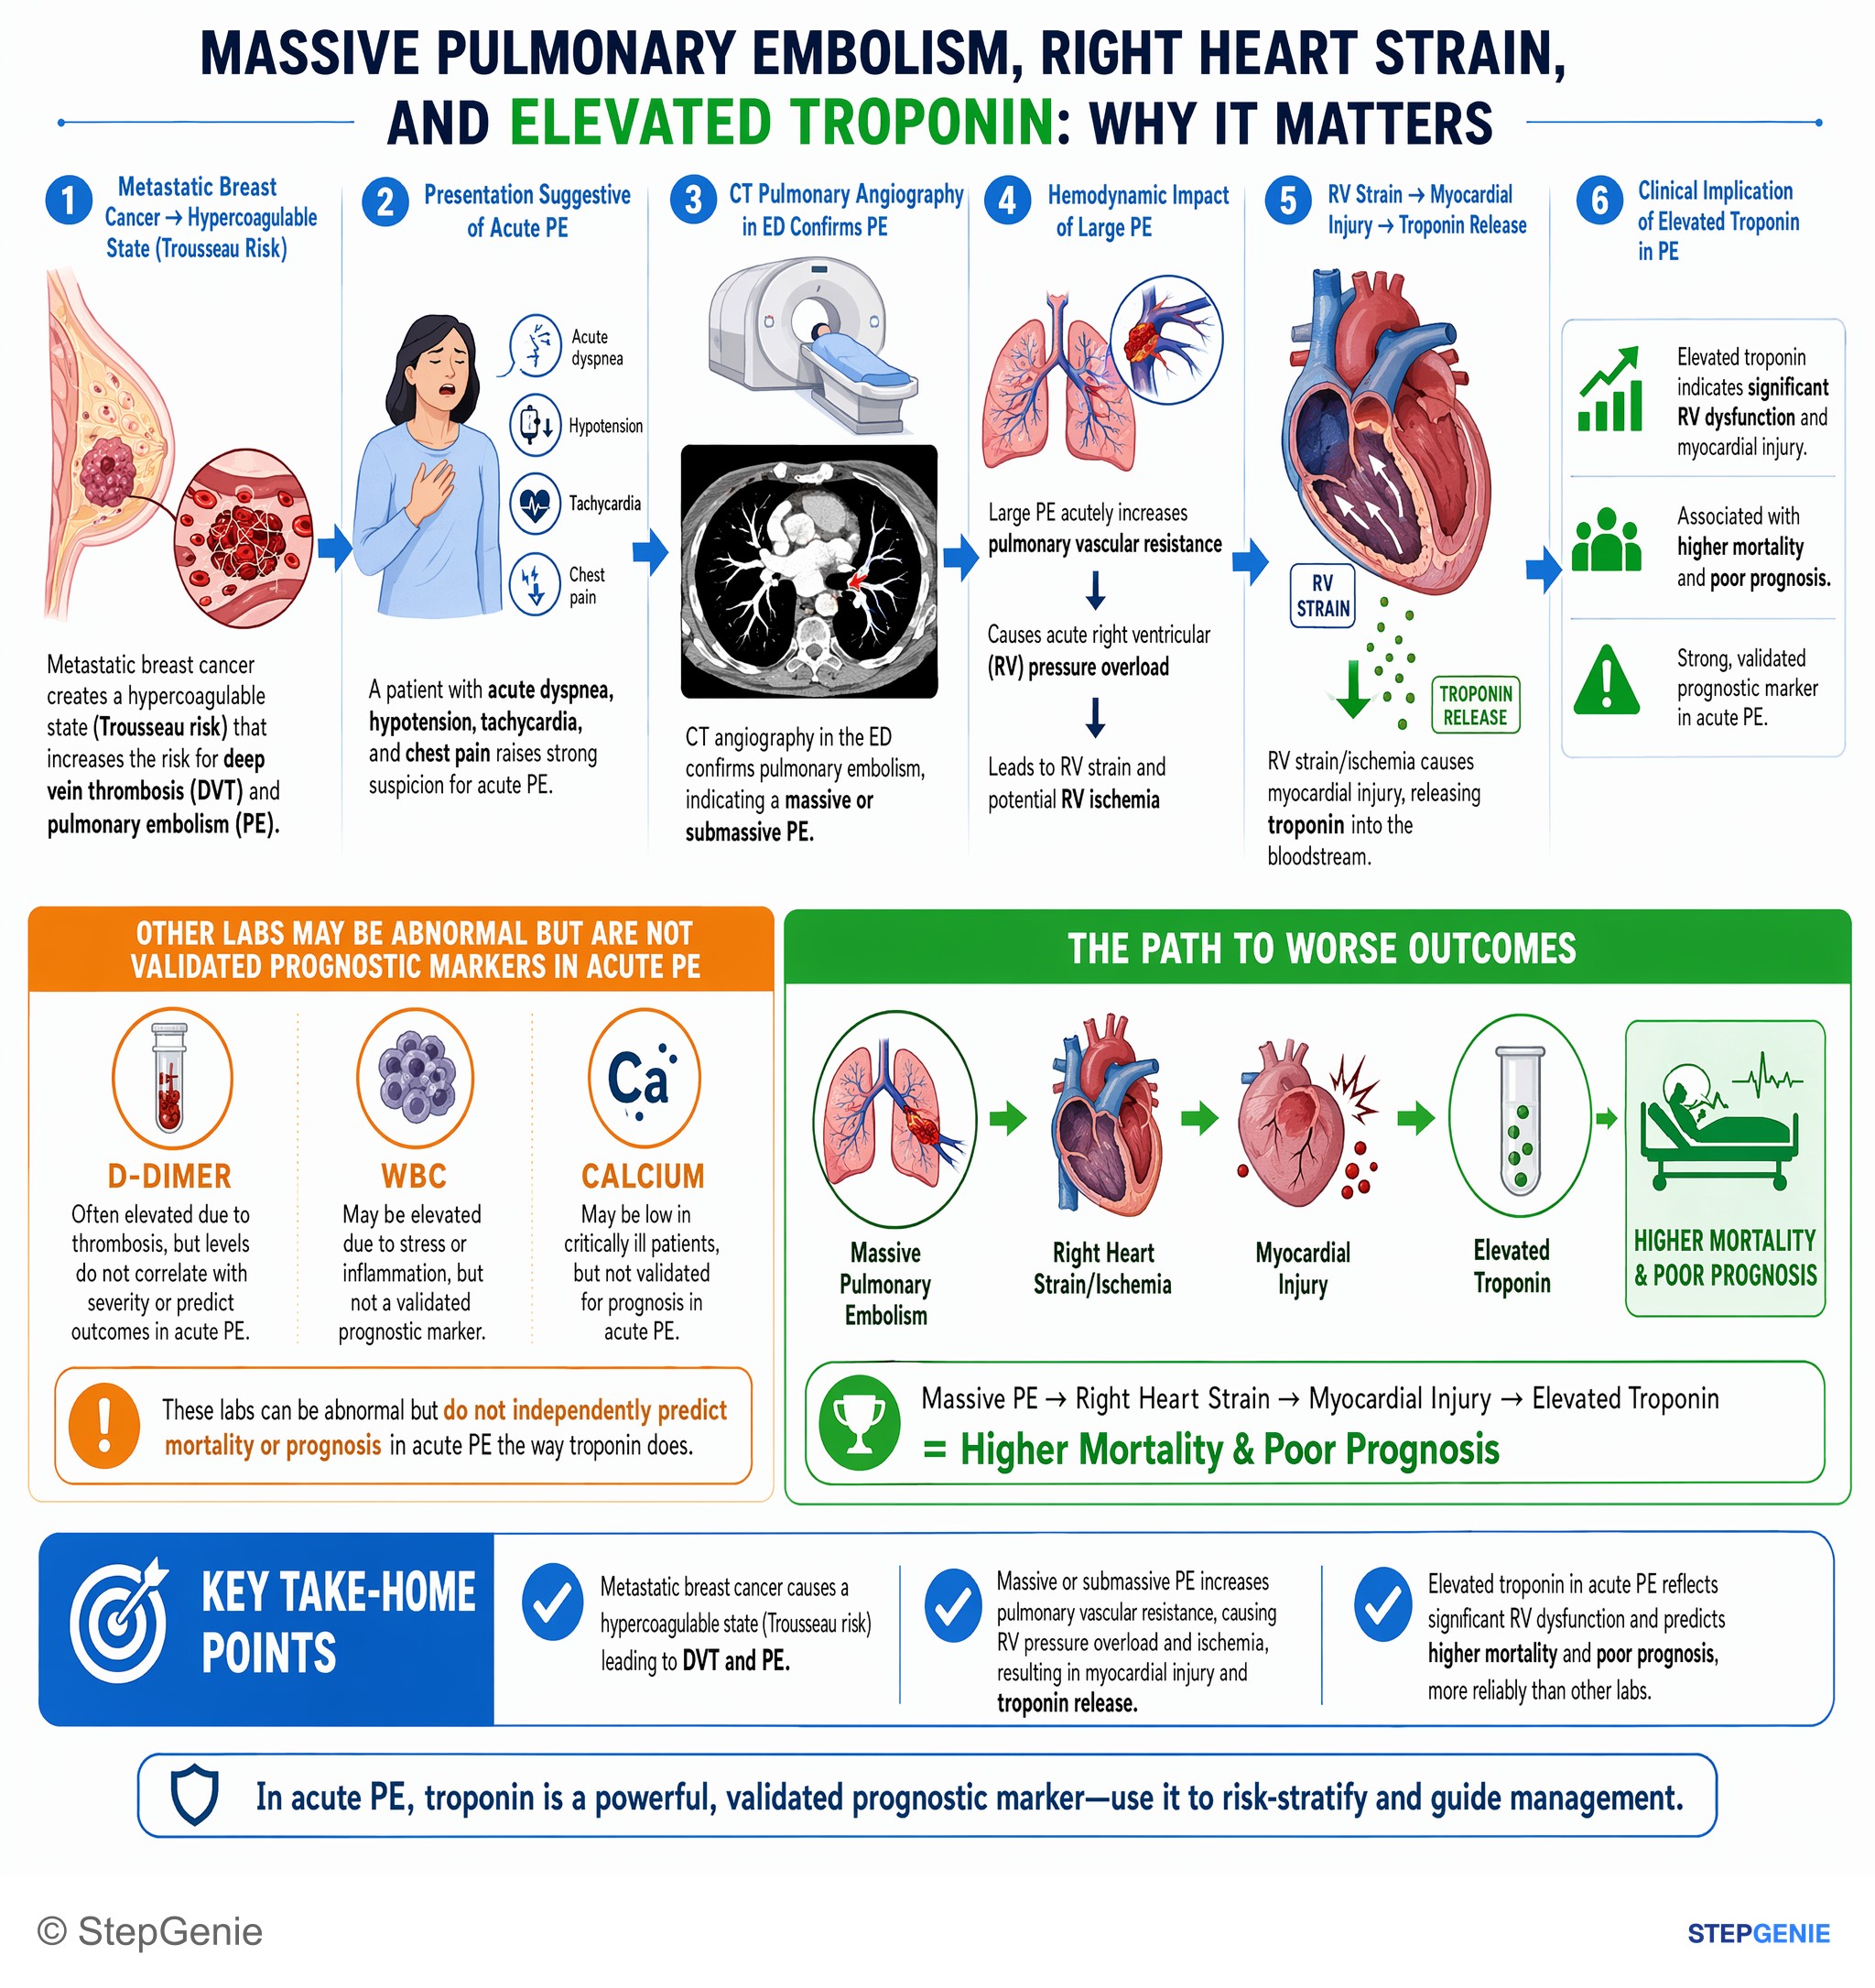
Massive pulmonary embolism with right heart strain can cause myocardial injury; elevated troponin predicts worse prognosis and higher…
USMLE Step 2Frequently Asked Questions
Why are troponin and CK-MB positive in MI but usually negative in angina?
They are positive in MI because myocardial necrosis causes cardiac myocyte membranes to lose integrity and release intracellular proteins into the blood. Angina represents ischemia without necrosis, so biomarkers are typically negative. This is the key distinction: biomarkers diagnose infarction rather than ischemia alone, which is why NSTEMI and STEMI are biomarker-positive but unstable angina is not.
How do you tell reinfarction from persistent troponin elevation after a recent MI?
On Step 1, the classic answer is CK-MB, because it returns to normal much sooner than troponin. Troponin can stay elevated for 7 to 10 days, sometimes up to about 14 days, so it may remain positive from the first infarct and mask a second event. CK-MB rises in 4 to 6 hours, peaks in 18 to 24 hours, and normalizes in 2 to 3 days, making a new rise helpful for reinfarction. In current practice, the 2026 Fifth Universal Definition relies on serial troponin instead: a new rise suggests recurrence, and CK-MB adds cost without providing diagnostic clarity.
Can an elevated troponin happen without a classic plaque-rupture MI?
Yes, an elevated troponin indicates myocardial injury, not automatically a primary (type 1) plaque-rupture MI. High-yield causes include myocarditis, heart failure exacerbation, tachyarrhythmias, pulmonary embolism, sepsis or critical illness, renal failure, cardiac contusion, and Takotsubo cardiomyopathy. Elevated troponin with normal coronaries or a clear alternative cause should make you think myocardial injury rather than classic acute coronary syndrome.
How do you differentiate STEMI, NSTEMI, and unstable angina using biomarkers?
STEMI and NSTEMI both have positive troponin because both involve myocardial necrosis, while unstable angina is troponin negative because it is ischemia without infarction. STEMI has ST elevations on EKG, or a STEMI-equivalent pattern of acute coronary occlusion such as a posterior MI or a new LBBB or RBBB with other signs of ischemia, plus positive troponin. NSTEMI has no ST elevation but still has positive troponin. Unstable angina has no ST elevation and troponin that is negative or below the diagnostic threshold.
Do you wait for troponins before treating suspected acute coronary syndrome on exams?
No, you do not wait for biomarkers before treating suspected acute coronary syndrome. On exams, management is based on clinical suspicion and the EKG while biomarkers are still pending. Biomarkers help confirm infarction and timing, but urgent treatment decisions in suspected ACS depend first on the patient’s presentation and electrocardiographic findings.