Cardiogenic shock is one of those Step questions where the “right” answer is only half the game—the real points come from proving why the other choices are wrong. The vignette will hand you a crashing patient and five interventions; your job is to match physiology to management fast.
Clinical Vignette (Q-bank style)
A 68-year-old man with a history of hypertension and hyperlipidemia presents with severe chest pressure and dyspnea. He is diaphoretic and confused. Vitals: T 37°C, HR 122/min, BP 78/52 mm Hg, RR 28/min, SpO₂ 90% on room air. Exam shows cool, clammy extremities, delayed capillary refill, jugular venous distension, and bilateral crackles. ECG shows ST-segment elevations in leads V2–V5. Bedside ultrasound: markedly reduced LV systolic function.
Labs: lactate 5.2 mmol/L.
A pulmonary artery catheter is placed and shows: PCWP 26 mm Hg, cardiac index 1.6 L/min/m², SVR elevated.
Question: Which of the following is the most appropriate next step in management?
A. High-dose IV furosemide
B. IV norepinephrine and dobutamine
C. Large-volume IV normal saline bolus
D. IV sodium nitroprusside
E. IV alteplase (tPA)
Step 1: Diagnose Cardiogenic Shock Before You Treat It
This patient has classic cardiogenic shock due to acute MI:
- Hypotension (MAP low) + signs of end-organ hypoperfusion (confusion, cool clammy skin, high lactate)
- Pulmonary edema (crackles) and JVD → volume backing up
- Hemodynamics:
- Low cardiac index (pump failure)
- High PCWP (left-sided filling pressure elevated)
- High SVR (compensatory vasoconstriction)
Hemodynamic pattern table (high-yield)
| Shock type | CO | SVR | PCWP |
|---|---|---|---|
| Cardiogenic | ↓ | ↑ | ↑ |
| Hypovolemic | ↓ | ↑ | ↓ |
| Distributive (septic/anaphylactic) | ↑ (early) / ↓ (late) | ↓ | ↓/normal |
| Obstructive (PE, tamponade, tension PTX) | ↓ | ↑ | variable (tamponade often ↑ RA pressure) |
Correct Answer: B. IV norepinephrine and dobutamine
Why this is the best next step
In cardiogenic shock, the immediate priorities are:
- Restore perfusion pressure (you can’t perfuse organs without MAP)
- Improve forward flow (increase cardiac output)
- Definitive treatment: urgent revascularization (PCI preferred) for MI-related shock
Norepinephrine is often the first-line vasopressor in cardiogenic shock because it:
- Strongly increases SVR via
- Provides some support
- Is less arrhythmogenic than dopamine (a common NBME/Step nuance)
Dobutamine is an inotrope that:
- Increases contractility via → raises cardiac output
- Mildly decreases SVR via (so you often pair it with a pressor if hypotensive)
Practical Step phrasing:
- If they’re cold and wet (congested + hypoperfused): pressor + inotrope, plus rapid reperfusion if MI.
High-yield add-on: “Cold vs Warm” HF profiles (quick triage mental model)
| Profile | Perfusion | Congestion | Typical hemodynamics | Typical acute approach |
|---|---|---|---|---|
| Warm & wet | OK | Yes | CO normal-ish, PCWP ↑ | Diuretics + vasodilators |
| Cold & wet | Poor | Yes | CO ↓, PCWP ↑ | Pressor ± inotrope, cautious diuresis, reperfusion if MI |
| Cold & dry | Poor | No | CO ↓, PCWP low/normal | Gentle fluids or inotrope (case-dependent) |
| Warm & dry | OK | No | Near normal | Optimize chronic therapy |
Why Every Other Answer Choice is Wrong (and what it would fit)
A. High-dose IV furosemide
Why it’s tempting: crackles + pulmonary edema = “diurese.”
Why it’s wrong right now: this patient is in shock. The immediate problem is low cardiac output and hypotension, not “too much fluid” in the tank.
- Aggressive diuresis can drop preload and further reduce cardiac output → worse hypotension
- In “cold & wet,” you stabilize hemodynamics first (pressors/inotropes), then carefully address volume
When furosemide is right:
- Acute decompensated HF with adequate perfusion (warm & wet) and stable blood pressure.
C. Large-volume IV normal saline bolus
Why it’s tempting: shock = “give fluids.”
Why it’s wrong: cardiogenic shock is pump failure, and he already has evidence of high filling pressures:
- PCWP 26 mm Hg (elevated)
- Pulmonary edema on exam
More fluids will worsen pulmonary edema and oxygenation without fixing the failing LV.
When fluids are right:
- Hypovolemic shock (hemorrhage, dehydration): low PCWP, flat neck veins
- Some cases of right ventricular infarct can be preload-dependent, but you’d expect clear lungs and RV findings (inferior MI pattern, hypotension with JVD but minimal crackles).
D. IV sodium nitroprusside
Why it’s tempting: afterload reduction can improve forward flow in some HF states.
Why it’s wrong: nitroprusside is a potent arterial/venous vasodilator → it drops SVR and BP, which is dangerous in someone already hypotensive (78/52).
Rule of thumb:
- Vasodilators (nitroprusside, nitroglycerin) are for hypertensive acute pulmonary edema or “warm & wet” patients who can tolerate decreased afterload.
High-yield pearl: Nitroprusside can cause cyanide toxicity (especially with prolonged infusion, renal dysfunction), presenting with metabolic acidosis, altered mental status.
E. IV alteplase (tPA)
Why it’s tempting: STEMI is present; “lyse the clot.”
Why it’s wrong in this vignette: With cardiogenic shock and STEMI, the preferred definitive management is emergent PCI when available. Fibrinolysis is typically for:
- STEMI when PCI is not available within the recommended time window (classically within ~120 minutes of first medical contact in many teaching frameworks)
- And when no contraindications exist
Also, tPA is not the immediate hemodynamic stabilizer here. This patient needs perfusion restored now (pressor/inotrope) while moving to definitive reperfusion.
Test-day nuance: If a question forces “best next step” and includes urgent PCI as an option, that often beats thrombolysis in an unstable STEMI patient—especially in shock.
What USMLE Loves You to Know About Cardiogenic Shock
Classic findings
- Cold, clammy skin (high SVR)
- Pulmonary edema, JVD
- S3 gallop (volume overload + systolic dysfunction)
- Low urine output, altered mental status
- Labs: elevated lactate, metabolic acidosis possible
Common causes (board favorites)
- Acute MI (most common)
- Acute decompensated systolic HF
- Papillary muscle rupture → acute severe MR (post-MI; loud systolic murmur + pulmonary edema)
- Ventricular septal rupture (harsh holosystolic murmur, shock)
- Fulminant myocarditis
- Life-threatening arrhythmia (VT/VF, complete heart block)
Management priorities (high-yield sequence)
- Airway/oxygenation (pulmonary edema often requires positive pressure ventilation)
- Vasopressor (often norepinephrine) to maintain MAP
- Inotrope (e.g., dobutamine) if low output persists
- Definitive therapy
- Revascularization for MI (PCI)
- Fix mechanical complications (surgery)
- Consider mechanical circulatory support (IABP, Impella, VA-ECMO) in refractory cases (test questions may hint “despite pressors/inotropes”)
Rapid “Answer Choice” Pattern Recognition
- Crackles + JVD + hypotension + cold extremities → cardiogenic shock
- Treatment pair you should think of:
- Norepinephrine (pressure) + dobutamine (pump)
If you can say out loud: “low CO, high PCWP, high SVR”, the rest of the question becomes elimination.
Key Takeaways (what to remember on exam day)
- Cardiogenic shock = pump failure → low CO with high PCWP and high SVR.
- Norepinephrine supports MAP; dobutamine improves contractility and output.
- Do not reflexively give fluids when PCWP is high and lungs are wet.
- Vasodilators are for “warm” patients with adequate BP—not for shock.
- In MI-related cardiogenic shock, stabilize hemodynamics and move toward urgent PCI.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
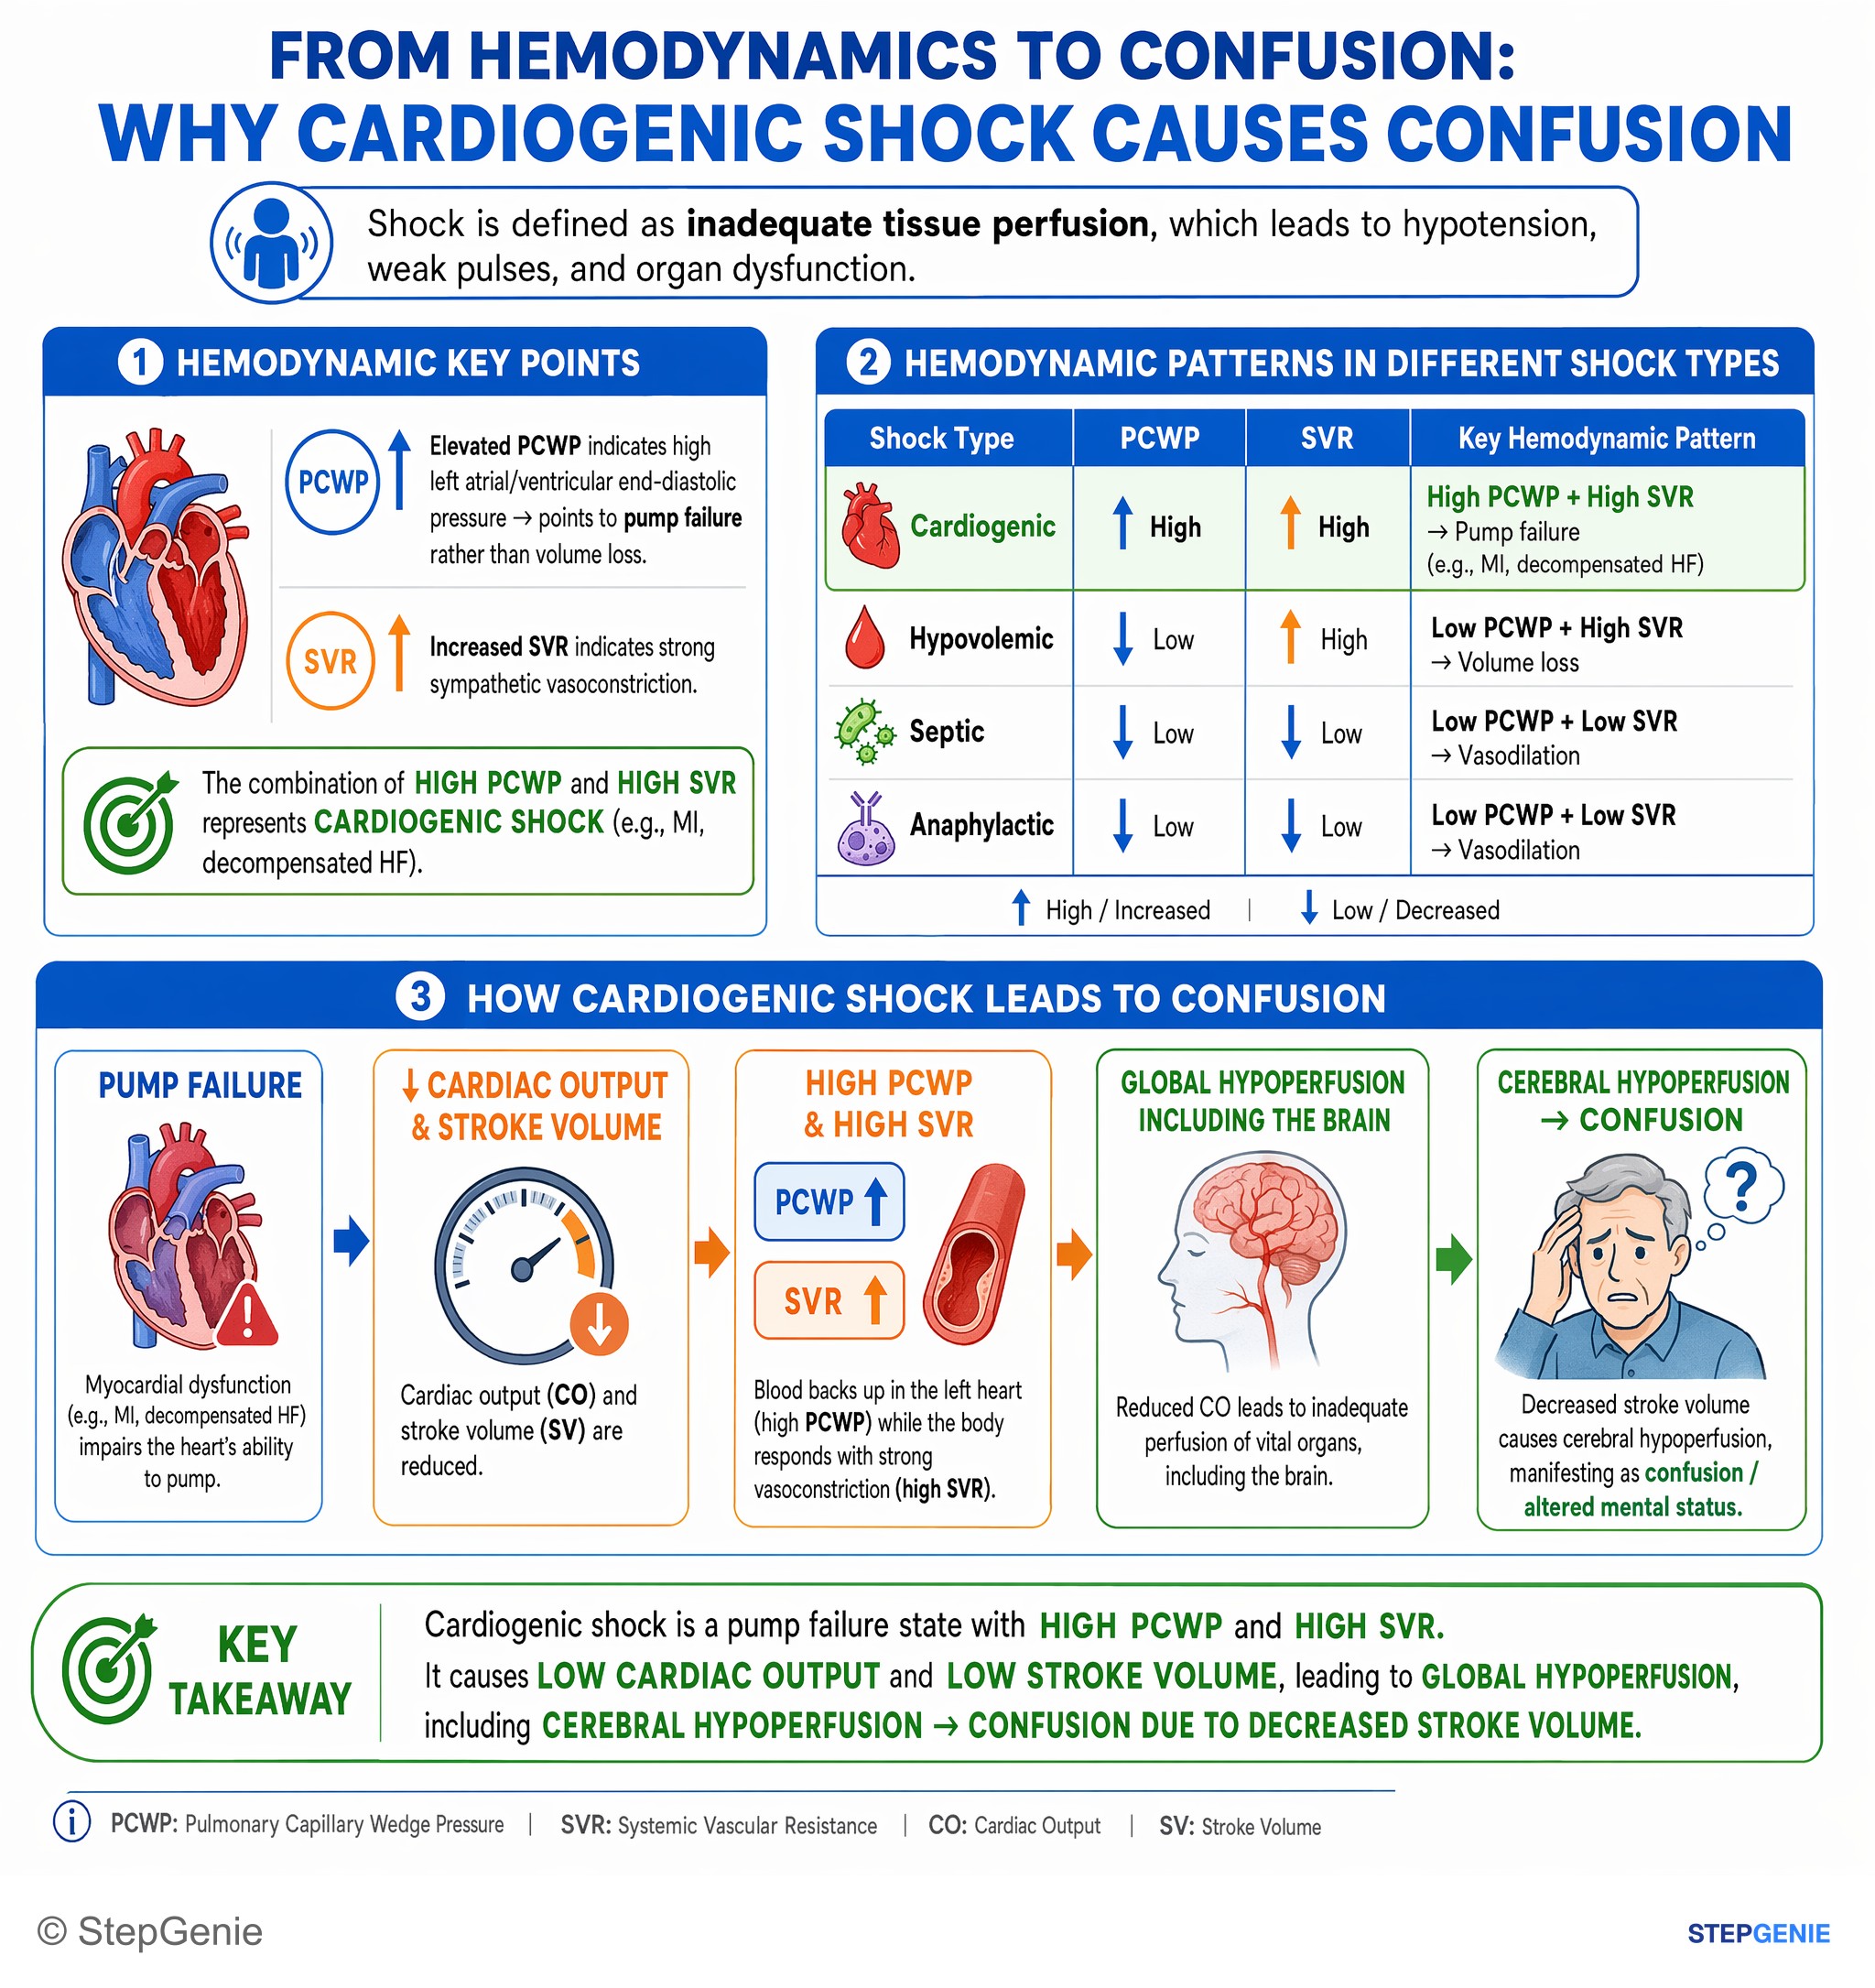
Cardiogenic shock causes low cardiac output with high PCWP and high SVR, leading to cerebral hypoperfusion and confusion from decreased…
USMLE Step 1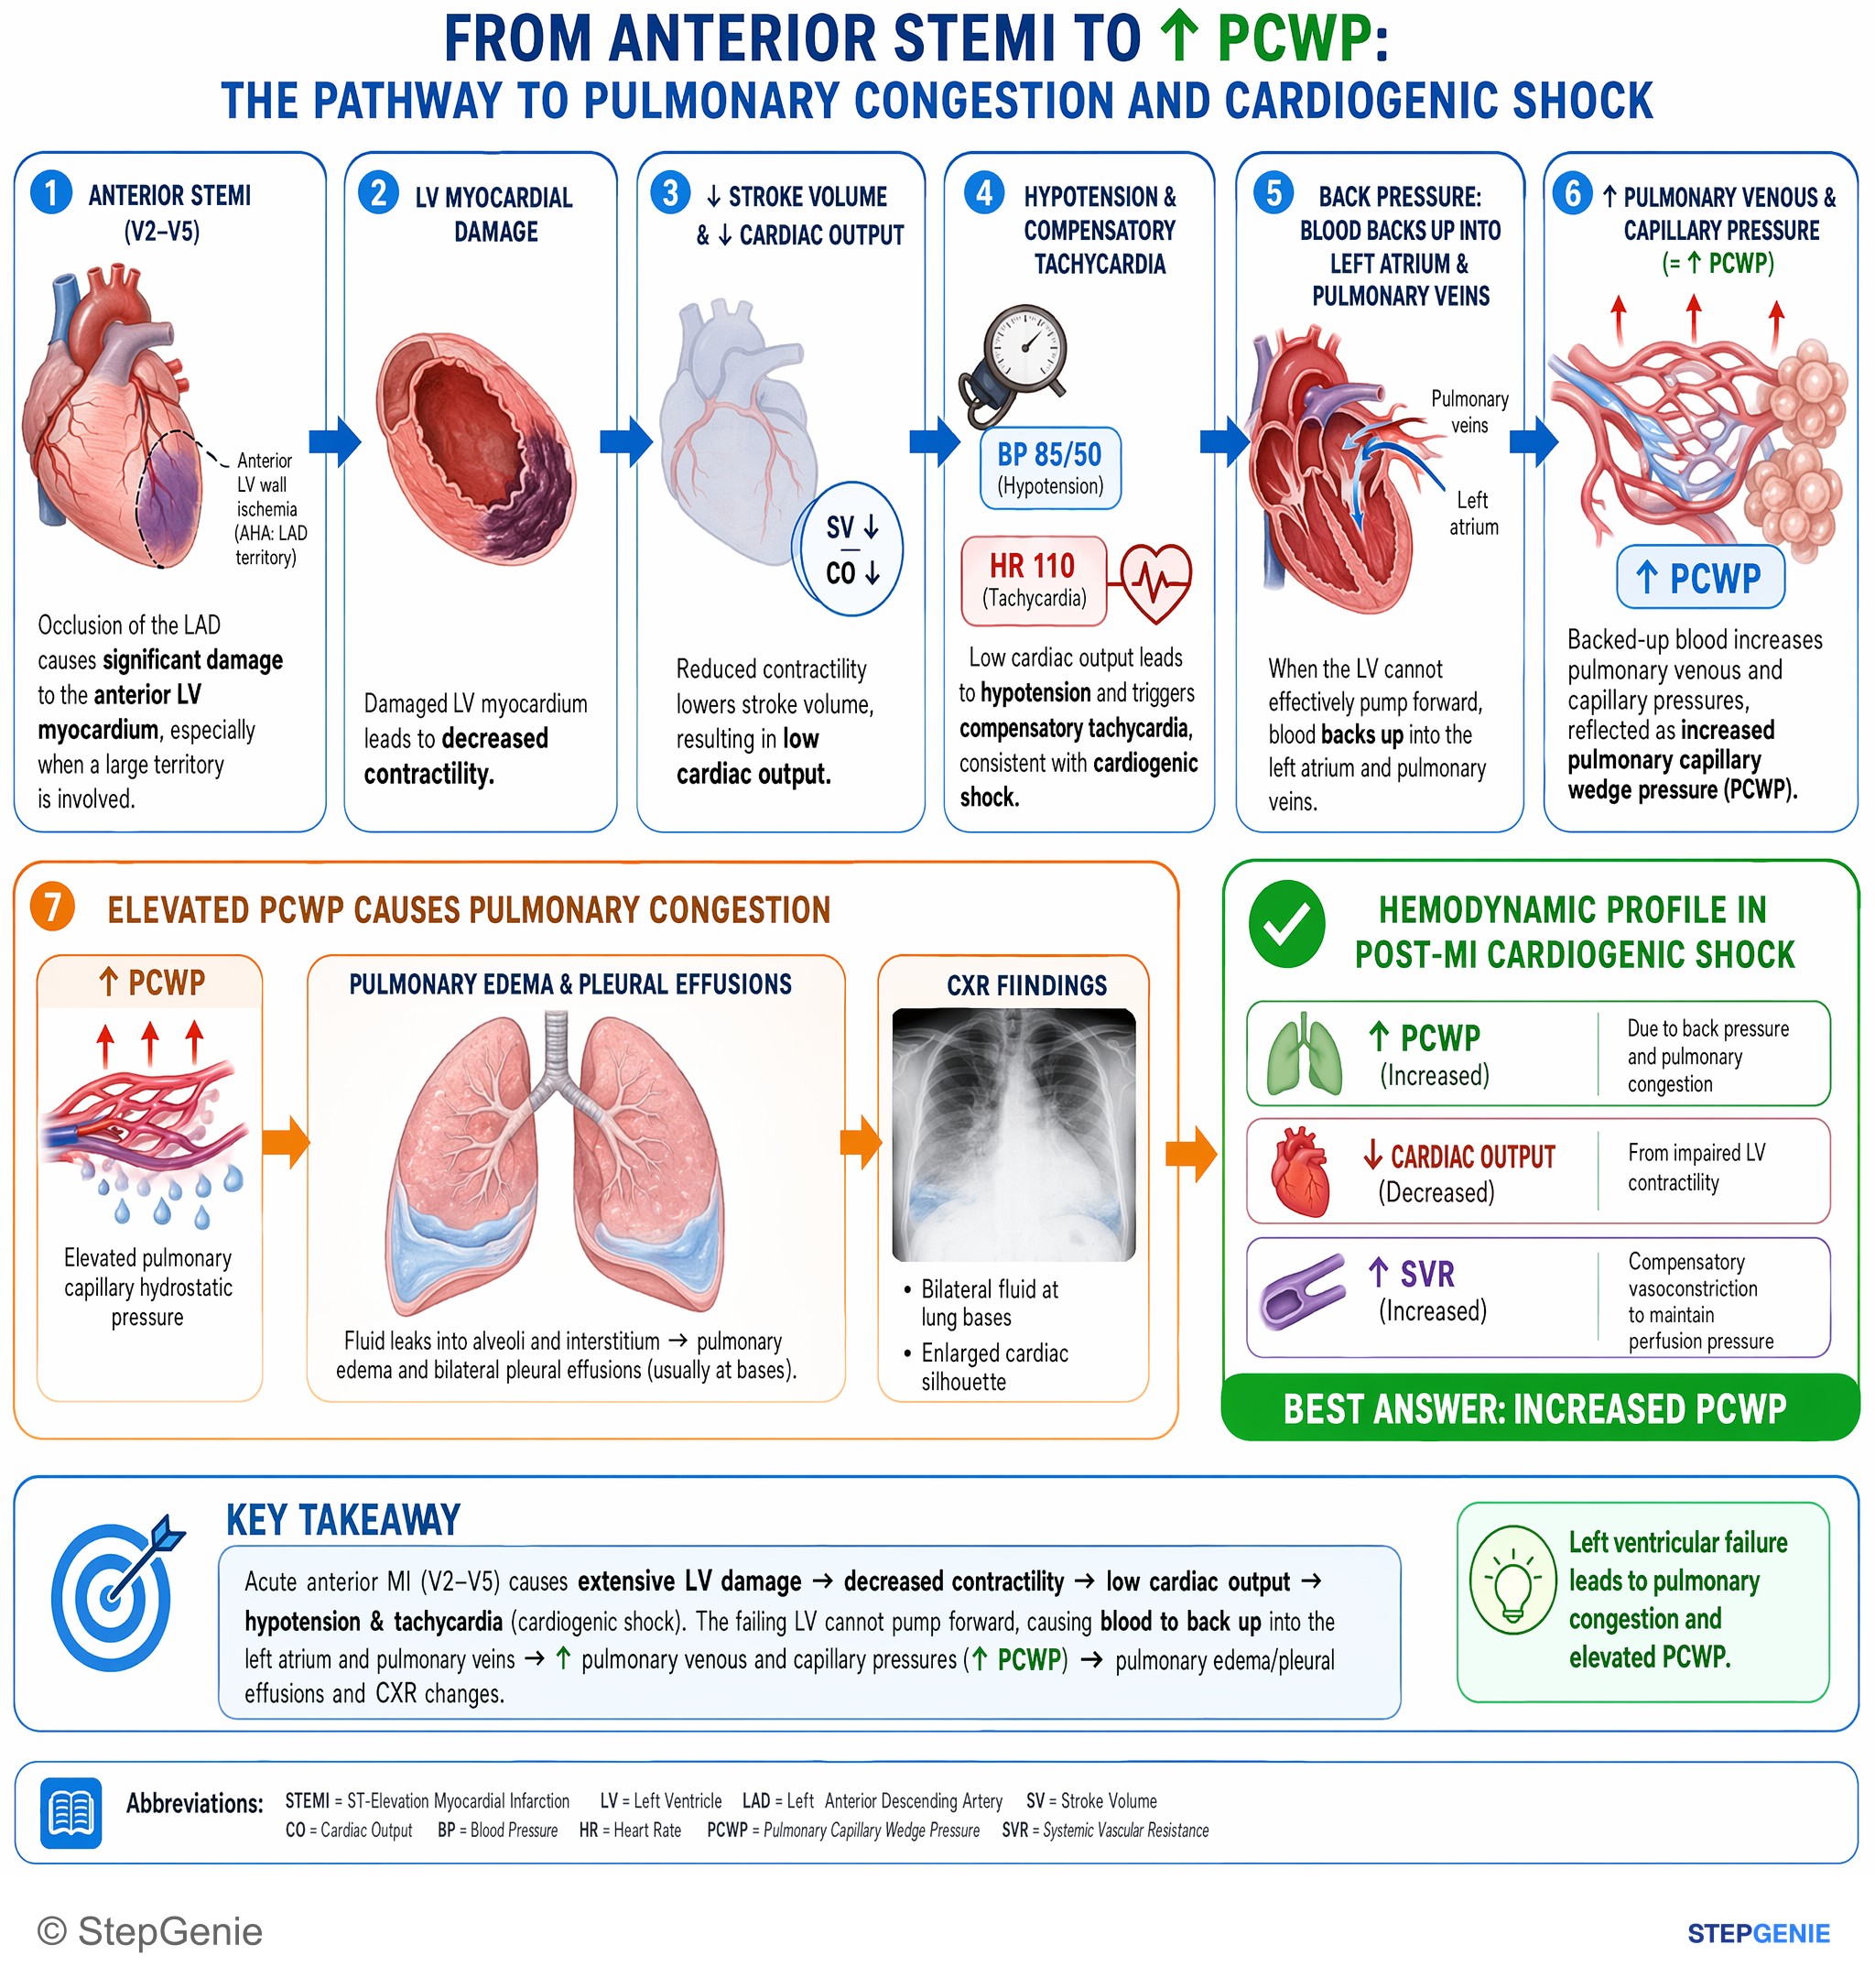
Acute anterior MI with cardiogenic shock → left ventricular failure → blood backs into lungs → elevated pulmonary capillary wedge pressure…
USMLE Step 1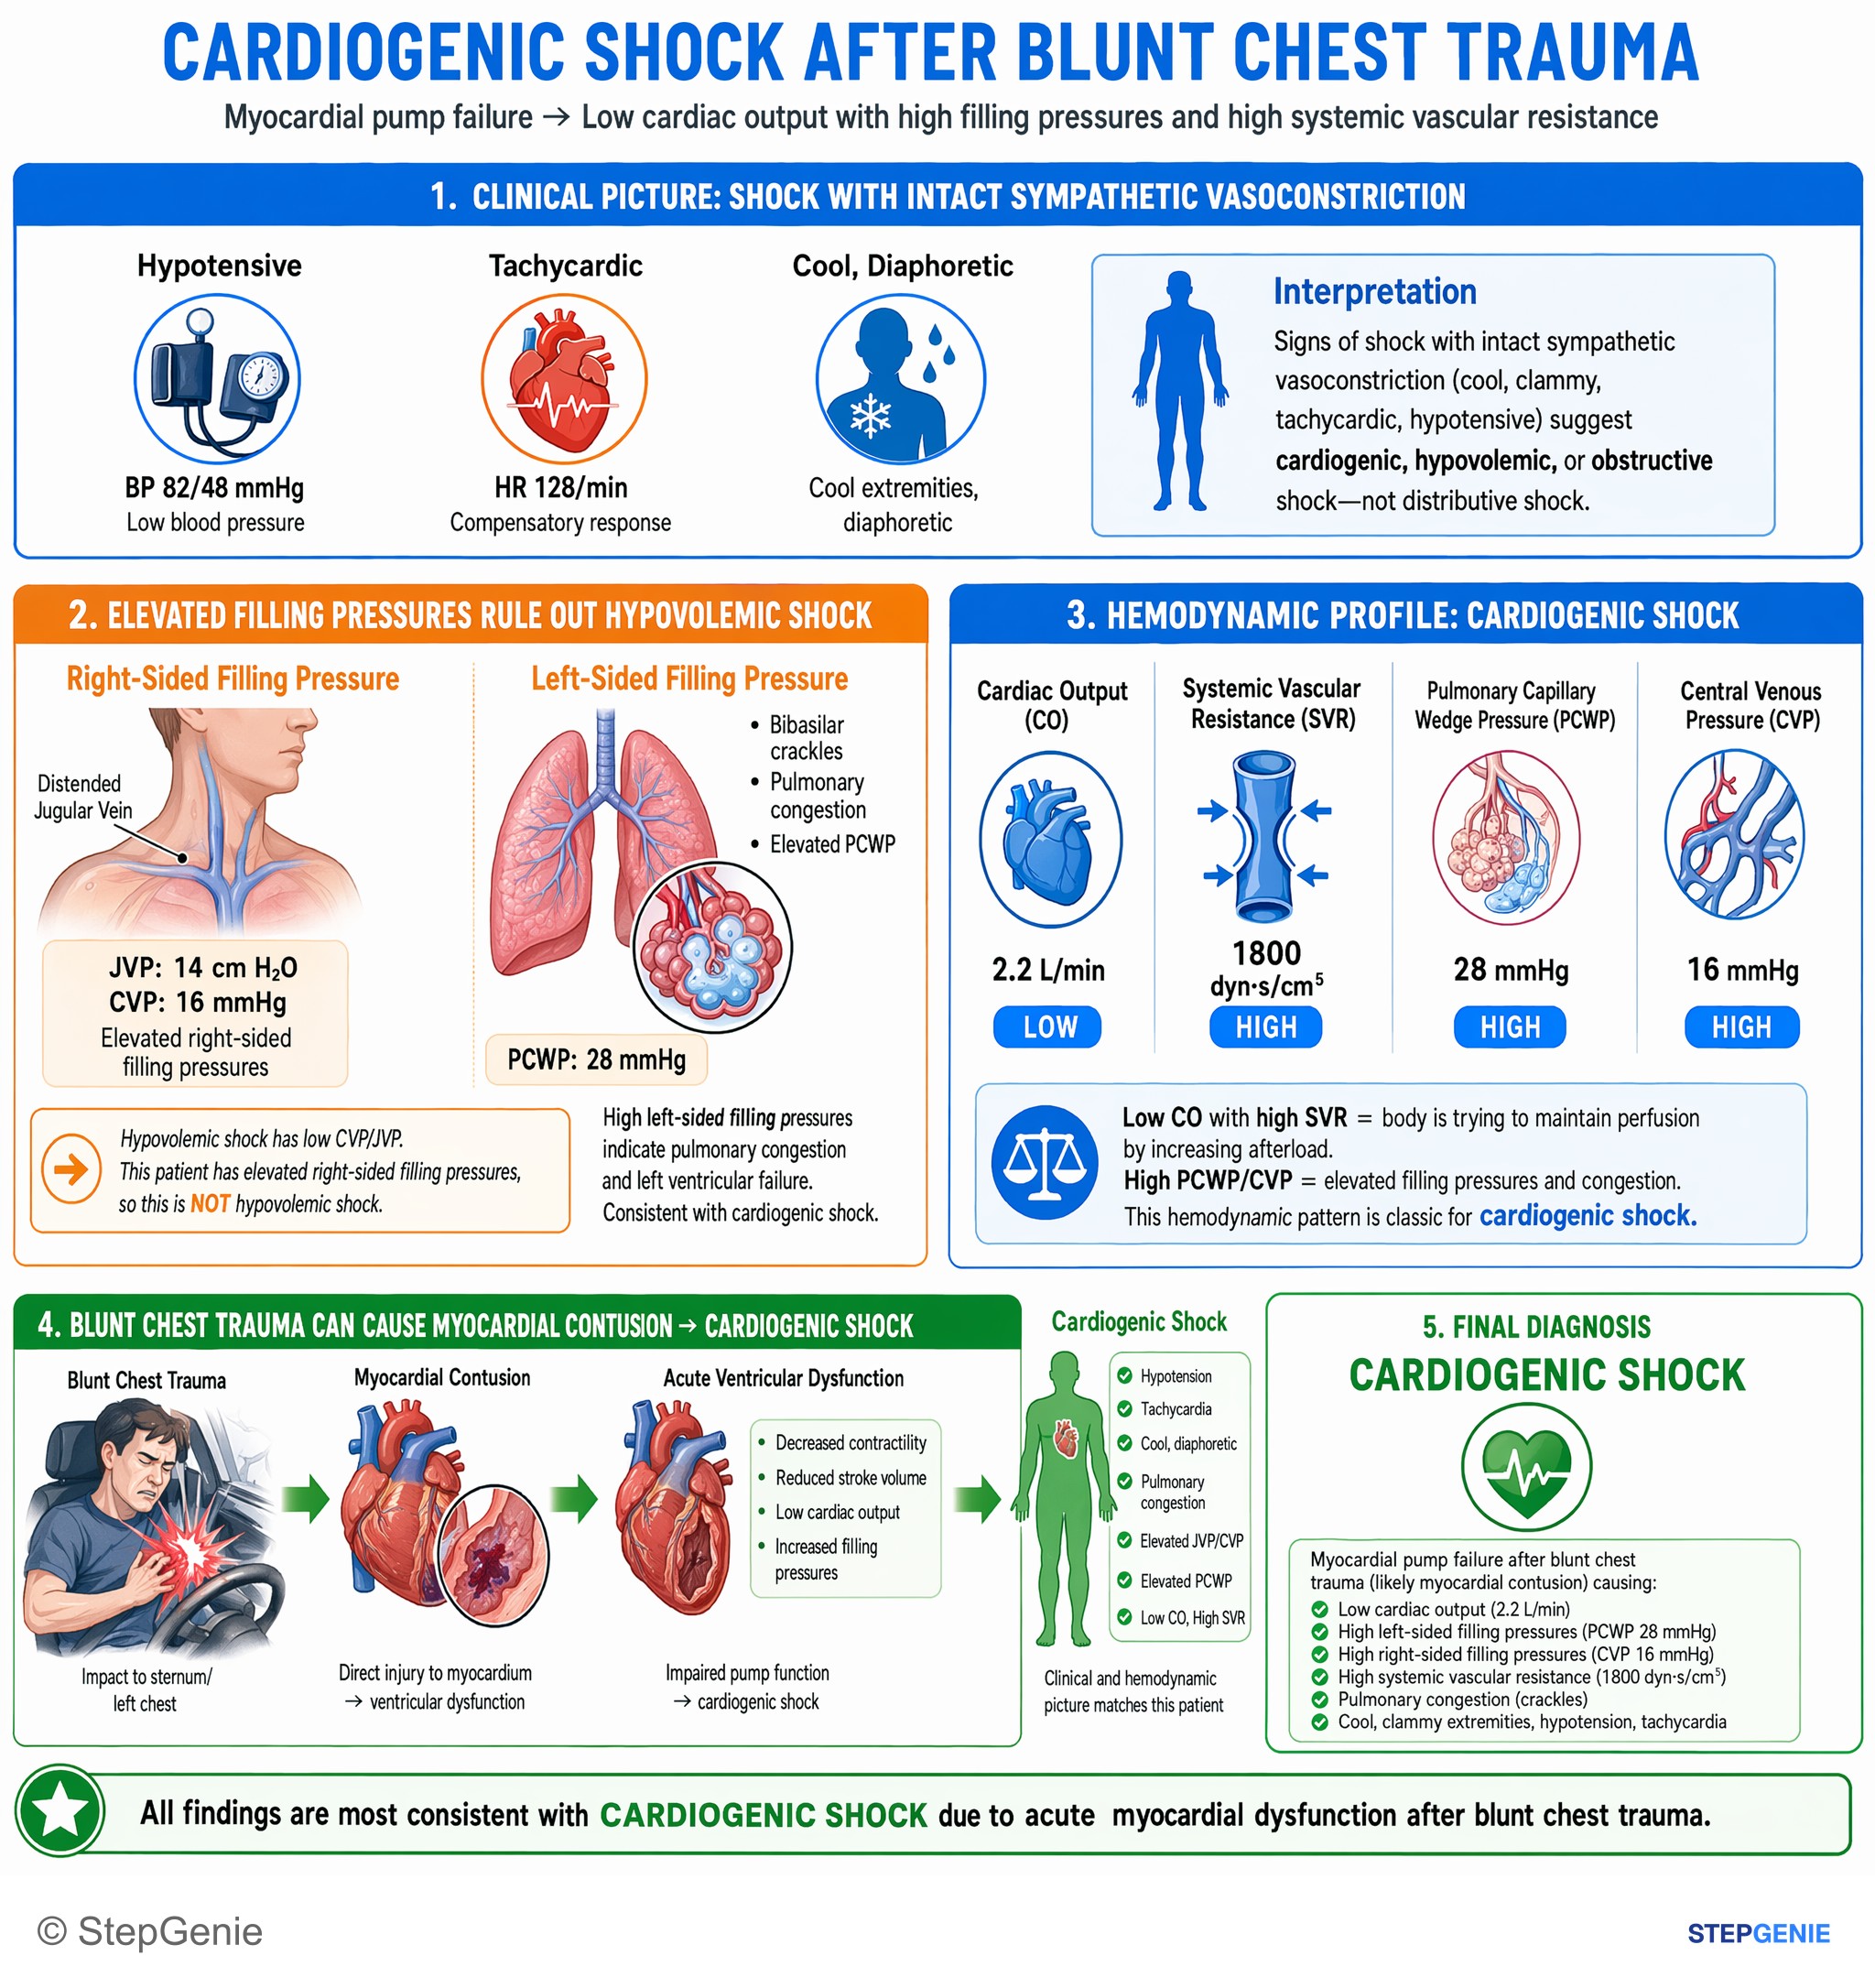
Cardiogenic shock: myocardial pump failure after blunt chest trauma → low CO, high PCWP, high SVR, cool/clammy extremities, pulmonary…
USMLE Step 2Frequently Asked Questions
How do you recognize cardiogenic shock after an acute MI on a vignette?
Cardiogenic shock after an acute MI is recognized by hypotension with end-organ hypoperfusion plus signs of volume backing up into the lungs and venous system. A typical presentation includes confusion, cool clammy skin, elevated lactate, crackles, and jugular venous distension. Hemodynamics support the diagnosis when the cardiac index is low, the PCWP is high, and the SVR is elevated, reflecting pump failure with compensatory vasoconstriction.
What is the most appropriate next step in management for MI-related cardiogenic shock?
The best next step is IV norepinephrine and dobutamine. Norepinephrine helps restore perfusion pressure by increasing SVR and also provides some beta-1 support, while dobutamine increases contractility and raises cardiac output. This combination fits the "cold and wet" profile of congestion plus hypoperfusion. In MI-related cardiogenic shock, urgent revascularization with PCI is the definitive treatment, but hemodynamic stabilization comes first.
Why is high-dose IV furosemide wrong in a patient with cardiogenic shock and pulmonary edema?
High-dose IV furosemide is wrong initially because the immediate problem is shock from low cardiac output and hypotension, not simply excess fluid. In a "cold and wet" patient, aggressive diuresis can lower preload further and worsen cardiac output, leading to even worse hypotension. Diuretics are more appropriate in acute decompensated heart failure when perfusion is adequate and blood pressure is stable, such as a "warm and wet" presentation.
Why is a large IV normal saline bolus a bad choice in cardiogenic shock?
A large IV normal saline bolus is inappropriate because cardiogenic shock is caused by pump failure, not lack of intravascular volume. This patient already has high filling pressures, shown by an elevated PCWP, along with pulmonary edema and jugular venous distension. Giving more fluid would worsen lung congestion and oxygenation without fixing the failing left ventricle. Fluids are more appropriate in hypovolemic shock, where PCWP is low and neck veins are flat.
Why isn’t IV alteplase the best immediate answer in a STEMI patient with cardiogenic shock?
IV alteplase is not the best immediate answer because STEMI with cardiogenic shock is best managed definitively with emergent PCI when available. Fibrinolysis is generally used when PCI cannot be performed within the recommended time window and there are no contraindications. It also does not provide immediate hemodynamic stabilization. In this setting, the patient first needs perfusion supported with a pressor and inotrope while being moved toward urgent reperfusion.