Pacemaker cells are the cardiac cells with automaticity: they have no stable resting potential and drift up to threshold on their own. In the SA and AV nodes the action potential has only three phases: phase 4 is the spontaneous "pacemaker potential," driven mainly by the funny current (I_f, a mixed Na+/K+ current through HCN channels that is net inward because Na+ entry dominates) plus T-type Ca2+ current; phase 0 is a slow upstroke carried by L-type Ca2+ channels (not fast Na+ channels); and phase 3 is repolarization by K+ efflux. The slope of phase 4 sets the heart rate: sympathetic (β1) stimulation steepens it, vagal (M2) stimulation flattens it and hyperpolarizes the cell. The SA node wins because it depolarizes fastest; the AV junction and the His-Purkinje system are slower backups that appear as escape rhythms.
Where the pacemakers are
| Site | Rate | Escape QRS | Key point |
|---|---|---|---|
| SA node | Resting sinus rate 60-100/min in adults; intrinsic rate about 100-110/min without vagal tone | — | Fastest phase 4, so it is the dominant pacemaker |
| AV node / junction | Junctional escape about 35-50/min (Merck); StatPearls gives 40-60/min | Narrow (above the His bifurcation) | Same slow Ca2+-dependent action potential as the SA node; reliable backup |
| His-Purkinje / ventricular | Ventricular escape about 20-40/min | Wide | Fast Na+ upstroke with only slow phase 4 pacemaker activity; unreliable, can fail into asystole |
At rest vagal tone dominates: the SA node's intrinsic rate is about 100-110/min, and continuous vagal input brings it down to the familiar 60-80/min. That is why atropine, which blocks the muscarinic receptors on the SA node, speeds the heart.
The pacemaker action potential: phases 4, 0, 3
| Phase | What happens | Main current |
|---|---|---|
| 4 (pacemaker potential) | From about −60 mV, slow spontaneous depolarization toward threshold (about −40 to −30 mV) | I_f (funny current) starts it; T-type Ca2+ joins near −50 mV; outward K+ current keeps falling |
| 0 (upstroke) | Slow depolarization, so slow conduction | L-type Ca2+ influx (opens near −40 mV) |
| 3 (repolarization) | Back down to about −60 mV | K+ efflux; L-type Ca2+ channels inactivate |
- No phases 1 or 2. Nodal cells have no notch and no plateau, and no functioning fast Na+ channels, which is why they are called "slow-response" cells.
- Why "funny"? HCN stands for hyperpolarization-activated cyclic nucleotide-gated: the channel is activated by hyperpolarization (the very negative voltage at the end of phase 3) rather than by depolarization, and cAMP boosts it, which is how sympathetic input speeds the rate.
- Hyperpolarization is required. If the cell cannot repolarize fully, the pacemaker channels are not activated and phase 4 flattens. That is why hyperkalemia and cellular hypoxia (ischemia) both depolarize nodal cells and cause bradycardia; severe hypoxia can stop pacemaker activity.
- The AV node has the same currents and its own intrinsic pacemaker activity.
Pacemaker cells vs ventricular myocytes
| Feature | SA/AV nodal cells ("slow response") | Ventricular myocytes ("fast response") |
|---|---|---|
| Resting potential | None: drifts up from about −60 mV | Stable at about −90 mV (K+ channels open) |
| Phase 0 | L-type Ca2+, slow | Fast Na+, rapid |
| Phases present | 4, 0, 3 | 0, 1 (transient outward K+), 2 (Ca2+ plateau), 3, 4 |
| Conduction | Slow | Fast |
| Refractoriness | Outlasts repolarization (long) | Ends with repolarization |
| Drugs that act mainly here | β-blockers, verapamil/diltiazem, adenosine, ivabradine | Class I Na+ channel blockers (class III K+ blockers act on both tissues) |
Purkinje fibers are the twist: they are fast-response cells with a Na+ upstroke, yet they still show slow phase 4 pacemaker activity, which is why they can generate a (slow) ventricular escape rhythm.
How heart rate is tuned: the phase 4 slope
| Sympathetic | Parasympathetic (vagal) | |
|---|---|---|
| Transmitter and receptor | Norepinephrine on β1 (Gs) | Acetylcholine on M2 muscarinic receptors |
| Second messenger | ↑ cAMP | ↓ cAMP |
| Currents | ↑ I_f and ↑ Ca2+ currents | ↓ I_f and ↓ Ca2+ currents, plus ↑ K+ conductance |
| Phase 4 | Steeper → threshold reached sooner | Flatter, starting from a more negative (hyperpolarized) level → threshold reached later |
| Heart rate (chronotropy) | ↑ | ↓ |
| AV conduction (dromotropy) | Faster, shorter PR | Slower, longer PR; excess vagal tone can cause AV block |
Vagal tone also wins head-to-head: prejunctional M2 receptors inhibit norepinephrine release. The right vagus mainly supplies the SA node and the left vagus mainly the AV node. These are the efferent arms of the baroreceptor reflex, so any reflex question ends here: more vagal tone = flatter phase 4 = slower rate.
Other things that change the slope:
- Hormones: hyperthyroidism causes tachycardia, hypothyroidism bradycardia; circulating epinephrine acts like norepinephrine.
- Potassium: hyperkalemia slows or can even stop SA nodal firing; hypokalemia speeds phase 4 (the real effects of K+ are complex).
- Digoxin: vagotonic, so it slows the SA node and AV conduction; at toxic levels it increases automaticity (Na+/K+-ATPase inhibition) and causes tachyarrhythmias.
The AV node: the built-in delay
Conduction is slowest in the AV node and fastest in the Purkinje fibers (Klabunde's approximate figures):
| Tissue | Conduction velocity |
|---|---|
| Atrial muscle | about 0.5 m/s |
| AV node | about 0.05 m/s (slowest) |
| His bundle and bundle branches | about 2 m/s |
| Purkinje fibers | about 4 m/s (fastest) |
The delay lets the atria finish contracting before the ventricles depolarize, and much of the PR interval reflects AV nodal delay. Because nodal phase 0 depends on L-type Ca2+, verapamil and diltiazem slow AV conduction (and can cause AV block), whereas class I drugs slow conduction in fast Na+ tissue. Interval rules are in normal ECG intervals.
Drugs that act on pacemaker cells
| Drug | Target | Effect on pacemaker tissue | High-yield extra |
|---|---|---|---|
| β-blockers (class II) | β1 | ↓ automaticity, slow AV conduction, prolong refractoriness | Can cause AV block when the node is already diseased |
| Verapamil, diltiazem (class IV) | L-type Ca2+ channels | ↓ automaticity, slow AV conduction, ↑ PR | Terminate SVT, slow AF or flutter; dihydropyridines are vascular, not nodal |
| Adenosine | A1 receptors (Gi) | Opens K+ channels (hyperpolarizes), ↓ cAMP → ↓ L-type Ca2+, ↓ I_f; slows or blocks AV conduction | Half-life under 10 seconds; converts PSVT, not AF, flutter or VT; blocked by caffeine and theophylline, potentiated by dipyridamole, not blocked by atropine |
| Digoxin | Na+/K+-ATPase; vagotonic | Prolongs AV nodal conduction | Toxicity: ↑ automaticity, many arrhythmias, AV block |
| Ivabradine | HCN channels (I_f) | Slows the SA node with no effect on contractility | Adults: stable symptomatic HFrEF (EF ≤35%, sinus rhythm, resting HR ≥70 on maximally tolerated β-blocker or β-blocker contraindicated) to cut HF hospitalization; children 6 months and older: HF from dilated cardiomyopathy; phosphenes, AF, bradycardia, fetal toxicity |
| Atropine | Muscarinic receptors | Removes vagal brake → steeper phase 4 | Helps vagally mediated nodal block (e.g., inferior MI); infranodal block needs pacing |
More drug detail is in the antiarrhythmics (class I-IV) breakdown.
When pacemakers fail
- Sick sinus syndrome (sinus node dysfunction): inappropriate sinus bradycardia, sinus pauses or arrest, SA exit block, chronotropic incompetence, or alternating bradycardia and atrial tachyarrhythmias (brady-tachy syndrome, usually with atrial fibrillation). Mostly older patients; the most common cause is idiopathic SA node fibrosis. Check TSH; symptomatic disease without a reversible cause gets a pacemaker.
- AV block: block in the AV node (Mobitz I with a narrow QRS) progresses slowly, and if it becomes complete a reliable narrow junctional escape (about 35-55/min) takes over. Block below the node (Mobitz II) can progress suddenly to complete block with a slow (20-40/min), unreliable wide escape, so it needs a pacemaker. See the AV block cheat sheet.
- MI territory: AV block in inferior MI usually reflects AV nodal dysfunction from vagal tone or local adenosine, may respond to atropine or aminophylline and often resolves; AV block in anterior MI reflects His-Purkinje necrosis and needs pacing.
To spot these rhythms on a tracing (P-QRS relationship, narrow vs wide escape), use the stepwise approach in how to read an ECG.
Practice question
A 72-year-old man who takes metoprolol for hypertension comes to the emergency department after an episode of lightheadedness. His pulse is 38/min and blood pressure is 110/70 mm Hg. An ECG shows sinus bradycardia. After IV atropine, his heart rate rises to 60/min. Which of the following ionic currents is most responsible for the spontaneous diastolic depolarization that sets his heart rate?
A. Fast inward Na+ current through voltage-gated Na+ channels B. Inward Ca2+ current through L-type Ca2+ channels C. Delayed rectifier K+ current D. Hyperpolarization-activated inward current through HCN channels (I_f) E. Transient outward K+ current (I_to)
Answer: D. The funny current starts phase 4 in SA nodal cells and accounts for a large part of their automaticity; how steep phase 4 is determines how often the node fires. His slow rate reflects a flattened phase 4 (β1 blockade plus vagal tone). Atropine blocks the muscarinic receptors, removing the vagal brake: cAMP rises, I_f and Ca2+ currents increase, K+ conductance falls, and phase 4 steepens.
- A: fast Na+ channels carry phase 0 in atrial and ventricular myocytes and Purkinje fibers; nodal cells have no functioning fast Na+ current.
- B: L-type Ca2+ current carries the nodal upstroke (phase 0) and only the very end of phase 4; it is the right answer if the question asks about the SA node upstroke or the target of verapamil.
- C: K+ efflux repolarizes the cell (phase 3). It ends the beat rather than starting the next one.
- E: I_to produces phase 1, the early notch of the ventricular action potential; pacemaker cells have no phase 1 or 2.
Key takeaways
- Pacemaker (nodal) action potential = phases 4, 0, 3 only: 4 = I_f (+ T-type Ca2+), 0 = L-type Ca2+, 3 = K+ out.
- Phase 4 slope = heart rate. β1 (↑ cAMP) steepens it; M2 (↓ cAMP, ↑ K+ conductance) flattens it and hyperpolarizes.
- The SA node is fastest and dominant; junctional escape is narrow and reliable, ventricular escape wide, slow and unreliable.
- AV node = slowest conduction (about 0.05 m/s), Purkinje fastest; AV nodal delay accounts for much of the PR interval.
- Hyperkalemia, hypoxia, digoxin, β-blockers and verapamil/diltiazem slow pacemakers; ivabradine blocks I_f without lowering contractility.
- Adenosine (A1, Gi, opens K+ channels) blocks AV conduction for seconds; caffeine and theophylline blunt it, dipyridamole enhances it.
Sources
- Sinoatrial Node Action Potentials — CV Physiology, Richard E. Klabunde (2023)
- Regulation of Pacemaker Activity — CV Physiology, Richard E. Klabunde (2022)
- Non-Pacemaker Action Potentials — CV Physiology, Richard E. Klabunde (2023)
- Normal and Abnormal Electrical Conduction — CV Physiology, Richard E. Klabunde (2023)
- Adrenergic and Cholinergic Receptors in the Heart — CV Physiology, Richard E. Klabunde (2022)
- Overview of Arrhythmias — Merck Manual Professional Edition (2025)
- Medications for Arrhythmias — Merck Manual Professional Edition (2025)
- Atrioventricular Block — Merck Manual Professional Edition (2024)
- Sick Sinus Syndrome — Merck Manual Professional Edition (2024)
- Junctional Rhythm — StatPearls, NCBI Bookshelf (2026)
- Adenosine — CV Pharmacology, Richard E. Klabunde (2023)
- CORLANOR (ivabradine) label — DailyMed (2021)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
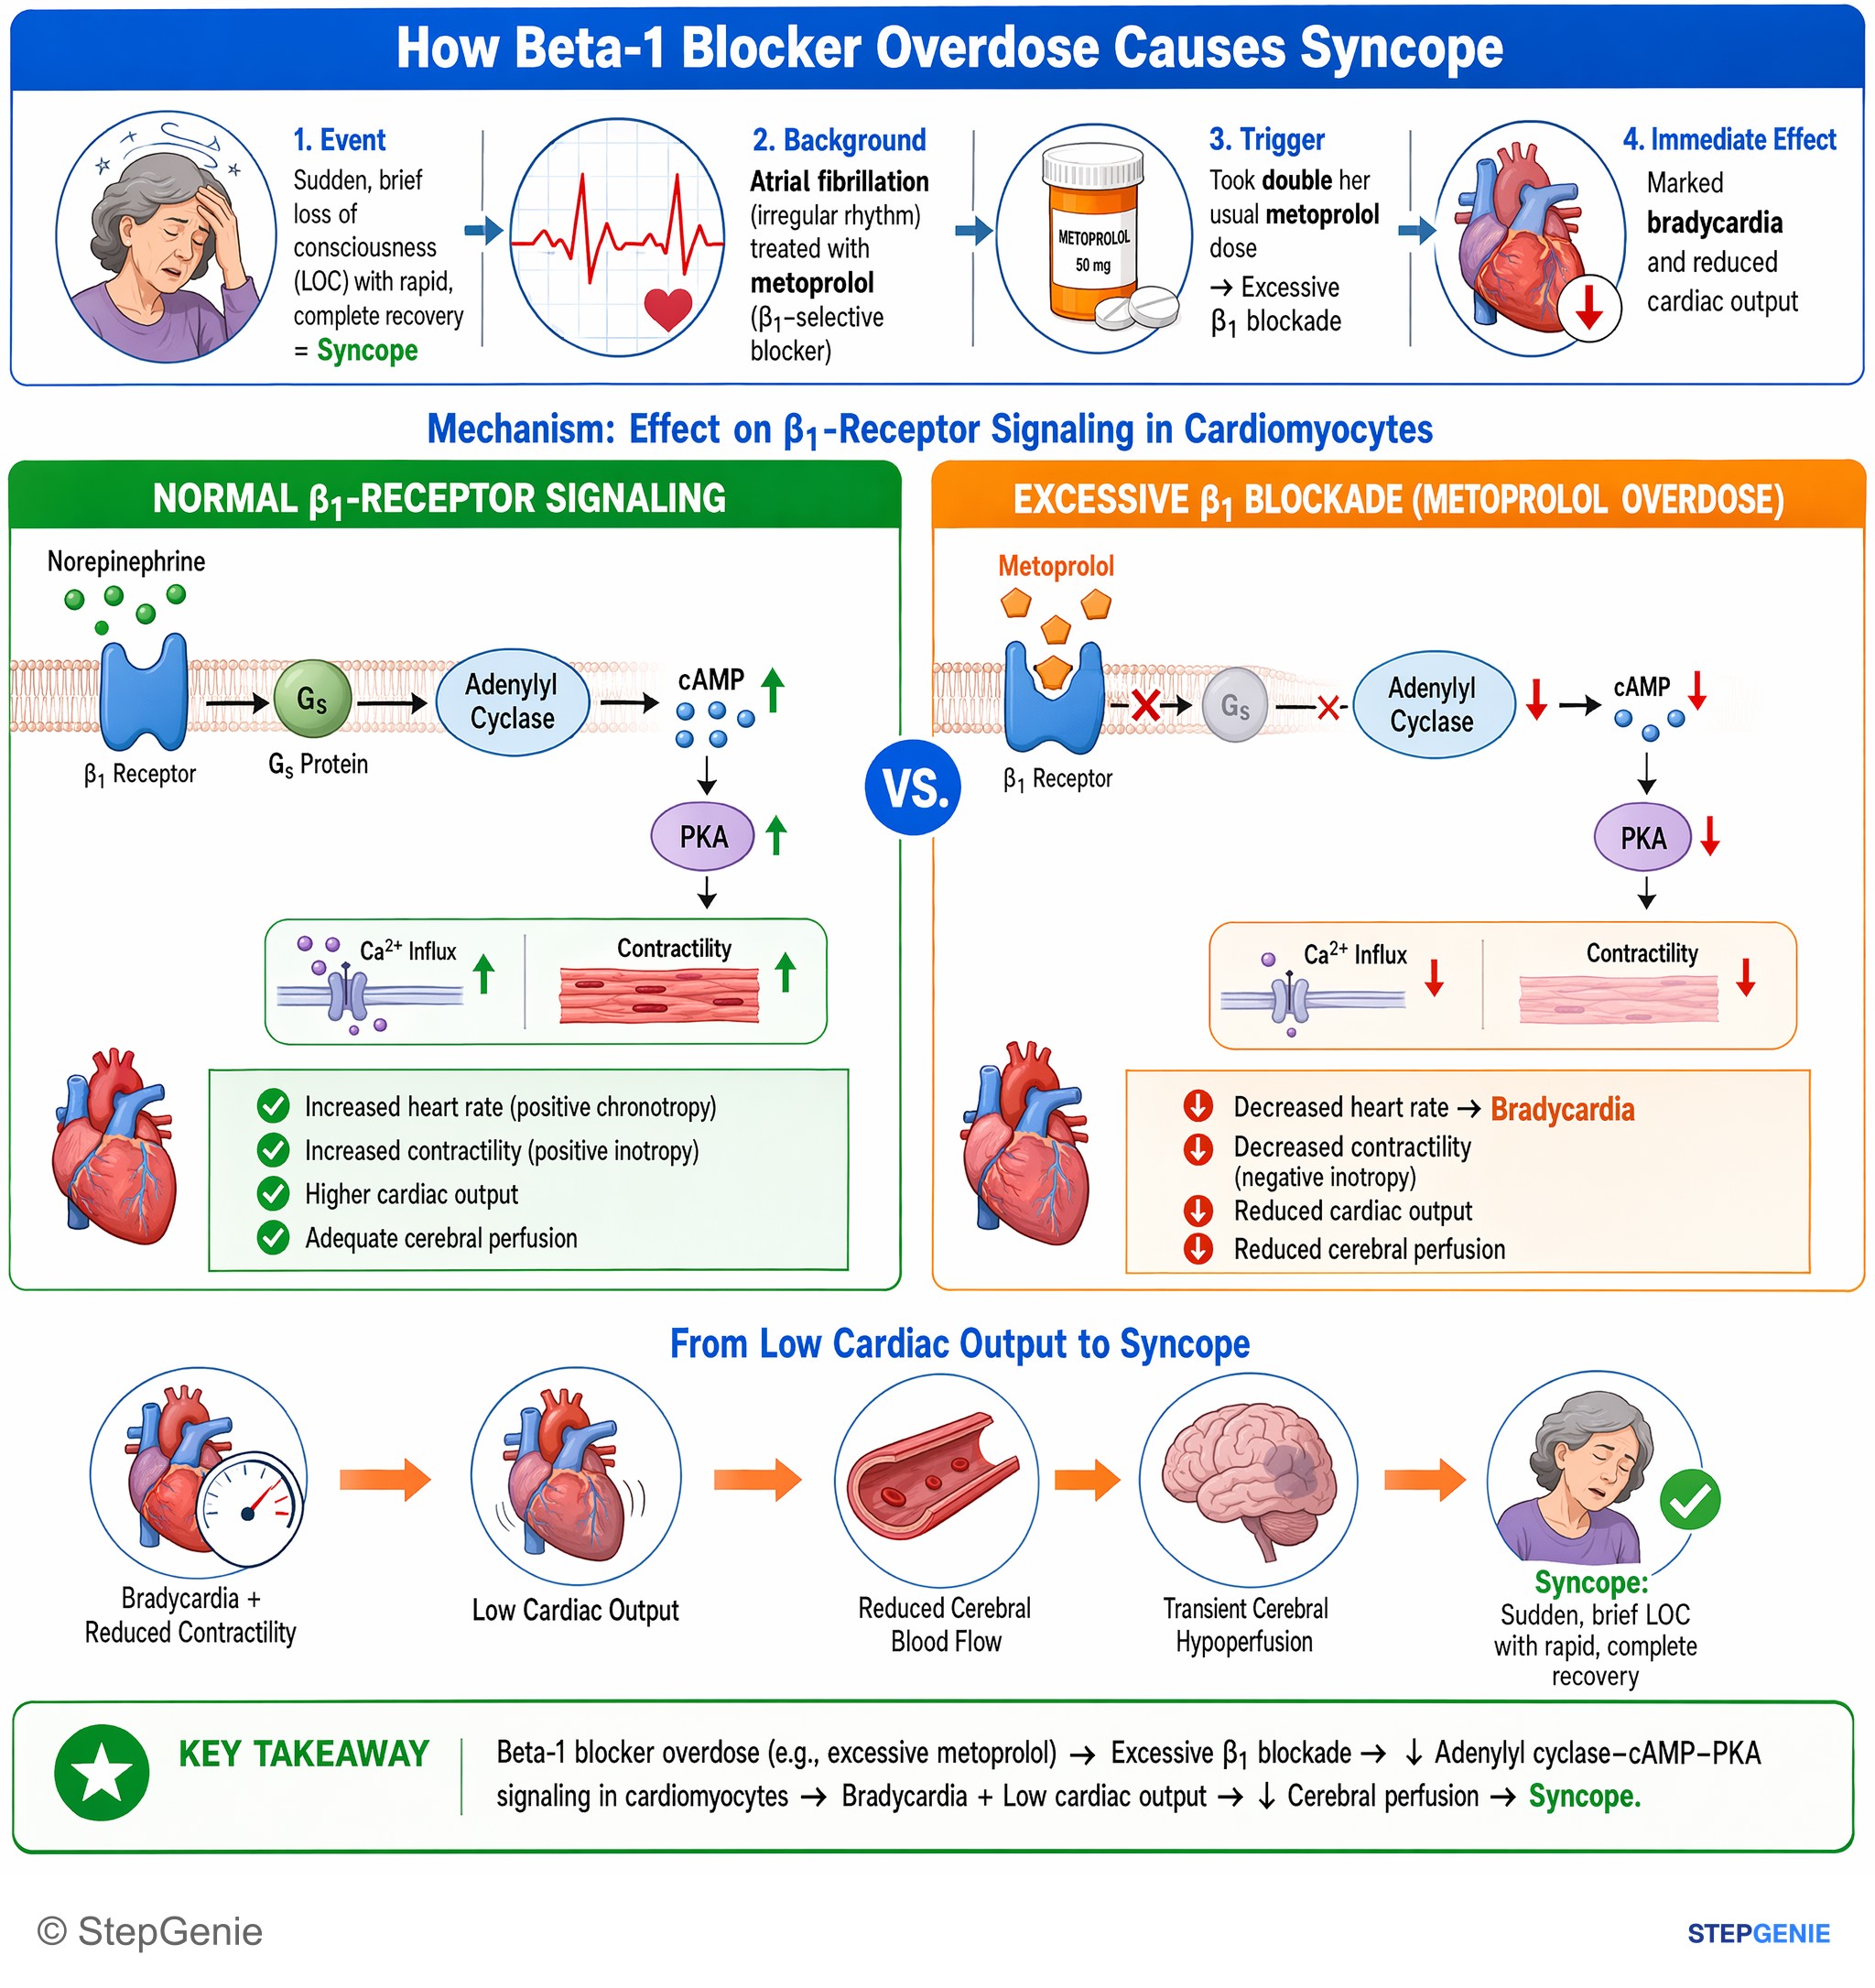
Beta-1 blockade overdose decreases adenylyl cyclase–cAMP–PKA signaling in cardiomyocytes, causing bradycardia, low cardiac output, and…
USMLE Step 1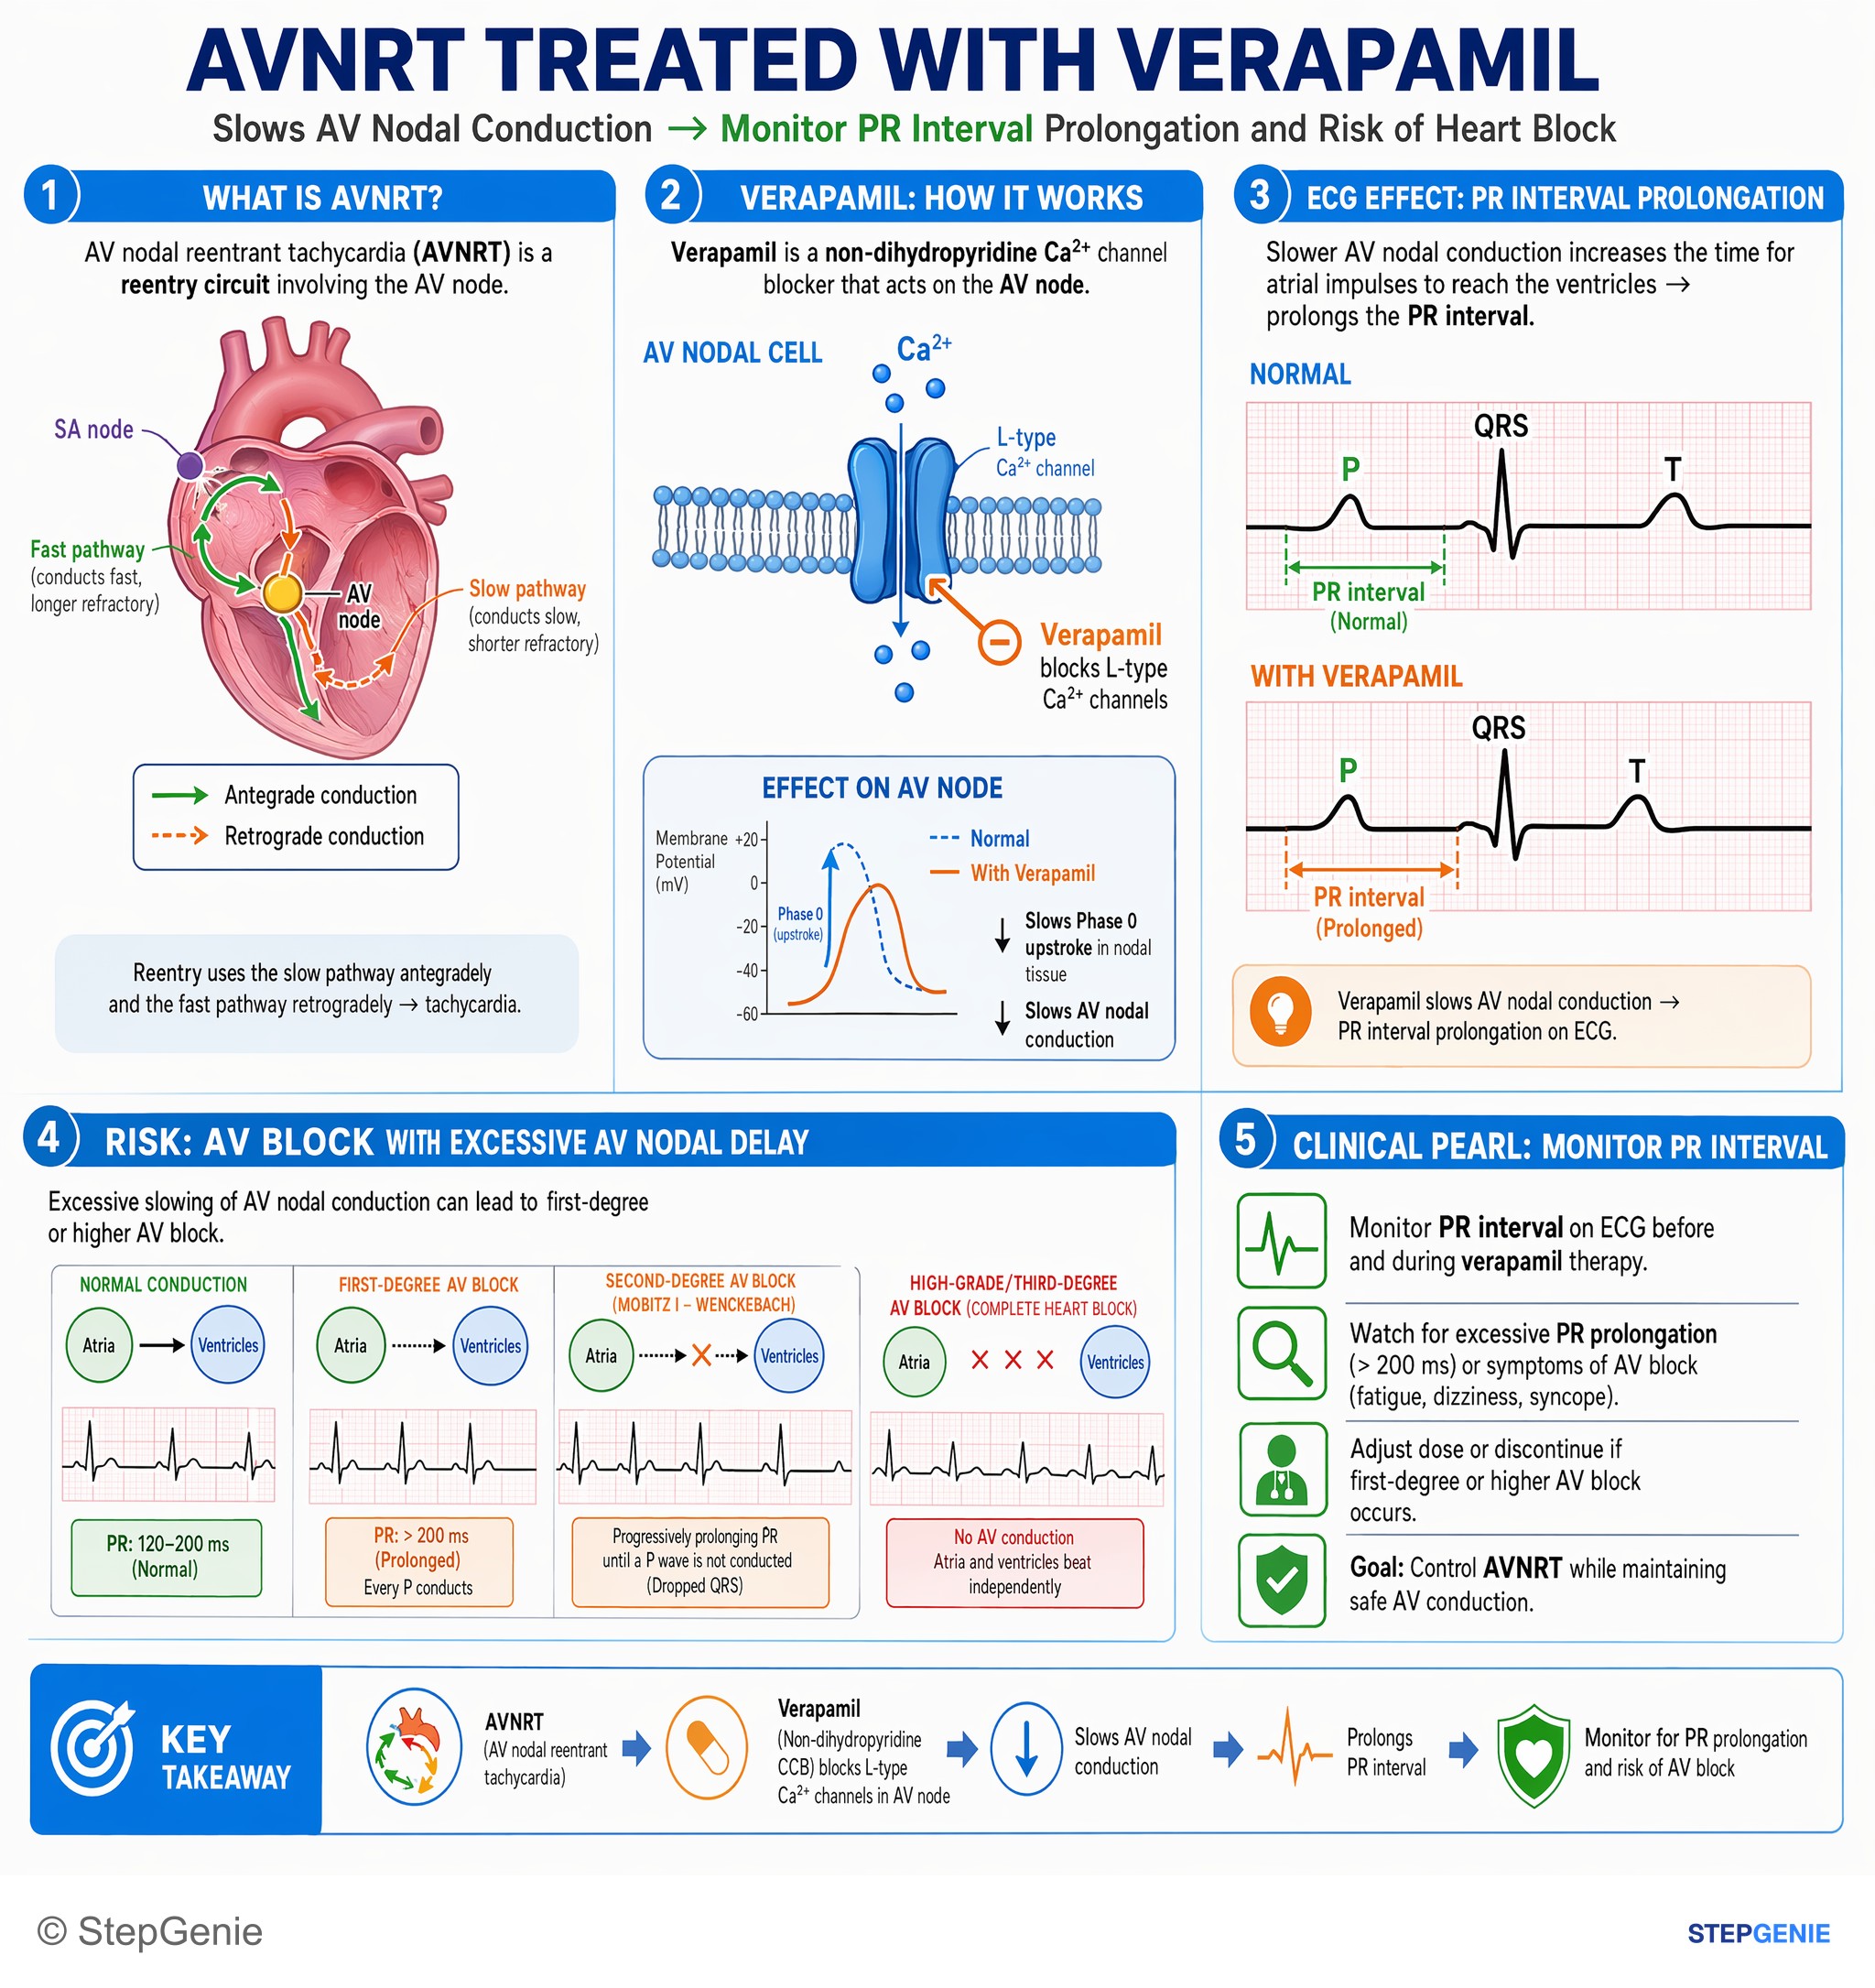
AVNRT treated with verapamil (non-dihydropyridine CCB) slows AV nodal conduction → monitor PR interval prolongation and risk of heart block.
USMLE Step 1Frequently Asked Questions
What are the phases of the pacemaker action potential?
SA and AV nodal cells have only three phases. Phase 4 is the spontaneous pacemaker potential: starting from about minus 60 mV, the funny current (If) and then T-type calcium current slowly depolarize the cell toward threshold. Phase 0 is a slow upstroke carried by L-type calcium channels rather than fast sodium channels. Phase 3 is repolarization as potassium leaves the cell. Nodal cells have no phase 1 notch and no phase 2 plateau.
What is the funny current in the heart?
The funny current (If) is a mixed sodium and potassium current through HCN channels, short for hyperpolarization-activated cyclic nucleotide-gated channels; during diastole it is net inward because sodium entry dominates. It is called funny because it is switched on by hyperpolarization at the end of phase 3 rather than by depolarization. It starts phase 4 in SA nodal cells and accounts for much of their automaticity. cAMP increases it, and ivabradine blocks it to slow the sinus rate without reducing contractility.
Why is the SA node the normal pacemaker of the heart?
The SA node has the fastest spontaneous phase 4 depolarization, so its cells reach threshold and fire before any other tissue, and their impulses set the rhythm. Slower tissues act as backups. If the SA node or AV conduction fails, a junctional escape rhythm (narrow QRS, about 35 to 50 per minute in Merck and 40 to 60 in StatPearls) or a ventricular escape rhythm (wide QRS, about 20 to 40 per minute) takes over.
How do sympathetic and parasympathetic stimulation change heart rate?
Norepinephrine acts on beta-1 receptors, raises cAMP and increases the funny current and calcium currents, so phase 4 becomes steeper and threshold is reached sooner. Acetylcholine from the vagus acts on M2 muscarinic receptors, lowers cAMP, reduces the funny current and calcium currents and increases potassium conductance, which flattens phase 4 and hyperpolarizes the cell. Vagal tone dominates at rest, which is why atropine raises the heart rate.
How are pacemaker cells different from ventricular myocytes?
Pacemaker cells in the SA and AV nodes have no stable resting potential, use L-type calcium channels for a slow phase 0 and have only phases 4, 0 and 3. Ventricular myocytes rest at about minus 90 mV, depolarize rapidly through fast sodium channels and have five phases, including a phase 1 notch and a phase 2 calcium plateau. Purkinje fibers are fast-response cells that still show slow phase 4 pacemaker activity.
Why is conduction slowest in the AV node?
AV nodal cells depolarize slowly because their upstroke depends on L-type calcium channels, so impulses travel at only about 0.05 meters per second, compared with about 4 meters per second in Purkinje fibers. This delay lets the atria finish contracting before the ventricles depolarize, and much of the PR interval reflects it. Sympathetic stimulation shortens the delay, while vagal tone, beta-blockers, verapamil, diltiazem, digoxin and adenosine lengthen it.