The baroreceptor reflex is the fast, beat-to-beat negative-feedback loop that holds arterial pressure near its set point. Stretch receptors in the carotid sinus (sinus nerve of Hering → glossopharyngeal nerve, CN IX) and the aortic arch (aortic nerve → vagus, CN X) fire more when pressure rises and less when it falls, and the nucleus tractus solitarius (NTS) in the medulla shifts autonomic output the opposite way. A drop in BP (standing up, hemorrhage, a vasodilator) means less firing, more sympathetic and less vagal outflow, so heart rate, contractility and arteriolar and venous tone rise. A rise in BP (phenylephrine, norepinephrine) produces reflex bradycardia and vasodilation. Baroreceptors adapt to sustained pressure changes, so long-term BP control belongs to the kidneys and hormones, not this reflex.
The reflex arc, step by step
| Step | Structure | What to know |
|---|---|---|
| Sensor | Stretch-sensitive mechanoreceptors in the carotid sinus (at the carotid bifurcation) and the aortic arch | Firing rises with wall stretch; they also sense how fast pressure changes and the pulse pressure |
| Afferent | Carotid sinus → sinus nerve of Hering → glossopharyngeal nerve (CN IX); aortic arch → aortic nerve → vagus nerve (CN X) | Both end in the same place: the NTS |
| Integrator | Nucleus tractus solitarius (NTS) in the medulla | NTS activity excites vagal neurons (nucleus ambiguus) and inhibits sympathetic neurons in the rostral ventrolateral medulla (RVLM), relayed through the caudal ventrolateral medulla (CVLM) |
| Efferent | Vagus to the SA and AV nodes; sympathetic fibers to the heart, arterioles and veins | The right vagus mainly supplies the SA node and the left vagus the AV node, with overlap |
| Effectors | Heart rate, AV conduction, contractility, arteriolar tone (SVR), venous tone (venous return) | Most blood vessels have no parasympathetic supply, so reflex vasodilation is really sympathetic withdrawal |
Memory hook: the glossopharyngeal nerve stays in the neck (carotid sinus), while the vagus wanders into the chest (aortic arch). How vagal and sympathetic input actually change the heart rate (the slope of phase 4 in the SA node) is covered in pacemaker cells and the SA node action potential.
Carotid sinus vs aortic arch vs carotid body
The same two nerves also carry the nearby chemoreceptors, a favorite distractor.
| Carotid sinus | Aortic arch | Carotid body | |
|---|---|---|---|
| Receptor type | Baroreceptor (stretch) | Baroreceptor (stretch) | Peripheral chemoreceptor |
| Senses | Arterial pressure | Arterial pressure | Low PO2 (main stimulus); high PCO2 and low pH also increase firing |
| Nerve | CN IX via the sinus nerve of Hering | CN X via the aortic nerve | CN IX (fibers join the sinus nerve) |
| Range and sensitivity | Responds over about 60-180 mm Hg; most sensitive near normal MAP | Higher threshold, less sensitive | Firing climbs as PO2 falls below about 95 mm Hg |
| Main job | Quantitatively the most important baroreceptor | Pressure sensing, less important than the sinus | Mainly regulates breathing (chemoreceptor reflex) |
BP down vs BP up: the arrows
| BP falls (standing, hemorrhage, vasodilator) | BP rises (phenylephrine, norepinephrine) | |
|---|---|---|
| Stretch and baroreceptor firing | ↓ | ↑ |
| Sympathetic outflow | ↑ (disinhibited) | ↓ |
| Vagal outflow | ↓ | ↑ |
| Heart rate and AV conduction | ↑ | ↓ (reflex bradycardia) |
| Contractility | ↑ | ↓ |
| Arterioles (SVR) | Constrict | Dilate |
| Veins | Constrict → more venous return | Relax |
| Result | BP partly restored | BP pulled back toward the set point |
Three details that separate a good answer from a fast one:
- It works by disinhibition. At normal pressure, baroreceptor firing tonically inhibits medullary sympathetic outflow. When BP falls, less firing releases that brake, so sympathetic activity rises. (Venous constriction and its effect on filling are mapped on venous return curves.)
- Pulse pressure counts. Receptors respond to the rate of change as well as to mean pressure, so at the same MAP a narrower pulse pressure lowers firing. In hemorrhage both fall, which amplifies the response.
- It is built for drops. The reflex buffers rises and falls, but its most important job is defending against sudden falls: standing up and blood loss.
Why it can't fix chronic hypertension
Baroreceptors adapt to a sustained change: when BP falls on standing, firing drops at first and then drifts back toward normal as the receptors adjust. In chronic hypertension the response curve shifts to the right (resetting), so the reflex defends the higher pressure as if it were normal. That is why long-term control is renal and hormonal: with continued standing, the renin-angiotensin-aldosterone system and vasopressin (ADH) retain sodium and water and expand blood volume.
Aging blunts the reflex too. Merck attributes the higher rate of orthostatic hypotension in older adults (about 15-20%) to reduced baroreceptor responsiveness plus stiffer arteries; the blunted baroreceptor response delays cardioacceleration and vasoconstriction on standing.
Classic USMLE scenarios
| Scenario | Primary change | Reflex response | What the stem shows |
|---|---|---|---|
| Standing up | ½-1 L of blood pools in leg and trunk veins → ↓ venous return → ↓ CO → ↓ BP | ↓ firing → sympathetic ↑, vagal ↓ | Small, brief rise in HR; BP barely changes in a healthy person |
| Hemorrhage | ↓ MAP and ↓ pulse pressure | Strong baroreceptor-mediated sympathetic activation | Tachycardia, ↑ contractility, vasoconstriction, cool clammy skin |
| Phenylephrine (α1 agonist) | ↑ SVR → ↑ BP | Vagal ↑ | Reflex bradycardia and lower cardiac output |
| Norepinephrine (α1 plus β1) | ↑ SVR → ↑ BP | Vagal ↑ | HR slows despite β1 stimulation; stroke volume rises |
| Hydralazine, minoxidil, dihydropyridine CCBs | ↓ SVR → ↓ BP | Sympathetic ↑ | Reflex tachycardia, which can precipitate angina |
| α1 blockers (prazosin, terazosin, doxazosin) | Can't vasoconstrict on standing | Arc intact, effector blocked | First-dose syncope, orthostatic hypotension |
| Carotid sinus massage | ↑ stretch at the sinus | Vagal ↑ | Slows the SA node and AV node; can end AV nodal reentrant tachycardia |
| Cushing triad (↑ intracranial pressure) | Sympathetic surge to keep cerebral perfusion | Bradycardia | Hypertension with wide pulse pressure, bradycardia, slow irregular breathing |
Notes on the tricky rows:
- Reflex tachycardia is the price of pure arteriolar dilators. Merck lists tachycardia (and angina in coronary disease) for hydralazine and minoxidil, and says dihydropyridines "sometimes cause reflexive tachycardia"; the nondihydropyridines (verapamil, diltiazem) slow the heart instead (see calcium channel blockers). Merck also notes ACE inhibitors lower vascular resistance without reflex tachycardia.
- Vagal maneuvers. Valsalva, unilateral carotid sinus massage and ice water to the face raise vagal tone and can terminate reentrant SVT (AV nodal reentry is the most common type); StatPearls puts carotid sinus massage alone at about 20% of episodes. Sinus tachycardia only slows.
- Carotid sinus syndrome. An oversensitive carotid sinus turns everyday neck pressure (a tight collar, shaving, turning the head) into hypotension and syncope.
- Cushing triad. Markedly raised ICP classically produces hypertension (usually with a widened pulse pressure), bradycardia and respiratory depression or irregular breathing. The classic exam explanation is a baroreceptor reflex to the BP surge; StatPearls notes that newer work also points to direct compression of the vagus inside the skull. Raised ICP after bleeding is covered in hemorrhagic stroke.
When the reflex fails: orthostatic hypotension
Definition: a fall in systolic BP of ≥20 mm Hg or diastolic BP of ≥10 mm Hg within 3 minutes of standing. Measure BP and heart rate after 5 minutes supine, then at 1 and 3 minutes standing. Merck: this happens when the afferent, central or efferent part of the arc is impaired, when the heart or vessels cannot respond, when volume is low, or when hormonal responses fail.
The heart rate tells you which part failed:
| On standing | Heart rate change | Meaning | Think |
|---|---|---|---|
| BP falls ≥20/10 | Rises >30/min or to >100/min | Reflex intact, tank empty | Hypovolemia: bleeding, dehydration, diuretics |
| BP falls ≥20/10 | Rises <10/min | Reflex arc broken | Autonomic failure: diabetic or amyloid neuropathy, Parkinson disease, multiple system atrophy, pure autonomic failure |
| Little or no BP fall | Rises ≥30/min or to ≥120/min | Not orthostatic hypotension | POTS (within 10 minutes of standing; in adolescents, a rise of at least 40/min) |
Common causes (Merck): hypovolemia, medications and prolonged bed rest (acute); aging, medications and autonomic dysfunction (chronic). Culprit drugs include α1 blockers, clonidine, nitrates, calcium channel blockers, diuretics, tricyclic antidepressants and antipsychotics. Neurologic causes are central (Parkinson disease, multiple system atrophy; see the Parkinson disease flowchart) or peripheral (diabetic, alcohol-related or amyloid neuropathy).
Management: treat the cause and stop offending drugs; rise slowly, keep up fluids and salt (if there is no heart failure or hypertension), raise the head of the bed and use waist-high compression. Drug options:
- Fludrocortisone: mineralocorticoid; retains sodium and expands plasma volume (watch for supine hypertension, heart failure, hypokalemia).
- Midodrine: prodrug of the α1 agonist desglymidodrine; boxed warning for supine hypertension, so it is dosed during the day and not after the evening meal. Its label notes a slight slowing of heart rate "primarily due to vagal reflex": the baroreflex again.
- Droxidopa: converted to norepinephrine by dopa decarboxylase; FDA approved for symptomatic neurogenic orthostatic hypotension (Parkinson disease, multiple system atrophy, pure autonomic failure, dopamine β-hydroxylase deficiency, non-diabetic autonomic neuropathy), also with a supine hypertension boxed warning.
Practice question
A 34-year-old man becomes hypotensive after induction of general anesthesia: blood pressure 84/48 mm Hg, pulse 86/min and oxygen saturation 99%. He receives an IV bolus of phenylephrine. Two minutes later his blood pressure is 132/80 mm Hg and his pulse is 58/min. Which of the following best explains the change in heart rate?
A. Direct stimulation of β1 receptors on the sinoatrial node B. Increased carotid sinus firing carried by the glossopharyngeal nerve to the nucleus tractus solitarius, raising vagal outflow C. Decreased aortic arch firing carried by the vagus nerve, withdrawing sympathetic tone D. Stimulation of carotid body chemoreceptors E. A direct negative chronotropic action of phenylephrine on pacemaker cells
Answer: B. Phenylephrine is an α1 agonist: it constricts arterioles, raises SVR and BP, and stretches the carotid sinus and aortic arch. More firing travels via CN IX (carotid sinus) and CN X (aortic arch) to the NTS, which increases vagal output and inhibits sympathetic output. The phenylephrine label describes exactly this: as BP rises, vagal activity increases, "resulting in reflex bradycardia."
- A: phenylephrine acts on α1 receptors, and β1 stimulation would speed the heart, not slow it.
- C: wrong direction. A rise in BP increases firing at both sites; falling firing with sympathetic activation is the response to hypotension.
- D: carotid bodies sense low PO2, high PCO2 and low pH, and his saturation is normal. They mainly drive breathing.
- E: the slowing is a vagal reflex, not a direct drug effect, which is why a muscarinic blocker such as atropine would blunt it.
Key takeaways
- Sensors: carotid sinus (CN IX via the sinus nerve of Hering) and aortic arch (CN X); integrator: NTS in the medulla.
- BP up → more firing → vagal up, sympathetic down → bradycardia and vasodilation. BP down → the reverse, by sympathetic disinhibition.
- The carotid sinus is the main sensor (about 60-180 mm Hg); aortic receptors have a higher threshold. Carotid bodies are chemoreceptors, not baroreceptors.
- Pressors (phenylephrine, norepinephrine) → reflex bradycardia; arteriolar dilators (hydralazine, minoxidil, dihydropyridines) → reflex tachycardia.
- Baroreceptors adapt and reset (the curve shifts right in chronic hypertension), so they don't set long-term BP.
- Orthostatic hypotension: ≥20 systolic or ≥10 diastolic within 3 minutes; HR rise <10/min suggests autonomic failure, >30/min suggests hypovolemia.
- Carotid sinus massage raises vagal tone and can stop AV nodal reentrant tachycardia; an oversensitive sinus causes syncope with tight collars, shaving or head turning.
Sources
- Physiology, Baroreceptors — StatPearls, NCBI Bookshelf (2023)
- Arterial Baroreceptors — CV Physiology, Richard E. Klabunde (2022)
- Autonomic Innervation of the Heart and Vasculature — CV Physiology, Richard E. Klabunde (2022)
- Chemoreceptors — CV Physiology, Richard E. Klabunde (2022)
- Orthostatic Hypotension — Merck Manual Professional Edition (2024)
- Medications for Hypertension — Merck Manual Professional Edition (2025)
- Reentrant (Paroxysmal) Supraventricular Tachycardias (PSVT) — Merck Manual Professional Edition (2024)
- BIORPHEN (phenylephrine hydrochloride) injection label — DailyMed (2026)
- LEVOPHED (norepinephrine bitartrate) injection label — DailyMed (2023)
- Midodrine hydrochloride tablets label — DailyMed (2025)
- Cushing Reflex — StatPearls, NCBI Bookshelf (2023)
- Postural Tachycardia Syndrome (POTS) — National Institute of Neurological Disorders and Stroke (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
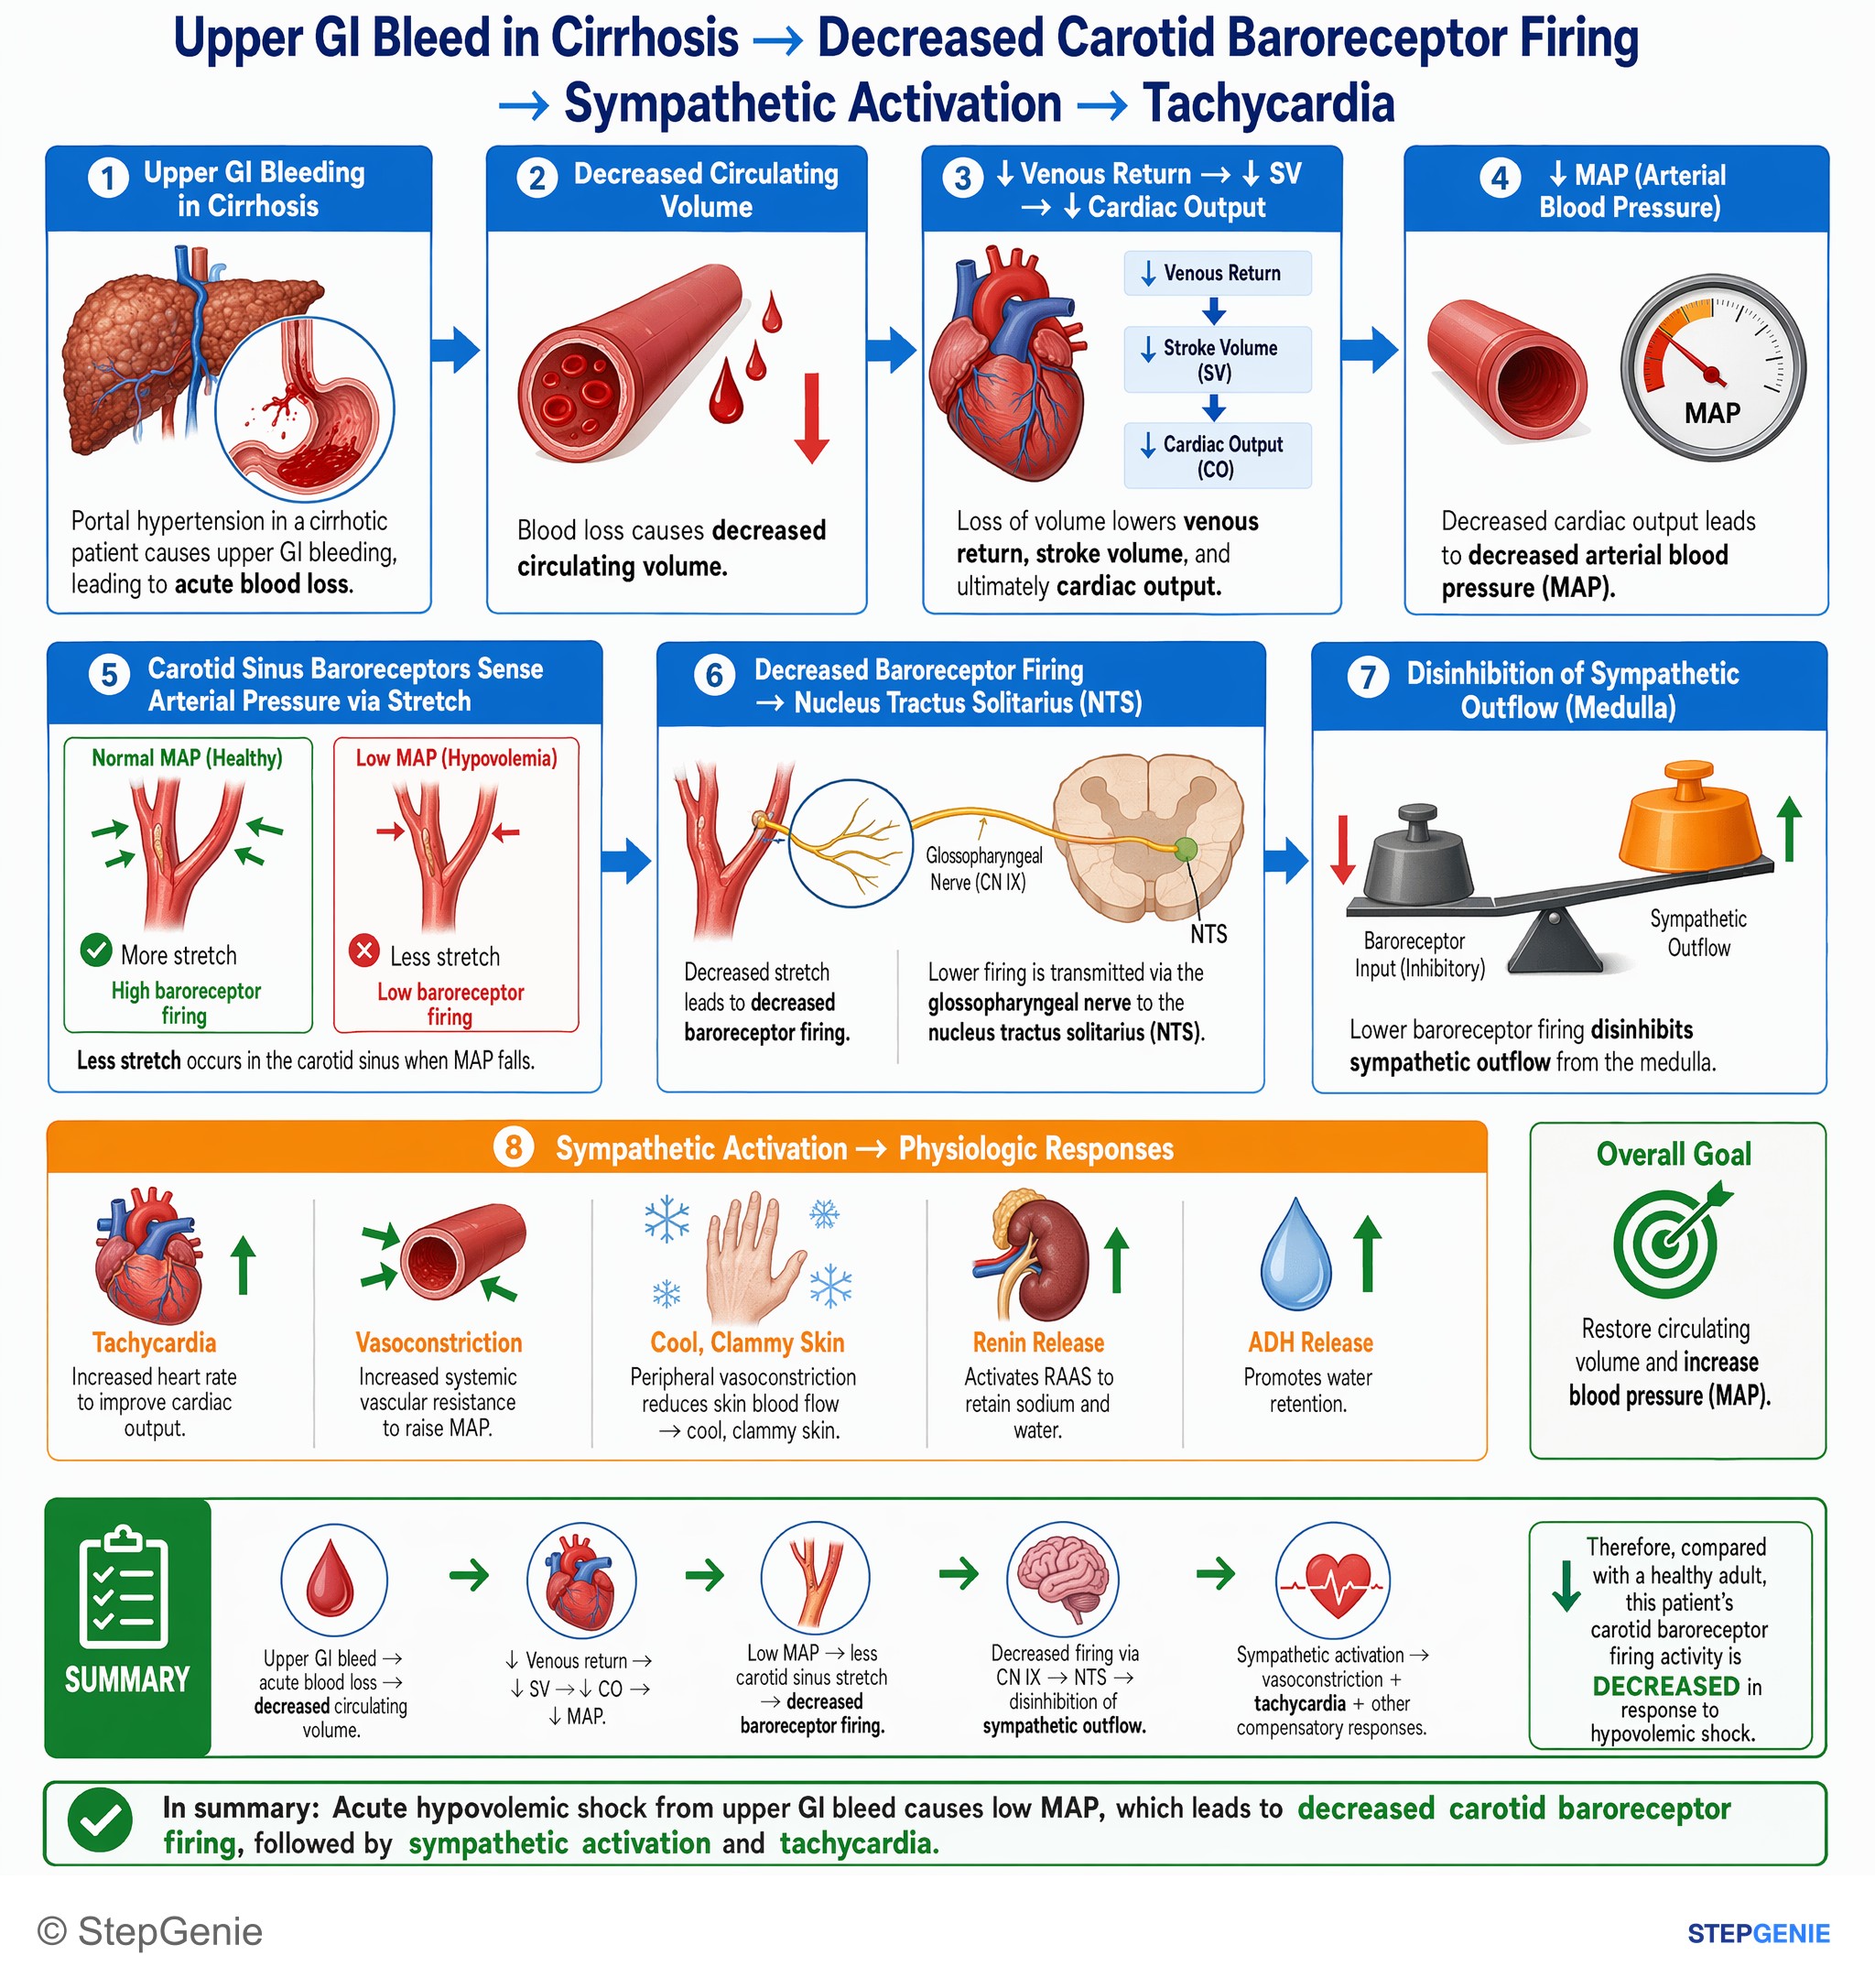
Acute hypovolemic shock from upper GI bleed → low MAP → decreased carotid baroreceptor firing → sympathetic activation and tachycardia.
USMLE Step 1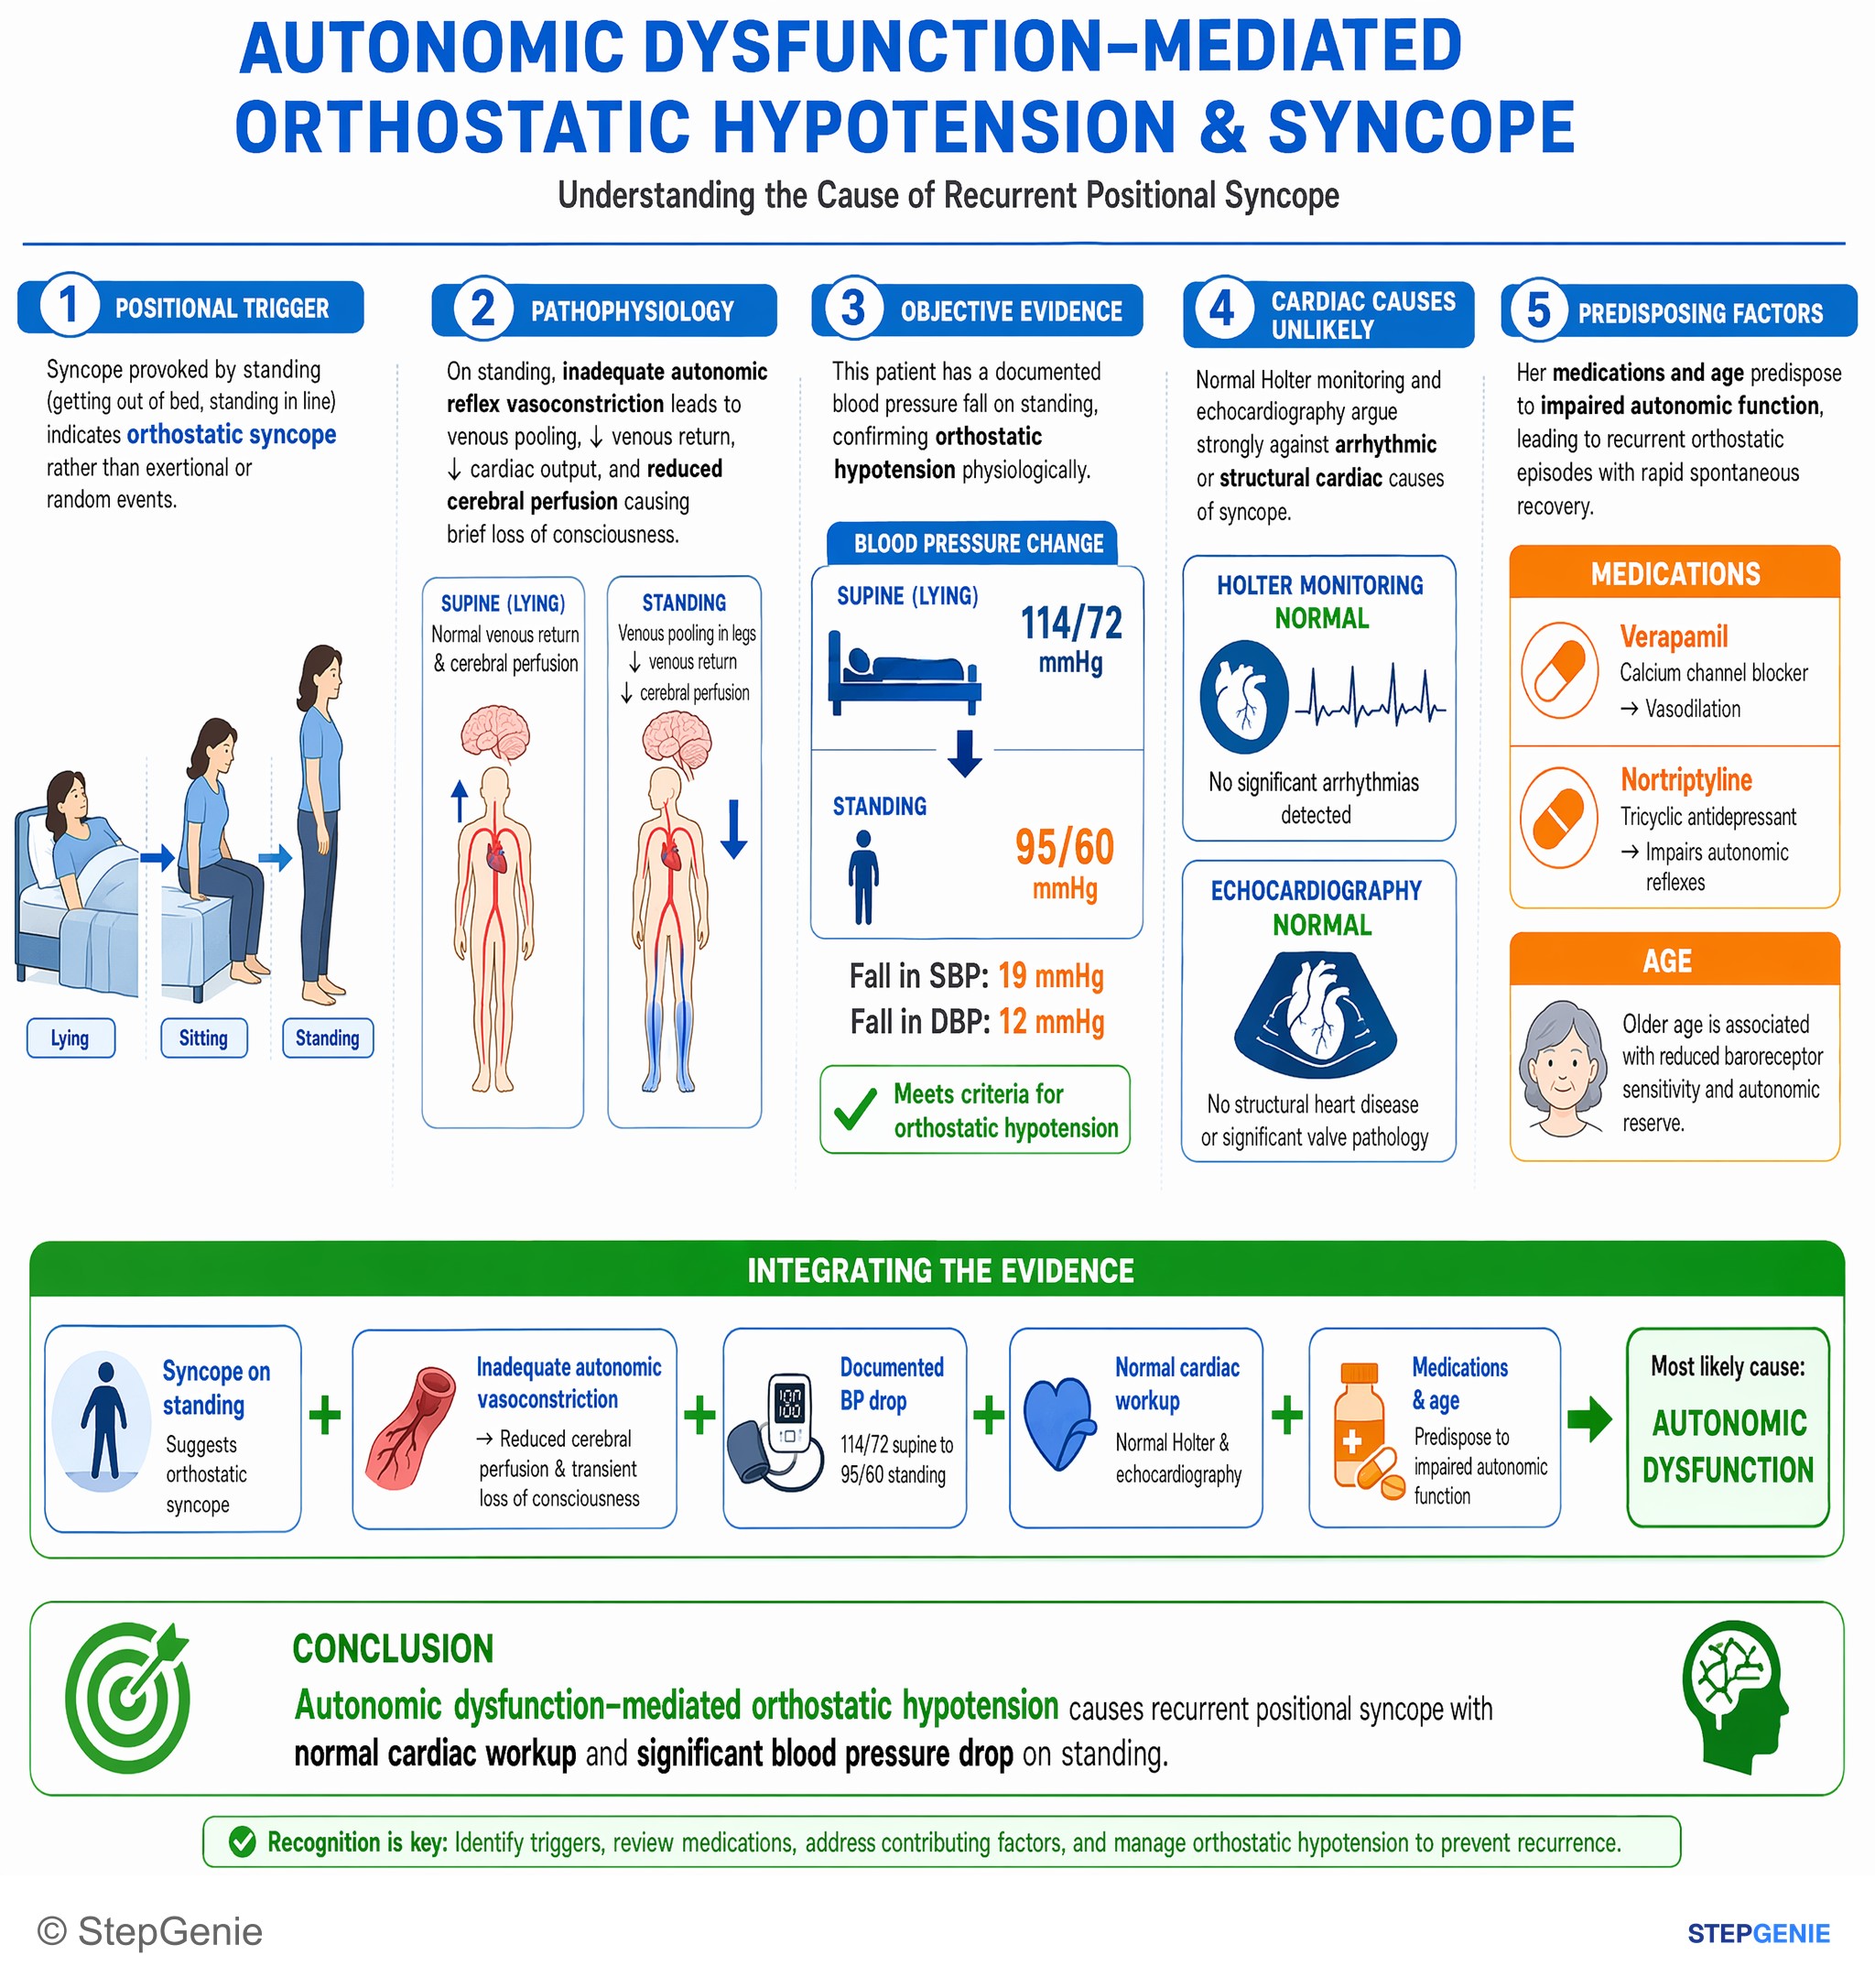
Autonomic dysfunction–mediated orthostatic hypotension causes recurrent positional syncope with normal cardiac workup and significant BP…
USMLE Step 2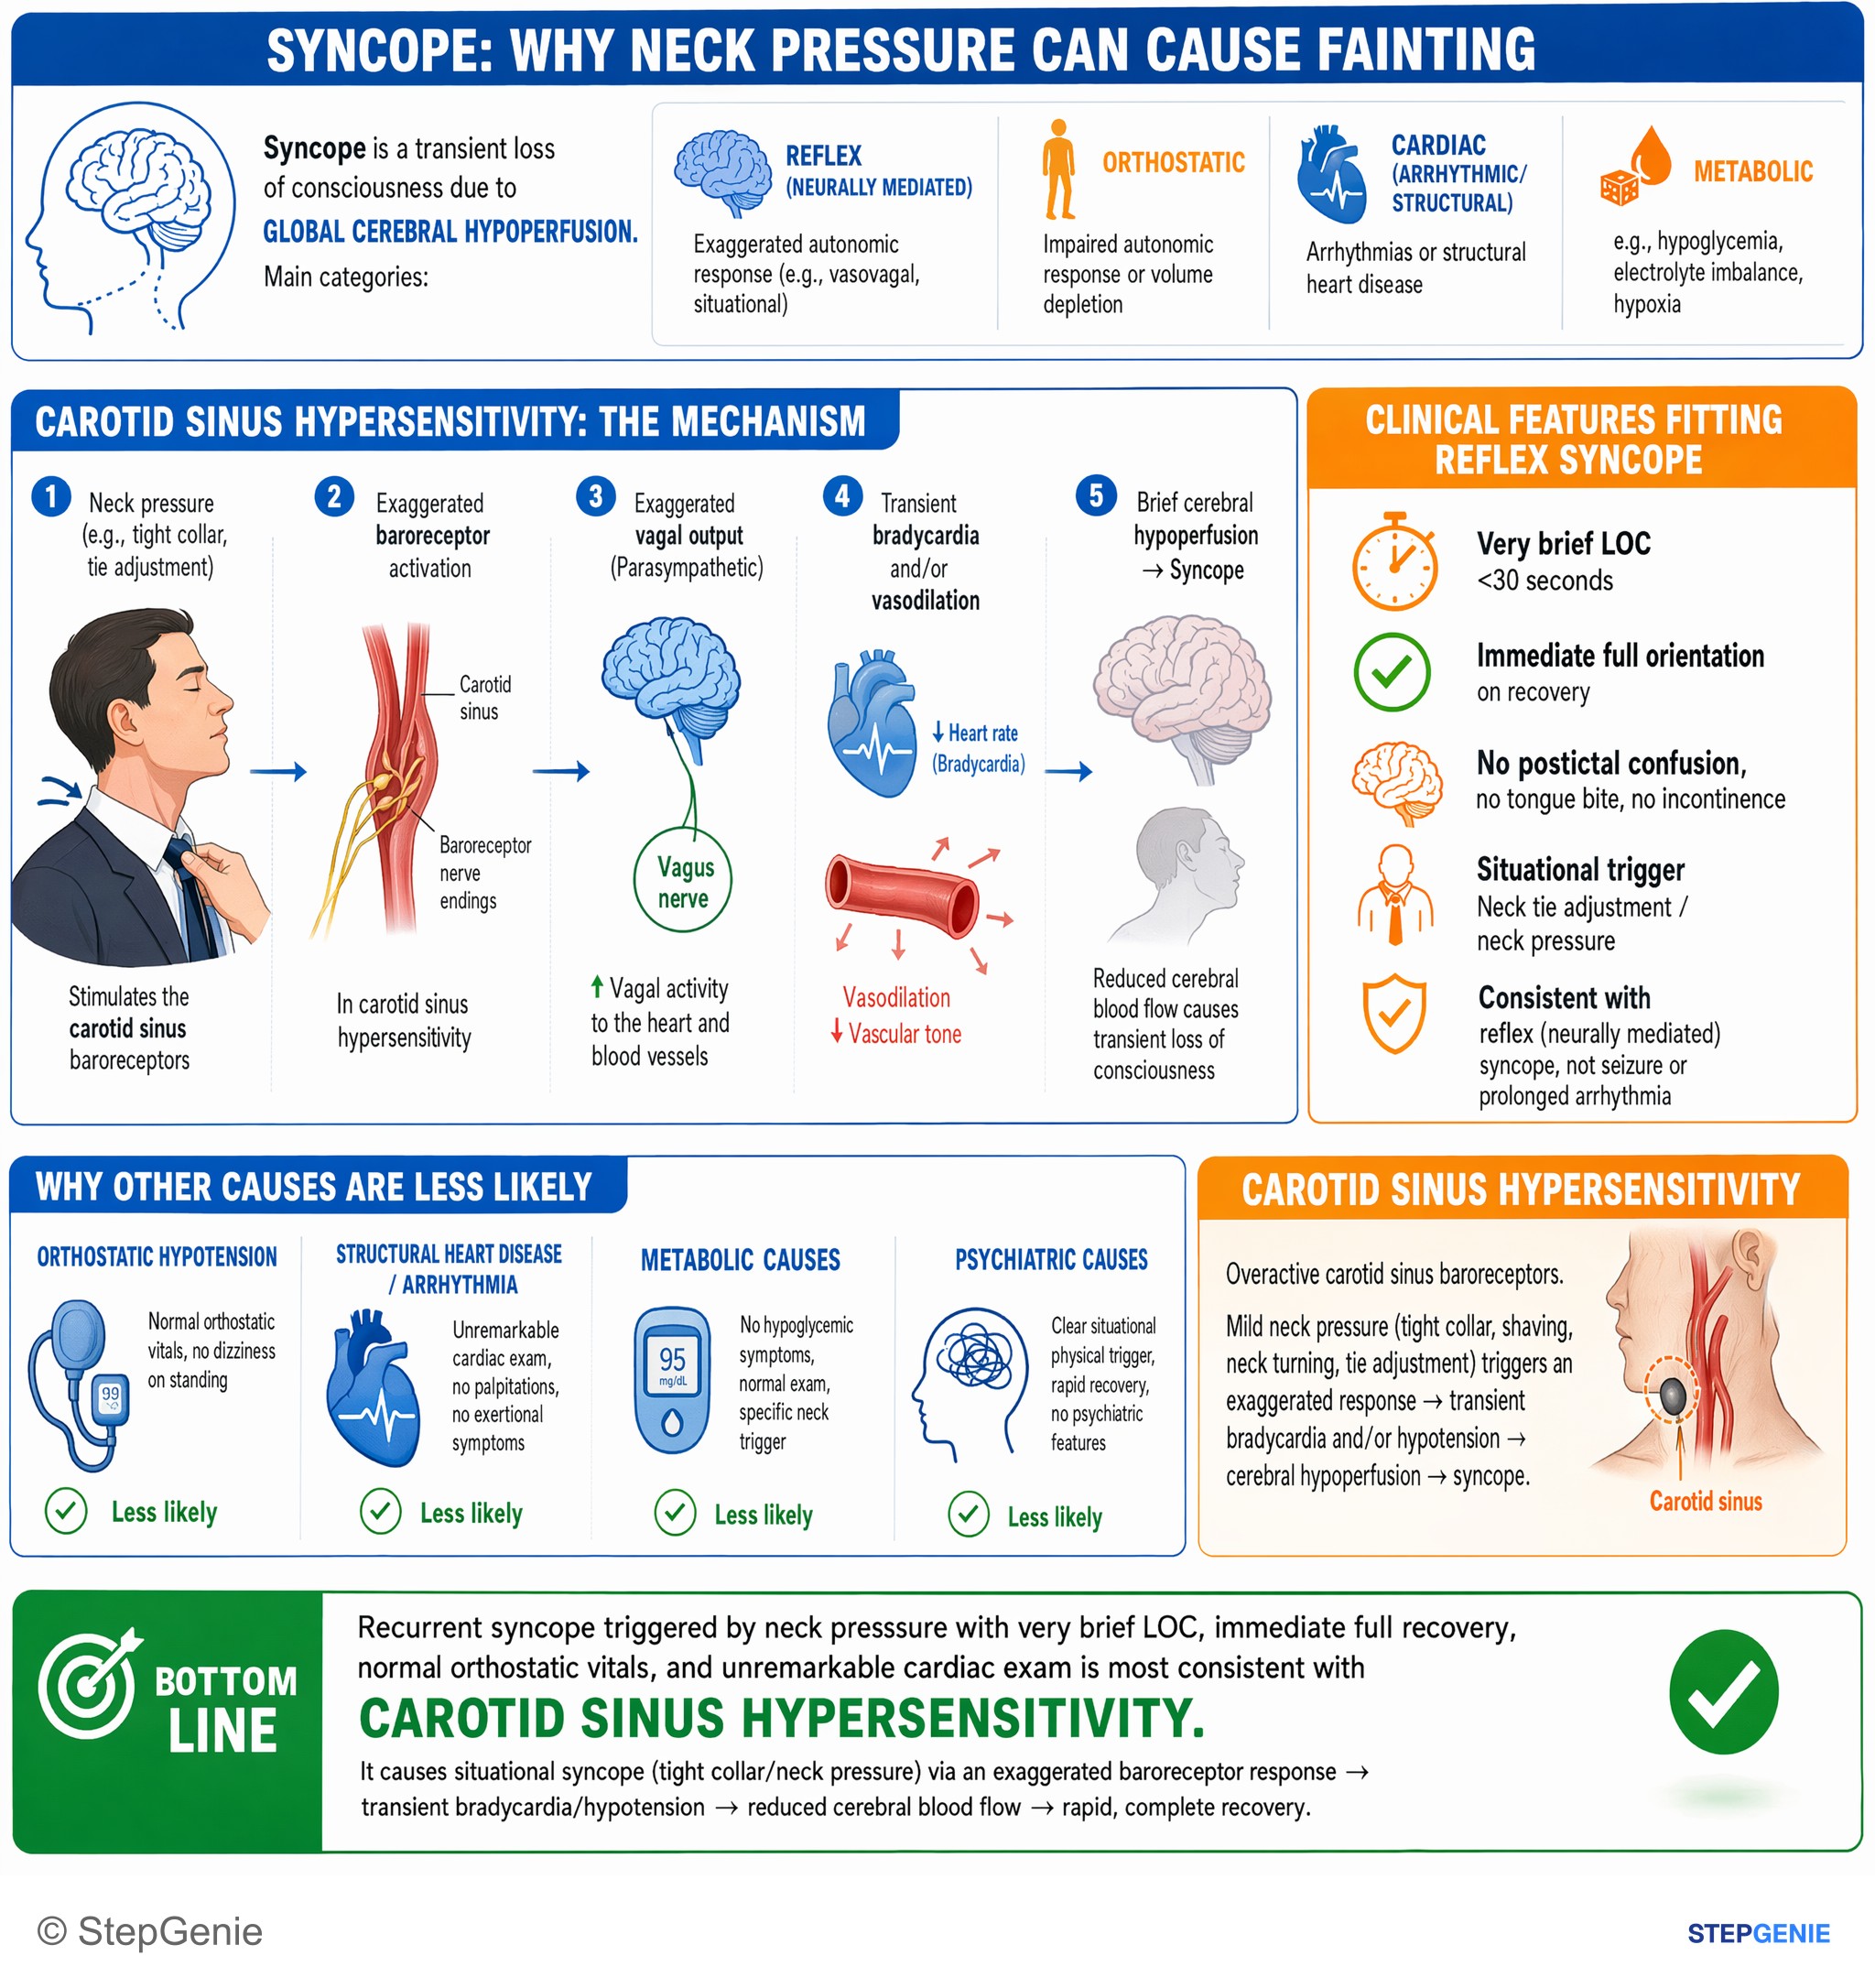
Carotid sinus hypersensitivity causes situational syncope (tight collar/neck pressure) via exaggerated baroreceptor response → transient…
USMLE Step 2Frequently Asked Questions
What is the pathway of the baroreceptor reflex?
Stretch receptors in the carotid sinus and aortic arch sense arterial pressure. Carotid sinus signals travel in the sinus nerve of Hering to the glossopharyngeal nerve (CN IX), and aortic arch signals travel in the vagus nerve (CN X), both to the nucleus tractus solitarius in the medulla. The NTS then adjusts output: it excites vagal neurons in the nucleus ambiguus and inhibits sympathetic neurons in the rostral ventrolateral medulla, which change heart rate, contractility and vascular tone.
Which cranial nerves carry the baroreceptor reflex?
The afferent limb uses two cranial nerves. Carotid sinus baroreceptors send signals through the sinus nerve of Hering, a branch of the glossopharyngeal nerve (CN IX). Aortic arch baroreceptors send signals through the aortic nerve, which joins the vagus nerve (CN X). On the efferent side, the vagus nerve carries the parasympathetic output to the SA and AV nodes, while sympathetic fibers carry the output to the heart and blood vessels.
Why does phenylephrine cause reflex bradycardia?
Phenylephrine is an alpha-1 agonist that constricts arterioles, so systemic vascular resistance and blood pressure rise. The higher pressure stretches the carotid sinus and aortic arch, baroreceptor firing increases, and the nucleus tractus solitarius raises vagal output while lowering sympathetic output. The result is a slower heart rate. The drug label describes this directly: as blood pressure increases, vagal activity also increases, resulting in reflex bradycardia, and it warns that the drug can cause severe bradycardia and decreased cardiac output.
Why doesn't the baroreceptor reflex correct chronic hypertension?
Baroreceptors adapt to sustained changes in pressure. After a while their firing returns toward baseline, and in chronic hypertension the response curve shifts to the right, so the reflex treats the higher pressure as the new set point. This is called resetting. The baroreceptor reflex therefore controls blood pressure over seconds to minutes, while long-term control depends on the kidneys and hormones such as the renin-angiotensin-aldosterone system and vasopressin.
What is the difference between the carotid sinus and the carotid body?
The carotid sinus is a baroreceptor: it senses stretch from arterial pressure and is the most important site of the baroreceptor reflex. The carotid body is a peripheral chemoreceptor: it fires mainly when arterial PO2 falls, and also with high PCO2 or low pH, and its main job is to drive breathing. Both send signals through the glossopharyngeal nerve (CN IX), which is why exam questions like to swap them.
How does heart rate help explain orthostatic hypotension?
Orthostatic hypotension is a fall of at least 20 mm Hg systolic or 10 mm Hg diastolic within 3 minutes of standing. If the heart rate rises by more than 30 beats per minute or above 100, the reflex is working and volume loss is likely. If the heart rate rises by less than 10, the reflex arc is impaired, as in autonomic failure from diabetes or Parkinson disease. A large heart rate rise without a blood pressure fall suggests POTS.