AV block is delayed or failed conduction from the atria to the ventricles, graded by two questions: what is the PR interval doing, and does every P wave reach the ventricles? First-degree block is a PR over 200 ms with every P wave conducted; Mobitz I (Wenckebach) stretches the PR until a QRS drops and usually sits in the AV node; Mobitz II drops a QRS without warning after constant PR intervals and sits below the node (His-Purkinje); in third-degree block no P wave conducts and an escape rhythm runs the ventricles. The 2018 ACC/AHA/HRS bradycardia guideline, still the current US guideline, recommends a permanent pacemaker for Mobitz II, high-grade and third-degree AV block not caused by a reversible or physiologic problem, regardless of symptoms.
The one-page table
| Block | ECG criteria | Level of block | QRS | Classic causes | Treatment |
|---|---|---|---|---|---|
| 1st degree (really "AV delay") | PR >200 ms, every P conducts (1:1) | Usually AV node | Usually narrow | Vagal tone, athletes, AV nodal drugs, inferior MI, Lyme | None; review drugs. Pace only if PR is very long and symptoms are clearly due to it |
| Mobitz I (Wenckebach) | PR lengthens beat by beat until one P fails to conduct; shortest PR right after the pause; grouped beating | AV node (nearly always if QRS narrow) | Usually narrow | Sleep, athletes, AV nodal drugs, inferior MI | None if asymptomatic; atropine if symptomatic; pace only for symptoms clearly caused by the block |
| Mobitz II | Constant PR before and after a suddenly blocked P; P waves at a steady rate | Infranodal: His bundle (about 25%) or bundle branches | Usually wide (bundle branch block) | Conduction-system fibrosis, anterior MI, sarcoidosis, cardiac surgery, TAVR | Permanent pacemaker regardless of symptoms |
| 2:1 | Every other P conducts | Cannot be called Mobitz I or II from the strip | Narrow favors node; wide favors infranodal | Either type | Localize it (longer strip, exercise, EPS); infranodal 2:1 block is paced like Mobitz II, with or without symptoms; nodal 2:1 only for symptoms clearly due to it |
| High-grade (advanced) | 2 or more consecutive blocked P waves at a normal rate, some conduction (e.g. 3:1) | Usually within or below the His bundle | Often wide | Same as Mobitz II | Permanent pacemaker |
| 3rd degree (complete) | No P wave conducts: P waves and QRS complexes march independently, atrial rate > ventricular rate | AV node or infranodal | Narrow junctional or wide ventricular escape | Idiopathic fibrosis and ischemic heart disease (the top two causes of AV block overall, about 40% and 20%), drugs, Lyme, sarcoidosis, congenital | Atropine or pacing if unstable; permanent pacemaker unless reversible |
Read any strip in five questions
- Is every P wave followed by a QRS? If yes and the PR is longer than one large box (5 small boxes, 200 ms at standard paper speed), it is first-degree block. Normal values are in the normal ECG intervals breakdown.
- Some P waves have no QRS? Compare the PR just before and just after the pause. Longest before, shortest after: Mobitz I. Identical: Mobitz II.
- Only 2:1 conduction? With no two conducted beats in a row, the type can't be named; use QRS width and other strips.
- Two or more P waves in a row blocked, but some still conduct? That is high-grade AV block.
- Nothing conducts? PR intervals vary at random, P waves outnumber QRS complexes: third-degree block. Then judge the escape rhythm by its QRS width and rate.
Level of block decides the prognosis
| AV node (supra-Hisian) | His-Purkinje (infranodal) | |
|---|---|---|
| Typical rhythms | 1st degree, Mobitz I, narrow-QRS 2:1, inferior MI block | Mobitz II, high-grade, fibrosis or anterior MI block |
| QRS | Narrow | Usually wide (bundle branch or fascicular block) |
| Escape if it becomes complete | Junctional: narrow, about 40-60/min (StatPearls; Merck gives 35-50), reliable | Ventricular: wide, 20-40/min, unreliable |
| Symptoms | Milder: fatigue, light-headedness, effort intolerance | Presyncope, syncope, heart failure |
| Atropine, exercise | Improve conduction | Unlikely to help; block can worsen as the sinus rate rises |
| Progression | Slow | Can jump suddenly to complete block |
Each block in brief: what the table can't hold
First-degree AV block
- No P wave is actually blocked, which is why the guideline prefers "first-degree AV delay." Common: about 1-1.5% of people until age 60, 6% after, and more than 10% of young athletes (StatPearls). Vagal tone explains it in the young and conduction-system fibrosis in the old; AV nodal blockers (beta blockers, verapamil, diltiazem, digoxin, amiodarone) are the classic drug cause.
- A PR over 300 ms ("marked") can cost AV synchrony and cause exertional dyspnea and fatigue (pseudo-pacemaker syndrome). Pacing is reasonable only when symptoms are clearly due to the block.
Mobitz I and Mobitz II
- Mobitz I with a narrow QRS is nearly always in the AV node. With a wide QRS (over 120 ms), 60-70% are in the His-Purkinje system (Merck), which changes management.
- Mobitz I is often physiologic in young, athletic people and during sleep, and rarely progresses suddenly. Pacing an asymptomatic nodal Mobitz I is a Class III (harm) recommendation.
- Mobitz II sits in the His bundle in 25% and the bundle branches in the rest (Merck), so its QRS is usually wide, often with a bundle branch block. In patients aged 18-60 with new Mobitz II or complete block and no obvious structural disease, up to one-third have cardiac sarcoidosis (Merck).
2:1 and high-grade block
- The guideline is explicit that 2:1 block "cannot be classified as Mobitz I or II." A narrow QRS, Wenckebach cycles elsewhere on the strip and better conduction with exercise or atropine point to the node. A wide QRS or bundle branch block (though 15-20% of these are still nodal) and worse conduction with exercise point below it. An electrophysiology study can settle the level.
- High-grade block (2 or more consecutive blocked P waves at a normal rate, such as 3:1) is generally within or below the His bundle and is paced.
Third-degree (complete) AV block
- Exam signs of AV dissociation: cannon a waves in the jugular veins, and beat-to-beat changes in S1 loudness and blood pressure.
- Causes beyond the table: amyloidosis, valve surgery, TAVR, and congenital block from maternal anti-Ro/SSA and anti-La/SSB antibodies (maternal lupus; see SLE).
MI and AV block: inferior vs anterior
| Inferior MI | Anterior MI | |
|---|---|---|
| Artery | RCA; the AV nodal artery usually arises from the RCA in right-dominant hearts | LAD |
| Mechanism | AV nodal: high vagal tone and local adenosine release | Extensive necrosis involving the His-Purkinje system |
| Typical block | 1st degree, Mobitz I, narrow-QRS complete block | Mobitz II, high-grade, wide-QRS complete block |
| Course | Usually resolves; complete block develops in 5-10% and may resolve within 2-48 hours | Worse prognosis; more often needs a permanent pacemaker |
| Acute treatment | May respond to atropine (aminophylline is an option) | Immediate transvenous pacing (Merck) |
Guideline rules after MI: wait before deciding on a permanent pacemaker; then pace persistent Mobitz II, high-grade, alternating bundle branch or third-degree block (persistent or infranodal); and do not pace transient block that resolves. ECG localization of the infarct is in the STEMI patterns post.
Reversible causes: fix them before a pacemaker
- Lyme carditis (about 1 in 100 Lyme cases, CDC): usually nodal block that can vary in degree and change rapidly. Severe carditis (symptoms, PR ≥300 ms, or second- or third-degree block) means admission and IV ceftriaxone 2 g daily, then oral therapy once high-grade block resolves, 14-21 days in total. About 40% need temporary pacing; permanent block is rare. More in the Lyme disease breakdown.
- Drug toxicity: digoxin (anti-digoxin Fab if severe), beta blocker overdose (glucagon may help), calcium channel blockers. Block on stable therapeutic doses usually does not reverse when the drug is stopped.
- Others: hyperkalemia, severe hypothyroidism, high vagal tone (sleep apnea, athletes).
Guideline rule: treat a reversible cause first, with temporary transvenous pacing if needed, and do not implant a permanent pacemaker after complete resolution.
Unstable bradycardia from AV block: the acute ladder
- Atropine 1 mg IV every 3-5 minutes, up to 3 mg (2025 AHA bradycardia algorithm). It acts on the AV node, so it helps nodal block, is unlikely to help infranodal block (use it cautiously when the QRS is wide), and is ineffective in a transplanted heart without vagal reinnervation.
- If atropine fails: transcutaneous pacing and/or a dopamine or epinephrine infusion (isoproterenol is another option); the 2018 guideline reserves beta-agonists for patients unlikely to have coronary ischemia.
- Temporary transvenous pacing for refractory block, then decide on a permanent device.
How USMLE tests it
- 2:1 can't be classified, so choose the answer that localizes it.
- Blocked premature atrial complex mimics Mobitz II, but its P wave comes early (often hidden in the T wave). Mobitz II needs P waves at a steady rate.
- AV dissociation is not always complete block. In complete block the atria beat faster than the ventricles; dissociation with a faster junctional or ventricular rhythm is a different problem.
- Atropine for a wide-QRS infranodal block is the wrong answer when pacing is available.
- Young patient, summer, erythema migrans, fluctuating block: Lyme carditis, treated with antibiotics and, if needed, temporary pacing, not an immediate permanent pacemaker.
- Asymptomatic Mobitz I in an athlete: reassurance. Pacing is harm.
Practice question
A 74-year-old man has had two episodes of near-syncope in the past week. He takes no medications and has no tick exposure. He is alert, with pulse 54/min and blood pressure 132/74 mm Hg. ECG shows sinus P waves at a regular rate of 78/min. Most P waves conduct with a constant PR interval of 0.17 seconds, but every third or fourth P wave is suddenly not followed by a QRS complex; the PR interval is identical before and after each blocked P wave. QRS duration is 0.14 seconds with a right bundle branch block pattern. Potassium and TSH are normal. Which is the most appropriate next step?
A. Reassurance and a repeat ECG in 6 months B. 30-day ambulatory ECG monitoring before deciding on therapy C. IV atropine, with discharge if the heart rate improves D. Permanent pacemaker implantation E. Oral theophylline
Answer: D. A constant PR with suddenly blocked P waves at a steady atrial rate, plus a wide QRS, is Mobitz II: infranodal block that can progress without warning to complete heart block with an unreliable ventricular escape. With no reversible cause, permanent pacing is a Class I recommendation, with or without symptoms.
- A: reassurance suits first-degree block or asymptomatic nodal Mobitz I, not infranodal block.
- B: long-term monitoring helps link intermittent symptoms to nodal block. Mobitz II already meets the pacing indication, so waiting only adds risk.
- C: atropine works on the AV node and is unlikely to improve infranodal block; even a brief response would not remove the need for a pacemaker.
- E: aminophylline and theophylline have a limited role in AV nodal block during acute inferior MI. They do not treat degenerative His-Purkinje disease.
Key takeaways
- 1st degree: PR >200 ms with 1:1 conduction; usually benign and untreated.
- Mobitz I: PR lengthens until a beat drops; AV node; physiologic in athletes and sleep; inferior MI. No pacemaker unless symptoms are clearly caused by the block.
- Mobitz II: constant PR, sudden drop, usually wide QRS; His-Purkinje; pacemaker regardless of symptoms.
- High-grade and third-degree block (AV dissociation, atrial rate > ventricular rate, cannon a waves) get a pacemaker unless the cause is reversible.
- Reversible causes first: Lyme carditis, drug toxicity, hyperkalemia and transient post-MI block get treatment and, if needed, temporary pacing.
- Atropine for nodal block, pacing for infranodal block. The full ECG approach is in How to Read an ECG.
Sources
- Atrioventricular Block — Merck Manual Professional Edition (2024)
- Atrioventricular Block — StatPearls, NCBI Bookshelf (2024)
- First-Degree Heart Block — StatPearls, NCBI Bookshelf (2023)
- Second-Degree Atrioventricular Block — StatPearls, NCBI Bookshelf (2023)
- Third-Degree Atrioventricular Block — StatPearls, NCBI Bookshelf (2023)
- Atrioventricular Node — StatPearls, NCBI Bookshelf (2026)
- 2018 ACC/AHA/HRS Guideline on the Evaluation and Management of Patients With Bradycardia and Cardiac Conduction Delay, full text — Heart Rhythm (2019), copy hosted by STS
- 2018 ACC/AHA/HRS Guideline on Bradycardia and Cardiac Conduction Delay: Key Points — American College of Cardiology (2018)
- Clinical Care and Treatment of Lyme Carditis — CDC (2026)
- Atropine — StatPearls, NCBI Bookshelf (2025)
- Adult Bradycardia With a Pulse Algorithm — American Heart Association (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
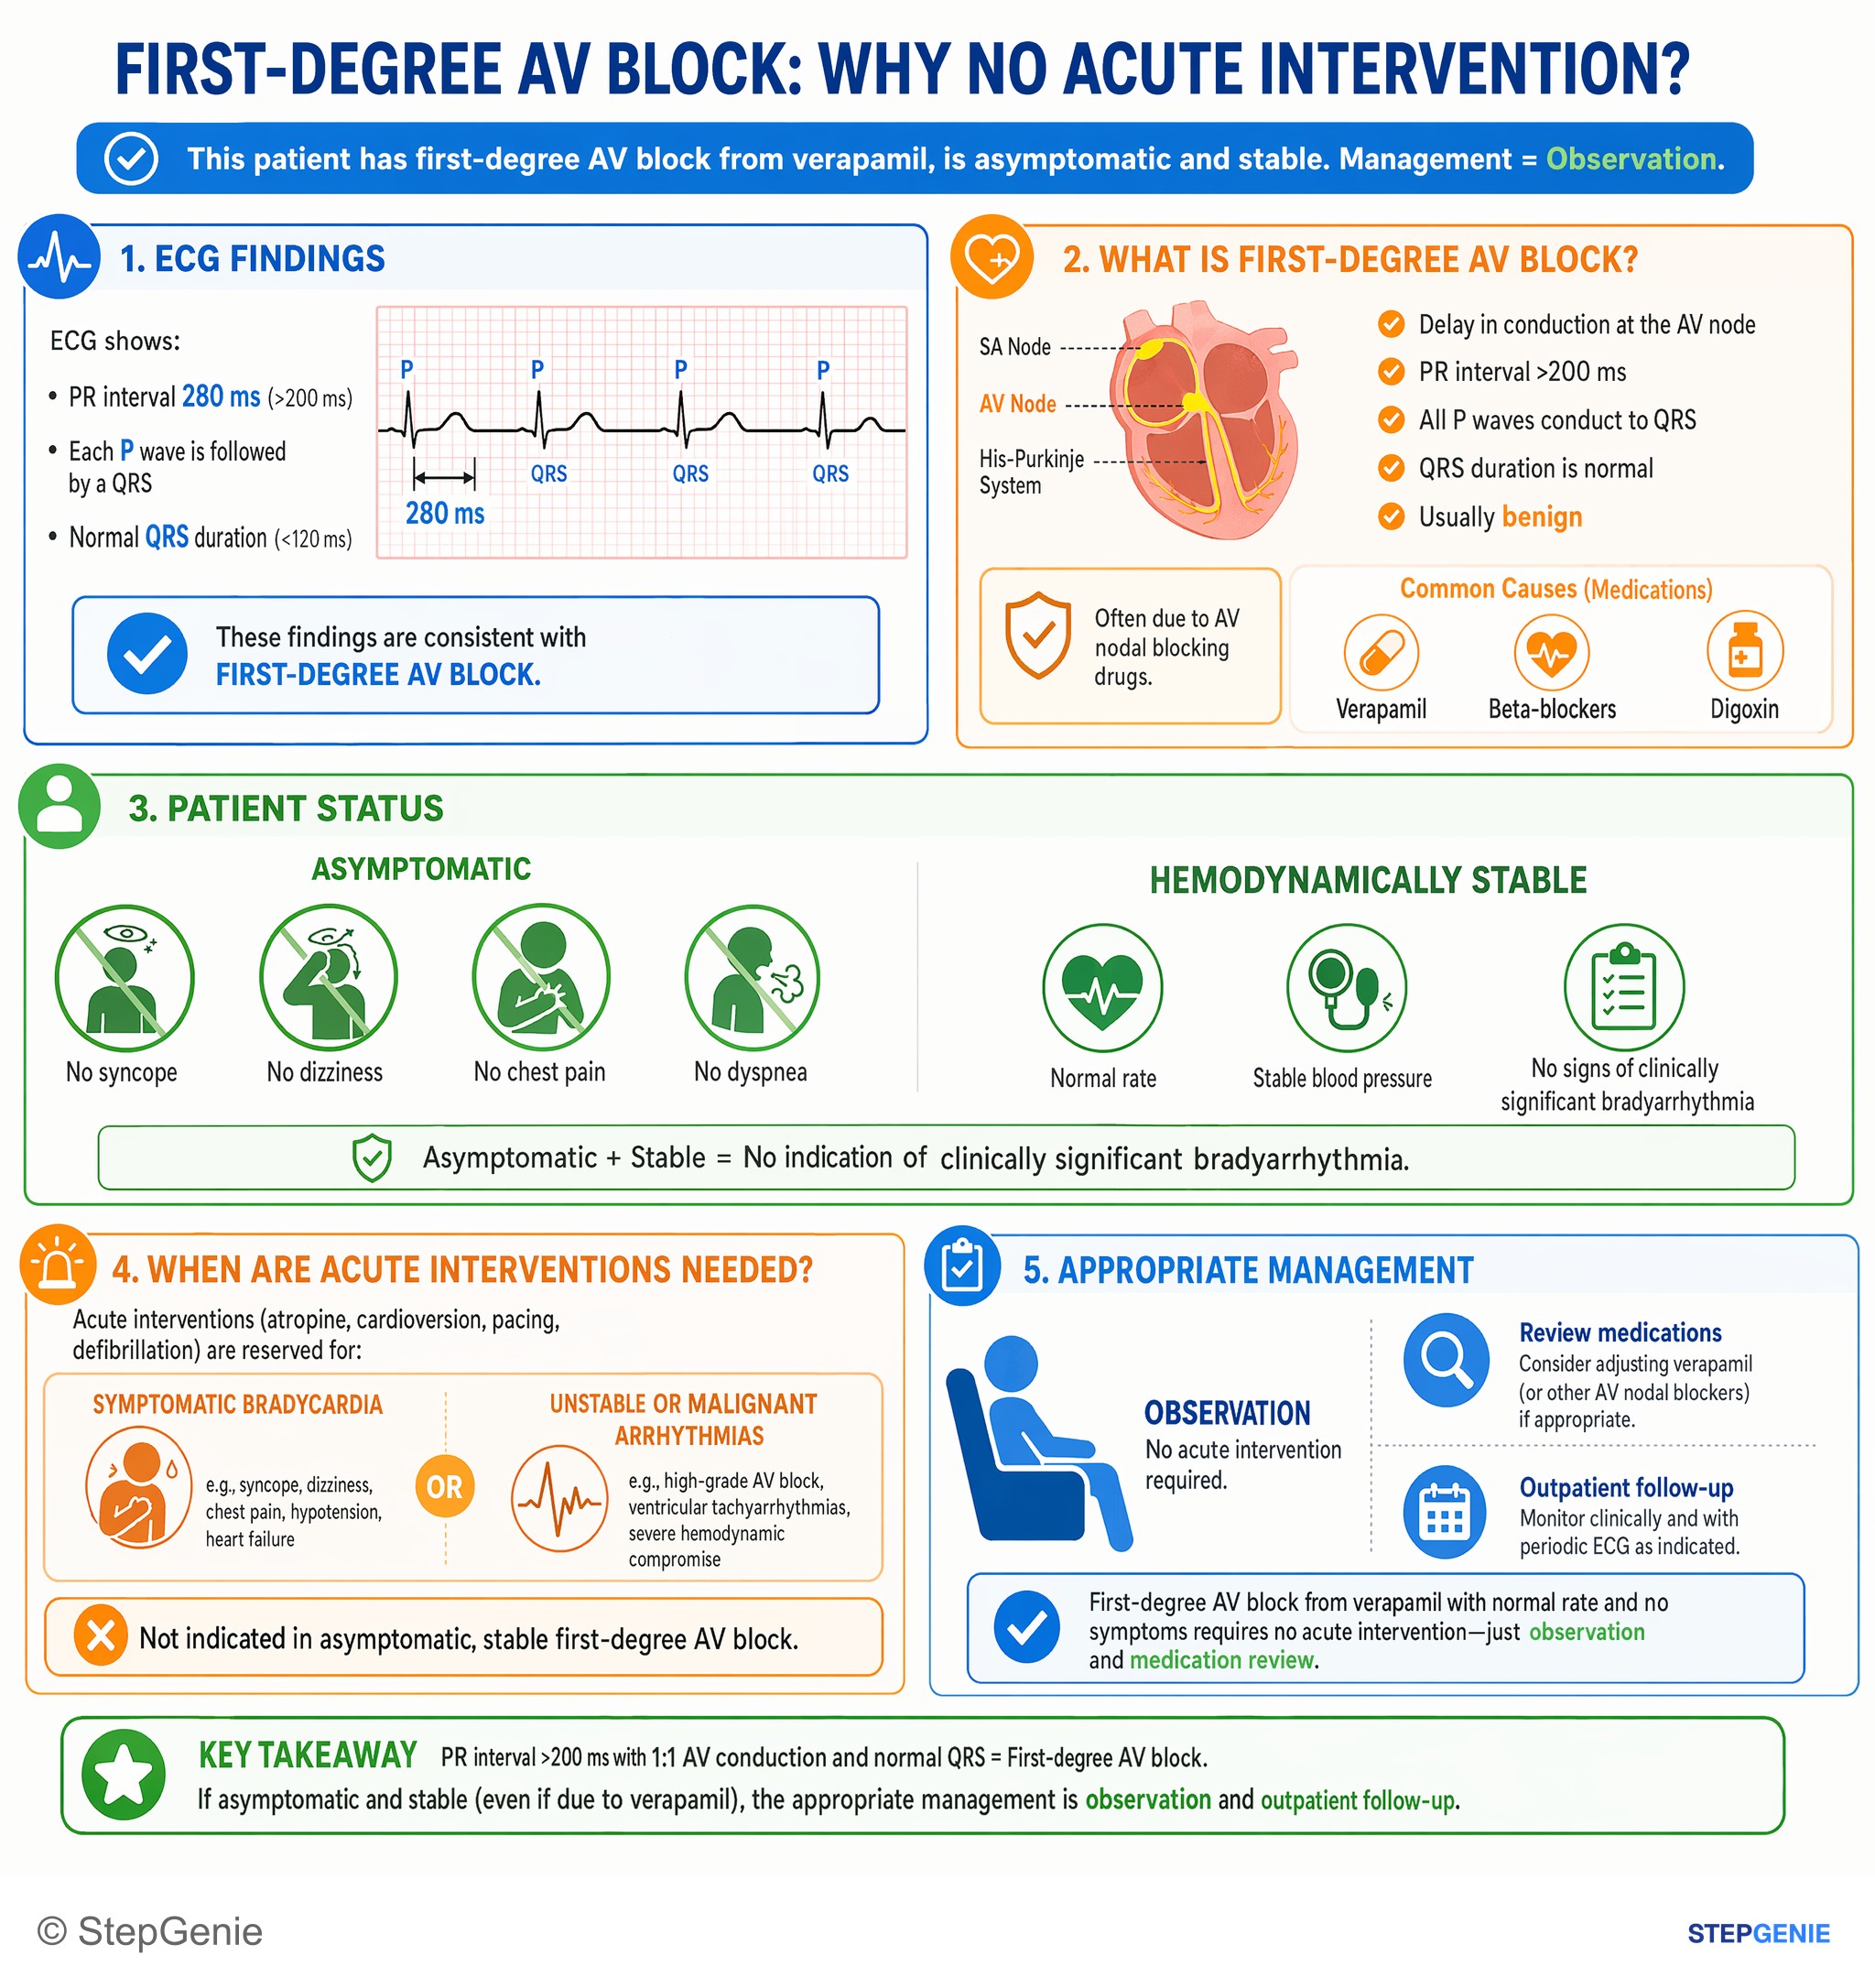
First-degree AV block from verapamil with normal rate and no symptoms requires no acute intervention—just observation and medication review.
USMLE Step 2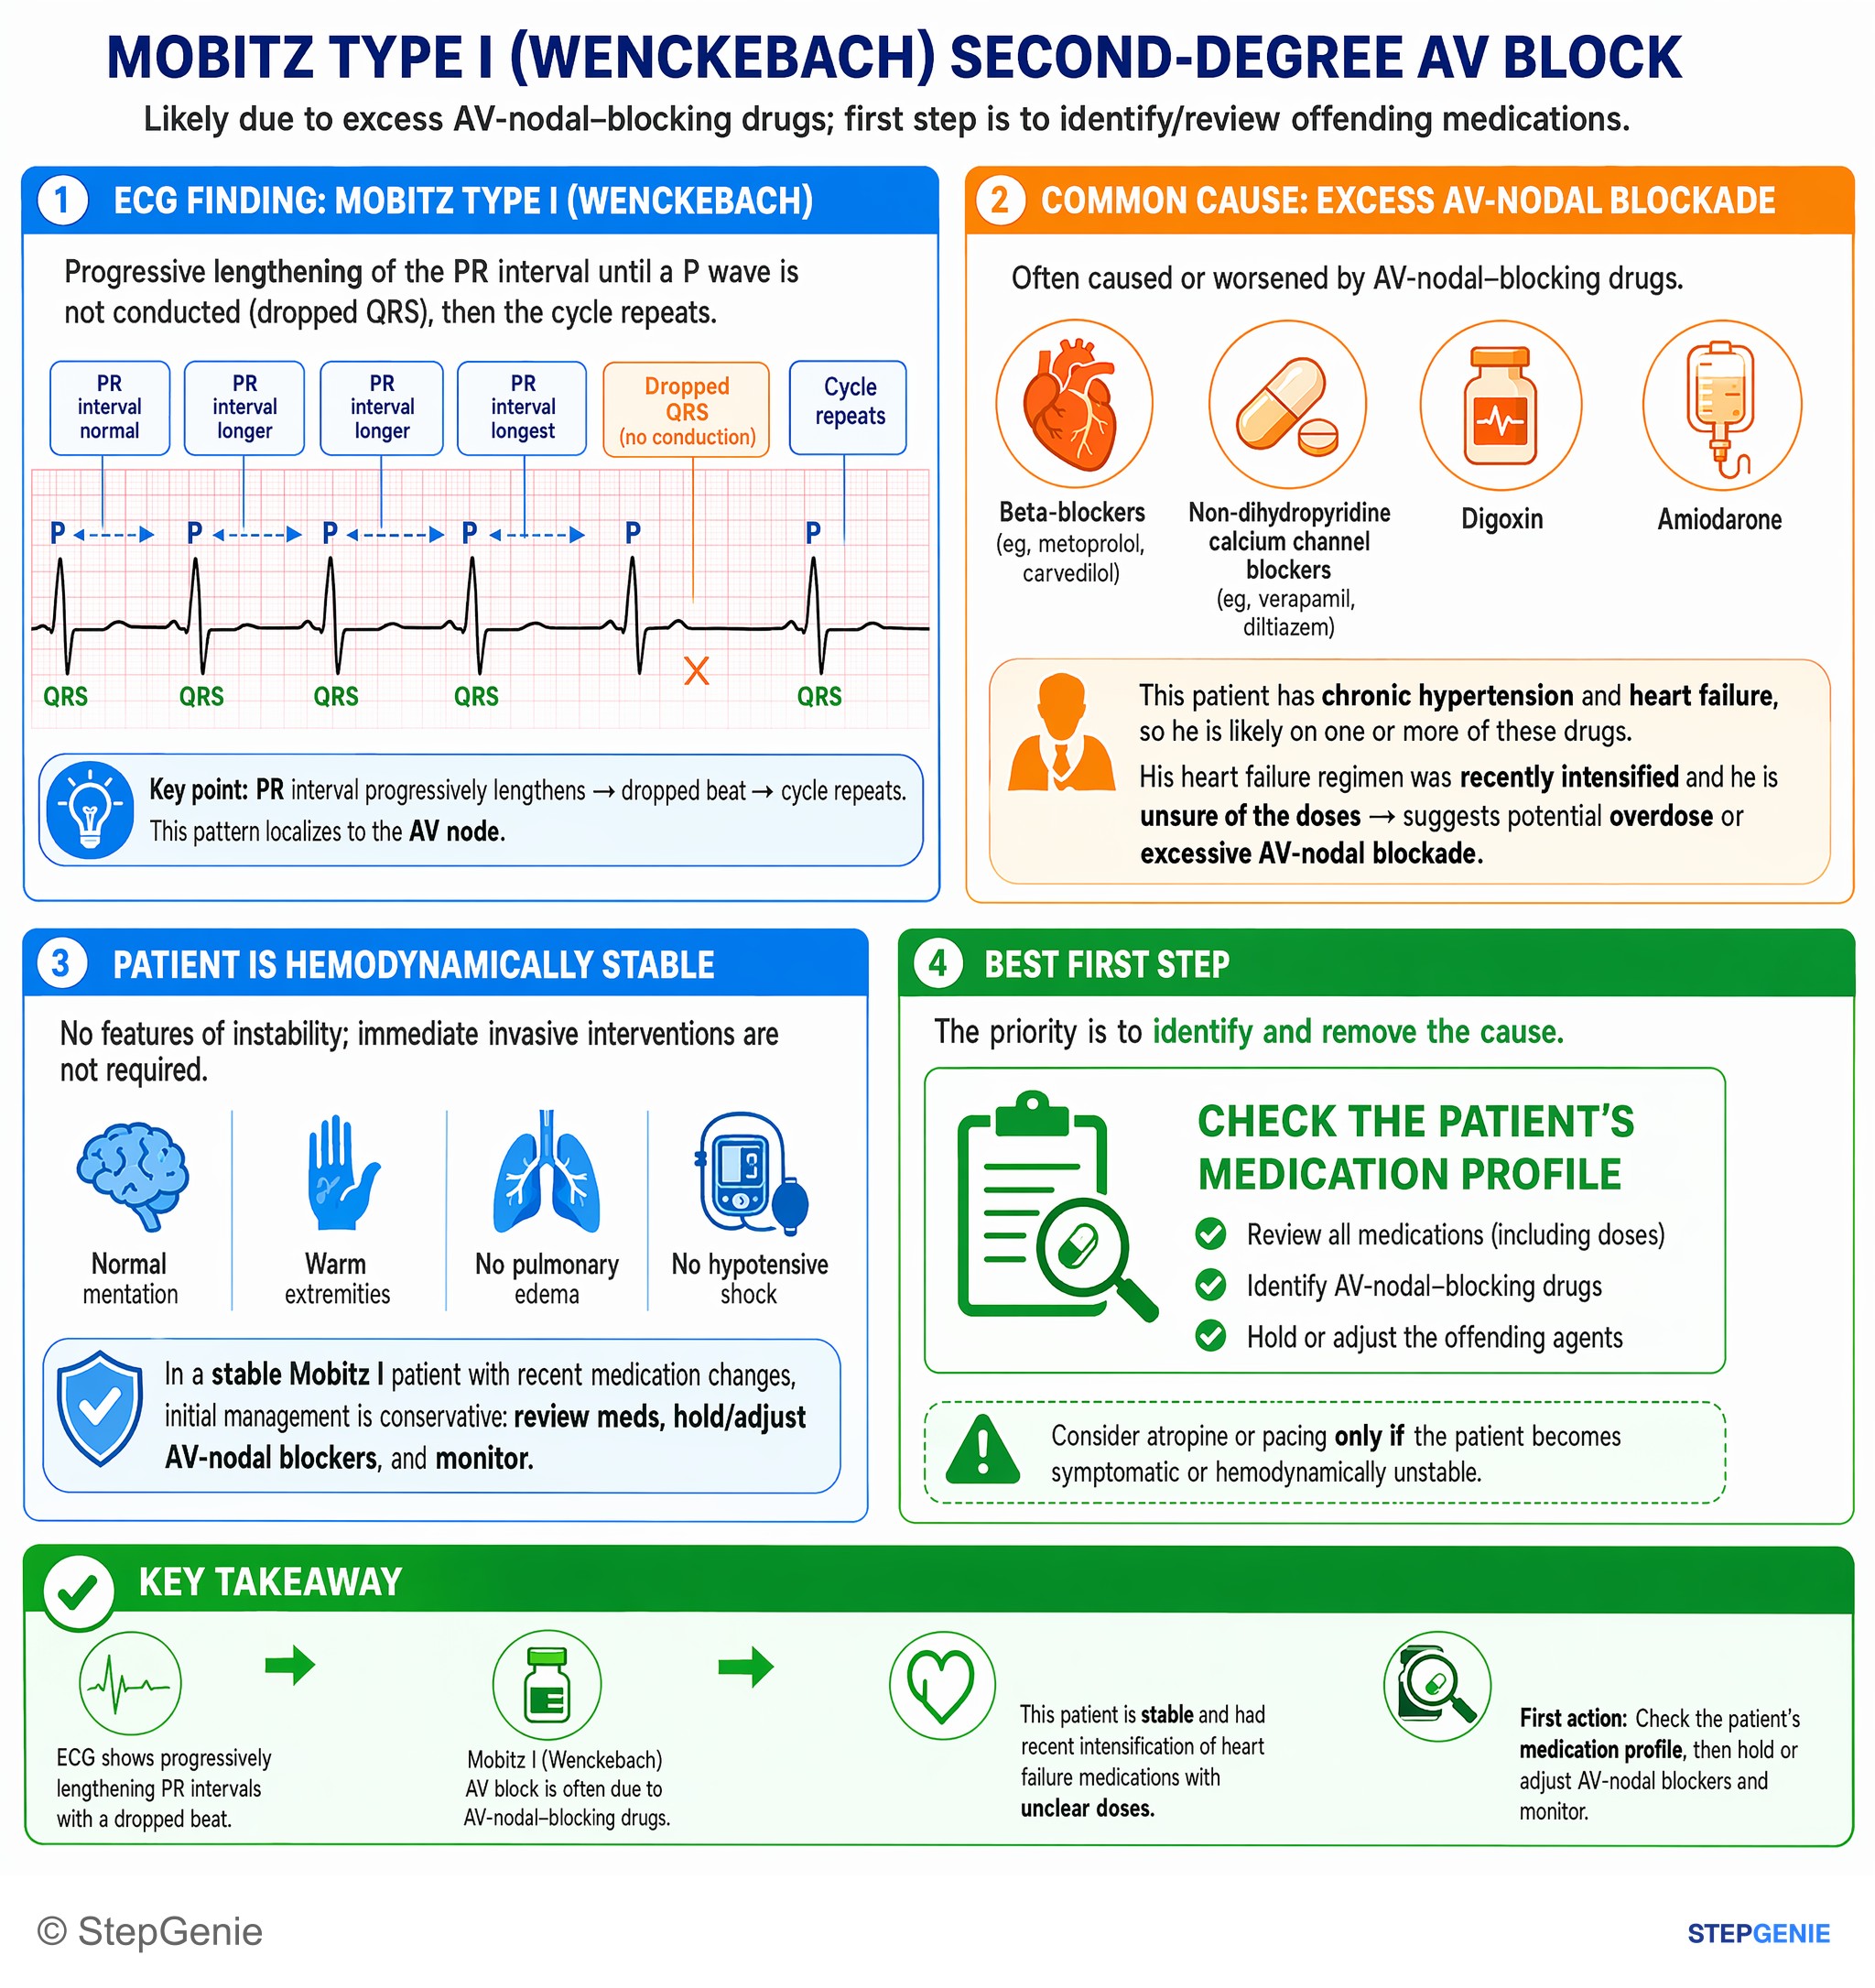
Mobitz type I (Wenckebach) AV block likely due to excess AV-nodal–blocking drugs; first step is to identify/review offending medications.
USMLE Step 2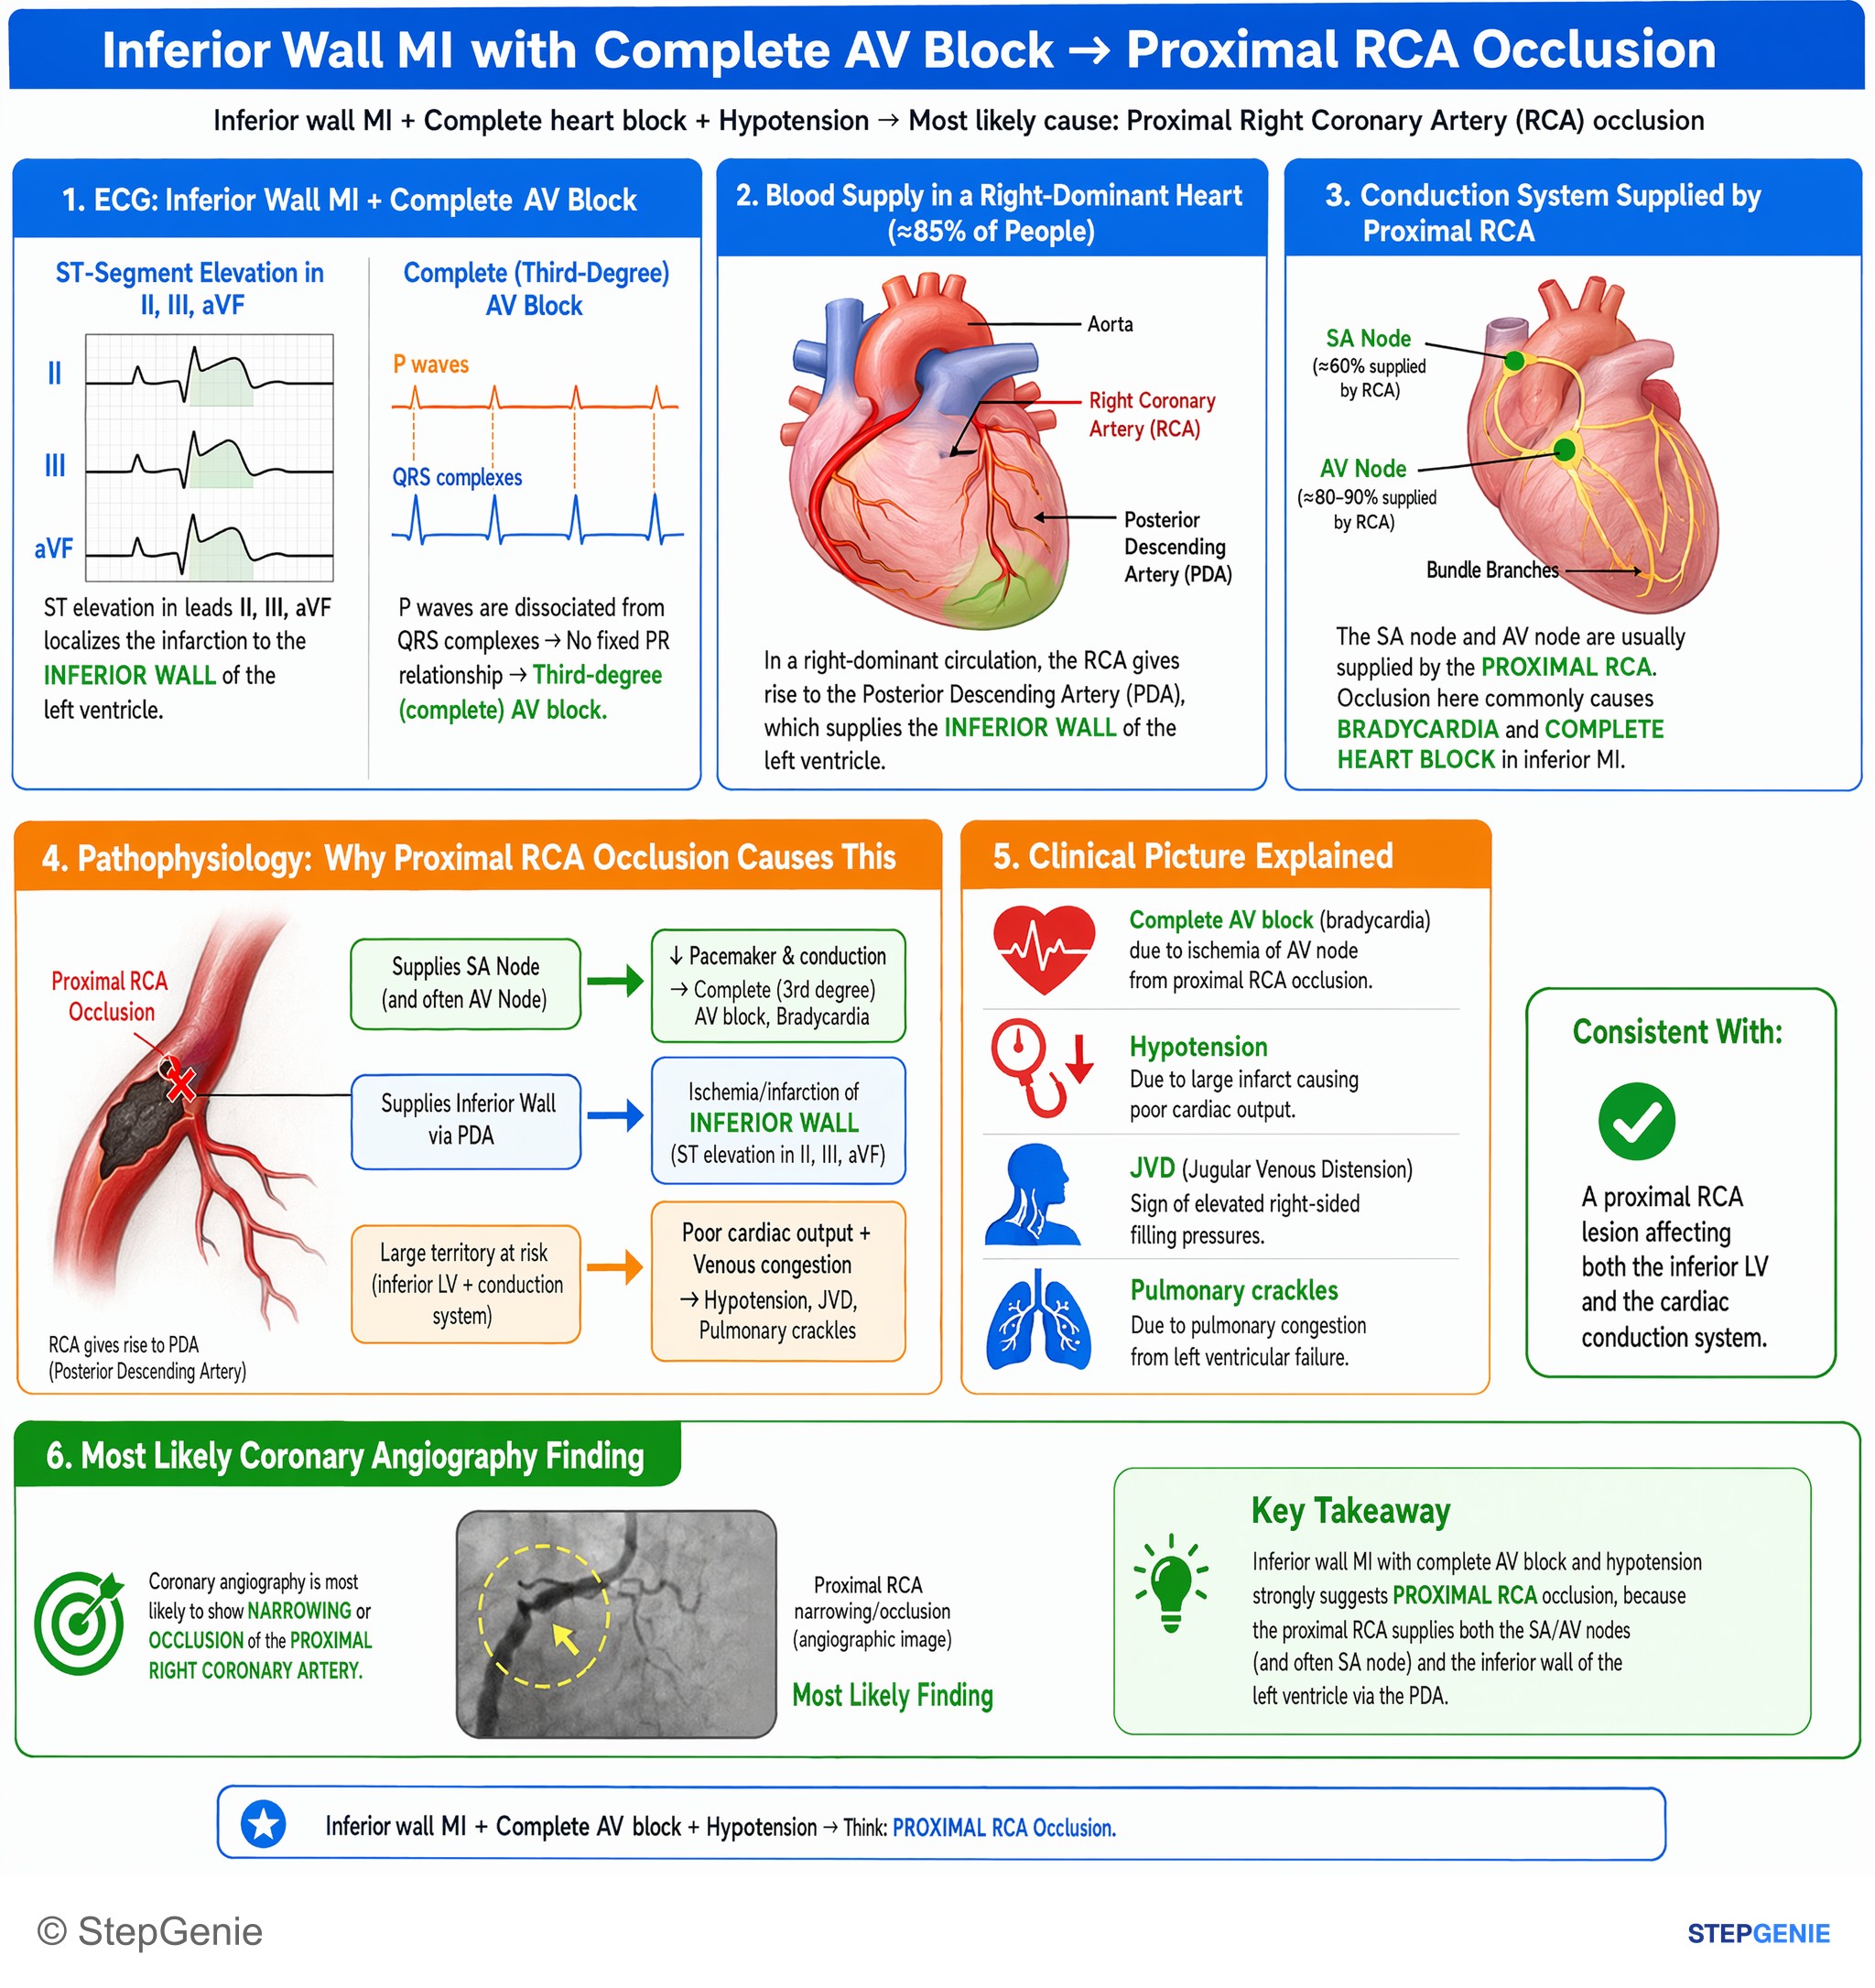
Inferior wall MI with complete AV block and hypotension implies proximal RCA occlusion supplying SA/AV nodes and inferior LV wall.
USMLE Step 1Frequently Asked Questions
How do you tell Mobitz I from Mobitz II on an ECG?
Compare the PR interval just before and just after the dropped beat. In Mobitz I (Wenckebach) the PR lengthens beat by beat until a P wave fails to conduct, so the PR before the pause is the longest and the one after it is the shortest. In Mobitz II the PR stays constant before and after a suddenly blocked P wave, and the QRS is usually wide. Mobitz I is usually in the AV node; Mobitz II is below it, in the His-Purkinje system.
Why is Mobitz II more dangerous than Mobitz I?
Mobitz II is block below the AV node, in the His bundle or bundle branches. Infranodal block can progress suddenly to complete heart block, and the ventricular escape rhythm that then takes over is slow (about 20-40 beats per minute) and unreliable, which causes syncope or worse. Nodal Mobitz I progresses slowly, and its junctional escape is faster and more reliable. That is why the ACC/AHA/HRS guideline recommends a permanent pacemaker for Mobitz II regardless of symptoms.
Is 2:1 AV block Mobitz I or Mobitz II?
Neither can be named from the strip. In 2:1 AV block every other P wave is blocked, so there are never two conducted beats in a row to show whether the PR lengthens, and the guideline says 2:1 block cannot be classified as Mobitz I or II. A narrow QRS, Wenckebach cycles elsewhere on the strip and better conduction with exercise or atropine point to the AV node; a wide QRS and worse conduction with exercise point below it. An electrophysiology study can settle the level.
What does third-degree heart block look like on an ECG?
In third-degree (complete) heart block no P wave reaches the ventricles. P waves and QRS complexes each keep their own rhythm, the PR interval varies at random, and the atrial rate is faster than the ventricular rate. A junctional escape gives a narrow QRS at about 40-60 beats per minute (Merck gives 35-50) and is fairly reliable; a ventricular escape gives a wide QRS at 20-40 and is unreliable. On examination, look for cannon a waves and a first heart sound that changes in loudness.
When does AV block need a pacemaker?
Under the 2018 ACC/AHA/HRS guideline, still the current US bradycardia guideline, a permanent pacemaker is recommended for acquired Mobitz II, high-grade and third-degree AV block not caused by a reversible or physiologic problem, whether or not the patient has symptoms. First-degree, Mobitz I and nodal 2:1 block are paced only when symptoms are clearly caused by the block. Reversible causes such as Lyme carditis, drug toxicity or transient block after MI are treated first, with temporary pacing if needed.
Which type of MI causes which AV block?
Inferior MI usually involves the right coronary artery, which gives rise to the AV nodal artery in right-dominant hearts, so the block sits at the AV node, driven by vagal tone, local adenosine and ischemia. Expect first-degree block, Mobitz I or narrow-complex complete block that usually resolves and may respond to atropine. Anterior MI causes block through extensive necrosis of the His-Purkinje system: Mobitz II or wide-complex complete block, a worse prognosis and a need for immediate transvenous pacing.