You’re on a question block, and suddenly the stem hits: “unresponsive, no pulse, monitor shows chaotic waveform.” This is one of those Step-defining moments—because ventricular fibrillation (VF) is both instantly lethal and instantly testable. The trick isn’t just recognizing VF; it’s understanding why every other option is wrong so you don’t get trapped by “sounds right” management.
Tag: Cardiovascular > ECG Interpretation
The Clinical Vignette (Q-Bank Style)
A 62-year-old man collapses in the hospital hallway. He’s unresponsive and apneic. No palpable pulse. A rhythm strip is shown with irregular, chaotic oscillations of varying amplitude with no identifiable P waves or QRS complexes.
What is the next best step in management?
Stepwise Approach (How You Should Think on Test Day)
When someone is unresponsive + pulseless, you don’t “interpret ECGs” first—you run an arrest algorithm.
- Confirm pulselessness quickly (≤10 seconds)
- Start high-quality CPR
- Identify rhythm:
- Shockable: VF / pulseless VT → defibrillate
- Non-shockable: asystole / PEA → CPR + epinephrine (no shock)
VF is a shockable rhythm because the myocardium is electrically chaotic but still “excitable” enough to be reset.
The Correct Answer: Immediate Unsynchronized Defibrillation (Plus CPR)
Why this is correct
Ventricular fibrillation is:
- Chaotic ventricular activity
- No effective cardiac output → no pulse
- Rapidly progresses to death without intervention
Best next step:
- Immediate defibrillation (unsynchronized) + CPR
- Then follow ACLS: epinephrine, repeat shocks, antiarrhythmic, address reversible causes
High-yield VF management pearls
- Defibrillation is unsynchronized (no organized QRS to sync with)
- Do not delay shock to intubate, get labs, or place lines
- After shock:
- Resume CPR immediately for 2 minutes
- Recheck rhythm/pulse
- Epinephrine every 3–5 min
- Amiodarone for refractory VF/pulseless VT (lidocaine is an alternative)
ECG Hallmarks: How VF Looks vs “Almost VF”
| Rhythm | Key ECG Feature | Pulse? | Shock? |
|---|---|---|---|
| Ventricular fibrillation | Chaotic, irregular waveform; no identifiable P/QRS/T | No | Yes (defibrillate) |
| Pulseless VT | Wide, regular tachycardia | No | Yes (defibrillate) |
| Torsades de pointes | Polymorphic VT “twisting” around baseline | Often unstable/pulseless | Often shock + magnesium |
| Asystole | Flatline (confirm in ≥2 leads) | No | No |
| PEA | Organized electrical activity without pulse | No | No |
Why the Other Answer Choices Matter (Distractor Breakdown)
Below are the most common distractors for VF questions—and exactly why they’re wrong.
Distractor 1: Synchronized Cardioversion
Why it tempts you: “Electrical shock fixes arrhythmias.”
Why it’s wrong in VF: Cardioversion requires a QRS to synchronize with. In VF there is no organized QRS, so synchronized mode can:
- Fail to deliver a shock, or
- Delay definitive treatment
Use synchronized cardioversion for:
- Unstable atrial fibrillation
- Unstable atrial flutter
- Unstable SVT
- Unstable monomorphic VT with a pulse
Bottom line: VF is pulseless + disorganized → defibrillation (unsynchronized).
Distractor 2: Atropine
Why it tempts you: “They’re crashing—give atropine!”
Why it’s wrong: Atropine treats symptomatic bradycardia (and historically was used in asystole, but that’s no longer standard in ACLS). VF is not a vagal/brady problem—it’s chaotic ventricular depolarization.
Atropine is for:
- Symptomatic sinus bradycardia
- Some AV nodal blocks (often temporary bridge)
Bottom line: Atropine won’t fix VF, and it wastes time.
Distractor 3: Amiodarone (before defibrillation)
Why it tempts you: “It’s a ventricular arrhythmia, so give an antiarrhythmic.”
Why it’s wrong: In VF, the priority is electric reset. Antiarrhythmics are adjuncts for refractory VF/pulseless VT—not first-line before shock.
When amiodarone fits:
- VF/pulseless VT persisting after defibrillation attempts
- Given during ongoing CPR as part of ACLS sequence
Bottom line: Shock first. Drugs support the algorithm—they don’t replace it.
Distractor 4: Adenosine
Why it tempts you: “Rapid rhythm—try adenosine.”
Why it’s wrong: Adenosine transiently blocks AV node conduction, useful for:
- AVNRT / AVRT
- Some regular, narrow-complex tachycardias
VF is not AV-node dependent and has no organized atrial-to-ventricular conduction to interrupt.
Bottom line: Adenosine does nothing for VF (or for atrial fibrillation).
Distractor 5: IV Magnesium
Why it tempts you: Magnesium is famous in boards questions.
Why it’s wrong (for classic VF): Magnesium is most classically indicated for:
- Torsades de pointes (polymorphic VT associated with prolonged QT)
- Hypomagnesemia-related arrhythmias
VF management is still CPR + defibrillation first. If the rhythm is actually torsades (polymorphic VT “twisting”), magnesium becomes central.
Board tip: If the strip looks like “twisting points” and the stem hints at prolonged QT (e.g., macrolides, antipsychotics, hypocalcemia, congenital long QT) → think torsades → magnesium.
Distractor 6: Epinephrine as the first step
Why it tempts you: Epinephrine is part of ACLS arrest care.
Why it’s wrong as first step in VF: In shockable rhythms, defibrillation is the definitive initial intervention. Epinephrine is important, but not before the first shock unless the scenario explicitly has you already mid-algorithm.
Best sequence conceptually:
- CPR + defibrillation ASAP for VF/pulseless VT
- Epinephrine comes during ongoing cycles after initial shock attempts
Bottom line: Don’t replace electricity with catecholamines.
“But What If…” Rapid-Fire USMLE Traps
1) “There’s VF on the monitor—but the patient has a pulse.”
That’s almost never true VF. Consider:
- Artifact (loose leads, tremor)
- Another rhythm misread
True VF = no pulse (by definition clinically).
2) “Flatline—so shock?”
Asystole is not shockable. Before committing:
- Check leads/connection
- Increase gain
- Confirm in two leads
Management is CPR + epinephrine and search for reversible causes.
3) The H’s and T’s you should reflexively consider
In any arrest, especially if refractory:
H’s:
- Hypovolemia
- Hypoxia
- Hydrogen ion (acidosis)
- Hypo-/hyperkalemia
- Hypothermia
T’s:
- Tension pneumothorax
- Cardiac tamponade
- Toxins
- Thrombosis (pulmonary)
- Thrombosis (coronary)
High-Yield Summary (What You Need to Remember)
- Ventricular fibrillation = chaotic rhythm + no pulse → immediate unsynchronized defibrillation + CPR
- Synchronized cardioversion requires an organiz
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
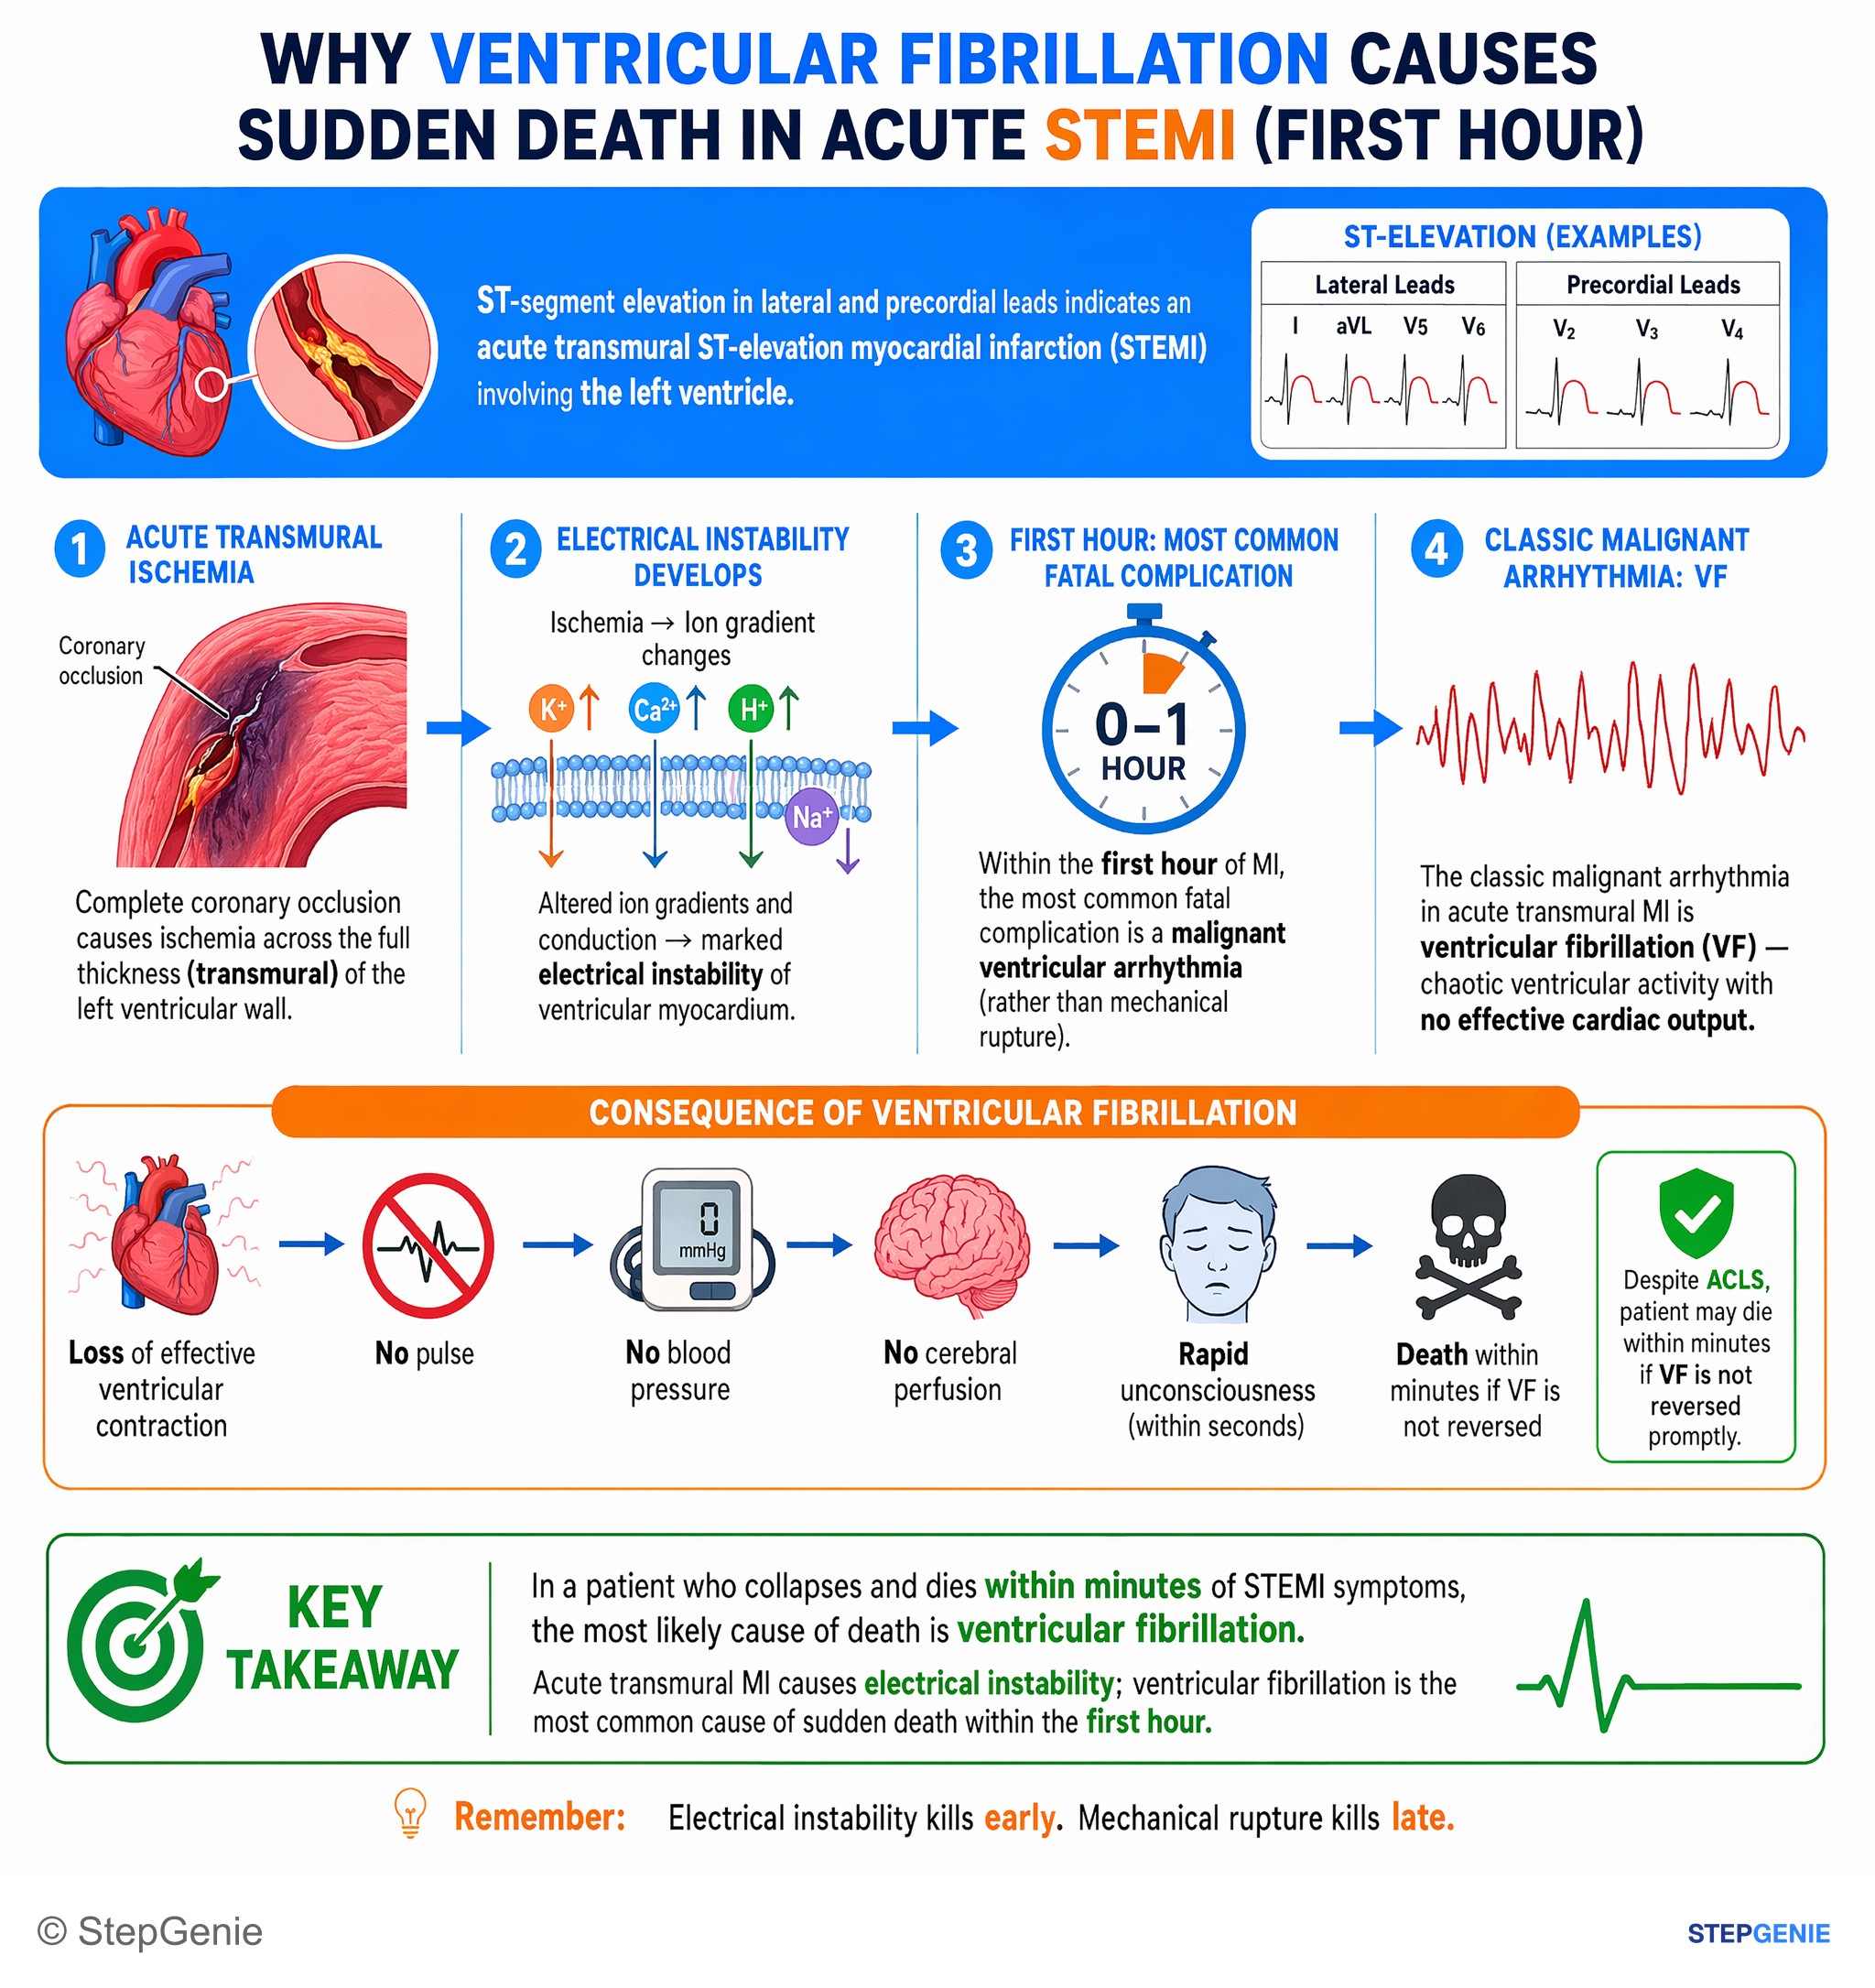
Acute transmural MI causes electrical instability; ventricular fibrillation is the most common cause of sudden death within the first hour.
USMLE Step 1Frequently Asked Questions
What is the next best step for ventricular fibrillation on an exam stem?
The next best step is immediate unsynchronized defibrillation with high-quality CPR. Ventricular fibrillation is chaotic ventricular activity with no effective cardiac output, so the patient has no pulse and can rapidly die without intervention. Because VF is a shockable rhythm, you should not delay the shock to intubate, get labs, or place lines, and then continue the ACLS sequence afterward.
Why is ventricular fibrillation treated with unsynchronized defibrillation instead of synchronized cardioversion?
Ventricular fibrillation is treated with unsynchronized defibrillation because there is no organized QRS complex to synchronize to. Synchronized cardioversion depends on detecting a QRS, so in VF it may fail to deliver a shock or delay definitive treatment. VF is pulseless and electrically chaotic, making defibrillation the correct intervention rather than synchronized cardioversion.
How do you tell ventricular fibrillation from pulseless VT, torsades, asystole, and PEA on ECG?
Ventricular fibrillation appears as a chaotic, irregular waveform with varying amplitude and no identifiable P waves, QRS complexes, or T waves. Pulseless VT is a wide, regular tachycardia, while torsades is polymorphic VT that twists around the baseline. Asystole is a flatline that should be confirmed in at least two leads, and PEA shows organized electrical activity without a pulse.
Why is amiodarone not the first treatment for ventricular fibrillation?
Amiodarone is not the first treatment for ventricular fibrillation because the priority is an immediate electrical reset with defibrillation. Antiarrhythmic drugs are adjuncts used for refractory VF or pulseless VT that persists after defibrillation attempts. In a VF arrest, shock first and continue CPR, then add medications such as epinephrine and amiodarone as part of the ACLS sequence.
When should you think magnesium instead of classic VF management?
You should think magnesium when the rhythm is torsades de pointes rather than classic ventricular fibrillation. Torsades is a polymorphic VT that appears to twist around the baseline and is often associated with prolonged QT. In classic VF, management still starts with CPR and defibrillation first, whereas magnesium becomes central when the rhythm strip and clinical clues point to torsades.