Atherosclerosis is one of those “if you can draw it, you can’t forget it” Step topics—because the pathogenesis is basically a predictable timeline: endothelial injury → lipid entry → inflammation → smooth muscle response → fibrous cap → rupture/thrombosis. Here’s a quick, shareable draw-it-out method to lock in the sequence and the high-yield associations.
The Draw-It-Out Method (30 seconds, one napkin)
Step 1: Draw the artery wall (3 layers)
Sketch a tube and label:
- Intima (where plaques live)
- Media
- Adventitia
Add a thin inner lining = endothelium.
Step 2: Add the “injury lightning bolt” to the endothelium
Write Endothelial dysfunction/injury and draw a crack.
Common USMLE triggers:
- HTN (shear stress)
- Smoking
- Hyperlipidemia (esp. ↑ LDL)
- Diabetes (glycation, oxidative stress)
- Inflammation (e.g., chronic)
One-liner: Atherosclerosis starts with endothelial dysfunction, not a clot.
The Mnemonic Visual: “LDL = Lipid Dumps into the Lining”
Step 3: Draw LDL particles slipping into the intima
Put a few circles labeled LDL under the endothelium.
Then add “sparks” or “rust” marks: oxidized LDL.
High-yield point:
- Oxidized LDL is pro-inflammatory and chemoattracts immune cells.
One-liner: LDL enters the intima and becomes oxidized—now it’s inflammatory bait.
“Monocytes → Macrophages → Foam Cells” (the fatty streak)
Step 4: Draw immune cells crawling in
Draw a monocyte crossing the endothelium and turning into a macrophage.
Add receptors and label: scavenger receptors.
Then draw the macrophage stuffed with lipid bubbles = foam cell.
Key Step facts:
- Macrophages ingest oxidized LDL via scavenger receptors (not downregulated like LDL receptors) → keeps eating → foam cells
- Fatty streaks are the earliest lesion; can be seen even in young people
One-liner: Foam cells form when macrophages endlessly eat oxidized LDL via scavenger receptors.
Smooth Muscle Migration + Fibrous Cap (the “stable plaque” build)
Step 5: Draw smooth muscle cells (SMCs) moving up into the intima
From the media, draw SMCs migrating into intima and multiplying.
Label what they do:
- Proliferate
- Deposit ECM (collagen)
- Form a fibrous cap over a lipid core
Core concepts:
- PDGF (platelet-derived growth factor) is a classic signal promoting SMC migration/proliferation
- Plaque = lipid core + fibrous cap
One-liner: SMCs “patch” the injury by building a collagen cap—but the lipid core keeps growing underneath.
Stable vs Vulnerable Plaques (USMLE favorite comparison)
| Feature | Stable Plaque | Vulnerable (Unstable) Plaque |
|---|---|---|
| Fibrous cap | Thick | Thin |
| Lipid core | Smaller | Large |
| Inflammation | Less | More macrophages |
| Main complication | Chronic ischemia (stable angina) | Rupture → thrombosis (MI/ACS) |
High-yield tie-in:
- Macrophages secrete MMPs (matrix metalloproteinases) → degrade collagen → thin cap → rupture risk.
One-liner: Stable plaques stenose; vulnerable plaques rupture.
The “Rupture → Thrombus → MI” Finish
Step 6: Draw a crack in the fibrous cap + a red clot
When the cap ruptures/erodes:
- Thrombogenic material (collagen, tissue factor) is exposed
- Platelets adhere/activate/aggregate → thrombus
- Can cause acute coronary syndrome (UA/NSTEMI/STEMI)
High-yield associations:
- STEMI: usually complete occlusion after rupture → transmural ischemia
- NSTEMI/UA: partial occlusion or transient thrombus
One-liner: Most MIs come from plaque rupture with superimposed thrombosis—not gradual narrowing.
Ultra-High-Yield “5 Arrow” Pathogenesis Summary (shareable)
Write this as a single chain on your page:
Endothelial dysfunction → LDL in intima (oxidized) → macrophages → foam cells (fatty streak) → SMC migration + collagen = fibrous cap → rupture/erosion → thrombosis → MI/ACS
Quick Clinical Anchors (Step 1 + Step 2 integrations)
Why risk factors matter (mechanistically)
- HTN: increases endothelial injury (shear stress)
- Smoking: oxidative stress + endothelial dysfunction
- Diabetes: endothelial damage + pro-inflammatory state
- High LDL / low HDL:
- LDL delivers cholesterol into vessel wall
- HDL helps remove cholesterol (reverse transport)
Where plaques like to form
- Branch points and turbulent flow areas (endothelial stress zones)
What “calcification” on imaging hints at
- Often a marker of chronic plaque burden (can be present in stable plaques), but calcification doesn’t guarantee “safe.”
Mini Self-Quiz (30 seconds)
- Earliest lesion? → Fatty streak (foam cells)
- Cell type making the fibrous cap? → Smooth muscle cells
- Most dangerous plaque feature for MI? → Thin cap + large lipid core + inflammation
- Key event that converts plaque to ACS? → Rupture/erosion → thrombosis
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
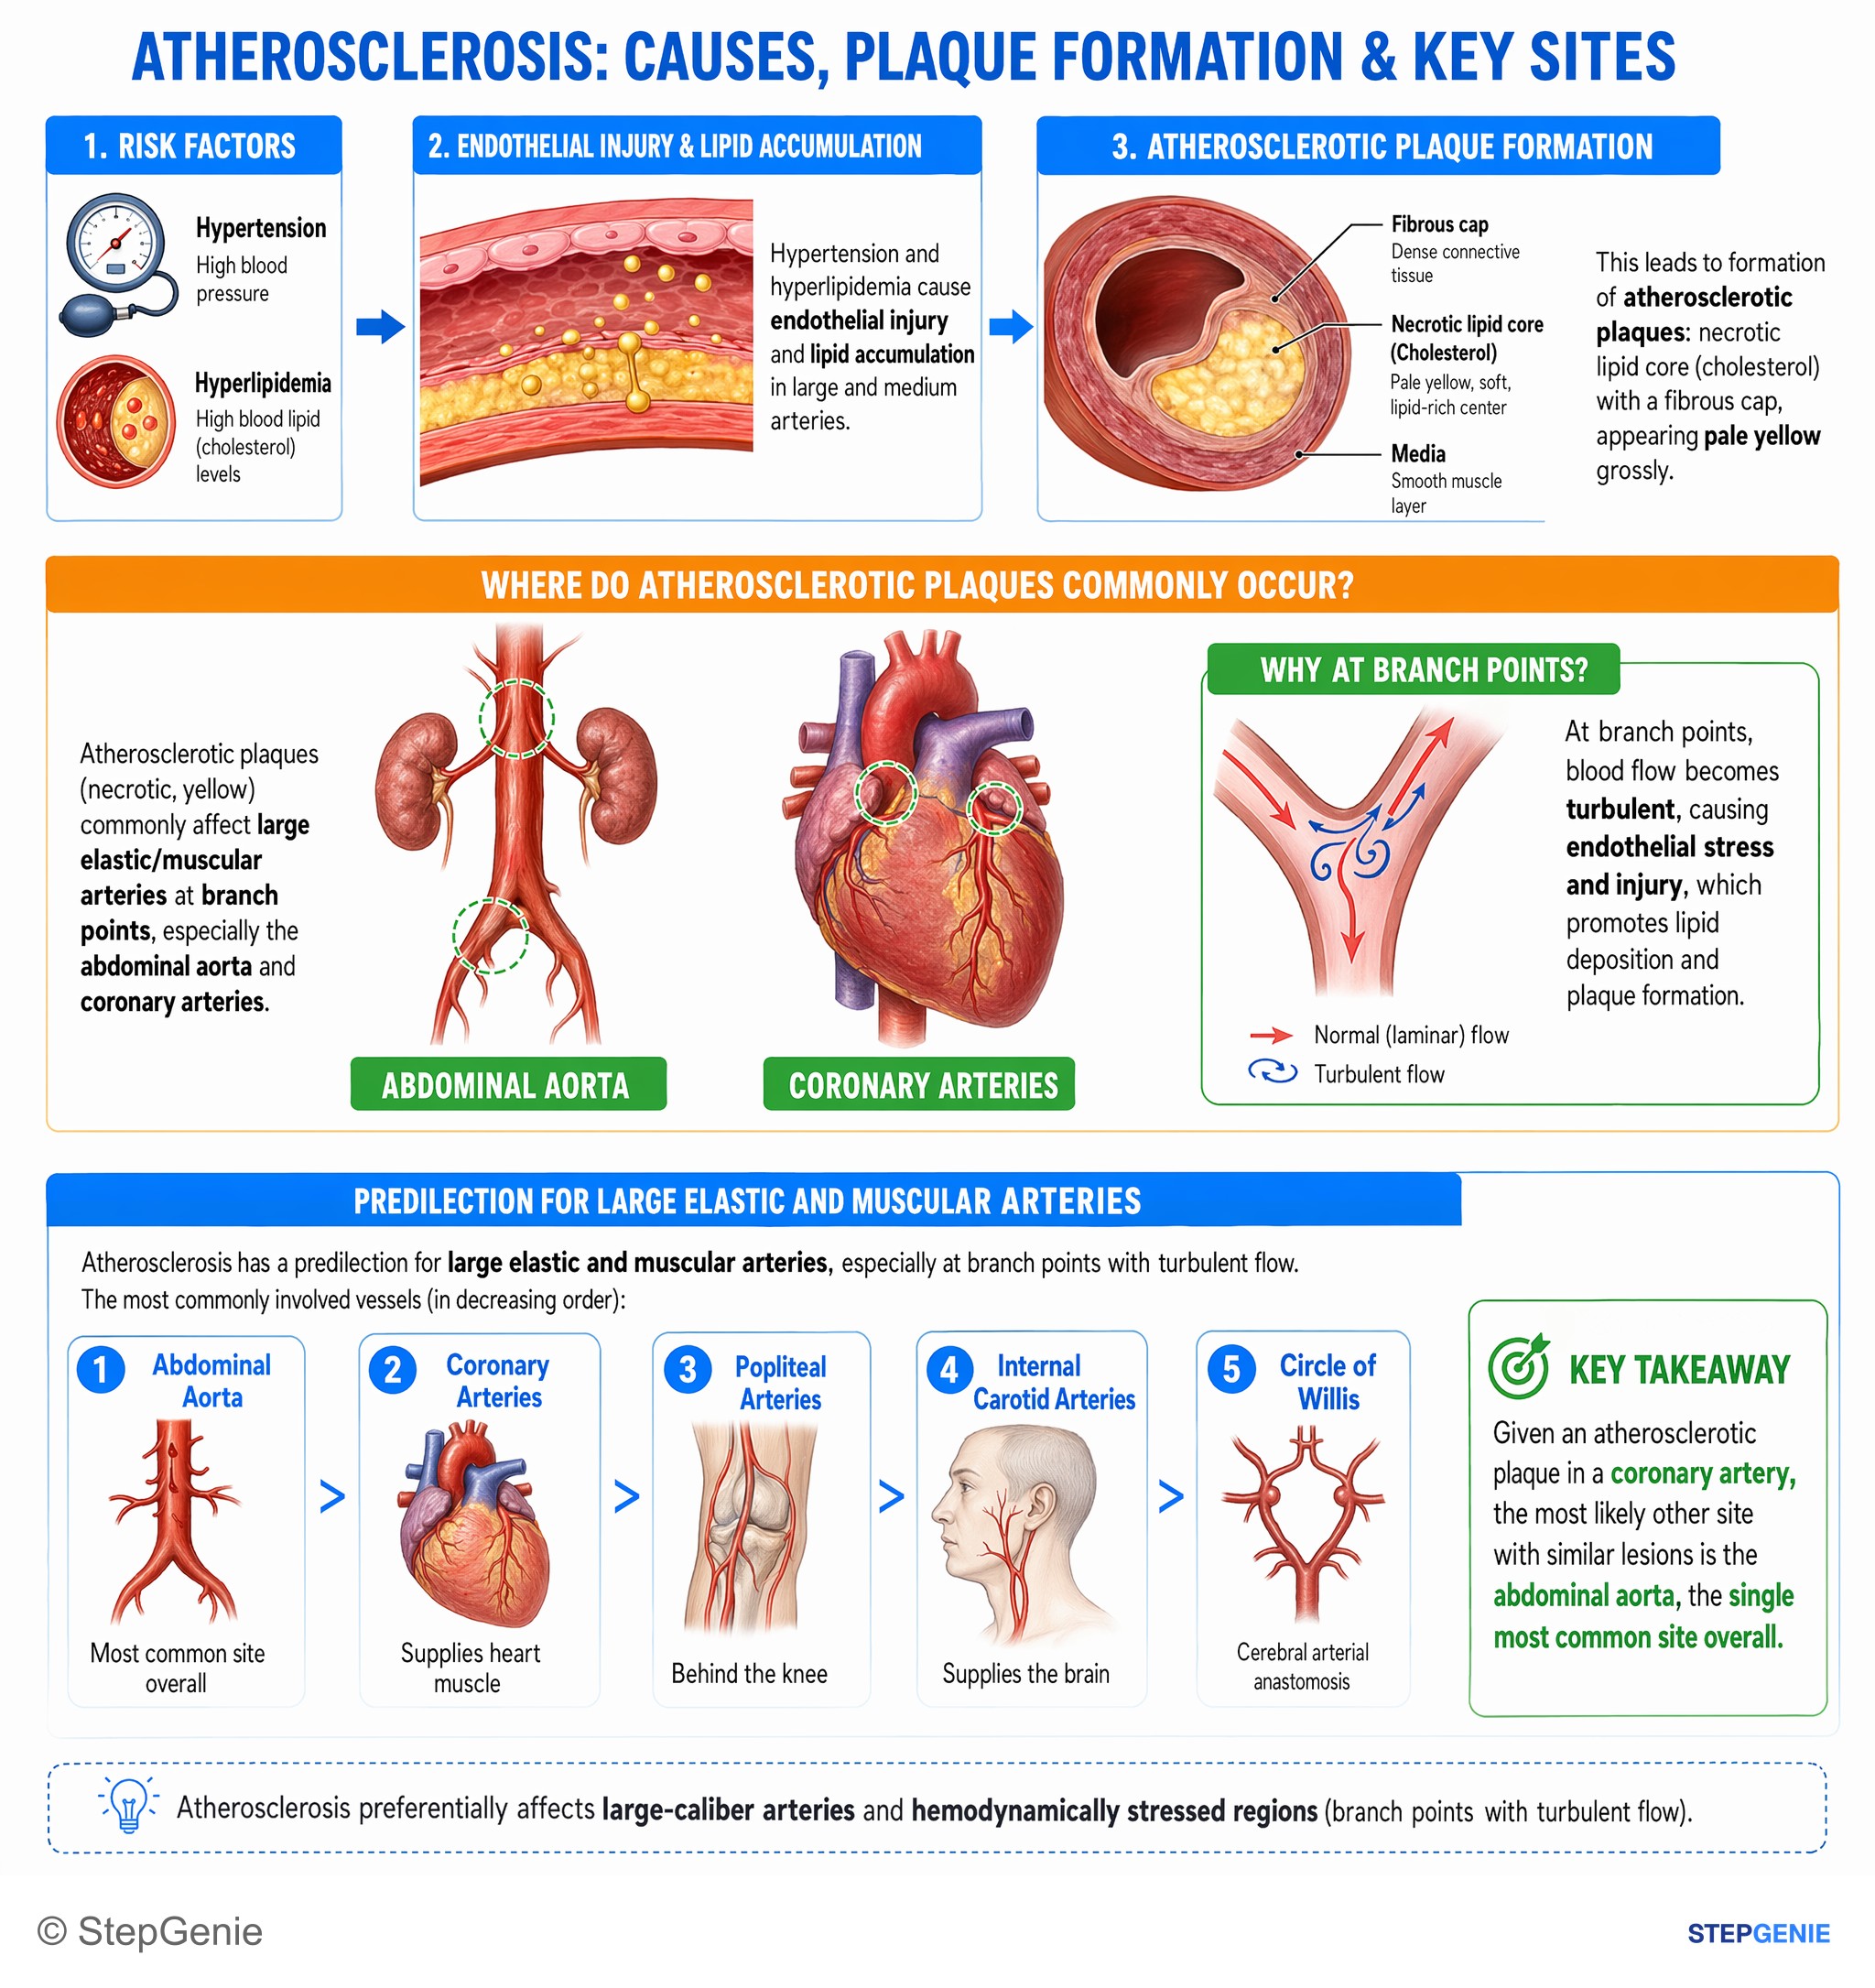
Atherosclerotic plaques (necrotic, yellow) commonly affect large elastic/muscular arteries at branch points, especially abdominal aorta…
USMLE Step 1Frequently Asked Questions
What is the earliest lesion in atherosclerosis?
The earliest lesion is the fatty streak made of foam cells. It begins after endothelial dysfunction allows LDL to enter the intima and become oxidized. Monocytes then cross the endothelium, turn into macrophages, and ingest oxidized LDL through scavenger receptors. Those lipid-laden macrophages become foam cells, creating the fatty streak that can appear even in young people.
Why does oxidized LDL matter in atherosclerosis?
Oxidized LDL matters because it is pro-inflammatory and attracts immune cells into the vessel wall. After LDL slips into the intima beneath injured endothelium, it becomes oxidized and acts like inflammatory bait. Macrophages then ingest this oxidized LDL through scavenger receptors, continue accumulating lipid, and form foam cells, driving fatty streak formation and plaque progression.
How do you tell a stable plaque from a vulnerable plaque?
A stable plaque has a thick fibrous cap, a smaller lipid core, and less inflammation, while a vulnerable plaque has a thin cap, a large lipid core, and more macrophages. Stable plaques are more associated with chronic ischemia such as stable angina. Vulnerable plaques are dangerous because macrophage MMPs degrade collagen, weaken the cap, and increase the risk of rupture with thrombosis.
What actually triggers an acute MI or acute coronary syndrome in atherosclerosis?
Acute coronary syndrome is usually triggered by plaque rupture or erosion followed by thrombosis, not by slow narrowing alone. When the fibrous cap cracks, thrombogenic material such as collagen and tissue factor becomes exposed. Platelets then adhere, activate, and aggregate to form a thrombus. Complete occlusion typically causes STEMI, while partial or transient occlusion is more associated with NSTEMI or unstable angina.
Why do hypertension, smoking, diabetes, and high LDL increase atherosclerosis risk?
These risk factors increase atherosclerosis because they promote endothelial dysfunction and make lipid-driven inflammation more likely. Hypertension causes shear stress injury, smoking causes oxidative stress and endothelial dysfunction, diabetes causes glycation, oxidative stress, and a pro-inflammatory state, and high LDL increases cholesterol delivery into the vessel wall. Together, these changes favor LDL entry into the intima and plaque formation.