Normal adult ECG intervals: a PR interval of 120-200 ms (3-5 small boxes at 25 mm/s), a QRS duration under 120 ms (usually about 70-100 ms), and a heart-rate-corrected QT (QTc) up to about 440-450 ms in men and 460 ms in women. A PR over 200 ms is first-degree AV block, a short PR with a delta wave is pre-excitation (Wolff-Parkinson-White), a QRS of 120 ms or more means bundle branch block or another wide-complex cause, and a QTc above 500 ms carries a markedly higher risk of torsades de pointes. On exam questions, a value just outside these ranges is almost always a deliberate clue.
The Q-bank question
A 24-year-old man has a preparticipation ECG before joining a college soccer team. He feels well, takes no medications and has no family history of sudden cardiac death. The ECG, recorded at the standard paper speed of 25 mm/s, shows sinus rhythm at 72/min with a normal axis. Which of the following measurements is within the normal adult range?
A. PR interval of 6 small boxes (0.24 s) B. PR interval of 2 small boxes (0.08 s) with a slurred QRS upstroke C. QRS duration of 3.5 small boxes (0.14 s) D. QTc of 0.52 s E. PR interval of 4 small boxes (0.16 s)
Answer and why every choice matters
Answer: E. At 25 mm/s each small box is 0.04 s (40 ms), so 4 small boxes = 0.16 s, squarely inside the normal PR range of 0.12-0.20 s. The PR interval runs from the start of atrial depolarization to the start of ventricular depolarization, and it includes the deliberate delay at the AV node.
A. PR 0.24 s: first-degree AV block. Every P wave is conducted, but the PR is longer than 0.20 s. First-degree block can be physiologic in young people with high vagal tone and in well-trained athletes, so this soccer player may be perfectly healthy, yet the value is still outside the normal range. Other causes: beta-blockers, calcium channel blockers, digoxin and amiodarone, idiopathic fibrosis of the conduction system, and ischemic heart disease. It is rarely symptomatic and usually needs no treatment. Mobitz I, Mobitz II and complete block are in the AV block cheat sheet.
B. PR 0.08 s with a slurred upstroke: pre-excitation. A short PR plus a delta wave (the slurred start of the QRS) means an accessory pathway activates part of the ventricle early, bypassing the AV node: the Wolff-Parkinson-White pattern. The trap that follows: in atrial fibrillation with a wide QRS from pre-excitation, AV nodal blockers can push conduction down the bypass tract and cause ventricular fibrillation.
C. QRS 0.14 s: wide QRS. A QRS of 0.12 s or more is wide: in a beat conducted from above it means complete bundle branch block or an intraventricular conduction delay, and otherwise the beat started outside the normal conduction system. Think bundle branch block (see LBBB vs RBBB criteria), a ventricular rhythm or PVC, a paced beat, pre-excitation, hyperkalemia, or sodium-channel blockade such as a tricyclic overdose.
D. QTc 0.52 s: markedly prolonged. The risk of torsades rises with the degree of QTc prolongation, particularly above 0.50 s. Causes are QT-prolonging drugs, hypokalemia, hypomagnesemia, hypocalcemia and congenital long QT syndrome. In a young athlete this value calls for a careful drug and family history and further evaluation.
Normal ECG intervals at a glance
| Measurement | Normal adult value | Small boxes at 25 mm/s | What it represents | Abnormal: think of |
|---|---|---|---|---|
| P wave | Up to about 0.12 s wide and 2.5 mm tall; upright in most leads except aVR | Up to 3 wide | Atrial depolarization | Atrial enlargement: tall, peaked P in II, III, aVF (Merck: over 2 mm) = right; broad, double-peaked P in II = left |
| PR interval | 0.12-0.20 s (120-200 ms) | 3-5 | Atrial depolarization plus AV nodal delay and His-Purkinje conduction | Long: first-degree AV block. Short: pre-excitation |
| QRS duration | Under 0.12 s; usually 0.07-0.10 s | Under 3 | Ventricular depolarization | Wide: BBB, ventricular or paced rhythm, hyperkalemia, Na-channel blockers |
| ST segment | Isoelectric, level with the PR segment; about 0.08-0.12 s | 2-3 | Ventricles fully depolarized | Elevation or depression: ischemia, pericarditis and others |
| T wave | Upright in most leads, usually under 10 mm | — | Ventricular repolarization | Peaked: hyperkalemia. Flat, with U waves: hypokalemia |
| QTc | Up to about 440-450 ms (men) and 460 ms (women) | — | Ventricular depolarization plus repolarization | Long: torsades risk. Short: hypercalcemia, digoxin, short QT syndrome |
| U wave | Small wave after the T; often present in healthy people | — | Delayed repolarization (Purkinje fibers or papillary muscles) | Prominent: hypokalemia, hypomagnesemia, ischemia |
| QRS axis | −30° to +90° | — | Mean direction of ventricular depolarization | Left or right axis deviation |
Reading the grid: boxes, milliseconds and heart rate
- Paper speed 25 mm/s: 1 small box = 0.04 s (40 ms); 1 large box = 5 small boxes = 0.20 s (200 ms); 5 large boxes = 1 second.
- Quick checks: a PR wider than one large box is long; a QRS of 3 small boxes or more is wide.
- Rate in a regular rhythm: 300 ÷ the number of large boxes between R waves, or 1,500 ÷ the number of small boxes. Four large boxes = 75/min.
- Rate in an irregular rhythm: count the QRS complexes in a 10-second strip and multiply by 6.
- The full reading order (rate, rhythm, axis, intervals, then ST-T changes) is in how to read an ECG.
PR interval: long vs short
| Long PR (over 200 ms) | Short PR (under 120 ms) | |
|---|---|---|
| Meaning | Slowed AV conduction; every P wave still conducts | Ventricles activated early through an accessory pathway, or accelerated AV conduction |
| Classic causes | High vagal tone and athletes; beta-blockers, calcium channel blockers, digoxin, amiodarone; conduction-system fibrosis; ischemic heart disease; early hyperkalemia | WPW (delta wave, often a wider QRS); a short PR without a delta wave can also reflect accelerated AV conduction |
| Exam move | Usually benign; watch for progression to second-degree patterns | In pre-excited atrial fibrillation, avoid AV nodal blockers |
Sources differ on the lower limit. Merck's ECG chapter (2026) lists a normal PR of 0.10-0.20 s, while StatPearls and most exam resources use 0.12-0.20 s. For USMLE, use 120-200 ms and treat a PR under 120 ms as a prompt to look for a delta wave. Inferior MI matters for the long PR too: AV block in an acute inferior MI usually reflects AV nodal dysfunction from increased vagal tone and/or local adenosine release, and in most cases it resolves on its own over several days (Merck).
QRS duration: narrow vs wide
- Normal: 0.07-0.10 s (Merck); StatPearls phrases it as under 120 ms, usually 60-100 ms.
- 0.10-0.11 s: incomplete bundle branch block or a nonspecific intraventricular conduction delay, depending on QRS shape.
- 0.12 s or more: complete bundle branch block or intraventricular conduction delay, or a beat that did not start in the normal conduction system (PVC, ventricular rhythm, paced beat, pre-excitation).
- Hyperkalemia sequence (Merck): above about 5.5 mEq/L, tall peaked T waves with a longer PR and a shorter QT; above about 6.5 mEq/L, QRS widening and loss of P waves; then a sine-wave pattern and ventricular fibrillation or asystole. IV calcium stabilizes the myocardium first. More in hypokalemia and hyperkalemia.
- Tricyclic overdose (StatPearls): fast sodium-channel blockade slows phase 0. A QRS over 100 ms predicts seizures and over 160 ms predicts ventricular arrhythmias; an R wave over 3 mm in aVR is another warning sign. Give sodium bicarbonate for a QRS over 100 ms, seizures or hemodynamic instability.
QT and QTc: correction, cut-offs and causes
The QT runs from the start of the QRS to the end of the T wave. It shortens as the heart rate rises, so it is corrected for rate:
- Bazett: QTc = QT ÷ √RR (both in seconds). It is built into most ECG machines, underestimates QTc in bradycardia and overestimates it in tachycardia, and is most accurate at about 60-100/min. Example: at 100/min (RR 0.6 s), a QT of 0.36 s gives a Bazett QTc of about 0.465 s.
- Fridericia: QTc = QT ÷ ∛RR (cube root). The Framingham formula is another alternative to Bazett.
- Cut-offs vary slightly by source. Merck's ECG chapter gives a normal adult QTc of 350-450 ms in men and 360-460 ms in women; StatPearls uses 440 ms or less (men) and 460 ms or less (women). Women normally run longer.
- Over 500 ms is the number that matters at the bedside: torsades risk rises with the degree of prolongation, particularly above 500 ms (StatPearls, Merck).
| Long QT (torsades risk) | Short QT |
|---|---|
| Drugs that block hERG (IKr) potassium channels and delay phase 3 repolarization: class IA, IC and III antiarrhythmics (quinidine, procainamide, flecainide, sotalol, dofetilide, amiodarone), macrolides, fluoroquinolones, antipsychotics (haloperidol, ziprasidone), some antidepressants (citalopram, tricyclics), methadone, ondansetron | Hypercalcemia |
| Electrolytes: hypokalemia, hypomagnesemia, hypocalcemia (low calcium lengthens the ST segment) | Congenital short QT syndrome |
| Congenital: Romano-Ward syndrome (autosomal dominant; KCNQ1, KCNH2, SCN5A) and Jervell and Lange-Nielsen syndrome (autosomal recessive, with profound congenital hearing loss) | Acidosis, hyperthermia, hyperkalemia (StatPearls) |
| Other: hypothyroidism, bradycardia, structural heart disease, acute brain injury (subarachnoid or intracerebral hemorrhage) | Digoxin, hypermagnesemia, Graves disease (Merck) |
Watch the hypokalemia trap: the T wave flattens and a large U wave appears, and a T wave merging into a U wave can be mistaken for QT prolongation. Torsades treatment (Merck): an episode long enough to cause hemodynamic compromise gets unsynchronized cardioversion (defibrillation); otherwise IV magnesium sulfate 2 g over 1-2 minutes; temporary pacing and/or IV isoproterenol (a faster rate shortens the QT); correct hypokalemia and stop the QT-prolonging drug.
How USMLE tests normal intervals
- "Which value is normal?" Each wrong option stands for one pattern: long PR, short PR plus delta wave, wide QRS, long QTc.
- Boxes instead of milliseconds: convert at 40 ms per small box first.
- Electrolyte pairs: potassium changes the T wave (peaked when high, flat with U waves when low); calcium changes the QT (short when high, long when low).
- Drug stems: a new macrolide, fluoroquinolone, antiemetic or antipsychotic plus palpitations or syncope means QTc and torsades. Overdose plus a wide QRS and hypotension means sodium-channel blockade, treated with sodium bicarbonate.
- Bazett at extremes: fast rates inflate the QTc and slow rates hide prolongation.
Key takeaways
- PR 120-200 ms (3-5 small boxes); QRS under 120 ms; QTc up to about 440-450 ms in men and 460 ms in women.
- At 25 mm/s, 1 small box = 40 ms and 1 large box = 200 ms.
- PR over 200 ms = first-degree AV block; short PR plus delta wave = WPW, and no AV nodal blockers in pre-excited atrial fibrillation.
- QRS 120 ms or more = complete BBB, ventricular or paced rhythm, pre-excitation, hyperkalemia or sodium-channel blockade.
- QTc over 500 ms = clearly higher torsades risk: review drugs, check potassium, magnesium and calcium; treat torsades with IV magnesium (unsynchronized cardioversion if unstable).
- Hypercalcemia and digoxin shorten the QT; hypocalcemia lengthens it.
- Bazett's formula overcorrects at fast heart rates and undercorrects at slow ones.
Sources
- Electrocardiography — Merck Manual Professional Edition (2026)
- Electrocardiogram — StatPearls, NCBI Bookshelf (2023)
- QT Prolonging Drugs — StatPearls, NCBI Bookshelf (2023)
- Torsades de Pointes Ventricular Tachycardia — Merck Manual Professional Edition (2024)
- Atrioventricular Block — Merck Manual Professional Edition (2024)
- Atrial Fibrillation — Merck Manual Professional Edition (2024)
- Tricyclic Antidepressant Toxicity — StatPearls, NCBI Bookshelf (2023)
- Hyperkalemia — Merck Manual Professional Edition (2025)
- Hypokalemia — Merck Manual Professional Edition (2025)
- Hypocalcemia — Merck Manual Professional Edition (2025)
- Romano-Ward Syndrome — MedlinePlus Genetics (2017)
- Jervell and Lange-Nielsen Syndrome — MedlinePlus Genetics (2017)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
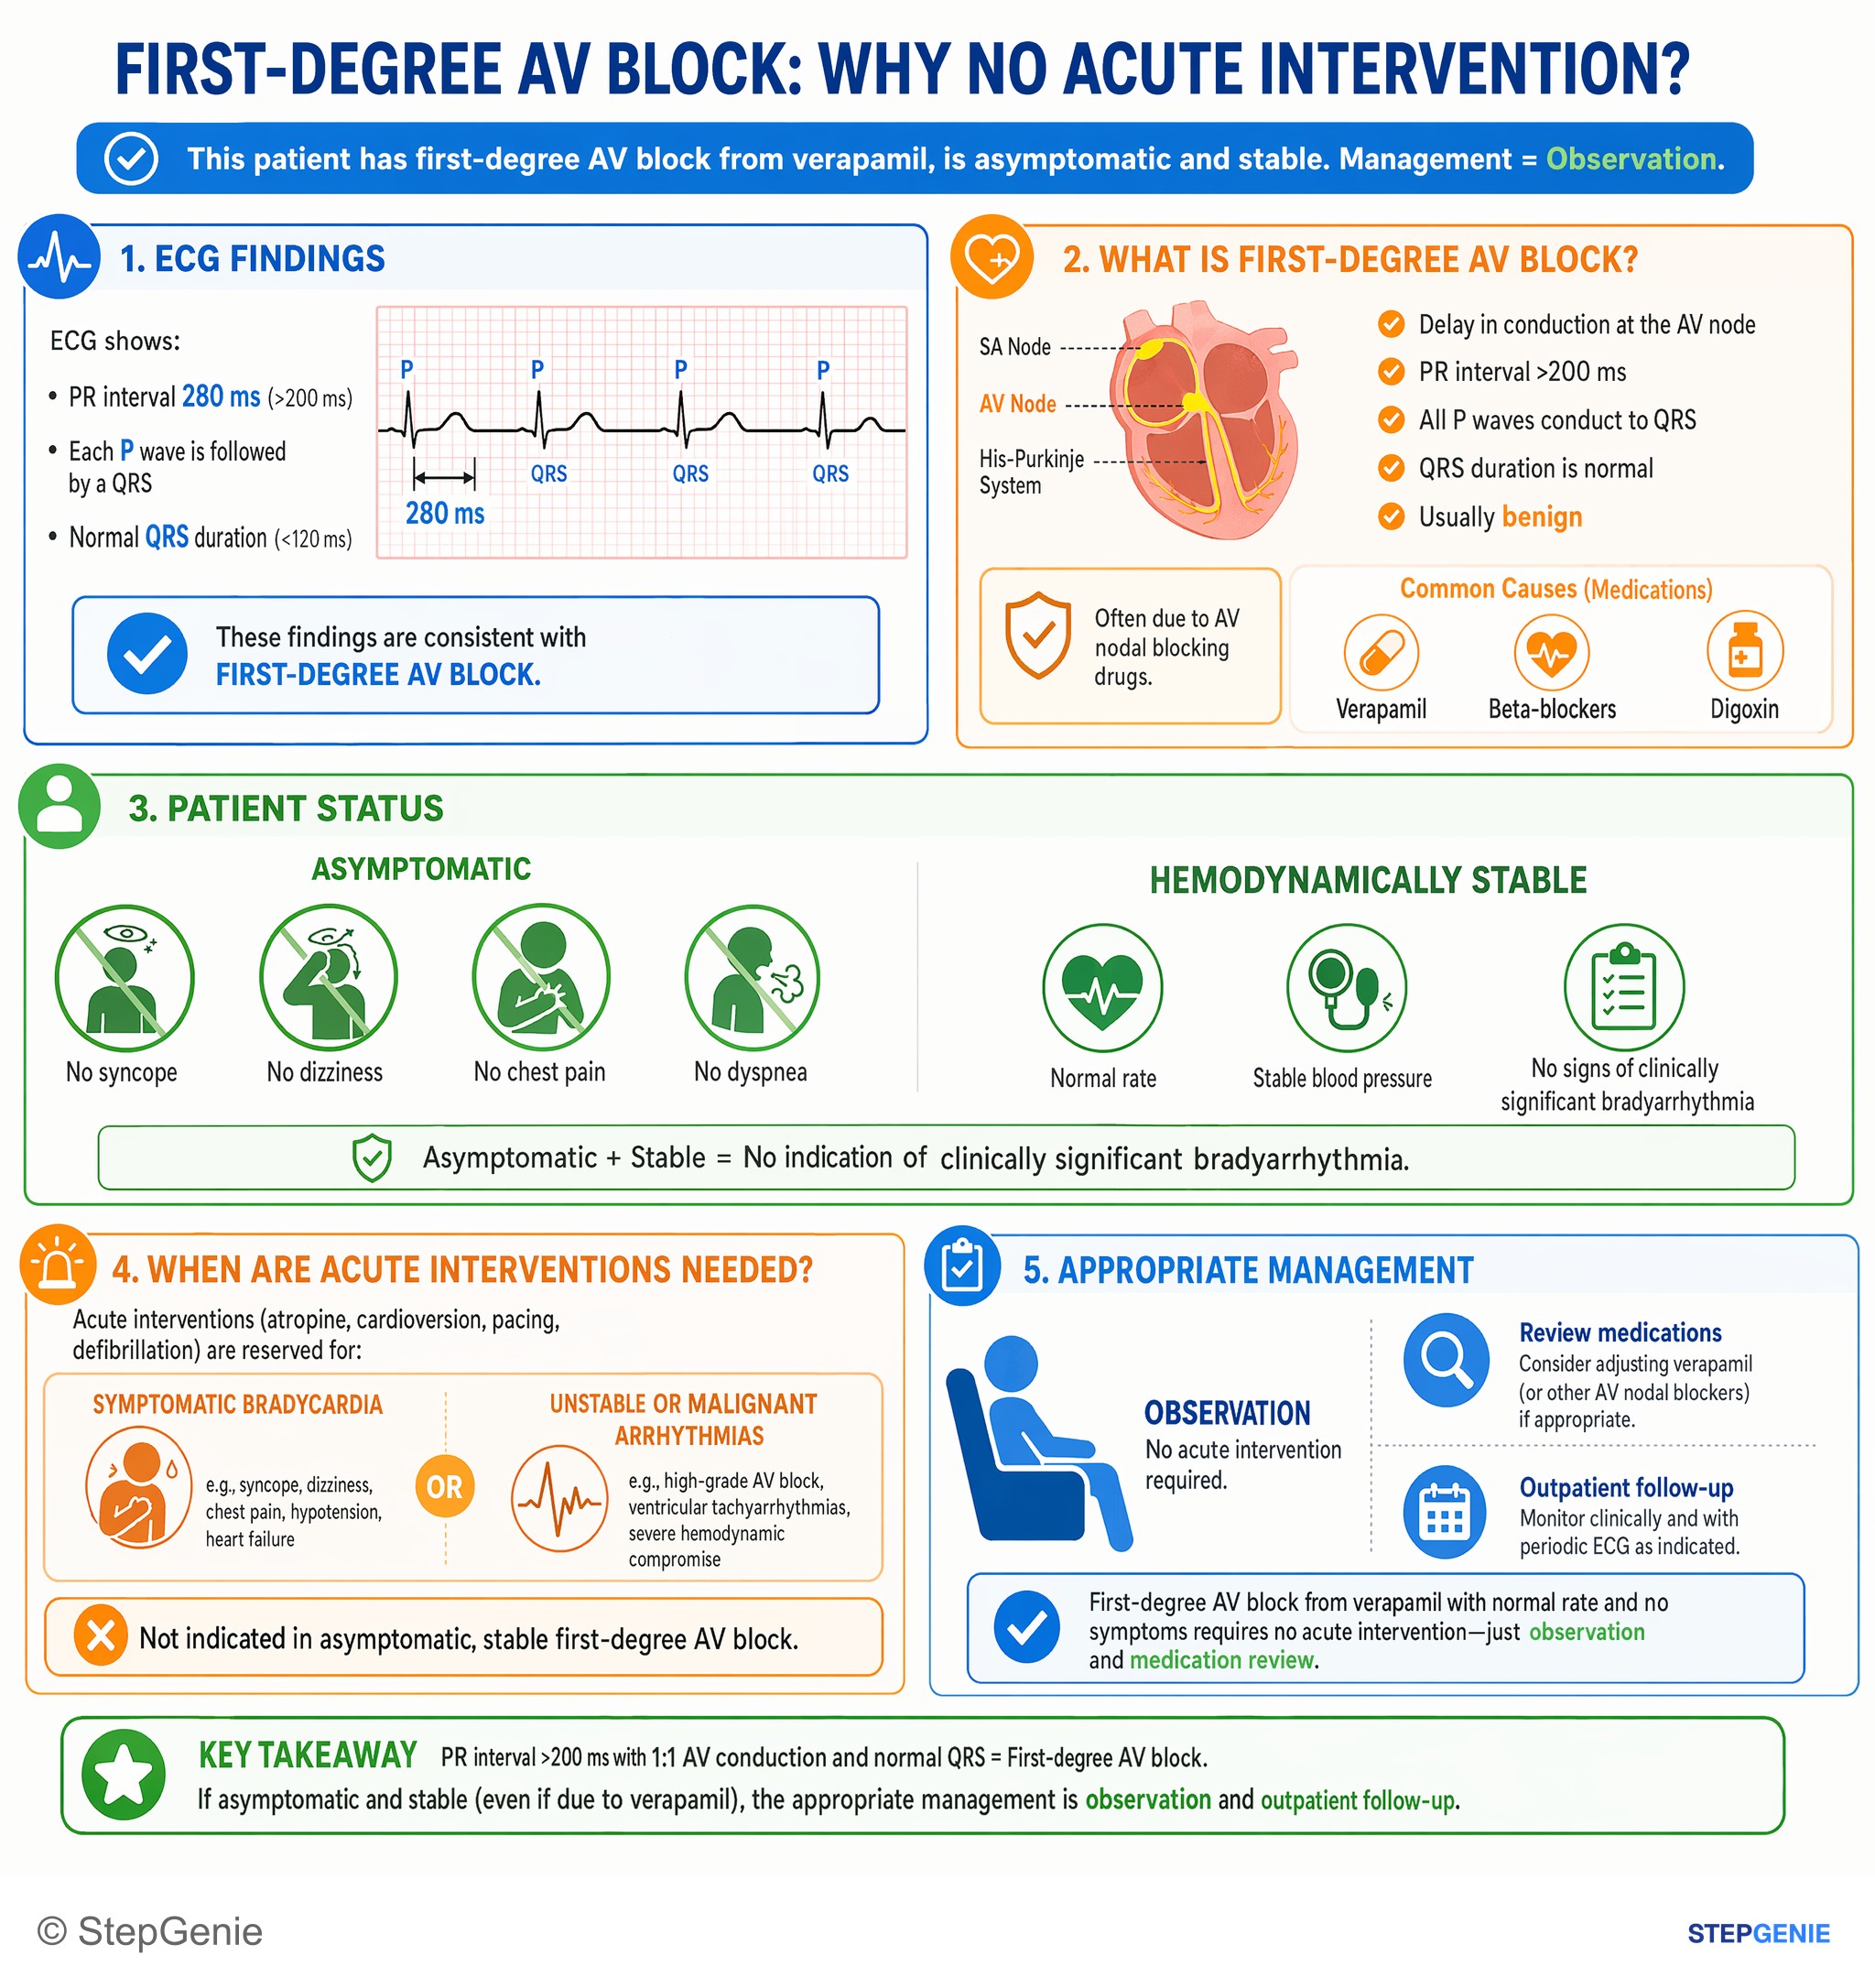
First-degree AV block from verapamil with normal rate and no symptoms requires no acute intervention—just observation and medication review.
USMLE Step 2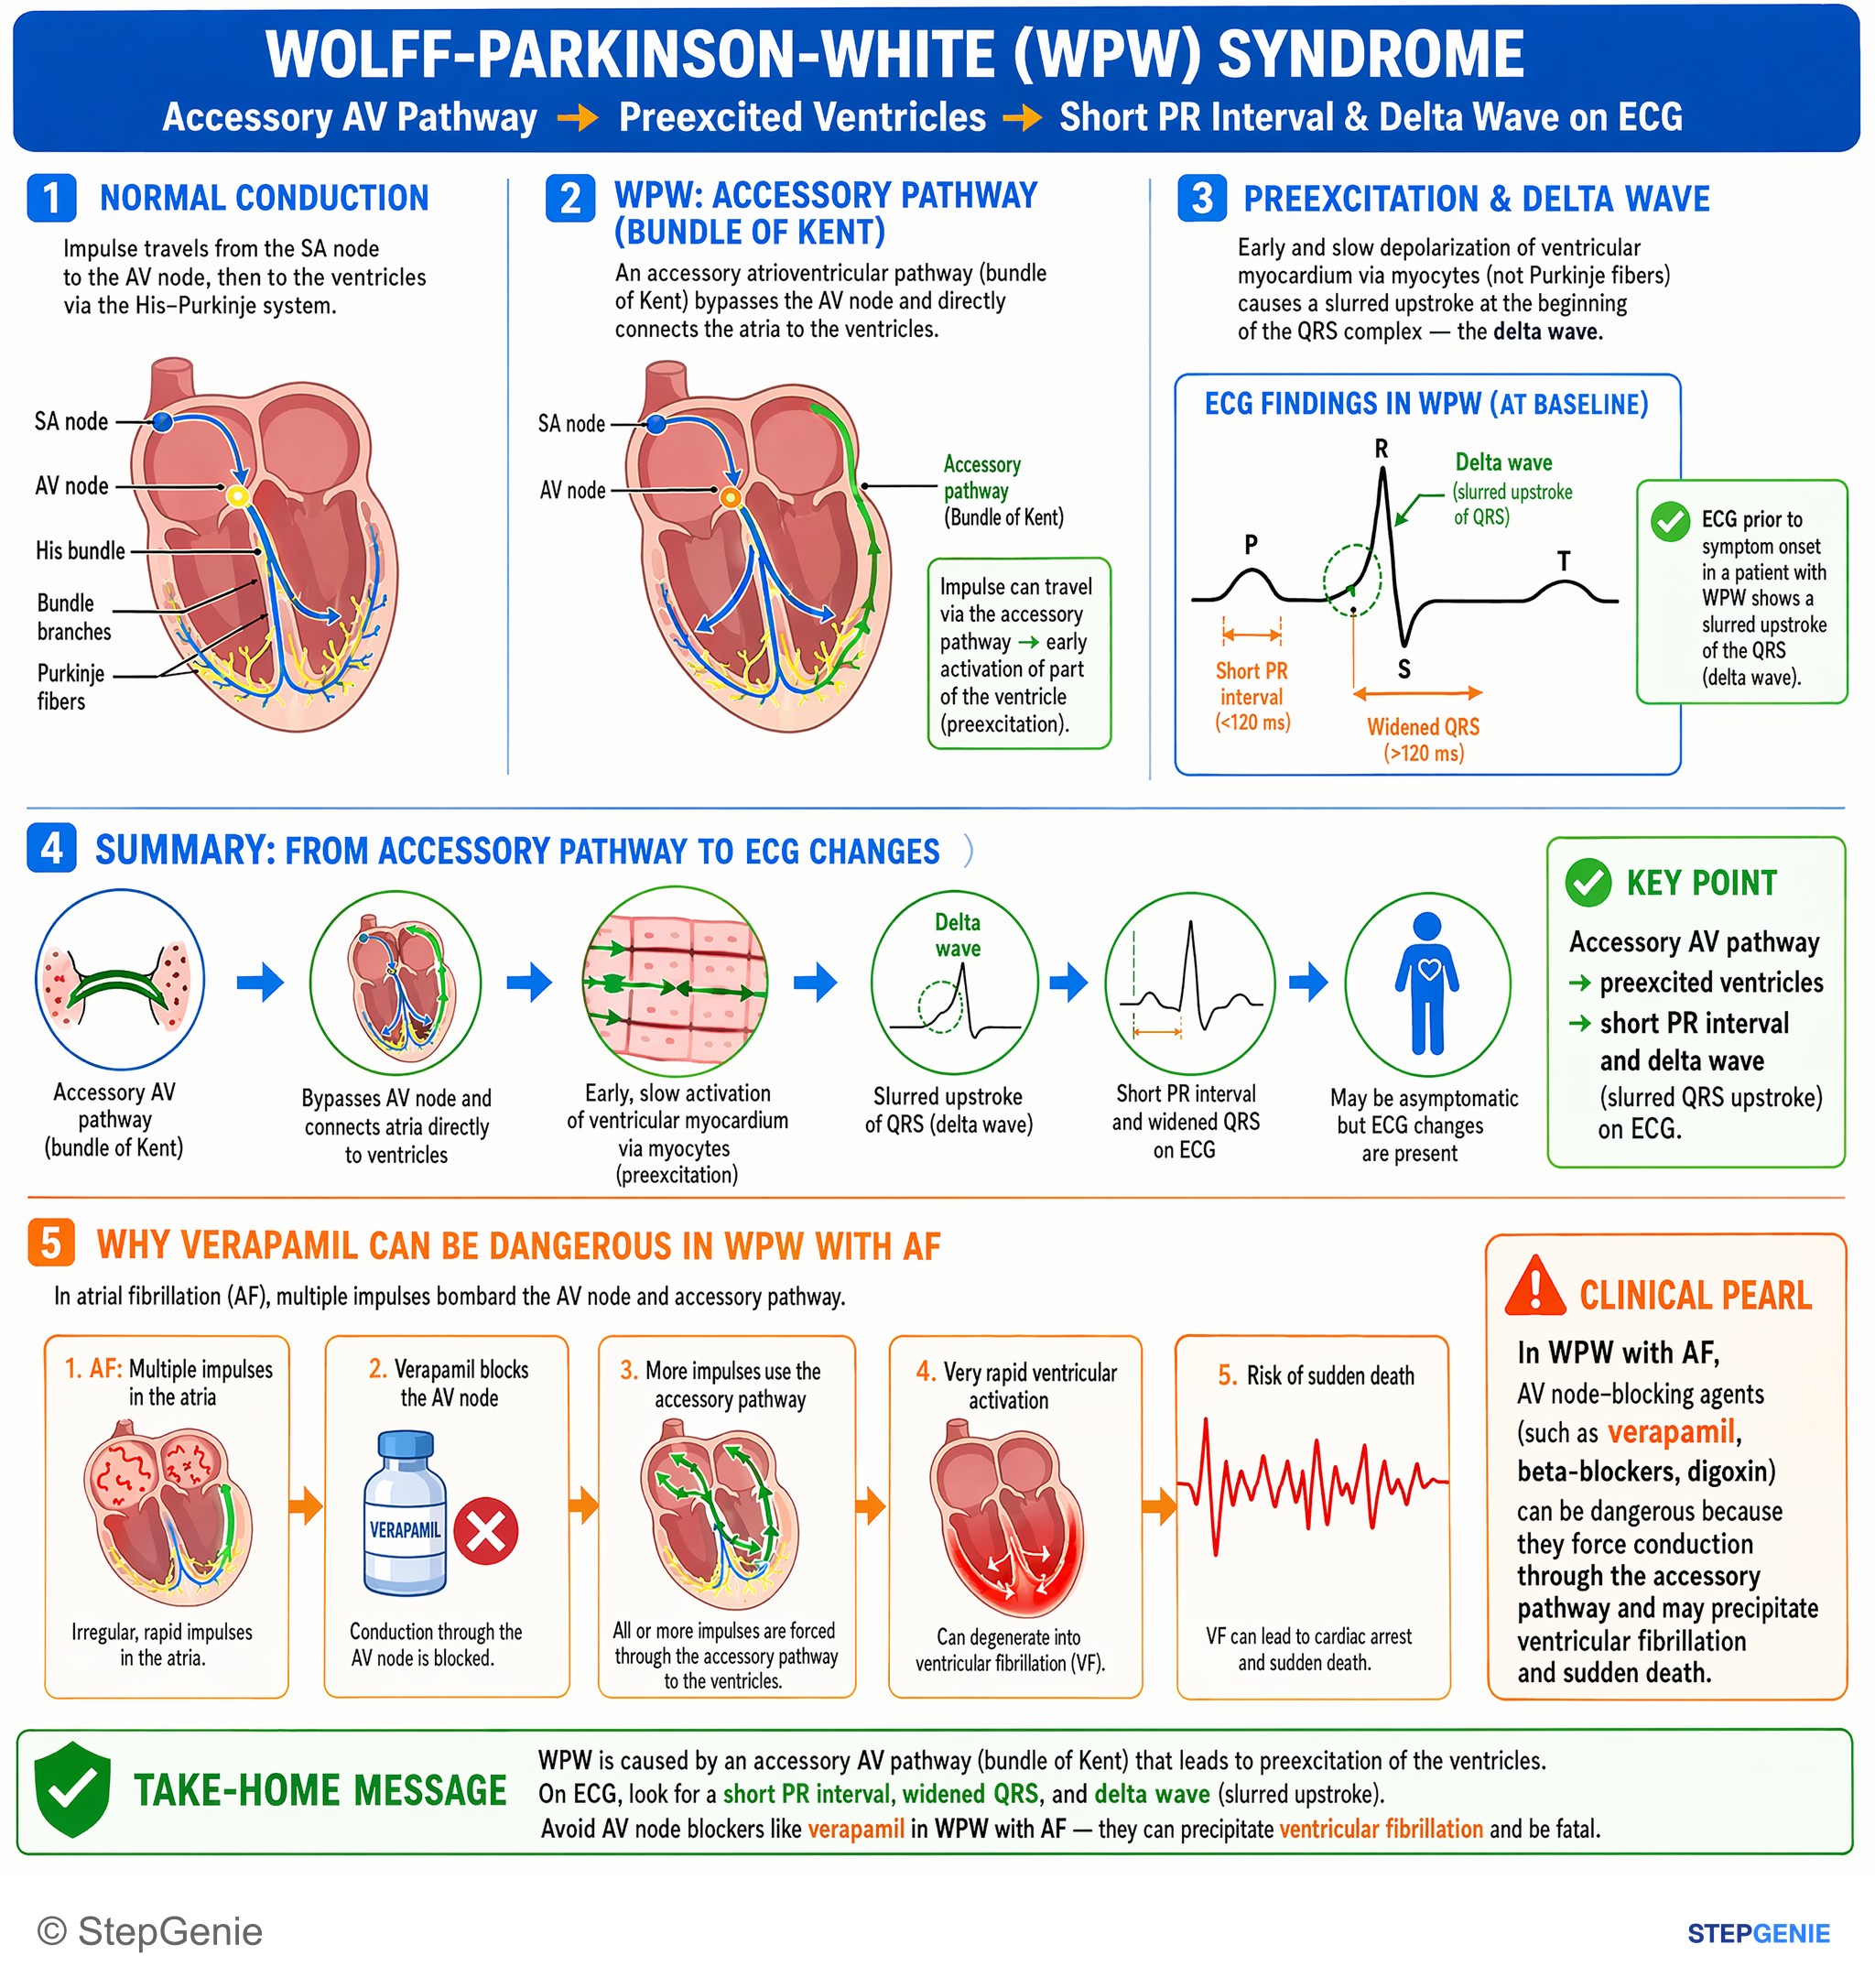
Wolff-Parkinson-White (WPW): accessory AV pathway → preexcited ventricles → short PR interval and delta wave (slurred QRS upstroke) on ECG.
USMLE Step 1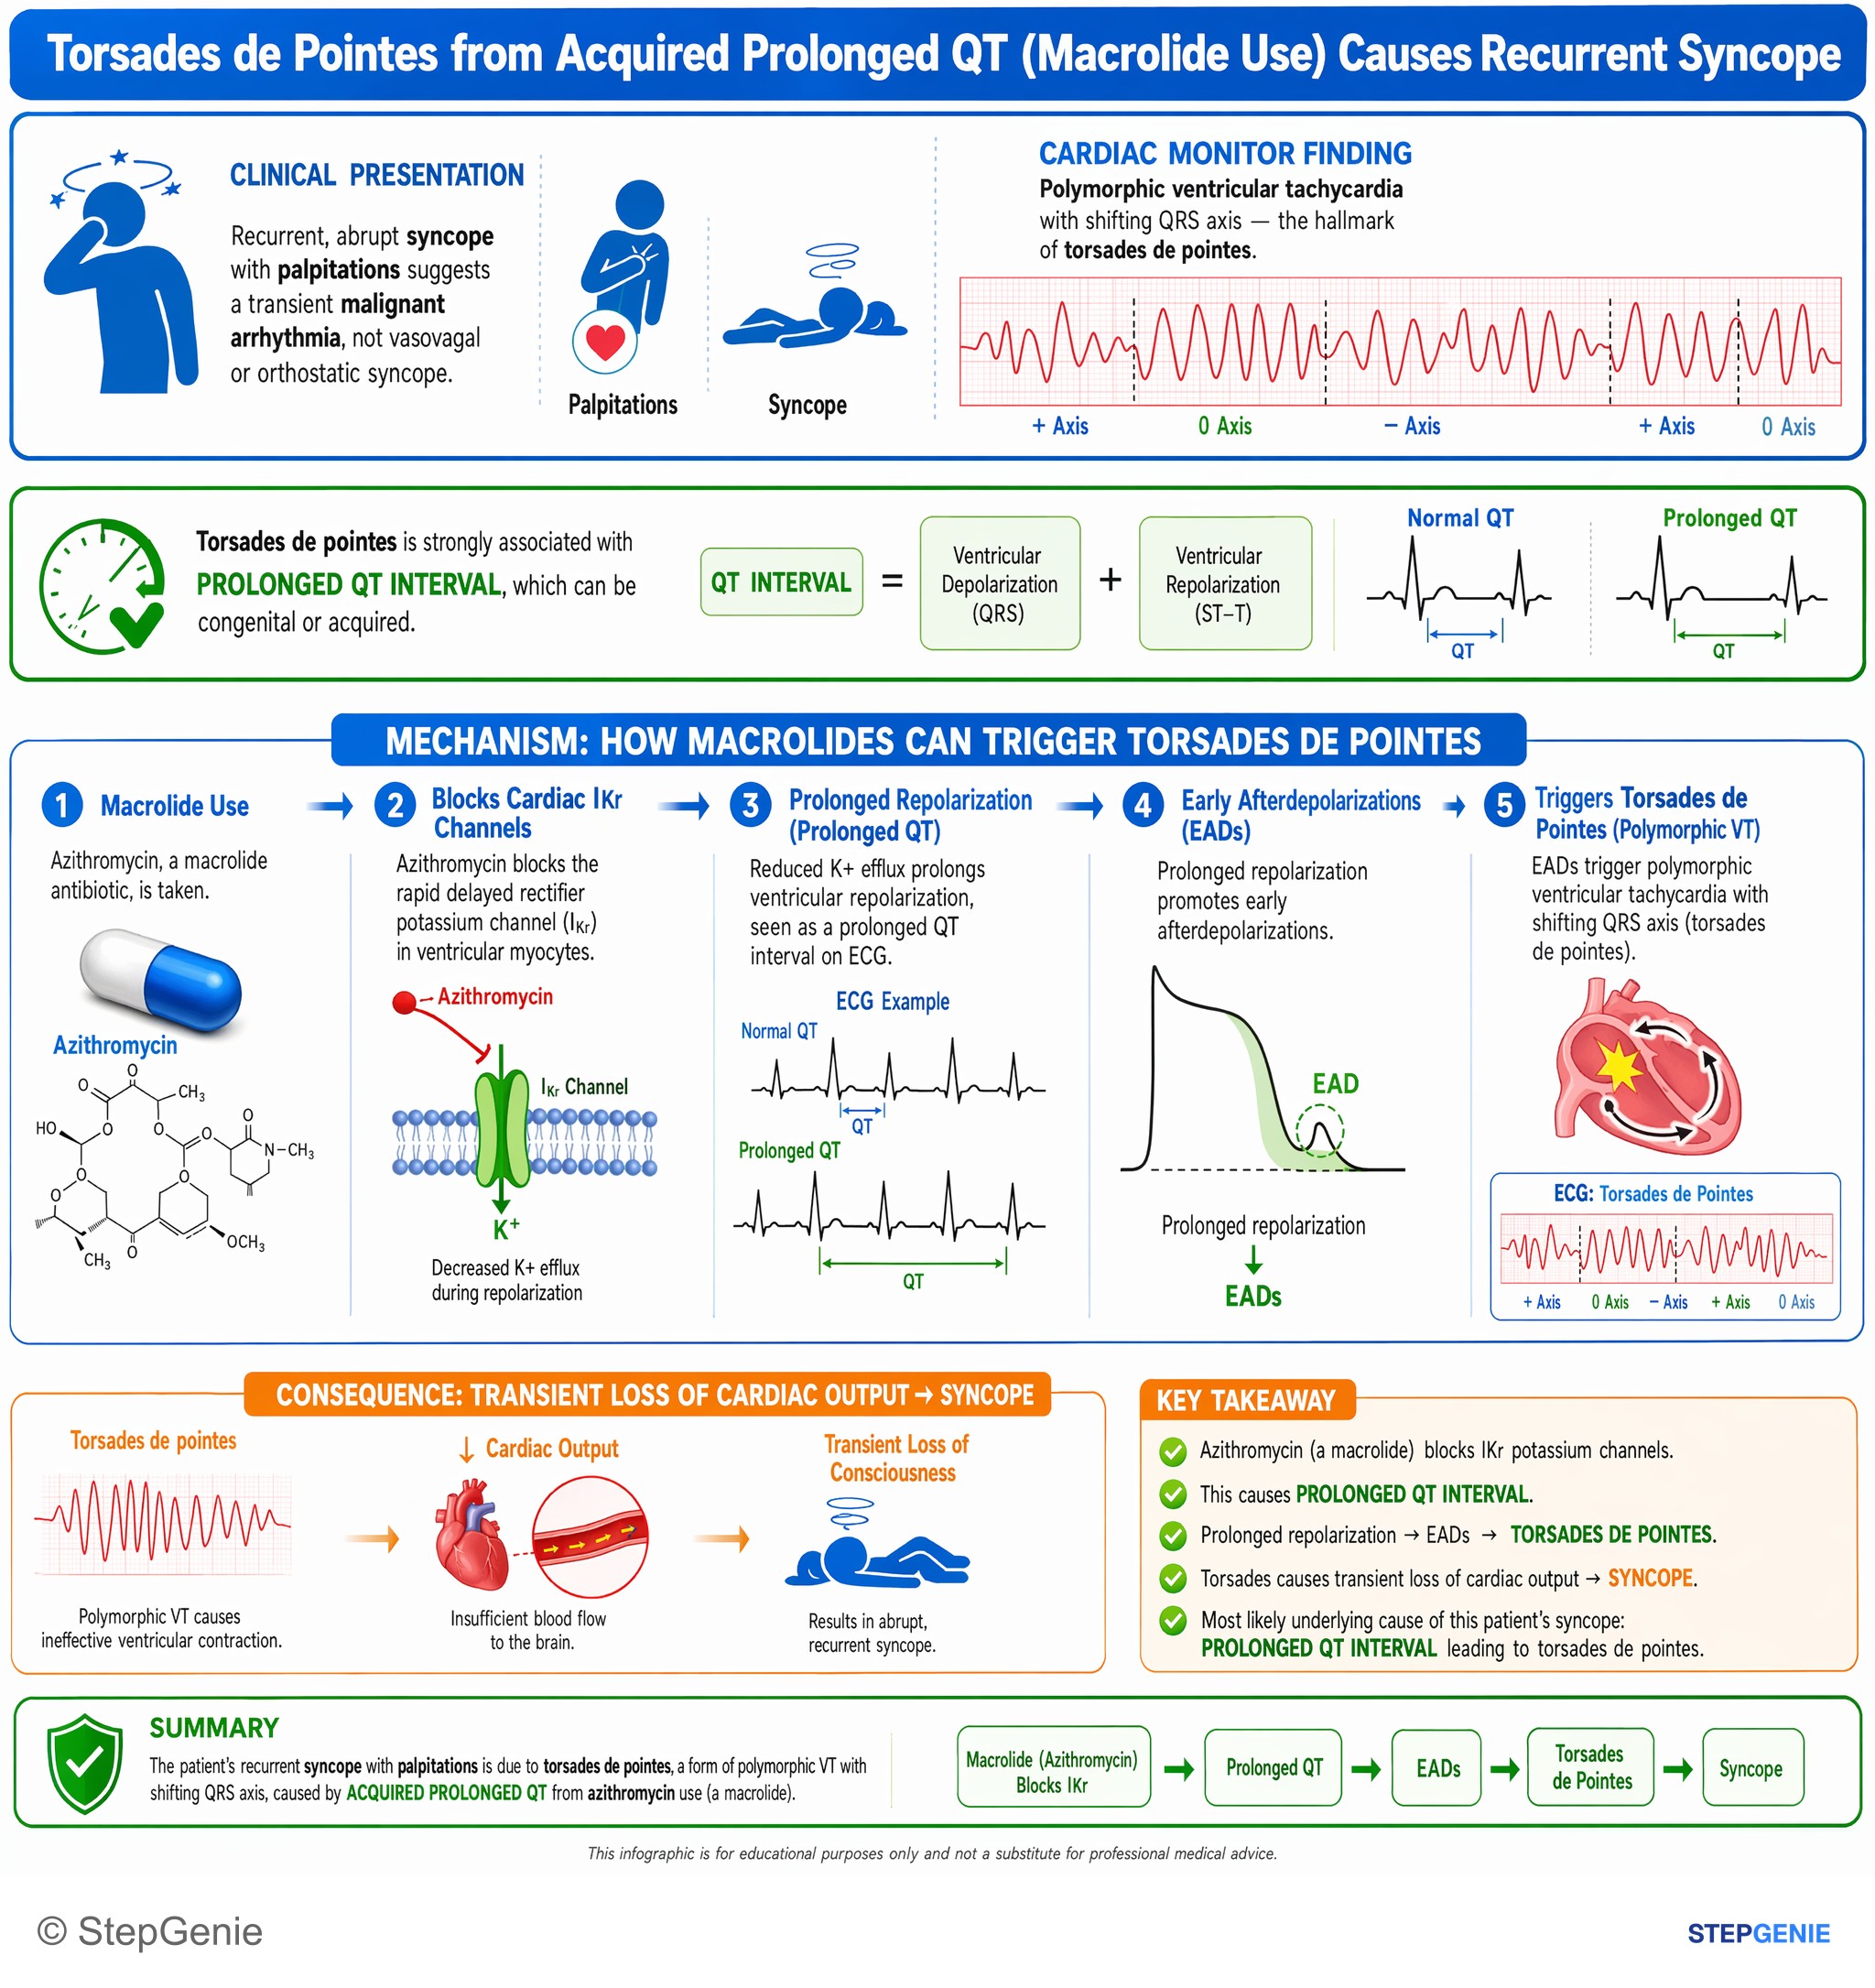
Torsades de pointes from acquired prolonged QT (macrolide use) causes recurrent syncope and polymorphic VT with shifting QRS axis.
USMLE Step 2Frequently Asked Questions
What are the normal ECG intervals in adults?
In adults, the PR interval is normally 120 to 200 milliseconds (3 to 5 small boxes at 25 mm/s), the QRS duration is under 120 milliseconds (usually about 70 to 100), and the heart-rate-corrected QT (QTc) is up to about 440 to 450 milliseconds in men and 460 in women. A PR over 200 ms is first-degree AV block, a QRS of 120 ms or more is wide, and a QTc above 500 ms markedly raises the risk of torsades de pointes.
What is a normal PR interval and what does it represent?
A normal PR interval is 0.12 to 0.20 seconds (120 to 200 ms), measured from the start of the P wave to the start of the QRS complex. It covers atrial depolarization, the built-in delay at the AV node and conduction through the His-Purkinje system. A PR over 0.20 seconds is first-degree AV block, and a short PR with a delta wave suggests Wolff-Parkinson-White pre-excitation. Merck lists the lower limit as 0.10 seconds, but exam resources use 0.12 seconds.
What QRS duration is considered wide?
A QRS of 0.12 seconds (120 ms, three small boxes) or longer is wide. Merck gives a normal QRS of 0.07 to 0.10 seconds and calls 0.10 to 0.11 seconds an incomplete bundle branch block or a nonspecific intraventricular conduction delay. Causes of a wide QRS include complete bundle branch block, ventricular rhythms and PVCs, paced beats, pre-excitation, hyperkalemia and sodium-channel blockers such as tricyclic antidepressants in overdose.
What is a normal QTc for men and women?
Most sources put the upper limit of a normal QTc at about 440 to 450 milliseconds in men and 460 milliseconds in women; Merck's ECG chapter gives 350 to 450 ms for men and 360 to 460 ms for women. A QTc above 500 ms is the key danger threshold because the risk of torsades de pointes is clearly higher above it. Bazett's formula, the QT divided by the square root of the RR interval, overestimates the QTc at fast heart rates and underestimates it at slow ones.
How do you convert ECG boxes to milliseconds and calculate heart rate?
At the standard paper speed of 25 mm/s, one small box is 0.04 seconds (40 ms) and one large box, made of five small boxes, is 0.20 seconds (200 ms). A normal PR spans 3 to 5 small boxes and a normal QRS fewer than 3. For a regular rhythm, heart rate is 300 divided by the number of large boxes between R waves, or 1,500 divided by the number of small boxes; for an irregular rhythm, count the beats in a 10-second strip and multiply by 6.
What causes a long or short QT interval?
The QT lengthens with drugs that block cardiac potassium channels (class IA, IC and III antiarrhythmics, macrolides, fluoroquinolones, antipsychotics, some antidepressants, methadone and ondansetron), with hypokalemia, hypomagnesemia and hypocalcemia, with hypothyroidism, and in congenital long QT syndromes such as Romano-Ward and Jervell and Lange-Nielsen. Hypercalcemia and digoxin shorten the QT, as does the rare congenital short QT syndrome. A long QT matters because it predisposes to torsades de pointes.