Aortic stenosis (AS) is one of those “you either recognize it instantly or you miss points” Step diagnoses. Here’s a quick, shareable mnemonic you can picture in your head on test day—plus the high-yield physiology and classic clues USMLE loves.
The Acronym Trick: AS = A SLOW Exit
Think of Aortic Stenosis as the left ventricle trying to push blood through a too-small door.
One-liner
AS = “A SLOW exit” → blood exits the LV slowly → systolic crescendo–decrescendo murmur with a delayed carotid upstroke.
Visual / Mental Image Mnemonic
Picture this:
A narrow aortic valve door with a big sign:
“AS: A SLOW Exit”
Next to it, a turtle-shaped carotid pulse crawling forward (slow rise), and a pressure gauge in the LV shooting up (high LV pressure).
The “AS” Mini-Checklist (Fast Recall)
A = Angina
- Due to LV hypertrophy increasing oxygen demand + reduced coronary perfusion (especially with high LV pressures).
S = Syncope
- Often exertional: fixed outflow obstruction → can’t increase cardiac output appropriately.
(Plus) Dyspnea/Heart Failure
- LV pressure overload → concentric hypertrophy → diastolic dysfunction → pulmonary congestion.
Classic triad: Angina + Syncope + Dyspnea (late finding, poor prognosis when symptomatic)
How It Sounds (Auscultation Hits)
Murmur
- Systolic crescendo–decrescendo ejection murmur
- Best heard at the right upper sternal border (RUSB)
Radiation
- Radiates to the carotids (very high-yield)
Maneuvers (Step favorite)
| Maneuver | Effect on AS murmur | Why |
|---|---|---|
| Squatting | ↑ | ↑ venous return + ↑ afterload → more flow across stenotic valve |
| Standing / Valsalva | ↓ | ↓ preload → less flow across valve |
| Handgrip | usually ↓ (or softer relative to MR) | ↑ afterload favors regurgitant murmurs (MR/AR/VSD) more than fixed obstruction |
The Pulse + Heart Sounds Clues
Carotid pulse
- Pulsus parvus et tardus = weak and delayed upstroke
(“parvus” = small amplitude; “tardus” = late peak)
Heart sound
- Soft/absent A2 in severe AS (immobile calcified valve)
Pathophysiology in One Breath (Why LV Hypertrophies)
AS causes chronic pressure overload, so the LV adapts with concentric hypertrophy to reduce wall stress.
High-yield physics tie-in (Laplace):
- As pressure rises, the heart increases wall thickness → lowers wall stress .
Etiologies USMLE Loves (Age + Risk Factors)
| Cause | Typical patient | Clue |
|---|---|---|
| Calcific degeneration | Older adult | Risk factors similar to atherosclerosis |
| Congenital bicuspid valve | Younger (50s-60s) | Can be associated with aortic dilation; early calcification |
| Rheumatic heart disease | Variable | Often mitral involvement too; commissural fusion |
Classic Complications/Associations
- LVH → diastolic dysfunction → pulmonary edema
- Reduced coronary perfusion → angina
- Risk of sudden death when symptomatic (esp. syncope/heart failure)
- Heyde syndrome (testable association): severe AS → acquired von Willebrand factor deficiency → GI angiodysplasia bleeding
Quick Differentiation: AS vs HCM (Common Trap)
| Feature | Aortic stenosis | Hypertrophic cardiomyopathy (HCM) |
|---|---|---|
| Murmur radiation | To carotids | No carotid radiation typical |
| Valsalva/standing | ↓ | ↑ |
| Squatting | ↑ | ↓ |
| Pulse | parvus et tardus | “spike-and-dome” carotid possible |
10-Second Exam Stem Recognition
If you see:
- Elderly or bicuspid valve history
- Crescendo–decrescendo systolic murmur at RUSB
- Radiation to carotids
- Syncope/angina/dyspnea
- Delayed carotid upstroke
…it’s A SLOW Exit: Aortic Stenosis.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
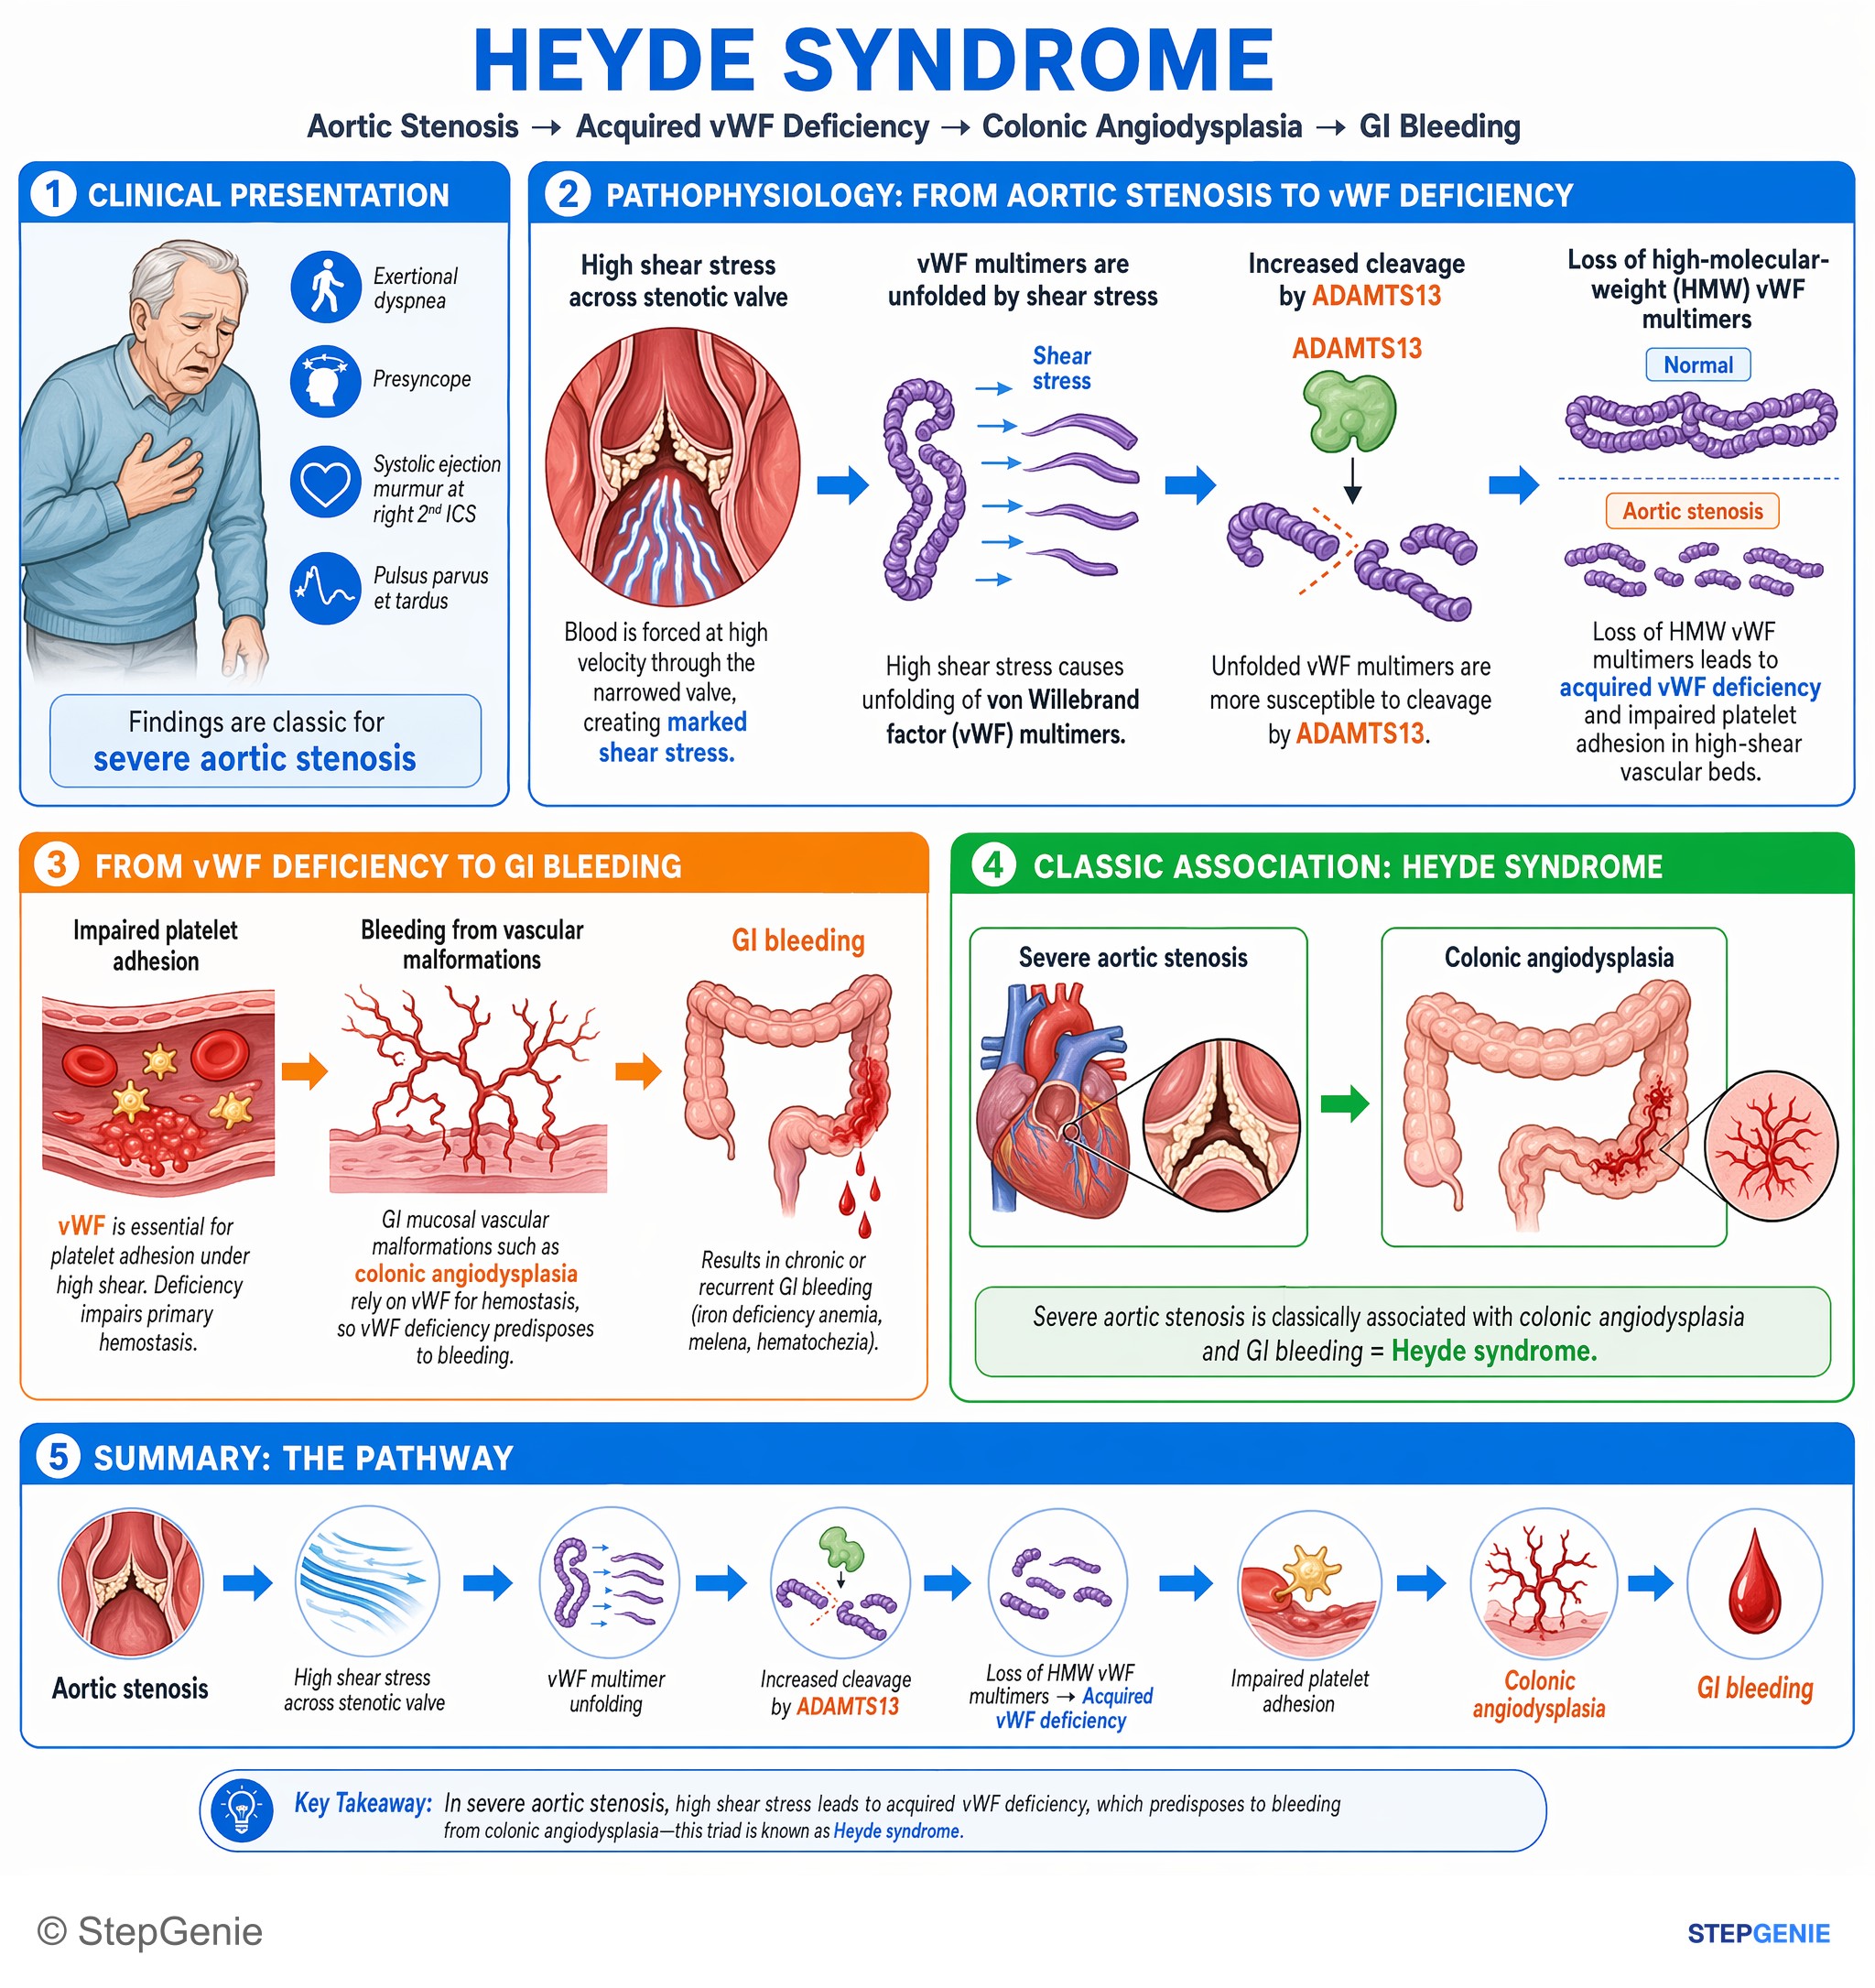
Aortic stenosis causes high shear stress across the valve → acquired vWF deficiency → GI bleeding from colonic angiodysplasia (Heyde…
USMLE Step 1Frequently Asked Questions
Why does aortic stenosis cause left ventricular hypertrophy?
Aortic stenosis causes left ventricular hypertrophy because it creates chronic pressure overload. The left ventricle has to generate much higher pressure to push blood through the narrowed aortic valve, so it adapts with concentric hypertrophy to reduce wall stress. This pressure overload can later lead to diastolic dysfunction and pulmonary congestion.
How do you tell aortic stenosis from hypertrophic cardiomyopathy on maneuvers and exam?
Aortic stenosis is suggested by carotid radiation, a weak delayed carotid pulse, and a murmur that decreases with standing or Valsalva but increases with squatting. Hypertrophic cardiomyopathy usually does not radiate to the carotids, increases with standing or Valsalva, and decreases with squatting. Pulsus parvus et tardus is a classic clue favoring aortic stenosis.
What are the classic symptoms of aortic stenosis?
The classic symptoms are angina, syncope, and dyspnea. Angina occurs because left ventricular hypertrophy raises oxygen demand while coronary perfusion is reduced. Syncope is often exertional because the fixed outflow obstruction prevents an appropriate rise in cardiac output. Dyspnea reflects pressure overload leading to concentric hypertrophy, diastolic dysfunction, and pulmonary congestion.
What murmur and pulse findings are most classic for aortic stenosis?
The classic findings are a systolic crescendo-decrescendo ejection murmur at the right upper sternal border with radiation to the carotids, plus pulsus parvus et tardus. That pulse means the carotid upstroke is weak and delayed. In severe disease, the aortic component of S2 can also be soft or absent because the calcified valve is immobile.
What causes the aortic stenosis murmur to get louder or softer with bedside maneuvers?
The aortic stenosis murmur gets louder with squatting and softer with standing or Valsalva because the amount of flow across the stenotic valve changes. Squatting increases venous return and afterload, which increases flow across the narrowed valve and intensifies the murmur. Standing and Valsalva reduce preload, so less blood crosses the valve and the murmur becomes quieter.