Prosthetic heart valves fail in a small set of testable ways: thrombosis and thromboembolism, bleeding from anticoagulation, endocarditis, paravalvular leak with hemolysis, structural deterioration or pannus, and conduction block, remembered here as PATCHES. Mechanical valves last but need lifelong warfarin (a vitamin K antagonist, VKA): the usual target INR is 2.5 for a bileaflet mechanical aortic valve without thromboembolic risk factors and 3.0 for a mechanical mitral valve or a higher-risk aortic valve, and DOACs are not used (dabigatran is contraindicated and apixaban is not recommended). Bioprosthetic (tissue) valves usually need only aspirin long term but deteriorate faster, especially in younger patients.
PATCHES: the prosthetic valve complications mnemonic
| Letter | Complication | Why it happens | Classic stem clue | What to do |
|---|---|---|---|---|
| P | Paravalvular leak | Blood leaks around the sewing ring instead of through the valve; more common after TAVI than after surgical replacement | New regurgitant murmur, heart failure or hemolysis after valve replacement | Echo to locate it; repair by surgery or, in selected patients without active infection, catheter-based closure |
| A | Anticoagulant-related bleeding | Lifelong warfarin for mechanical valves | Bleeding with a high INR | Reverse warfarin; prothrombin complex concentrate for significant bleeding |
| T | Thrombosis and thromboembolism | Interrupted or subtherapeutic warfarin; obstructive thrombosis occurs mainly with mechanical valves | Dyspnea, heart failure or an embolic event (such as stroke) with a low INR; high gradient across the valve | TTE, then TEE, CT or fluoroscopy; obstructive left-sided thrombosis: fibrinolysis or surgery |
| C | Conduction block | Aortic valve replacement, more often TAVI than surgery; valve ring abscess in endocarditis | New heart block after valve replacement; new AV block during endocarditis | Permanent pacemaker when needed; abscess or heart block in endocarditis is an indication for early surgery |
| H | Hemolysis | Shear stress fragments red cells, especially with a paravalvular leak or a malfunctioning mechanical valve | Anemia with ↑ LDH, ↑ indirect bilirubin, ↓ haptoglobin and schistocytes; iron deficiency from hemosiderinuria | Look for and treat a paravalvular leak; replace iron if deficient |
| E | Endocarditis | Early (within 1 year of surgery): staphylococci lead in the first 2 months; late: organisms like native-valve endocarditis | Fever or persistent bacteremia in anyone with a prosthetic valve | Blood cultures and TEE; early surgery for heart failure, abscess, heart block, fungi or resistant organisms, or persistent bacteremia |
| S | Structural deterioration and pannus | Bioprosthetic leaflets degenerate over years, faster in younger patients; pannus is fibrous tissue ingrowth that narrows a prosthesis | Gradual heart failure and a new stenotic or regurgitant murmur years after bioprosthetic replacement | Echo; reoperation, or a catheter-based valve-in-valve procedure in selected patients |
Three of the letters travel together on exams: a paravalvular leak (P) causes hemolysis (H), and endocarditis (E) that spreads into the valve ring causes abscesses and conduction block (C).
Mechanical vs bioprosthetic valves
| Feature | Mechanical valve | Bioprosthetic (tissue) valve |
|---|---|---|
| Durability | Very durable | Finite; deteriorates faster in younger patients |
| Long-term antithrombotic therapy | Lifelong warfarin for every patient | Lifelong aspirin if there is no other indication for anticoagulation |
| Early after surgical implantation | Warfarin | Warfarin (INR about 2.5) for 3 to 6 months is an option if bleeding risk is low |
| DOACs | Not used: dabigatran contraindicated, apixaban not recommended | An alternative to warfarin for atrial fibrillation starting more than 3 months after implantation |
| Main trade-off | More bleeding, from lifelong anticoagulation | More reintervention, from faster deterioration |
| Usual choice for aortic valve replacement | Under age 50 | Over age 65; between 50 and 65, individualized |
Survival and valve thrombosis rates are similar with the two types; the choice turns on bleeding risk versus durability. The age cutoffs follow durability: ACC/AHA guideline tables put the 15-year risk of structural deterioration of a bioprosthesis at about 30% for a 40-year-old and 50% for a 20-year-old, but under 10% for patients older than 70.
Anticoagulation targets for mechanical valves
| Valve | Warfarin target |
|---|---|
| Bileaflet mechanical aortic valve, no thromboembolic risk factors | INR 2.5 (range 2.0–3.0) |
| Mechanical aortic valve with atrial fibrillation, previous thromboembolism or LV dysfunction | INR 3.0 (range 2.5–3.5) |
| Mechanical mitral or tricuspid valve | INR 3.0 (range 2.5–3.5) |
| Older caged-ball or caged-disk valve | INR 3.0 (range 2.5–3.5) |
| Any mechanical valve | No DOACs: dabigatran contraindicated, apixaban not recommended |
Low-dose aspirin is added to warfarin only in selected cases, for example after thromboembolism despite a therapeutic INR. It never replaces warfarin.
Why not DOACs? In RE-ALIGN, dabigatran was compared with warfarin in patients with mechanical valves, and the trial was stopped early because dabigatran caused more thromboembolic events (valve thrombosis, stroke, transient ischemic attack and myocardial infarction) and more major bleeding. Dabigatran's label now lists a mechanical valve as a contraindication, apixaban's label says it is not recommended with prosthetic valves, and the 2020 ACC/AHA guideline says patients with a mechanical prosthesis and atrial fibrillation should receive a VKA. For how these drugs work, see heparin, warfarin and DOACs.
Valve thrombosis vs pannus
Both obstruct a prosthesis, but the treatment differs:
| Feature | Valve thrombosis | Pannus |
|---|---|---|
| What it is | Clot on the valve | Fibrous tissue ingrowth |
| Typical setting | Interrupted or subtherapeutic warfarin, mainly with mechanical valves | Gradual ingrowth, identified on imaging |
| Imaging | TEE or CT shows thrombus | TEE or CT shows tissue ingrowth |
| Treatment | Fibrinolysis or surgery | Surgery is favored |
The ACC/AHA table for choosing between fibrinolysis and surgery favors surgery with low surgical risk and available expertise, a large clot (> 0.8 cm²), recurrent thrombosis, NYHA class IV symptoms, left atrial thrombus, other valve disease, coronary disease needing revascularization, a contraindication to fibrinolysis, or possible pannus; it favors fibrinolysis with high surgical risk, a small clot (≤ 0.8 cm²), a first episode and NYHA class I to III symptoms.
Bioprosthetic valves can thrombose too; with leaflet degeneration, thrombosis is one of the two causes of bioprosthetic valve dysfunction, and therapeutic warfarin has been associated with less reduced leaflet motion, a sign of leaflet thrombosis, on imaging.
Exam traps
- A DOAC for a mechanical valve is the wrong answer. Use warfarin, not dabigatran or apixaban.
- Aspirin never replaces warfarin for a mechanical valve; it is only an add-on in selected patients.
- Dyspnea or an embolic event with a low INR in someone with a mechanical valve means valve thrombosis until proven otherwise. Obstructive thrombosis needs fibrinolysis or surgery; restarting warfarin alone does not relieve the obstruction.
- New AV block during endocarditis signals spread into the valve ring (abscess), an indication for early surgery. Prosthetic valve infections are particularly likely to cause ring abscesses, and TTE sensitivity is limited, so get a TEE. For native-valve endocarditis, see the infective endocarditis Q-bank breakdown.
- Early prosthetic valve endocarditis isn't only S. epidermidis. Coagulase-negative staphylococci are the classic association, but in the first 2 months S. aureus is the most frequent cause, followed by coagulase-negative staphylococci, gram-negative bacilli and Candida; late infection looks like native-valve endocarditis (streptococci, S. aureus, coagulase-negative staphylococci, enterococci).
- TAVI vs surgical aortic valve replacement: TAVI increases the need for a permanent pacemaker and causes more paravalvular regurgitation.
- Hemolysis after valve replacement can leave iron deficiency from chronic hemosiderinuria.
- Pregnancy: warfarin crosses the placenta and can cause fetal abnormalities, mainly in the first trimester, but the risk is dose-dependent and very low at 5 mg/day or less. Substituting heparin for warfarin in the first 12 weeks and the last 2 weeks of pregnancy reduces the risk.
Worked example
Vignette. A 58-year-old man with a bileaflet mechanical mitral valve stopped taking warfarin 2 weeks ago because of cost. He has 2 days of worsening dyspnea, crackles at both lung bases and a diastolic murmur. INR is 1.1. TTE shows a markedly elevated transmitral gradient, and fluoroscopy shows restricted leaflet motion. What is the most appropriate management?
Answer: Urgent treatment of obstructive mechanical valve thrombosis with fibrinolytic therapy or surgery; with NYHA class IV symptoms, surgery is favored if his surgical risk is low and expertise is available.
Reasoning: A subtherapeutic INR, a stenotic murmur, acute heart failure and restricted leaflet motion add up to obstructive left-sided mechanical valve thrombosis. The ACC/AHA table weighs surgical risk, clot size, NYHA class, recurrence and the possibility of pannus to choose between fibrinolysis and surgery. Restarting warfarin alone does not relieve an obstructed valve, and a DOAC is not an option for a mechanical valve. Once he recovers, his target INR is 3.0.
Key takeaways
- PATCHES: Paravalvular leak, Anticoagulant bleeding, Thrombosis and thromboembolism, Conduction block, Hemolysis, Endocarditis, Structural deterioration and pannus.
- Mechanical valves: lifelong warfarin; INR 2.5 for a low-risk bileaflet aortic valve, 3.0 for a mitral or higher-risk aortic valve; no DOACs.
- Bioprosthetic valves: lifelong aspirin, with warfarin for 3–6 months after surgery as an option if bleeding risk is low; deterioration is faster in the young.
- Obstructive mechanical valve thrombosis: fibrinolysis or surgery, chosen by surgical risk, clot size, NYHA class and possible pannus.
- Prosthetic valve endocarditis: staphylococci dominate the first 2 months; use TEE; abscess or heart block means early surgery.
- Paravalvular leak causes regurgitation and hemolysis; catheter-based closure is an option in selected patients without active infection.
Sources
- 2020 ACC/AHA Guideline for the Management of Patients With Valvular Heart Disease — Circulation
- 2017 AHA/ACC Focused Update of the 2014 AHA/ACC Guideline for the Management of Patients With Valvular Heart Disease — Circulation
- Overview of Cardiac Valvular Disorders — Merck Manual Professional Edition
- Prosthetic Valve Endocarditis — StatPearls, NCBI Bookshelf
- Microangiopathic Hemolytic Anemia — Merck Manual Professional Edition
- PRADAXA (dabigatran etexilate) prescribing information — DailyMed, National Library of Medicine
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
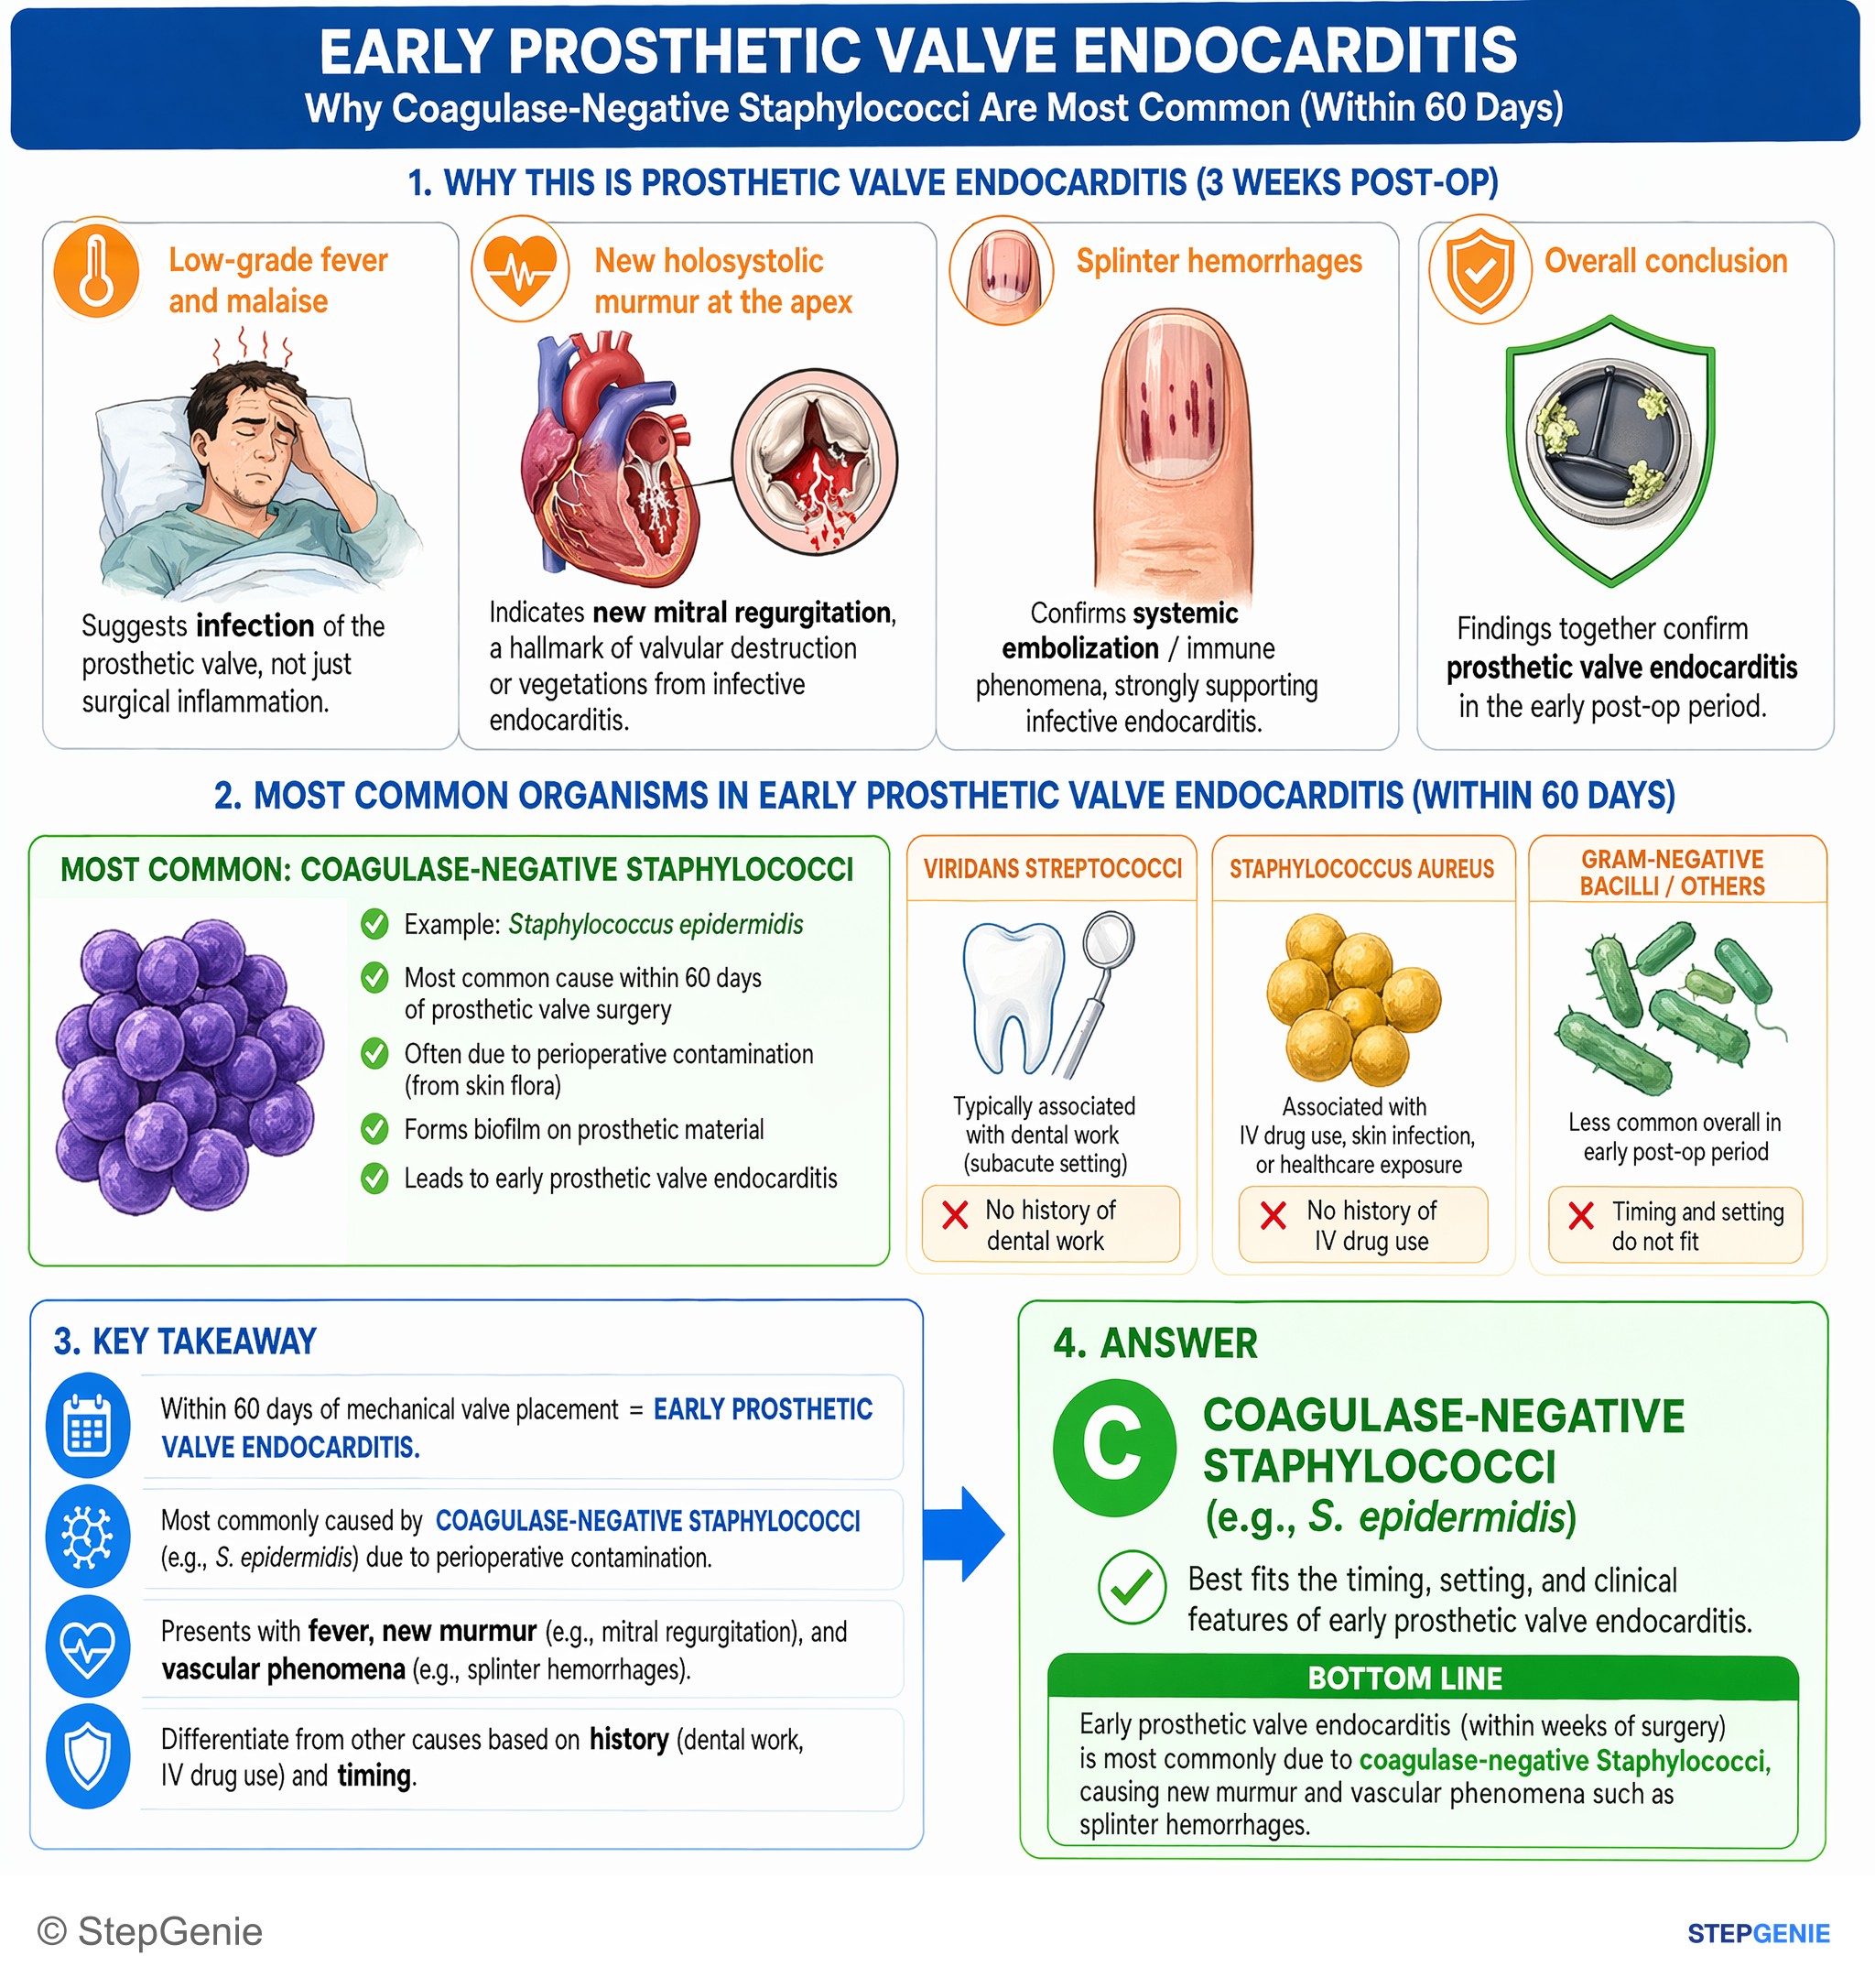
Prosthetic valve endocarditis within weeks of surgery is most commonly due to coagulase-negative Staphylococci causing new murmur and…
USMLE Step 2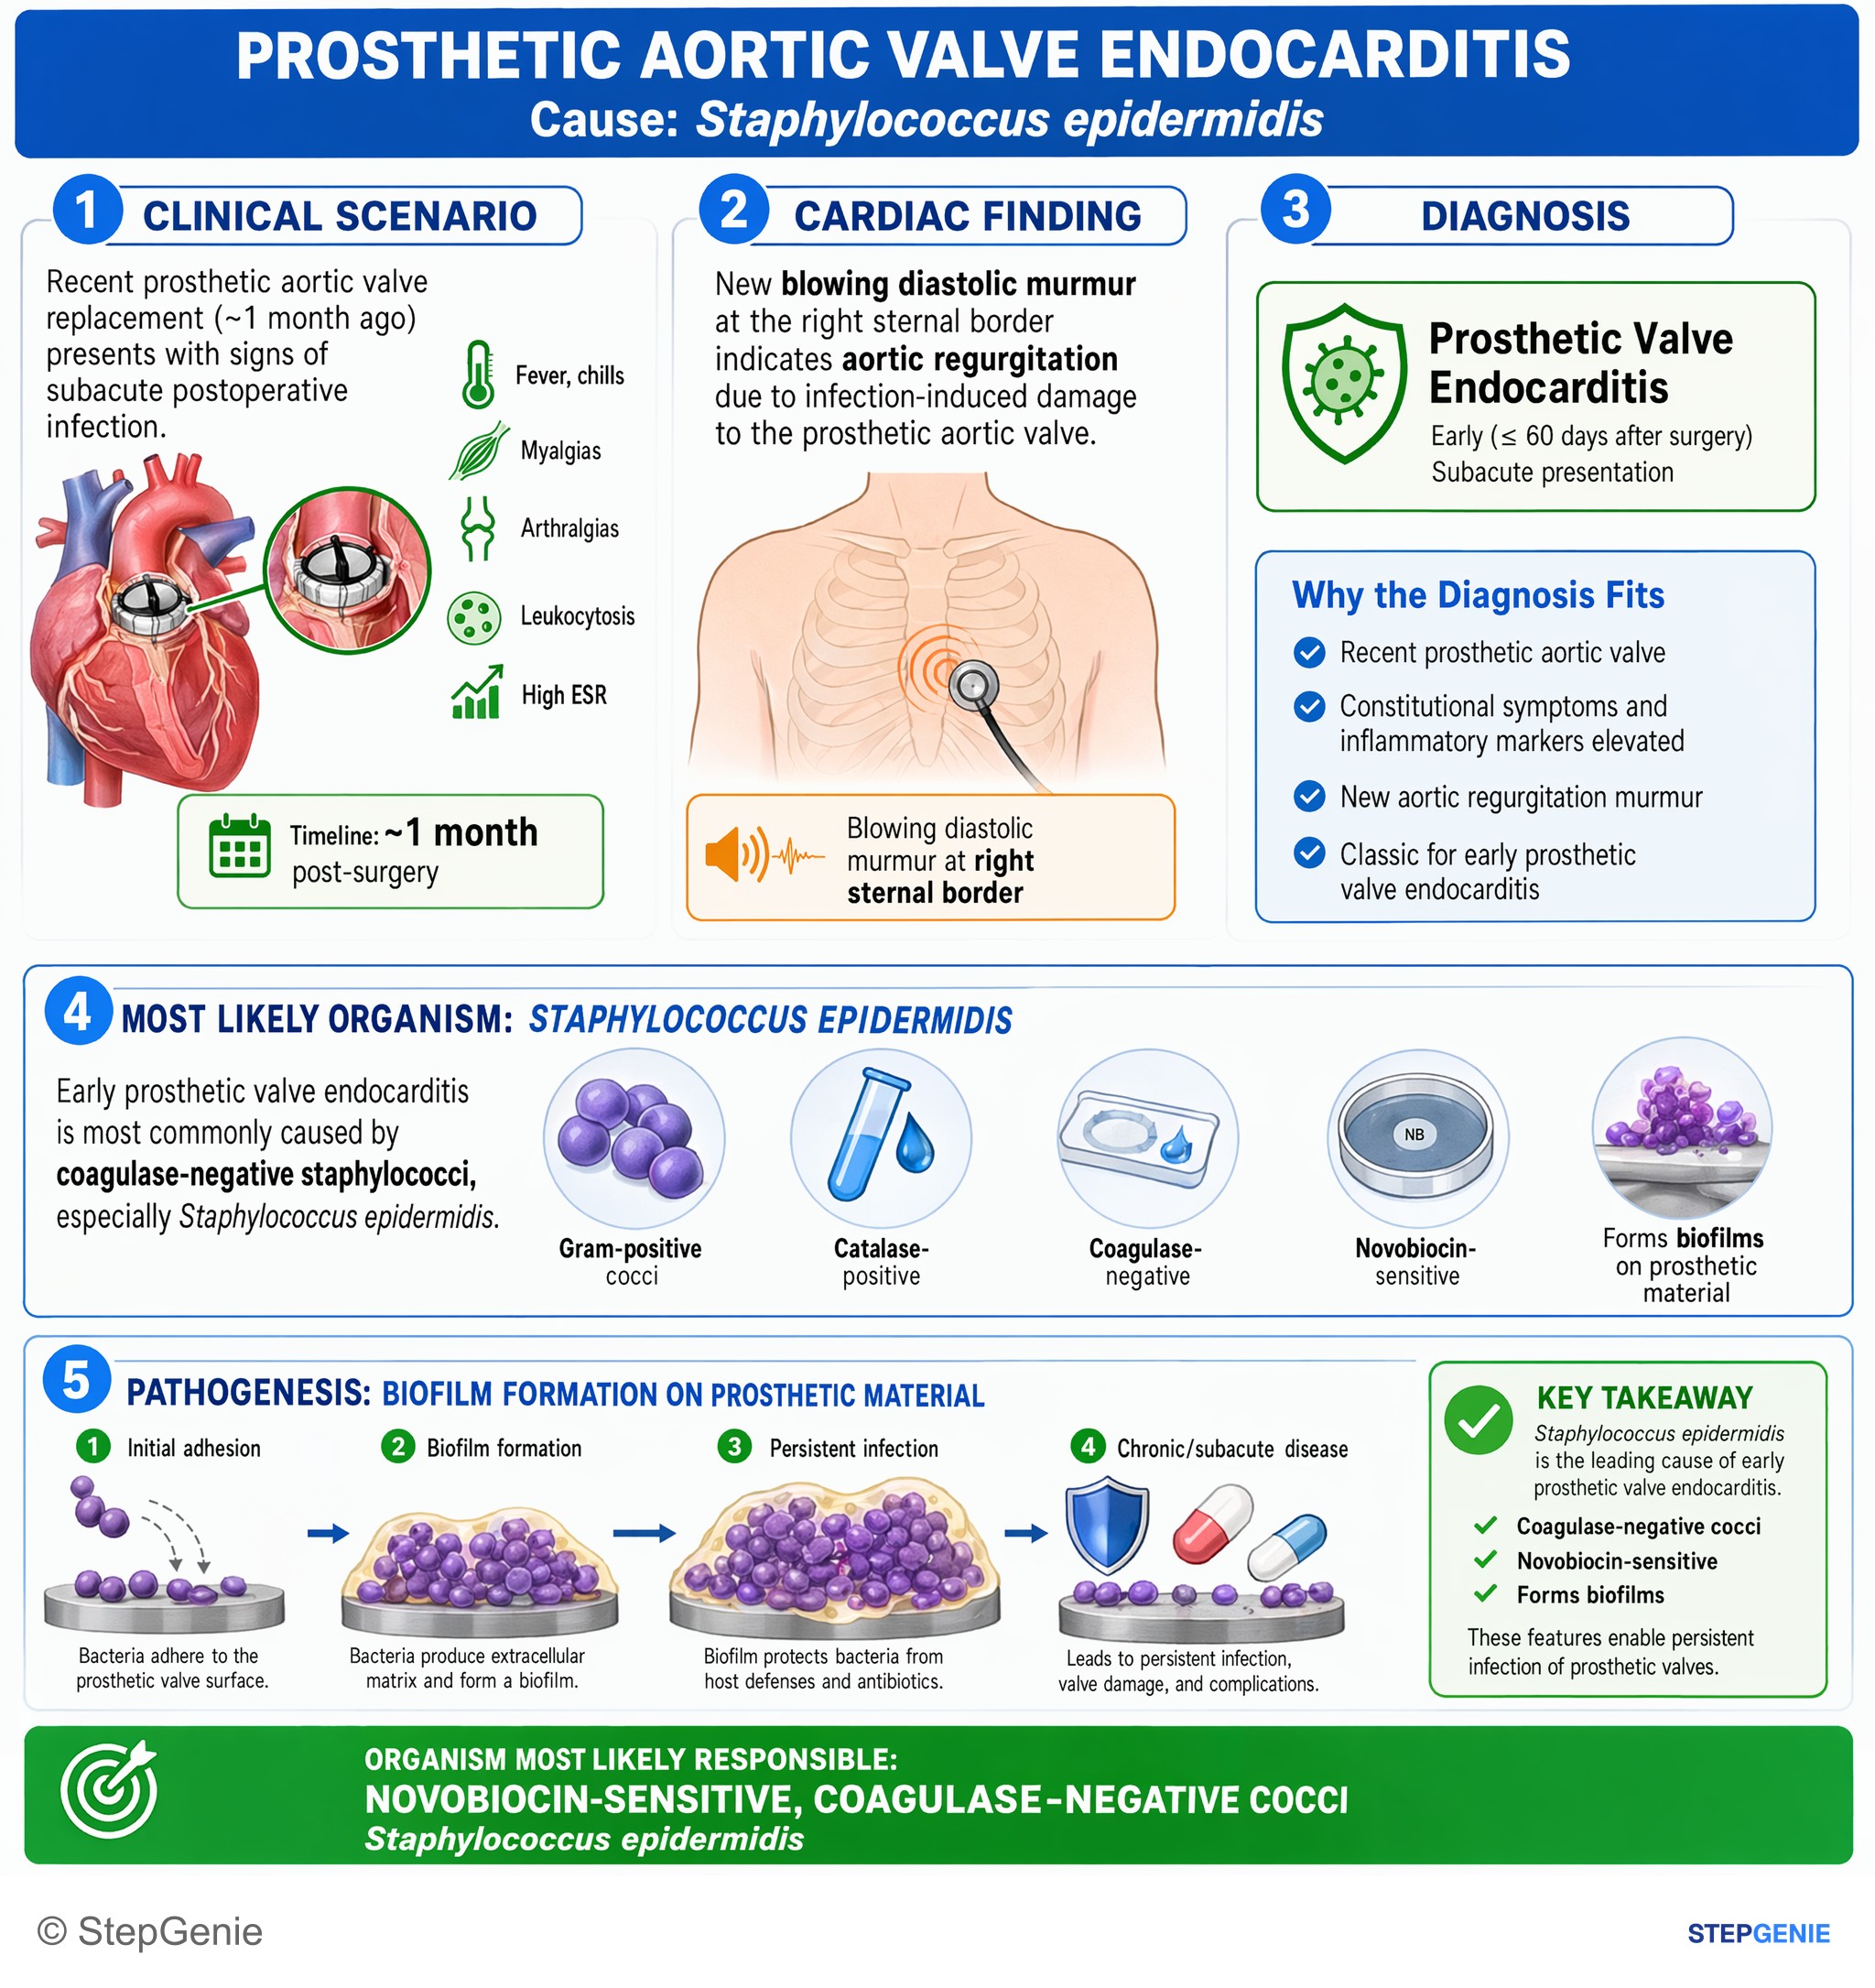
Staphylococcus epidermidis causes early prosthetic valve endocarditis; it is coagulase-negative, novobiocin-sensitive and forms biofilms…
USMLE Step 1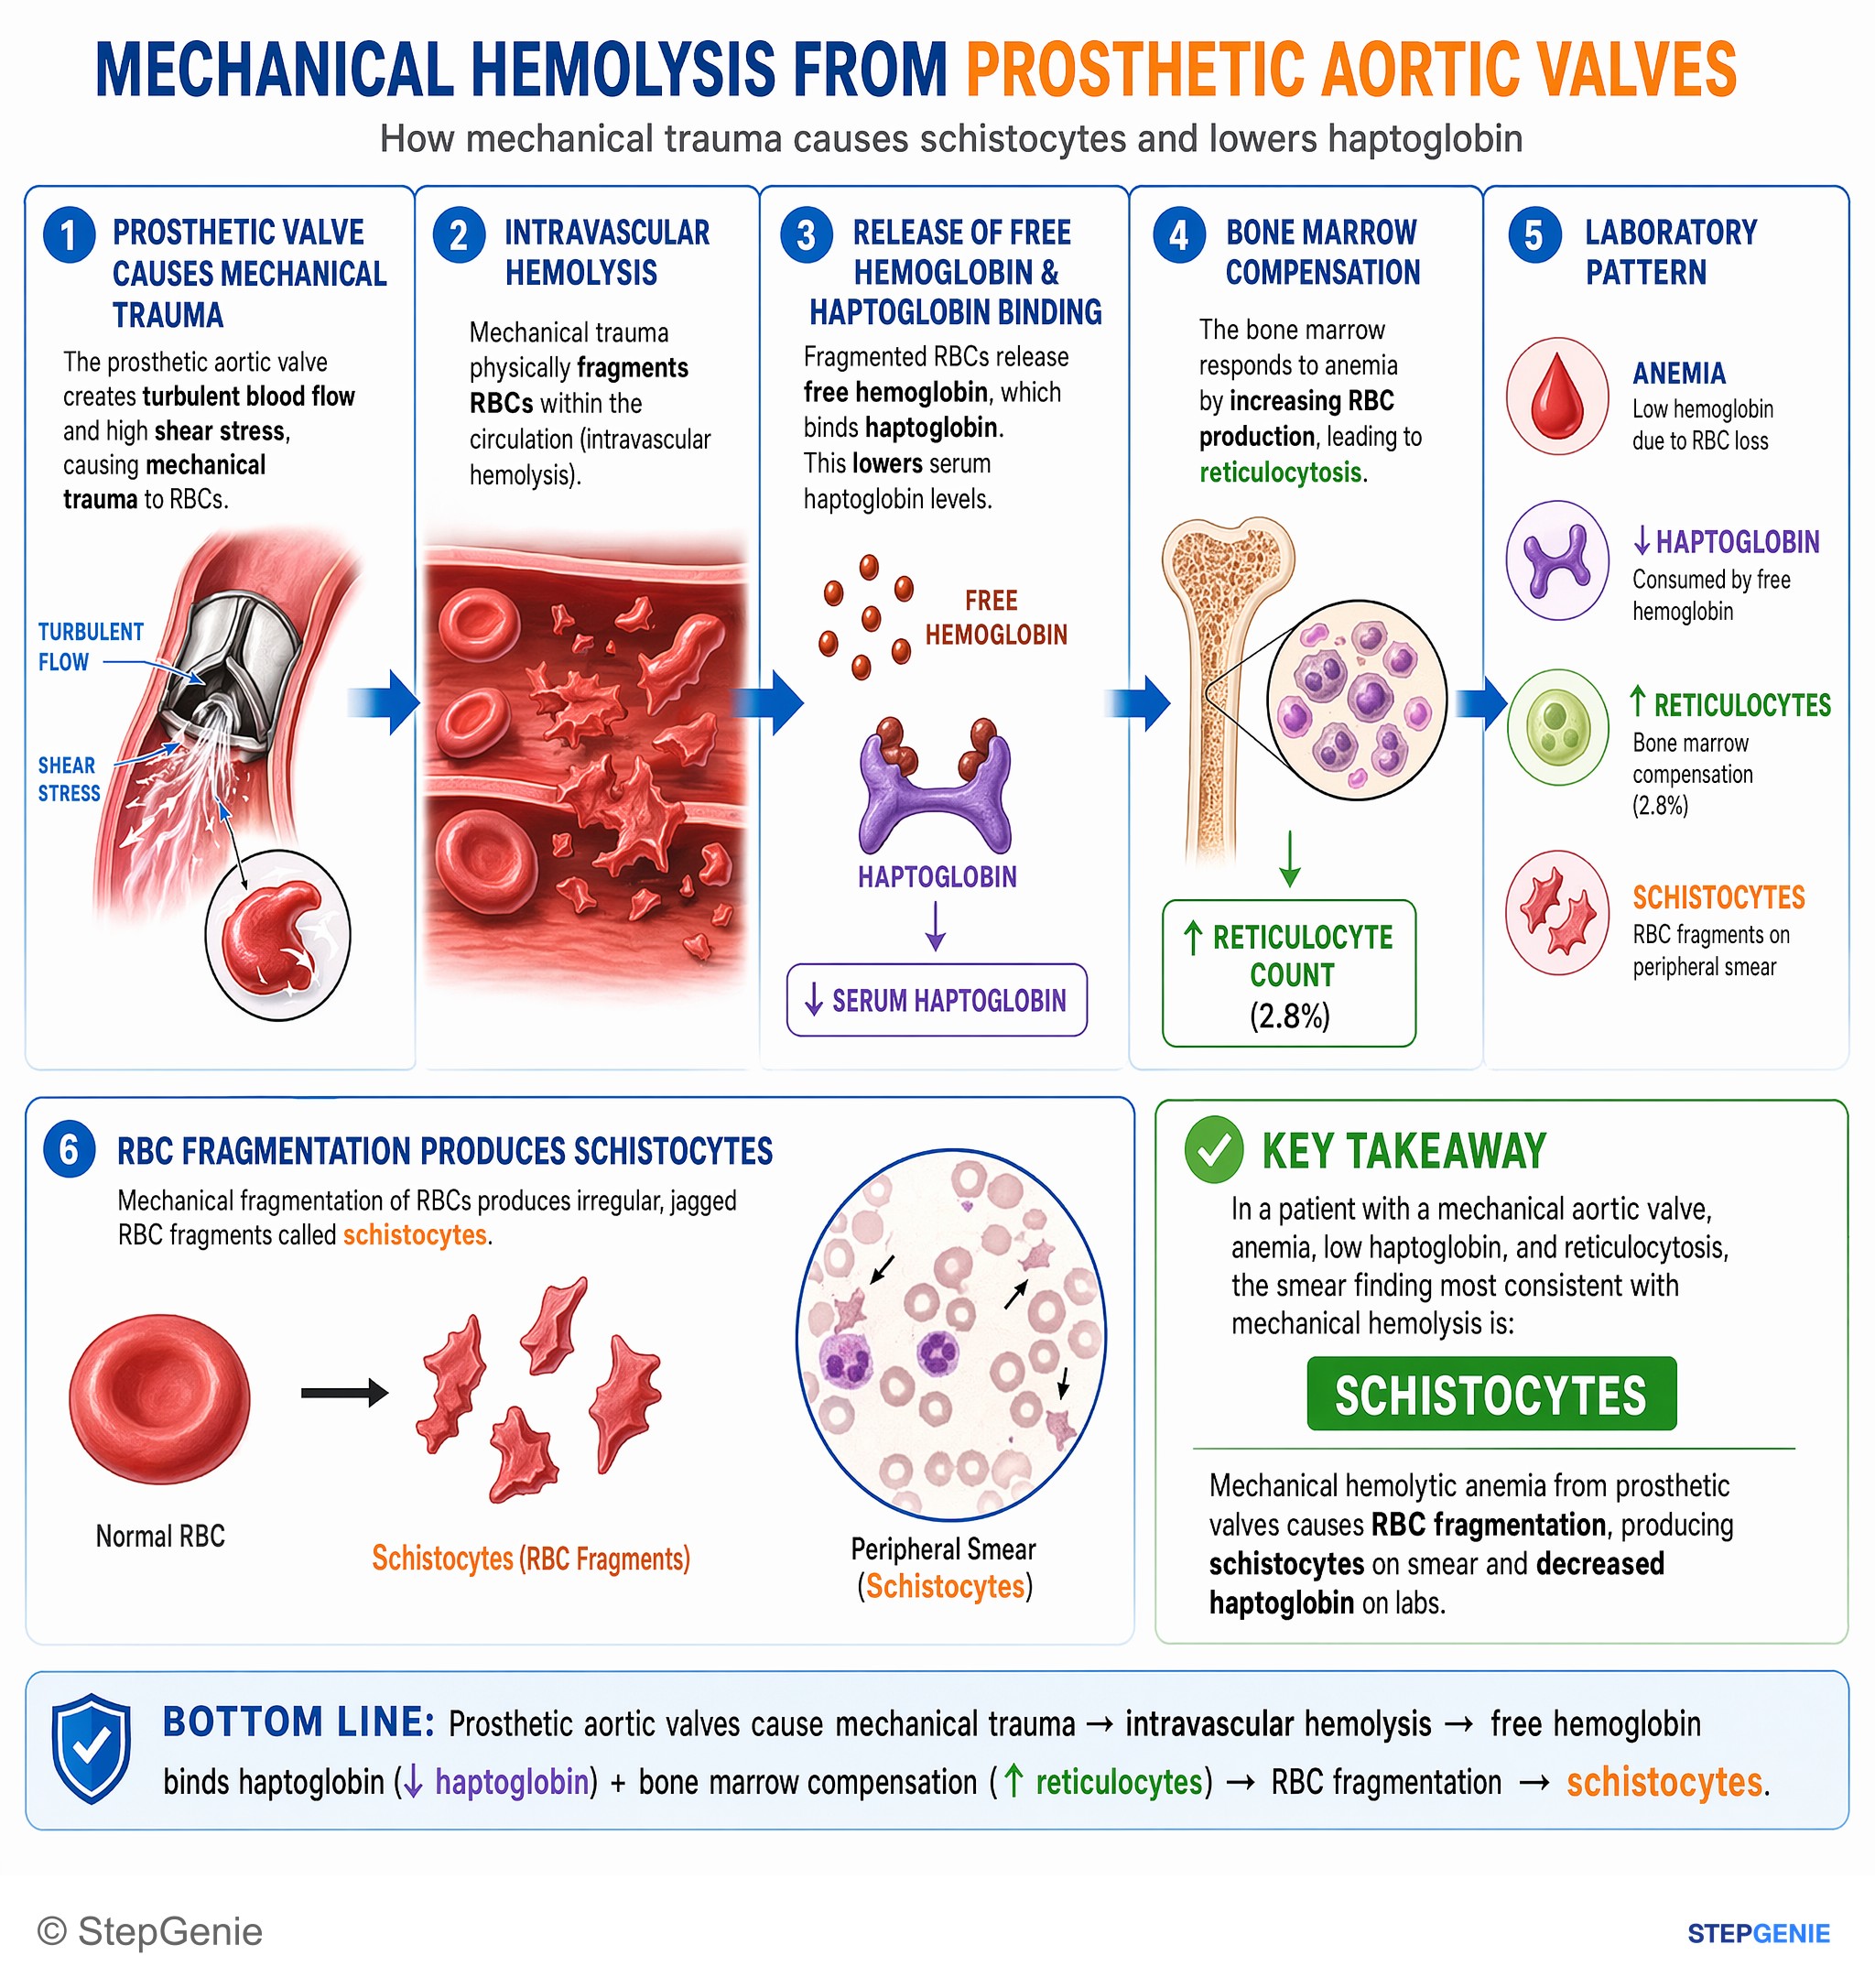
Mechanical hemolytic anemia from prosthetic valves causes RBC fragmentation, producing schistocytes and decreased haptoglobin on labs.
USMLE Step 1Frequently Asked Questions
Can you use a DOAC with a mechanical heart valve?
No. Warfarin, a vitamin K antagonist, is the only appropriate oral anticoagulant for a mechanical valve. Dabigatran is contraindicated after the RE-ALIGN trial was stopped early for more thromboembolic events and more major bleeding than with warfarin, and apixaban's label says it is not recommended with prosthetic valves. In patients with prosthetic valves, DOACs are an option only for atrial fibrillation with a bioprosthetic valve more than 3 months after implantation.
What is the INR goal for a mechanical mitral valve?
The target is 3.0 (range 2.5 to 3.5) with warfarin. A modern bileaflet mechanical aortic valve without thromboembolic risk factors is kept at 2.5 (range 2.0 to 3.0), rising to 3.0 with atrial fibrillation, previous thromboembolism or LV dysfunction. Older caged-ball valves also need a target of 3.0.
What are the signs of prosthetic valve thrombosis?
Mechanical valve thrombosis presents with obstruction (dyspnea, heart failure, a new stenotic murmur) or with embolic events such as stroke, typically after warfarin has been stopped or the INR has run low. Echocardiography shows a high gradient across the valve, and TEE, CT or fluoroscopy shows restricted leaflet motion and helps separate thrombus from pannus. Obstructive left-sided thrombosis is treated with fibrinolytic therapy or surgery.
Why does a prosthetic valve cause hemolytic anemia?
Red cells are fragmented by shear stress as blood jets through a paravalvular leak or around a malfunctioning mechanical valve. The pattern is intravascular hemolysis: anemia with high LDH and indirect bilirubin, low haptoglobin and schistocytes, and chronic hemosiderinuria can add iron deficiency. Management means finding and fixing the leak, surgically or with catheter-based closure in selected patients, and replacing iron if needed.
What organisms cause prosthetic valve endocarditis?
Early prosthetic valve endocarditis, within 1 year of surgery, is dominated by staphylococci: in the first 2 months Staphylococcus aureus is most frequent, followed by coagulase-negative staphylococci such as Staphylococcus epidermidis, gram-negative bacilli and Candida. From 2 to 12 months, streptococci, S. aureus and coagulase-negative staphylococci predominate, and infection after 1 year resembles native-valve endocarditis. TEE is preferred because TTE has limited sensitivity with prosthetic valves.