The pheochromocytoma mnemonic is the 5 P's: Pressure (hypertension, sustained or in paroxysms), Pain (headache), Perspiration, Palpitations and Pallor. Headache, sweating and palpitations form the classic triad; in a patient with hypertension they call for plasma free or 24-hour urine fractionated metanephrines first and imaging second, and a confirmed tumor gets an alpha-blocker before any beta-blocker, because a beta-blocker alone leaves alpha-1 vasoconstriction unopposed.
The 5 P's are a memory aid, not a diagnostic rule. About half of pheochromocytomas are now found before they cause symptoms, on imaging done for another reason or by screening relatives who carry a mutation. In a prospective study of more than 2,000 patients tested for these tumors, sweating, palpitations and pallor were 30–90% more common in those who had one, while headache and blood pressure differed little or not at all. The diagnosis rests on biochemistry, then imaging.
A pheochromocytoma is a catecholamine-secreting tumor of chromaffin cells in the adrenal medulla. The same tumor outside the adrenal is a paraganglioma, and the two are grouped as PPGL. The old "rule of 10s" no longer holds: about 35–40% of PPGLs are hereditary, so every patient should be offered genetic testing.
The 5 P's of pheochromocytoma
| P | Means | What to expect | Caveat |
|---|---|---|---|
| Pressure | Hypertension | Present in most patients; paroxysmal in about 45% | Norepinephrine favors sustained hypertension, epinephrine spells; some patients have orthostatic or even low blood pressure |
| Pain | Headache | Up to 90% of patients | Little or no more common in patients with PPGL than in people tested who did not have one |
| Perspiration | Sweating | Excessive, often truncal, in about 60–70% | Among the best discriminators |
| Palpitations | Forceful, rapid heartbeat | Pounding or racing heart during spells | Also discriminating; heart rate runs higher in true cases |
| Pallor | Facial pallor | About 27% | Flushing is uncommon |
Pressure and palpitations trace back to adrenergic receptors: α1 stimulation constricts vessels and raises blood pressure, β1 stimulation speeds the heart, and epinephrine acting on β2 receptors dilates peripheral arteries, which can lower blood pressure. The National Cancer Institute (NCI) lists catecholamine-excess symptoms almost exactly as the mnemonic does: hypertension, headache, perspiration, forceful palpitations, tremor and facial pallor.
How to use it. The shorter "3 P's" (pain, palpitations, perspiration) are the classic triad, and in a patient with hypertension they should prompt immediate suspicion. Use the mnemonic to decide whom to test; metanephrines decide the diagnosis.
Where it falls short. The 5 P's describe a symptomatic, catecholamine-secreting tumor. They fail for the many tumors now found without symptoms, as incidentalomas or by family screening, and for tumors that secrete mainly dopamine or nothing, such as most skull base and neck paragangliomas; and they overlap with anxiety disorders, hyperthyroidism and drug-induced hypertension.
One more P for the syndromes: MEN2A has two P's (pheochromocytoma and parathyroid hyperplasia or adenoma) plus medullary thyroid carcinoma; MEN2B has one P (pheochromocytoma) plus medullary thyroid carcinoma, mucosal neuromas and a marfanoid habitus.
The classic triad and pheochromocytoma spells
The classic triad is episodic headache, sweating and tachycardia (palpitations). Spells may come weekly, several times a day or only every few months; most last less than an hour, sometimes only minutes. Between spells, blood pressure may be normal or high: sustained hypertension between paroxysms occurs in 50–60% of patients with pheochromocytoma.
Spells can be set off by exertion, posture changes, palpation of the tumor, anesthesia or surgery, tyramine-rich foods, urination (bladder wall tumors) and the drugs listed below.
Other clues include tremor, anxiety or a sense of impending doom, nausea, weight loss despite a normal appetite, constipation, orthostatic hypotension, hyperglycemia and erythrocytosis. Untreated catecholamine excess can cause myocardial infarction, arrhythmias, pulmonary edema, cardiomyopathy and shock.
Spells without a tumor: StatPearls' differential includes anxiety disorder, hyperthyroidism, migraine, carcinoid syndrome and drug-induced hypertension, and panic disorder is the classic look-alike. PPGLs are found in only 0.2–0.6% of hypertensive patients in general outpatient clinics, so test when the picture fits: spells, hypertension resistant to several drugs, a hypertensive reaction to a triggering drug, or an adrenal mass. Other secondary causes are compared in essential vs secondary hypertension.
The rule of 10s is outdated
The classic teaching held that 10% of pheochromocytomas are familial, 10% malignant, 10% extra-adrenal and 10% in children; other versions add 10% bilateral or 10% normotensive. StatPearls calls the rule oversimplified and incorrect.
| "10%" | Current figure | What it means |
|---|---|---|
| Familial | About 35–40% of PPGLs are hereditary; up to 25% of apparently sporadic cases carry a germline variant, as do 50–80% of children with PPGL | Offer genetic testing to every patient |
| Extra-adrenal | 15–20% of chromaffin-cell tumors are paragangliomas; about 30% in children | Look beyond the adrenal: organ of Zuckerkandl near the aortic bifurcation, bladder, carotid body |
| Malignant | 10–17% metastasize; more for sympathetic paragangliomas (15–35%, vs 5–20% for pheochromocytomas) and SDHB carriers (24–58%) | No tumor is labeled benign; follow-up is lifelong |
| Bilateral | About 10% overall and 20% in children; at least 50% in MEN2 and von Hippel–Lindau disease | Bilateral tumors suggest a syndrome |
| In children | About 9% of patients in large cohorts | Still roughly right |
| Normotensive | 10–20% have normal blood pressure; many screen-detected patients have no hypertension, and about half are diagnosed before symptoms | Normal blood pressure does not exclude a tumor |
Pheochromocytoma investigation: metanephrines first, imaging second
Who to test. The Endocrine Society lists suggestive (especially paroxysmal) symptoms, symptoms provoked by a crisis-triggering drug, an adrenal incidentaloma, a hereditary predisposition or syndromic features, and a previous PPGL. Nearly 5% of incidental adrenal masses prove to be pheochromocytomas. The 2023 European incidentaloma guideline limits testing to masses not typical of a benign adenoma (for example, unenhanced CT attenuation above 10 HU), because the chance of a pheochromocytoma at 10 HU or below is close to zero; on the exam, metanephrines for an incidentaloma remain the safe answer. See the adrenal incidentaloma workup.
Step 1: biochemistry.
- Measure plasma free metanephrines or 24-hour urine fractionated metanephrines. Draw blood after the patient has lain supine for at least 30 minutes; seated sampling gives higher values and more false positives.
- Metanephrines beat catecholamines because catechol-O-methyltransferase inside tumor cells converts catecholamines to metanephrines continuously, independent of release, so levels stay raised between spells; plasma catecholamines, released in bursts, can be normal. Plasma free metanephrines have a sensitivity of 97–99%, and a normal result typically excludes a secreting tumor; false negatives occur with tumors under 1 cm, dopamine-secreting skull base and neck tumors (measure methoxytyramine) and nonsecreting tumors.
- Reading the result: a rise of 3-fold or more above the upper limit is rarely a false positive, except in patients taking antidepressants or psychostimulants. Smaller rises need repeat testing under proper conditions, off interfering drugs if possible, or a clonidine suppression test: a tumor is likely if plasma normetanephrine is still raised 3 hours after oral clonidine and has fallen by less than 40%.
| Cause of a false positive | Effect |
|---|---|
| Tricyclic antidepressants, phenoxybenzamine | Raise normetanephrine with any assay |
| MAO inhibitors | Raise both normetanephrine and metanephrine |
| Sympathomimetics, cocaine, levodopa | Raise metanephrines; levodopa also raises methoxytyramine |
| Acetaminophen, labetalol, sotalol, methyldopa, buspirone, sulfasalazine | Interfere with some assay methods |
| Physical or emotional stress | Raises values |
Step 2: imaging. Localize only once there is clear biochemical evidence. CT of the abdomen and pelvis comes first; MRI is preferred for skull base and neck paragangliomas, metastatic disease, contrast allergy, and patients who should avoid radiation, such as children, pregnant women and germline carriers. For functional imaging, gallium-68 DOTATATE PET/CT (a somatostatin receptor tracer) is replacing ¹²³I-MIBG scintigraphy and is now considered the most effective test for metastases; ¹⁸F-FDOPA PET is preferred for VHL- and EPAS1-related tumors, and MIBG scans still select patients for ¹³¹I-MIBG therapy.
Never biopsy first. Fine-needle aspiration can trigger a crisis, and pheochromocytoma must be excluded before any adrenal biopsy.
Step 3: genetic testing. The Endocrine Society and other societies recommend referring everyone with a PPGL for genetic testing, with SDHx testing for paragangliomas and SDHB testing for metastatic disease.
Alpha or beta blocker first? Alpha first
Start the alpha-blocker before any beta-blocker, always. Catecholamines constrict vessels through α1 receptors, while β2 receptors mediate vasodilation in skeletal muscle. A beta-blocker given alone removes that vasodilation and leaves α1 vasoconstriction unopposed, so blood pressure can rise paradoxically into a life-threatening crisis. NCI states that beta-blockade "must never be initiated before alpha-adrenergic blockade," and metoprolol's label says to start it only after an alpha-blocker.
Preoperative preparation:
- Alpha-blocker for 7–14 days. Phenoxybenzamine, an irreversible, nonselective α1 and α2 blocker, is the usual choice; expect orthostatic hypotension, reflex tachycardia, nasal congestion and miosis. Because it also blocks the presynaptic α2 receptors that inhibit norepinephrine release, it causes more reflex tachycardia than the shorter-acting selective α1 blockers (doxazosin, prazosin, terazosin), an accepted alternative.
- High-sodium diet and fluids to reverse catecholamine-induced volume contraction and prevent severe hypotension after the tumor is removed.
- Beta-blocker only after alpha blockade, usually at least 3–4 days later, to control tachycardia (propranolol, atenolol or metoprolol).
- Calcium channel blockers (amlodipine, nifedipine) as add-ons, or as first agents when blood pressure is normal or only mildly raised.
- Metyrosine, which inhibits tyrosine hydroxylase, the rate-limiting enzyme of catecholamine synthesis, when control is inadequate or the tumor is unresectable; its main side effects are sleepiness, anxiety and depression.
Labetalol is not a substitute. Given IV, it blocks α and β receptors in a ratio of about 1:7, so it acts mainly as a beta-blocker; it is on the Endocrine Society's list of crisis-triggering drugs.
Surgery and after.
- Laparoscopic adrenalectomy for most pheochromocytomas; open surgery for large (over 6 cm) or invasive tumors and most paragangliomas; partial (cortical-sparing) adrenalectomy for selected hereditary cases.
- Intraoperative surges are treated with IV phentolamine, nitroprusside or nicardipine; once the tumor is out, blood pressure can drop sharply and need fluids and vasopressors.
- Hypotension is the most common postoperative complication. Hypoglycemia can follow, because catecholamines suppress insulin secretion and their sudden fall lets insulin rebound, so glucose is checked every 4–6 hours. Up to half of patients stay hypertensive for a few days.
- Recheck metanephrines 2–4 weeks after surgery, then annually for life.
Pheochromocytoma crisis: triggers, myths and treatment
A crisis is a rapid, massive catecholamine release causing severe hypertension (sometimes alternating with hypotension), arrhythmias, myocardial infarction, pulmonary edema, heart failure or shock. The first seven rows are the Endocrine Society's list of drug classes that can precipitate one:
| Trigger | Examples |
|---|---|
| Beta-blockers without alpha blockade | Propranolol, nadolol, timolol, sotalol, labetalol; selective β1 blockers at higher doses |
| Dopamine D2 antagonists | Metoclopramide, prochlorperazine, chlorpromazine, droperidol |
| Corticosteroids | Dexamethasone, prednisone, hydrocortisone, betamethasone |
| Peptides | Glucagon, ACTH |
| Sympathomimetics | Ephedrine, pseudoephedrine, phentermine, methylphenidate, dextroamphetamine |
| Reuptake and MAO inhibitors | Amitriptyline, imipramine; rarely SSRIs; phenelzine, tranylcypromine |
| Opioids and neuromuscular blockers | Morphine, meperidine (pethidine), tramadol; succinylcholine, atracurium |
| Procedures and food | Anesthesia induction, intubation, tumor handling, fine-needle aspiration, labor, tyramine-rich foods |
The labels of metoclopramide and glucagon list pheochromocytoma as a contraindication.
Contrast is a myth; steroids are not. CT contrast was long avoided for fear of a crisis. A small prospective NIH study found no rise in plasma catecholamines after low-osmolar contrast (diastolic pressure did rise) and concluded that contrast-enhanced CT is safe even in patients not taking alpha- or beta-blockers, and Merck states that no adrenoceptor blockade is needed with isotonic contrast agents. Glucocorticoids are a real risk: a 2008 case series described crises after them, one fatal, and warned that steroid premedication for a contrast allergy can also put patients at risk. Crises have followed the high-dose dexamethasone suppression test (2 mg every 6 hours), but the 1-mg overnight test is still considered generally safe; a recent cohort of 106 patients reported the first crisis after it.
Treating a crisis. Use short-acting IV drugs: an alpha-blocker such as phentolamine where available, or nicardipine, clevidipine or nitroprusside. Never give a beta-blocker before alpha blockade, and avoid IV diuretics unless there is heart failure, because these patients are volume-depleted. Once pressure is controlled, switch to an oral alpha-blocker such as doxazosin, adding a beta-blocker for persistent tachycardia. Other IV choices are compared in hypertensive emergency vs urgency, and tricyclic and MAO inhibitor reactions in SSRIs vs SNRIs vs TCAs vs MAOIs.
Hereditary pheochromocytoma: syndromes and genetic testing
| Syndrome | Gene | PPGL pattern | Other clues |
|---|---|---|---|
| MEN2A | RET | Pheochromocytoma in about 50%, often bilateral; secretes epinephrine | Medullary thyroid carcinoma (95%), primary hyperparathyroidism (20–30%) |
| MEN2B | RET | Pheochromocytoma in 50%; about half multiple, often bilateral | Medullary thyroid carcinoma (100%, early childhood), mucosal neuromas, marfanoid habitus, intestinal ganglioneuromatosis |
| Von Hippel–Lindau disease | VHL | Often small, multifocal or bilateral; normetanephrine-predominant; high risk in type 2 | Retinal and CNS hemangioblastomas, clear cell renal cell carcinoma, pancreatic cysts and neuroendocrine tumors |
| Neurofibromatosis type 1 | NF1 | PPGL in fewer than 1% of adults | Café-au-lait macules, axillary freckling, neurofibromas, Lisch nodules |
| Hereditary paraganglioma–pheochromocytoma syndromes | SDHB, SDHD, SDHC, SDHA, SDHAF2, MAX, TMEM127 | SDHB: extra-adrenal sympathetic paragangliomas, metastatic in 24–58%; SDHD: mainly skull base and neck, multifocal in 75% | Gastrointestinal stromal tumors; renal cell carcinoma |
- Inheritance: all are autosomal dominant, but SDHD and SDHAF2 (and possibly MAX) cause disease almost only when inherited from the father, so a negative family history does not exclude them.
- Biochemical clue: MEN2 tumors make epinephrine (metanephrine rises); VHL, SDHB, SDHC and SDHD tumors make mainly norepinephrine (normetanephrine), and SDHx tumors may also make dopamine (methoxytyramine). SDHB is the gene most often found in metastatic PPGL.
- MEN2 surgery order: check metanephrines before any operation; remove a pheochromocytoma, after alpha blockade, before thyroidectomy. See thyroid cancer types and MEN1 vs MEN2A vs MEN2B.
PPGL terminology: metastatic, not malignant
- Pheochromocytoma is the WHO term for an intra-adrenal paraganglioma, the classic sympathetic form. Paragangliomas arise outside the adrenal and are sympathetic (abdomen, pelvis, chest; usually secreting) or parasympathetic (skull base and neck, along the glossopharyngeal and vagal nerves; usually nonsecreting).
- All PPGLs arise from neural crest tissue. Histology shows nests ("zellballen") of cells positive for chromogranin and synaptophysin, with S100-positive sustentacular cells.
- No more "benign" or "malignant." Since the WHO's 4th edition, and again in the 2022 5th edition, PPGLs are not classified as benign or malignant, because any of them can metastasize and no features reliably predict which will. Metastasis means tumor in tissue that normally lacks chromaffin cells, such as lymph nodes or bone; the WHO neither endorses nor discourages histologic risk scores.
- Lifelong follow-up: 6.5–16.5% of apparently benign tumors recur, usually 5–15 years after surgery.
- Metastatic PPGL: 5-year survival is 50–70%; treatments include surgery, chemotherapy, ¹³¹I-MIBG, peptide receptor radionuclide therapy and belzutifan, an oral hypoxia-inducible factor inhibitor approved by the FDA in May 2025.
USMLE traps: classic teaching vs current evidence
| Trap | What's actually true |
|---|---|
| Start a beta-blocker or labetalol for the tachycardia | Alpha-blocker first; beta-blocker only after alpha blockade |
| Order a CT first | Metanephrines first; image only after biochemical confirmation |
| Biopsy the adrenal mass | Exclude pheochromocytoma before any adrenal biopsy |
| Screen with urine VMA or a glucagon stimulation test | Plasma free or urine fractionated metanephrines; VMA is rarely used and provocative tests are dangerous |
| Mildly raised normetanephrine on a tricyclic means a tumor | Likely false positive; repeat off the drug or do a clonidine suppression test |
| Give metoclopramide for nausea | Contraindicated |
| Alpha-block before contrast CT | Not needed |
| MEN2 with medullary thyroid cancer: thyroidectomy first | Exclude or remove pheochromocytoma first |
| 10% are hereditary | About 35–40%; offer genetic testing to all |
More endocrine walkthroughs are on the Endocrinology hub.
Worked vignettes
Vignette 1: the spell. A 34-year-old woman has had episodes of pounding headache, palpitations, sweating and pallor several times a week, each lasting about 15 minutes. During one in clinic, her blood pressure is 210/120 mm Hg and heart rate 128/min; between episodes it is 136/86 mm Hg. She takes no medications. What is the best initial test?
Answer: Plasma free metanephrines drawn supine, or 24-hour urine fractionated metanephrines.
Reasoning: The 5 P's raise suspicion; biochemistry confirms. CT first is the wrong order, urine VMA is outdated, a beta-blocker could provoke a crisis, and "panic attacks" would miss the tumor.
Vignette 2: the beta-blocker. A 45-year-old man in the emergency department with palpitations, blood pressure 188/110 mm Hg and heart rate 132/min is given IV metoprolol. Ten minutes later his blood pressure is 250/140 mm Hg and he has chest pain. A 5-cm pheochromocytoma is found later. What caused the rise, and what is the best treatment now?
Answer: Unopposed α1 vasoconstriction; give IV phentolamine, or nicardipine or nitroprusside.
Reasoning: Metoprolol is β1-selective, but selectivity fades at higher doses, and its label warns of this paradoxical rise: blunting beta-mediated vasodilation in skeletal muscle left α1 vasoconstriction unopposed. More beta-blocker, including IV labetalol, would not help.
Vignette 3: getting ready for surgery. A 39-year-old man with hypertension resistant to three drugs has plasma normetanephrine 6 times the upper limit, and CT shows a 4-cm right adrenal mass. Adrenalectomy is planned. What is the next step, and what should the team watch for after removal?
Answer: An alpha-blocker (phenoxybenzamine or doxazosin) for 7–14 days with a high-sodium diet and fluids, adding a beta-blocker only after alpha blockade if he is tachycardic; afterward, watch for hypotension and hypoglycemia.
Reasoning: Salt and fluids prevent post-resection hypotension, and the fall in catecholamines lets insulin rebound. Offer genetic testing too.
Vignette 4: MEN2A. A 31-year-old woman has a thyroid nodule; fine-needle aspiration shows medullary thyroid carcinoma, and her serum calcium is mildly raised. Her father died of a hypertensive crisis during surgery. What must be done before thyroidectomy, and which gene is involved?
Answer: Measure metanephrines and, if a pheochromocytoma is found, remove it after alpha blockade before the thyroidectomy; RET (MEN2A).
Reasoning: Medullary thyroid carcinoma, hyperparathyroidism and a family history of an anesthesia-induced crisis point to MEN2A, in which about half of patients develop pheochromocytoma. Her first-degree relatives should be offered RET testing.
Key takeaways
- 5 P's: pressure, pain (headache), perspiration, palpitations, pallor; headache, sweating and palpitations are the classic triad. A memory aid, not a diagnostic rule.
- Investigation: plasma free (supine) or 24-hour urine fractionated metanephrines first; image only after biochemical confirmation.
- Alpha before beta: alpha-blocker for 7–14 days with salt and fluids; beta-blocker only afterward; labetalol is not a substitute.
- Crisis triggers: unopposed beta-blockade, metoclopramide, glucocorticoids, glucagon, sympathomimetics, tricyclics, MAO inhibitors, opioids, anesthesia, biopsy; low-osmolar IV contrast is safe.
- Rule of 10s is outdated: about 35–40% are hereditary (MEN2, VHL, NF1, SDHx); offer genetic testing to all. The WHO no longer classifies any PPGL as benign or malignant, so follow-up is lifelong.
Sources
- Lenders JWM, et al. Pheochromocytoma and Paraganglioma: An Endocrine Society Clinical Practice Guideline — J Clin Endocrinol Metab (2014)
- Pheochromocytoma and Paraganglioma Treatment (PDQ), Health Professional Version — National Cancer Institute (2024)
- Pheochromocytoma — StatPearls, NCBI Bookshelf (2024)
- Perioperative Management of Pheochromocytoma — StatPearls, NCBI Bookshelf (2023)
- Pheochromocytoma and Paraganglioma — Endotext, NCBI Bookshelf (2025)
- Pheochromocytoma — Merck Manual Professional Edition (2026)
- Hereditary Paraganglioma-Pheochromocytoma Syndromes — GeneReviews, NCBI Bookshelf (2023)
- Multiple Endocrine Neoplasia Type 2 — GeneReviews, NCBI Bookshelf (2023)
- Von Hippel-Lindau Syndrome — GeneReviews, NCBI Bookshelf (2025)
- Neurofibromatosis 1 — GeneReviews, NCBI Bookshelf (2025)
- Mete O, et al. Overview of the 2022 WHO Classification of Paragangliomas and Pheochromocytomas — Endocr Pathol (2022)
- Fassnacht M, et al. European Society of Endocrinology Clinical Practice Guidelines on the Management of Adrenal Incidentalomas — Eur J Endocrinol (2023)
- Geroula A, et al. Pheochromocytoma and Paraganglioma: Clinical Feature-Based Disease Probability — Eur J Endocrinol (2019)
- Baid SK, et al. Radiographic Contrast Infusion and Catecholamine Release in Patients With Pheochromocytoma — Ann Intern Med (2009)
- Rosas AL, et al. Pheochromocytoma Crisis Induced by Glucocorticoids — Eur J Endocrinol (2008)
- Zawadzka K, et al. The Role of Cortisol Secretion in Pheochromocytomas and Paragangliomas — J Clin Endocrinol Metab (2026)
- Sarathi V. Characteristics of Pediatric Pheochromocytoma/Paraganglioma — Indian J Endocrinol Metab (2017)
- Park H, et al. Clinical Presentation and Treatment Outcomes of Children and Adolescents With Pheochromocytoma and Paraganglioma — Front Endocrinol (2020)
- Reglan (Metoclopramide) Tablets Label — DailyMed, NLM (2026)
- Glucagon for Injection Label — DailyMed, NLM (2026)
- Metoprolol Tartrate Tablets Label — DailyMed, NLM (2026)
- Phenoxybenzamine Hydrochloride Capsules Label — DailyMed, NLM (2026)
- FDA Approves Belzutifan for Pheochromocytoma or Paraganglioma — U.S. Food and Drug Administration (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
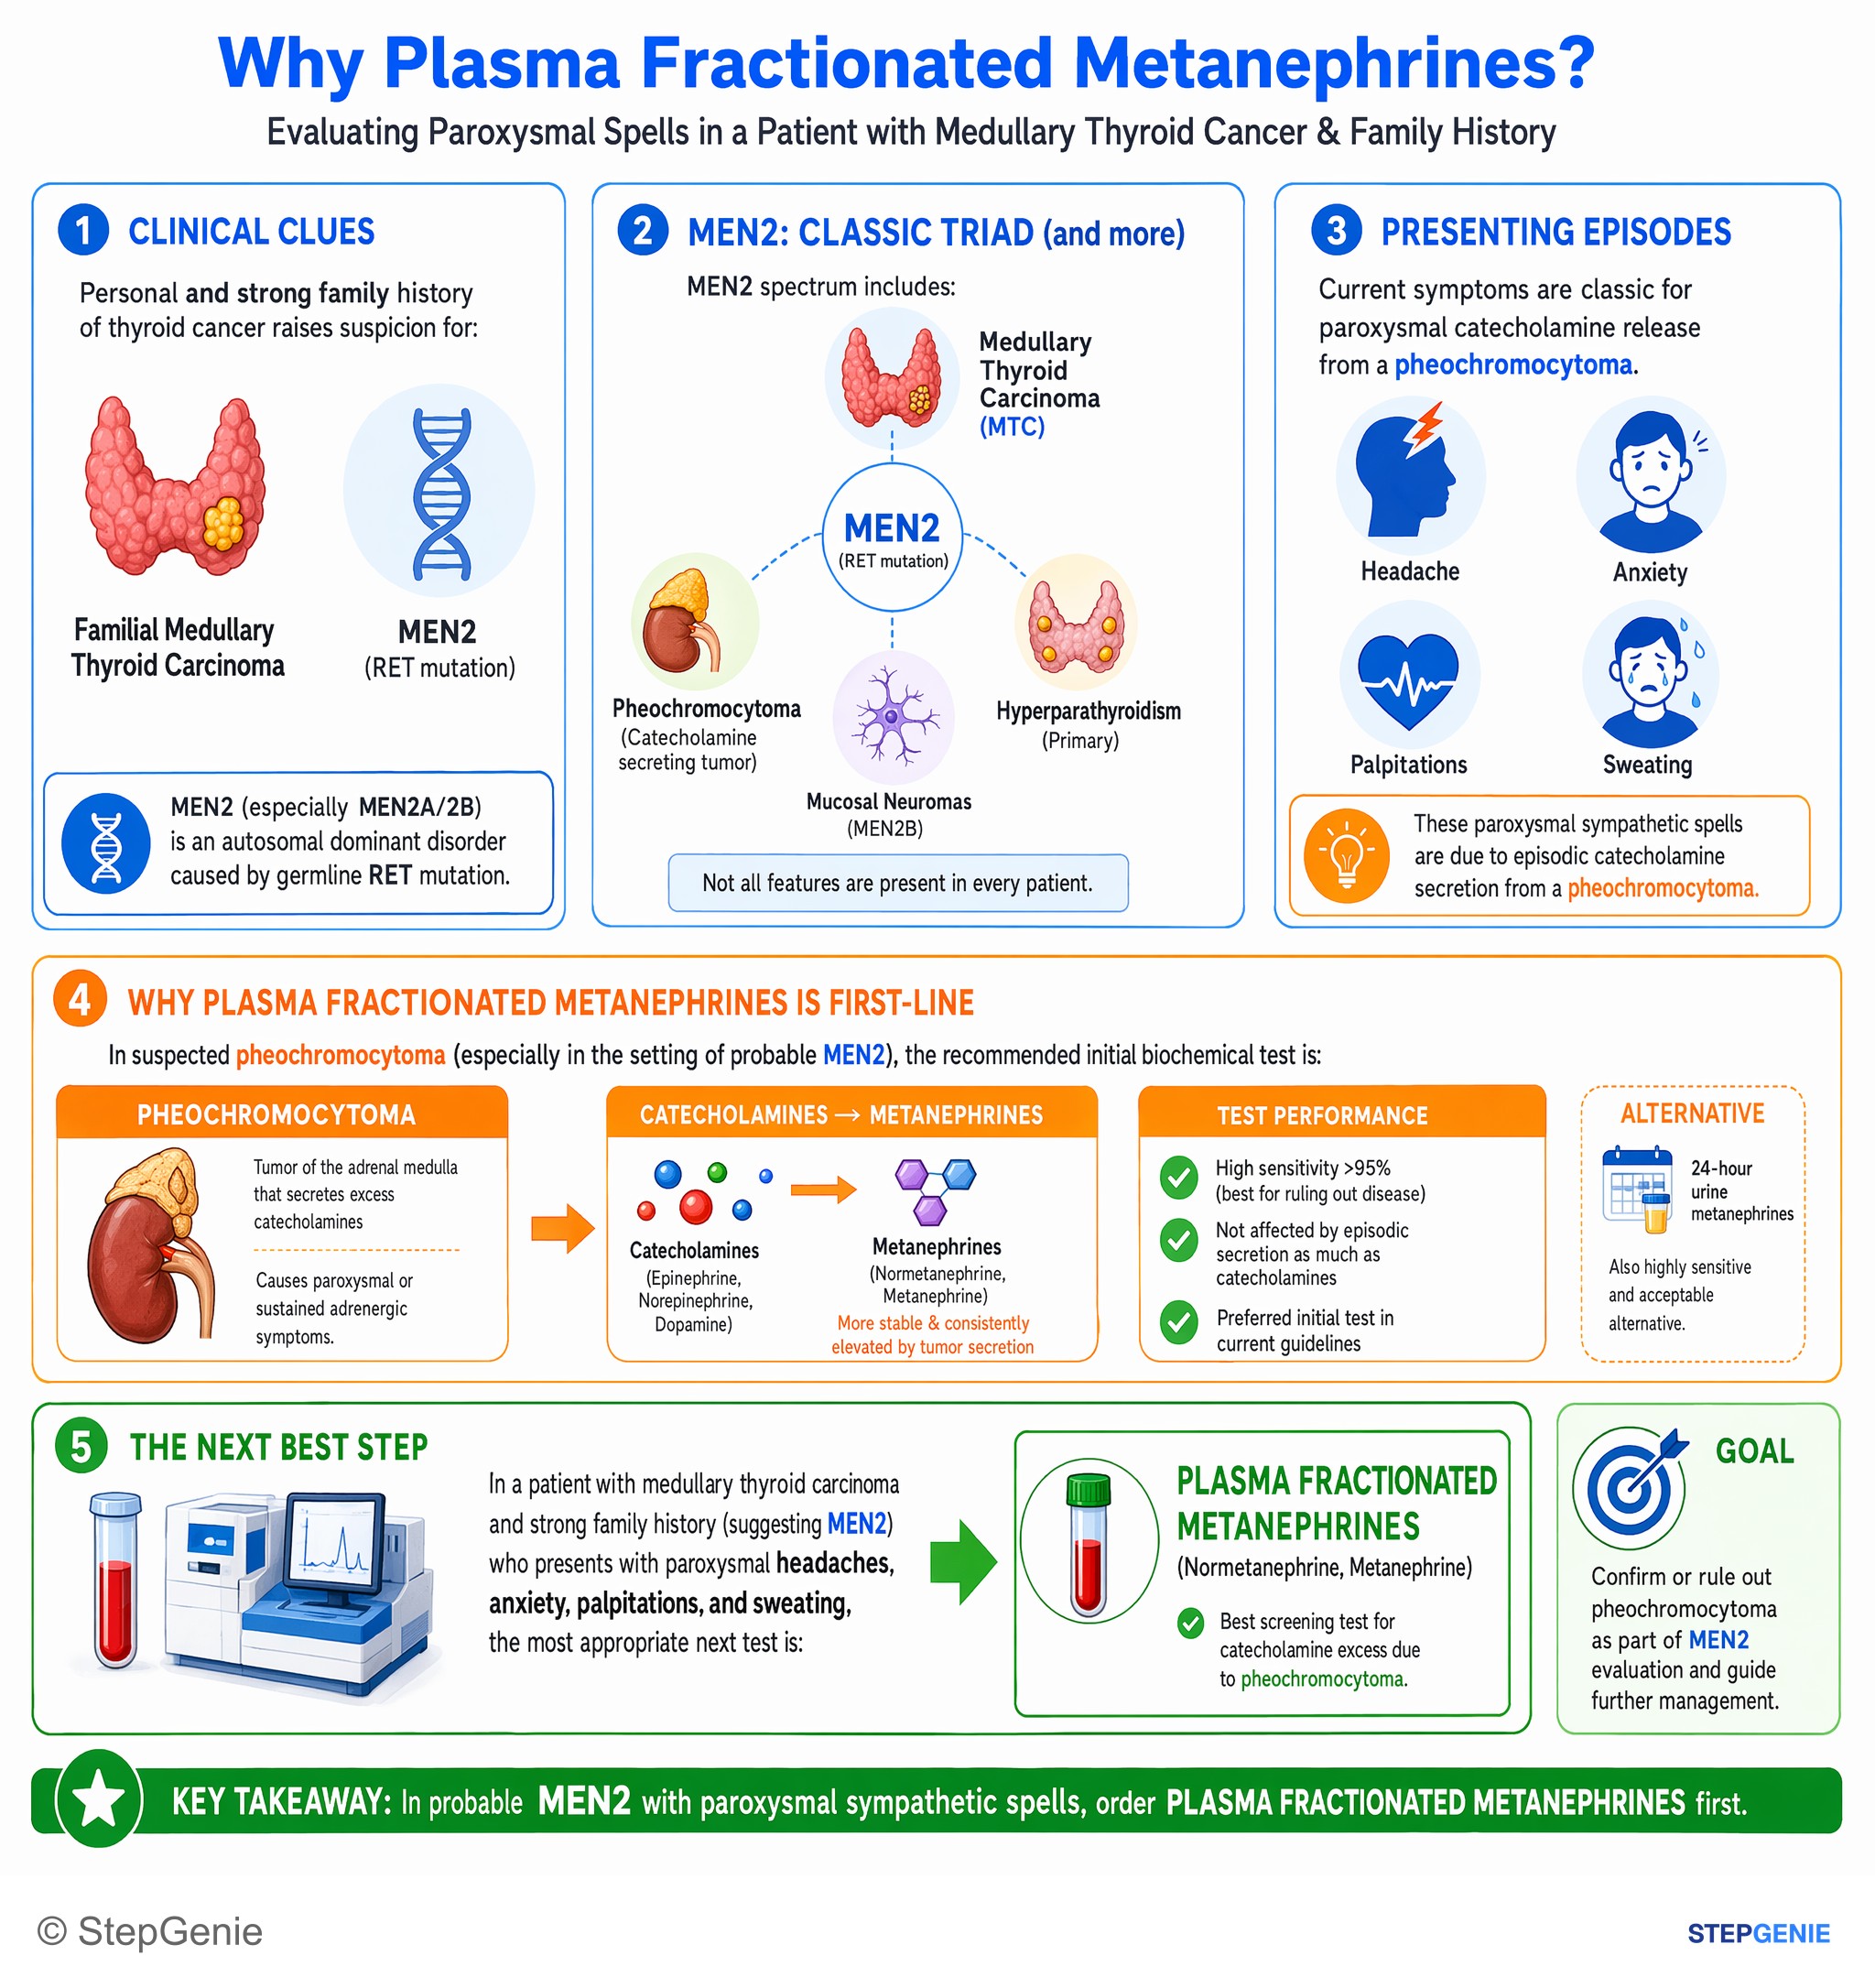
Pheochromocytoma in probable MEN2 (medullary thyroid carcinoma + family history) → screen with plasma fractionated metanephrines for…
USMLE Step 2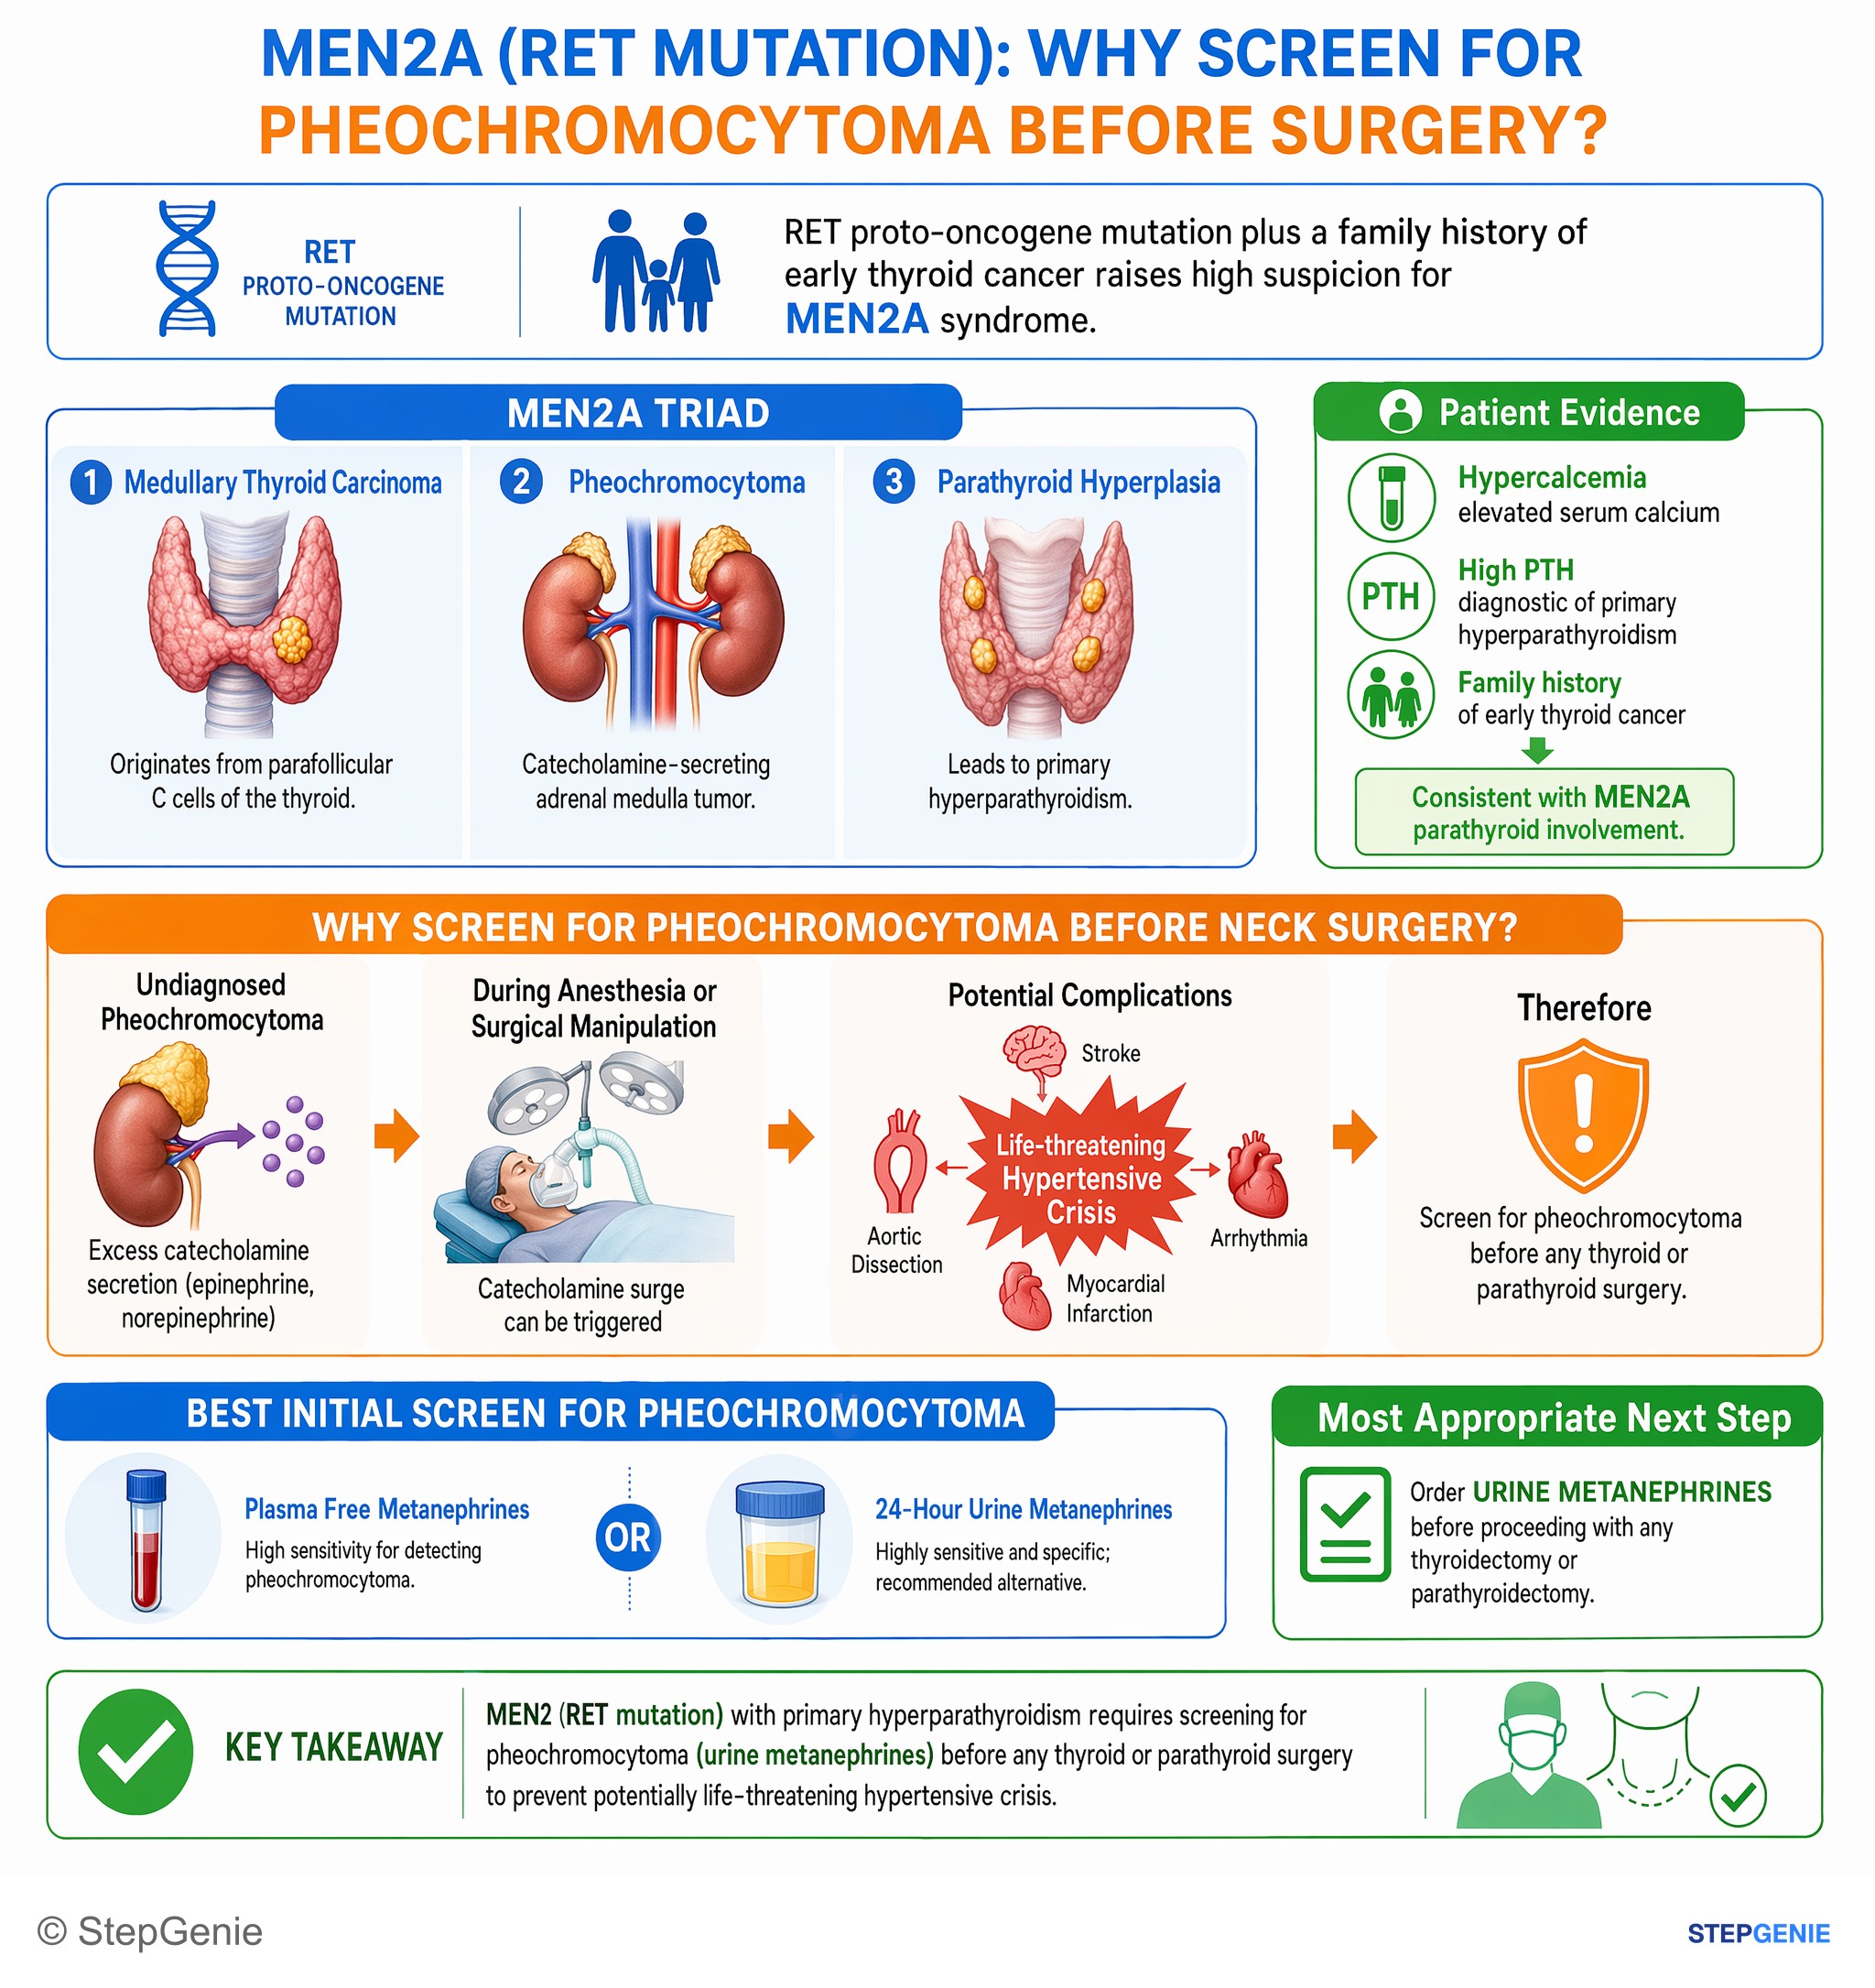
MEN2 (RET mutation) with primary hyperparathyroidism requires screening for pheochromocytoma (urine metanephrines) before any thyroid or…
USMLE Step 2Frequently Asked Questions
What are the 5 P's of pheochromocytoma?
The 5 P's are pressure (hypertension, sustained or in paroxysms), pain (headache), perspiration, palpitations and pallor. Headache, sweating and palpitations form the classic triad. The mnemonic is a memory aid, not a diagnostic rule: about half of pheochromocytomas are now found before they cause symptoms, and headache differs little between people tested who have the tumor and those who do not. The diagnosis is usually confirmed by raised plasma free or urine fractionated metanephrines.
What is the classic triad of pheochromocytoma?
The classic triad is episodic headache, sweating and palpitations (tachycardia), usually in a patient with hypertension. Spells may come several times a day or only every few months, and most last less than an hour. The triad should prompt testing with plasma free or 24-hour urine fractionated metanephrines, but it cannot confirm the diagnosis, because anxiety disorders, hyperthyroidism and drug-induced hypertension can look similar.
Is an alpha blocker or a beta blocker given first in pheochromocytoma, and why?
The alpha blocker comes first. Phenoxybenzamine or a selective alpha-1 blocker such as doxazosin is started 7 to 14 days before surgery, with a high-sodium diet and fluids. A beta blocker is added only after alpha blockade, usually at least 3 to 4 days later, to control tachycardia. Given first, a beta blocker removes beta-2-mediated vasodilation and leaves alpha-1 vasoconstriction unopposed, which can cause a hypertensive crisis.
What is the first investigation for suspected pheochromocytoma?
Measure plasma free metanephrines, drawn after the patient has been supine for at least 30 minutes, or 24-hour urine fractionated metanephrines. Tumors convert catecholamines to metanephrines continuously, so levels stay raised between spells. A rise of 3 times the upper limit or more is rarely a false positive; smaller rises need repeat testing off interfering drugs such as tricyclic antidepressants, or a clonidine suppression test. Imaging, usually CT, comes only after biochemical confirmation.
Is the rule of 10s for pheochromocytoma still true?
Mostly not. About 35 to 40% of pheochromocytomas and paragangliomas are hereditary, not 10%, and 15 to 20% are extra-adrenal paragangliomas. About 10 to 17% metastasize, but the WHO no longer labels any of these tumors benign or malignant, because any of them can spread. The share in children, about 9%, still roughly fits. Because so many cases are hereditary, every patient should be offered genetic testing.
Which genetic syndromes cause pheochromocytoma?
The main ones are MEN2A and MEN2B (RET), von Hippel-Lindau disease (VHL), neurofibromatosis type 1 (NF1) and the hereditary paraganglioma-pheochromocytoma syndromes (SDHB, SDHD, SDHC, SDHA, SDHAF2, MAX and TMEM127). All are autosomal dominant, though SDHD and SDHAF2 cause disease almost only when inherited from the father. About half of people with MEN2 develop pheochromocytoma, and SDHB is the gene most often found in metastatic disease.