Dressler syndrome is one of those “post-MI complications” that shows up when you’ve finally moved on mentally from the acute event—then the patient comes back with chest pain and fever. On Step 1, it’s a classic autoimmune pericarditis scenario with a very testable timeline, symptom cluster, and treatment choice that isn’t the same as every other pericarditis vignette.
What is Dressler Syndrome?
Dressler syndrome (also called post–myocardial infarction syndrome) is a delayed, immune-mediated pericarditis that occurs weeks to months after myocardial injury, classically after an MI, but it can also follow:
- Cardiac surgery (postpericardiotomy syndrome)
- Trauma
- Any injury exposing cardiac antigens (e.g., percutaneous cardiac procedures)
High-yield definition:
Autoimmune fibrinous pericarditis occurring weeks to months after MI due to antibodies against exposed cardiac antigens.
Pathophysiology (the “why” that Step questions love)
Core mechanism: immune response to cardiac antigens
- Myocardial necrosis/injury exposes intracellular cardiac antigens
- Immune system forms anti-heart antibodies
- Immune complexes / inflammatory response targets the pericardium and pleura
- Results in fibrinous pericarditis ± pleuritis and effusions
Why the delayed timing matters
Unlike early post-MI pericarditis (within days, due to direct inflammation overlying the infarct), Dressler requires time for an adaptive immune response to develop—hence weeks to months.
Timeline: Dressler vs Early Post-MI Pericarditis (Must-know table)
| Feature | Early post-MI pericarditis | Dressler syndrome |
|---|---|---|
| Timing | 1–3 days after MI | 2–8 weeks (can be months) after MI |
| Mechanism | Direct inflammation over infarct | Autoimmune reaction to cardiac antigens |
| Symptoms | Pleuritic chest pain, rub | Pleuritic chest pain, fever, malaise |
| Associated findings | Usually localized | Pericardial ± pleural effusions, elevated ESR/CRP |
| Treatment (classic) | NSAIDs (careful) | High-dose aspirin (preferred post-MI) ± colchicine |
Exam tip: If the question stem emphasizes fever and weeks after MI, think Dressler.
Clinical Presentation
Symptoms
- Pleuritic chest pain (worse with inspiration, better sitting forward)
- Fever
- Dyspnea (often due to effusion or pain-limited breathing)
- Fatigue/malaise
Physical exam
- Pericardial friction rub (scratchy, best at left lower sternal border)
- Possible signs of effusion:
- Muffled heart sounds (larger effusion)
- Tachycardia
High-yield associations
- Pericarditis + pleuritis (patients may have pleuritic pain and small pleural effusions)
- Elevated inflammatory markers (ESR/CRP)
- Can be associated with pericardial effusion; rarely progresses to tamponade
Diagnosis: What confirms it on exams?
Dressler is largely a clinical diagnosis based on timing + features of pericarditis after myocardial injury.
Typical workup findings
ECG (acute pericarditis pattern)
- Diffuse ST-segment elevations (often concave up)
- PR segment depressions
- (Later) T-wave inversions after ST normalizes
Labs
- ↑ ESR / ↑ CRP
- Troponins: may be mildly elevated in pericarditis/myopericarditis, but in Dressler the key is timing and inflammatory picture rather than a new MI pattern.
Echocardiogram
- May show pericardial effusion
- Important if concern for tamponade physiology
Chest imaging
- Can show pleural effusions (supporting the pleuropericardial inflammation concept)
Differentiate from reinfarction (common trap)
Reinfarction tends to have:
- Localized ST changes in a coronary distribution (or new Q waves)
- Rising troponins/CK-MB in an acute pattern
- Often not diffuse ST elevation + PR depression
Treatment (Step-relevant and very testable)
First-line (post-MI preferred)
- High-dose aspirin
- Preferred because other NSAIDs can impair myocardial healing after MI in some contexts.
- Colchicine (often added to reduce recurrence in pericarditis)
If refractory/contraindicated
- Glucocorticoids (used selectively; can increase recurrence risk in idiopathic pericarditis, but may be needed in severe autoimmune cases)
If complications
- Pericardiocentesis if cardiac tamponade develops
High-Yield Complications & “Red Flags”
Pericardial effusion → tamponade (rare but critical)
Know tamponade findings:
- Hypotension
- JVD
- Muffled heart sounds (Beck triad)
- Pulsus paradoxus
- Echo: diastolic collapse of right atrium/ventricle
Constrictive pericarditis (less common here)
Chronic inflammation can lead to pericardial scarring/calcification. Classic findings include:
- Kussmaul sign
- Pericardial knock
- JVP elevation
USMLE “Buzzwords” and Classic Vignettes
Vignette pattern 1
6 weeks after an MI, patient returns with fever, pleuritic chest pain, and a pericardial friction rub. ECG shows diffuse ST elevations.
Answer: Dressler syndrome (autoimmune pericarditis)
Vignette pattern 2 (trap)
2 days after MI, pleuritic pain and rub.
Answer: Early post-MI pericarditis (direct inflammation), not Dressler.
Vignette pattern 3
Post–cardiac surgery patient weeks later with fever, pericarditis symptoms, and effusions.
Answer: Postpericardiotomy syndrome (same autoimmune concept as Dressler)
First Aid Cross-References (where this lives in your memory palace)
Use these as “anchors” in First Aid for the USMLE Step 1 (exact page numbers vary by edition):
- Cardiovascular → Pericardial disease
- Acute pericarditis ECG findings: diffuse ST elevation + PR depression
- Cardiovascular → Ischemic heart disease / MI complications
- Dressler syndrome as a late post-MI complication
- Inflammation/Immunology tie-in
- Type II/III immune-mediated injury concept (antibodies/immune complexes against self-antigens after tissue injury)
Memory hook:
Days = direct irritation (early post-MI pericarditis)
Weeks = antibodies (Dressler)
Quick High-Yield Summary (what to recall in 10 seconds)
- Dressler syndrome = autoimmune fibrinous pericarditis weeks to months after MI
- Symptoms: fever + pleuritic chest pain + friction rub
- ECG: diffuse ST elevation + PR depression
- Labs: ↑ ESR/CRP
- Tx: high-dose aspirin (post-MI preferred) ± colchicine
- Key differentiation: timing (weeks) and diffuse ECG changes vs reinfarction
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
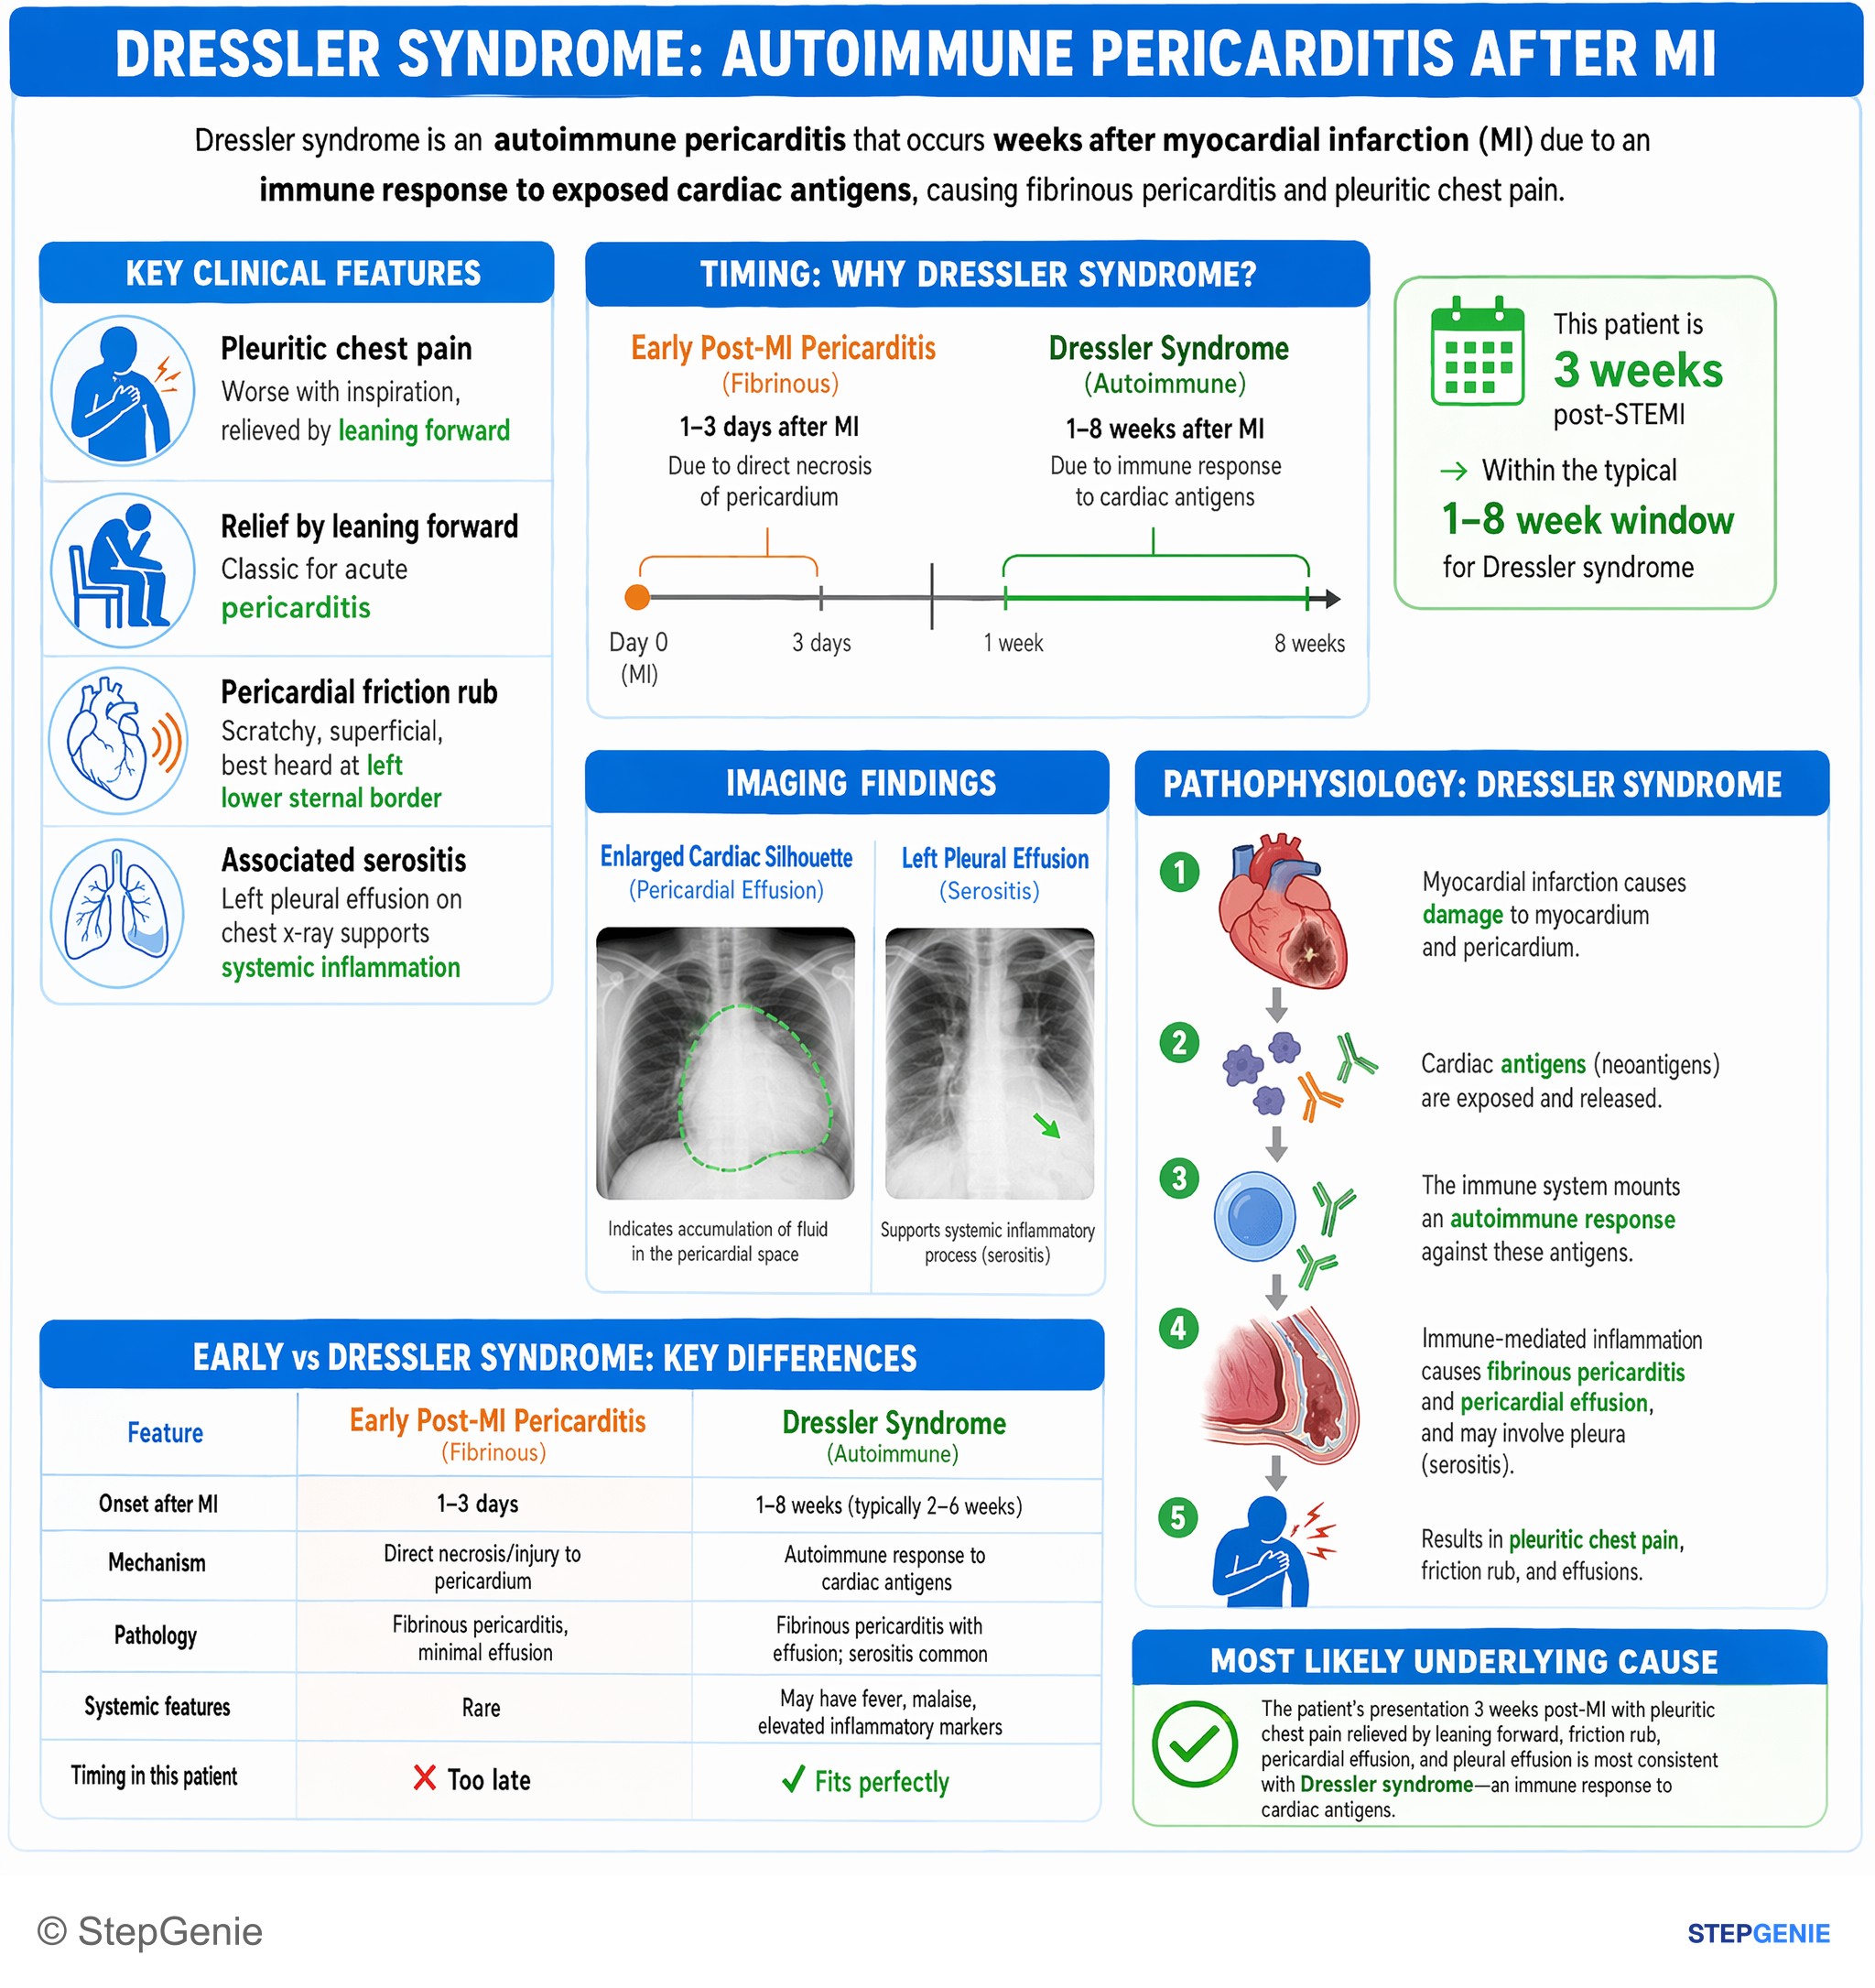
Dressler syndrome: autoimmune pericarditis weeks after MI due to immune response to exposed cardiac antigens causing fibrinous…
USMLE Step 1Frequently Asked Questions
Why does Dressler syndrome happen weeks after an MI instead of right away?
Dressler syndrome happens weeks to months after myocardial injury because it is an autoimmune fibrinous pericarditis that requires time for an adaptive immune response to form. Myocardial necrosis exposes cardiac antigens, the immune system generates anti-heart antibodies, and the resulting inflammatory response targets the pericardium and sometimes the pleura. That delayed immune process explains why it appears later than early post-MI pericarditis.
How do you tell Dressler syndrome from early post-MI pericarditis on an exam?
The key distinction is timing and mechanism. Dressler syndrome occurs about 2 to 8 weeks, or even months, after MI and is autoimmune, whereas early post-MI pericarditis appears within 1 to 3 days from direct inflammation over the infarct. Dressler also classically includes fever, malaise, and possible pericardial or pleural effusions, making "fever weeks after MI" a strong clue.
How do you differentiate Dressler syndrome from reinfarction?
Dressler syndrome is suggested by a post-MI patient with pericarditis features such as pleuritic chest pain, fever, diffuse ST-segment elevations, and PR depressions, often with elevated ESR or CRP and possible effusions. Reinfarction instead tends to show localized ST changes in a coronary distribution or new Q waves, along with rising troponins or CK-MB in an acute pattern rather than a primarily inflammatory picture.
What is the first-line treatment for Dressler syndrome after an MI?
High-dose aspirin is the preferred first-line treatment for Dressler syndrome after MI, and colchicine is often added to reduce recurrence. Aspirin is favored because other NSAIDs can impair myocardial healing after MI in some contexts. If the condition is refractory or aspirin is contraindicated, glucocorticoids may be used selectively, and pericardiocentesis is needed if tamponade develops.
What clinical clues should make you think of Dressler syndrome?
Think of Dressler syndrome when a patient returns weeks after myocardial injury with pleuritic chest pain, fever, dyspnea, fatigue, and a pericardial friction rub. The chest pain is worse with inspiration and better when sitting forward. Supporting findings include diffuse ST elevations with PR depressions on ECG, elevated ESR or CRP, and possible pericardial or pleural effusions.