HFrEF is FAT failure, a dilated ventricle that can't pump (EF 40% or less, S3), and its four mortality-lowering pillars spell ABMS: ARNI/ACE inhibitor/ARB, Beta-blocker, MRA and SGLT2 inhibitor. HFpEF is THICK failure, a stiff ventricle that can't fill (EF 50% or more, S4): diuretics and SGLT2 inhibitors help, but no drug clearly lowers mortality.
Every mnemonic here is a memory aid, not a guideline term: the US guideline calls the four classes guideline-directed medical therapy (GDMT) and never uses "four pillars" or "fantastic four." The full comparison, with trial numbers, is in HFrEF vs HFpEF: differences, drugs and mortality.
Numbers follow the 2022 AHA/ACC/HFSA guideline, still the current US guideline (its successor is scheduled for the third quarter of 2027); newer documents that differ are flagged.
The FAT vs THICK mnemonic: HFrEF vs HFpEF
- HFrEF = FAT failure: "can't pump." A big, baggy chamber whose wall is thin for its size. Myocyte loss and volume load drive eccentric remodeling (sarcomeres added in series), so end-diastolic volume climbs and EF falls. Blood rushing into that dilated, overfilled ventricle in early diastole gives an S3.
- HFpEF = THICK failure: "can't fill." A thick wall around a small or normal cavity. Pressure overload drives concentric hypertrophy (sarcomeres added in parallel) and stiffness, so filling pressure rises even though the ventricle still ejects a normal fraction of what it holds. The atrium kicking blood into that stiff ventricle at the end of diastole gives an S4.
Spell it out (memory aid): F-A-T is Fraction 40% or less, Apex displaced laterally, Third heart sound. T-H-I-C-K is Tension (hypertension), Hypertrophy (concentric), Impaired relaxation, Contraction that looks normal (EF 50% or more) and atrial Kick (the S4).
FAT describes the ventricle, not the patient. Obesity is a major risk factor for HFpEF, the THICK side. And THICK is the classic picture, not a requirement: many patients with HFpEF have normal ventricular structure, so the diagnosis rests on a preserved EF plus evidence of raised filling pressure.
| Feature | HFrEF ("FAT") | HFpEF ("THICK") |
|---|---|---|
| Ejection fraction | 40% or less | 50% or more, with evidence of raised LV filling pressure |
| LV shape | Dilated; eccentric remodeling | Normal or small cavity; classically concentric LVH |
| End-diastolic volume | Increased | Normal or decreased |
| Exam clue | S3; laterally displaced point of maximal impulse | S4 (lost in atrial fibrillation) |
| Typical patient | Coronary artery disease or prior MI; dilated cardiomyopathy | Older woman with hypertension, obesity, diabetes, atrial fibrillation or CKD |
| Natriuretic peptides | Elevated | Usually elevated, but a normal level doesn't exclude it; lower with obesity |
| Drugs that lower mortality | ARNI/ACE inhibitor/ARB, beta-blocker, MRA, SGLT2 inhibitor | None proven |
Dyspnea, orthopnea, edema and raised jugular venous pressure occur in both, so the echocardiogram, not the history, sorts them (see the systolic vs diastolic heart failure Q-bank breakdown).
The 4 pillars of heart failure (GDMT) mnemonic: ABMS
The FAT heart needs its ABMS (memory aid; say "abs"): each letter is a class 1 recommendation in the 2022 guideline to reduce death and hospitalization in symptomatic HFrEF.
| Letter | What it encodes | The rule behind it |
|---|---|---|
| A | ARNI (sacubitril/valsartan), or an ACE inhibitor, or an ARB | ARNI for NYHA class II–III; ACE inhibitor if an ARNI isn't feasible; ARB after ACE inhibitor cough or angioedema. ARNI at least 36 hours after the last ACE inhibitor dose; no ARNI or ACE inhibitor after any angioedema |
| B | Beta-blocker, one of the 3 proven ones | Bisoprolol, carvedilol or metoprolol succinate; start once compensated |
| M | Mineralocorticoid receptor antagonist | Spironolactone or eplerenone, NYHA class II–IV, if eGFR is above 30 and potassium below 5.0 mEq/L |
| S | SGLT2 inhibitor | Dapagliflozin or empagliflozin, with or without diabetes |
What ABMS doesn't tell you:
- An order. There isn't one: all four may start together at low doses, and the 2024 ACC expert consensus pathway says low doses of all four likely beat one or two at maximal doses, with titration to maximally tolerated doses within 3 months when feasible.
- Who qualifies. Current or previous symptoms. In stage B (EF 40% or less, never symptomatic), an ACE inhibitor and a beta-blocker are recommended to prevent symptoms.
- The other lifesavers: hydralazine-nitrate, ICDs and CRT (below).
"Fantastic four" is the title of a 2021 European Heart Journal editorial; the 2026 ESC guideline calls them "foundational medical therapy." Details: ACE inhibitors vs ARBs (A), potassium-sparing diuretics (M).
S3 vs S4 mnemonic
Two memory aids:
- Cadence: an S3 gallop sounds like "Ken-tuc-ky" (S1, S2, S3); an S4 gallop sounds like "Ten-nes-see" (S4, S1, S2).
- S3 = Slosh, S4 = Stiff: blood sloshing into a dilated ventricle early in diastole, vs the atrium pushing into a stiff one at the end of diastole.
| Feature | S3 | S4 |
|---|---|---|
| Timing | Early diastole, after S2, during passive filling | Late diastole, just before S1, during atrial contraction |
| Mechanism | Filling of a dilated, volume-overloaded ventricle | Atrial contraction against a stiff, less compliant ventricle |
| Usual setting | Systolic dysfunction (HFrEF), volume overload | LVH from hypertension or aortic stenosis, HFpEF, active ischemia or a recent MI |
| Can it be normal? | Yes: children, young adults up to about age 40, pregnancy, some athletes | Usually not; Merck calls it always abnormal |
| Atrial fibrillation | Still possible (passive filling) | Absent: no atrial kick |
Both are low-pitched and best heard with the bell; a left-sided S3 is loudest at the apex, patient in left lateral decubitus. An S3, with or without an S4, is usual in significant systolic dysfunction; an S4 alone, in diastolic dysfunction. The Wiggers diagram cheat sheet places both on the cardiac cycle.
NYHA classification mnemonic, and the ACC/AHA stages
NYHA class grades today's symptoms in stage C or D and can improve with treatment; the ACC/AHA stage tracks disease progression and does not go back.
Memory aid: N-Y-H-A spells the four classes in order.
| Class | Memory aid | 2022 guideline wording |
|---|---|---|
| I | No limitation | No limitation of physical activity from heart failure |
| II | Your ordinary day brings symptoms | Comfortable at rest; slight symptoms with ordinary activity |
| III | Hardly any activity tolerated | Comfortable at rest; symptoms with less than ordinary activity |
| IV | At rest | Unable to do any physical activity without symptoms; symptoms at rest |
Two cut points do the work: ordinary vs less-than-ordinary activity (II vs III), and comfortable at rest or not (III vs IV).
Memory aid: A-B-C-D is At risk, Before symptoms, Current or prior symptoms, Despite treatment.
| Stage | 2022 definition |
|---|---|
| A: at risk | Risk factors (hypertension, diabetes, obesity, cardiotoxins) without symptoms, structural disease or abnormal biomarkers |
| B: pre-HF | No symptoms ever, but structural disease, raised filling pressures, or raised natriuretic peptide or troponin |
| C: symptomatic HF | Structural heart disease with current or previous symptoms |
| D: advanced HF | Marked symptoms and recurrent hospitalizations despite optimized GDMT |
The trap: a stage C patient whose symptoms resolve is NYHA class I but still stage C (HF in remission only if every symptom, sign and structural abnormality resolves). The 2026 ESC guideline adopted the same stages.
I NEED HELP: the advanced heart failure mnemonic
I NEED HELP flags advanced (stage D) heart failure: time to refer to an advanced heart failure team to assess a left ventricular assist device (LVAD), transplant or palliative care. The 2022 guideline prints the list (from a 2017 transplant-journal article) as a referral prompt, not diagnostic criteria.
| Letter | Trigger (2022 guideline list) |
|---|---|
| I | Intravenous inotropes |
| N | NYHA class IIIB–IV, or persistently elevated natriuretic peptides |
| E | End-organ dysfunction |
| E | EF 35% or less |
| D | Defibrillator shocks |
| H | Hospitalizations, more than 1 |
| E | Edema despite escalating diuretics |
| L | Low systolic blood pressure (90 mm Hg or less), high heart rate |
| P | Prognostic medication: progressive intolerance or down-titration of GDMT |
Refer early. Timely referral is a class 1 recommendation and needs no complete workup first; after end-organ dysfunction or cardiogenic shock, patients may no longer qualify for advanced therapies. Losing pillars to hypotension or worsening renal function is itself a red flag.
Causes: what makes a heart FAT or THICK (and cardiomegaly causes)
FAT (HFrEF) is most often caused by coronary artery disease, usually after an MI; the other big bucket is dilated cardiomyopathy, most often idiopathic. Memory aid for other causes of a big, dilated heart: ABCCCD. Alcohol; Beriberi (wet, from thiamine deficiency); Coxsackie B myocarditis (the classic answer, though recent series implicate parvovirus B19 and HHV-6 most often); Cocaine; Chagas disease; Doxorubicin and other anthracyclines. Add HIV, peripartum and genetic cardiomyopathy, tachycardia-induced cardiomyopathy, hemochromatosis and sarcoidosis (this dilated cardiomyopathy visual sorts them). Chronic aortic or mitral regurgitation remodels the ventricle eccentrically.
Cardiomegaly on a chest x-ray is a cardiothoracic ratio of 50% or more on a PA film. Look-alikes include pericardial effusion, an anterior mediastinal mass, an epicardial fat pad and an AP or expiratory film.
THICK (HFpEF) makes up about half of heart failure. Hypertension and aortic stenosis thicken the ventricle by pressure overload (hear aortic stenosis in the heart murmur table); look for aortic stenosis in every suspected case, and exclude the mimics: amyloidosis and other restrictive cardiomyopathies, hypertrophic cardiomyopathy and constrictive pericarditis.
EF categories: HFrEF, HFmrEF, HFpEF and HFimpEF
Memory aid: grade the EF like an exam. 40 or below fails (reduced), 50 or above passes (preserved), 41–49 is borderline (mildly reduced), and a fail that climbs above 40 is "improved" but keeps studying: every drug stays.
| Category | LVEF (2022 US guideline) | Key rule |
|---|---|---|
| HFrEF | 40% or less | All four ABMS classes |
| HFmrEF (mildly reduced) | 41–49% | Needs evidence of raised LV filling pressure |
| HFpEF | 50% or more | Needs evidence of raised LV filling pressure |
| HFimpEF (improved) | Previously 40% or less, now above 40% | Keep all HFrEF drugs (class 1) |
- Improved is not cured. HFimpEF stays a subgroup of HFrEF even if the EF passes 50%. In TRED-HF, withdrawing therapy after recovery from dilated cardiomyopathy led to relapse in 44% within 6 months.
- What changed in 2026. The ESC guideline dropped HFmrEF and calls an LVEF below 50% HFrEF, since those patients "share similar pathophysiology and benefit from similar treatments"; an EF of 45% is HFmrEF in the US but HFrEF under ESC 2026. A 2026 universal definition (AHA, ACC, ESC, World Heart Federation) also moves away from fixed cut-offs, but it sets terminology, not treatment.
Drugs that lower mortality vs drugs that only ease symptoms
Memory aid: ABMS plus H save lives; the two D's don't. H is hydralazine plus isosorbide dinitrate in the right patient; the D's are diuretics and digoxin.
| Drug or device | Mortality in HFrEF | Where it fits |
|---|---|---|
| ABMS | Lower | Every symptomatic patient |
| Hydralazine plus isosorbide dinitrate | Lower in self-identified African American patients | NYHA class III–IV on optimal therapy (class 1) |
| ICD | Lower | EF 35% or less, NYHA class II–III on GDMT (40 or more days after an MI) |
| CRT | Lower | EF 35% or less, sinus rhythm, LBBB with QRS 150 ms or more |
| Loop diuretic | Uncertain | Relieves congestion; never used alone |
| Digoxin | No effect | Fewer HF hospitalizations (2b) |
| Ivabradine | Composite lowered, mainly via fewer admissions | EF 35% or less, sinus rate 70/min or more on a maximally tolerated beta-blocker (2a) |
| Vericiguat | Composite lowered; all-cause death unchanged | Recent worsening despite GDMT (2b) |
Drugs that worsen HFrEF (class 3, harm): verapamil and diltiazem, class IC antiarrhythmics such as flecainide, dronedarone, thiazolidinediones such as pioglitazone, saxagliptin and alogliptin, and NSAIDs. Amlodipine or felodipine can treat blood pressure but not the failure.
What helps in HFpEF: the SODA memory aid
Same letters, different grades (2022 US guideline):
| Pillar | HFrEF | HFmrEF (41–49%) | HFpEF (50% or more) |
|---|---|---|---|
| A: ARNI, ACE inhibitor or ARB | 1 | 2b | ARNI or ARB 2b, mainly at the lower end of the range |
| B: evidence-based beta-blocker | 1 | 2b | No HFpEF recommendation |
| M: MRA | 1 | 2b | 2b, mainly at the lower end of the range |
| S: SGLT2 inhibitor | 1 | 2a | 2a |
Memory aid: the THICK heart gets SODA.
- S, SGLT2 inhibitor. Empagliflozin (EMPEROR-Preserved) and dapagliflozin (DELIVER) cut cardiovascular death or HF events, mainly HF events. The 2023 ESC focused update made them class I in HFmrEF and HFpEF; both are FDA-labeled for heart failure with no EF limit.
- O, obesity therapy. At a BMI of 30 or more, semaglutide (STEP-HFpEF) improved symptoms and walking distance, and tirzepatide (SUMMIT) lowered cardiovascular death or worsening heart failure (hazard ratio 0.62) through fewer HF events. The 2026 ACC pathway recommends incretin therapy at that BMI and ESC 2026 gives it a class IIa, but neither Wegovy nor Zepbound has an FDA heart failure indication.
- D, diuretics. Loop diuretics relieve congestion (class 1); their effect on survival is uncertain.
- A, aldosterone (mineralocorticoid receptor) antagonist. Spironolactone lowered only HF hospitalization in TOPCAT, missing its primary endpoint. Finerenone, a nonsteroidal MRA, cut worsening HF events plus cardiovascular death in FINEARTS-HF, though not cardiovascular death alone (8.1% vs 8.7%), and was FDA-approved in July 2025 for heart failure with an LVEF of 40% or more. The 2026 ACC pathway pairs it with an SGLT2 inhibitor as the base of therapy, ahead of spironolactone; ESC 2026 makes MRAs class I at any EF. Watch potassium.
Also: control blood pressure (class 1) and atrial fibrillation (2a). Sacubitril/valsartan narrowly missed its PARAGON-HF primary endpoint, with possible benefit at lower EF and in women, and the 2026 ACC pathway avoids routine beta-blockers unless needed for angina or rate control.
Why the gap? Neurohormonal activation drives HFrEF remodeling, and three of the four pillars block it; HFpEF is driven by stiffness, hypertension and metabolic disease, and even the new drugs cut events, not deaths. No drug has clearly lowered mortality in HFpEF.
USMLE traps: classic teaching vs current evidence
| Trap | What's actually true |
|---|---|
| Obese patient, so "FAT" failure | Obesity points to HFpEF; FAT describes the ventricle |
| Follow BNP on sacubitril/valsartan | Neprilysin inhibition raises BNP; follow NT-proBNP, which is not a neprilysin substrate |
| "Nothing works in HFpEF" | Outdated: SGLT2 inhibitors, finerenone and, with obesity, incretin drugs cut HF events or improve symptoms; none has clearly lowered mortality |
| Semaglutide or tirzepatide is FDA-approved for HFpEF | Neither has an FDA heart failure indication |
| Coxsackie B is the commonest cause of viral myocarditis | Classic answer; North American and European series now implicate parvovirus B19 and HHV-6 most often |
| Thick walls always mean hypertensive HFpEF | Thick walls with discordantly low QRS voltage, carpal tunnel syndrome or spinal stenosis suggest amyloidosis, where standard HF drugs may be poorly tolerated |
More on BNP and NT-proBNP, on amyloid in restrictive cardiomyopathy, and on the Cardiology hub.
Worked vignettes
Vignette 1: the missing letter. A 63-year-old man with an old anterior MI is dyspneic on stairs, with an S3 and an LVEF of 30%. He takes sacubitril/valsartan, carvedilol, spironolactone and furosemide; pulse is 64/min and regular, potassium 4.4 mEq/L. Which addition most lowers his risk of death? A. Digoxin. B. Diltiazem. C. Dapagliflozin. D. Ivabradine. E. Amlodipine.
Answer: C. A, B and M are in place; S is missing, and an SGLT2 inhibitor is class 1 with or without diabetes. Digoxin (A) cuts admissions, not deaths; diltiazem (B) harms HFrEF; ivabradine (D) needs a resting rate of 70/min or more; amlodipine (E) doesn't treat heart failure.
Vignette 2: the stiff ventricle. A 72-year-old woman with long-standing hypertension and type 2 diabetes has 6 months of exertional dyspnea, orthopnea and ankle edema. Blood pressure is 168/86 mm Hg, with bibasilar crackles, an S4 and an elevated BNP. Echocardiography shows an EF of 60%, concentric LVH, an enlarged left atrium and no significant valve disease. The underlying abnormality? A. Reduced contractility of a dilated ventricle. B. Impaired relaxation of a hypertrophied ventricle. C. Papillary muscle rupture. D. Amyloid infiltration. E. Constrictive pericarditis.
Answer: B. Preserved EF, thick ventricle, big left atrium and an S4 in an older hypertensive woman spell THICK. A gives a low EF; C is abrupt; D adds discordantly low QRS voltage or carpal tunnel syndrome; E gives an early diastolic knock, not an S4.
Vignette 3: better, not cured. A 58-year-old woman had pulmonary edema 2 years ago from dilated cardiomyopathy (LVEF 25%). On all four pillars she is now symptom-free with an LVEF of 52% and asks to stop her medicines. Which is correct? A. Stage B; stop the beta-blocker. B. Stage C, NYHA class I, HFimpEF; continue all four. C. Stage A; stop everything. D. Relabel as HFpEF; diuretic alone. E. Stage D; refer for transplant.
Answer: B. Prior symptoms keep her in stage C at NYHA class I, and an EF rising from 40% or less to above 40% is HFimpEF, which keeps every drug. Stage B (A) means never symptomatic, stage A (C) no structural disease, stage D (E) refractory symptoms; improved HFrEF isn't relabeled HFpEF (D).
Key takeaways
- FAT vs THICK: HFrEF is EF 40% or less, dilated, S3; HFpEF is EF 50% or more plus raised filling pressure, stiff, S4 (never in atrial fibrillation). The echo sorts them.
- ABMS: ARNI/ACE inhibitor/ARB, bisoprolol/carvedilol/metoprolol succinate, an MRA and an SGLT2 inhibitor, in no fixed order, titrated within 3 months.
- Lifesavers: ABMS, hydralazine-nitrate in the right patient, ICD and CRT; not diuretics or digoxin.
- SODA for HFpEF: SGLT2 inhibitor, obesity therapy, diuretics, aldosterone antagonist (finerenone); none clearly lowers mortality.
- Scales: NYHA (N-Y-H-A) moves with symptoms; the stage (A-B-C-D) doesn't go back; I NEED HELP means refer.
- Numbers: 40, 41–49 and 50 in the US; HFimpEF keeps every drug; ESC 2026 calls an LVEF below 50% HFrEF.
Sources
- 2022 AHA/ACC/HFSA Guideline for the Management of Heart Failure — Circulation (2022)
- 2022 AHA/ACC/HFSA Heart Failure Guideline: Top 10 Take-Home Messages — Heart Failure Society of America (2022)
- ACC Expert Consensus for Treatment of HFrEF: Key Points — American College of Cardiology (2024)
- Updated ACC Expert Consensus Decision Pathway Addresses Management of HFpEF — American College of Cardiology (2026)
- ACC Updates Expert Consensus Pathway for HFpEF Management — HCPLive (2026)
- 2023 Focused Update of the 2021 ESC Heart Failure Guidelines — European Heart Journal (2023)
- 2023 Focused Update of ESC HF Guidelines Entails New Recommendations in Three Sections — PACE-CME (2023)
- Major Changes Made to the ESC Guidelines on Heart Failure — European Society of Cardiology (2026)
- 5 Things to Know About the 2026 ESC Heart Failure Guidelines — AJMC (2026)
- Second Universal Definition of Heart Failure: Top Things to Know — American Heart Association (2026)
- Guideline Publication Schedule — American Heart Association (2026)
- Baumwol J. "I Need Help": A Mnemonic to Aid Timely Referral in Advanced Heart Failure — J Heart Lung Transplant (2017)
- Bauersachs J. Heart Failure Drug Treatment: The Fantastic Four — Eur Heart J (2021)
- Anker SD, et al. Empagliflozin in Heart Failure with a Preserved Ejection Fraction — N Engl J Med (2021)
- Solomon SD, et al. Dapagliflozin in Heart Failure with Mildly Reduced or Preserved Ejection Fraction — N Engl J Med (2022)
- Solomon SD, et al. Finerenone in Heart Failure with Mildly Reduced or Preserved Ejection Fraction — N Engl J Med (2024)
- Kosiborod MN, et al. Semaglutide in Patients with Heart Failure with Preserved Ejection Fraction and Obesity — N Engl J Med (2023)
- Packer M, et al. Tirzepatide for Heart Failure with Preserved Ejection Fraction and Obesity — N Engl J Med (2025)
- Pitt B, et al. Spironolactone for Heart Failure with Preserved Ejection Fraction — N Engl J Med (2014)
- Solomon SD, et al. Angiotensin-Neprilysin Inhibition in Heart Failure with Preserved Ejection Fraction — N Engl J Med (2019)
- Swedberg K, et al. Ivabradine and Outcomes in Chronic Heart Failure (SHIFT) — Lancet (2010)
- Halliday BP, et al. Withdrawal of Pharmacological Treatment for Heart Failure in Patients with Recovered Dilated Cardiomyopathy (TRED-HF) — Lancet (2019)
- Kerendia (Finerenone) Label — DailyMed, NLM (2026)
- Farxiga (Dapagliflozin) Label — DailyMed, NLM (2026)
- Jardiance (Empagliflozin) Label — DailyMed, NLM (2026)
- Wegovy (Semaglutide) Label — DailyMed, NLM (2026)
- Zepbound (Tirzepatide) Label — DailyMed, NLM (2026)
- Heart Failure and Ejection Fraction — StatPearls, NCBI Bookshelf (2024)
- Heart Failure With Preserved Ejection Fraction (HFpEF) — StatPearls, NCBI Bookshelf (2024)
- Left Ventricular Hypertrophy — StatPearls, NCBI Bookshelf (2026)
- Physiology, Heart Sounds — StatPearls, NCBI Bookshelf (2023)
- Dilated Cardiomyopathy — StatPearls, NCBI Bookshelf (2023)
- Cardiomegaly — StatPearls, NCBI Bookshelf (2022)
- Viral Myocarditis — StatPearls, NCBI Bookshelf (2023)
- Sacubitril-Valsartan — StatPearls, NCBI Bookshelf (2025)
- Cardiac Auscultation — Merck Manual Professional Edition (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
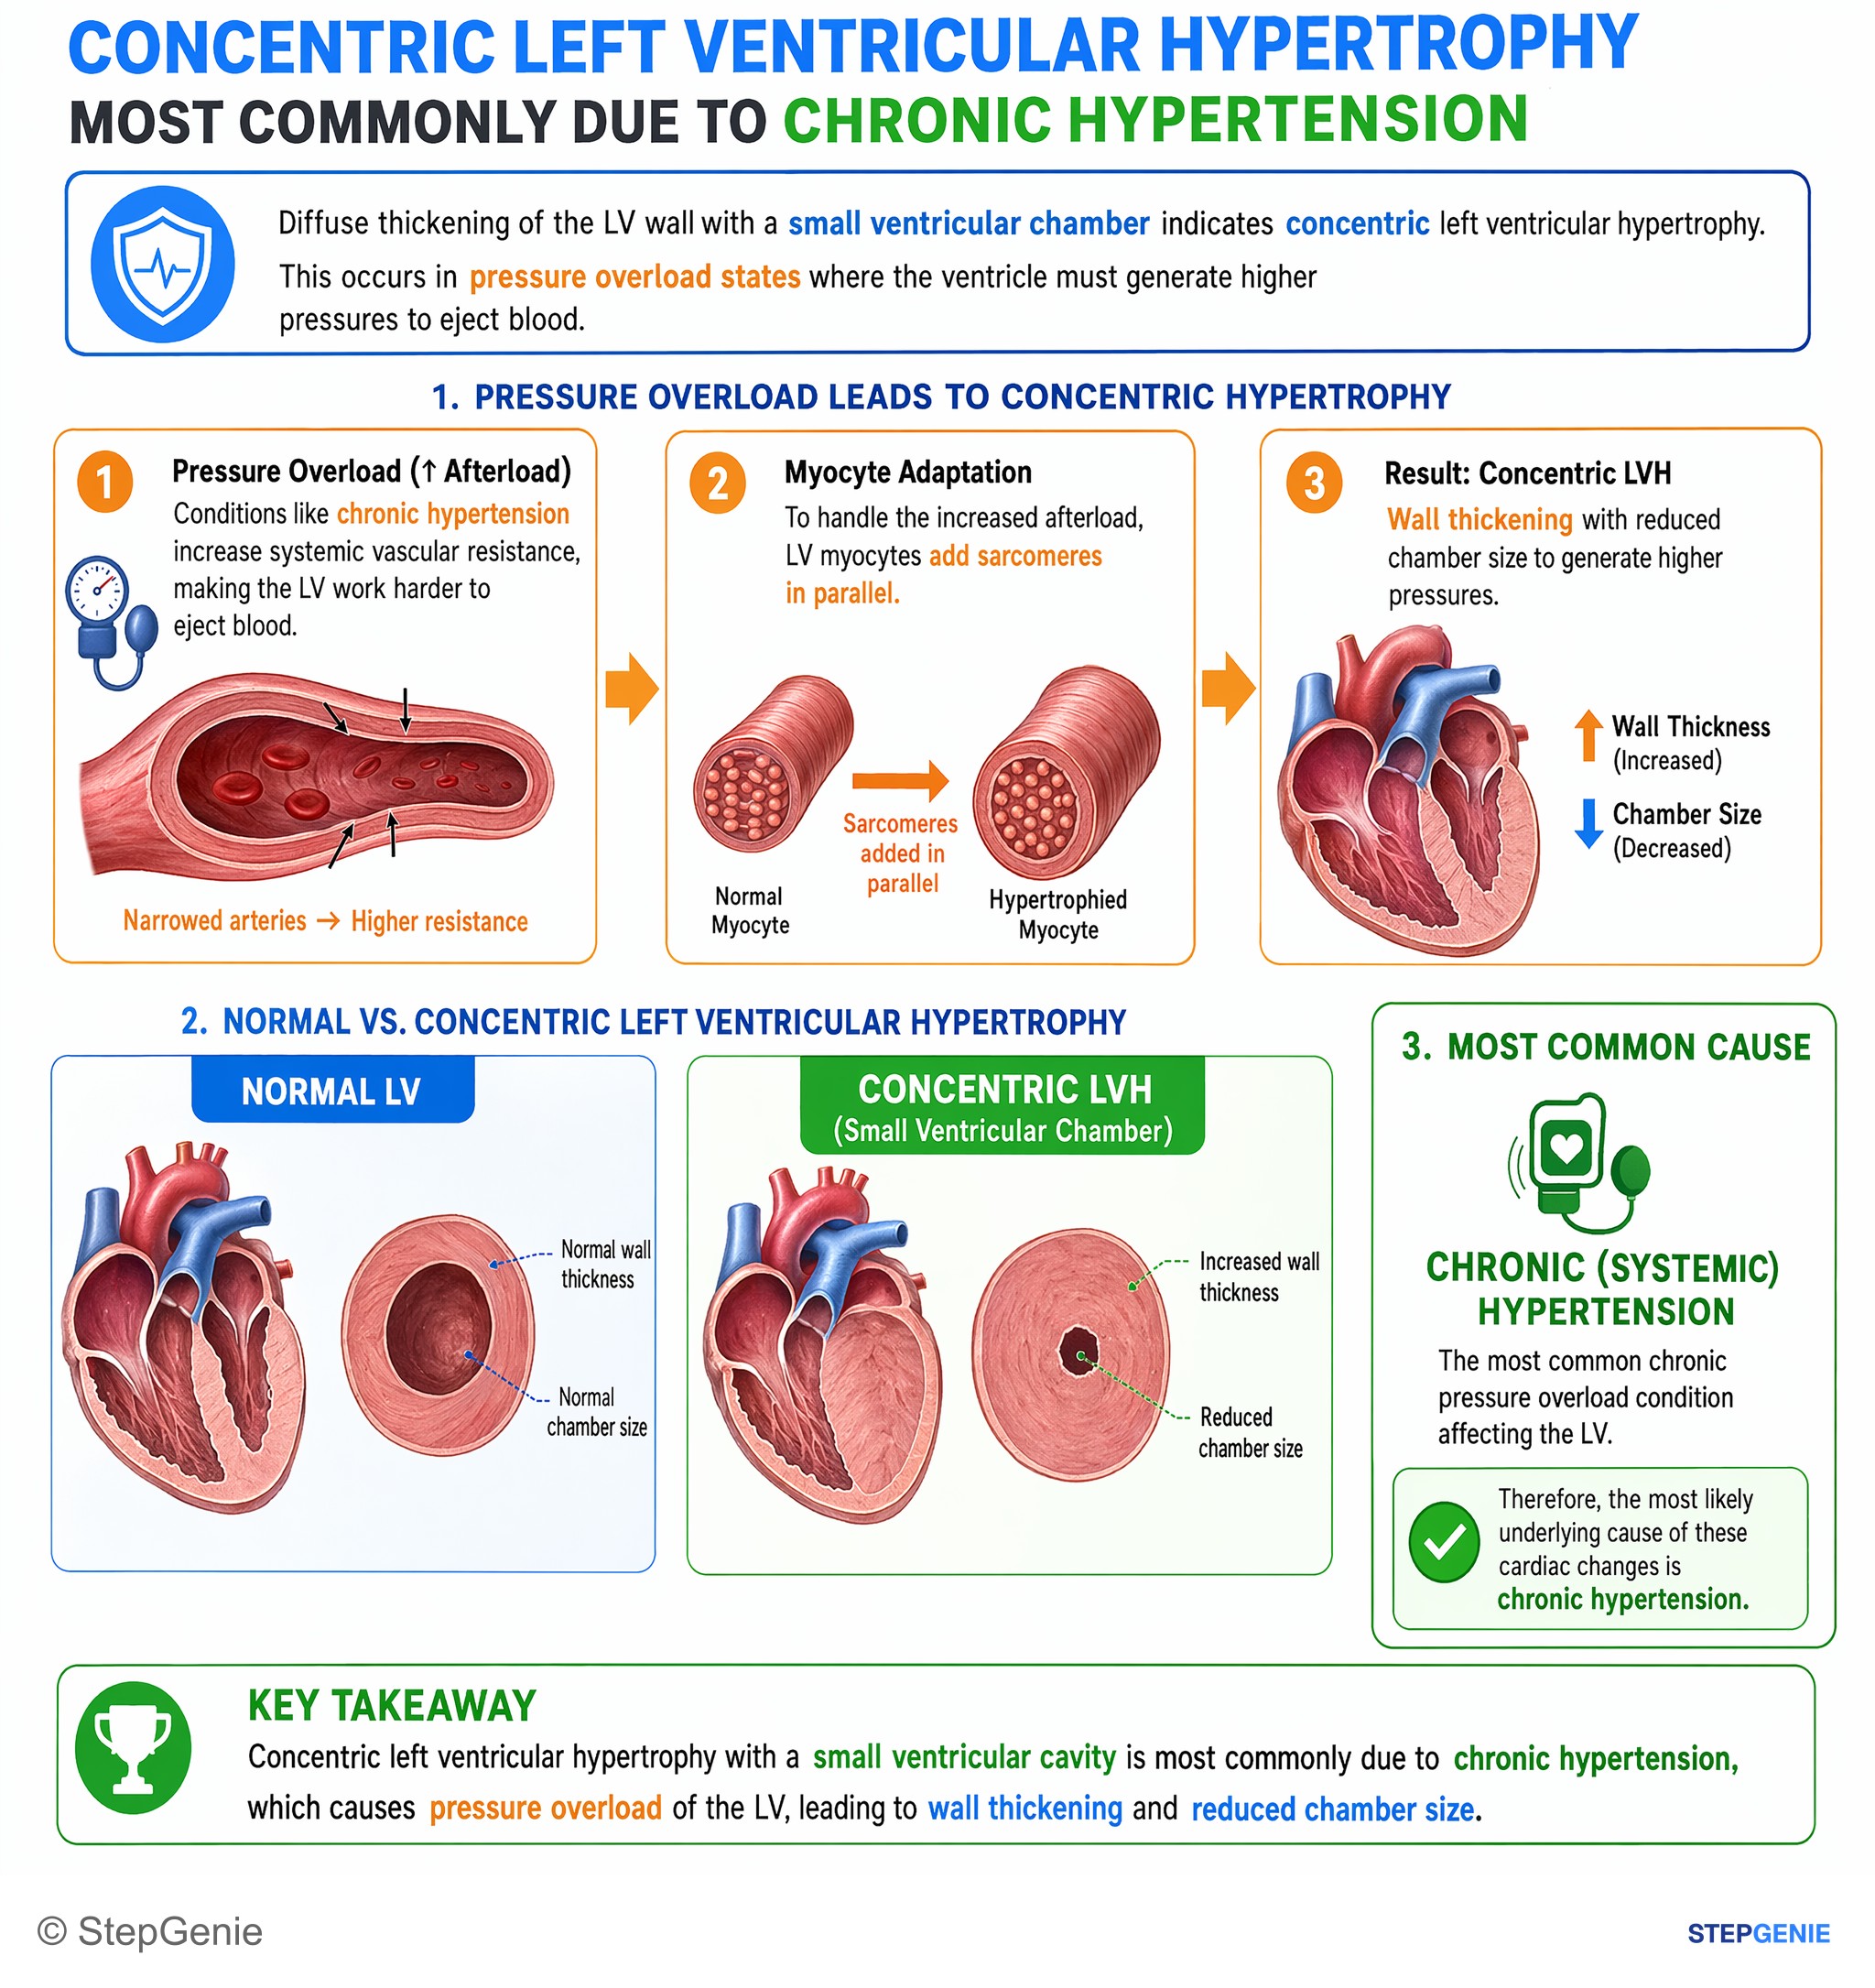
Concentric left ventricular hypertrophy with small ventricular cavity is most commonly due to chronic hypertension causing pressure…
USMLE Step 1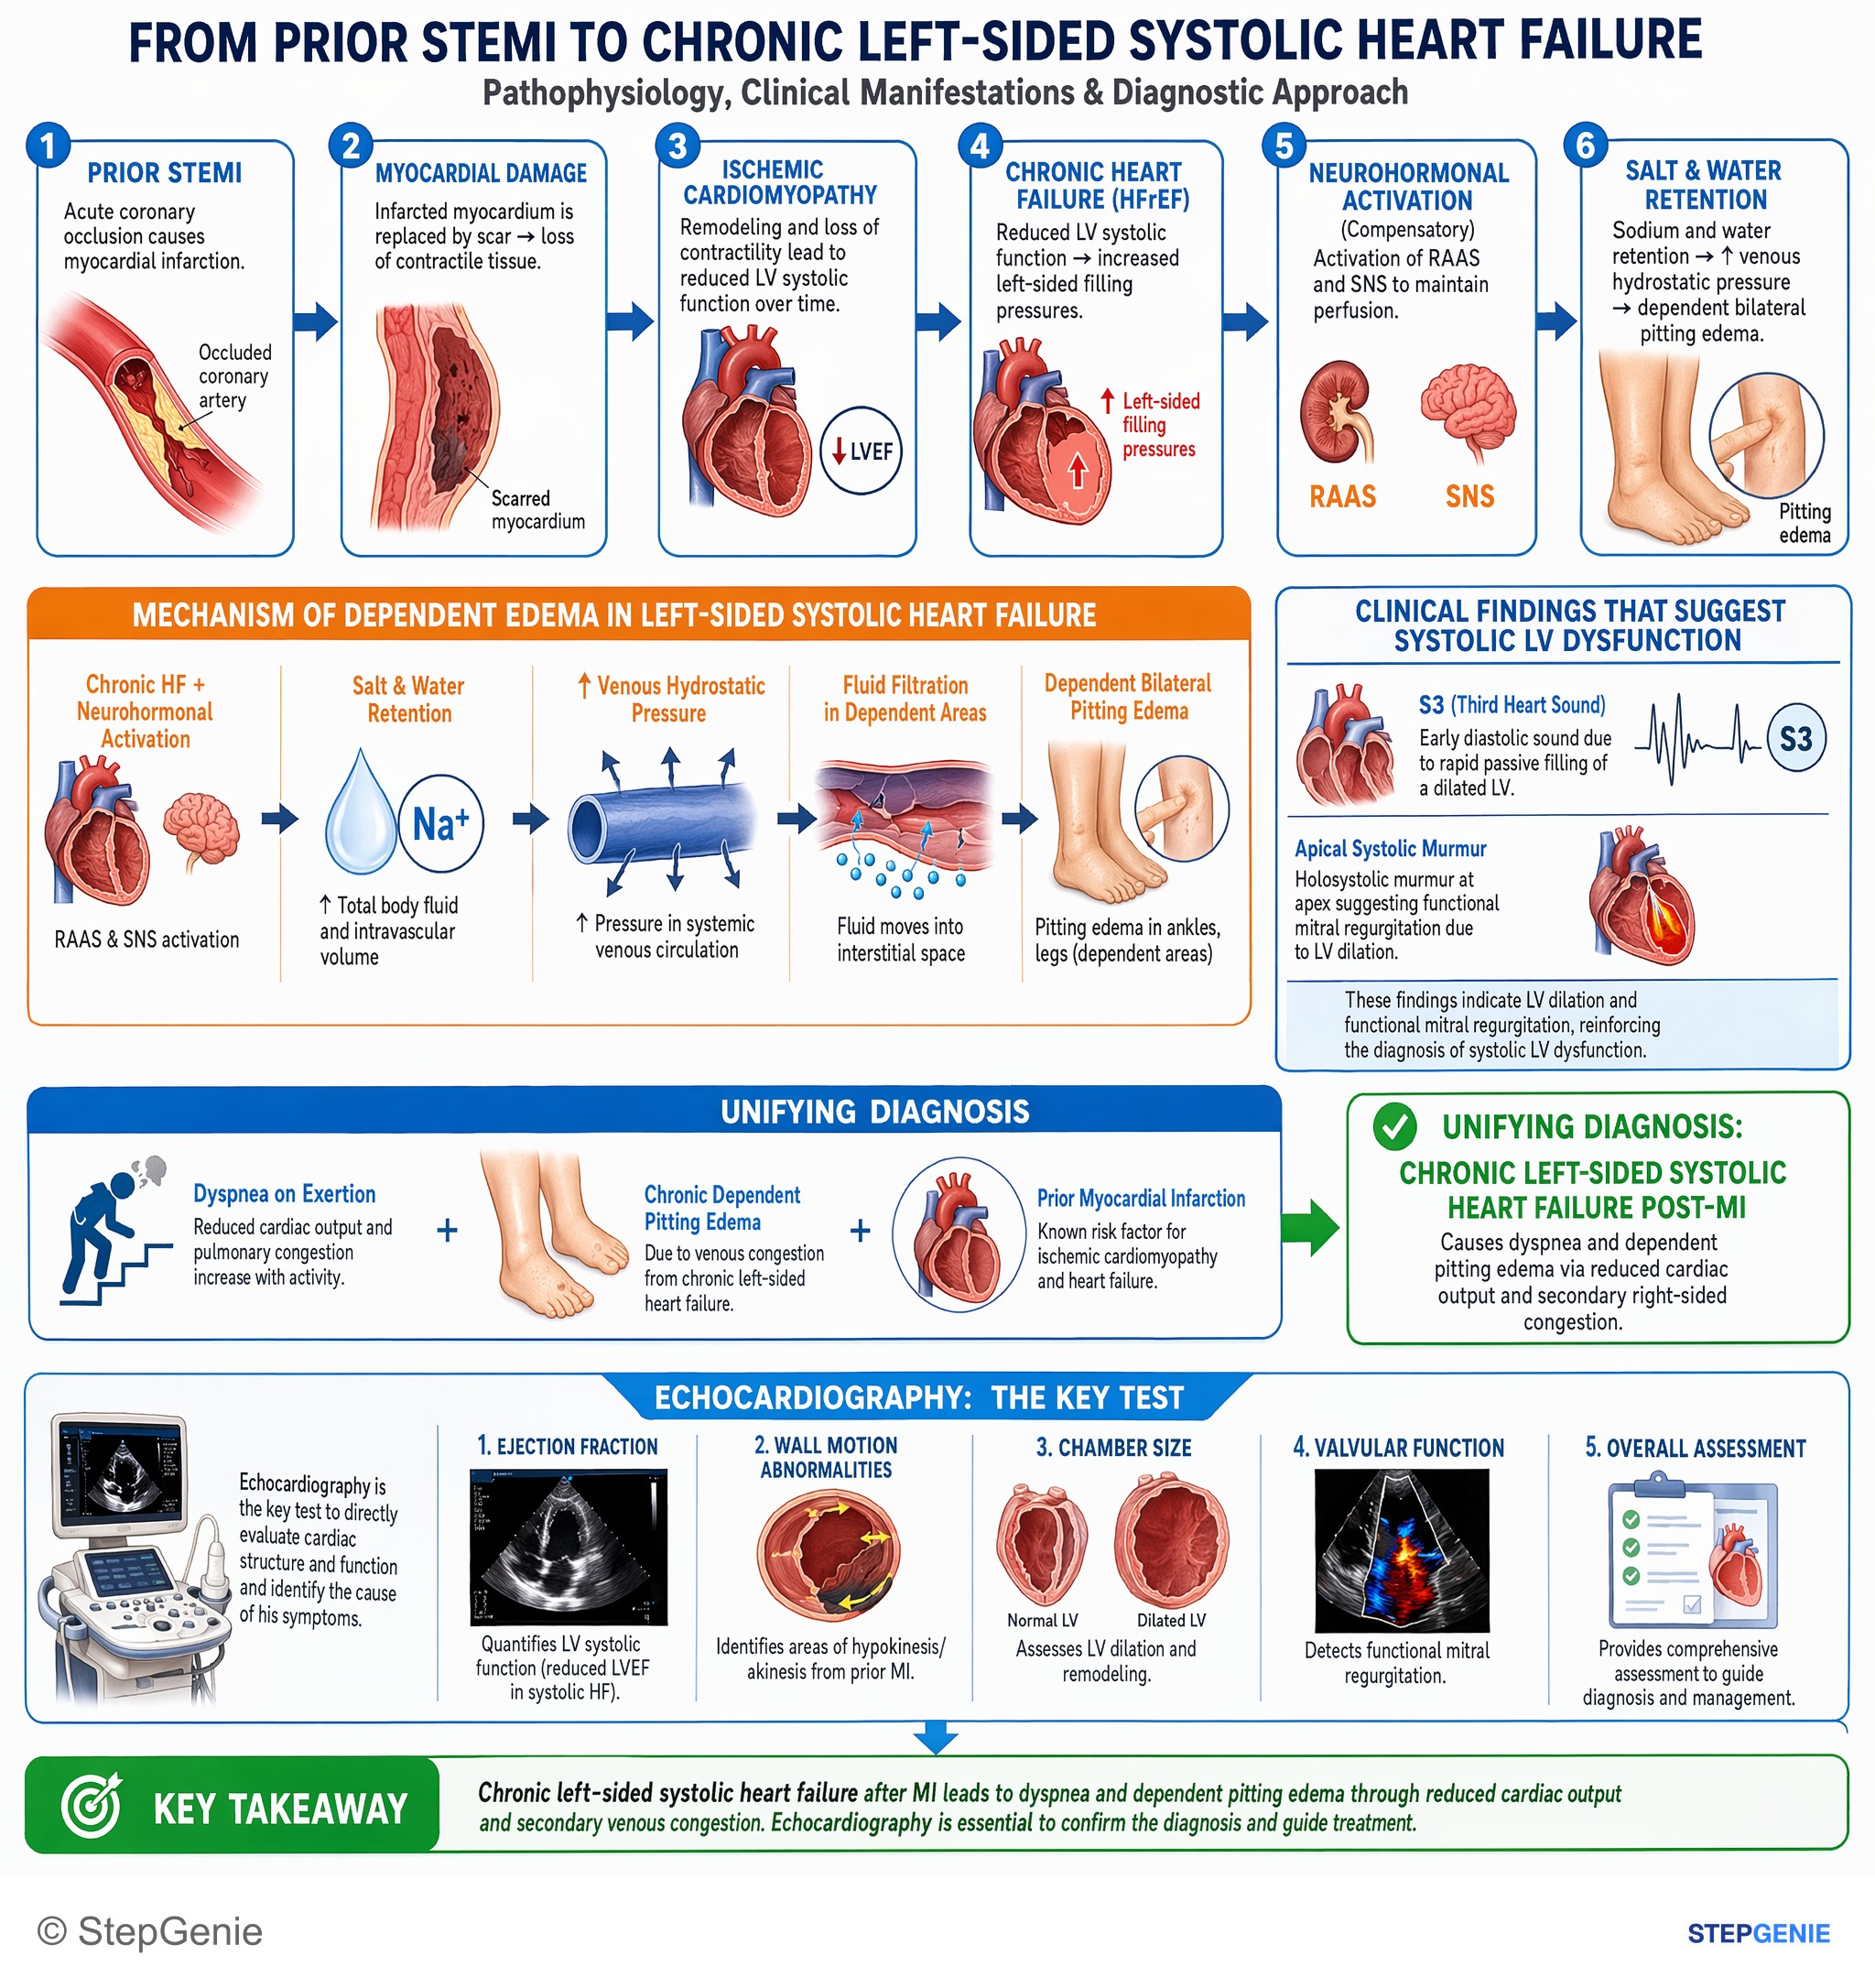
Chronic left-sided systolic heart failure post-MI causes dyspnea and dependent pitting edema via reduced cardiac output and secondary…
USMLE Step 2Frequently Asked Questions
What is the mnemonic for the 4 pillars of heart failure?
A simple memory aid is ABMS, the four drug classes that lower mortality in heart failure with reduced ejection fraction: an ARNI (sacubitril/valsartan), or an ACE inhibitor or ARB; one of three evidence-based beta-blockers (bisoprolol, carvedilol or metoprolol succinate); a mineralocorticoid receptor antagonist (spironolactone or eplerenone); and an SGLT2 inhibitor (dapagliflozin or empagliflozin). The letters are not an order: all four can start at low doses, with titration to maximally tolerated doses within 3 months when feasible.
What is the difference between HFrEF and HFpEF?
HFrEF is FAT failure: an ejection fraction of 40% or less from a dilated, weak left ventricle that can't pump, often with an S3 and usually caused by coronary artery disease. HFpEF is THICK failure: an ejection fraction of 50% or more with raised filling pressure, classically a stiff, hypertrophied ventricle that can't fill, with an S4, in an older patient with hypertension or obesity. Both cause congestion, so the echocardiogram tells them apart.
What ejection fraction is HFrEF, HFmrEF and HFpEF?
Under the 2022 AHA/ACC/HFSA guideline, HFrEF is an ejection fraction of 40% or less, HFmrEF (mildly reduced) is 41% to 49%, and HFpEF is 50% or more; HFmrEF and HFpEF also need evidence of raised filling pressure. A patient whose ejection fraction rises from 40% or less to above 40% has HFimpEF and keeps all HFrEF drugs. The 2026 ESC guideline drops HFmrEF and calls any ejection fraction below 50% HFrEF.
Is an S3 or S4 heard in HFpEF?
HFpEF classically produces an S4, the sound of the atrium contracting against a stiff, hypertrophied ventricle at the end of diastole, just before S1 (the Ten-nes-see cadence). Because it depends on atrial contraction, an S4 disappears in atrial fibrillation, and it is usually abnormal. An S3 comes early in diastole, after S2 (Ken-tuc-ky), and points to a dilated, volume-overloaded ventricle and HFrEF, although it can be normal in children, young adults and pregnancy.
What is a mnemonic for the NYHA classification?
One memory aid uses the letters N-Y-H-A in order. Class I: No limitation of physical activity. Class II: Your ordinary activity brings symptoms. Class III: Hardly any activity is tolerated, since less than ordinary activity causes symptoms, though the patient is comfortable at rest. Class IV: symptoms At rest. NYHA class can improve with treatment, unlike the ACC/AHA stage (A at risk, B pre-heart failure, C symptomatic, D advanced), which does not go back.
What does the I NEED HELP mnemonic mean in heart failure?
I NEED HELP lists signs of advanced heart failure that should prompt referral to an advanced heart failure team: Intravenous inotropes; NYHA class IIIB to IV or persistently elevated natriuretic peptides; End-organ dysfunction; Ejection fraction 35% or less; Defibrillator shocks; Hospitalizations, more than one; Edema despite escalating diuretics; Low systolic blood pressure (90 mm Hg or less) or high heart rate; and Prognostic medication, meaning intolerance or down-titration of guideline-directed therapy. Refer early, before shock or organ failure.