Mitral regurgitation (MR) is one of those Step vignettes that feels “too easy”… until the answer choices start baiting you with aortic stenosis physiology, HOCM maneuvers, and tricuspid findings. The trick is to lock in one crisp mental model of MR, then use it to eliminate every distractor on purpose—not by vibes.
Tag: Cardiovascular > Valvular Heart Disease
The Clinical Vignette (Q-bank style)
A 62-year-old man presents with progressive dyspnea on exertion and fatigue. He has a history of long-standing hypertension and prior inferior MI. On exam, there is a high-pitched holosystolic murmur best heard at the apex, radiating to the axilla. Bibasilar crackles are present. The murmur becomes louder with handgrip. Echocardiogram shows left atrial enlargement and left ventricular dilation.
Question: What is the most likely underlying pathophysiology?
Correct Answer: Mitral Regurgitation (Regurgitant flow during systole)
Why MR fits this stem
Classic MR clues:
- Holosystolic murmur (starts at S1 and goes to S2)
- Best at apex, radiates to axilla
- Louder with handgrip (increased afterload → more regurgitant flow)
- LA enlargement (volume overload of LA)
- LV dilation (chronic volume overload → eccentric hypertrophy)
Step-level physiology you should actually use
During systole, blood is ejected both:
- forward into the aorta, and
- backward into the left atrium through an incompetent mitral valve.
That means:
- LA volume overload → LA dilation → ↑ risk of atrial fibrillation
- ↑ pulmonary venous pressure → dyspnea, crackles
- LV volume overload (because regurgitated blood returns to LV in diastole) → eccentric hypertrophy
Hemodynamics (high yield):
- Increased preload (extra volume returns to LV)
- Decreased effective forward stroke volume (some SV leaks backward)
- Often reduced afterload tolerance; increased SV “demand” can unmask symptoms
Acute vs chronic MR (testable contrast)
| Feature | Acute MR (e.g., papillary muscle rupture) | Chronic MR (e.g., MVP, ischemic remodeling) |
|---|---|---|
| LV/LA adaptation | None | Dilation + eccentric hypertrophy |
| LA pressure | Abruptly high → pulmonary edema | More compensated initially |
| Murmur | Can be softer/shorter (rapid pressure equalization) | Loud holosystolic |
| Presentation | Flash pulmonary edema, hypotension | DOE, fatigue, AF |
High-yield causes:
- Ischemic heart disease → papillary muscle dysfunction (especially posteromedial papillary muscle: single blood supply via PDA)
- Mitral valve prolapse (myxomatous degeneration; click + late systolic murmur)
- Rheumatic disease (classically MS, but can cause MR)
- Infective endocarditis (valve destruction → regurg)
- Dilated cardiomyopathy → annular dilation (functional MR)
Why Handgrip Makes MR Louder (and why they love asking it)
Handgrip increases systemic vascular resistance (afterload). When afterload rises, it becomes harder to eject blood forward into the aorta, so a larger fraction of systolic flow goes backward through an incompetent mitral valve.
Rule of thumb:
- Handgrip: increases murmurs of MR, AR, VSD
- Decreases murmurs of HOCM and aortic stenosis (usually)
Now, the Distractors: Why Each Wrong Answer Is Wrong
Below are common answer choices that show up with an MR stem. The goal is to learn the signature move that eliminates them fast.
Distractor 1: Aortic Stenosis (AS)
How they bait you: older patient + exertional dyspnea.
Why it’s wrong here:
- AS murmur is crescendo–decrescendo systolic (not holosystolic)
- Best heard at right upper sternal border
- Radiates to carotids (not axilla)
- Classically softer with handgrip (handgrip reduces the LV-to-aorta gradient)
AS high-yield associations:
- Pulsus parvus et tardus (weak, delayed carotid upstroke)
- Syncope, angina, dyspnea
- Bicuspid valve younger patients; calcific degeneration in older adults
Distractor 2: Mitral Stenosis (MS)
How they bait you: left atrial enlargement + dyspnea.
Why it’s wrong here:
- MS is diastolic, not systolic:
- Opening snap after S2 + low-pitched diastolic rumble at apex
- LA enlargement is common in MS, but murmur timing is the giveaway.
MS high-yield associations:
- Classically due to rheumatic heart disease
- LA enlargement → atrial fibrillation → thromboembolism risk
- Can cause pulmonary hypertension and right-sided findings later
Distractor 3: Tricuspid Regurgitation (TR)
How they bait you: holosystolic murmur.
Why it’s wrong here:
- TR is best heard at the left lower sternal border
- Increases with inspiration (Carvallo sign) due to ↑ venous return to right heart
- Often comes with signs of right-sided congestion: JVP elevation, hepatomegaly, edema
TR high-yield causes:
- Right ventricular dilation (functional TR)
- Pulmonary hypertension
- Infective endocarditis in IV drug use
Distractor 4: Ventricular Septal Defect (VSD)
How they bait you: holosystolic murmur + increased with handgrip.
Why it’s wrong here:
- VSD is loudest at the left lower sternal border
- Often has a thrill
- Many adult vignettes mention a known congenital defect or post-MI complication with a harsh murmur and acute decompensation.
Post-MI mechanical complication timing:
- VSD rupture: classically 3–5 days after MI (macrophage-mediated tissue breakdown)
- Presents with acute HF + harsh holosystolic murmur + step-up in oxygen saturation in right heart
Distractor 5: Hypertrophic Obstructive Cardiomyopathy (HOCM)
How they bait you: systolic murmur + exertional symptoms.
Why it’s wrong here:
- HOCM murmur is crescendo–decrescendo systolic (not holosystolic)
- Best at left sternal border
- Increases with decreased preload (Valsalva, standing)
- Decreases with handgrip (increased afterload reduces obstruction)
HOCM high-yield:
- Autosomal dominant sarcomere mutation (e.g., -myosin heavy chain)
- Sudden cardiac death risk in young athletes
- S4 may be present due to stiff LV
Distractor 6: Aortic Regurgitation (AR)
How they bait you: “regurgitation” + heart failure symptoms.
Why it’s wrong here:
- AR is diastolic: early diastolic decrescendo murmur along left sternal border
- Often with widened pulse pressure: bounding pulses, head bobbing, etc.
- Handgrip increases AR (true), but the murmur timing and location don’t match.
AR high-yield causes:
- Aortic root dilation (Marfan, syphilis)
- Endocarditis
- Rheumatic disease
Mini Algorithm: Murmur ID Under Pressure
When you see “systolic murmur,” do this quickly:
-
Timing
- Holosystolic → think MR, TR, VSD
- Crescendo–decrescendo → think AS, HOCM
-
Location + radiation
- Apex → axilla = MR
- LLSB + inspiration = TR
- LLSB + thrill = VSD
- RUSB → carotids = AS
-
Maneuvers
- Handgrip ↑ MR/AR/VSD
- Valsalva/standing ↑ HOCM, MVP
- Squatting ↑ AS (usually), ↓ HOCM
High-Yield Extras They Love to Test in MR
1) Papillary muscle facts (MI tie-in)
- Posteromedial papillary muscle has single blood supply (PDA) → more vulnerable to ischemia.
- Papillary muscle rupture → acute severe MR → pulmonary edema, hypotension.
2) Chronic MR physical exam pearls
- Displaced apical impulse (LV dilation)
- Possible S3 due to volume overload
- Signs of pulmonary congestion if decompensated
3) Echo clue-word translations
- Eccentric hypertrophy = volume overload (MR, AR)
- Concentric hypertrophy = pressure overload (AS, HTN)
4) Management (high yield, not guideline minutiae)
- Afterload reduction (e.g., ACE inhibitors) can improve forward flow in functional MR.
- Acute severe MR with instability is often a surgical emergency.
Takeaway: “Every Answer Choice Matters” Strategy
For MR questions, don’t just recognize the murmur—prove it using:
- timing (holosystolic),
- location/radiation (apex → axilla),
- maneuvers (handgrip increases),
- remodeling pattern (LAE + LV dilation = chronic volume overload),
- and etiology hooks (post-MI papillary muscle dysfunction/rupture).
If you can explain why AS/HOCM/MS/TR/VSD/AR are wrong in one sentence each, you’ll stop missing the “easy” valve questions.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
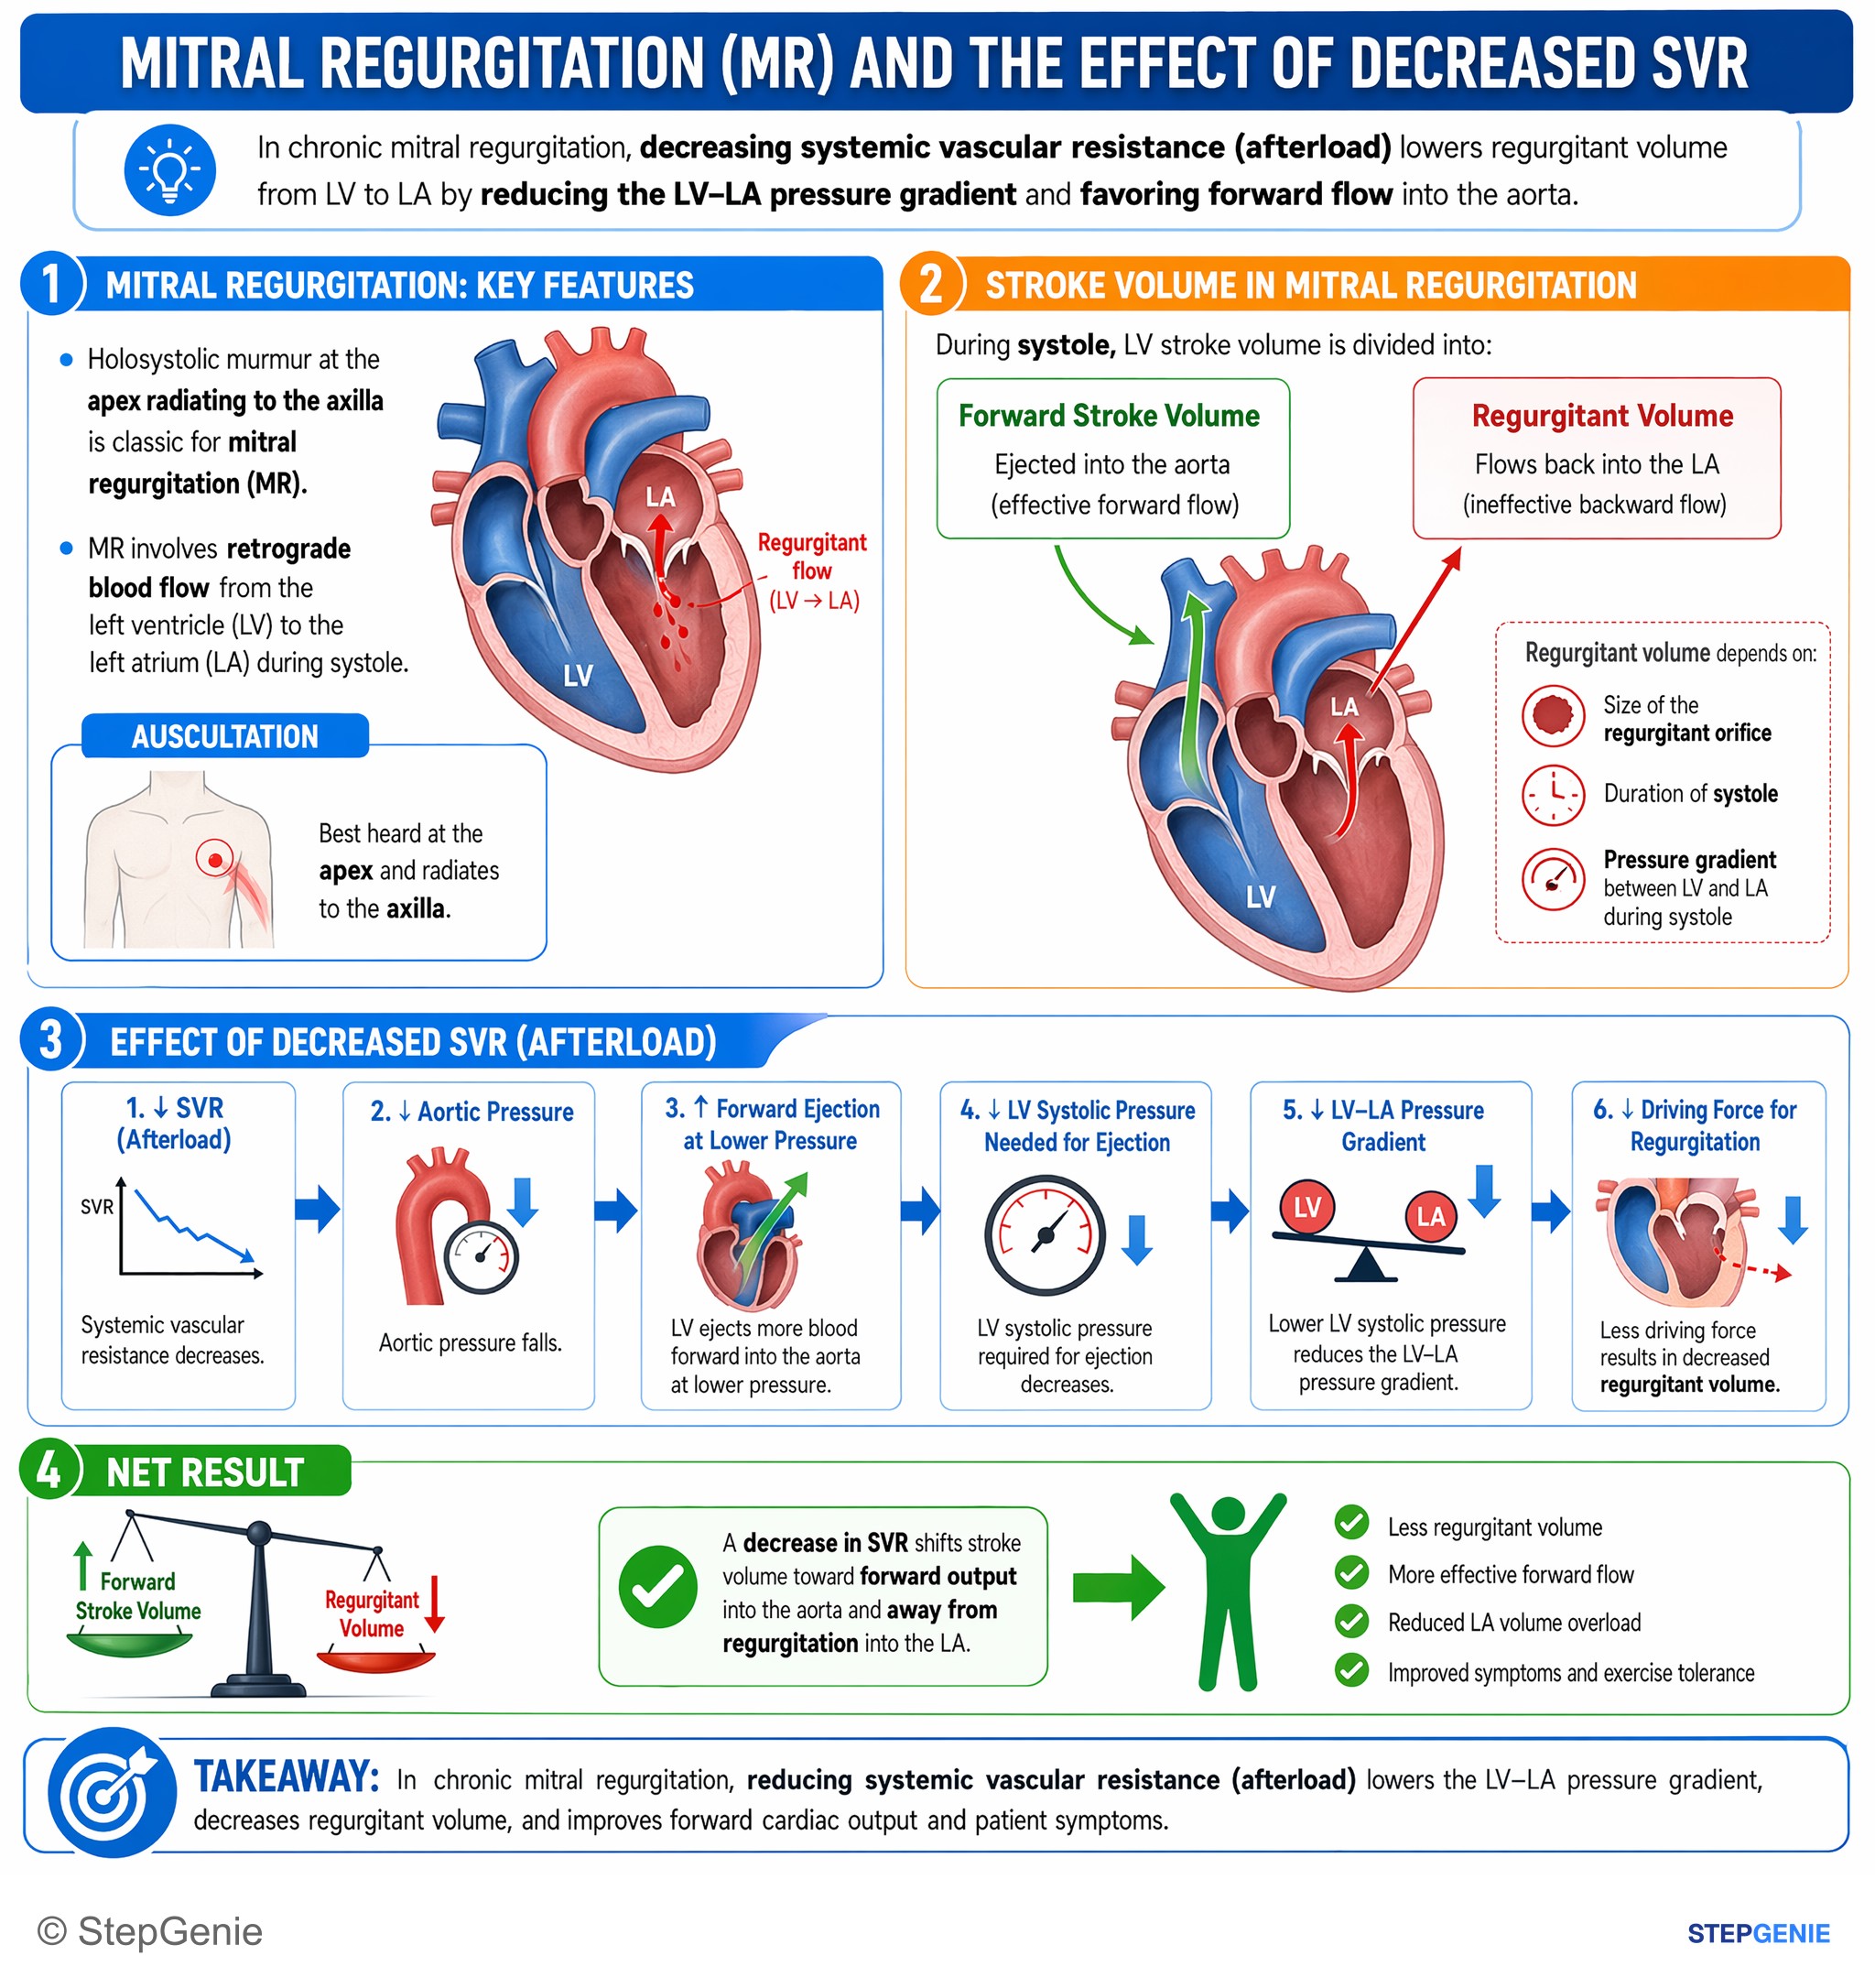
Chronic mitral regurgitation: reducing systemic vascular resistance (afterload) lowers regurgitant volume from LV to LA by favoring…
USMLE Step 1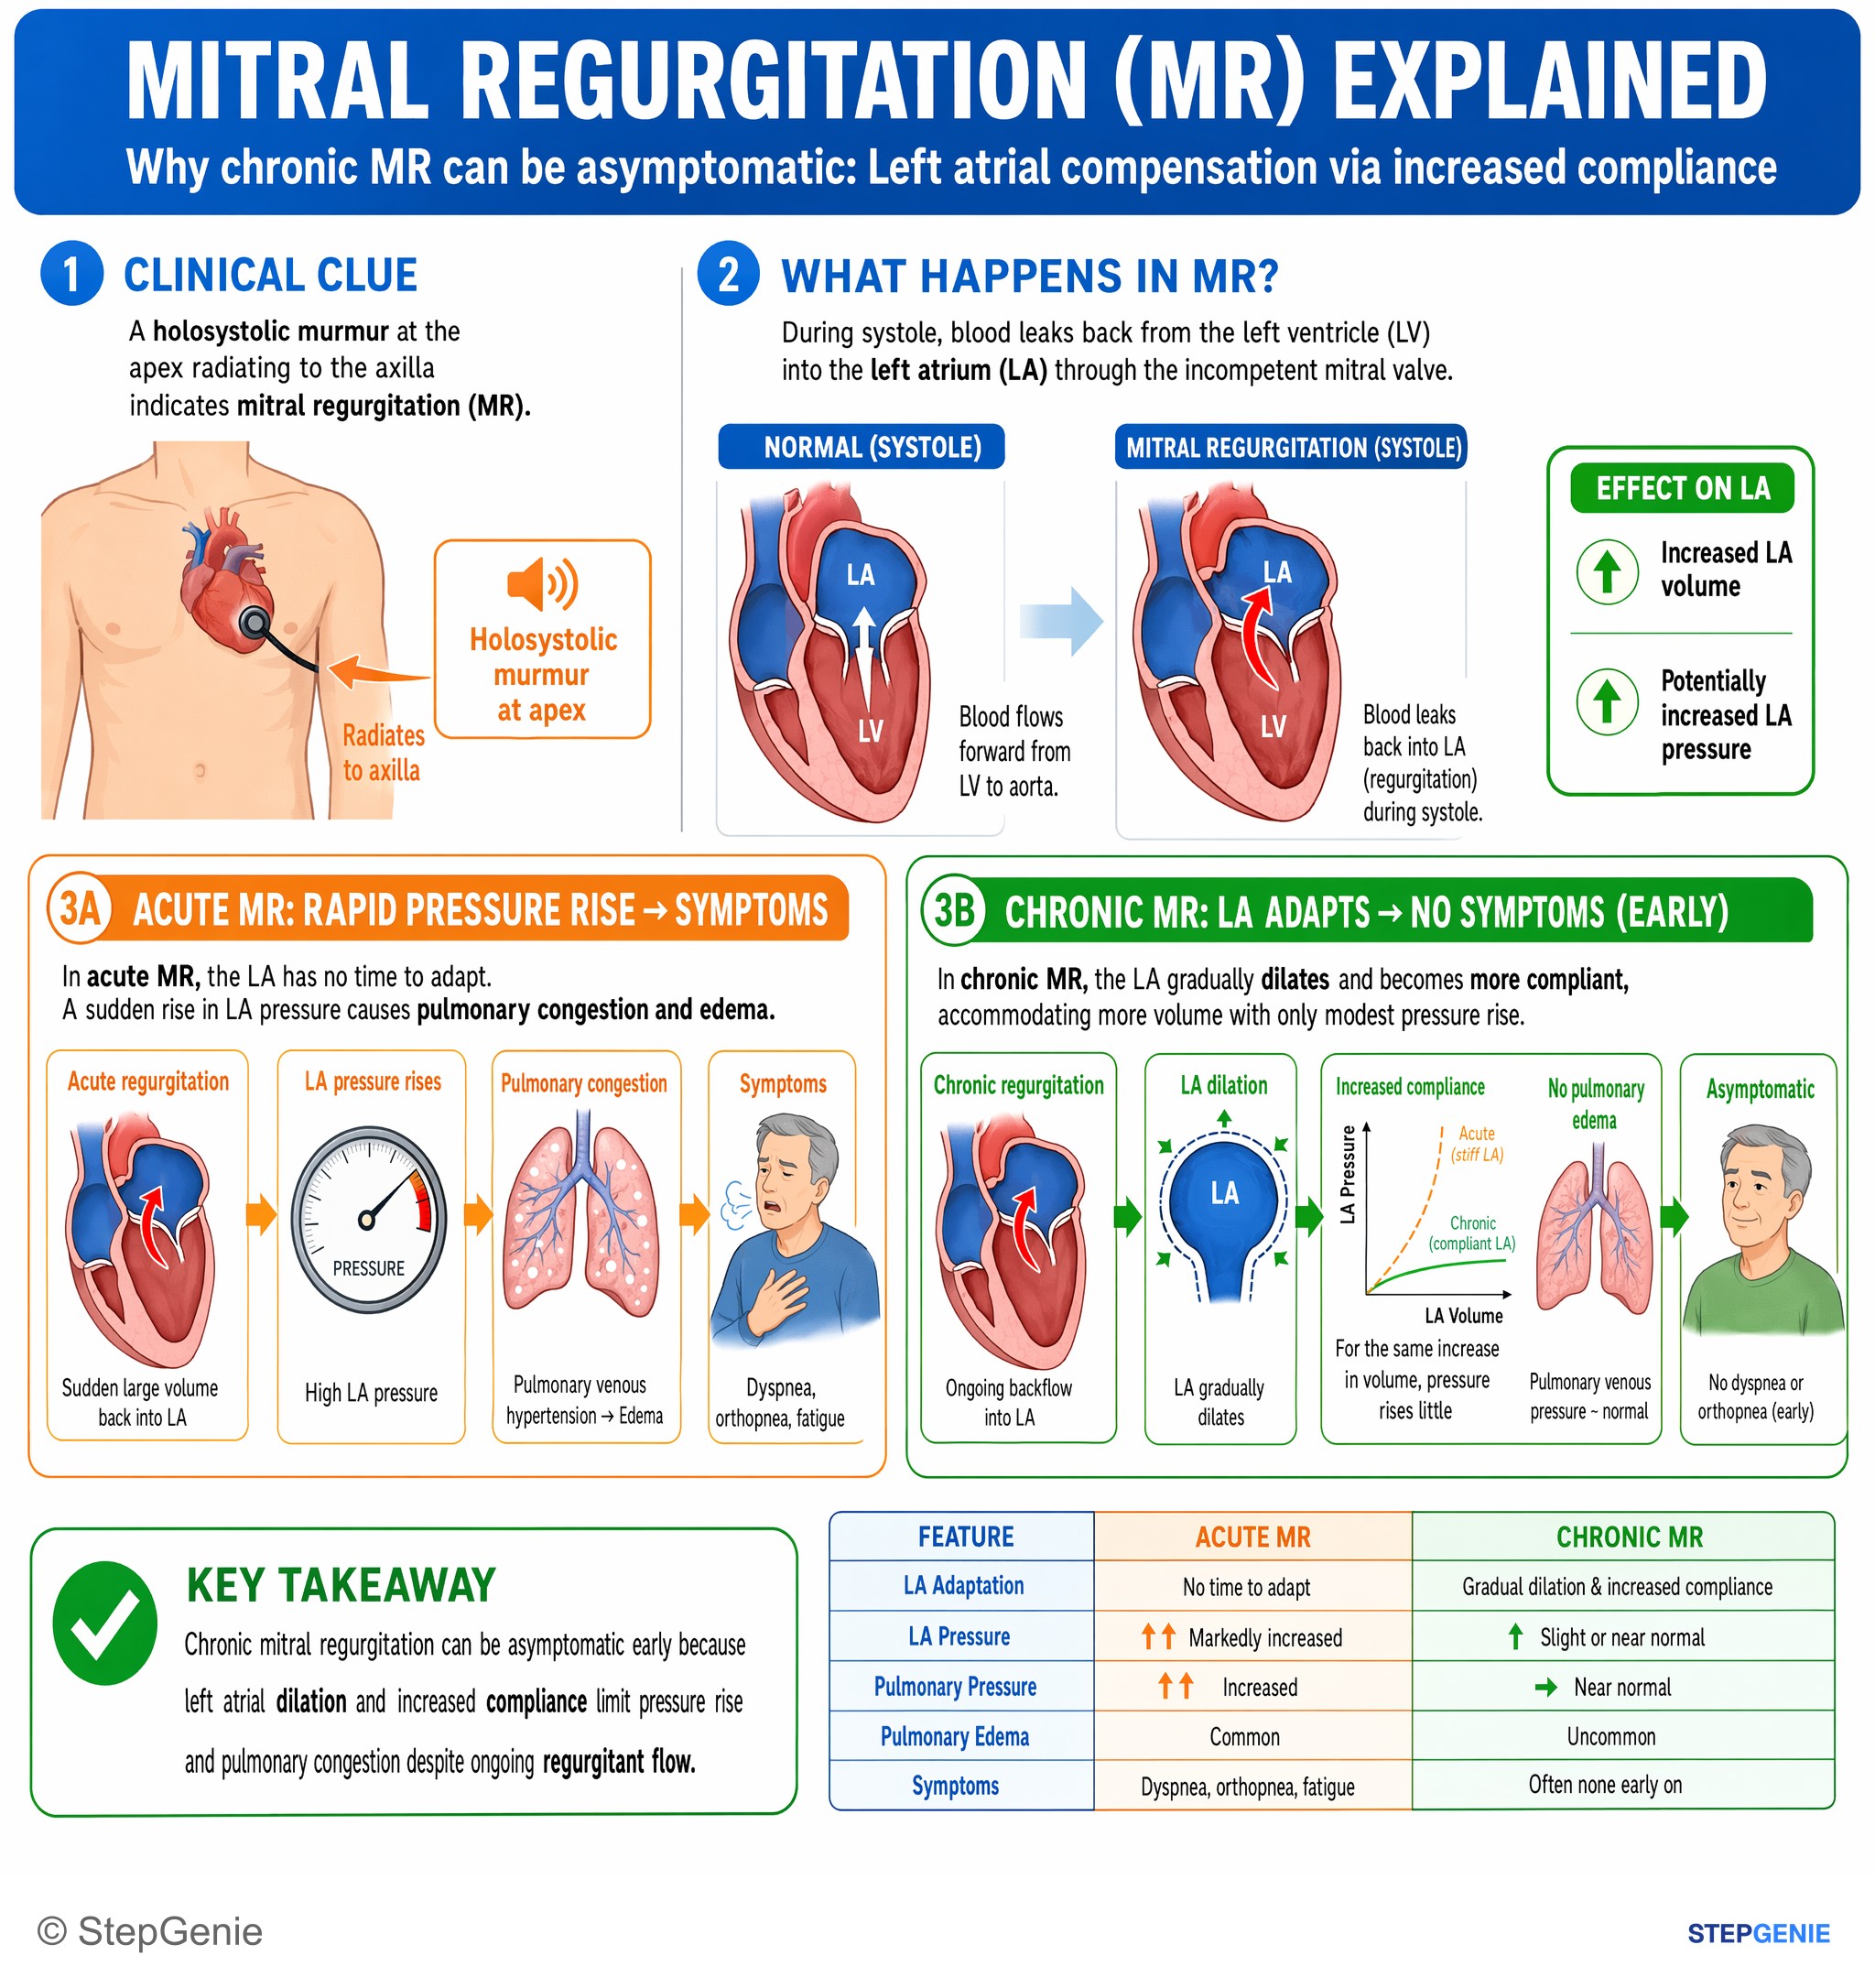
Chronic mitral regurgitation can be asymptomatic early because left atrial dilation/compliance limits pressure rise and pulmonary…
USMLE Step 1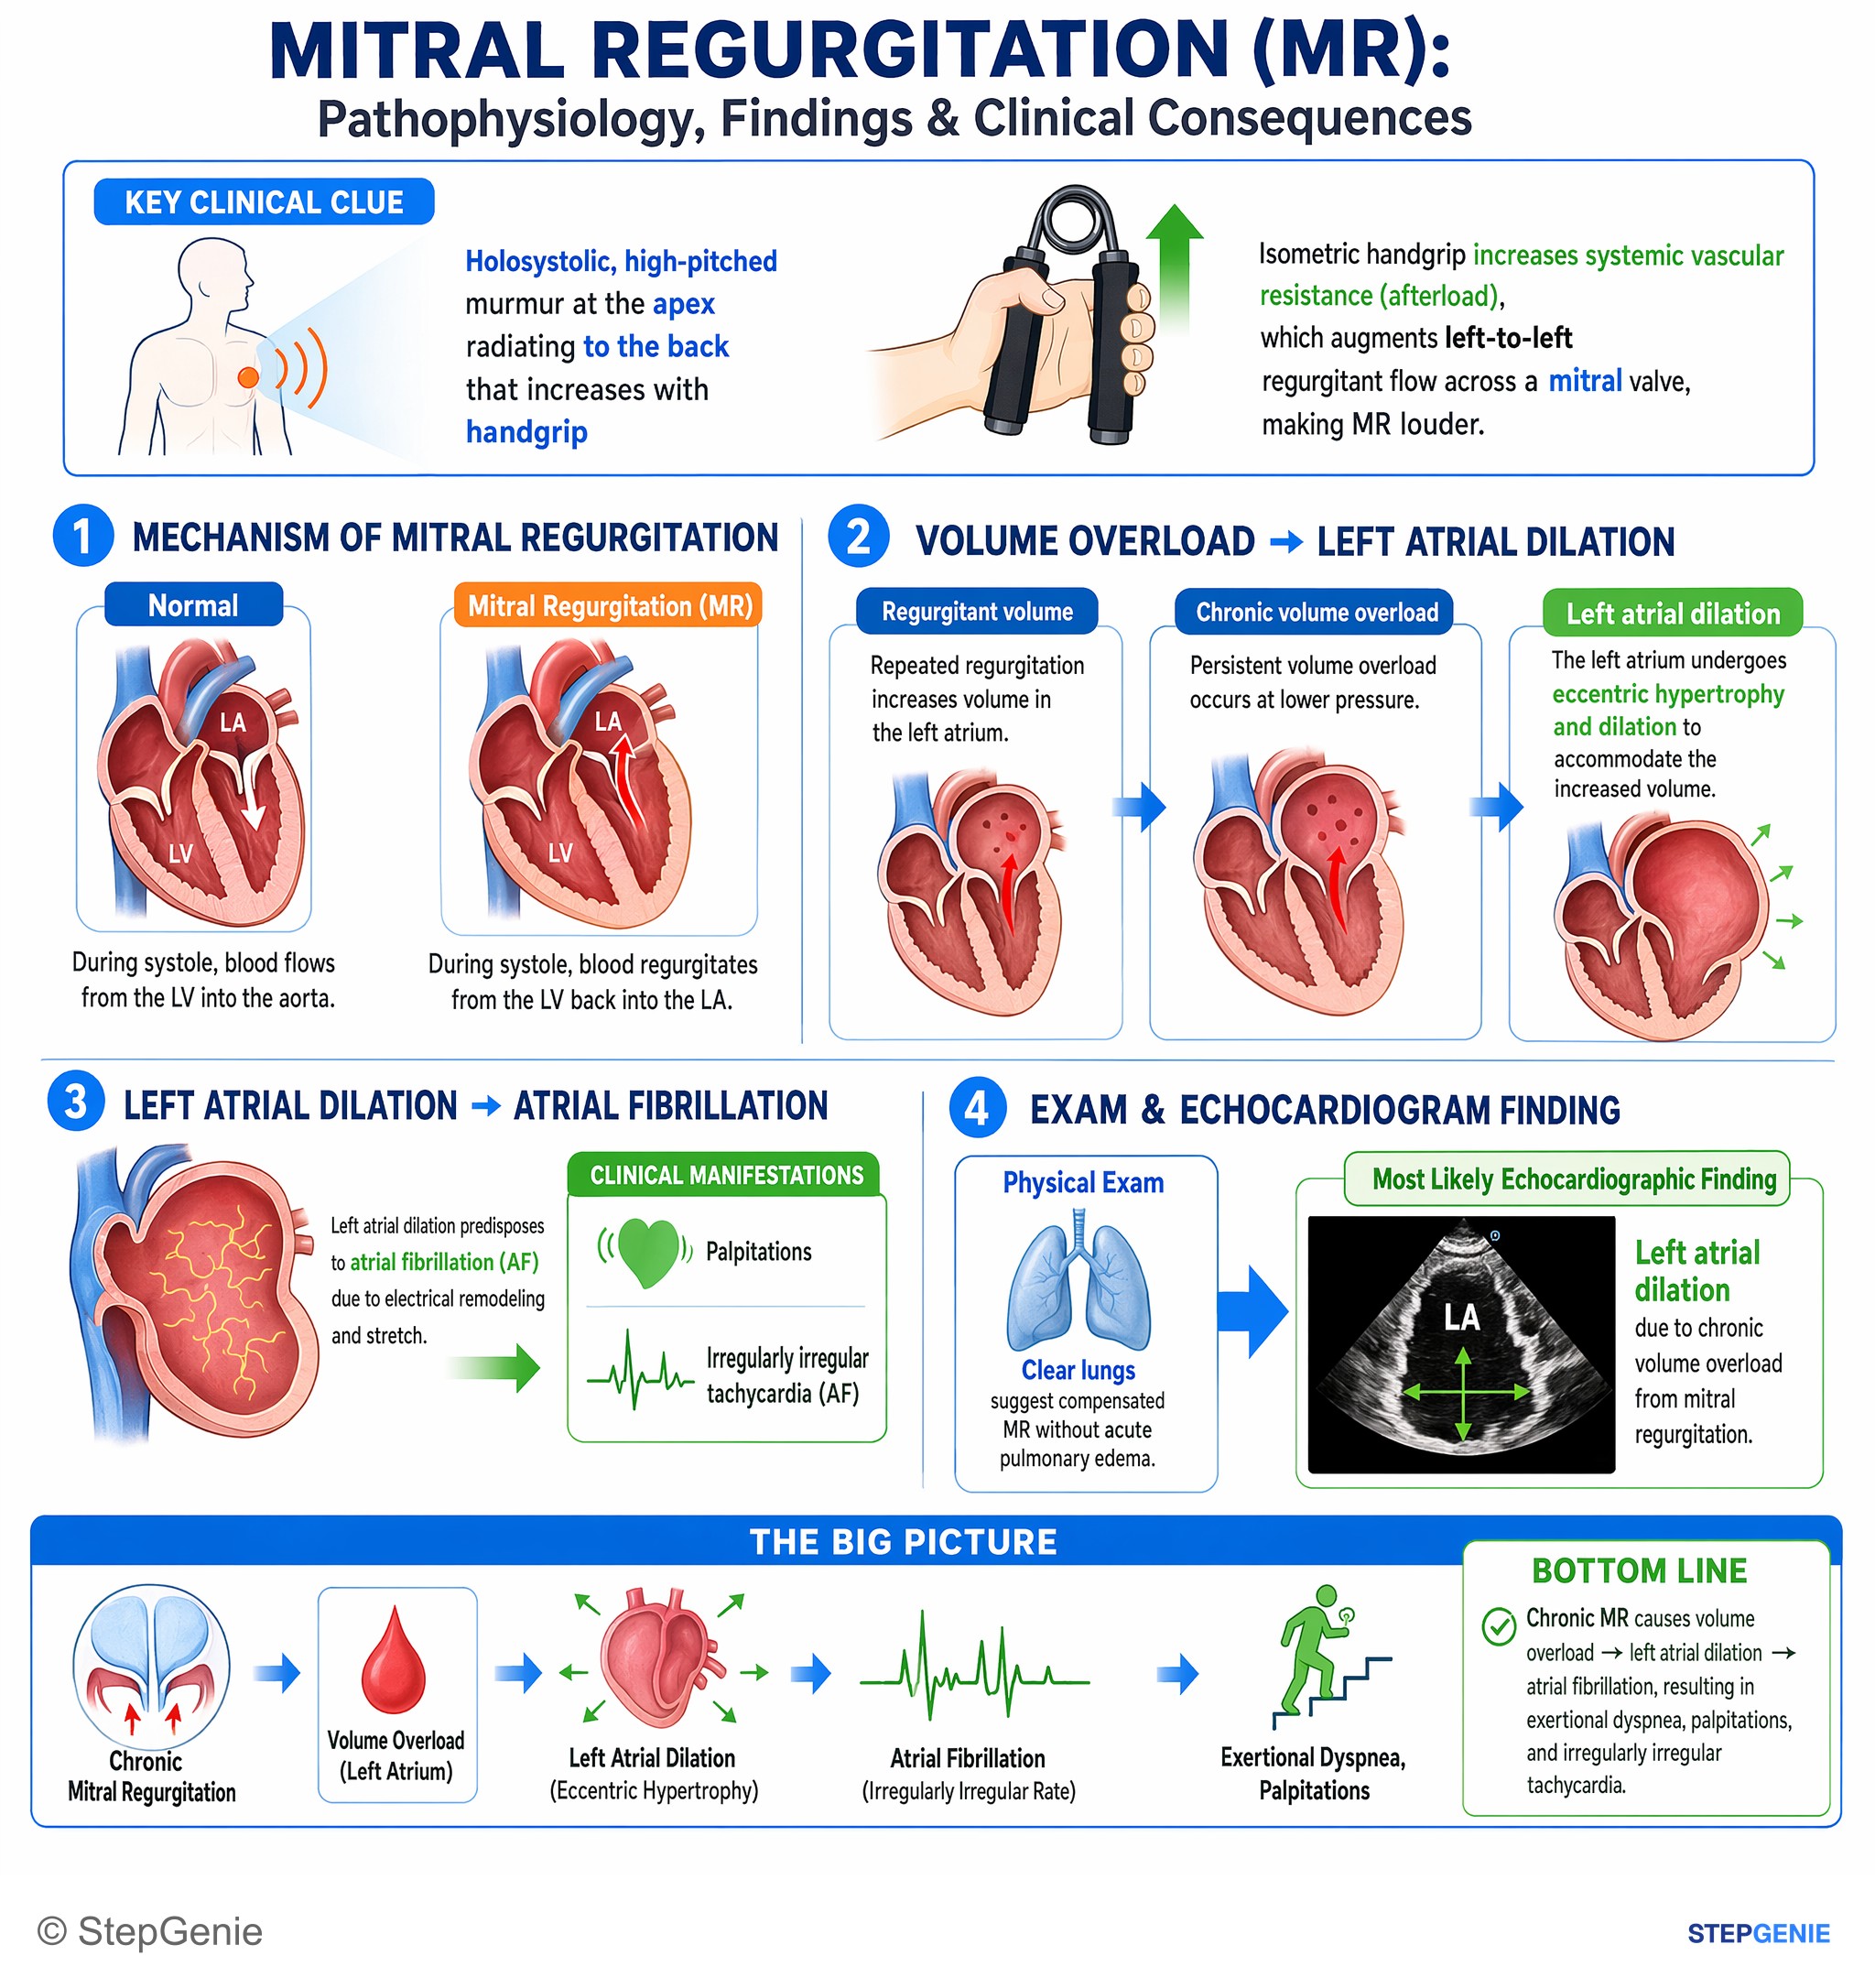
Chronic mitral regurgitation causes volume overload → left atrial dilation → exertional dyspnea, palpitations, and irregularly irregular…
USMLE Step 2Frequently Asked Questions
Why does handgrip make mitral regurgitation louder?
Handgrip makes mitral regurgitation louder because it increases systemic vascular resistance and therefore afterload. When afterload rises, the left ventricle has a harder time ejecting blood forward into the aorta, so a greater fraction of systolic flow is pushed backward through an incompetent mitral valve into the left atrium, making the murmur louder.
How do you tell mitral regurgitation from aortic stenosis on a murmur question?
Mitral regurgitation is distinguished by a high-pitched holosystolic murmur heard best at the apex with radiation to the axilla, and it becomes louder with handgrip. Aortic stenosis instead causes a crescendo-decrescendo systolic murmur at the right upper sternal border that radiates to the carotids and is usually softer with handgrip.
Why does chronic mitral regurgitation cause left atrial enlargement and left ventricular dilation?
Chronic mitral regurgitation causes volume overload in both the left atrium and left ventricle. During systole, some blood leaks backward into the left atrium, leading to left atrial dilation and a higher risk of atrial fibrillation. That regurgitated blood then returns to the left ventricle during diastole, increasing preload and producing left ventricular dilation with eccentric hypertrophy.
How do you tell mitral regurgitation from tricuspid regurgitation or VSD?
Mitral regurgitation is best identified by a holosystolic murmur at the apex that radiates to the axilla. Tricuspid regurgitation is also holosystolic, but it is loudest at the left lower sternal border and increases with inspiration. A ventricular septal defect is likewise loudest at the left lower sternal border, often has a thrill, and in adults may appear as a post-MI mechanical complication.
What is the key difference between acute and chronic mitral regurgitation on exams?
The key difference is adaptation versus no adaptation. Acute mitral regurgitation has no time for left atrial or left ventricular remodeling, so left atrial pressure rises abruptly and can cause flash pulmonary edema and hypotension; the murmur may even be softer or shorter. Chronic mitral regurgitation is more compensated at first and typically presents with dyspnea on exertion, fatigue, atrial fibrillation, and chamber dilation.