Infective endocarditis (IE) is one of those Step-style diagnoses where the clues are loud (fever + murmur + risk factor), but the question is really testing whether you can separate “most likely” from “also possible”. The fastest way to level up is to treat every answer choice like it’s trying to trick you—and learn exactly why it’s wrong.
Clinical Vignette (Q-bank style)
A 28-year-old man comes to the ED with 4 days of fever, chills, and malaise. He reports injecting heroin. Vitals: T 39.2°C (102.6°F), HR 115, BP 110/60. Exam shows track marks on the arms, conjunctival petechiae, and a new holosystolic murmur loudest at the left lower sternal border that increases with inspiration. Lungs are clear.
Labs: WBC 15,000/µL.
Two sets of blood cultures are drawn.
What is the most likely causative organism?
A. Staphylococcus epidermidis
B. Viridans streptococci
C. Staphylococcus aureus
D. Streptococcus gallolyticus (bovis)
E. HACEK organisms
Step-wise Approach (What the stem is screaming)
Key clues:
- IV drug use → think right-sided IE (classically tricuspid valve)
- New holosystolic murmur at LLSB that increases with inspiration → tricuspid regurgitation (Carvallo sign)
- Acute course (days), high fever, toxic appearance → suggests a high-virulence organism
- Conjunctival petechiae → supportive peripheral IE finding
Put together: acute right-sided endocarditis in an IVDU → Staphylococcus aureus.
Correct Answer: C. Staphylococcus aureus
Why it’s correct
- Most common cause of infective endocarditis overall in many settings
- Most common cause in IV drug users
- Causes acute, destructive endocarditis due to high virulence (can infect normal valves)
- Often hits the tricuspid valve → can produce septic pulmonary emboli (pleuritic chest pain, cough, hemoptysis, nodular infiltrates)
High-yield microbiology tie-ins
- Gram-positive cocci in clusters
- Catalase positive, coagulase positive
- Commonly associated with skin flora + needles in IVDU
Why Every Distractor Is Wrong (and when it would be right)
A. Staphylococcus epidermidis
Why it’s wrong here
- Typically causes subacute IE in the setting of prosthetic valves or indwelling devices
- Less virulent than S. aureus; classically needs a foreign surface to form biofilm
When it’s right
- Early prosthetic valve endocarditis (especially within the first year)
- Think: recent valve replacement + fevers + new regurg murmur
High-yield hook
- Biofilm formation on prosthetic material → helps it evade host defenses and antibiotics.
B. Viridans streptococci
Why it’s wrong here
- Usually subacute presentation over weeks
- Often after dental procedures or in patients with preexisting valve disease (e.g., MVP with regurg, rheumatic disease)
- Not the classic association for IVDU right-sided disease
When it’s right
- Poor dentition, dental work, or congenital valve abnormalities + slowly progressive symptoms (fatigue, low-grade fever)
High-yield hook
- Viridans streptococci produce dextrans → adhere to damaged valves.
D. Streptococcus gallolyticus (formerly S. bovis)
Why it’s wrong here
- Not linked to IVDU as a primary association
- Often left-sided disease and may be subacute
When it’s right
- IE + iron deficiency anemia or weight loss → think colon cancer
- Requires colonoscopy in many exam scenarios
High-yield hook
- S. gallolyticus bacteremia/endocarditis is associated with colorectal carcinoma (and sometimes polyps).
E. HACEK organisms
(Haemophilus, Aggregatibacter, Cardiobacterium, Eikenella, Kingella)
Why it’s wrong here
- HACEK IE is typically subacute, often in patients with underlying valve abnormalities
- Often linked to oral flora; may follow dental disease/procedures
- Not the go-to cause for acute, IVDU-associated tricuspid IE
When it’s right
- Culture-negative endocarditis suspicion with slow-growing gram-negative bacilli
- IE picture with negative routine cultures early on, especially if no antibiotics were given yet (HACEK can be missed unless cultures are held longer)
High-yield hook
- Important cause of culture-negative endocarditis (though overall less common than other causes).
High-Yield IE Facts You’re Expected to Know
1) Acute vs subacute patterns
| Pattern | Typical organisms | Valve status | Clinical tempo |
|---|---|---|---|
| Acute | S. aureus | Can be normal | Days, toxic |
| Subacute | Viridans, enterococci, HACEK, S. epidermidis (prosthetic) | Often abnormal or prosthetic | Weeks, indolent |
2) Right-sided vs left-sided IE
- Right-sided (tricuspid): IVDU, intracardiac devices
- Emboli go to lungs → septic pulmonary emboli
- Left-sided (mitral/aortic): more common overall in non-IVDU
- Emboli go systemic → stroke, splenic infarcts, kidney infarcts
3) Classic peripheral findings (Step favorites)
- Petechiae, splinter hemorrhages
- Janeway lesions: painless palms/soles lesions (microabscesses)
- Osler nodes: painful fingertip/toe nodules (immune complex)
- Roth spots: retinal hemorrhages
Remember: these are supportive, not required. Many real cases won’t have them.
4) Culture strategy (testable clinical reasoning)
- Draw at least 3 sets of blood cultures from different sites before antibiotics if the patient is stable.
- In unstable patients (septic shock), don’t delay antibiotics excessively—but still try to get cultures first if possible.
5) Empiric antibiotics (high-level Step framing)
Empiric therapy depends on:
- Native vs prosthetic valve
- Community vs healthcare-associated
- Organism risk (MRSA, enterococcus, gram-negatives)
A common Step-ready summary:
- Native valve, severe: cover MRSA + strep (often vancomycin-based)
- Prosthetic valve: broaden for staph epidermidis and resistant organisms (often includes vancomycin + additional agents)
(Exact regimens can vary by guideline; Step questions usually test the coverage logic.)
Rapid Takeaway: How to Lock the Answer in <10 seconds
- IVDU + new murmur at LLSB that gets louder with inspiration = tricuspid regurg
- Acute febrile illness + tricuspid valve IE in IVDU = S. aureus
- Viridans = dental/subacute; S. epidermidis = prosthetic; S. gallolyticus = colon cancer; HACEK = slow-growing/culture-negative subacute
Quick Self-Check (1-liner drill)
- IVDU + septic pulmonary emboli → tricuspid IE, usually S. aureus
- Dental work + subacute IE → viridans
- Prosthetic valve → S. epidermidis
- IE + colon cancer → S. gallolyticus
- Culture-negative-ish, slow gram-negative → HACEK
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
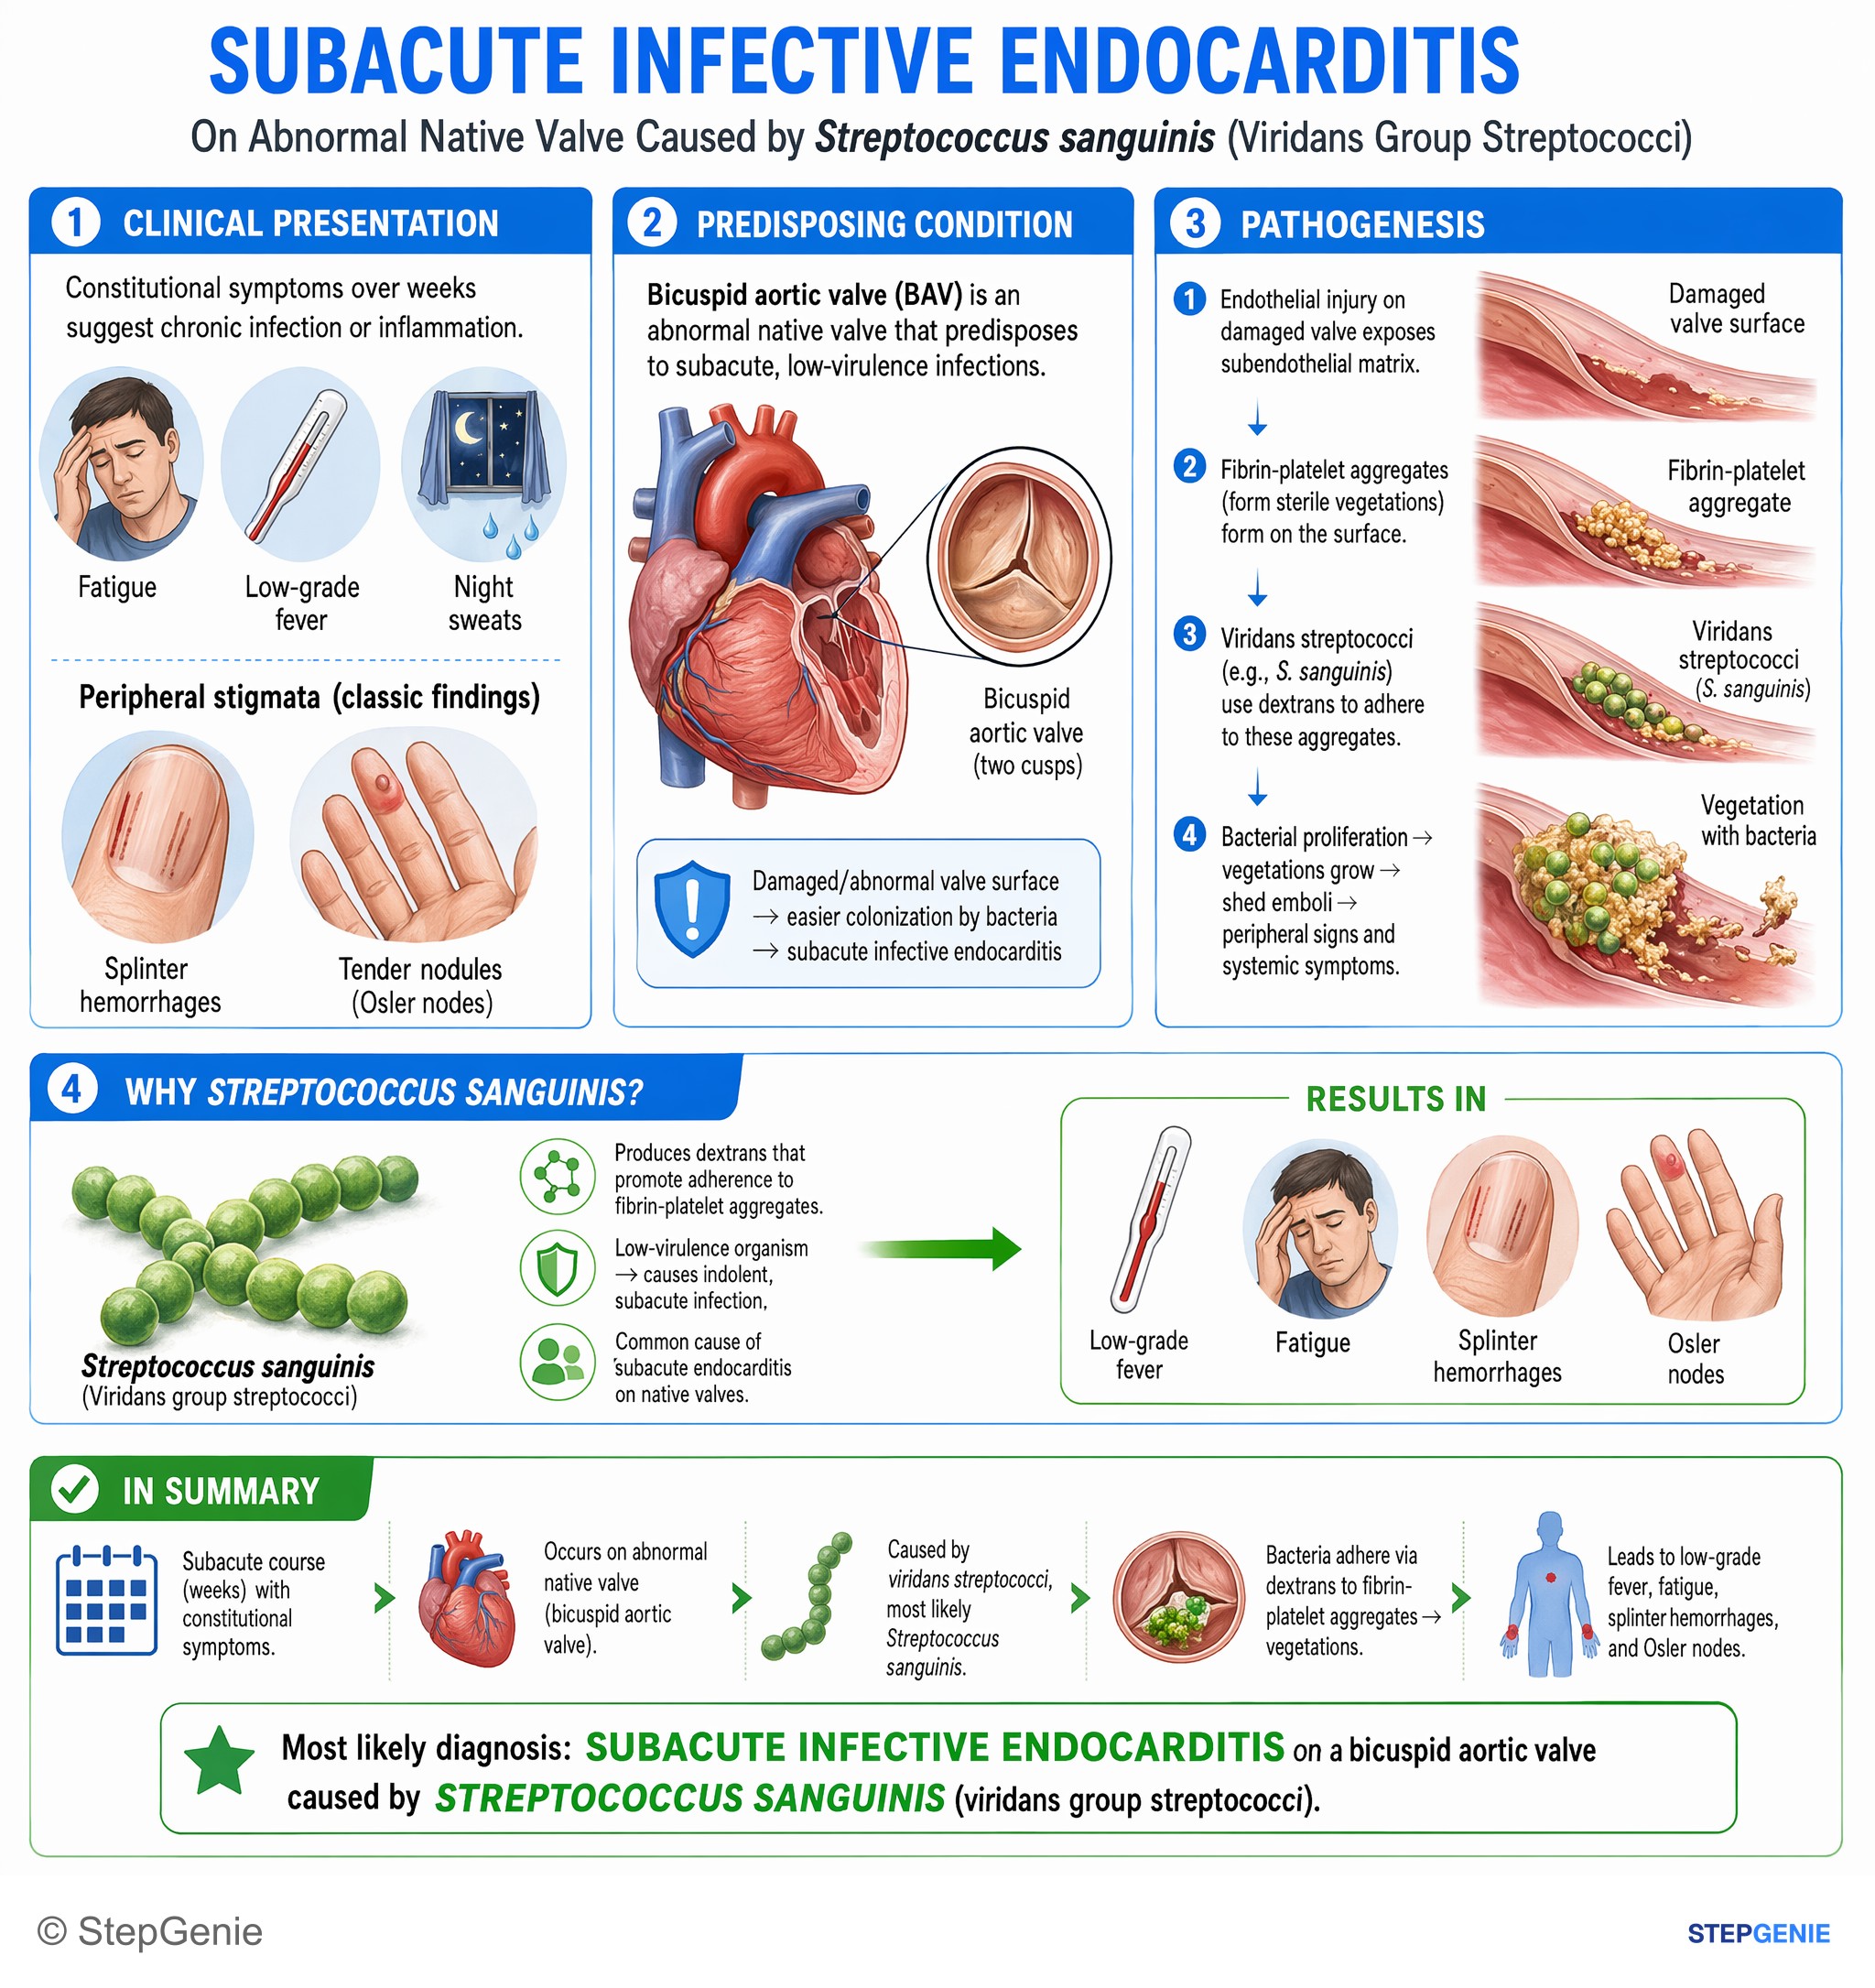
Subacute infective endocarditis on abnormal valve (bicuspid aortic) by viridans streptococci (S sanguinis) causing low-grade fever…
USMLE Step 1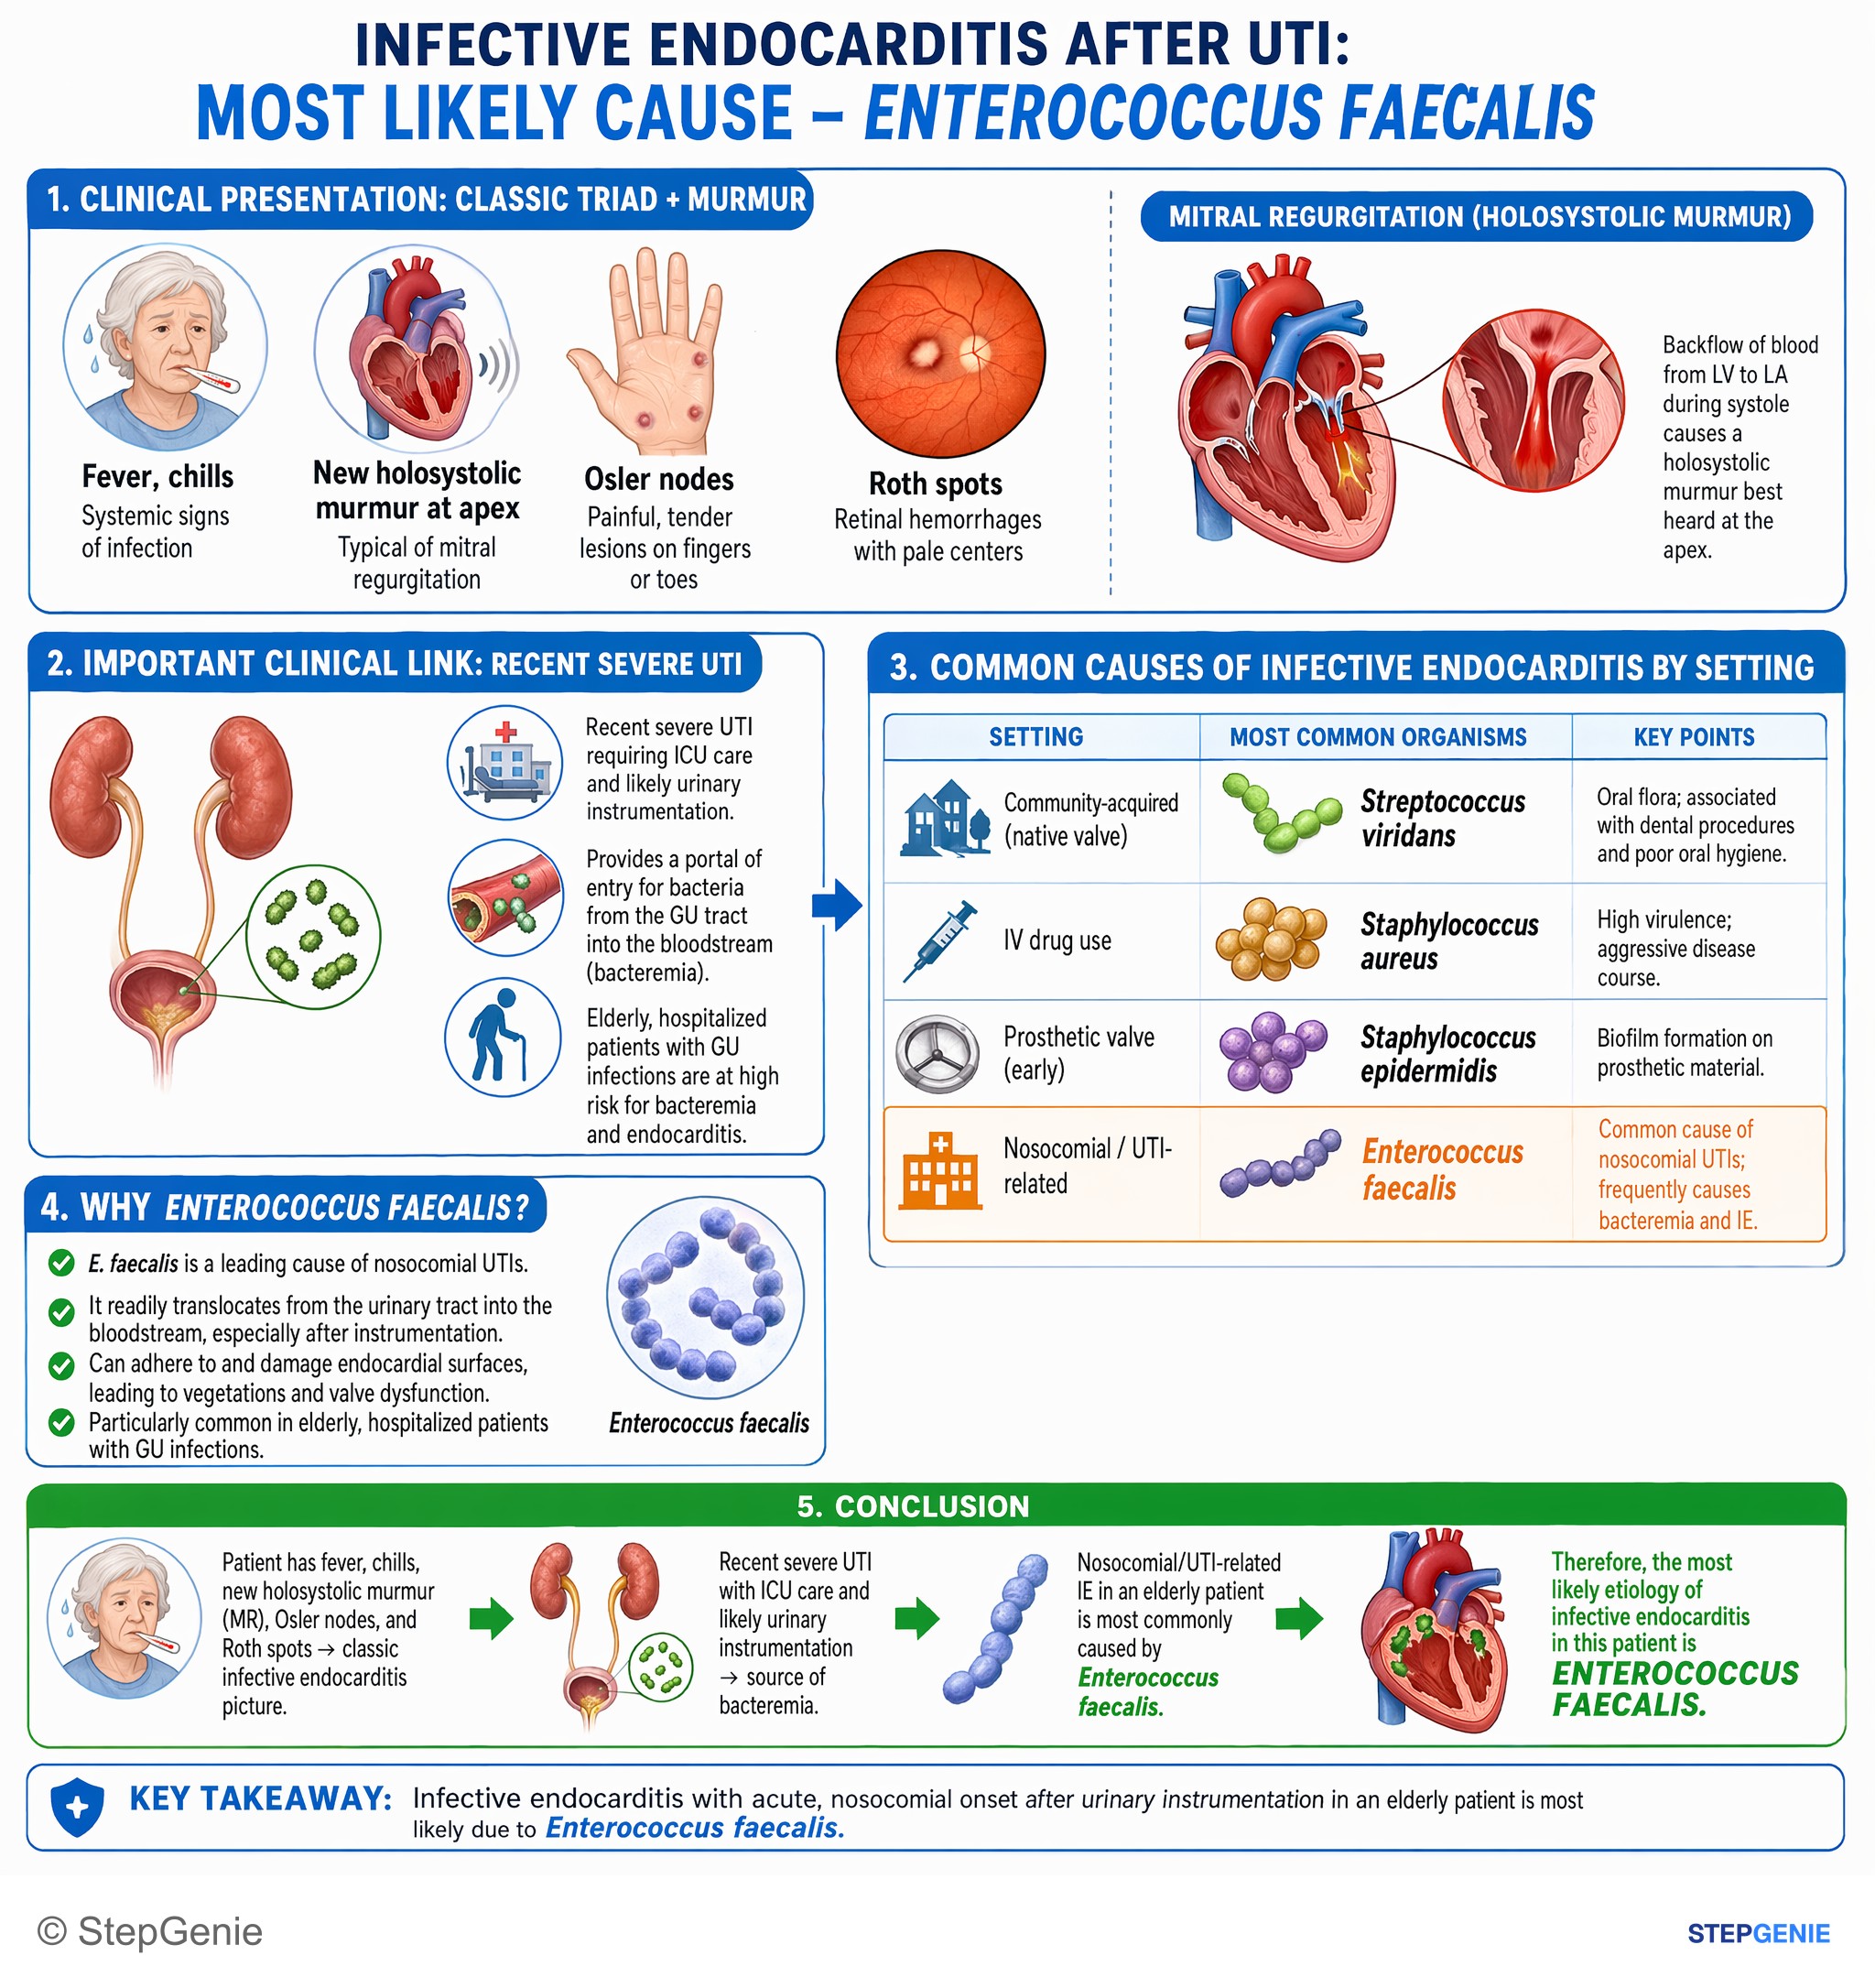
Infective endocarditis with acute, nosocomial onset after urinary instrumentation in an elderly patient is most likely due to Enterococcus…
USMLE Step 1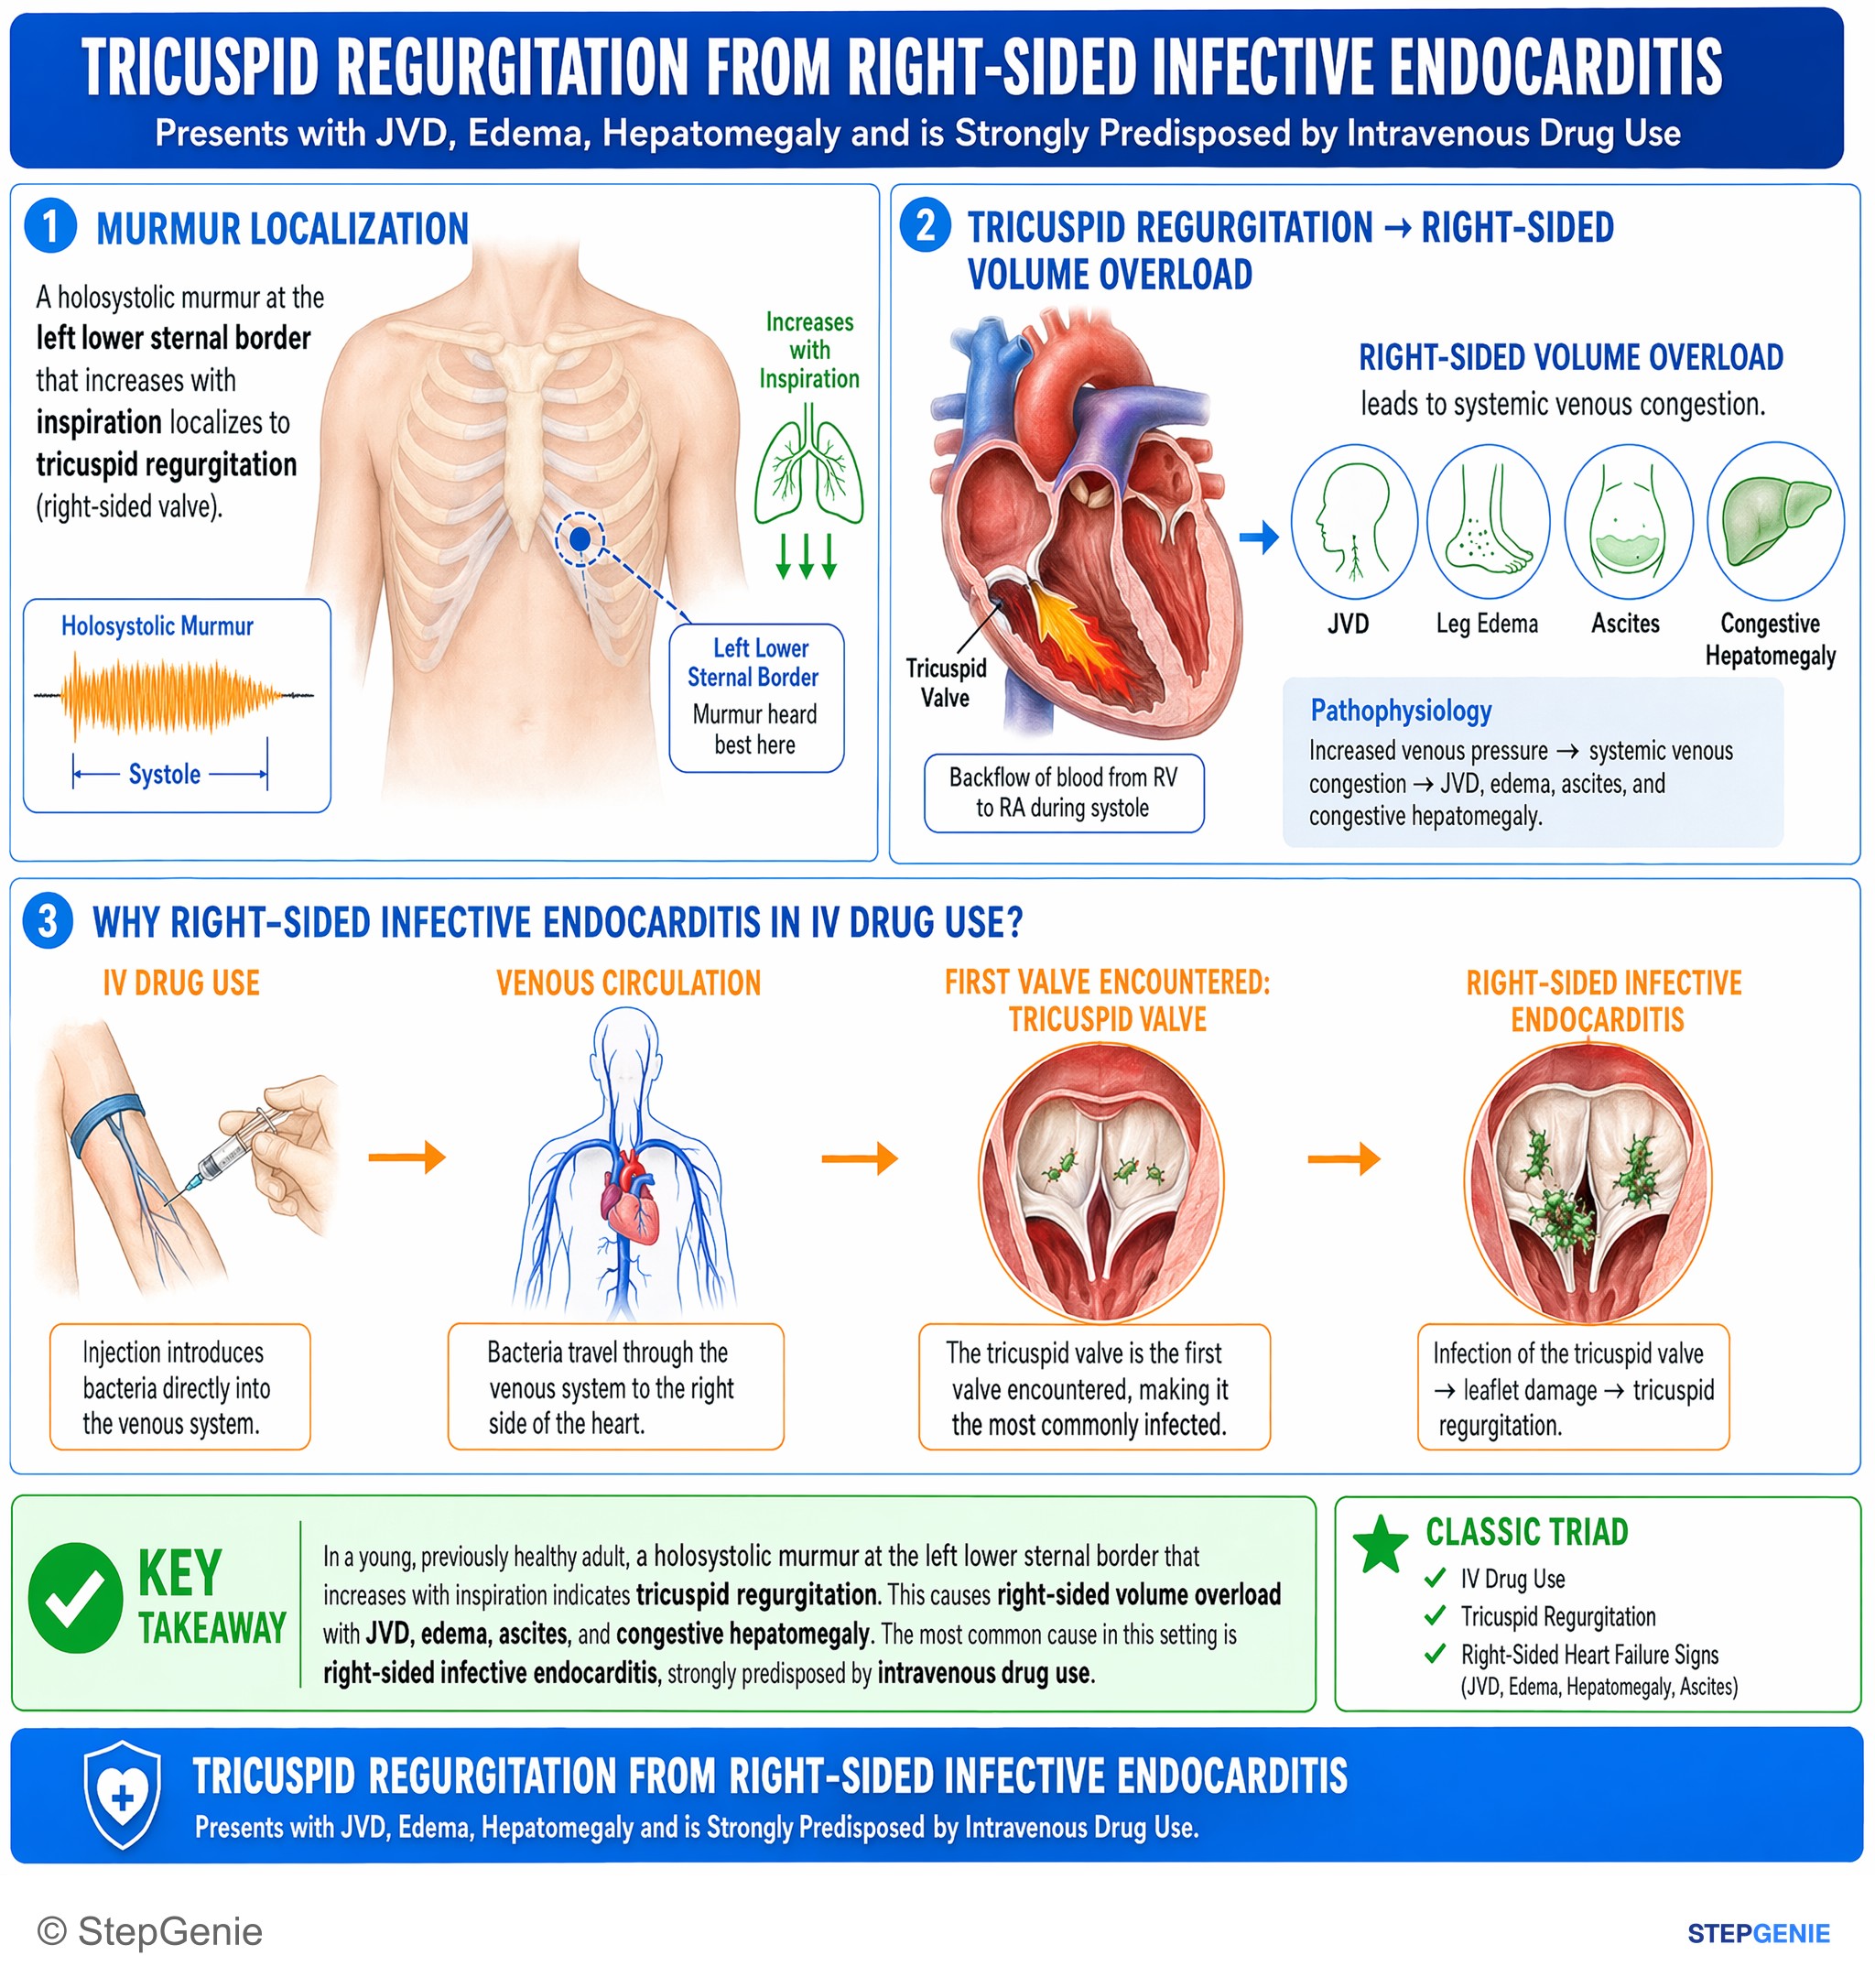
Tricuspid regurgitation from right-sided infective endocarditis presents with JVD, edema, hepatomegaly; strongly predisposed by…
USMLE Step 1Frequently Asked Questions
What is the most likely organism in an IV drug user with acute fever and a new tricuspid regurgitation murmur?
The most likely organism is Staphylococcus aureus. In an IV drug user, infective endocarditis classically involves the right side of the heart, especially the tricuspid valve. An acute presentation over days with high fever and a toxic appearance points to a high-virulence organism, and S. aureus is the classic cause of acute, destructive tricuspid valve endocarditis in this setting.
Why does a holosystolic murmur at the LLSB that gets louder with inspiration suggest tricuspid endocarditis?
A holosystolic murmur at the left lower sternal border that increases with inspiration suggests tricuspid regurgitation. In the setting of infective endocarditis, that localizes the infection to the tricuspid valve, which is the classic right-sided valve involved in IV drug use. This is a key clue that helps distinguish right-sided infective endocarditis from other causes of fever and murmur.
How do you tell acute Staphylococcus aureus endocarditis from subacute viridans streptococci endocarditis?
The main distinction is tempo and setting. Staphylococcus aureus causes an acute, destructive illness over days and can infect normal valves, making it the classic organism in IV drug users. Viridans streptococci usually cause a subacute illness over weeks, often after dental procedures or in patients with preexisting valve disease, and are not the classic cause of right-sided disease in IV drug use.
When should you think Staphylococcus epidermidis instead of Staphylococcus aureus in endocarditis?
You should think of Staphylococcus epidermidis when endocarditis occurs on a prosthetic valve or indwelling device, especially early after valve replacement. Unlike S. aureus, S. epidermidis is less virulent and classically causes a more subacute presentation. Its key microbiology clue is biofilm formation on foreign material, which helps it persist on prosthetic surfaces and evade host defenses and antibiotics.
What complications are classic for right-sided infective endocarditis?
The classic complication of right-sided infective endocarditis is septic pulmonary emboli. When the tricuspid valve is involved, infected material embolizes to the lungs rather than the systemic circulation. This can cause pleuritic chest pain, cough, hemoptysis, and nodular infiltrates. This pattern helps distinguish right-sided disease from left-sided endocarditis, which causes systemic embolic events such as stroke or splenic infarcts.