Adult = AD; baby = AR. ADPKD (autosomal dominant; PKD1 on chromosome 16 or PKD2 on chromosome 4) shows up in adults with hypertension, flank pain, hematuria and big, bilateral cystic kidneys, plus liver cysts and berry aneurysms that can rupture into a subarachnoid hemorrhage. ARPKD (autosomal recessive; PKHD1, which encodes fibrocystin) shows up in the fetus or newborn with huge echogenic kidneys, oligohydramnios leading to pulmonary hypoplasia (a Potter-like sequence) and congenital hepatic fibrosis leading to portal hypertension. The one-line tiebreaker: liver cysts = ADPKD; liver fibrosis = ARPKD.
The 10-second mnemonic: "ADULT = AD; BABY = AR"
Visual hook. Picture a hospital hallway:
- A hypertensive ADULT holding a berry (brain aneurysm) and pointing at a liver full of cysts → ADPKD.
- A BABY with a big belly (huge kidneys) and tiny lungs, next to a sign reading "hepatic fibrosis" → ARPKD.
Mini-mnemonics for flashcards:
- A.D. = Aneurysm + Dominant: an adult with a berry aneurysm and an affected parent. About 90% of patients inherit ADPKD from a parent; about 10% have a new (de novo) variant.
- A.R. = A Respiratory-risk baby: the severe newborn form can be fatal because of pulmonary hypoplasia, and Recessive goes with hepatic fibRosis.
ADPKD vs ARPKD at a glance
| Feature | ADPKD | ARPKD |
|---|---|---|
| Genes | PKD1 (chromosome 16, polycystin-1; most families) or PKD2 (chromosome 4, polycystin-2; about 15%) | PKHD1 (fibrocystin); rarely DZIP1L |
| How common | About 1 in 1,000 people | About 1 in 20,000 children (estimates range from 1 in 10,000 to 1 in 40,000) |
| Typical age | Adults; symptoms often start before 30; kidney failure usually after the fourth decade | Before birth or in the newborn period; some present later in childhood |
| Kidneys | Bilateral enlarged kidneys; cysts arise from tubule segments and enlarge with age | Bilateral enlarged, echogenic kidneys with small cysts from dilated collecting ducts |
| Liver | Liver cysts in most adults (more than 80% by age 30); liver function usually normal | Congenital hepatic fibrosis in every case, usually present at birth; can lead to portal hypertension |
| Brain and vessels | Intracranial (berry) aneurysms, about 10% overall | Not a classic feature |
| Other clues | Colonic diverticula, abdominal wall and inguinal hernias, kidney stones, valve disease | Oligohydramnios, pulmonary hypoplasia, hypertension in most children, growth failure |
| Outlook | Kidney failure in 35–45% by age 60; PKD1 truncating variants reach it in the 50s, PKD2 in the 70s | About 30% of affected newborns die within the first week of life; survivors often reach kidney failure before adulthood |
Why the cysts form and what they do
ADPKD. Polycystin-1 and polycystin-2 work in the primary cilia of tubular cells, which sense urine flow; polycystin-2 appears to act as an ion channel. When they fail, tubule segments dilate, separate from the nephron and fill with secreted fluid. Vasopressin drives cyst growth through cyclic AMP, which is why the V2-receptor blocker tolvaptan slows the disease. As cysts expand they compress renal vessels, causing intrarenal ischemia that activates the renin-angiotensin-aldosterone system; that is why hypertension is common and often appears early, and why ACE inhibitors and ARBs are first line. Polycystic liver disease develops earlier and is more severe in women, and estrogen exposure (estrogen-containing contraceptives or replacement therapy) is linked to larger, faster-growing liver cysts. Anemia is less common than in other chronic kidney disease, because erythropoietin production is relatively preserved.
ARPKD. It is a ciliopathy: fibrocystin sits in the primary cilia of renal tubular cells, and the disease affects both kidney and liver. The kidneys fill with dilated collecting ducts, kidney function falls before birth, and oligohydramnios leads to pulmonary hypoplasia and the compressed facies and limb findings of a Potter-like sequence. The liver lesion, congenital hepatic fibrosis, is usually present at birth and can lead to portal hypertension with splenomegaly, hypersplenism and varices; it is fibrosis, not liver cysts. For the portal hypertension side, see this cirrhosis and portal hypertension review.
How each one shows up in a stem
- ADPKD: a 20- to 40-year-old with new hypertension, flank pain, gross hematuria, recurrent UTIs or stones, bilateral flank masses and a parent on dialysis. The extrarenal hook is a "worst headache of my life" from a ruptured berry aneurysm, often in a relative. Review the bleed itself in this hemorrhagic stroke (ICH and SAH) guide.
- ARPKD: a prenatal ultrasound with enlarged echogenic kidneys and oligohydramnios, or a newborn in respiratory distress with huge flank masses and hypertension. An older child presents with splenomegaly or variceal bleeding from portal hypertension caused by hepatic fibrosis.
Diagnosis
- ADPKD in someone with an affected parent (KDIGO 2025 ultrasound criteria): at least 3 cysts in total at age 15–39, 2 or more in each kidney at 40–59 and 4 or more in each kidney at 60 or older. MRI is more sensitive: more than 10 cysts confirms the diagnosis at ages 16–40.
- Genetic testing is reserved for patients with no family history, equivocal imaging, or a young relative being evaluated as a kidney donor.
- ARPKD is diagnosed by ultrasound, often before birth: enlarged, echogenic kidneys and signs of liver fibrosis.
Management (Step 2 CK depth, KDIGO 2025 for ADPKD)
- Blood pressure: an ACE inhibitor or ARB first line (not both together). For ages 18–49 with preserved kidney function and BP above 130/85, KDIGO recommends a home target of 110/75 mm Hg or lower if tolerated.
- Water and salt: at least 2–3 L of water a day when eGFR is 30 or more, and a low-sodium diet. Water suppresses vasopressin.
- Tolvaptan (V2-receptor antagonist): for adults with eGFR of 25 or more who are at risk of rapid progression, judged mainly by the Mayo imaging class (1C–1E). It causes thirst and polyuria and can injure the liver, so liver tests are checked monthly for 18 months and then every 3 months.
- Aneurysm screening: time-of-flight MR angiography without gadolinium for patients with a personal history of SAH or a family history of aneurysm, SAH or unexplained sudden death, not for everyone. Smoking and uncontrolled BP are modifiable risk factors for aneurysm formation and rupture.
- Kidney failure: dialysis or transplantation; ADPKD does not recur in the graft. Track the decline with the CKD stages by GFR mnemonic.
- ARPKD: ventilatory support for newborns, antihypertensives, dialysis (peritoneal dialysis is preferred in children) and transplantation, sometimes a combined liver-kidney transplant.
Look-alikes on the answer list
| Answer choice | Key clue | Why it is not PKD |
|---|---|---|
| Simple kidney cysts | Older adult with one or a few cysts | Common with aging; low risk of CKD or hypertension |
| Acquired cystic kidney disease | Years of dialysis | Multiple cysts with long-term dialysis, usually after more than 10 years; high risk of renal cell carcinoma |
| Multicystic dysplastic kidney | Newborn with a unilateral cystic mass | A nonreniform mass of cysts and connective tissue with no functioning kidney tissue |
| Medullary sponge kidney | Adult with stones and nephrocalcinosis | Dilated papillary collecting ducts; linked to type 1 RTA; does not usually cause kidney failure |
| Tuberous sclerosis or von Hippel-Lindau disease | Skin, brain or retinal lesions | Angiomyolipomas (tuberous sclerosis); cysts with renal cell carcinoma, hemangioblastomas and pheochromocytoma (VHL) |
Exam traps
- Hepatic cysts ≠ hepatic fibrosis. Cysts mean ADPKD; fibrosis with portal hypertension means ARPKD.
- Liver cysts rarely cause liver failure. Pick pain or infection as their complications, not hepatic insufficiency.
- ADPKD does not raise the risk of renal cell carcinoma; acquired cystic disease on long-term dialysis does.
- Mitral valve prolapse is the classic board association, but KDIGO 2025 notes that newer studies using current criteria find it in about 3% of adults with ADPKD, similar to the general population.
- Don't screen every ADPKD patient for aneurysms. Screen with a personal or family history of aneurysm, SAH or sudden death.
- Both diseases enlarge the kidneys, so size alone doesn't decide it; age and the liver finding do.
Worked example
Vignette. A 34-year-old man with 3 years of hypertension has intermittent right flank pain and one episode of gross hematuria. His father had kidney cysts, started dialysis at 50 and died suddenly of a "brain bleed" at 54. BP is 152/94 mm Hg, and both flanks have palpable masses. Creatinine is 1.1 mg/dL. Ultrasound shows enlarged kidneys with innumerable bilateral cysts and several liver cysts. Which additional test is indicated?
Answer: Time-of-flight MR angiography of the brain to screen for an intracranial aneurysm. He meets the ultrasound criteria for ADPKD, and a family history of a brain bleed or sudden death is an indication for screening under KDIGO 2025. His blood pressure should be treated with an ACE inhibitor or ARB, and his Mayo imaging class should be checked to see whether he qualifies for tolvaptan.
Why the distractors are wrong:
- Genetic testing for PKD1 and PKD2: not needed, because imaging plus family history already establishes the diagnosis.
- Contrast CT to screen for renal cell carcinoma: ADPKD does not increase kidney cancer risk.
- Liver biopsy for the cysts: liver cysts usually leave liver function intact.
- Evaluation for portal hypertension and varices: that is congenital hepatic fibrosis, the ARPKD liver lesion.
Key takeaways
- Adult = AD; baby = AR.
- ADPKD: PKD1 (chromosome 16) or PKD2 (chromosome 4); hypertension from RAAS activation; liver cysts; berry aneurysms (about 10%); diverticula, hernias and stones.
- ARPKD: PKHD1 (fibrocystin); dilated collecting ducts; oligohydramnios with pulmonary hypoplasia; congenital hepatic fibrosis with portal hypertension.
- KDIGO 2025: ACE inhibitor or ARB, target BP of 110/75 or lower in younger adults, 2–3 L of water a day, tolvaptan for rapid progressors and aneurysm screening mainly for those with a personal or family history.
Sources
- Executive summary of the KDIGO 2025 Clinical Practice Guideline for ADPKD — Kidney International
- KDIGO 2025 ADPKD Guideline Key Takeaways: Therapies to Delay the Progression of Kidney Disease — KDIGO
- Autosomal Dominant Polycystic Kidney Disease (ADPKD) — Merck Manual Professional Edition
- Overview of Cystic Kidney Disease — Merck Manual Professional Edition
- Autosomal Recessive Polycystic Kidney Disease — NIDDK
- Polycystic Kidney Disease — MedlinePlus Genetics
- PKHD1 Gene — MedlinePlus Genetics
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
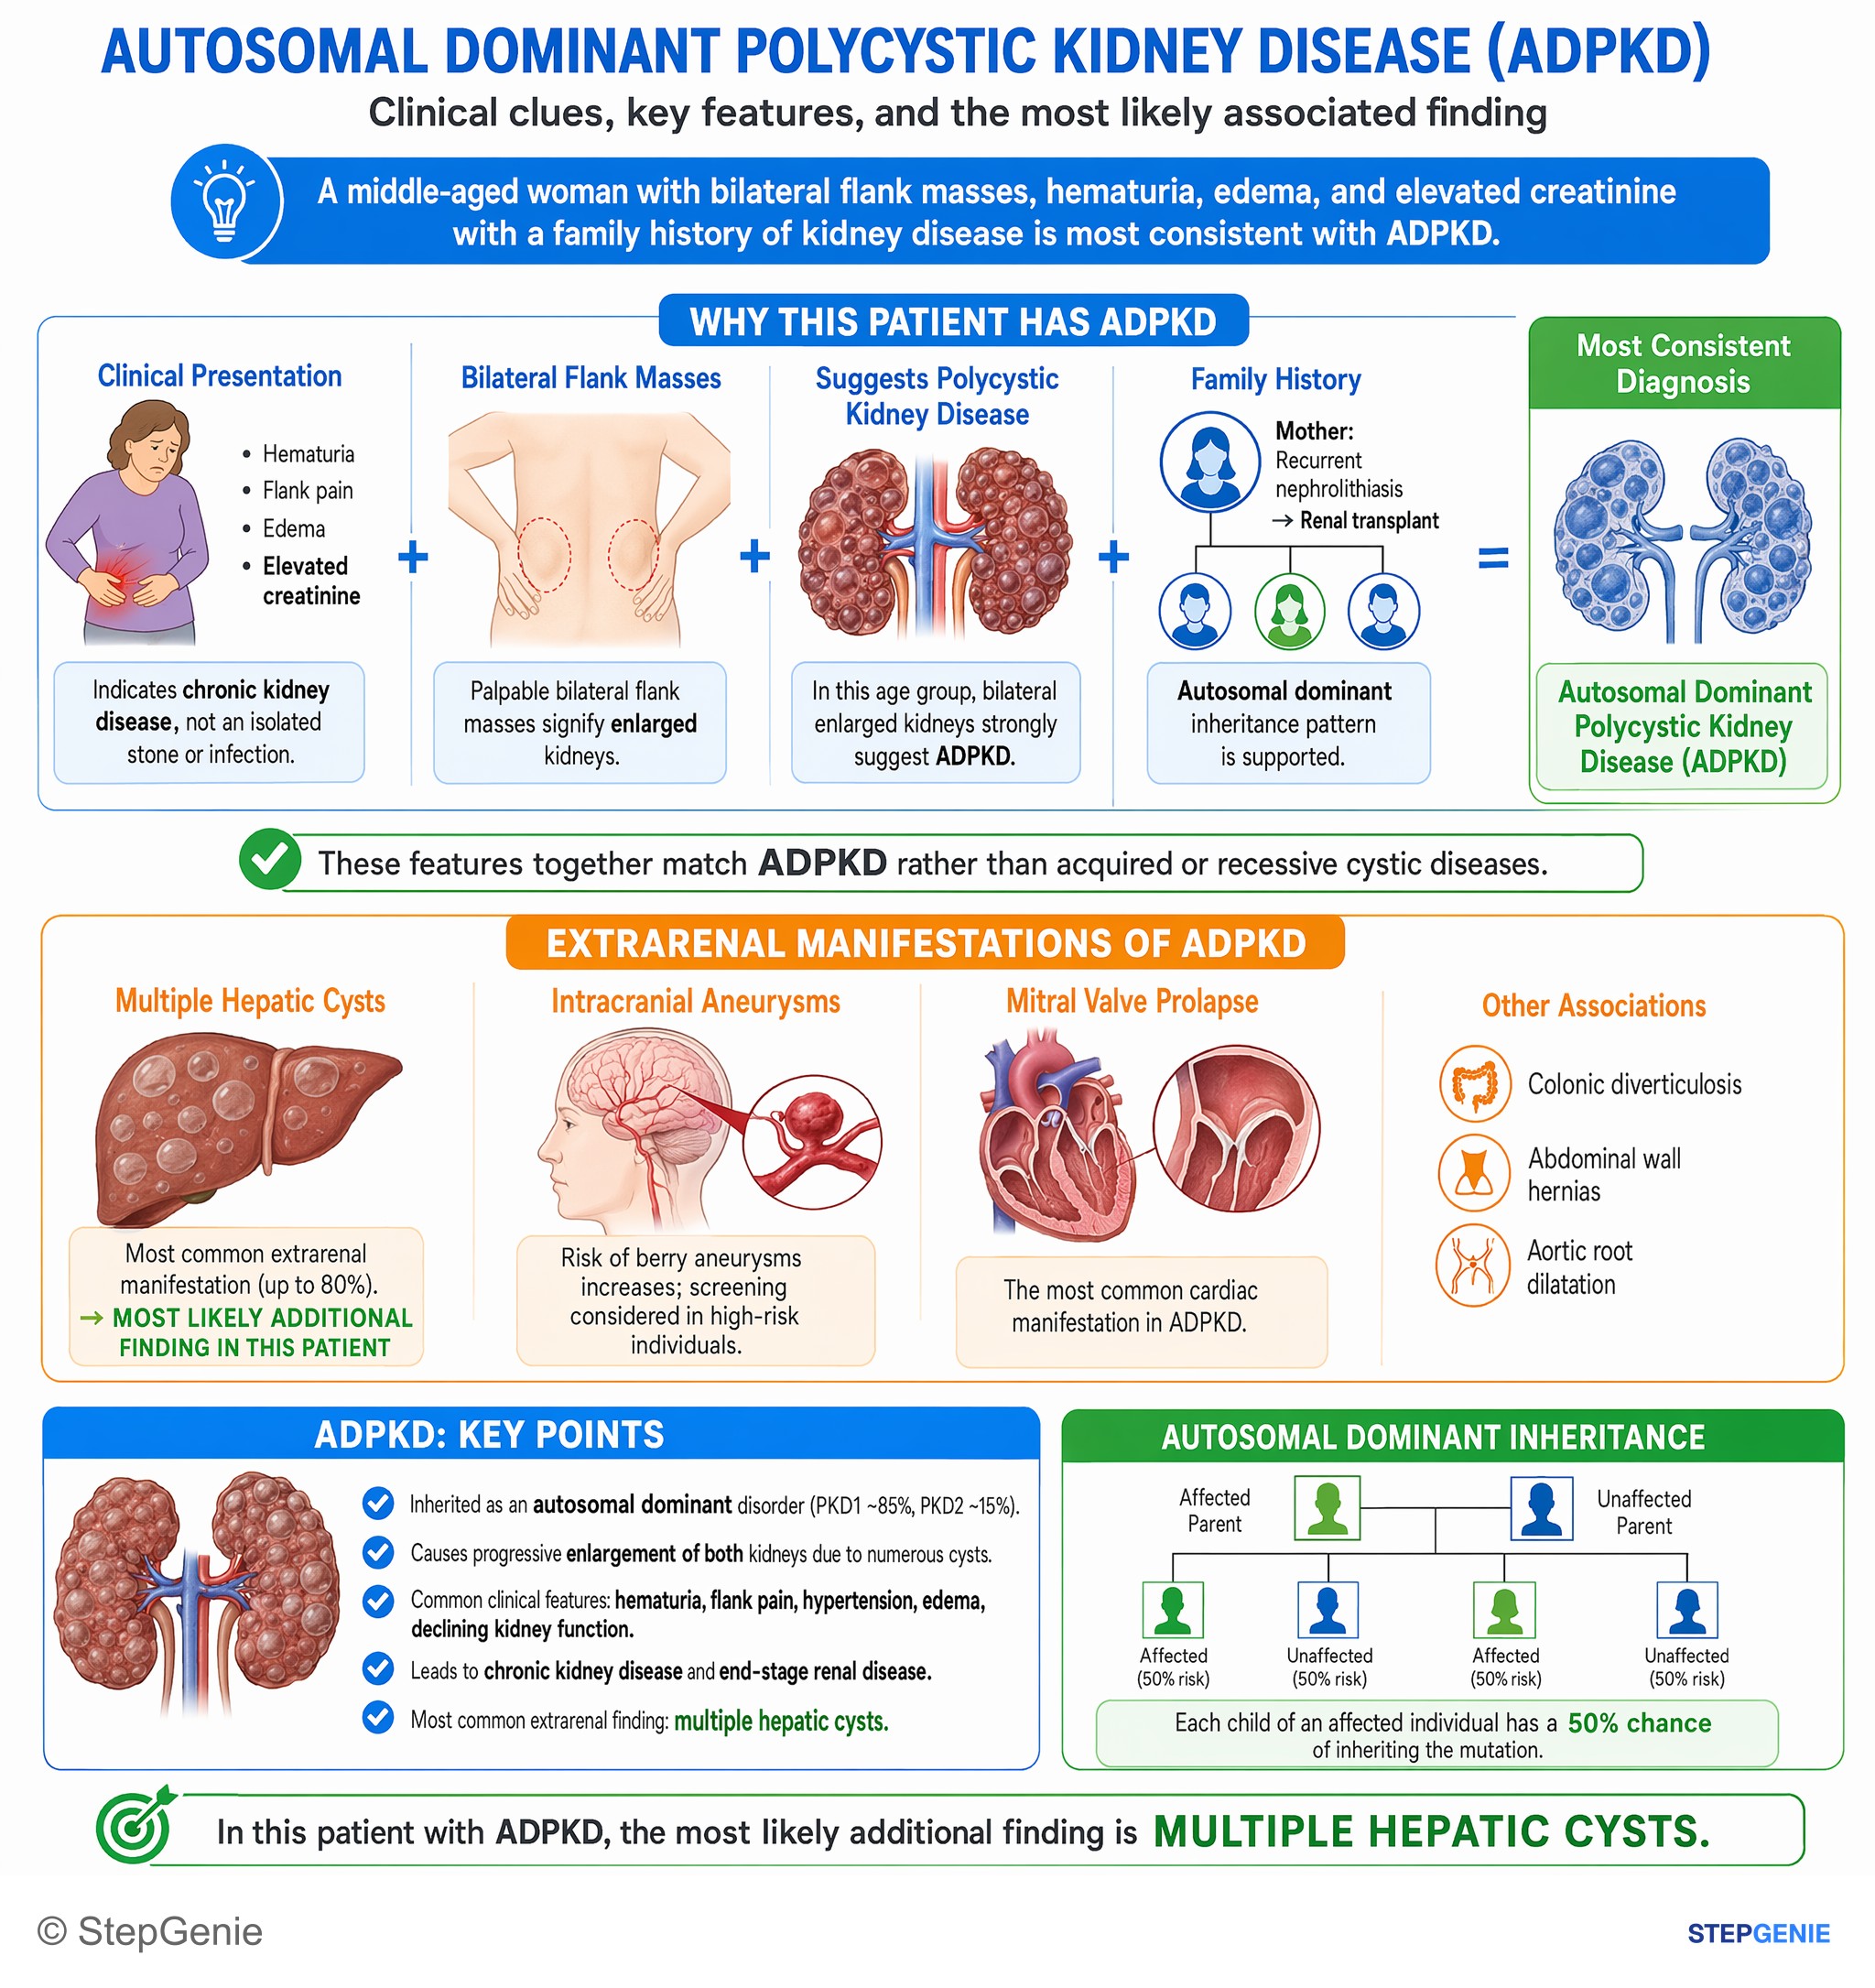
Autosomal dominant polycystic kidney disease causes bilateral renal enlargement, hematuria, renal failure, and is commonly associated with…
USMLE Step 1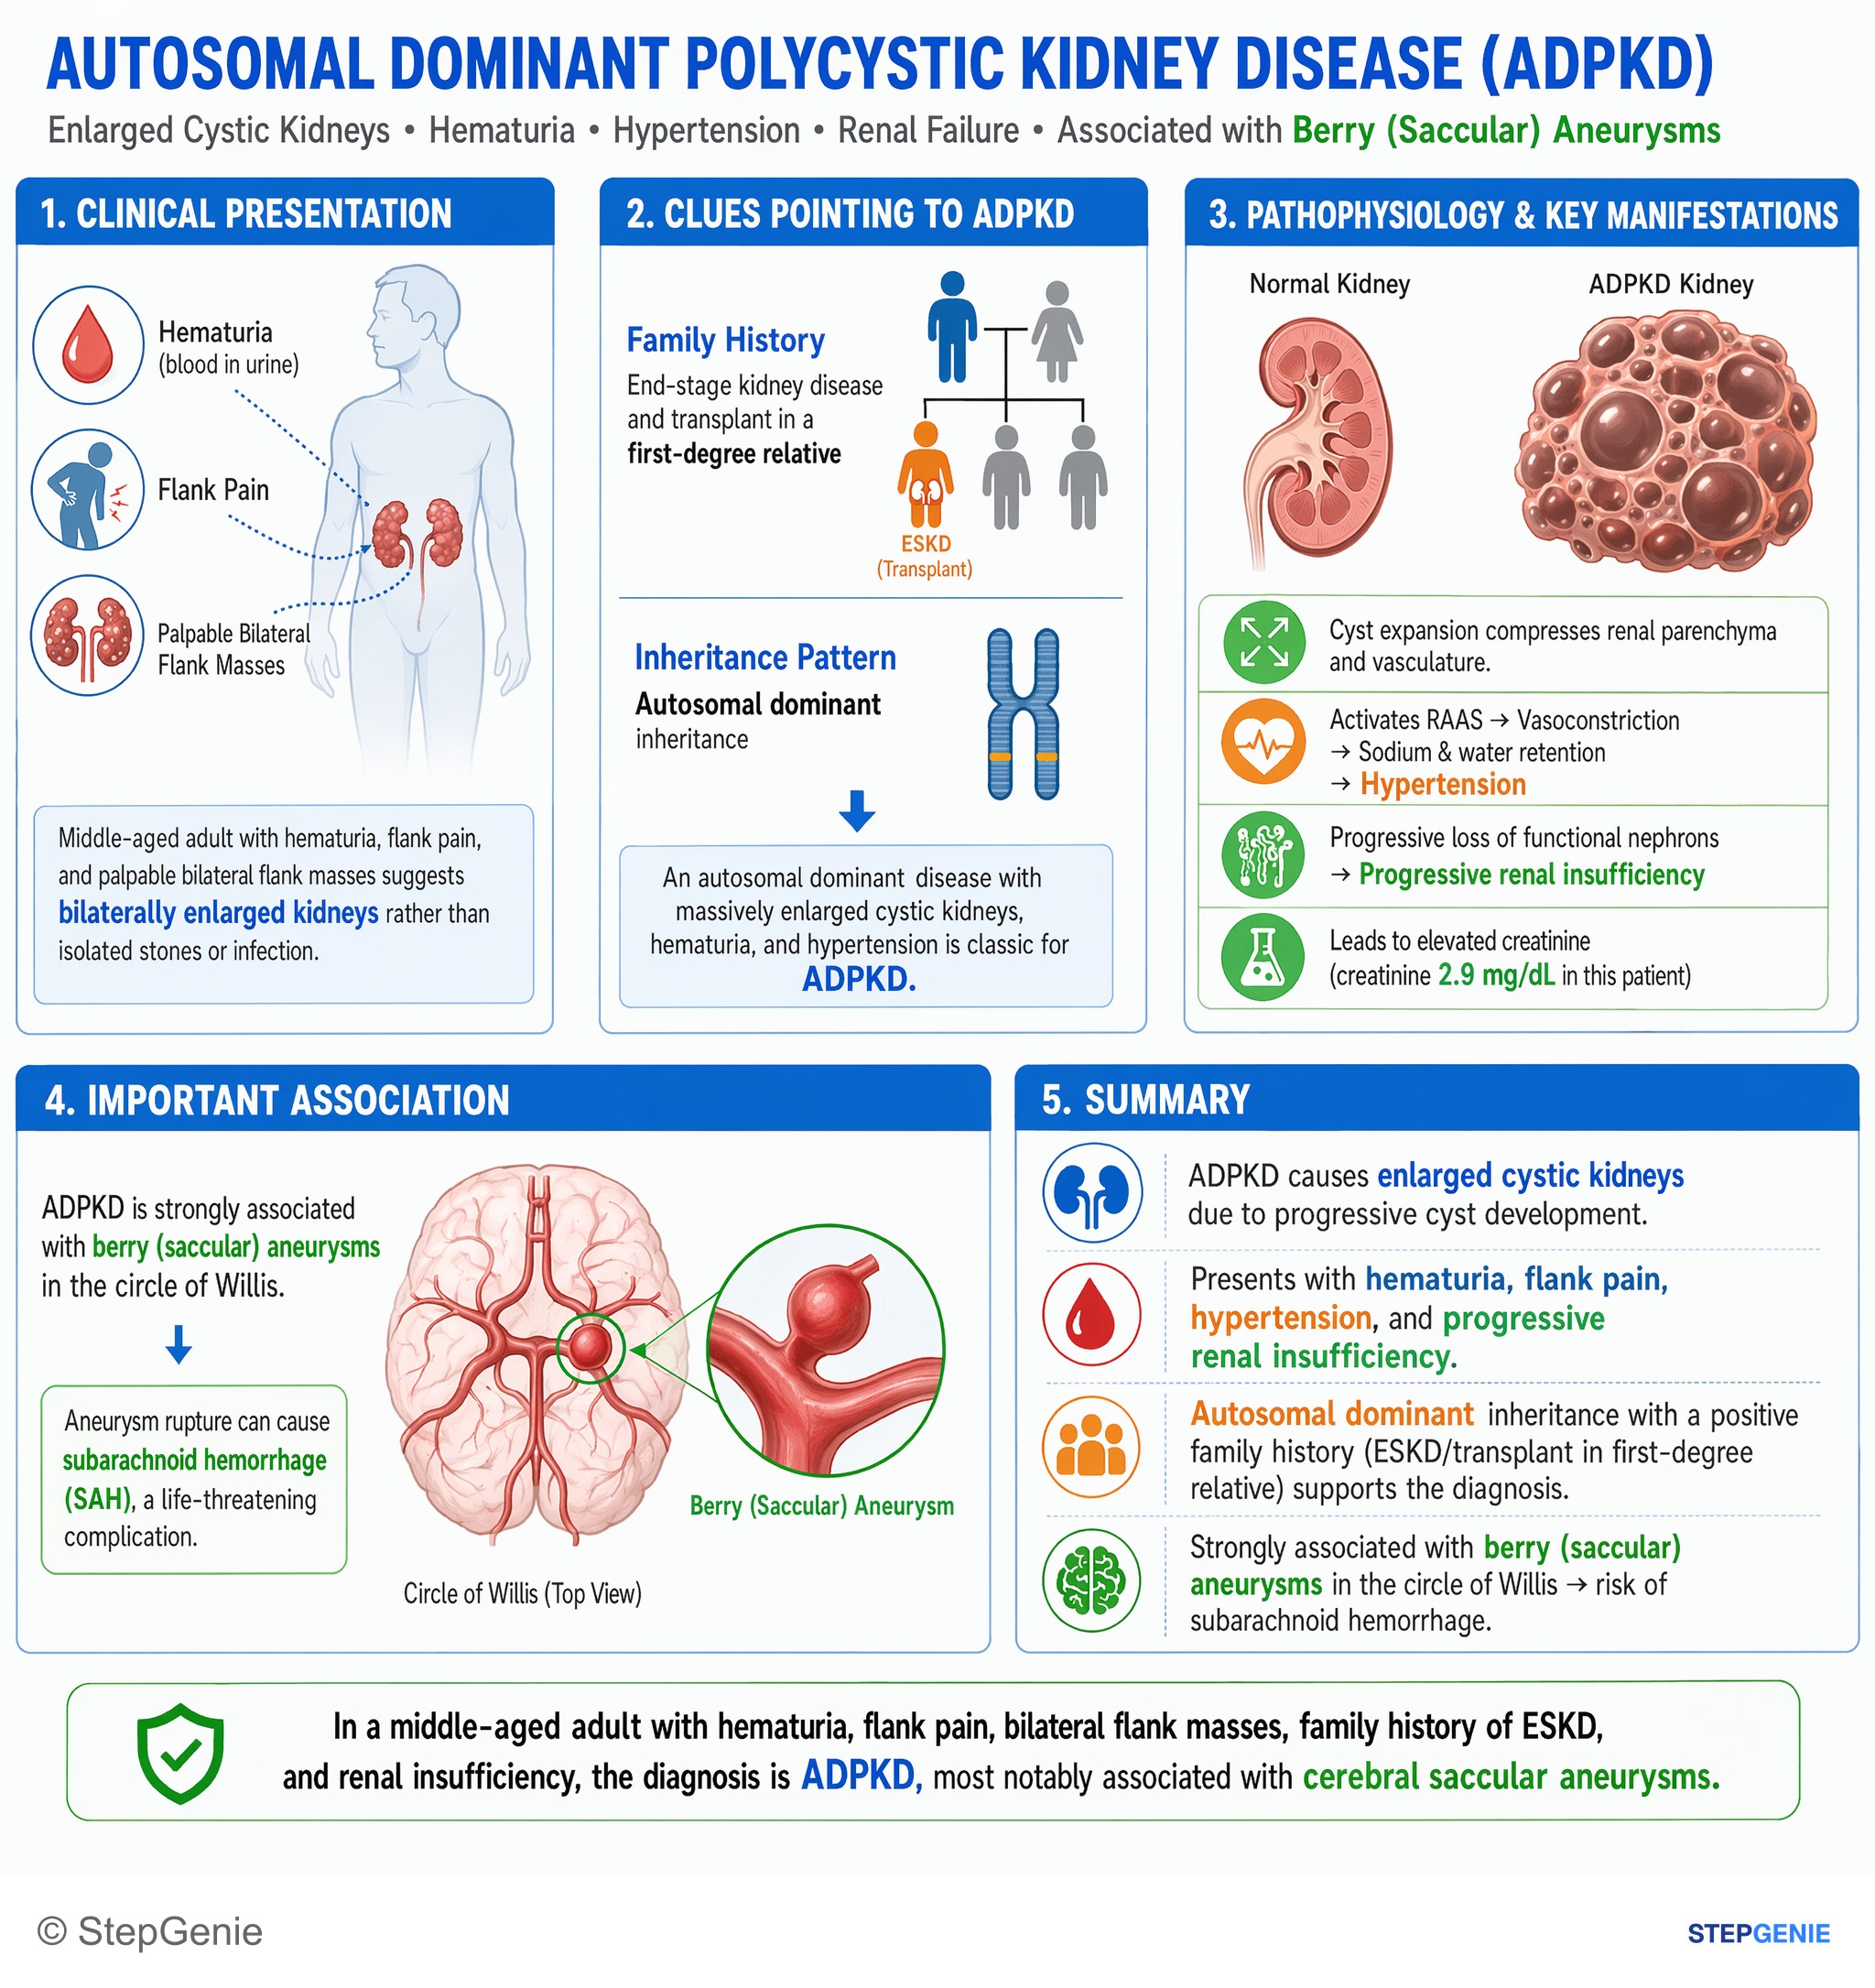
Autosomal dominant polycystic kidney disease (ADPKD) causes enlarged cystic kidneys, hematuria, HTN, renal failure, and is associated with…
USMLE Step 2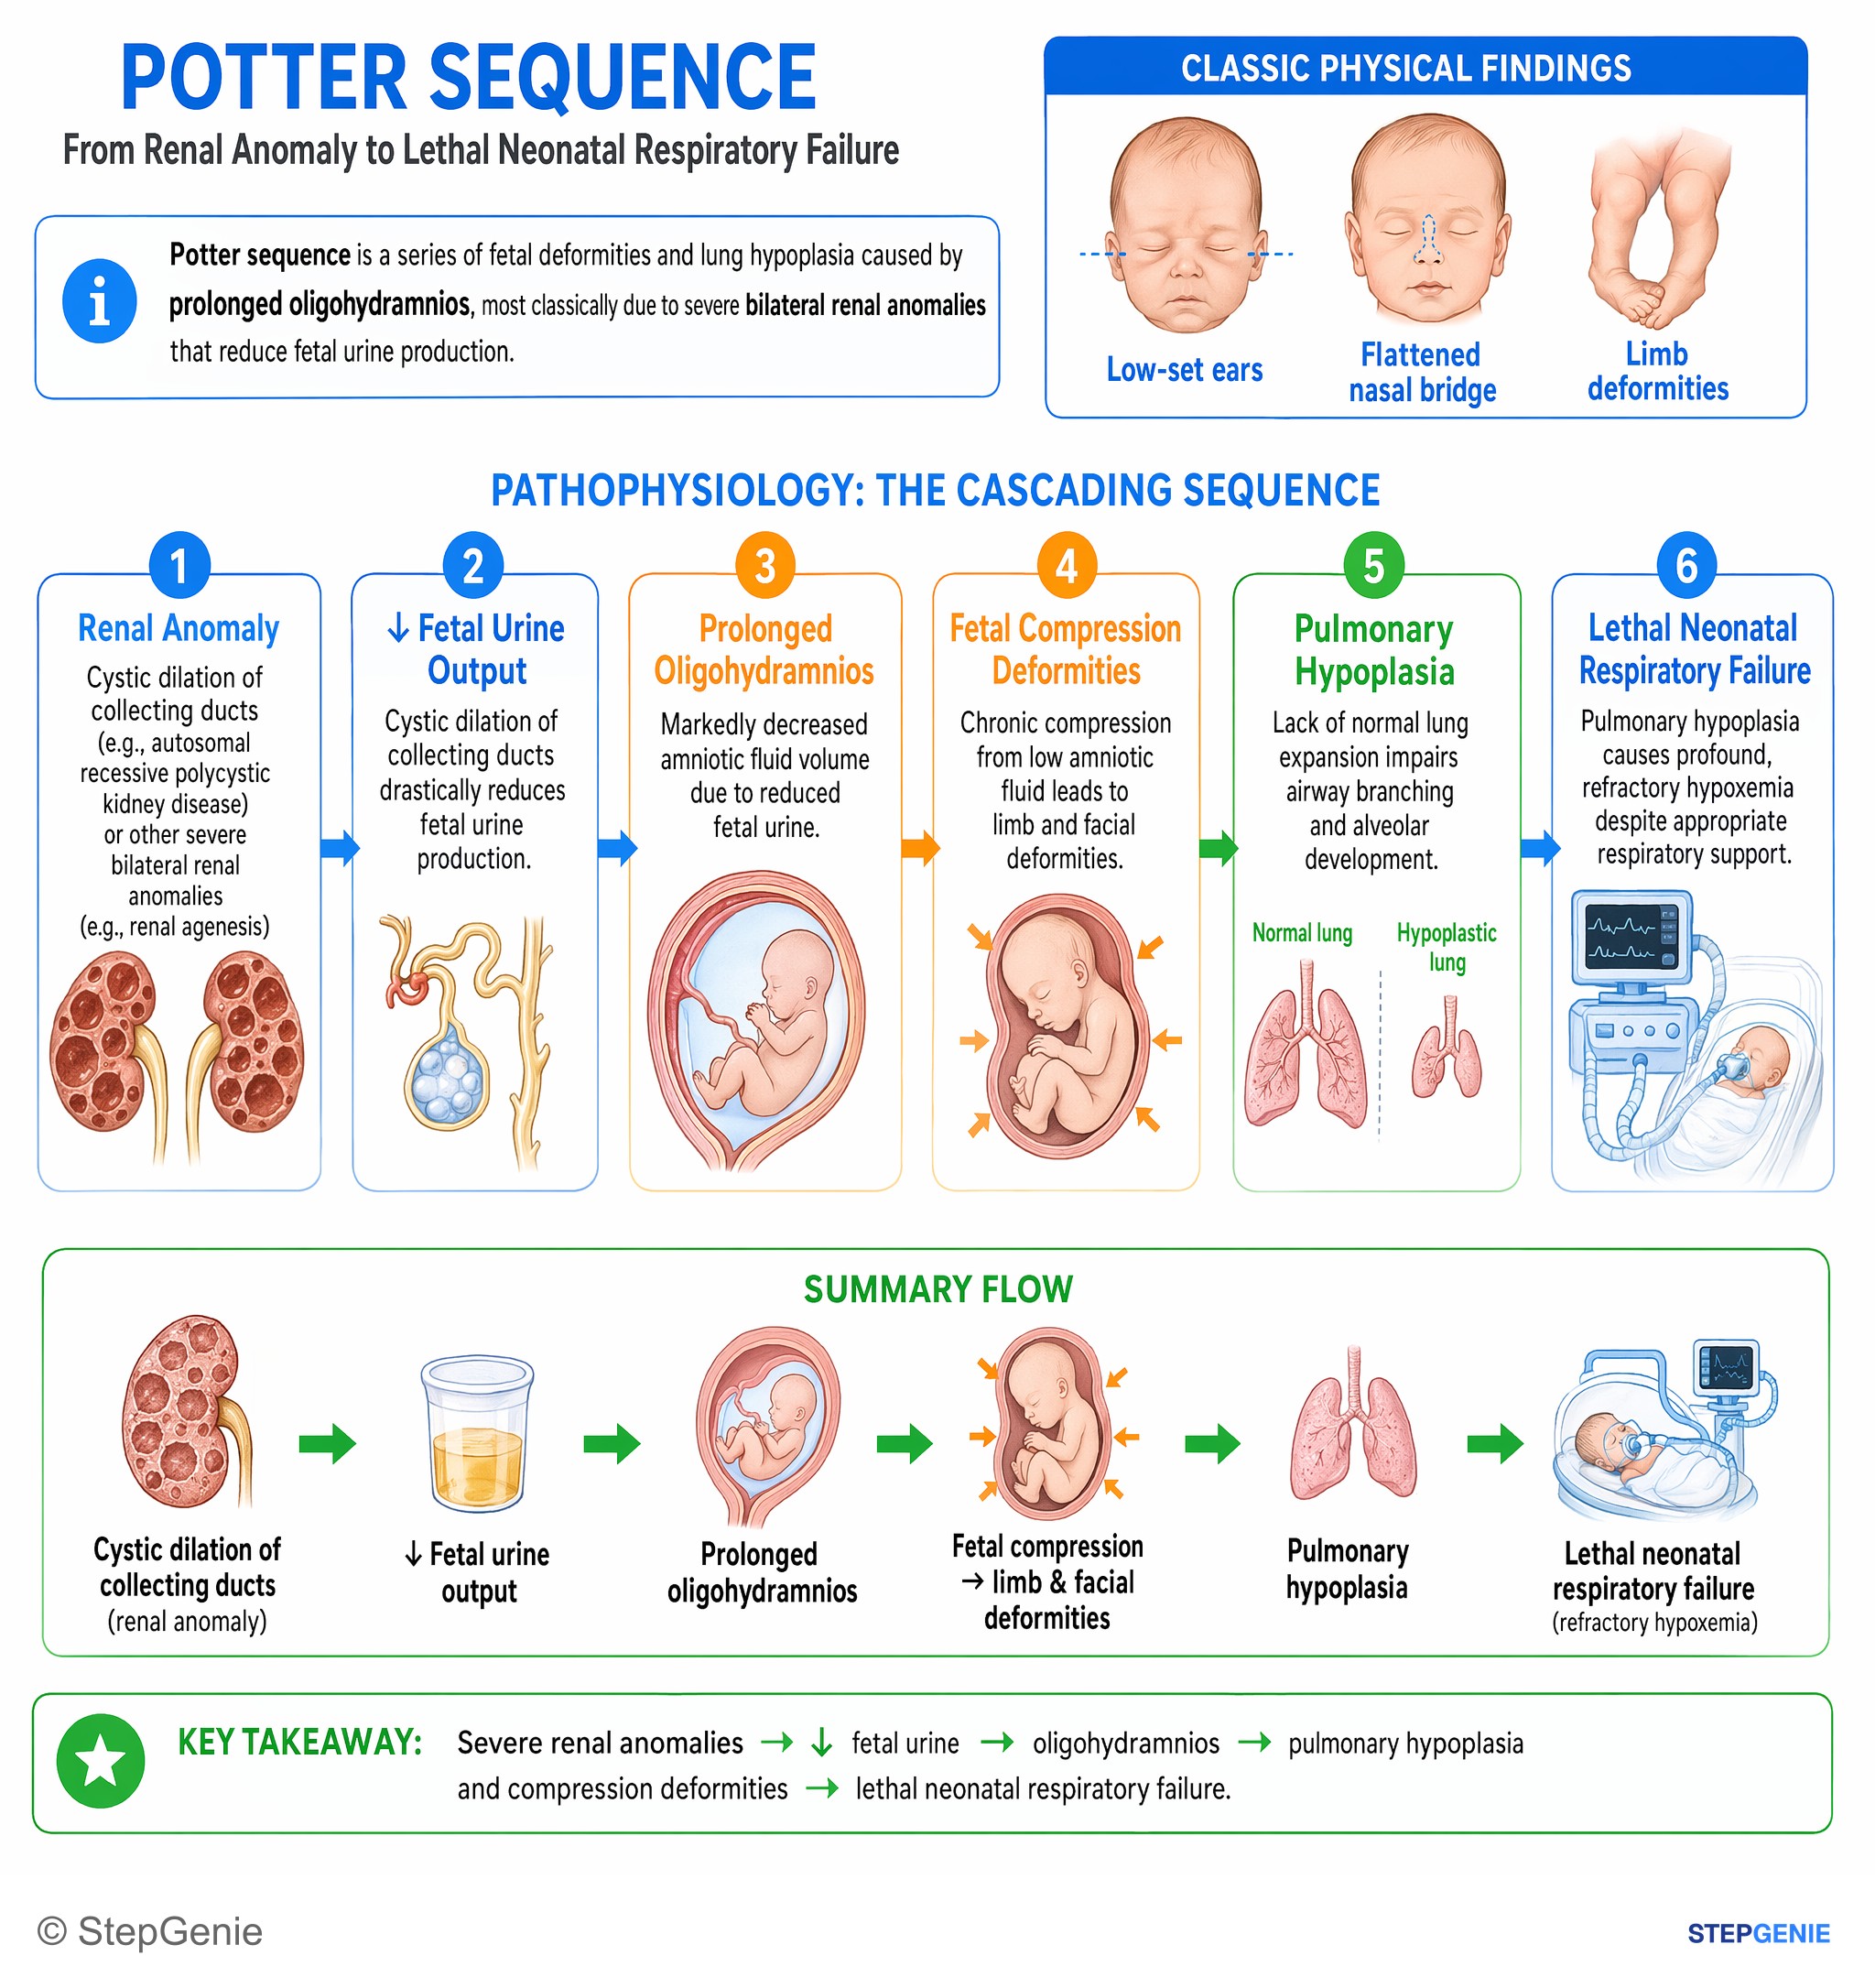
Potter sequence from severe renal anomaly → oligohydramnios → pulmonary hypoplasia → lethal neonatal respiratory failure with limb and…
USMLE Step 1Frequently Asked Questions
How do you tell ADPKD from ARPKD on a USMLE question?
Start with age and the liver. ADPKD presents in adults, usually with hypertension, flank pain, hematuria and bilateral cystic kidneys, often with liver cysts, berry aneurysms and an affected parent. ARPKD presents before birth or in infancy with enlarged echogenic kidneys, oligohydramnios and pulmonary hypoplasia, and it always comes with congenital hepatic fibrosis, which can cause portal hypertension. Kidney size alone does not separate them, because both enlarge the kidneys.
Why does ADPKD cause hypertension?
As cysts expand, they compress renal vessels and create areas of intrarenal ischemia, which activate the renin-angiotensin-aldosterone system. Hypertension is common and often appears early in ADPKD, and it predicts faster kidney decline and raises aneurysm risk. KDIGO 2025 recommends an ACE inhibitor or ARB as first-line treatment and, for adults aged 18 to 49 with preserved kidney function, a home blood pressure target of 110/75 mm Hg or lower if tolerated.
What extrarenal findings point to ADPKD instead of ARPKD?
ADPKD brings liver cysts, intracranial berry aneurysms, colonic diverticula, abdominal wall and inguinal hernias, kidney stones and heart valve disease. Mitral valve prolapse is the classic board association, although newer studies find it about as often as in the general population. ARPKD instead brings congenital hepatic fibrosis with portal hypertension, splenomegaly and varices, plus oligohydramnios and pulmonary hypoplasia in the newborn. Liver cysts point to ADPKD; liver fibrosis points to ARPKD.
Why can ARPKD cause respiratory distress in a newborn?
In severe ARPKD, kidney function is poor before birth, so amniotic fluid falls (oligohydramnios). Without enough amniotic fluid the lungs do not develop normally, causing pulmonary hypoplasia, and fetal compression produces Potter-like facial and limb findings. The huge kidneys can also press on the lungs. Breathing failure is the main reason about 30% of affected newborns die within the first week of life.
Which patients with ADPKD should be screened for brain aneurysms?
KDIGO 2025 recommends screening people with ADPKD who have a personal history of subarachnoid hemorrhage or a family history of intracranial aneurysm, subarachnoid hemorrhage or unexplained sudden death, provided they would be eligible for treatment. The test of choice is time-of-flight MR angiography without gadolinium, with CT angiography as an alternative. Screening can also be discussed in other settings, such as before major elective surgery or when the patient asks for it.