Calcium channel blockers (CCBs) are the classic “two-family” drug class that loves showing up in USMLE questions because they’re simple on paper—but easy to mix up in real life. If you can instantly sort dihydropyridines vs non-dihydropyridines, predict hemodynamic changes, and remember signature adverse effects, you’ll grab quick points on Step 1 and Step 2.
Tip 1: Split CCBs into “Vessels” vs “Ventricles” (the 2-family sorting trick)
The fastest way to avoid confusion is to decide what the drug “cares about” most:
Dihydropyridines = “Vessels” (arterioles)
Examples: amlodipine, nifedipine, nicardipine, felodipine, nimodipine, clevidipine
One-liner: DHPs dilate arterioles → drop afterload → reflex tachycardia.
Non-dihydropyridines = “Ventricles” (and nodes)
Examples: verapamil, diltiazem
One-liner: Non-DHPs slow the SA/AV node and decrease contractility → bradycardia + ↓ conduction.
Ultra-high-yield table (what questions are really testing)
| Feature | Dihydropyridines (e.g., amlodipine) | Non-DHPs (verapamil, diltiazem) |
|---|---|---|
| Primary target | Vascular smooth muscle | Cardiac muscle + SA/AV node |
| Main effect | ↓ SVR (afterload) | ↓ HR, ↓ AV conduction, ↓ contractility |
| Reflex tachycardia | Common (especially short-acting) | Uncommon |
| Classic uses | HTN, vasospastic angina | Rate control (AF), angina |
| Big “watch out” | Edema/flushing | Heart block, bradycardia |
Tip 2: Use the mnemonic “DHP = Drop the Pressure” (and remember reflex tachy)
Visual/Mnemonic device
Think of DHPs as opening wide the “arteriolar hydrants” → blood flows easily → pressure falls.
- DHP = Drop the Pressure
- Arteriolar dilation → ↓ afterload
- The baroreceptors notice the drop → reflex sympathetic activation
- ↑ HR (reflex tachycardia)
- ↑ contractility (can worsen demand ischemia in some settings)
USMLE-style one-liner
Short-acting DHP (like nifedipine) → big vasodilation → reflex tachycardia → can worsen angina.
Clinical pearl: Long-acting DHPs (e.g., amlodipine) have less dramatic reflex tachycardia and are favored for chronic HTN/angina management.
Tip 3: Lock in adverse effects with “A-V Block vs Ankle Swell”
Questions love asking you to match side effects to the right CCB subclass.
Non-DHP adverse effects: “A-V block + constipation (Verapamil)”
Visual hook: Picture Verapamil “verapamming” the AV node shut.
- Bradycardia
- AV block
- Worsening heart failure (negative inotropy)
- Constipation (especially verapamil)
Step trap: Avoid non-DHPs in HFrEF (reduced EF) because they decrease contractility.
DHP adverse effects: “Ankle swelling + flushing + headache”
Visual hook: Imagine arterioles dilating in the face and legs.
- Peripheral edema (ankles)
- Flushing
- Headache
- Dizziness
- Reflex tachycardia (esp. short-acting)
High-yield mechanism nugget: DHPs preferentially dilate precapillary arterioles, increasing hydrostatic pressure in capillaries → dependent edema (often without generalized fluid overload).
Quick clinical “When would you pick which?” mini-guide
- Hypertension (first-line option in many patients): often amlodipine
- Vasospastic (Prinzmetal) angina: DHP or non-DHP works; CCBs are key therapy
- Stable angina:
- DHPs: reduce afterload (↓ demand)
- Non-DHPs: reduce HR/contractility (↓ demand)
- Atrial fibrillation rate control: diltiazem or verapamil
- Subarachnoid hemorrhage vasospasm prevention: nimodipine (classic board association)
10-second recap (what to remember on test day)
- DHP = vessels → ↓ SVR → reflex tachy, edema, flushing/headache
- Verapamil/Diltiazem = heart → ↓ HR/AV conduction, constipation (verapamil), can worsen HFrEF
- If the question is about rate control, think non-DHP; if it’s about afterload reduction/HTN, think DHP.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
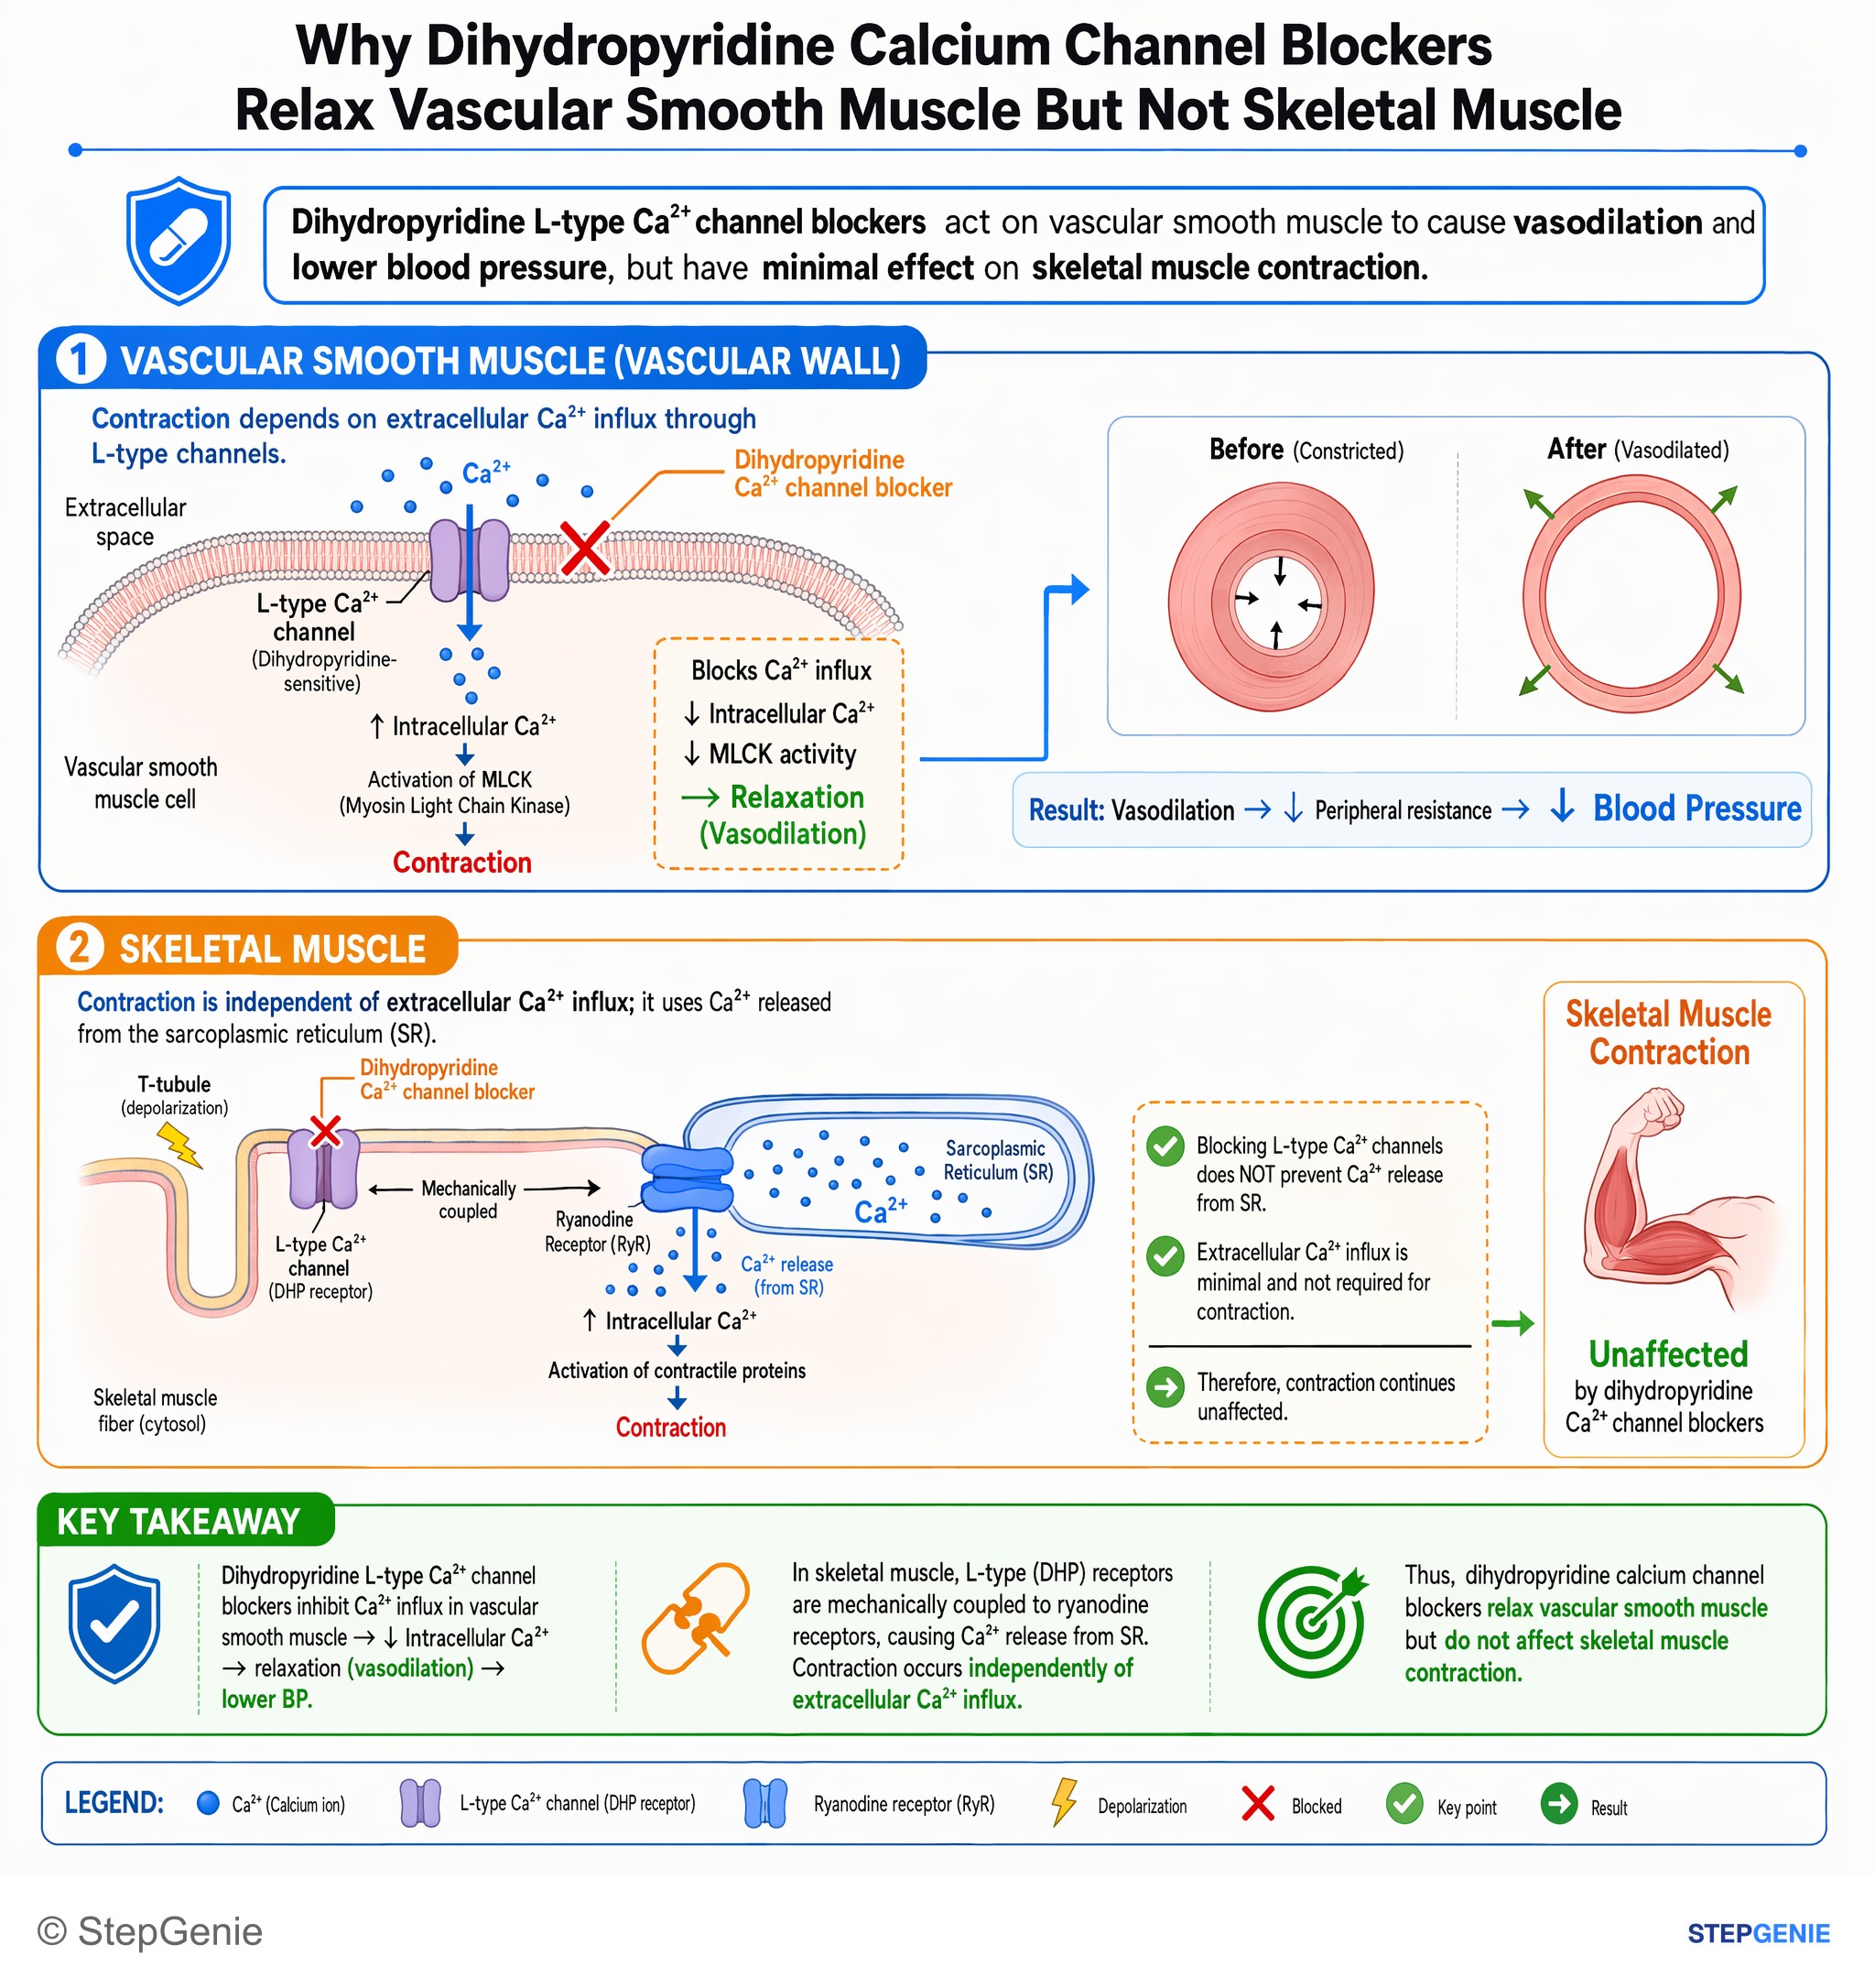
Dihydropyridine calcium channel blockers relax vascular smooth muscle but not skeletal muscle because skeletal muscle contraction uses…
USMLE Step 1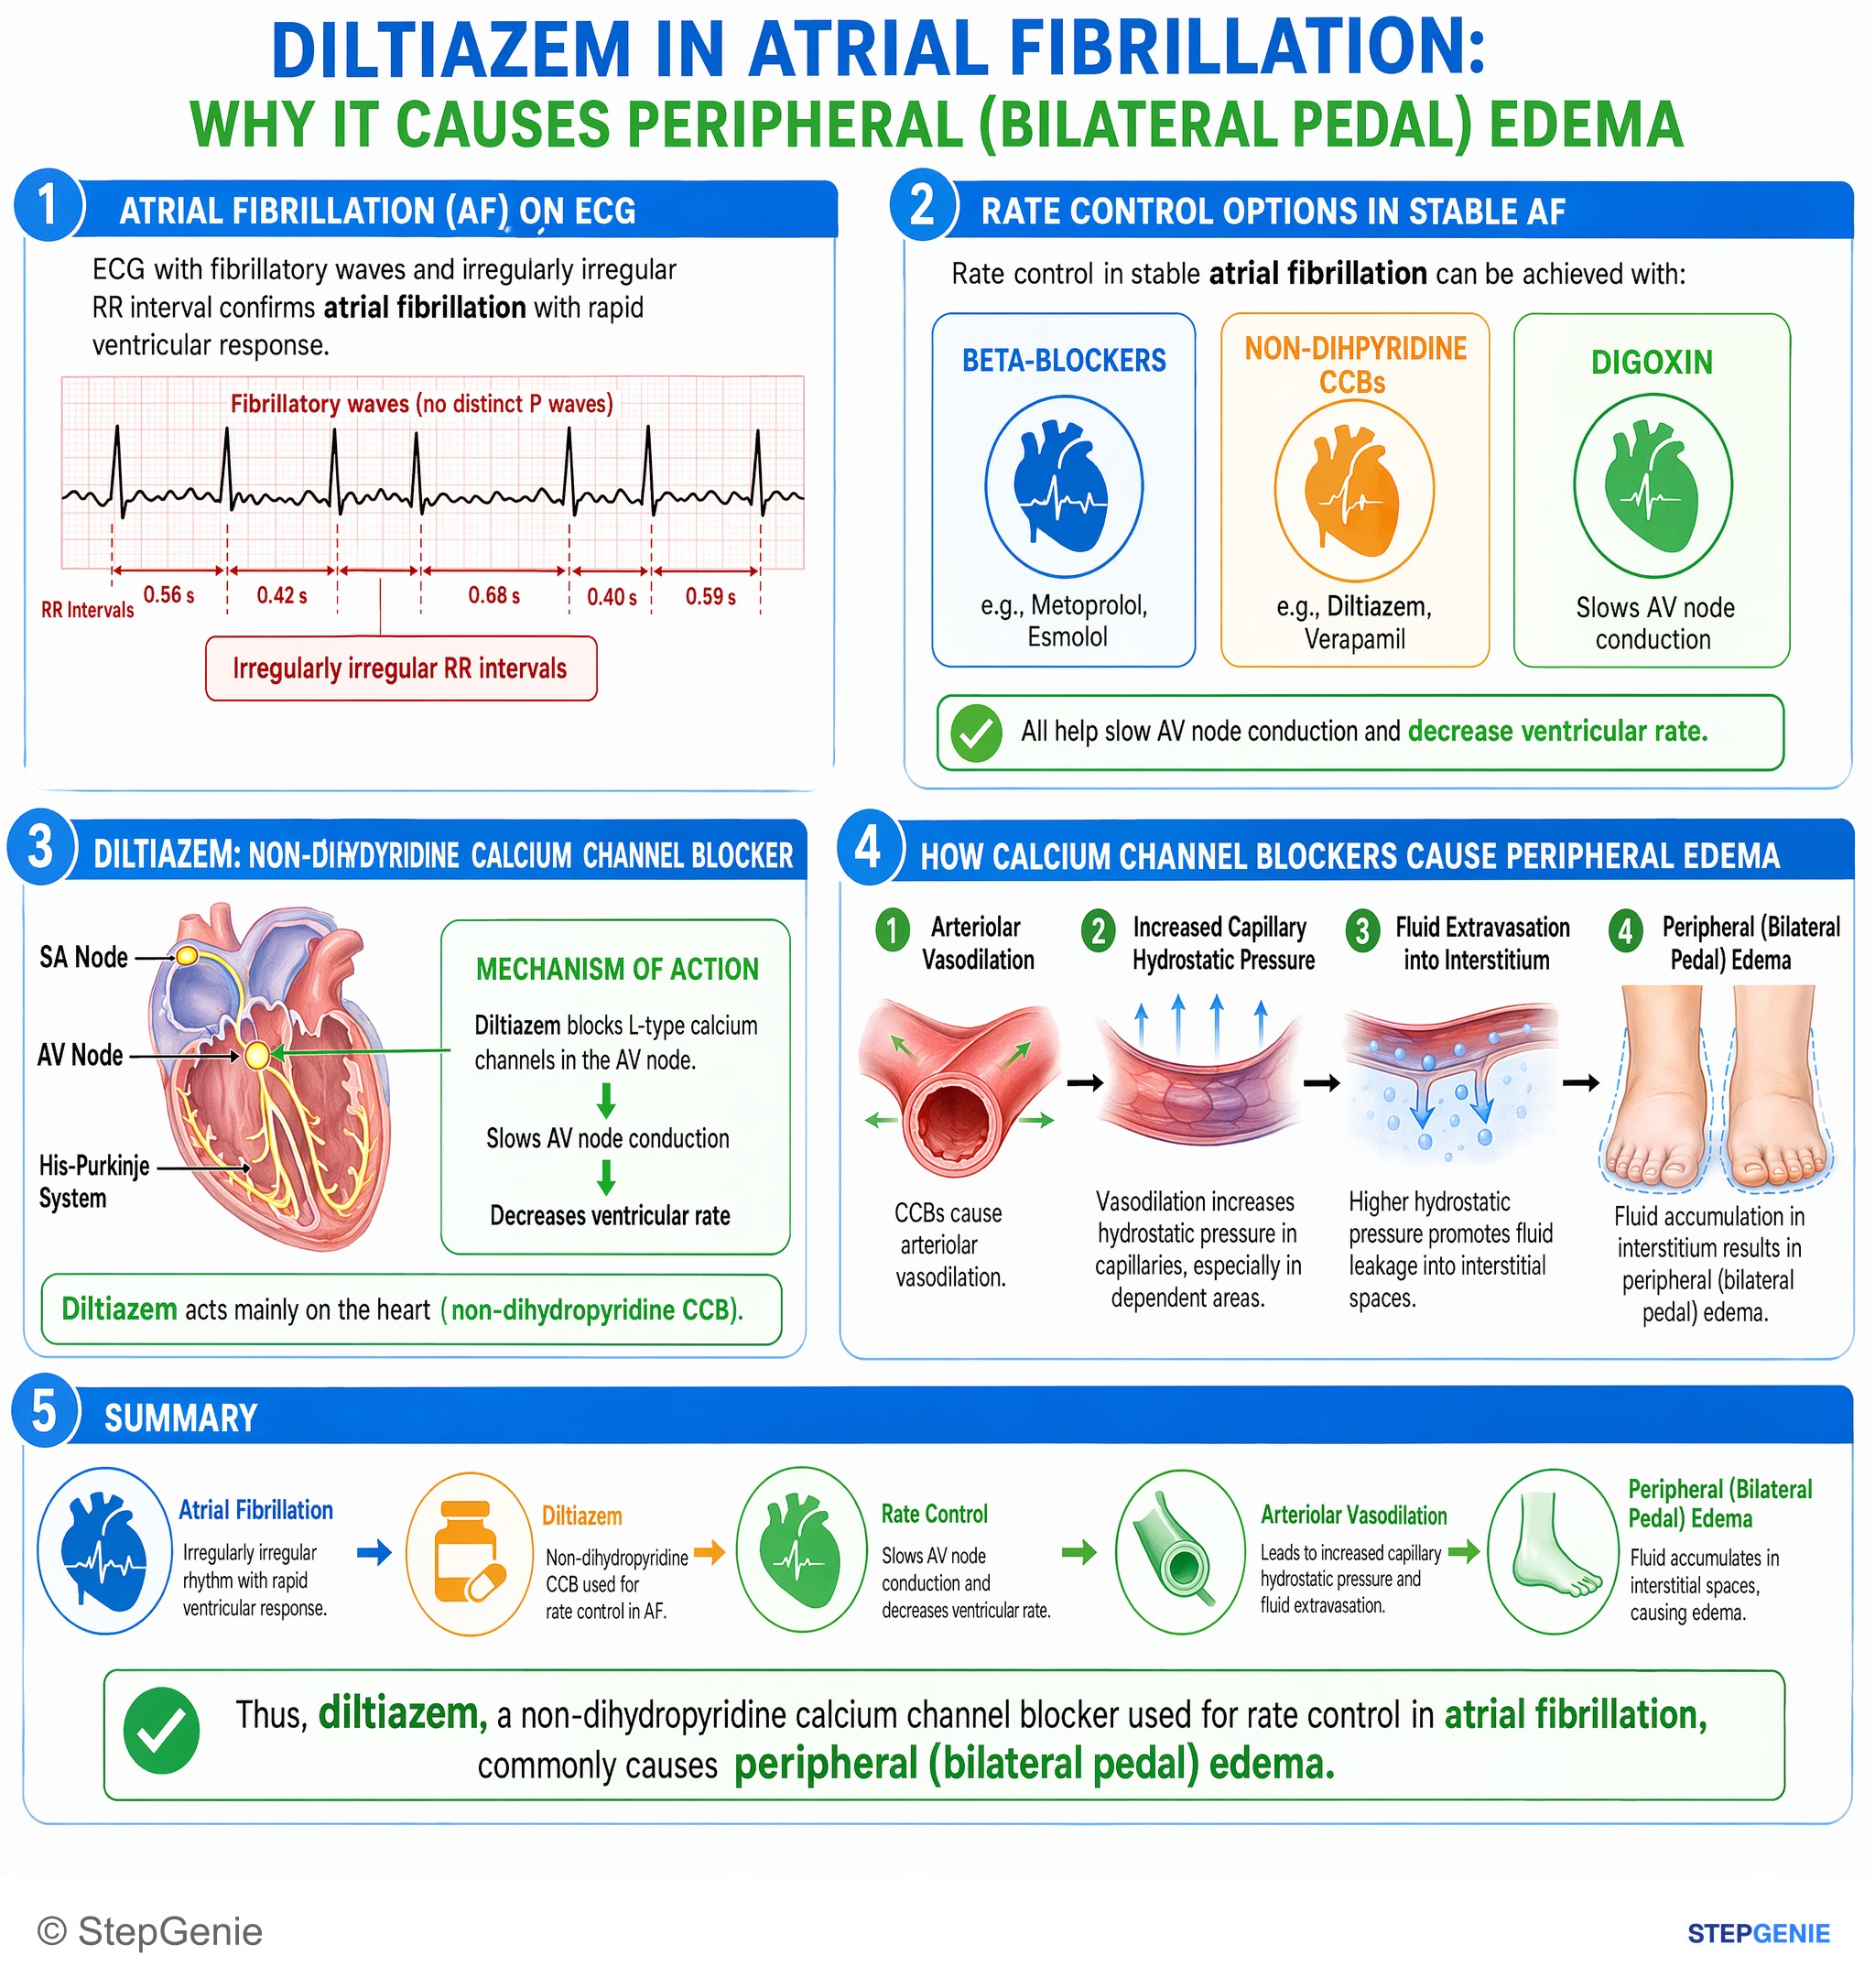
Diltiazem, a non-dihydropyridine calcium channel blocker used for rate control in atrial fibrillation, commonly causes peripheral…
USMLE Step 1Frequently Asked Questions
How do you tell dihydropyridine calcium channel blockers from verapamil and diltiazem on a question stem?
The fastest distinction is that dihydropyridines mainly act on vessels, while verapamil and diltiazem mainly act on the heart. Dihydropyridines such as amlodipine and nifedipine primarily dilate arterioles, lowering systemic vascular resistance and afterload. Non-dihydropyridines primarily affect cardiac muscle and the SA/AV node, so they decrease heart rate, AV conduction, and contractility.
Why do dihydropyridine calcium channel blockers cause reflex tachycardia?
Dihydropyridines cause reflex tachycardia because they produce arteriolar vasodilation that lowers afterload and blood pressure. Baroreceptors detect that pressure drop and trigger reflex sympathetic activation, which raises heart rate and can also increase contractility. This effect is especially noticeable with short-acting agents such as nifedipine and can worsen angina in some settings.
What side effects point to verapamil or diltiazem instead of a dihydropyridine?
Bradycardia, AV block, and constipation point toward a non-dihydropyridine, especially verapamil. Verapamil and diltiazem slow the SA/AV node and decrease contractility, so question stems may mention slowed conduction, heart block, or worsening heart failure from negative inotropy. Constipation is a particularly classic clue for verapamil rather than the dihydropyridine subclass.
Why do dihydropyridine calcium channel blockers cause ankle swelling and flushing?
Dihydropyridines cause ankle swelling and flushing because they preferentially dilate precapillary arterioles. That increases hydrostatic pressure in capillaries, which leads to dependent peripheral edema, often seen at the ankles, without generalized fluid overload. The same vasodilatory effect also explains common symptoms such as flushing, headache, dizziness, and sometimes reflex tachycardia.
When should you think of a non-dihydropyridine calcium channel blocker instead of a dihydropyridine?
Think of a non-dihydropyridine when the goal is rate control rather than afterload reduction. Verapamil and diltiazem are the calcium channel blockers associated with slowing the SA/AV node, so they are used for atrial fibrillation rate control. By contrast, dihydropyridines are the ones to associate more strongly with hypertension treatment and afterload reduction.