Marfan syndrome is one of those “connective tissue” diagnoses that shows up everywhere on Step 1: biochem (ECM proteins), cardio (aortic root dilation), MSK (tall habitus), eyes (lens subluxation), and even pharm (beta-blockers/ARBs). If you can connect the gene defect to the structural and signaling consequences, you’ll stop memorizing random features and start predicting them.
Where Marfan Fits in Biochemistry (Collagen & Connective Tissue)
Connective tissue strength depends on:
- Structural proteins (collagen, elastin, fibrillin)
- Cross-linking (e.g., lysyl oxidase uses copper)
- ECM organization (microfibrils scaffold elastic fibers)
Marfan syndrome is primarily a disorder of microfibrils, not collagen itself.
The Key Protein: Fibrillin-1
- Gene: FBN1 (autosomal dominant)
- Protein: Fibrillin-1
- Normal role:
- Forms microfibrils that provide a scaffold for elastic fiber formation (especially important in the aorta)
- Helps sequester TGF-β in the extracellular matrix (keeps TGF-β signaling in check)
High-yield Step framing:
Marfan = defective fibrillin → weak elastic tissue + ↑ TGF-β signaling.
Definition (Step 1-friendly)
Marfan syndrome is an autosomal dominant connective tissue disorder due to FBN1 mutation leading to defective fibrillin and dysregulated TGF-β signaling, causing aortic root disease, lens subluxation, and a tall, hypermobile habitus.
Pathophysiology: Two Big Mechanisms to Remember
1) Structural failure of elastic tissues
Defective fibrillin microfibrils → impaired elastic fiber integrity → tissues that rely on elastin become vulnerable:
- Aorta (especially aortic root)
- Heart valves
- Ligaments and periosteum
- Suspensory ligaments of the lens
2) Increased TGF-β signaling (often tested conceptually)
Fibrillin normally binds latent TGF-β complexes in ECM. With fibrillin defects:
- Less TGF-β sequestration
- ↑ TGF-β activity → abnormal remodeling, fibrosis, and weakening of vessel wall architecture
Clinical tie-in: This helps explain why ARBs (like losartan)—which reduce downstream effects of angiotensin II and can blunt TGF-β–mediated remodeling—are used.
Clinical Presentation (the “Classic Triad” + extras)
Cardiovascular (most life-threatening)
High-yield manifestations
- Aortic root dilation → aortic regurgitation
- Aortic aneurysm and aortic dissection
- Mitral valve prolapse (myxomatous degeneration)
What you might hear on a question stem
- Early diastolic murmur (AR) at left sternal border
- Sudden tearing chest/back pain (dissection)
- Tall patient with “thumb sign/wrist sign,” then aortic issues
Ocular
- Ectopia lentis (lens subluxation) upward and outward
- Mnemonic: Marfan = “Up” (lens goes up)
- Myopia is common
Step contrast:
- Marfan: lens up and out
- Homocystinuria: lens down and in
Musculoskeletal
- Tall, thin habitus
- Long limbs/fingers (arachnodactyly)
- Joint hypermobility
- Pectus excavatum/carinatum
- Scoliosis
- Increased arm span-to-height ratio
Pulmonary (often shows up as a “gotcha”)
- Spontaneous pneumothorax (apical blebs)
Skin/other
- Striae can occur (not specific)
- Dural ectasia (can be tested in more detailed vignettes)
Diagnosis: How It’s Made on Exams (and in real life)
Clinical diagnosis + family history
While real-world diagnosis often uses Ghent criteria, Step questions usually want you to recognize:
- Autosomal dominant inheritance pattern
- Tall habitus + lens dislocation upward
- Aortic root dilation/dissection risk
Key diagnostic tests you’ll see in vignettes
- Echocardiography: evaluates aortic root size, AR, MVP
- Slit-lamp exam: lens subluxation
- Genetic testing: FBN1 mutation (confirmatory/supportive)
Histology pearl (occasionally tested)
- Aortic media can show cystic medial degeneration (fragmentation of elastic fibers)
Treatment: What to Do and Why It Works
Prevent aortic catastrophe
Main goal = reduce shear stress and pathologic remodeling.
Medical
- Beta-blockers: lower HR and contractility → ↓ (less mechanical stress on aorta)
- ARBs (e.g., losartan): associated with improved aortic outcomes; mechanistically helps blunt maladaptive remodeling linked to TGF-β signaling
Surgical
- Prophylactic aortic root repair if dilation reaches thresholds (Step won’t test exact cutoffs often, but will test the concept)
Other supportive care
- Regular surveillance imaging (echo/CT/MRI)
- Activity modification (avoid high-intensity isometric/competitive sports if significant aortic dilation)
- Manage MVP/AR as indicated
High-Yield Associations & Differentials (very testable)
Marfan vs Ehlers-Danlos vs Homocystinuria (rapid table)
| Feature | Marfan | Ehlers-Danlos (EDS) | Homocystinuria |
|---|---|---|---|
| Primary defect | Fibrillin-1 (FBN1) | Collagen processing (varies; often type V, sometimes type III) | Cystathionine β-synthase deficiency (classically) |
| Inheritance | AD | Often AD (some AR types) | AR |
| Lens | Up and out | No classic direction | Down and in |
| Vascular risk | Aortic root dilation/dissection | Tissue fragility; some types → arterial/organ rupture | Thrombosis/atherosclerosis risk |
| Skin/joints | Hypermobile; striae | Hyperextensible skin, hypermobile joints | Marfanoid habitus possible |
| Key extras | MVP, pneumothorax | Poor wound healing | Intellectual disability, seizures; fair skin/hair |
| Labs | — | — | ↑ homocysteine, ± ↑ methionine |
Step-style “hooks” for Marfan
- “Tall, long fingers, pectus excavatum, scoliosis” + heart murmur
- “Lens subluxation superiorly”
- “Family history of sudden death due to aortic dissection”
- “Aortic root dilation on echo”
First Aid Cross-References (so you can anchor it fast)
These are the sections you should connect while studying:
- Biochemistry → Collagen synthesis / connective tissue disorders
- Marfan as a fibrillin-1 defect (microfibrils)
- Cardiovascular pathology
- Aortic dissection, aortic aneurysm, cystic medial degeneration
- MVP and aortic regurgitation
- Ophthalmology
- Ectopia lentis directionality: Marfan up, homocystinuria down
- Genetics
- Autosomal dominant inheritance patterns
(Note: First Aid page numbers vary by edition, but these are consistently the same topic buckets.)
Exam Tips: How to Not Miss Marfan Questions
1) If you see lens dislocation, ask “Which direction?”
- Up/out → Marfan
- Down/in → homocystinuria
2) If you see “tall + sudden chest pain,” think dissection first
Especially if there’s:
- Aortic regurg murmur
- Wide pulse pressure
- Family history
3) Mechanism question? Lead with fibrillin → TGF-β dysregulation
If they ask “why ARBs?” the safest Step logic:
- ARBs can reduce deleterious remodeling pathways tied to TGF-β signaling and decrease progression of aortic root dilation.
Quick High-Yield Summary (Last-minute review)
- Marfan = AD FBN1 mutation → defective fibrillin-1
- Weak elastic tissue + ↑ TGF-β signaling
- Aortic root dilation → AR, aneurysm, dissection (major killer)
- Ectopia lentis up and out
- Tall habitus, arachnodactyly, pectus deformity, scoliosis, hypermobile joints
- Tx: beta-blocker and/or ARB (losartan) + surveillance ± prophylactic surgery
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
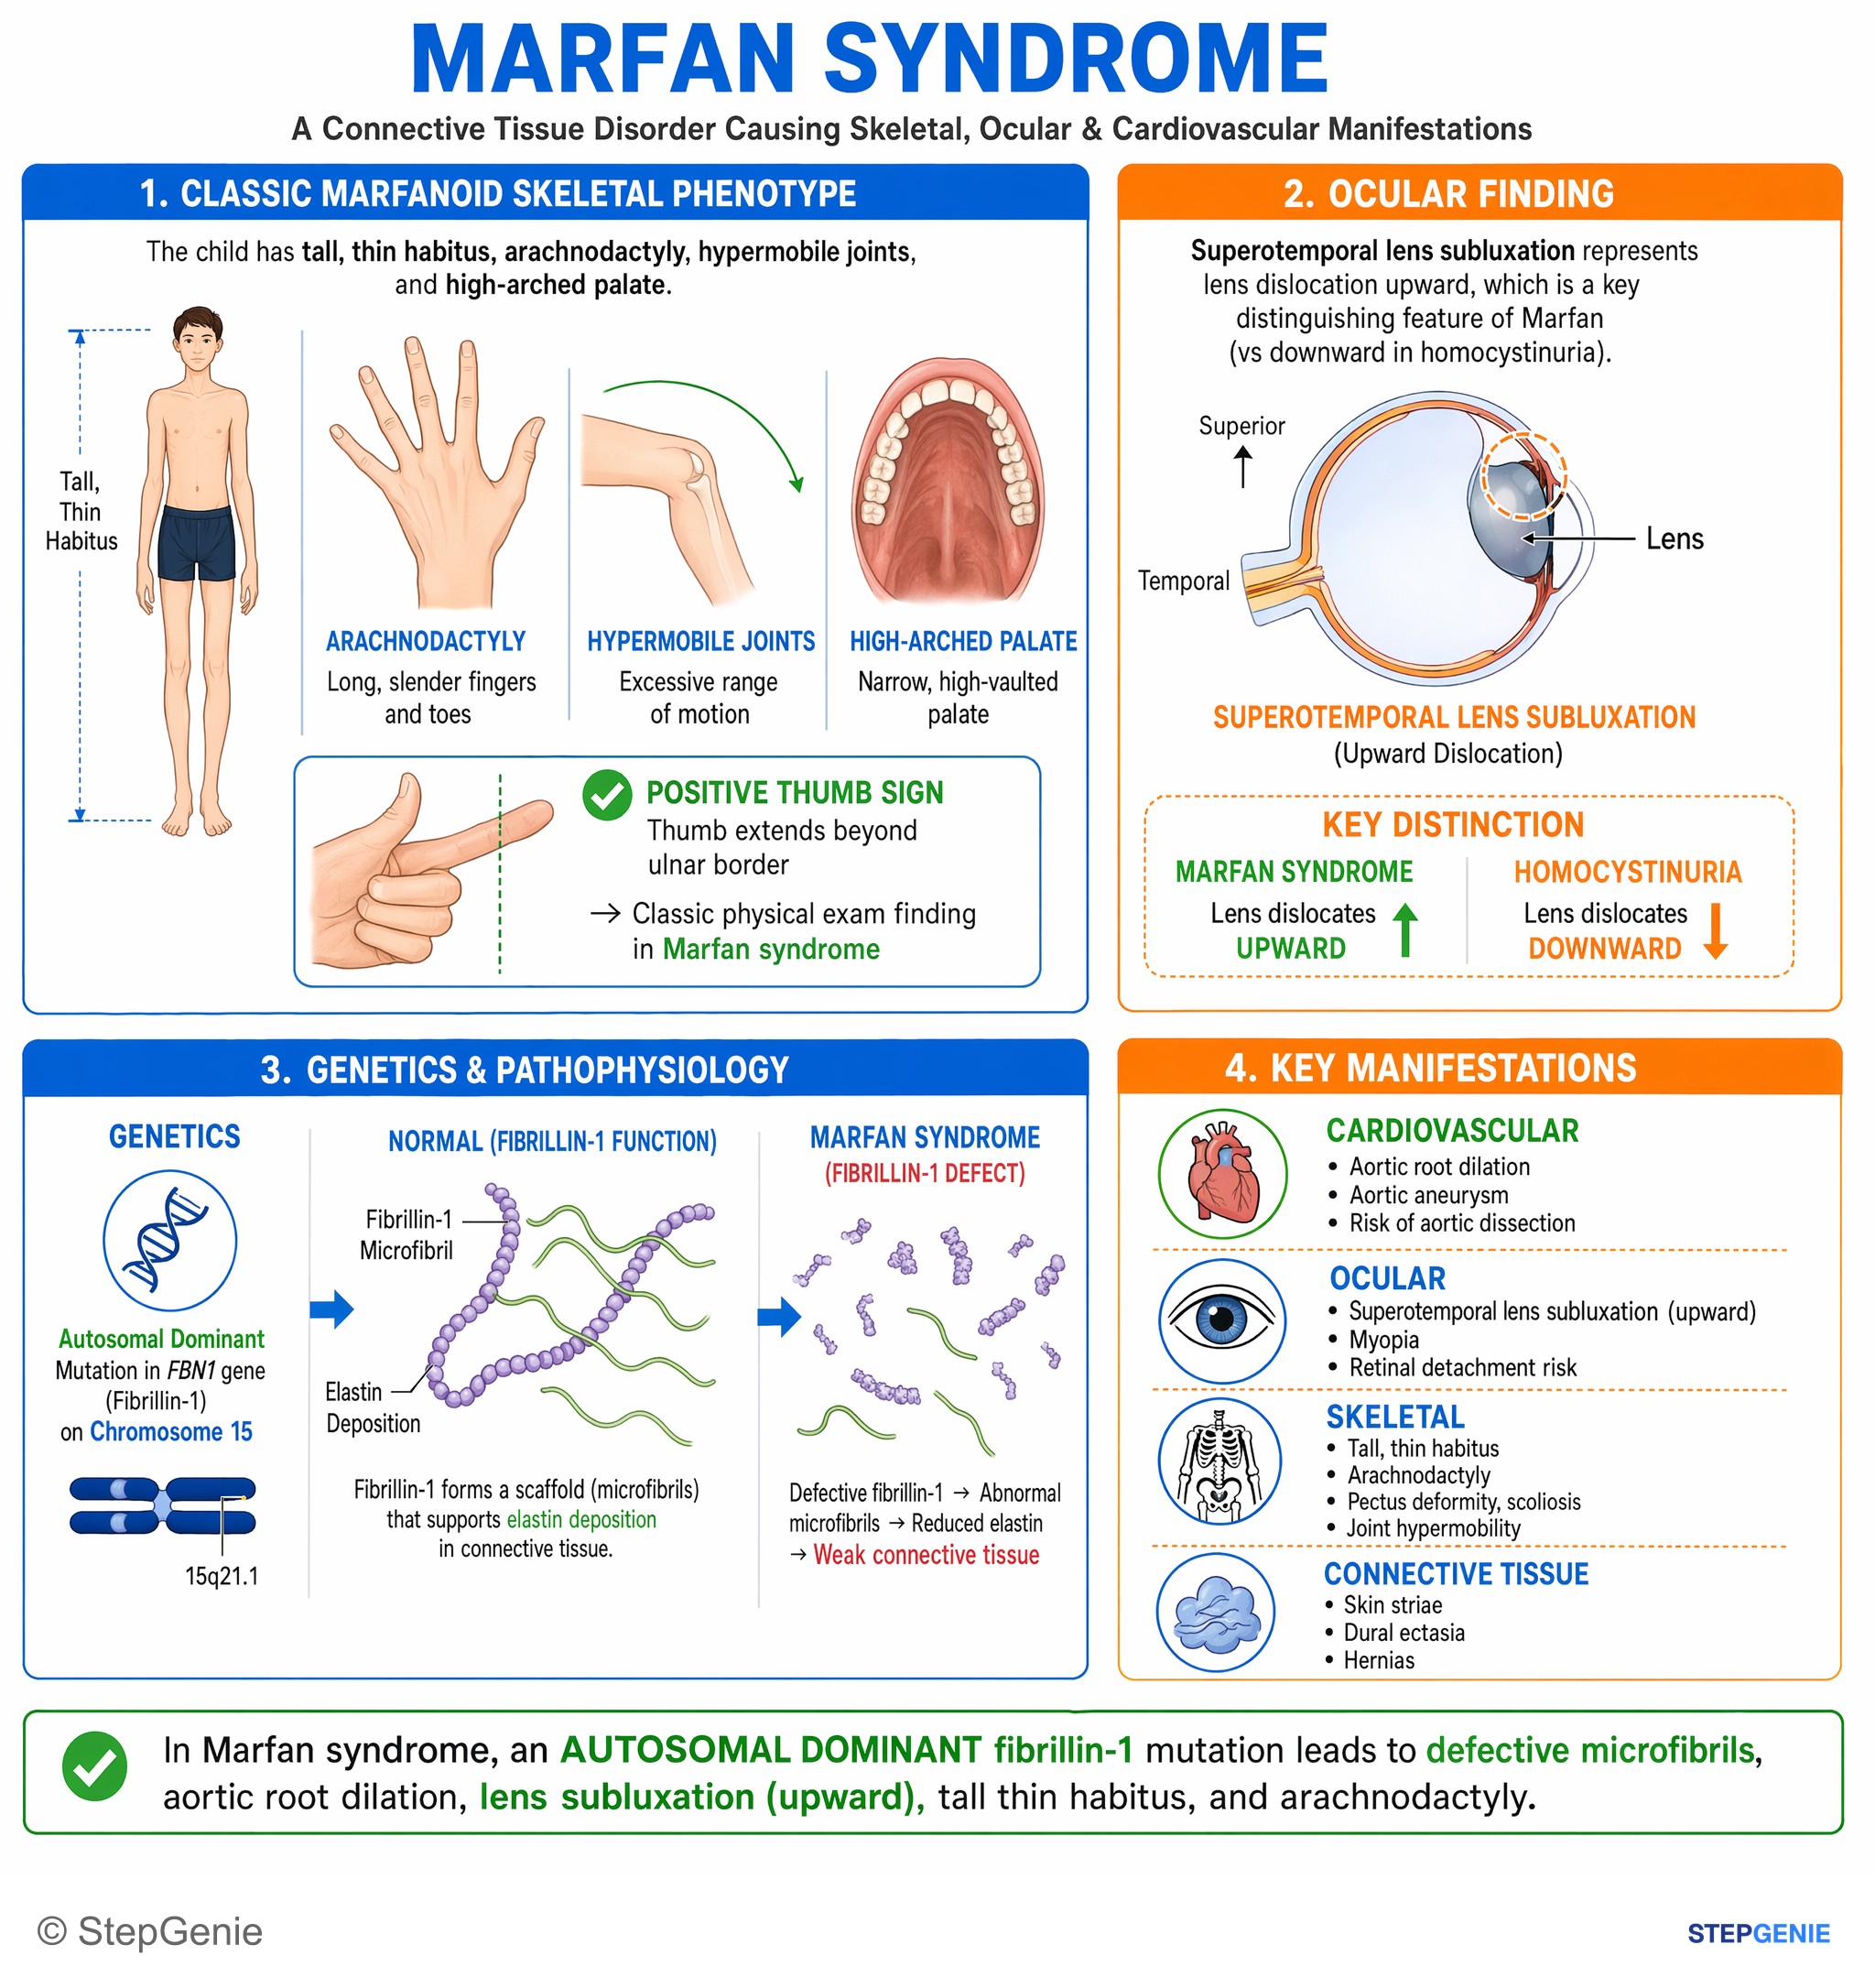
Marfan syndrome: autosomal dominant fibrillin-1 mutation → defective microfibrils, aortic root dilation, lens subluxation (upward), tall…
USMLE Step 1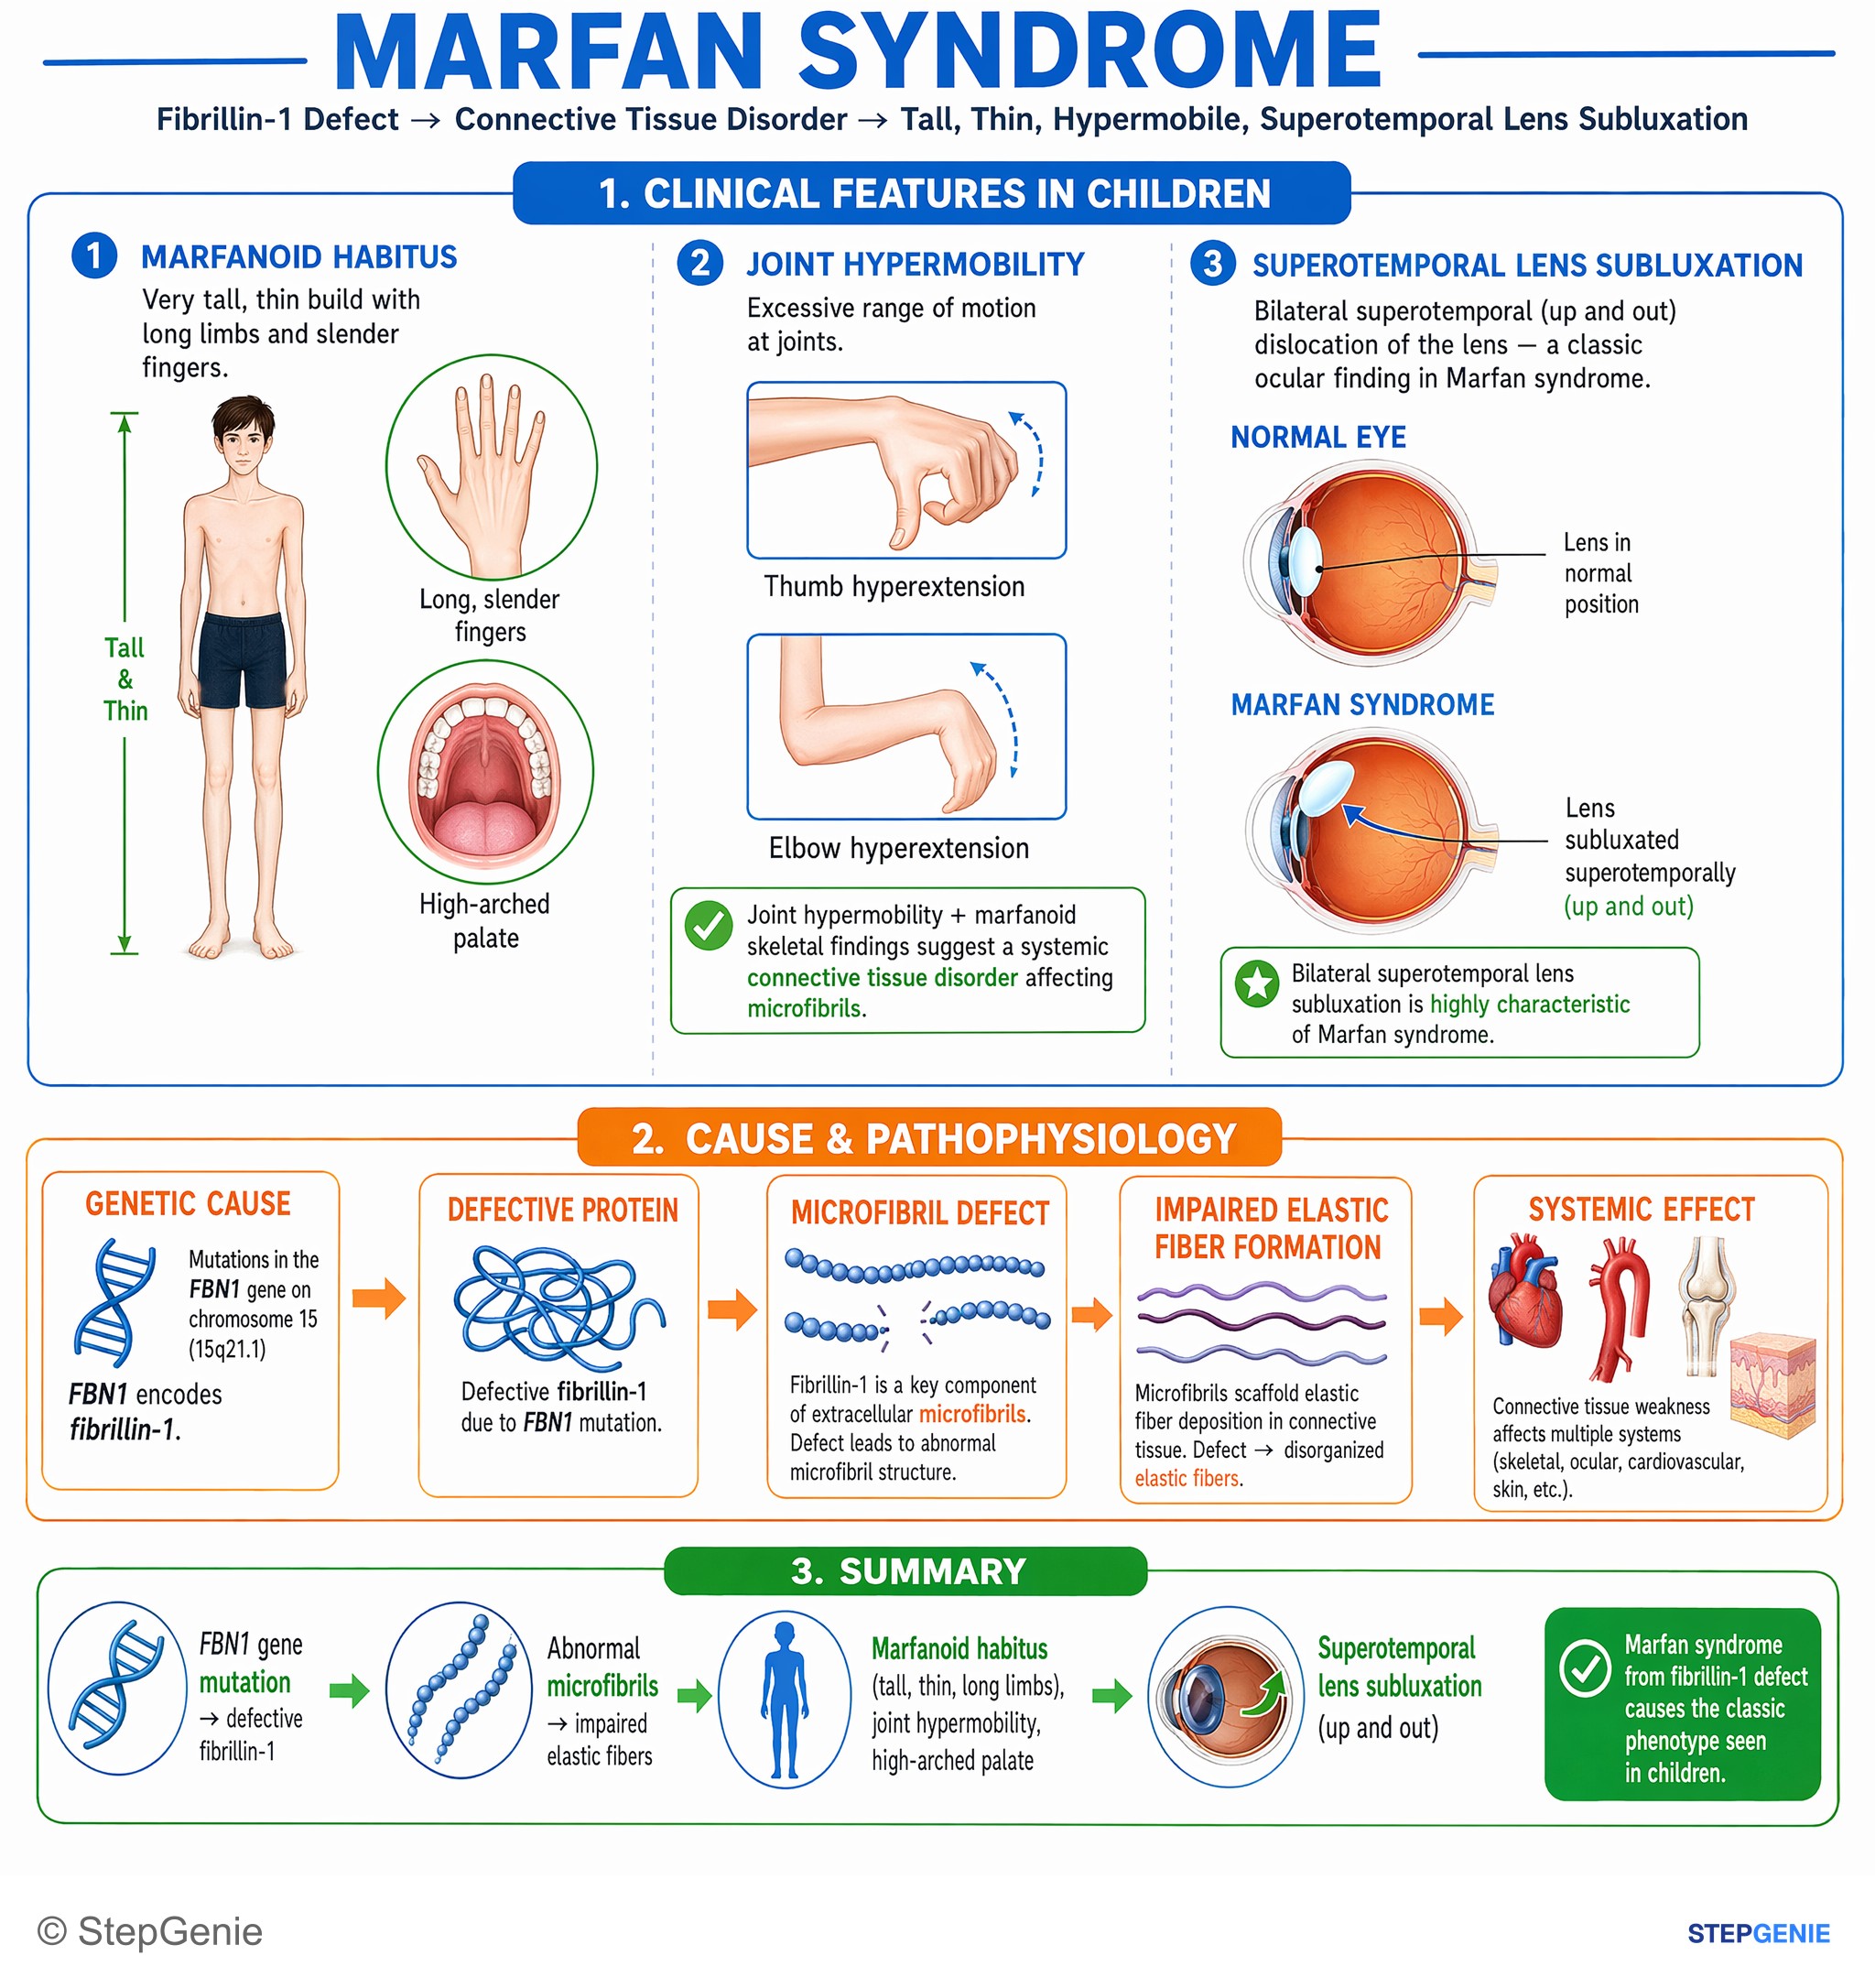
Marfan syndrome from fibrillin-1 defect causes tall, thin habitus, joint hypermobility, and superotemporal lens subluxation in children.
USMLE Step 1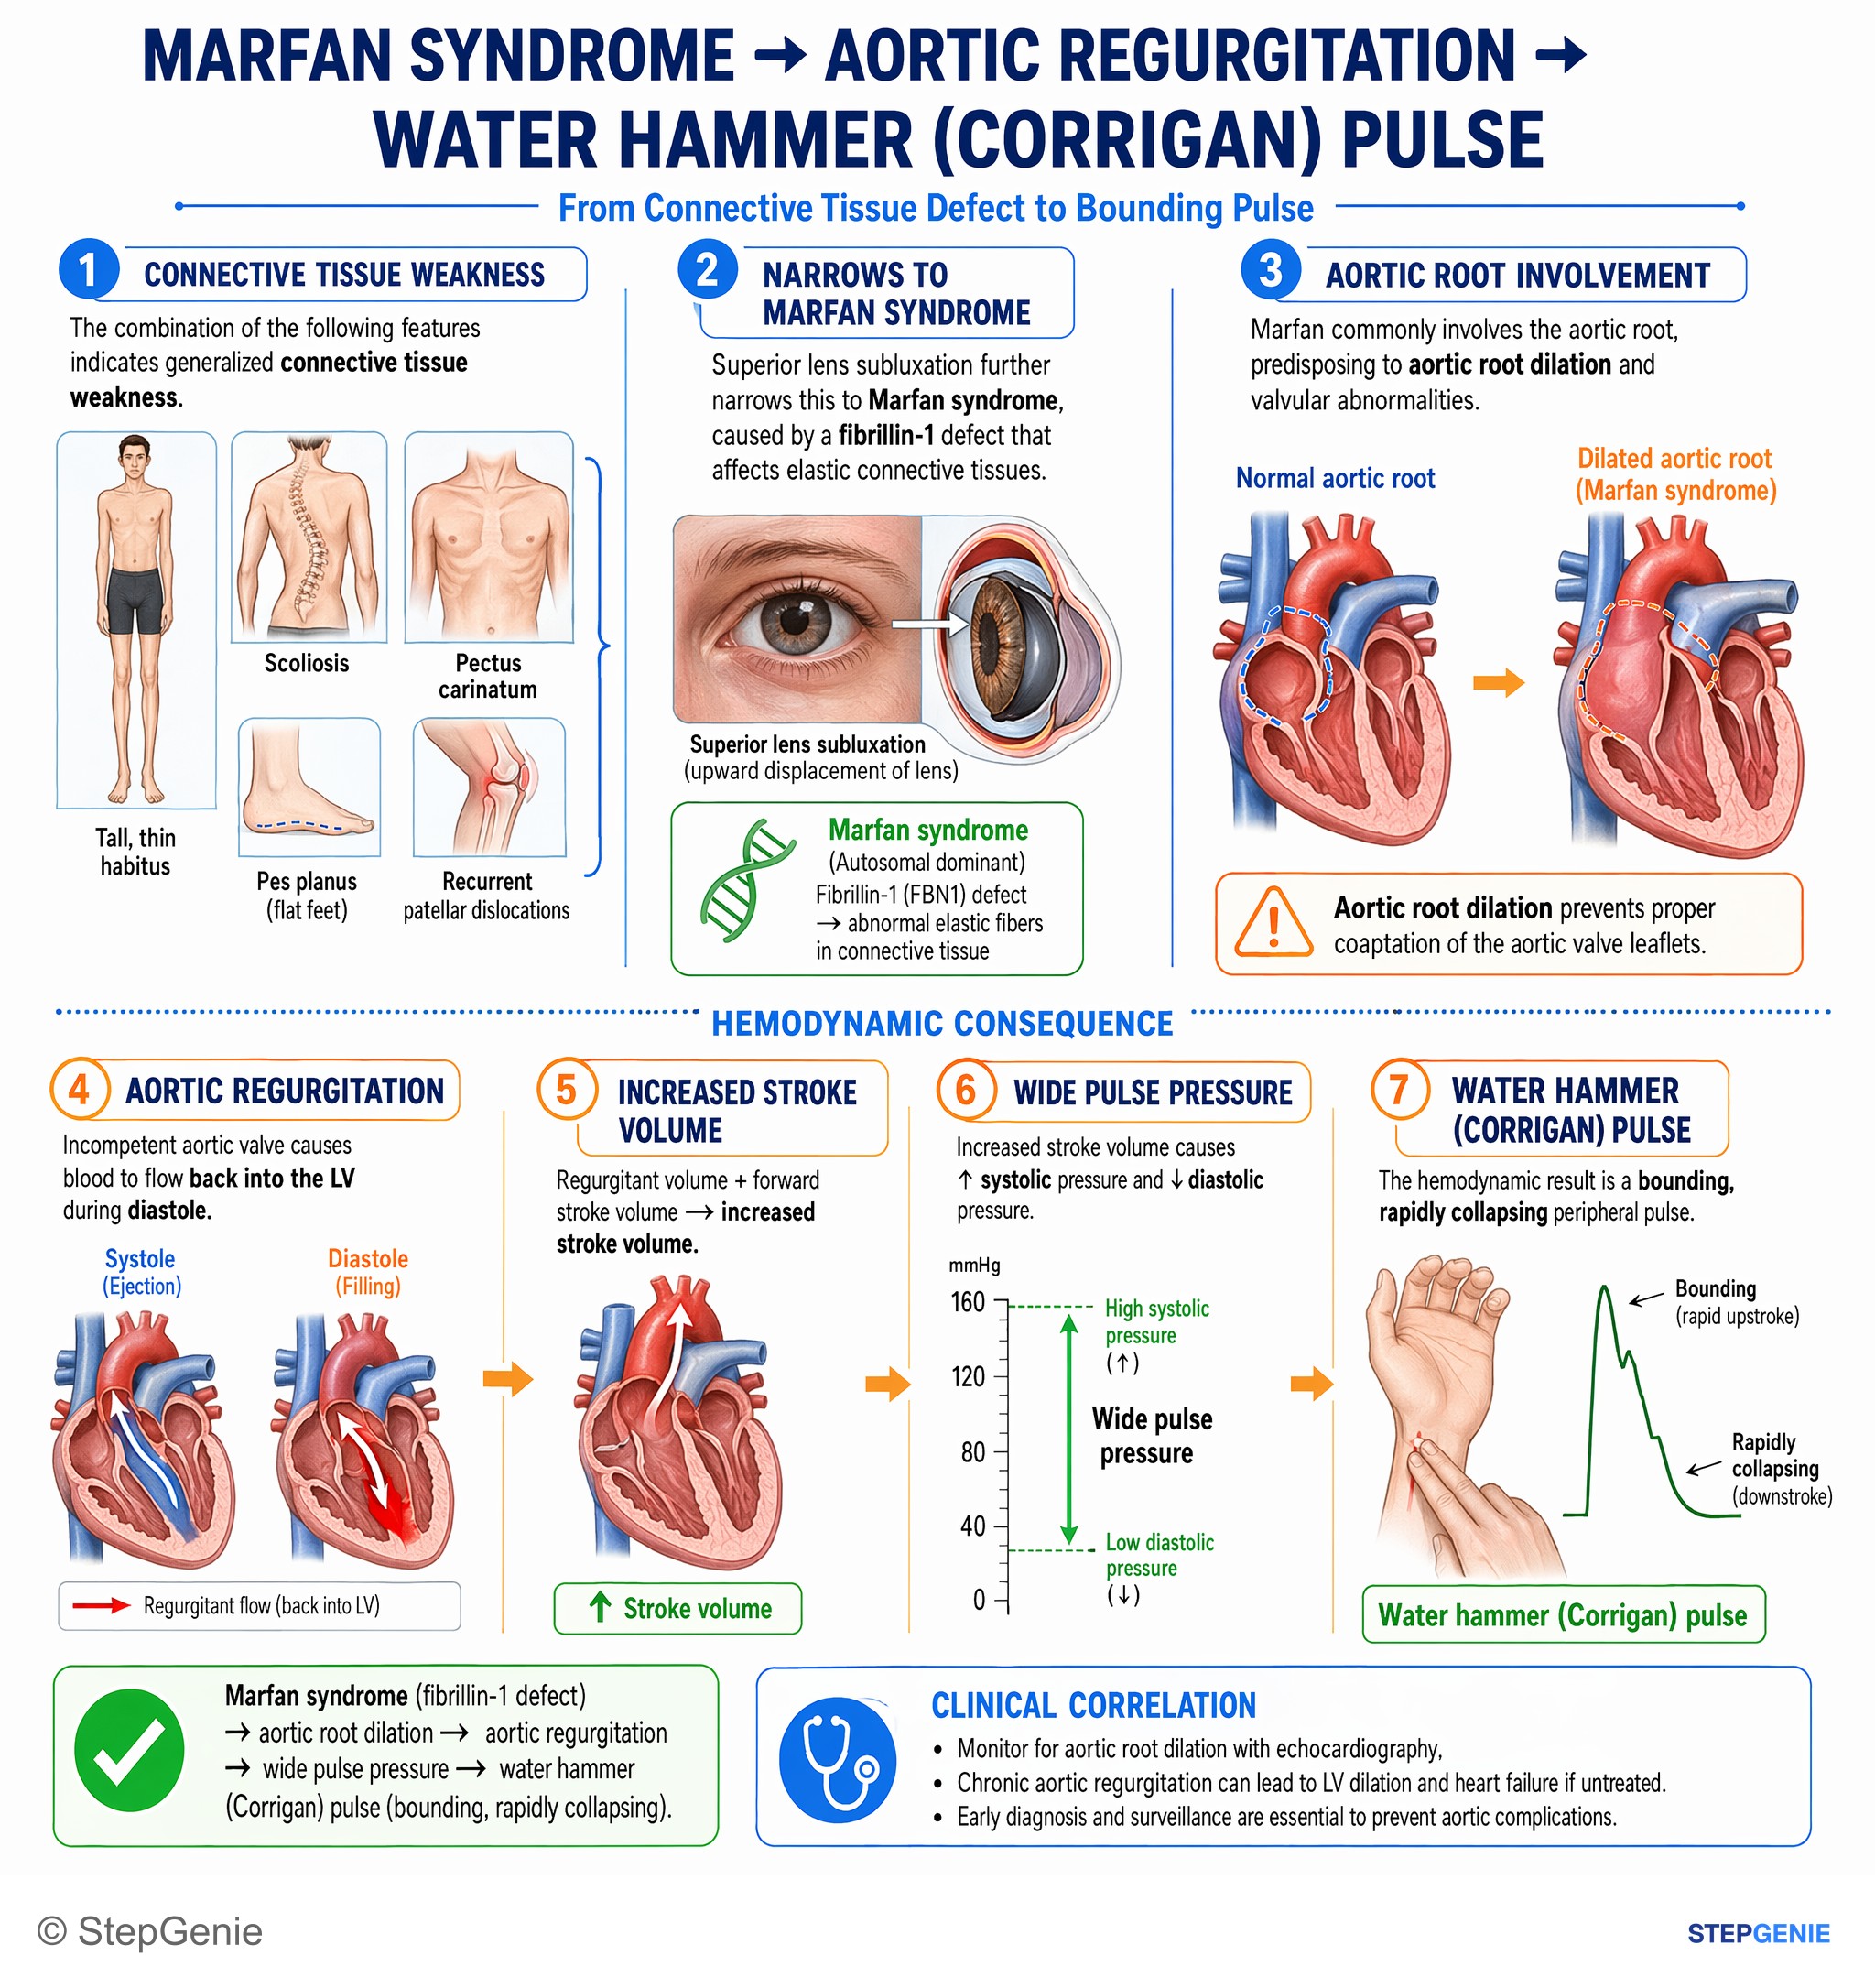
Marfan syndrome causing aortic root dilation → aortic regurgitation with wide pulse pressure and water hammer pulse (bounding, rapidly…
USMLE Step 1Frequently Asked Questions
Why does an FBN1 mutation cause aortic root dilation and dissection in Marfan syndrome?
An FBN1 mutation causes defective fibrillin-1, which weakens elastic tissue and increases TGF-β signaling. Fibrillin normally forms microfibrils that scaffold elastic fibers, especially in the aorta, and it also sequesters TGF-β in the extracellular matrix. When fibrillin is abnormal, the aortic wall loses structural integrity and undergoes maladaptive remodeling, making aortic root dilation, aneurysm, and dissection more likely.
How do you tell Marfan syndrome from homocystinuria on a Step 1 vignette?
The classic distinction is the direction of lens subluxation and the associated systemic clues. In Marfan syndrome, ectopia lentis is upward and outward, and the patient typically has autosomal dominant inheritance with aortic root dilation or dissection risk. In homocystinuria, the lens is down and in, inheritance is autosomal recessive, and thrombosis or atherosclerosis risk with elevated homocysteine may be present.
What is the first-line medical treatment for Marfan syndrome to prevent aortic complications?
Beta-blockers are used to reduce aortic stress, and ARBs such as losartan are also used because they can blunt maladaptive remodeling linked to TGF-β signaling. Beta-blockers lower heart rate and contractility, which decreases dP/dt and mechanical shear stress on the aorta. The overall treatment goal is to prevent aortic catastrophe by reducing both hemodynamic stress and pathologic vessel wall remodeling.
What are the highest-yield clinical features of Marfan syndrome for Step 1?
The highest-yield features are aortic root disease, upward lens subluxation, and a tall hypermobile habitus. Common clues include aortic root dilation with aortic regurgitation, aortic aneurysm or dissection, mitral valve prolapse, ectopia lentis upward and outward, arachnodactyly, pectus deformity, scoliosis, joint hypermobility, and an increased arm span-to-height ratio. Question stems may also mention spontaneous pneumothorax or a family history of sudden death from dissection.
How is Marfan syndrome usually diagnosed on exams?
On exams, Marfan syndrome is usually diagnosed clinically by recognizing the pattern of autosomal dominant inheritance, tall habitus, upward lens dislocation, and aortic root disease. Echocardiography is used to evaluate aortic root size, aortic regurgitation, and mitral valve prolapse, while slit-lamp exam shows lens subluxation. Genetic testing for an FBN1 mutation can provide confirmatory or supportive evidence.