Renal artery stenosis (RAS) is one of those “hypertension questions” that becomes easy once you draw the physiology once and reuse it forever. If you can picture a narrowed renal artery tricking the kidney into thinking the body is hypotensive, you’ll predict the labs, the physical exam, and the medication effects in seconds.
The one-liner (memorize this)
Renal artery stenosis = decreased renal perfusion → increased renin → increased angiotensin II + aldosterone → hypertension (often resistant) + hypokalemic metabolic alkalosis.
Draw-it-out method (quick sketch you can recreate on test day)
Step 1: Draw the core flowchart
Use this simple “kidney panic pathway”:
Renal artery stenosis (↓ renal blood flow/pressure)
→ JG cells: ↑ renin
→ ↑ angiotensin II (systemic vasoconstriction + efferent arteriole constriction)
→ ↑ aldosterone
→ ↑ Na⁺/H₂O retention + ↑ K⁺/H⁺ loss
→ Hypertension + hypokalemic metabolic alkalosis
Step 2: Add the “ACEi clue” branch
Now add the classic twist:
- Ang II constricts efferent arteriole to maintain glomerular pressure (especially when renal perfusion is low).
- If you block Ang II (ACE inhibitor/ARB), the efferent arteriole dilates, intraglomerular pressure drops, and GFR falls.
So in your drawing, add:
ACEi/ARB given → ↓ efferent constriction → ↓ GFR → ↑ creatinine
This is especially important in:
- Bilateral RAS
- RAS in a solitary functioning kidney
Visual mnemonic: “The Kidney Lies”
Picture the stenotic kidney holding up a sign:
“BP is LOW!” (even when the arm cuff says 180/110)
Because the kidney senses local perfusion, not systemic blood pressure, it “lies” to the body by activating RAAS.
Mnemonic phrase:
“Stenosed kidney screams ‘RENIN!’”
High-yield etiologies: atherosclerosis vs fibromuscular dysplasia
| Feature | Atherosclerotic RAS | Fibromuscular dysplasia (FMD) |
|---|---|---|
| Typical patient | Older adult, vascular risk factors | Young woman |
| Pathology | Plaque at ostium/proximal renal artery | “String of beads” in mid-to-distal artery |
| Exam clue | May have diffuse atherosclerosis | May have carotid/vertebral involvement too |
| Imaging buzzword | Proximal narrowing | “String of beads” on angiography |
| Treatment vibe | Medical therapy ± revascularization selected cases | Percutaneous angioplasty often effective |
Classic presentation (Step-friendly)
Think secondary HTN when you see:
- Resistant hypertension (uncontrolled on 3 meds including a diuretic)
- Abdominal bruit (epigastric/flank), sometimes lateralizing
- Unexplained hypokalemia (from aldosterone; may be worsened if on diuretics)
- Rise in creatinine after starting ACEi/ARB (big clue)
Lab/physiology pattern (the “predictable triad”)
RAS tends to push you toward:
- ↑ Renin
- ↑ Aldosterone
- ↓ Potassium and metabolic alkalosis (via increased H⁺ secretion in alpha-intercalated cells)
Unilateral vs bilateral: what changes?
Unilateral RAS
- The stenosed kidney pumps out renin → systemic HTN.
- The other kidney sees the higher systemic pressure and can natriurese (“pressure natriuresis”), partially buffering volume.
Net: Often more renin-driven HTN; kidney function may stay closer to normal initially.
Bilateral RAS (or solitary kidney)
- Both kidneys perceive low perfusion → strong RAAS activation.
- ACEi/ARB can drop GFR significantly because both kidneys rely on Ang II–mediated efferent constriction.
Net: Higher risk of acute kidney injury after ACEi/ARB, especially if volume depleted.
Diagnosis: what USMLE expects you to recognize
Common test-facing options:
- Renal artery duplex ultrasound (noninvasive screening)
- CTA or MRA (anatomic evaluation; consider renal function/contrast risks)
- Renal arteriography = definitive (invasive; often tied to intervention)
A frequent board-style line is:
“Creatinine increased after ACE inhibitor” + “abdominal bruit” → suspect RAS.
Treatment (conceptual, exam-focused)
- Risk factor management: statin, smoking cessation, diabetes control (atherosclerotic disease)
- Antihypertensives:
- ACE inhibitors/ARBs can be great in unilateral RAS (monitor creatinine and potassium)
- Use caution in bilateral RAS/solitary kidney
- Revascularization (angioplasty ± stent): selected cases (e.g., FMD, refractory HTN, recurrent flash pulmonary edema, progressive renal dysfunction attributable to RAS)
Rapid-fire USMLE pearls
- Abdominal bruit + severe HTN = renovascular disease until proven otherwise.
- ACEi/ARB → rise in creatinine is a feature, not a side effect, when it’s due to loss of efferent constriction.
- Hypokalemia + metabolic alkalosis points to hyperaldosteronism physiology—RAS is a classic secondary cause.
- FMD = young woman + “string of beads” + responds well to angioplasty.
Shareable “final snapshot”
RAS = kidney underperfused → renin surge → Ang II vasoconstriction + aldosterone → resistant HTN ± hypokalemic metabolic alkalosis; ACEi/ARB can unmask it by dropping GFR (↑ Cr), especially if bilateral.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
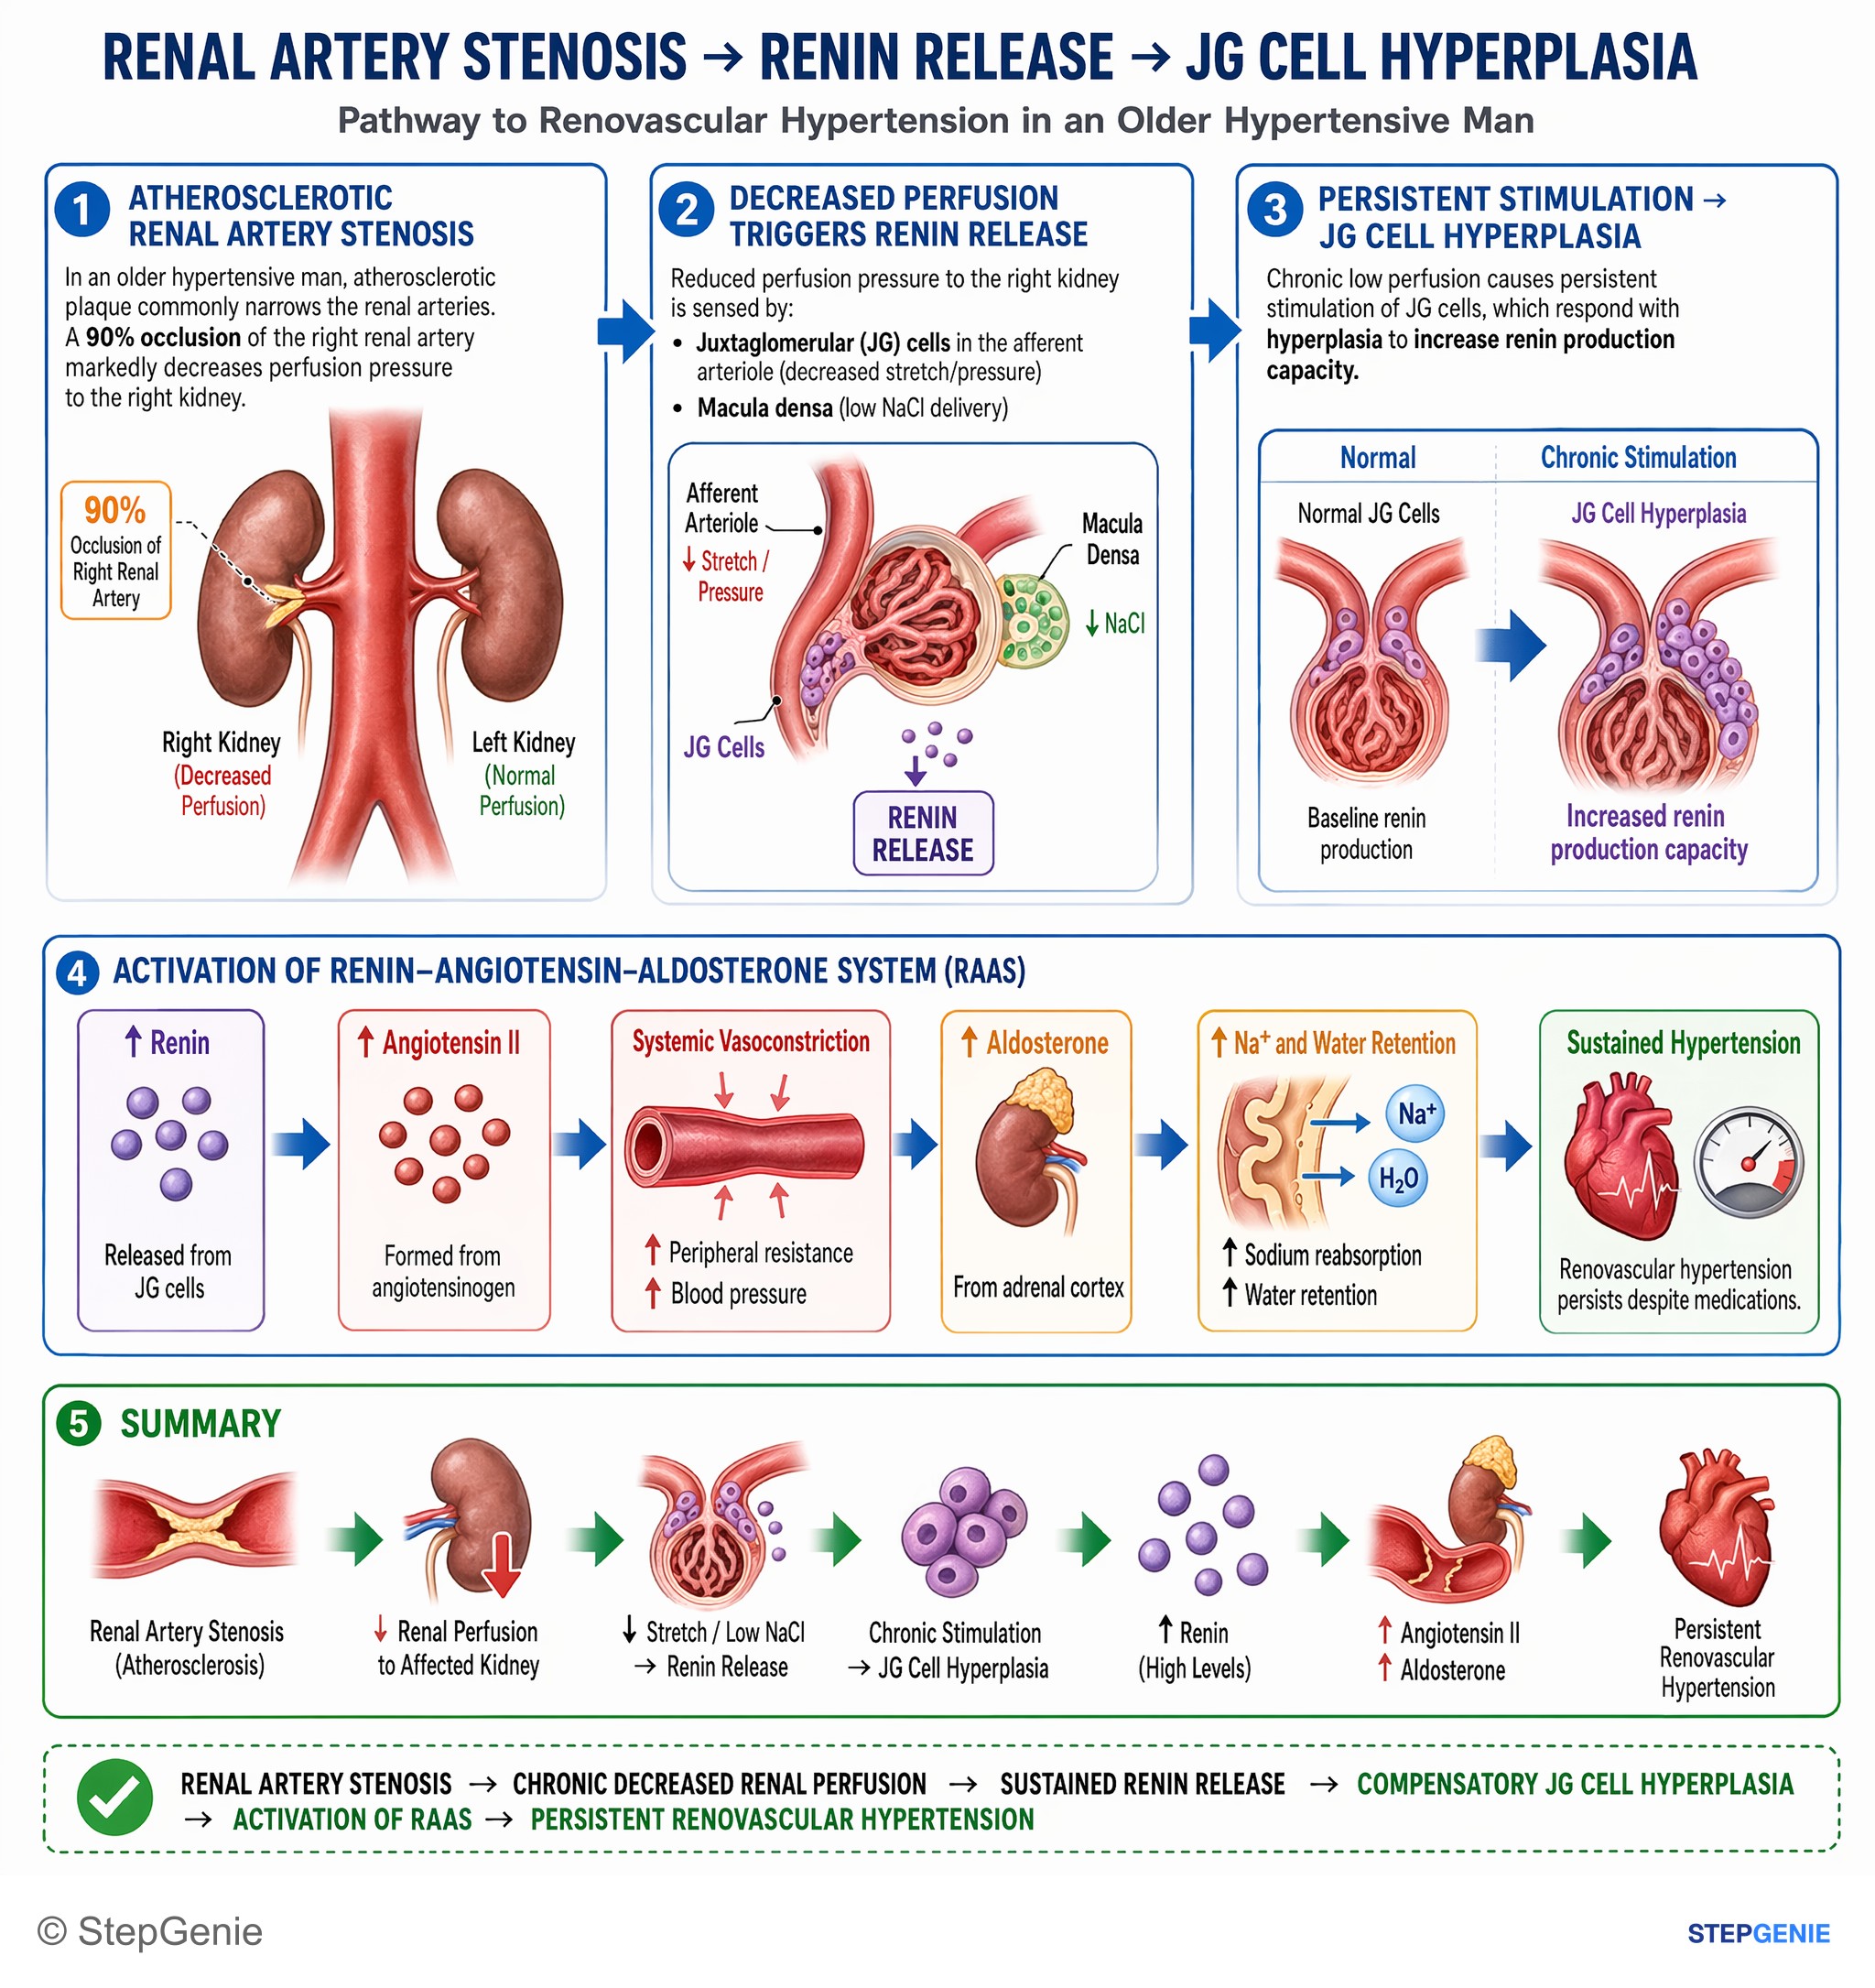
Renal artery stenosis → chronic decreased renal perfusion → sustained renin release → compensatory juxtaglomerular cell hyperplasia in the…
USMLE Step 1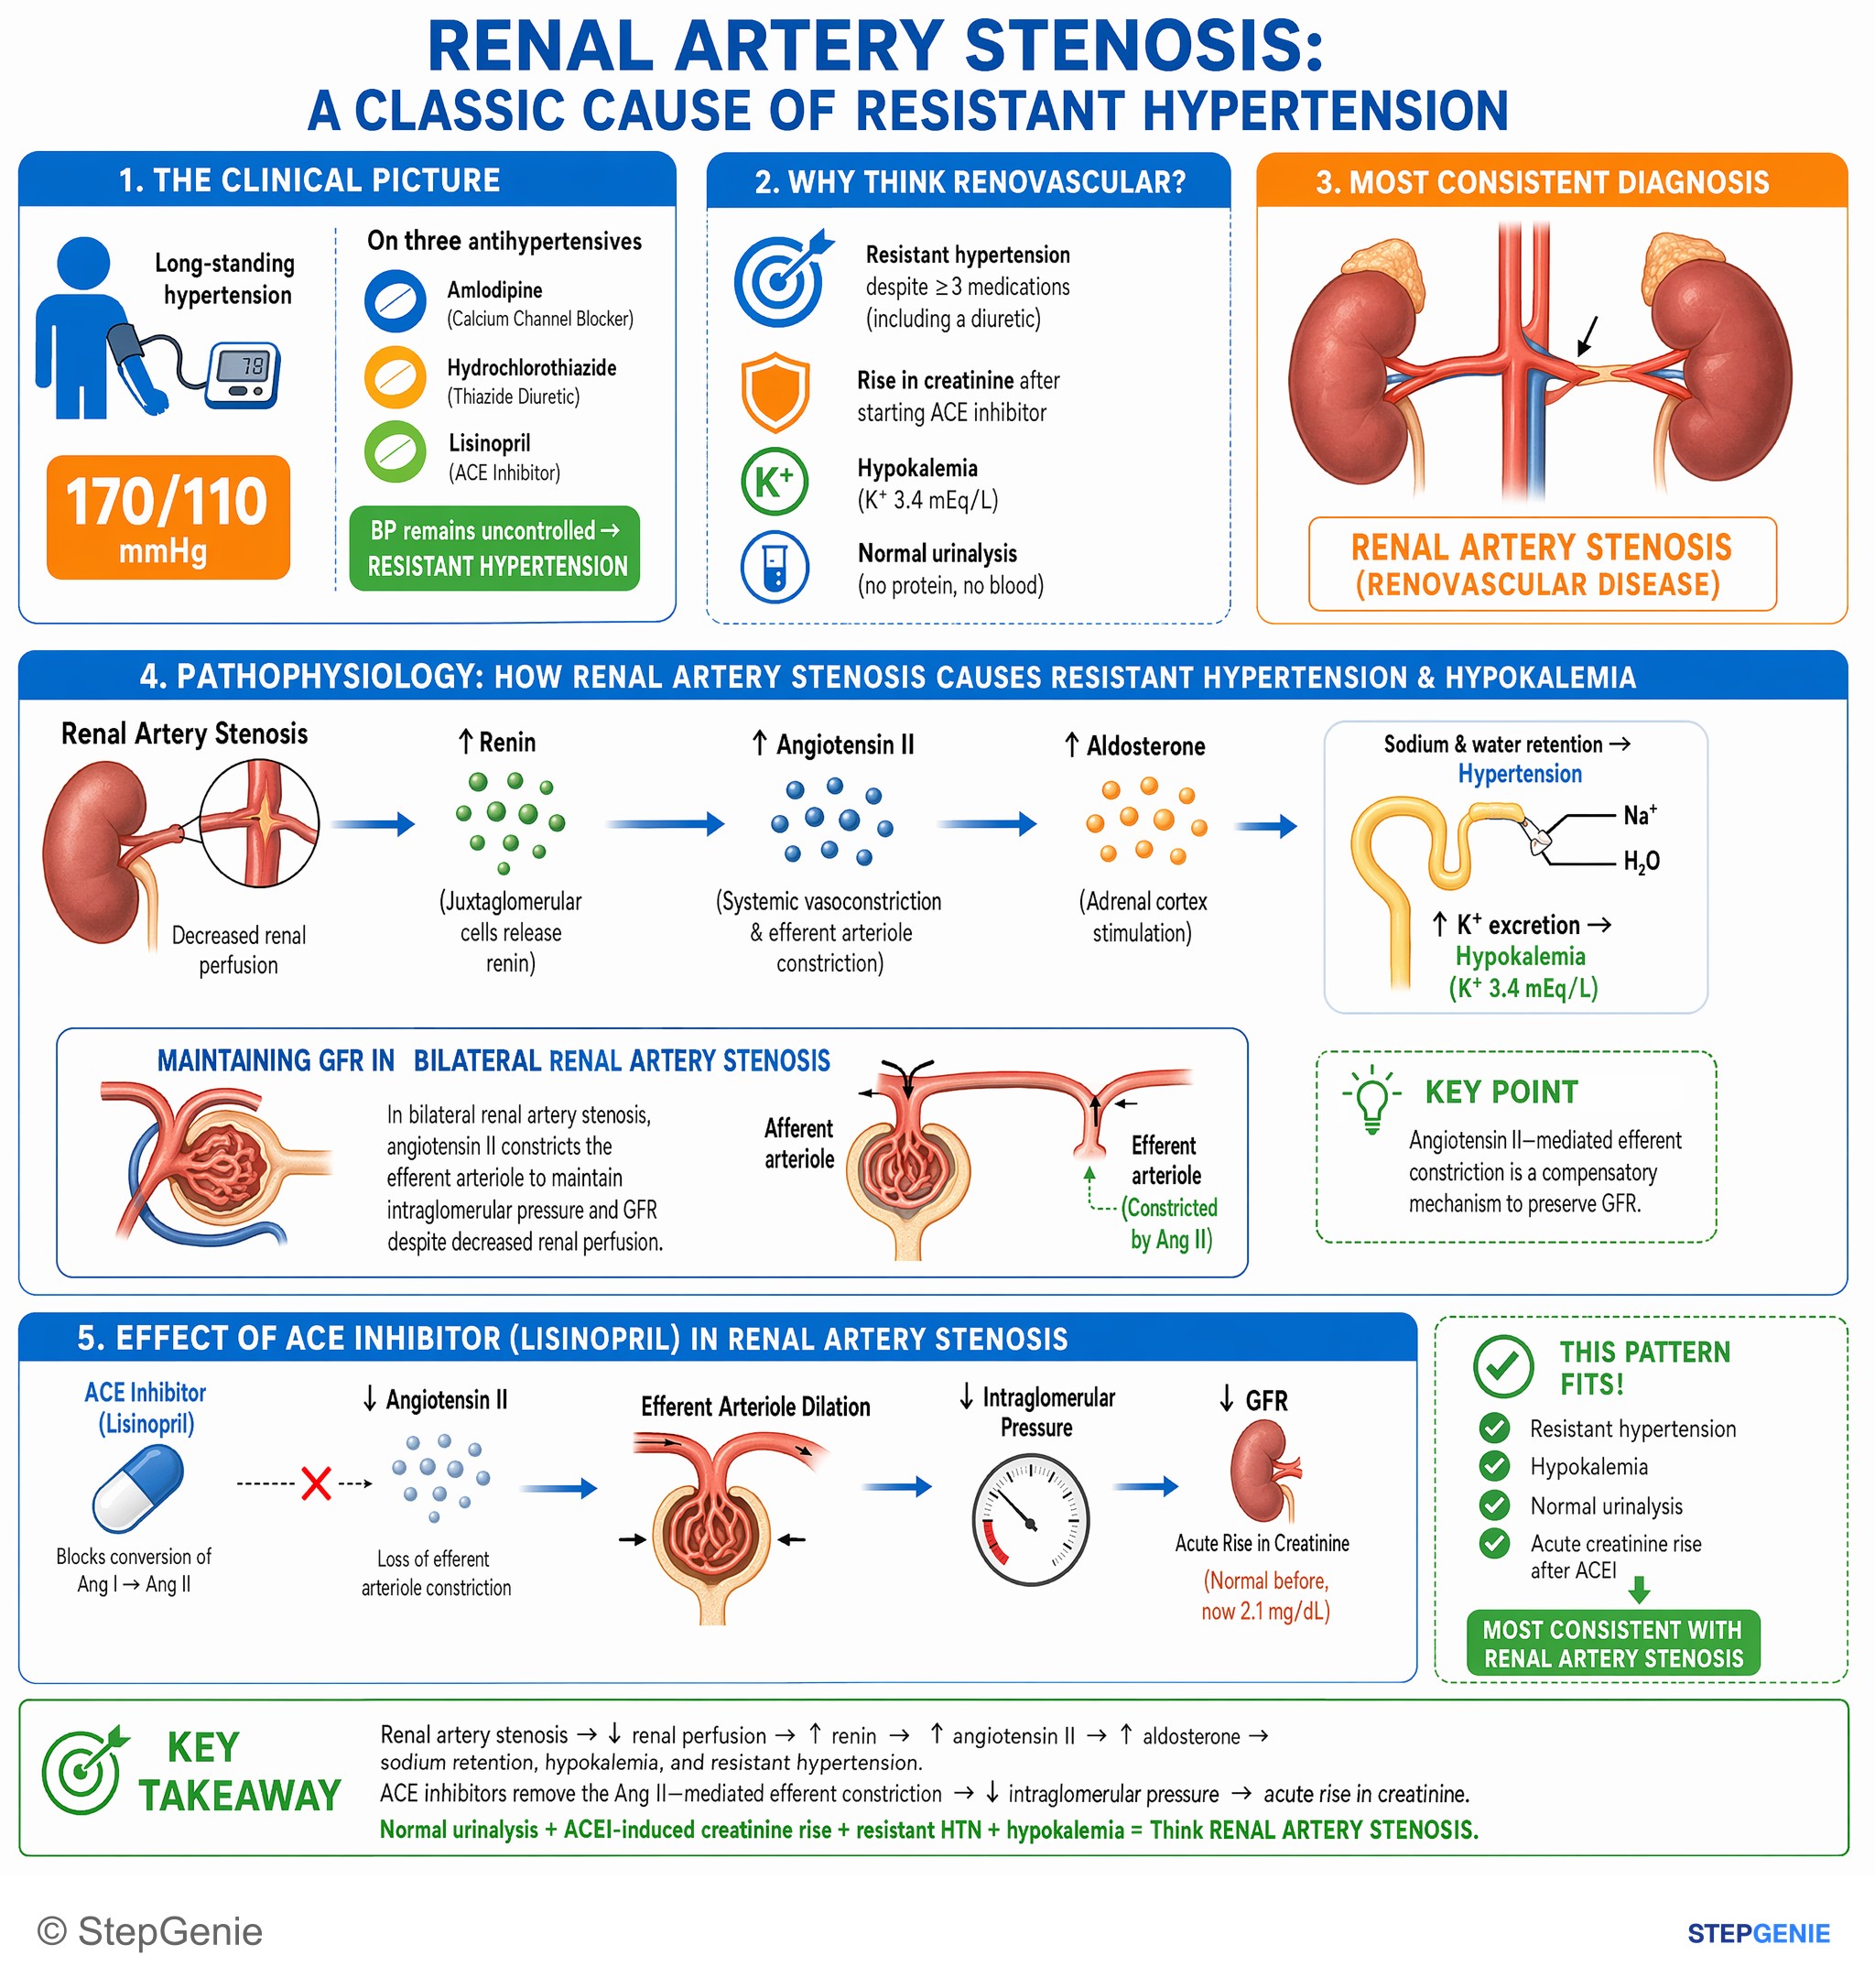
Renal artery stenosis from renovascular disease causes resistant hypertension, ACE-inhibitor–induced rise in creatinine, and secondary…
USMLE Step 2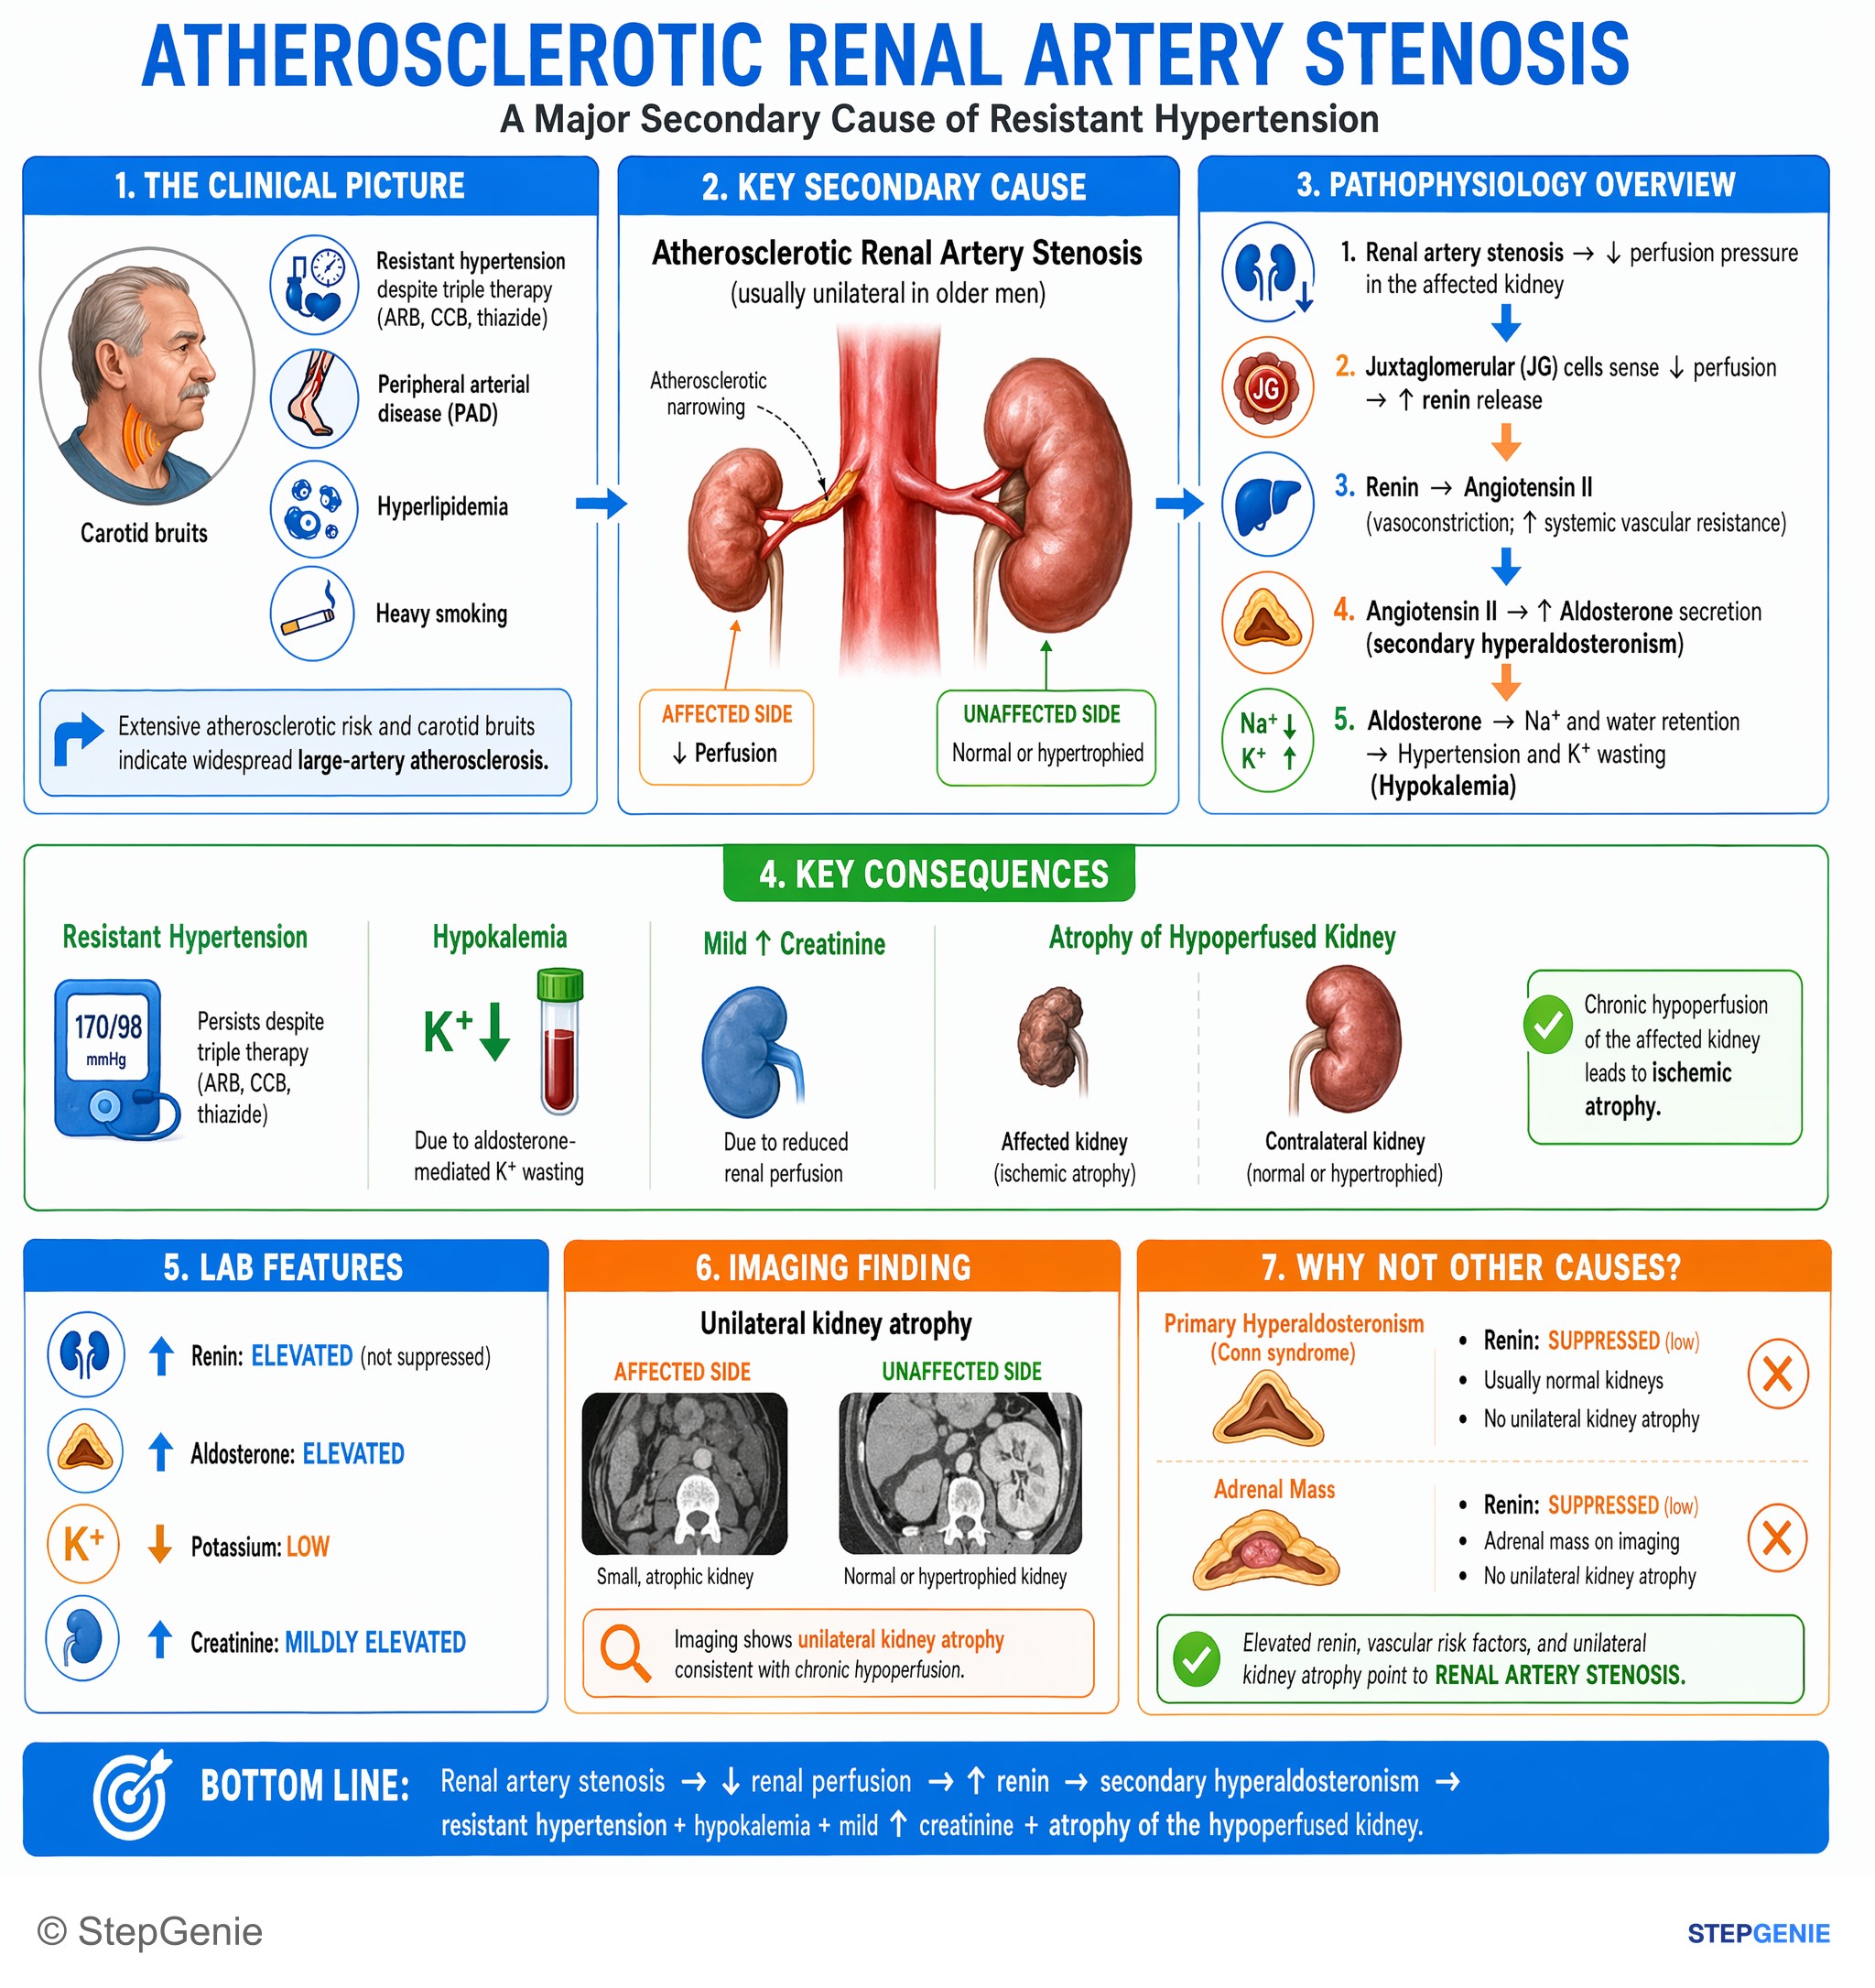
Renal artery stenosis → ↓ renal perfusion → ↑ renin, resistant hypertension, hypokalemia, mild ↑ creatinine, and atrophy of the…
USMLE Step 2Frequently Asked Questions
Why does renal artery stenosis cause hypokalemic metabolic alkalosis?
Renal artery stenosis causes hypokalemic metabolic alkalosis by increasing renin, angiotensin II, and then aldosterone. The narrowed renal artery lowers renal perfusion, so juxtaglomerular cells release renin and activate RAAS. Aldosterone then increases sodium and water retention while increasing potassium and hydrogen ion loss, which produces hypertension along with low potassium and metabolic alkalosis.
Why does creatinine rise after starting an ACE inhibitor or ARB in renal artery stenosis?
Creatinine rises because ACE inhibitors and ARBs remove angiotensin II–mediated efferent arteriolar constriction that is helping maintain glomerular pressure. In renal artery stenosis, perfusion to the kidney is already reduced, so the kidney relies on angiotensin II to preserve GFR. When that support is blocked, intraglomerular pressure falls, GFR drops, and serum creatinine increases.
How do you tell atherosclerotic renal artery stenosis from fibromuscular dysplasia?
Atherosclerotic renal artery stenosis usually occurs in an older adult with vascular risk factors and typically affects the ostium or proximal renal artery. Fibromuscular dysplasia classically occurs in a young woman, involves the mid-to-distal renal artery, and shows a “string of beads” on angiography. Fibromuscular dysplasia may also involve the carotid or vertebral arteries and often responds well to percutaneous angioplasty.
What clinical clues should make you suspect renal artery stenosis on a test question?
Renal artery stenosis should be suspected in secondary hypertension with resistant blood pressure, an abdominal bruit, unexplained hypokalemia, or a rise in creatinine after starting an ACE inhibitor or ARB. A classic board-style clue is severe hypertension plus an epigastric or flank bruit. The associated lab pattern is increased renin, increased aldosterone, low potassium, and metabolic alkalosis.
When are ACE inhibitors or ARBs especially risky in renal artery stenosis?
ACE inhibitors and ARBs are especially risky in bilateral renal artery stenosis or stenosis affecting a solitary functioning kidney. In those settings, both kidneys depend on angiotensin II–mediated efferent constriction to maintain glomerular filtration. Blocking that mechanism can significantly lower GFR and increase the risk of acute kidney injury, especially if the patient is volume depleted.