Diabetic nephropathy shows up in Q-banks the way “Staph aureus” shows up in abscess questions: often, with patterns you’re expected to recognize fast. The trick is that the wrong answers are also renal pathology greatest hits—so you need a clean mental algorithm to pick the right diagnosis and justify why everything else is wrong.
Tag: Renal > Glomerular Diseases
The Vignette (Q-bank style)
A 58-year-old man with a 15-year history of type 2 diabetes mellitus presents for routine follow-up. His A1c has been 9.2% over the past several years. BP is 154/92 mm Hg. He has mild bilateral ankle edema. Labs show:
- Serum creatinine: 1.8 mg/dL (baseline 1.2 last year)
- Urinalysis: 3+ protein, no RBC casts
- Urine albumin-to-creatinine ratio: 1,200 mg/g
- Lipids: elevated LDL
- Fundoscopy: diabetic retinopathy
Which renal histologic finding is most likely present?
A. Linear IgG deposition along the glomerular basement membrane
B. Nodular glomerulosclerosis with mesangial expansion
C. Crescent formation in Bowman space with pauci-immune staining
D. Diffuse thickening of capillary loops with “spike and dome” appearance
E. Congo red–positive deposits in glomeruli and vessel walls
The Correct Answer: B. Nodular glomerulosclerosis with mesangial expansion
Why this is diabetic nephropathy
This vignette screams advanced diabetic kidney disease:
- Longstanding diabetes with poor control
- Hypertension (both a cause and consequence of nephropathy)
- Heavy proteinuria (albuminuria in the nephrotic range)
- Progressive rise in creatinine
- Strong association with other microvascular disease: diabetic retinopathy
What you’re expected to know (high-yield pathology)
Diabetic nephropathy is driven by nonenzymatic glycation and hemodynamic stress → glomerular hyperfiltration early, then scarring.
Classic histology findings
- Mesangial expansion
- GBM thickening
- Kimmelstiel–Wilson nodules (nodular glomerulosclerosis)
- Hyaline arteriolosclerosis of both afferent and efferent arterioles (a favorite Step detail)
Hallmark clinical course
- Earliest: microalbuminuria (30–300 mg/day)
- Later: overt proteinuria (>300 mg/day) → can progress to nephrotic syndrome
- Progressive decline in GFR over time
Board-relevant mechanism (often tested)
- Hyperglycemia → ↑ SGLT2 proximal Na/glucose reabsorption → ↓ Na delivery to macula densa → afferent arteriole dilation → intraglomerular hypertension → damage.
- That’s why SGLT2 inhibitors are renoprotective (and why ACEi/ARBs help by ↓ efferent tone).
Rapid “Pattern Recognition” Box (USMLE-Style)
| Feature | Diabetic nephropathy |
|---|---|
| Proteinuria | Often albumin-predominant, can become nephrotic |
| UA sediment | Typically bland (no RBC casts) |
| Light microscopy | Nodular (Kimmelstiel–Wilson) or diffuse mesangial sclerosis |
| IF | Usually nonspecific; may see linear trapping of IgG/albumin (not the same as anti-GBM disease) |
| EM | GBM thickening, mesangial expansion |
| Vessels | Hyaline arteriolosclerosis afferent + efferent |
Why Each Distractor Is Wrong (and what it would indicate)
A. Linear IgG deposition along the GBM → Anti-GBM disease (Goodpasture)
Why it’s tempting: “Linear IgG” is memorable and sounds like diabetes because diabetes also has “linear changes” somewhere in your brain.
Why it’s wrong here:
- Anti-GBM classically presents with rapidly progressive glomerulonephritis (RPGN):
- Hematuria
- RBC casts
- Rising creatinine over days to weeks
- Often has pulmonary hemorrhage (hemoptysis) if Goodpasture syndrome.
What you should picture instead
- IF: Linear IgG and C3 along GBM (“painted basement membrane”)
- LM: Crescents
- Clinical: nephritic syndrome ± lung findings
Step tip: Diabetes can show linear staining due to nonspecific protein trapping, but the testable disease association for “linear IgG along GBM” is anti-GBM.
C. Crescents with pauci-immune staining → ANCA-associated vasculitis (GPA/MPA)
Why it’s wrong here:
- Pauci-immune crescentic GN is a nephritic picture:
- Hematuria and RBC casts
- Often systemic symptoms (fever, weight loss), ENT/lung findings (GPA), or pulmonary hemorrhage
- The vignette is protein-heavy, bland sediment, chronic DM.
What it would look like
- LM: Crescents
- IF: Pauci-immune (little/no immune deposits)
- Serology: c-ANCA (PR3) in GPA, p-ANCA (MPO) in MPA
D. “Spike and dome” with thickened capillary loops → Membranous nephropathy
Why it’s tempting: Nephrotic proteinuria fits. But the patient’s biggest risk factor isn’t membranous—it’s diabetes.
Why it’s wrong here:
- Membranous nephropathy is commonly linked to:
- PLA2R antibodies (primary)
- Secondary causes: HBV, HCV, solid tumors, SLE (class V), NSAIDs
- Diabetic nephropathy has mesangial expansion/nodules—not subepithelial spikes.
Key pathology
- EM: Subepithelial immune complex deposits
- Silver stain: “Spikes”
- IF: Granular (not linear) deposition along GBM
E. Congo red–positive deposits → Amyloidosis
Why it’s tempting: Another nephrotic syndrome cause. But the vignette points more strongly to diabetes (retinopathy + long duration + classic progression).
When to pick amyloid instead Look for:
- Multiple myeloma clues (bone pain, recurrent infections, elevated total protein)
- Chronic inflammatory disease (AA amyloid)
- Restrictive cardiomyopathy, hepatosplenomegaly, macroglossia, periorbital purpura
Key pathology
- Congo red: apple-green birefringence
- EM: randomly arranged fibrils
The “If You See This, Think Diabetes” Checklist
Choose diabetic nephropathy when you see:
- Longstanding diabetes + retinopathy/neuropathy
- Albuminuria progressing from micro → macro
- Hypertension with gradual GFR decline
- Bland urine sediment (no RBC casts)
High-Yield Clinical Management Pearls (Step 1 + Step 2)
- ACE inhibitor/ARB: reduces intraglomerular pressure (efferent dilation) → decreases proteinuria and slows progression.
- SGLT2 inhibitors: renoprotective beyond glucose control; reduce hyperfiltration and slow CKD progression.
- Tight BP control is as important as glucose control for renal outcomes.
- Screening: annual urine albumin-to-creatinine ratio in diabetes (timing depends on type: at diagnosis for T2DM; 5 years after diagnosis for T1DM).
- Complications: nephrotic-range proteinuria → edema, hyperlipidemia, hypercoagulability (think loss of antithrombin III).
Takeaway: Why Every Answer Choice Matters
This question isn’t just “know diabetic nephropathy.” It’s “separate the big nephrotic syndromes and the crescentic/nephritic syndromes under pressure.” Diabetes gives you progressive albuminuria + bland sediment + mesangial expansion/Kimmelstiel–Wilson nodules, while the distractors each point to a different immune pattern, EM finding, and clinical tempo.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
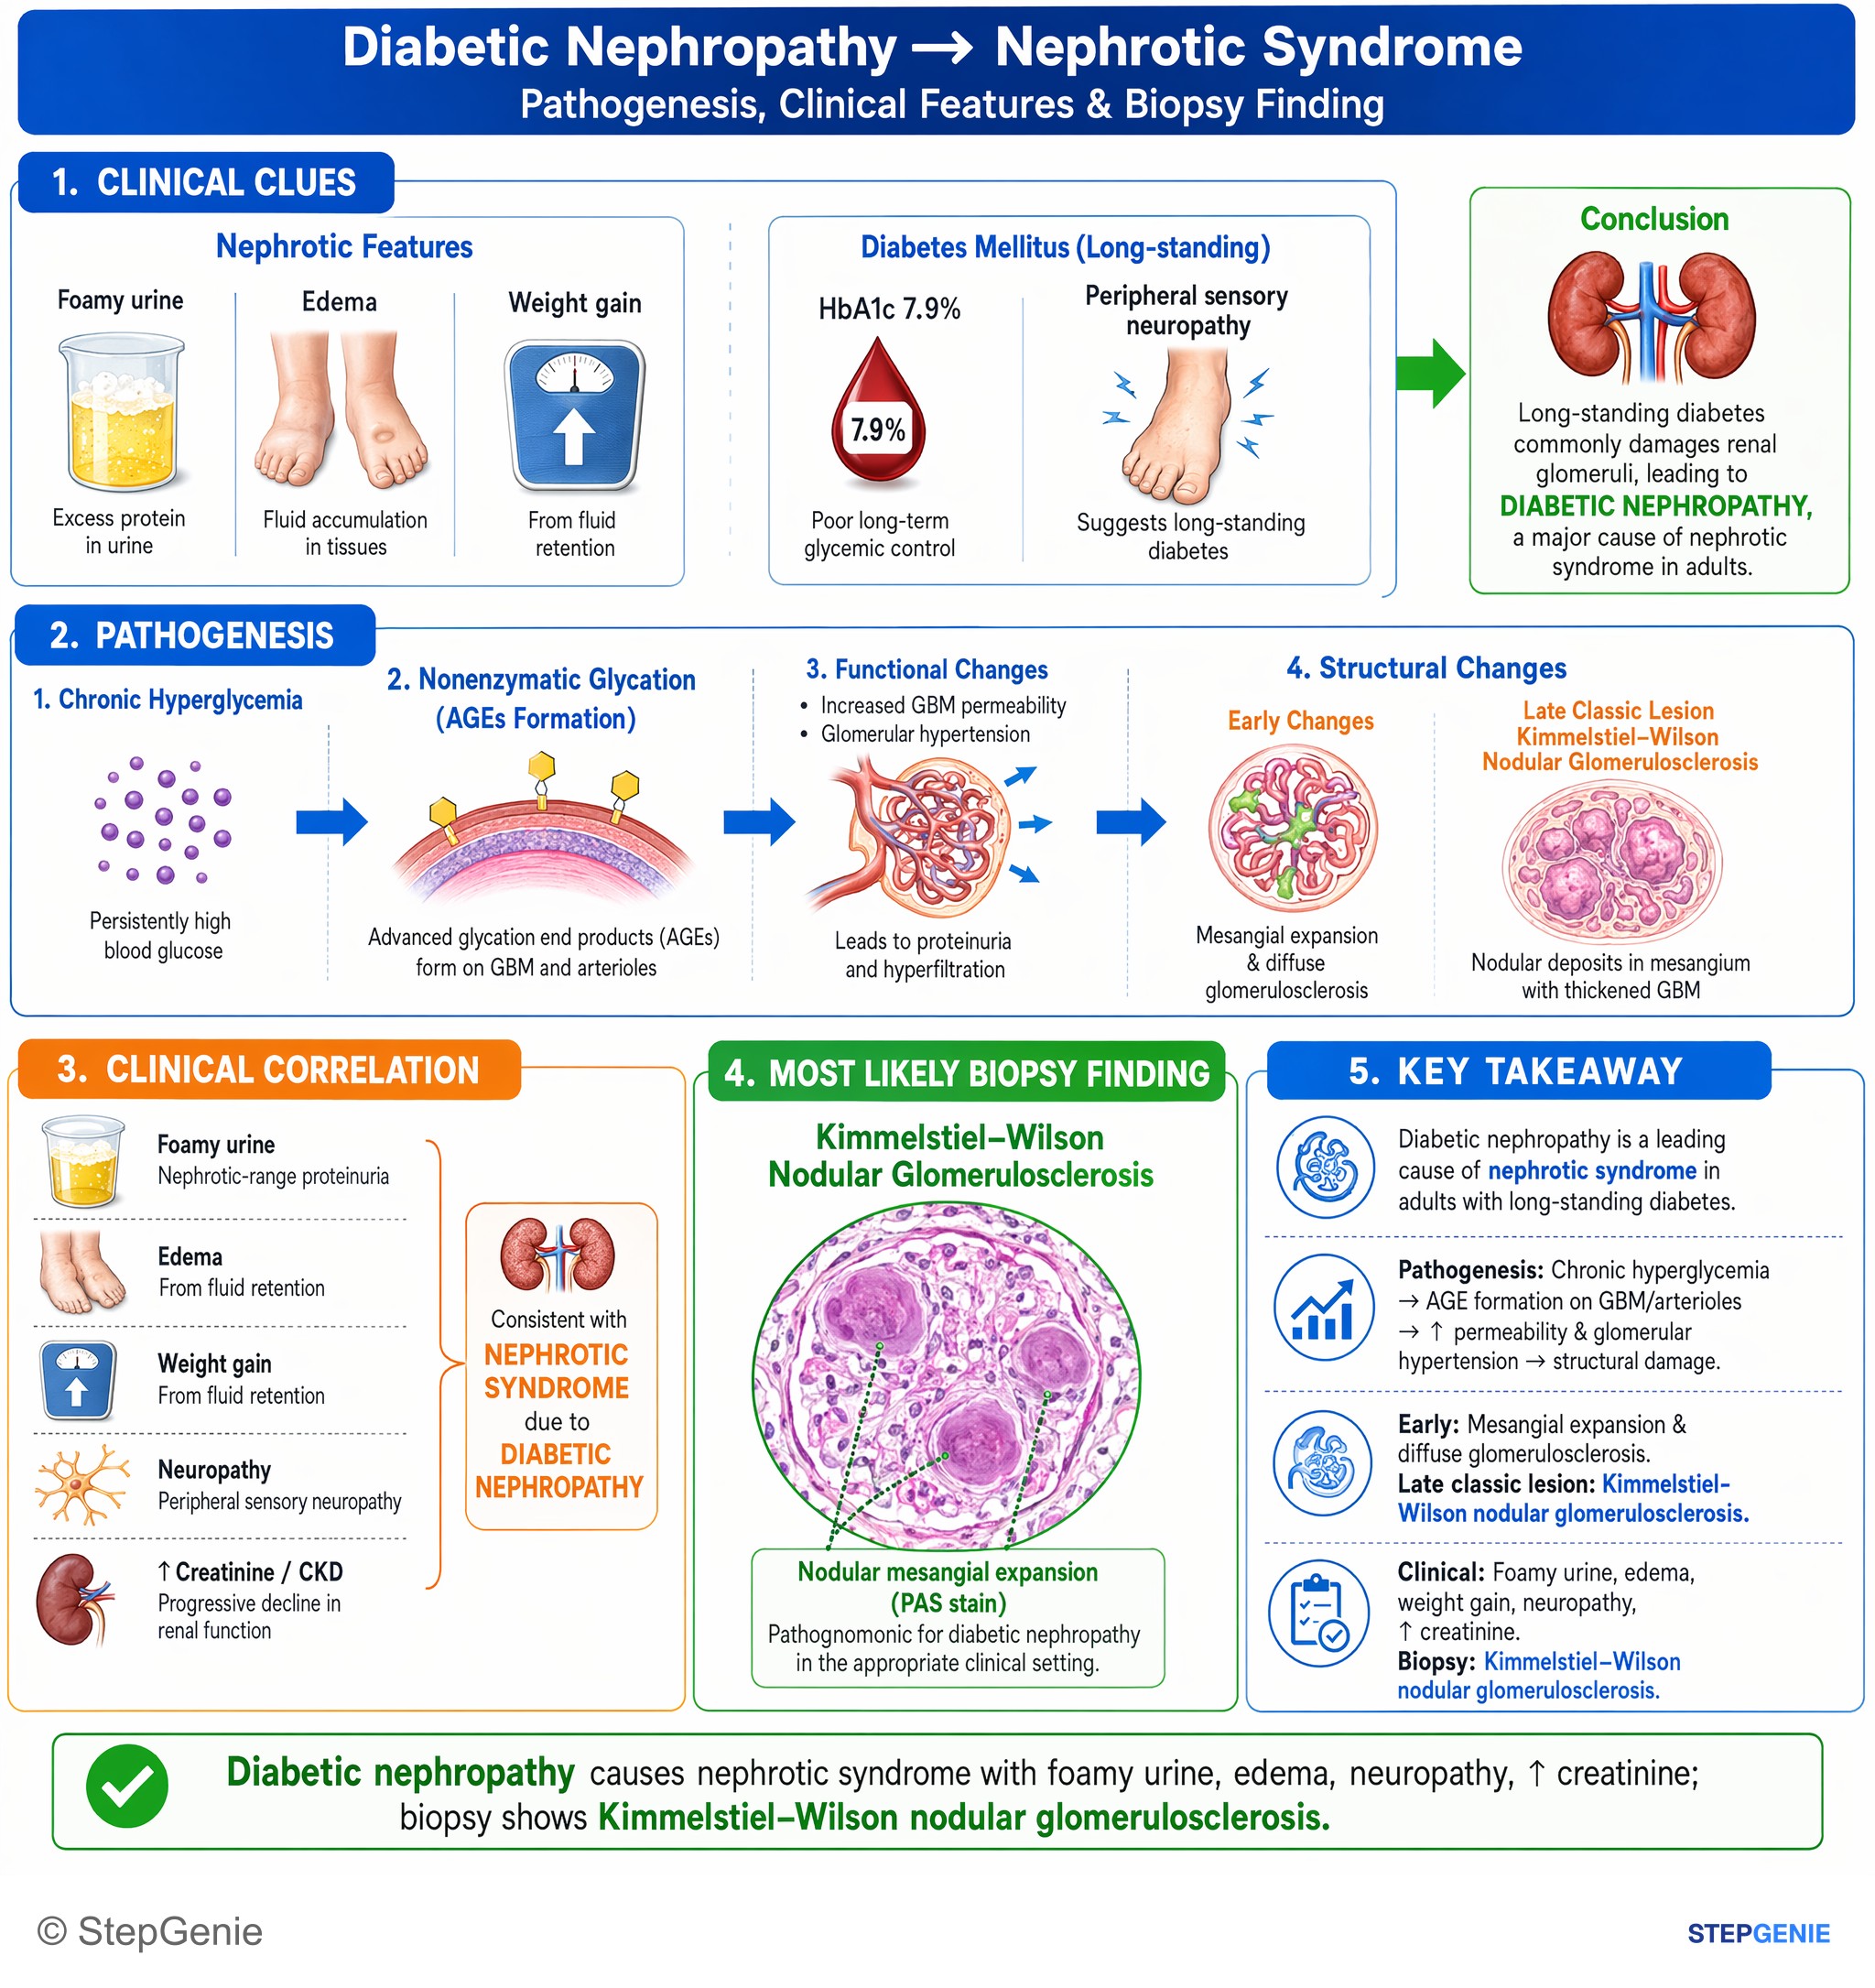
Diabetic nephropathy causes nephrotic syndrome with foamy urine, edema, neuropathy, ↑creatinine; biopsy shows Kimmelstiel–Wilson nodular…
USMLE Step 1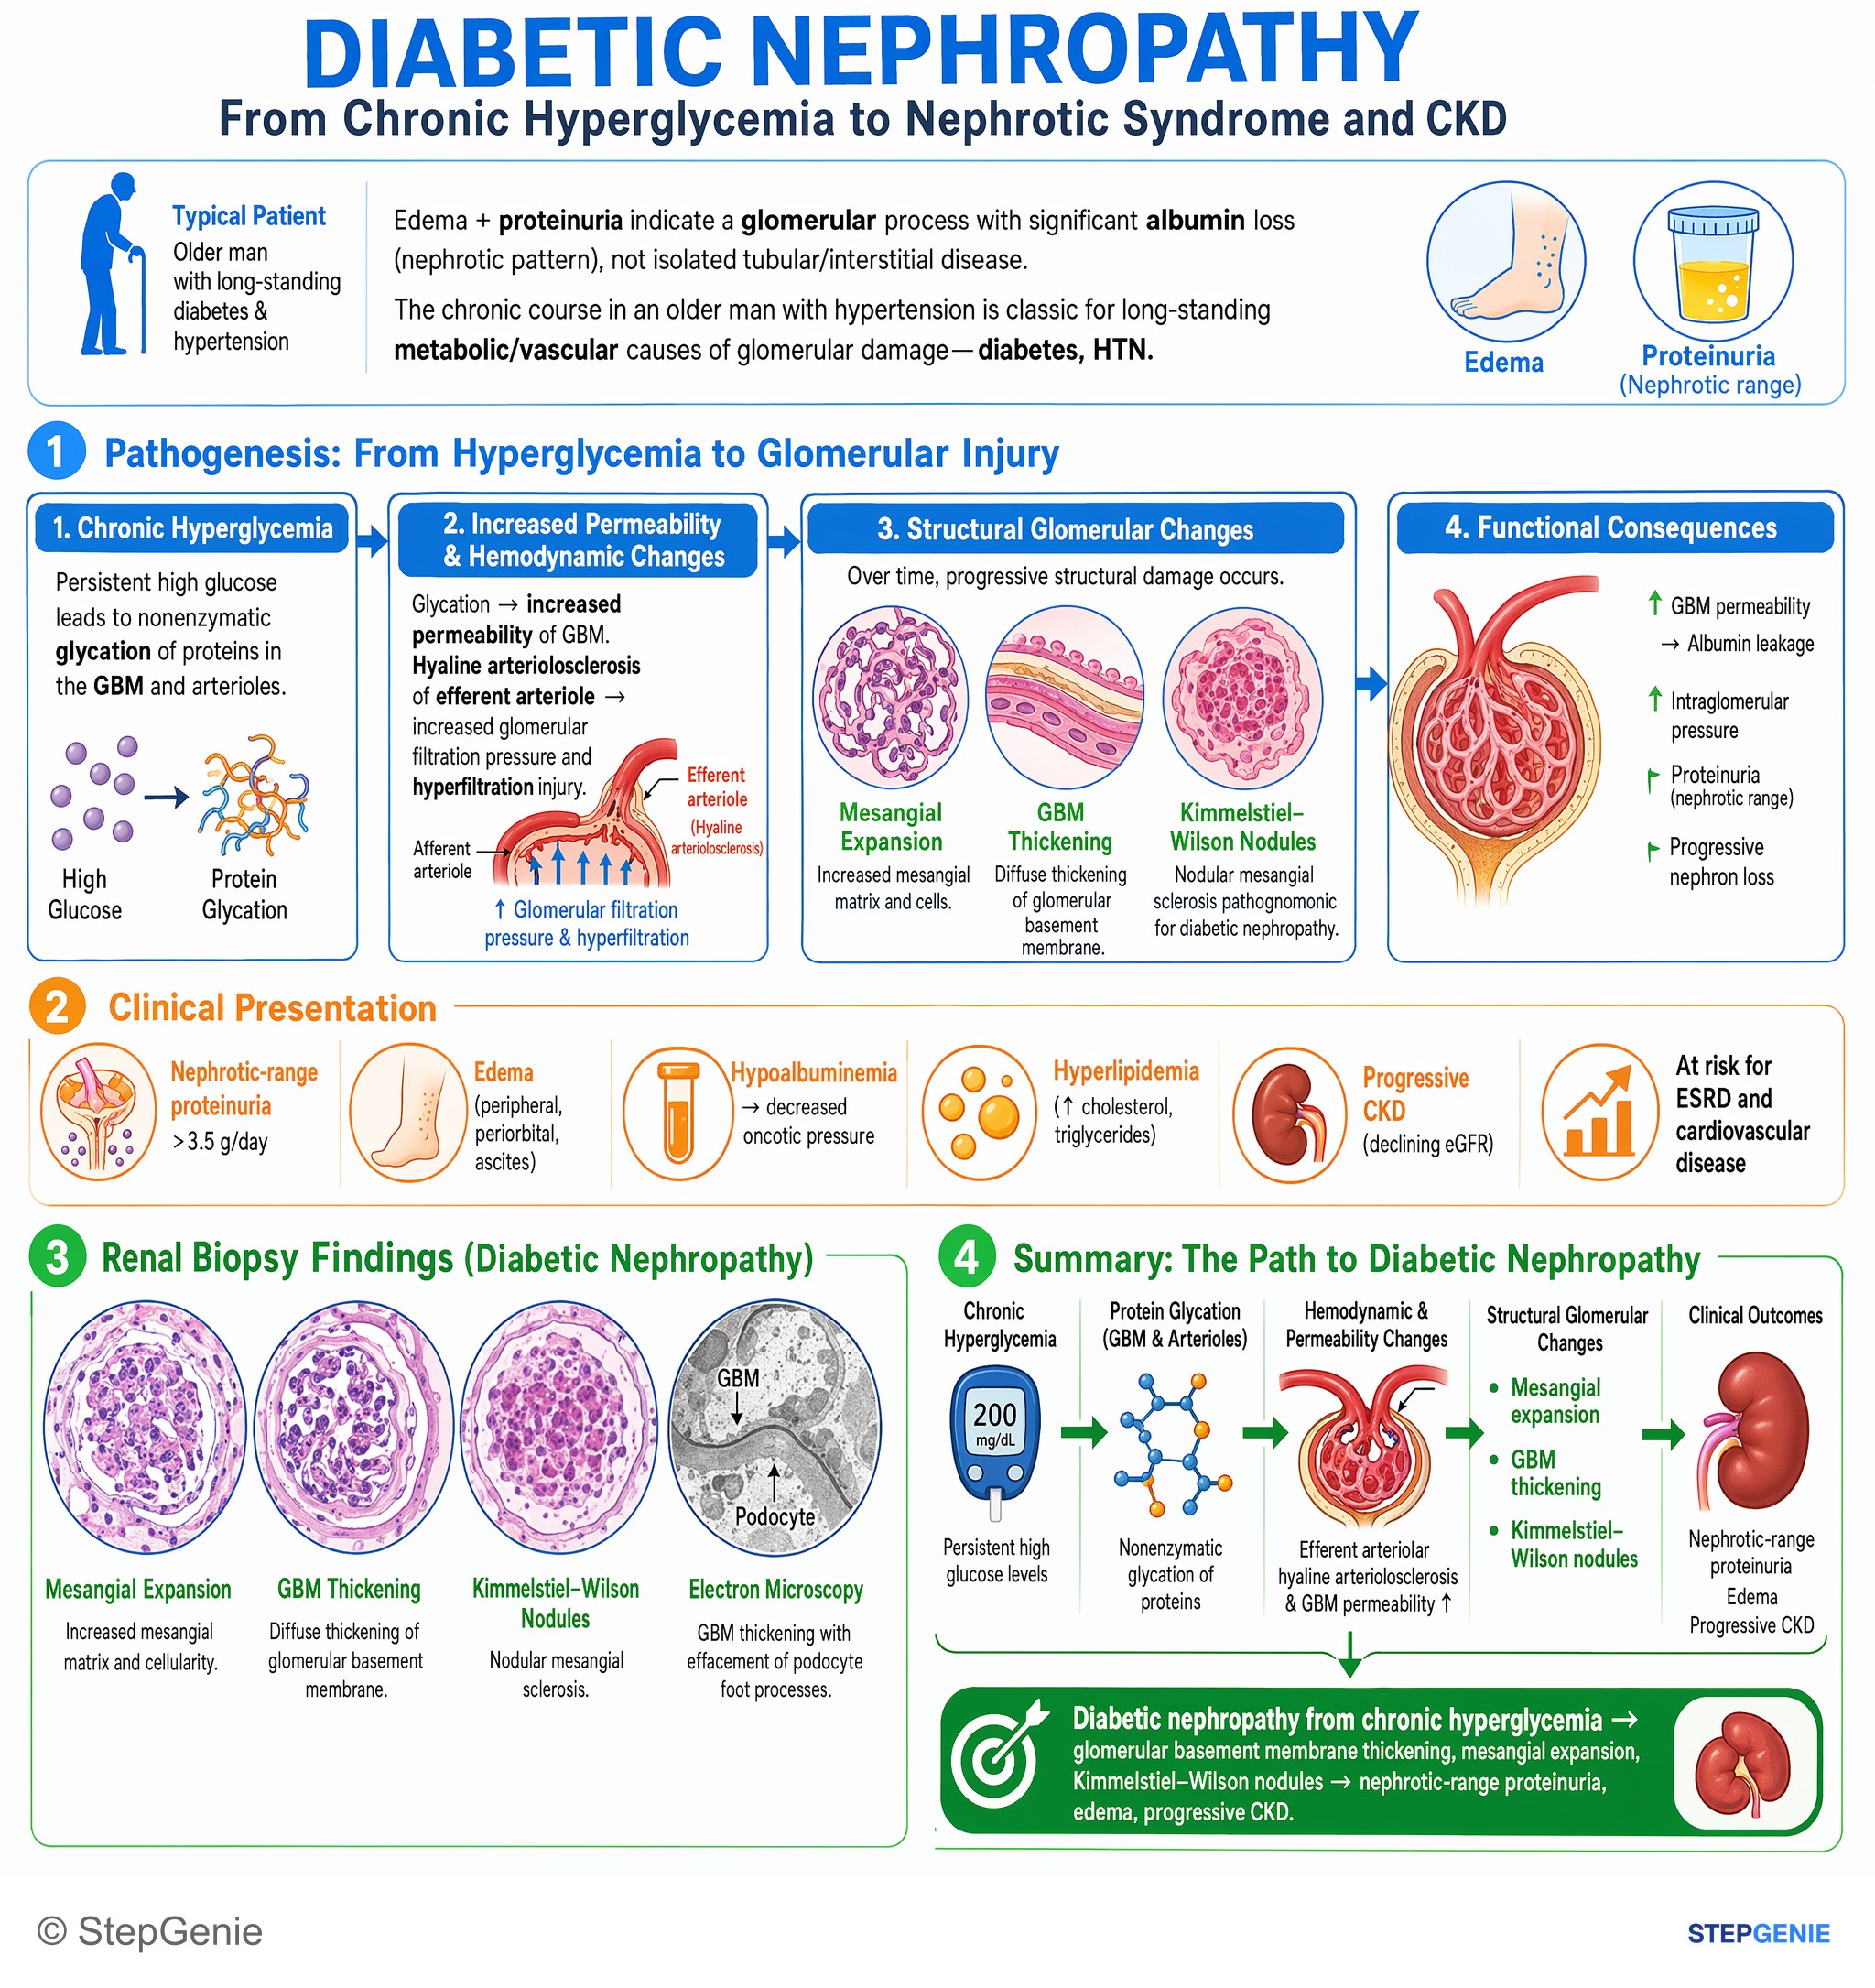
Diabetic nephropathy from chronic hyperglycemia → glomerular basement membrane thickening, mesangial expansion, Kimmelstiel–Wilson…
USMLE Step 1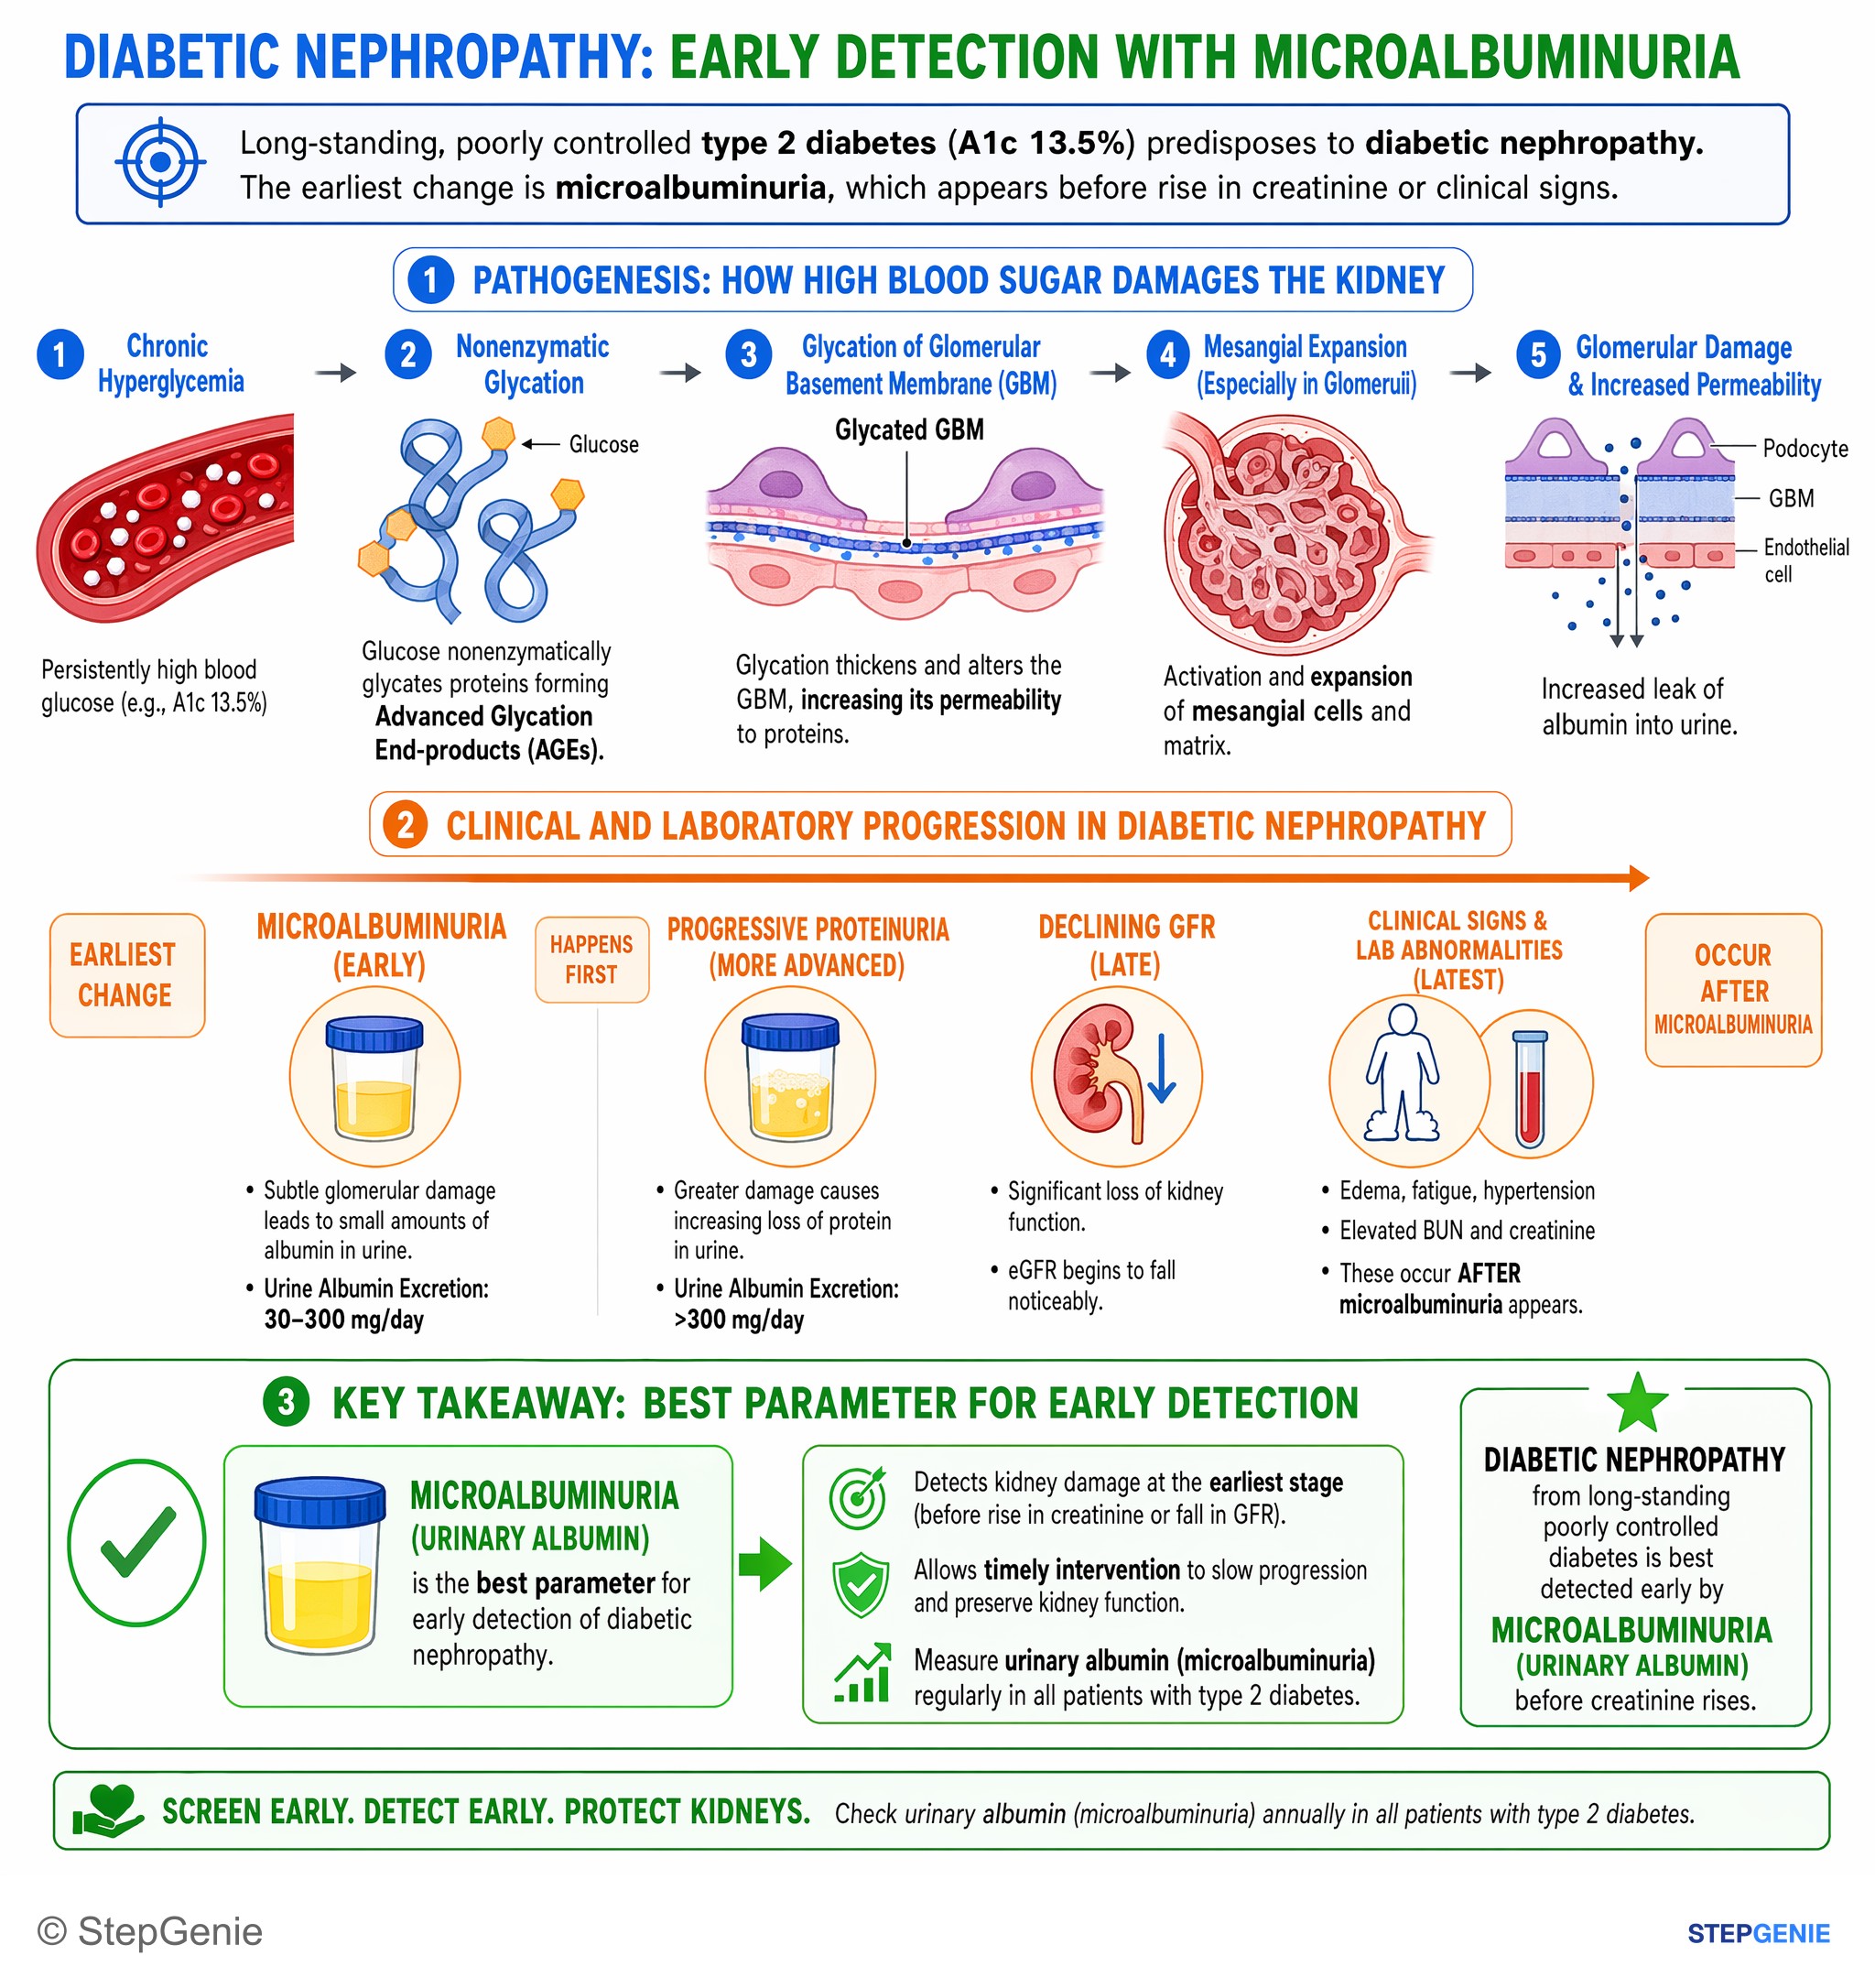
Diabetic nephropathy from long-standing poorly controlled diabetes is best detected early by microalbuminuria (urinary albumin) before…
USMLE Step 1Frequently Asked Questions
What histologic finding points to diabetic nephropathy in a patient with long-standing diabetes and heavy proteinuria?
The classic histologic finding is nodular glomerulosclerosis with mesangial expansion. In diabetic nephropathy, long-standing hyperglycemia causes nonenzymatic glycation and hemodynamic stress, which lead to mesangial expansion, GBM thickening, and Kimmelstiel–Wilson nodules. In a patient with poorly controlled diabetes, hypertension, rising creatinine, heavy albuminuria, and diabetic retinopathy, that pattern strongly supports diabetic kidney disease.
Why does hyperglycemia cause glomerular damage in diabetic nephropathy?
Hyperglycemia causes glomerular damage through increased proximal sodium and glucose reabsorption and resulting intraglomerular hypertension. The sequence is increased SGLT2-mediated Na/glucose reabsorption, decreased sodium delivery to the macula densa, afferent arteriole dilation, and higher pressure within the glomerulus. Over time, this hemodynamic stress, together with nonenzymatic glycation, drives early hyperfiltration and later scarring.
How do you tell diabetic nephropathy from anti-GBM disease on a renal question stem?
Diabetic nephropathy usually presents with heavy albumin-predominant proteinuria and a bland urine sediment, while anti-GBM disease presents as a rapidly progressive nephritic syndrome. Anti-GBM classically causes hematuria, RBC casts, and a creatinine rise over days to weeks, often with pulmonary hemorrhage. Diabetic nephropathy instead fits a chronic course with longstanding diabetes, hypertension, progressive creatinine increase, and diabetic retinopathy.
What is the earliest clinical sign of diabetic nephropathy?
The earliest clinical sign is microalbuminuria. Diabetic nephropathy typically starts with urine albumin excretion in the microalbuminuric range, then progresses to overt proteinuria and can eventually reach nephrotic levels. As the disease advances, GFR declines over time. This stepwise pattern is a hallmark clinical course of diabetic kidney disease.
What Step-style clue strongly supports diabetic nephropathy over other causes of nephrotic syndrome?
Diabetic retinopathy in a patient with longstanding diabetes is a strong clue favoring diabetic nephropathy. The association between diabetic kidney disease and other microvascular complications, especially retinopathy, helps distinguish it from other nephrotic causes. When retinopathy appears alongside poor glycemic control, hypertension, heavy proteinuria, and gradually rising creatinine, diabetic nephropathy becomes much more likely than membranous nephropathy or amyloidosis.