Electrolyte questions are the ultimate “every answer choice matters” traps—especially potassium. On Step 1/2, you’re rarely just asked “what’s the potassium?” You’re asked to identify the mechanism (shift vs true loss), anticipate ECG changes, connect acid–base physiology, and pick the single management step that prevents a bad outcome. Let’s break down a classic Q-bank-style vignette and then dissect each distractor like you would on test day.
Tag: Renal > Fluid, Electrolytes & Acid-Base
The Clinical Vignette (Q-bank style)
A 58-year-old man with type 2 diabetes and hypertension comes to the ED for weakness and palpitations. He missed dialysis this week due to travel. Medications include lisinopril. Vitals: BP 148/86, HR 112. Exam shows mild muscle weakness. ECG shows tall, narrow, peaked T waves. Labs:
- Na⁺ 138 mEq/L
- K⁺ 6.9 mEq/L
- Cl⁻ 102 mEq/L
- HCO₃⁻ 18 mEq/L
- BUN/Cr elevated (known ESRD)
Question: What is the most appropriate immediate next step?
Correct Answer: IV calcium gluconate
Why it’s correct
This patient has severe hyperkalemia with ECG changes. The immediate threat is ventricular arrhythmia due to potassium’s effect on cardiac membrane excitability. IV calcium gluconate stabilizes the cardiac myocyte membrane quickly (minutes), reducing risk of lethal dysrhythmias.
Key point:
- Calcium does not lower serum potassium.
- It buys time while you shift K⁺ into cells and remove it from the body.
The High-Yield Framework: Hyperkalemia Management (in order)
Think of three goals—stabilize, shift, shred (remove).
| Goal | Intervention | Onset | What it does |
|---|---|---|---|
| Stabilize myocardium | IV calcium gluconate (or calcium chloride) | Minutes | Raises threshold potential → protects heart |
| Shift K⁺ into cells | Insulin + dextrose, β₂-agonist (albuterol) | 15–30 min | Drives K⁺ intracellularly |
| Shift K⁺ into cells (if acidotic) | Sodium bicarbonate (selected cases) | Variable | Helps in metabolic acidosis (not reliable alone) |
| Remove K⁺ from body | Dialysis, loop diuretics (if making urine), potassium binders | Hours | Definitive elimination |
ESRD clue: If they missed dialysis and are oliguric/anuric, dialysis is definitive—but calcium comes first when ECG changes are present.
Now the Money Part: Why Each Distractor Is Wrong (or incomplete)
Below are common answer choices on USMLE-style items—your job is to eliminate them for the right reason.
Distractor 1: Insulin with dextrose
Why it’s tempting: It’s a cornerstone therapy and lowers potassium quickly.
Why it’s not the best immediate step here: ECG changes = unstable electrical substrate. You stabilize the myocardium first with calcium.
- Insulin moves K⁺ into cells by stimulating Na⁺/K⁺-ATPase.
- Dextrose prevents hypoglycemia (unless glucose already very high—some vignettes will let you skip dextrose).
Test-day rule:
- HyperK + ECG changes → Calcium first, then insulin/glucose.
Distractor 2: Albuterol (β₂-agonist)
Why it’s tempting: Also shifts K⁺ intracellularly.
Why it’s not the best immediate step: Same issue—doesn’t stabilize the myocardium. Also, response can be variable and less predictable than insulin.
Extra high yield: β₂-agonists stimulate Na⁺/K⁺-ATPase → intracellular K⁺ shift.
(And yes, this is why albuterol can cause hypokalemia.)
Distractor 3: Sodium bicarbonate
Why it’s tempting: The patient is acidotic (HCO₃⁻ 18), and acidosis is associated with hyperkalemia.
Why it’s usually not the first move: Bicarbonate is not reliably effective for acute hyperkalemia unless there’s significant metabolic acidosis and even then is adjunctive—not definitive and not myocardium-stabilizing.
High-yield physiology (Step 1 favorite):
- In metabolic acidosis, H⁺ moves into cells → K⁺ tends to move out to maintain electroneutrality → hyperkalemia.
- Exception you’ll see tested: organic acidosis (e.g., lactic acidosis, ketoacidosis) causes less K⁺ shift than mineral acidosis because the organic anions often enter cells with H⁺.
Distractor 4: Furosemide (loop diuretic)
Why it’s tempting: Loops increase urinary K⁺ excretion.
Why it’s wrong here: ESRD patient who missed dialysis likely has minimal urine output, so loop diuretics won’t remove enough K⁺ quickly (or at all).
When loops are reasonable: Hyperkalemia in a patient who is making urine, volume overloaded, or needs enhanced renal potassium excretion.
Distractor 5: Sodium polystyrene sulfonate (kayexalate) / potassium binders
Why it’s tempting: “Removes potassium from the body” sounds definitive.
Why it’s wrong as the immediate step: Onset is too slow for ECG-changes hyperkalemia. Also, older binders have safety/efficacy caveats.
- Kayexalate has been associated with intestinal necrosis (especially with sorbitol; classic caution).
- Newer binders (patiromer, sodium zirconium cyclosilicate) are more often used in chronic management—still not your acute “save the heart now” answer.
Distractor 6: Stop the ACE inhibitor (lisinopril)
Why it’s tempting: ACE inhibitors reduce aldosterone → can cause hyperkalemia.
Why it’s incomplete: Stopping the cause doesn’t treat the current life-threatening hyperkalemia with ECG changes.
High-yield mechanism:
- ↓ Angiotensin II → ↓ aldosterone → ↓ ENaC activity in principal cells → ↓ K⁺ secretion.
Distractor 7: Normal saline infusion
Why it’s tempting: Fluids are often “safe.”
Why it’s wrong: This is not primarily a volume depletion problem, and fluids won’t acutely fix dangerous hyperkalemia in ESRD (and may worsen volume overload).
ECG Progression You Must Know (HyperK vs HypoK)
Hyperkalemia ECG (in order—classic progression)
- Peaked T waves
- Prolonged PR
- Widened QRS
- Loss of P waves
- Sine wave → VF/asystole
Hypokalemia ECG
- Flattened T waves
- U waves
- ST depression, prolonged QT (often functionally “longer repolarization”)
- Increased risk of arrhythmias (esp. with digoxin)
USMLE pearl: If the vignette gives ECG changes, you’re supposed to treat the rhythm risk—not just “fix the number.”
Rapid-Fire High-Yield: Hypokalemia vs Hyperkalemia Differentials
Step 1/2 must-sort question: “Is it a shift or a true deficit/excess?”
Hypokalemia causes
Shift into cells (serum low, total body K normal):
- Insulin
- β₂-agonists (albuterol)
- Alkalosis
True loss (total body K low):
- GI loss: diarrhea (often metabolic acidosis), vomiting (metabolic alkalosis)
- Renal loss: diuretics (loop/thiazide), hyperaldosteronism, renal tubular disorders
- Hypomagnesemia (impairs K repletion)
Hyperkalemia causes
Shift out of cells (total body K may be normal):
- Acidosis (esp mineral)
- Insulin deficiency (DKA has hyperkalemia despite total-body K depletion)
- Cell lysis: rhabdomyolysis, tumor lysis, hemolysis
- β-blockers (less cellular uptake)
True excess or impaired excretion:
- Renal failure
- Hypoaldosteronism (Type 4 RTA)
- Drugs: ACEi/ARB, spironolactone/eplerenone, amiloride/triamterene, TMP-SMX (acts like amiloride), NSAIDs (↓ renin)
Mini-Bridge to Acid–Base (USMLE loves this connection)
Type 4 RTA = Hyperkalemic metabolic acidosis
- Mechanism: hypoaldosteronism or aldosterone resistance → decreased H⁺ secretion (α-intercalated) and decreased K⁺ secretion (principal cells)
- Common in diabetics (hyporeninemic hypoaldosteronism)
- Labs: normal anion gap metabolic acidosis + hyperkalemia
Memory anchor: Type 4 is the only RTA with high K.
How This Looks on Test Day: “What are they really asking?”
If the stem gives…
- K ≥ 6.5 OR ECG changes → IV calcium (stabilize)
- No ECG changes but high K → shift (insulin/glucose, albuterol) + remove cause/elimination
- ESRD + missed dialysis → strong lean toward dialysis as definitive removal (after calcium if ECG changes)
- DKA → potassium may be high but total-body K is low → once insulin starts, K will drop
Take-Home Cheat Sheet (what to remember under pressure)
- Calcium gluconate = membrane stabilization (fastest life-saving step with ECG changes).
- Insulin + dextrose = fastest reliable shift (but doesn’t stabilize).
- Dialysis = definitive in ESRD (but don’t skip calcium when ECG is abnormal).
- Hypokalemia + can’t replete = check magnesium.
- Type 4 RTA = hyperK + NAGMA, often in diabetics.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
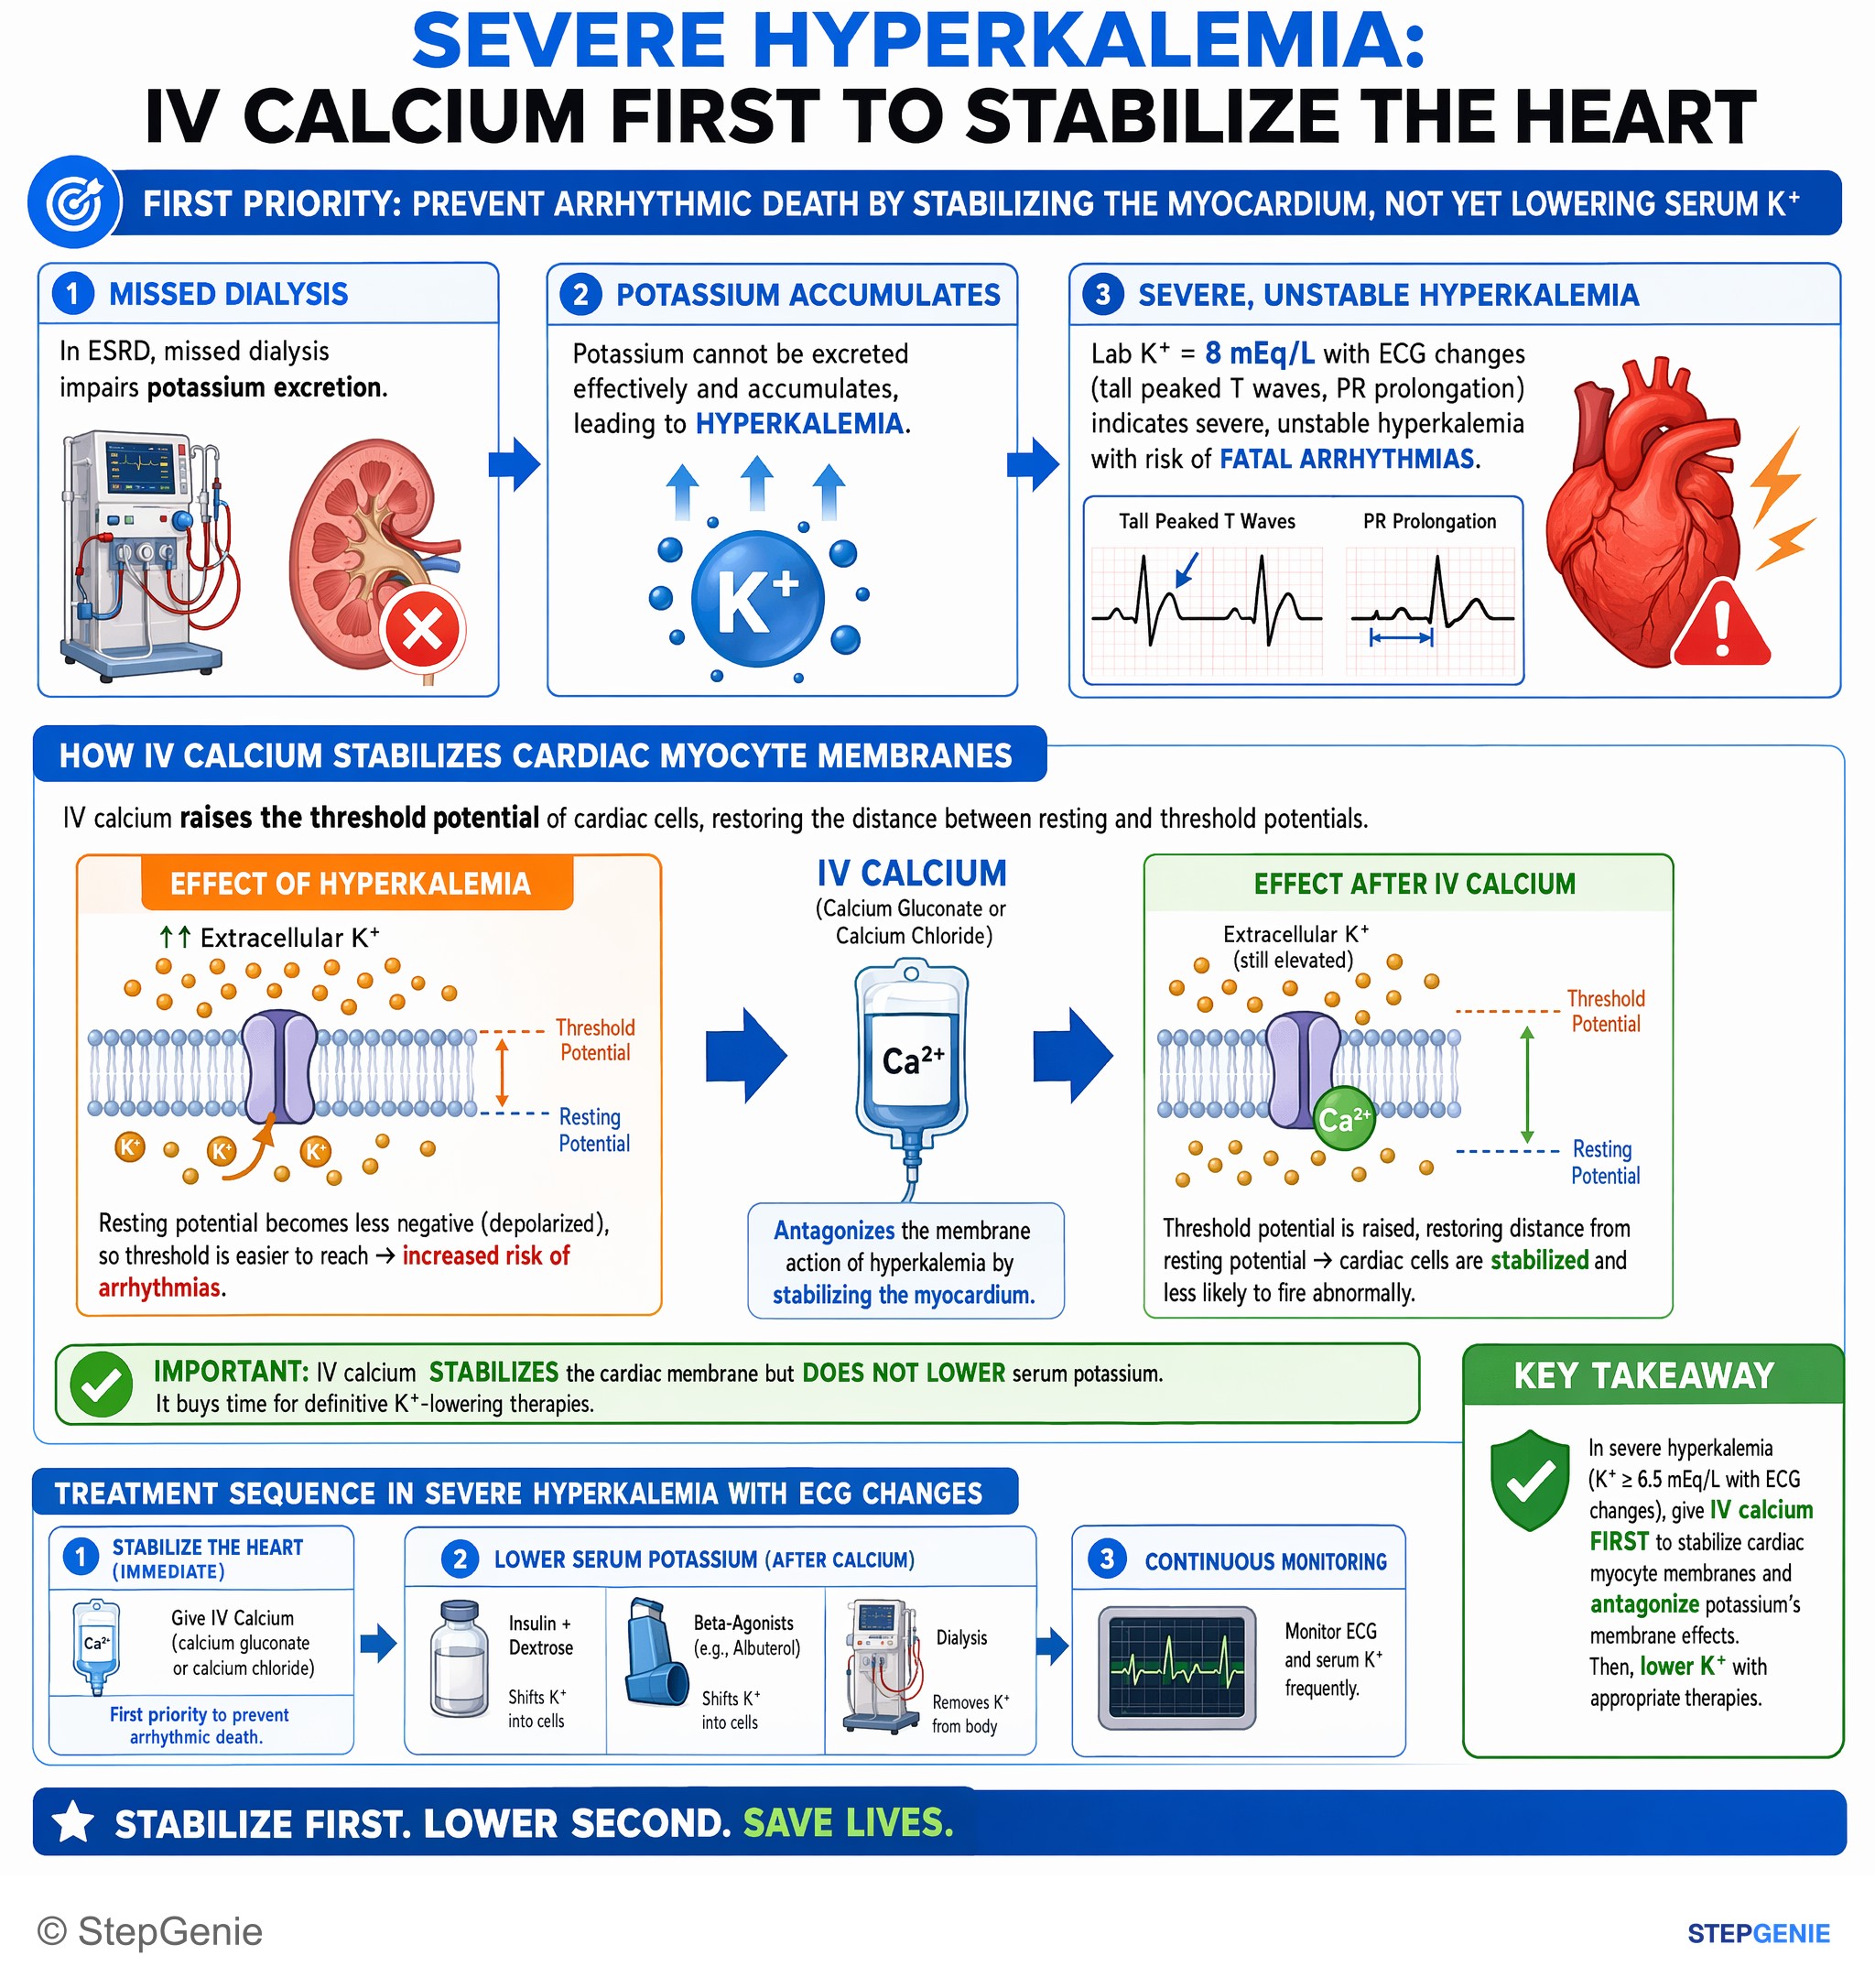
Severe hyperkalemia with ECG changes is treated first with IV calcium to stabilize cardiac myocyte membranes and antagonize potassium’s…
USMLE Step 1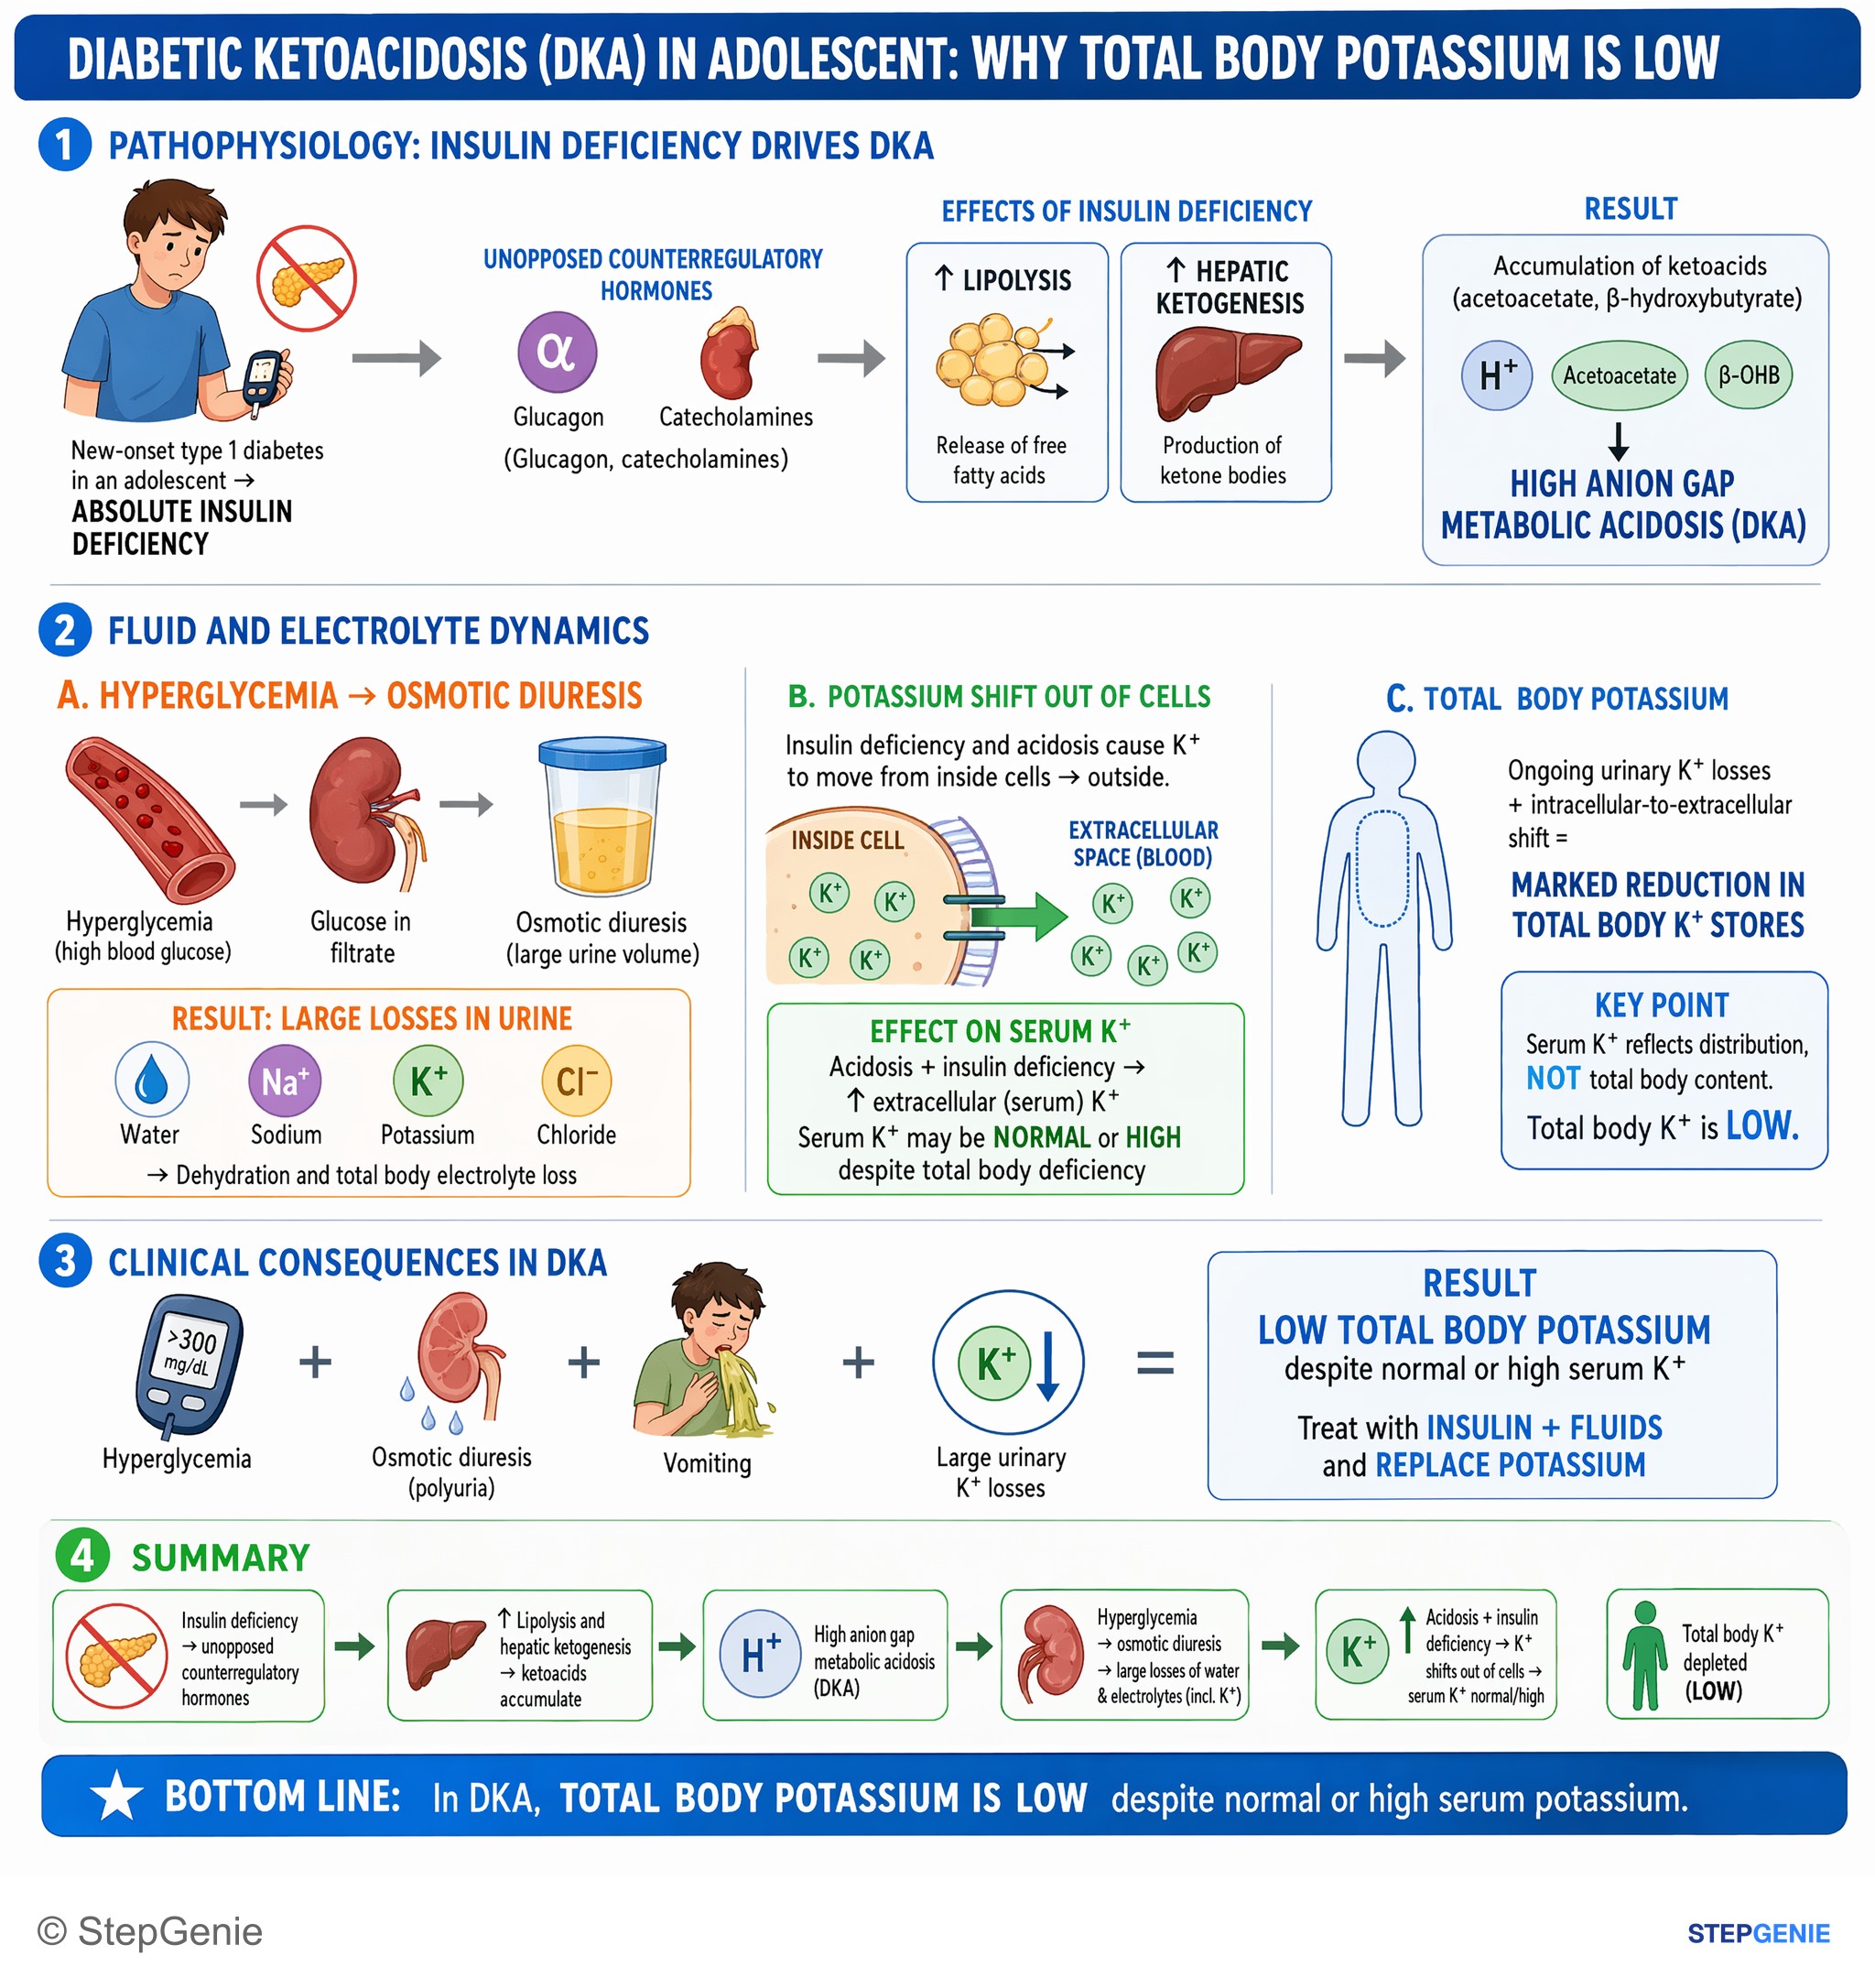
Diabetic ketoacidosis: insulin deficiency → hyperglycemia, osmotic diuresis, vomiting → large urinary K+ losses → low total body potassium…
USMLE Step 1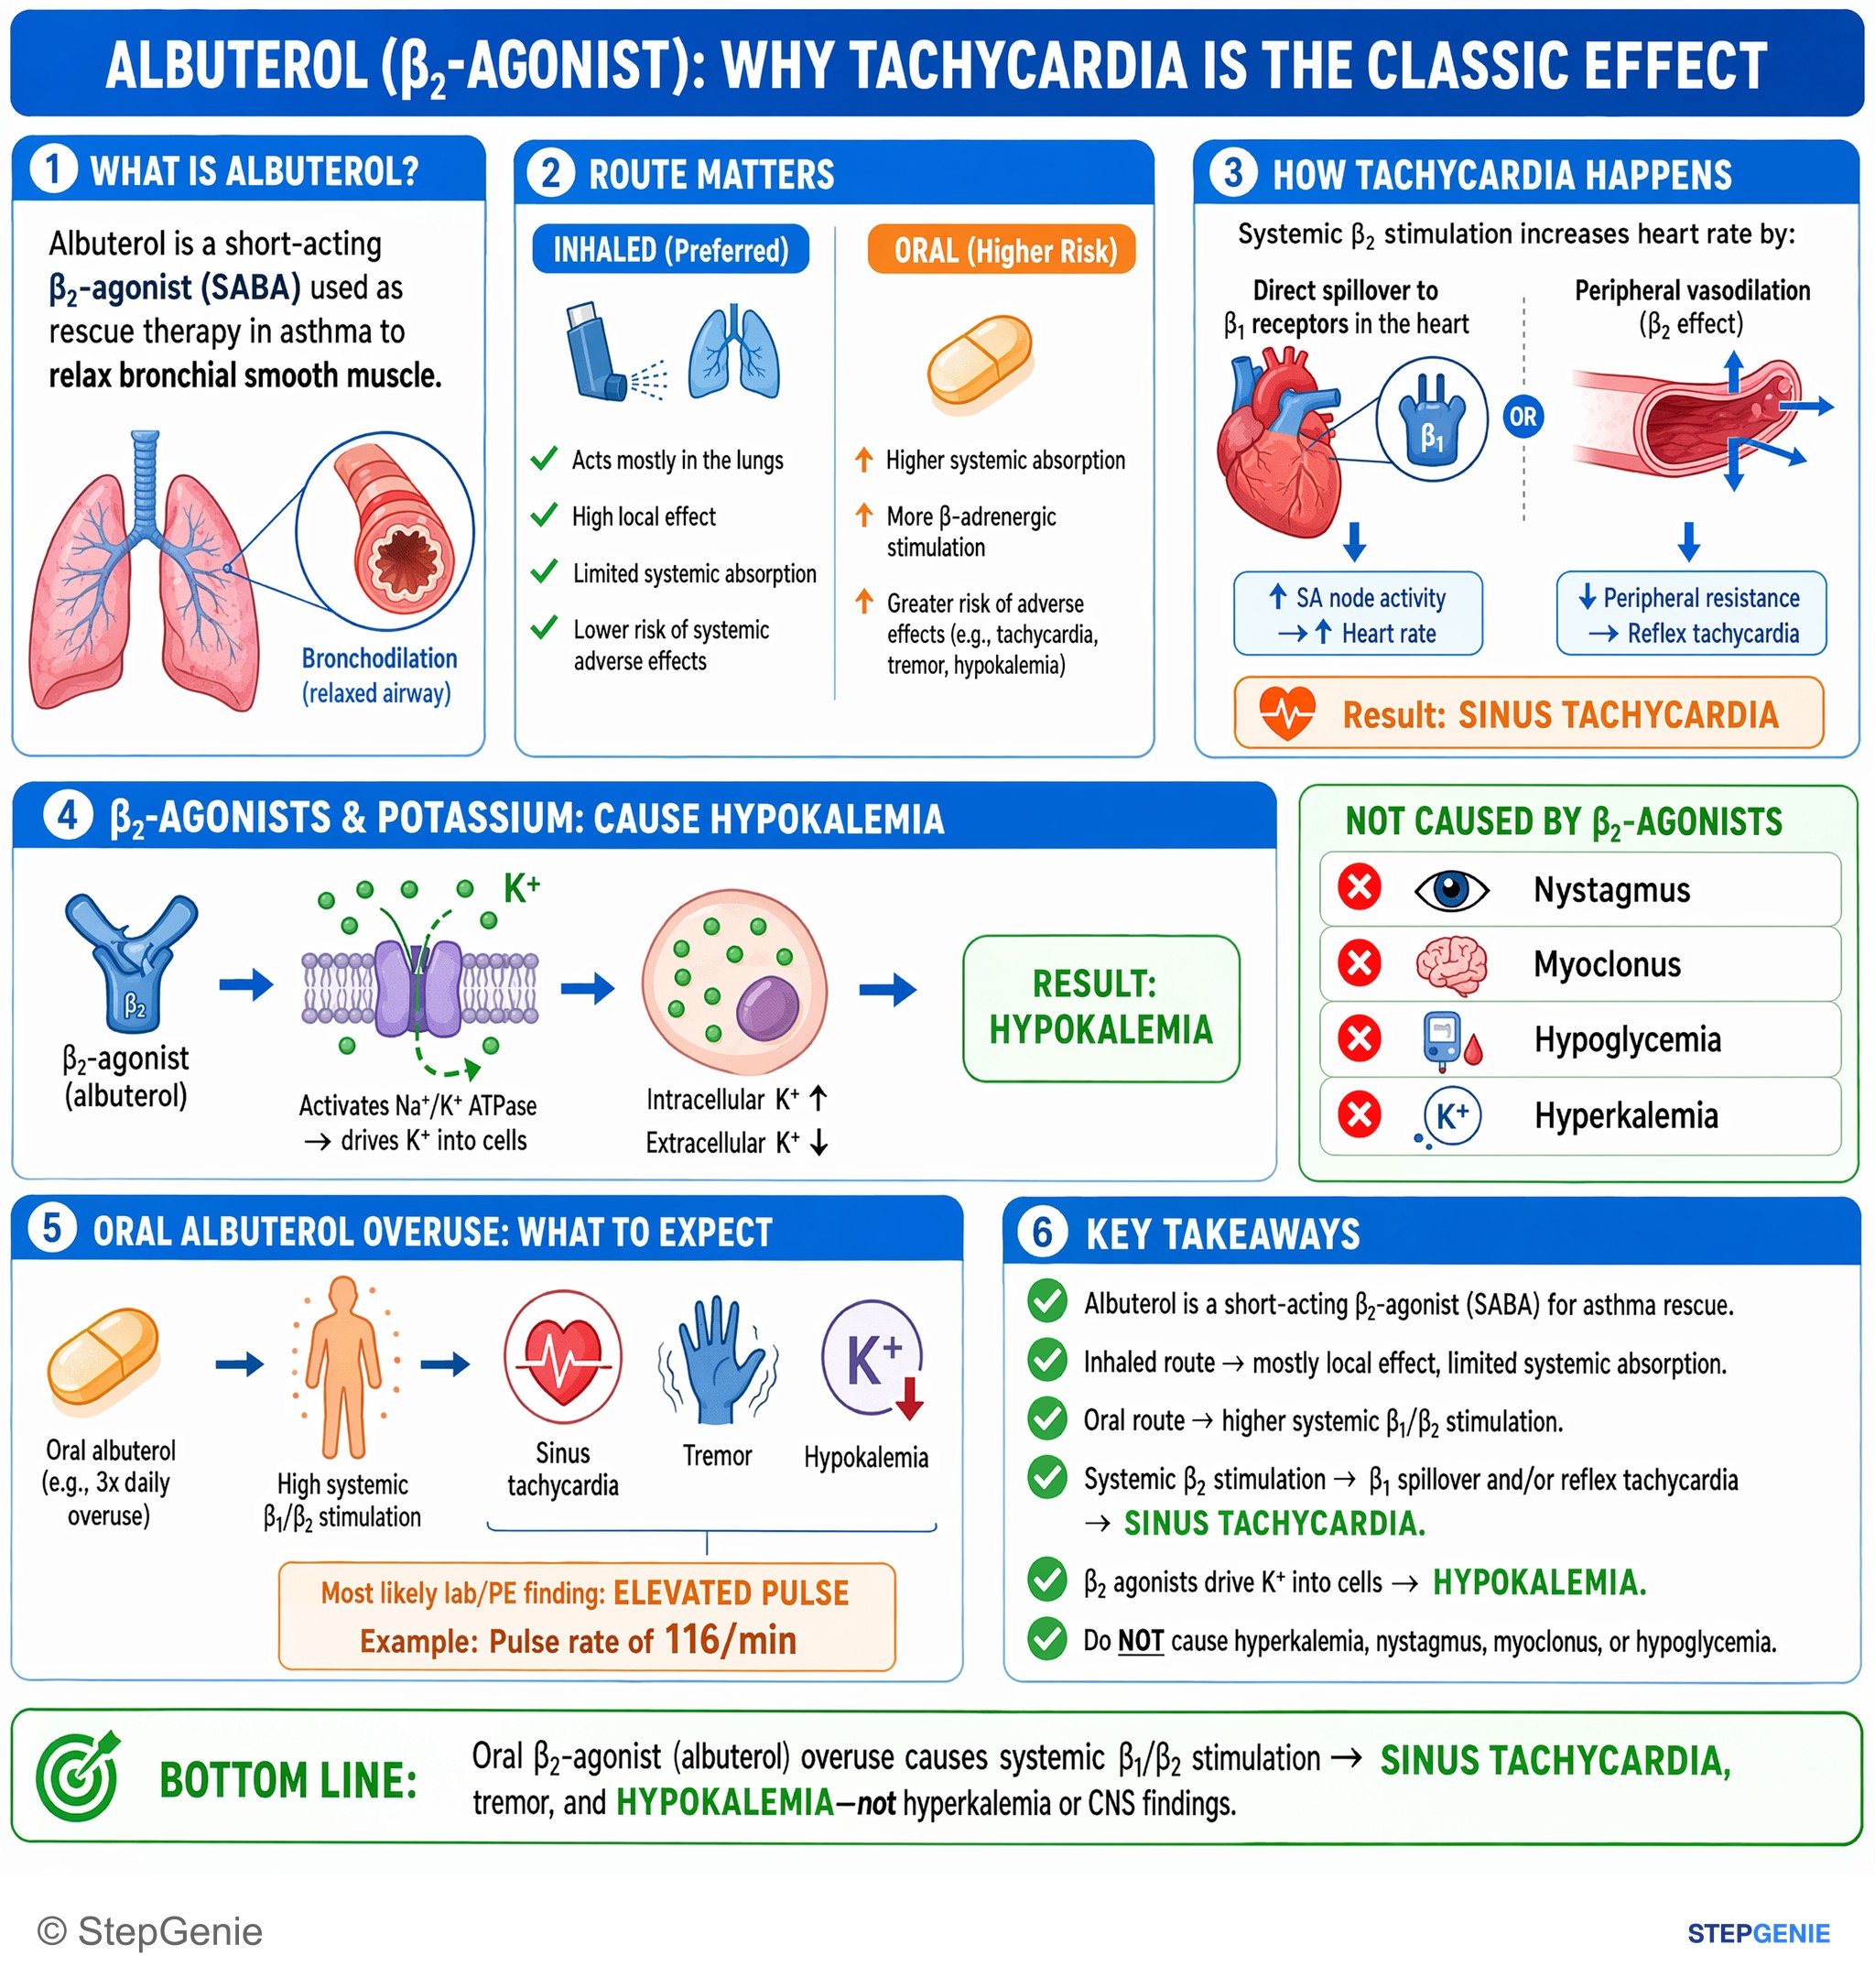
Oral β2-agonist (albuterol) overuse causes systemic β1/β2 stimulation → sinus tachycardia, tremor, and hypokalemia, not hyperkalemia or…
USMLE Step 1Frequently Asked Questions
What is the immediate next step for severe hyperkalemia with peaked T waves on ECG?
The immediate next step is IV calcium gluconate. In severe hyperkalemia with ECG changes such as tall, narrow, peaked T waves, the urgent danger is ventricular arrhythmia from altered cardiac membrane excitability. Calcium rapidly stabilizes the cardiac myocyte membrane within minutes, reducing the risk of lethal dysrhythmias. It does not lower serum potassium, but it buys time for therapies that shift potassium into cells or remove it from the body.
Why do you give calcium before insulin and dextrose in hyperkalemia with ECG changes?
You give calcium first because ECG changes mean the myocardium is electrically unstable and needs immediate protection. Insulin with dextrose lowers potassium quickly by driving it into cells through stimulation of the Na+/K+-ATPase, but it does not stabilize the cardiac membrane. In hyperkalemia with ECG findings, the priority is to prevent arrhythmia first, then use insulin and glucose to shift potassium intracellularly.
Why isn’t sodium bicarbonate the first-line immediate treatment for acute hyperkalemia?
Sodium bicarbonate is usually not the first immediate treatment because it does not reliably treat acute hyperkalemia and does not stabilize the myocardium. It may help in selected patients with significant metabolic acidosis, but it is considered adjunctive rather than definitive. The urgent problem in hyperkalemia with ECG changes is cardiac instability, which is why IV calcium is the first step before using shifting or removal therapies.
When is dialysis the definitive treatment for hyperkalemia?
Dialysis is the definitive treatment when a patient with ESRD has hyperkalemia and cannot effectively excrete potassium, especially after missing dialysis and being oliguric or anuric. Removal therapies are what actually eliminate potassium from the body, and in this setting dialysis is the key option. However, if ECG changes are present, calcium still comes first to stabilize the heart before definitive potassium removal.
Why can ACE inhibitors cause hyperkalemia?
ACE inhibitors can cause hyperkalemia because they reduce aldosterone production. Decreased angiotensin II leads to decreased aldosterone, which lowers ENaC activity in principal cells and reduces potassium secretion. That mechanism makes drugs such as lisinopril a common clue in hyperkalemia questions. However, simply stopping the ACE inhibitor does not treat life-threatening hyperkalemia with ECG changes in the moment.