You’ve probably noticed that RAAS questions are rarely “just physiology.” They’re really questions about where the kidney is sensing a problem, what it’s trying to fix (effective arterial blood volume, EABV), and which hormone changes are appropriate vs inappropriate for that context. The fastest way to level up your Q-bank accuracy is to treat every answer choice like a mini-diagnosis: What stimulus would make that option true? What finding would rule it out?
The Clinical Vignette (Q-Bank Style)
A 63-year-old man with long-standing hypertension and type 2 diabetes presents with worsening fatigue and leg swelling. Medications include lisinopril and furosemide. Blood pressure is 102/64 mm Hg. Physical exam shows bilateral pitting edema. Labs reveal:
| Lab | Value |
|---|---|
| Na⁺ | 132 mEq/L |
| K⁺ | 5.8 mEq/L |
| HCO₃⁻ | 19 mEq/L |
| BUN | 48 mg/dL |
| Creatinine | 2.6 mg/dL |
You suspect decreased renal perfusion and ask what hormone change is most expected due to ACE inhibitor therapy.
Which of the following best describes the expected hormone pattern?
A. ↑ Angiotensin II, ↑ aldosterone, ↑ renin
B. ↓ Angiotensin II, ↓ aldosterone, ↑ renin
C. ↓ Angiotensin II, ↑ aldosterone, ↓ renin
D. ↑ Angiotensin II, ↓ aldosterone, ↓ renin
E. ↓ Angiotensin II, ↓ aldosterone, ↓ renin
Step 1/2 Core: RAAS in One Minute
RAAS is a volume/EABV rescue pathway:
-
Renin (from juxtaglomerular cells) is released when:
- ↓ afferent arteriole pressure (intrarenal baroreceptor)
- ↓ NaCl at macula densa (via NKCC2 signaling)
- ↑ sympathetic tone (β1)
-
Renin converts angiotensinogen → angiotensin I
-
ACE converts angiotensin I → angiotensin II
-
Angiotensin II:
- Constrics efferent arteriole (helps maintain GFR when renal perfusion is low)
- Increases proximal tubule Na⁺ reabsorption via Na⁺/H⁺ exchanger
- Stimulates aldosterone release (zona glomerulosa)
- Stimulates ADH and thirst
-
Aldosterone (principal cells and α-intercalated cells):
- ↑ ENaC and Na⁺/K⁺-ATPase → ↑ Na⁺ reabsorption
- ↑ K⁺ secretion → hypokalemia
- ↑ H⁺ secretion (α-intercalated) → metabolic alkalosis
Correct Answer: B. ↓ Angiotensin II, ↓ Aldosterone, ↑ Renin
Why B is correct
This patient is taking lisinopril (ACE inhibitor), which blocks conversion of angiotensin I to angiotensin II.
So:
- Angiotensin II decreases
- Less angiotensin II → less stimulation of zona glomerulosa → aldosterone decreases
- But the kidney “senses” low EABV/renal perfusion (and also loses Ang II feedback) → renin increases via:
- Less angiotensin II–mediated negative feedback on renin release
- Often concurrent diuretic use/low perfusion states exacerbate the stimulus
High-yield tie-in to the vignette:
ACE inhibitors can cause hyperkalemia and non-anion gap metabolic acidosis (type 4 RTA physiology) due to hypoaldosteronism → decreased K⁺ and H⁺ secretion.
Distractor Autopsy: Why Each Wrong Choice Is Wrong (and When It Would Be Right)
A. ↑ Angiotensin II, ↑ Aldosterone, ↑ Renin
Why it’s wrong here: ACE inhibitor prevents angiotensin II formation, so angiotensin II can’t be high.
When A could be right (think “true RAAS activation”):
- Renal artery stenosis (especially unilateral early)
- Heart failure (low EABV)
- Cirrhosis (splanchnic vasodilation → low EABV)
- Diuretic use (volume depletion)
Board tip: If RAAS is turned on appropriately, you typically see:
- ↑ renin → ↑ angiotensin II → ↑ aldosterone
Unless a drug blocks a step.
C. ↓ Angiotensin II, ↑ Aldosterone, ↓ Renin
Why it’s wrong here: If angiotensin II is low due to ACE inhibition, aldosterone should fall (angiotensin II is the dominant stimulus). Also renin should rise, not fall.
When something like “low renin, high aldosterone” happens (pattern recognition):
- Primary hyperaldosteronism (Conn syndrome)
- ↑ aldosterone, ↓ renin, often hypertension + hypokalemic metabolic alkalosis
- Note: In Conn syndrome, angiotensin II is typically low-normal because renin is suppressed.
D. ↑ Angiotensin II, ↓ Aldosterone, ↓ Renin
Why it’s wrong here: This pattern is internally inconsistent for most classic physiology. If angiotensin II is high, it should stimulate aldosterone. If angiotensin II is high, renin is usually low (negative feedback), but then why would aldosterone be low?
When you might see “high angiotensin II but low aldosterone”:
- Adrenal insufficiency (zona glomerulosa failure) can produce low aldosterone despite high upstream stimuli.
- Aldosterone synthase defects (rare).
USMLE angle: If aldosterone is inappropriately low, think adrenal problem (or drug blocking aldosterone effect).
E. ↓ Angiotensin II, ↓ Aldosterone, ↓ Renin
Why it’s wrong here: ACE inhibitors lead to increased renin. Renin is the “upstream” compensatory response.
When E could be right (global RAAS suppression):
- Volume expansion (high EABV)
- SIADH with mild volume expansion can suppress RAAS (though clinically more nuanced)
- Direct renin inhibitor (aliskiren) can lower renin activity (renin concentration may rise, but activity decreases—some questions specify plasma renin activity)
Test-writer trick: Know whether they mean renin level vs plasma renin activity. Most Step-style questions mean the functional concept: RAAS is suppressed → renin is “down.”
The High-Yield Table: “Block the Pathway” Patterns
| Intervention/Condition | Renin | Angiotensin II | Aldosterone | Classic clinical clue |
|---|---|---|---|---|
| ACE inhibitor | ↑ | ↓ | ↓ | HyperK⁺, ↑Cr (esp bilateral RAS) |
| ARB (AT1 blocker) | ↑ | ↑ (can rise) | ↓ | Similar to ACEI, no cough/angioedema |
| Direct renin inhibitor (aliskiren) | ↓ activity (± ↑ level) | ↓ | ↓ | Less commonly tested |
| Primary hyperaldosteronism | ↓ | ↓/N | ↑ | HTN + hypokalemic metabolic alkalosis |
| Secondary hyperaldosteronism (RAS, HF) | ↑ | ↑ | ↑ | Low EABV states; abdominal bruit in RAS |
| Addison disease | ↑ | ↑ | ↓ | HyperK⁺, hypotension, hyperpigmentation |
Key nuance: With an ARB, angiotensin II can be increased (loss of feedback), but aldosterone remains low due to receptor blockade. That’s a favorite way to separate ACE inhibitors from ARBs if they ask about angiotensin II levels.
Micro-Mechanisms USMLE Loves
1) Where RAAS acts along the nephron
- Angiotensin II: boosts proximal tubule Na⁺ reabsorption (Na⁺/H⁺ exchanger)
- Aldosterone: boosts collecting duct Na⁺ reabsorption (ENaC) and K⁺/H⁺ secretion
2) Why ACE inhibitors can raise creatinine
- Angiotensin II preferentially constricts the efferent arteriole
- Blocking Ang II → efferent dilation → ↓ glomerular capillary hydrostatic pressure → ↓ GFR
- Big creatinine bump is concerning in:
- Bilateral renal artery stenosis
- Solitary functioning kidney with RAS
3) The acid-base connection (high yield)
- Low aldosterone → ↓ H⁺ secretion by α-intercalated cells → metabolic acidosis
- Also ↓ K⁺ secretion → hyperkalemia
- This is the physiologic backbone for type 4 RTA patterns (even when questions don’t use that label).
How to “Work Backward” From Answer Choices (Q-Bank Strategy)
When you see options listing renin/Ang II/aldosterone, ask:
-
Is RAAS being stimulated or suppressed?
- Low EABV → stimulated (renin up)
- Volume expanded → suppressed (renin down)
-
Is there a blockade?
- ACE inhibitor → Ang II down
- ARB → Ang II up (often) but receptor blocked → aldosterone down
- Spironolactone/eplerenone → aldosterone level may be high, effect blocked
-
Is the adrenal gland the problem?
- If aldosterone is low despite strong stimuli → adrenal insufficiency
Take-Home Summary (What You Need on Test Day)
- ACE inhibitor → ↓ angiotensin II, ↓ aldosterone, ↑ renin.
- If RAAS is activated appropriately, renin/Ang II/aldosterone usually rise together.
- If aldosterone is high but renin is low, think primary hyperaldosteronism.
- If ACEI/ARB causes hyperkalemia + metabolic acidosis, that’s hypoaldosterone physiology (type 4 RTA pattern).
- ACEI/ARB can drop GFR by dilating the efferent arteriole—dangerous in bilateral RAS.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
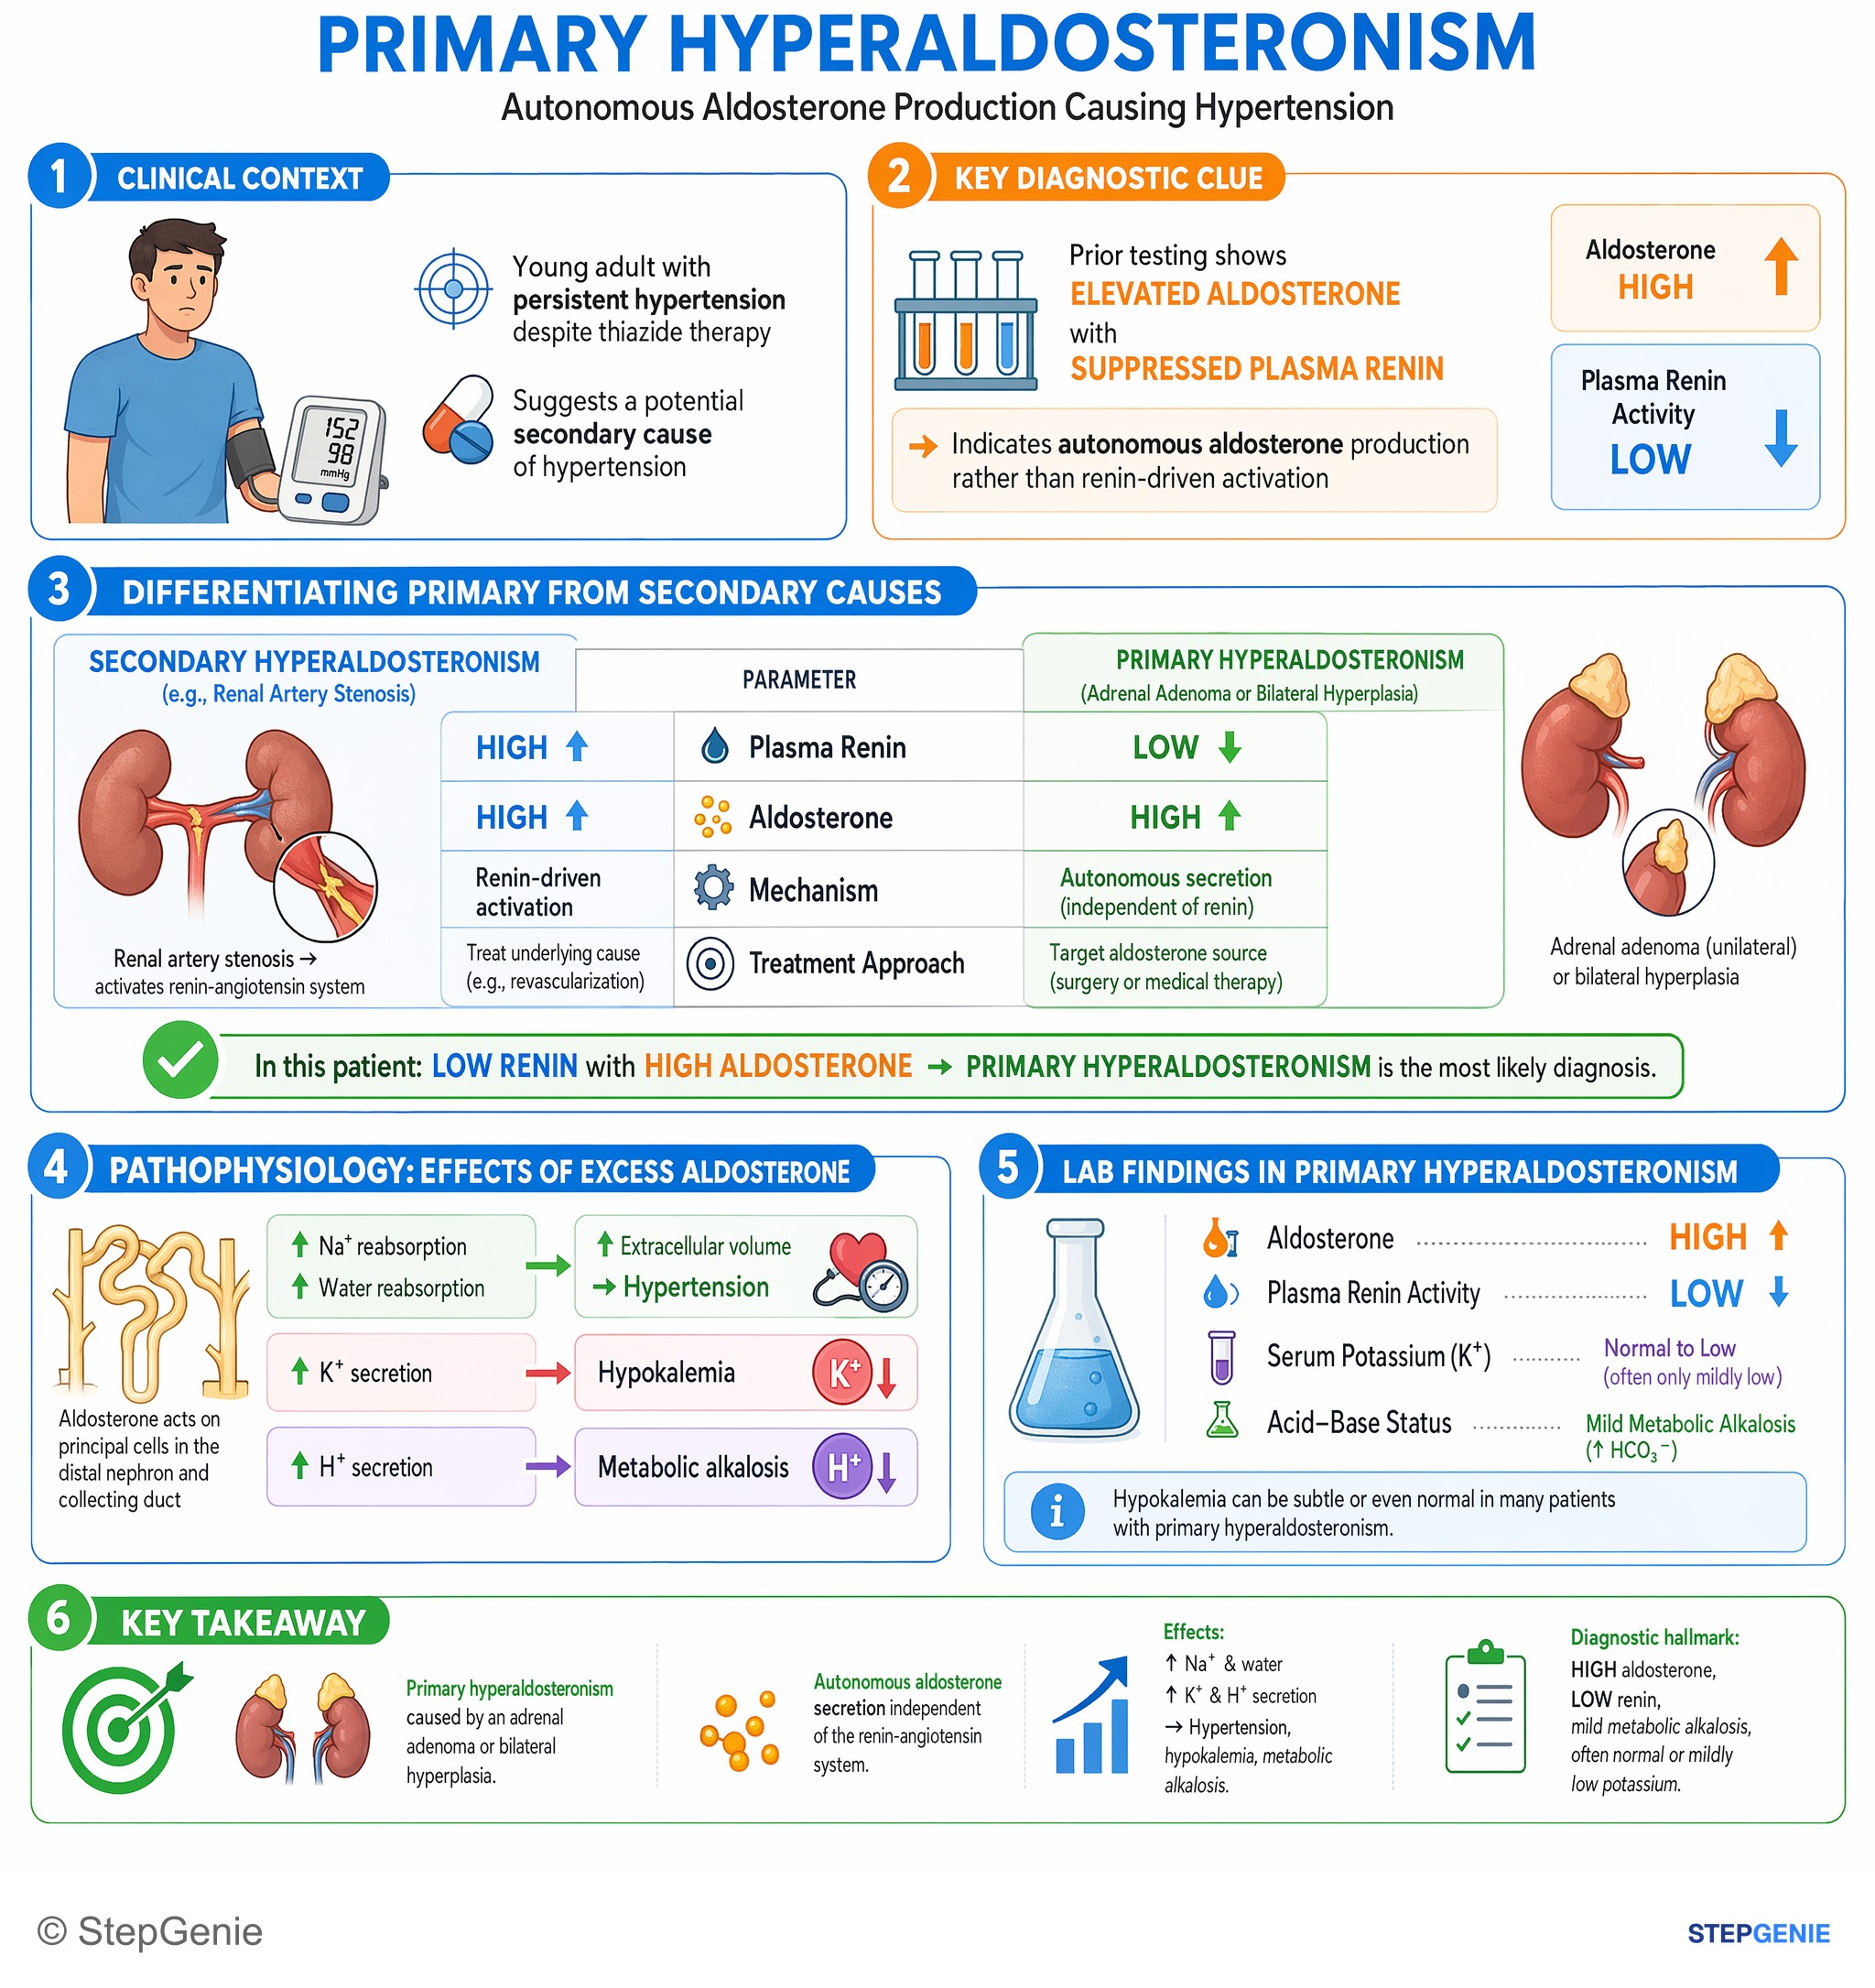
Primary hyperaldosteronism: autonomous aldosterone → hypertension with high aldosterone, low renin, mild metabolic alkalosis, often only…
USMLE Step 1Frequently Asked Questions
What hormone pattern do ACE inhibitors cause in the renin-angiotensin-aldosterone system?
ACE inhibitors cause decreased angiotensin II, decreased aldosterone, and increased renin. Blocking ACE prevents conversion of angiotensin I to angiotensin II, so aldosterone stimulation falls. The kidney then responds to perceived low effective arterial blood volume and the loss of angiotensin II negative feedback by increasing renin release.
Why do ACE inhibitors cause hyperkalemia and non-anion gap metabolic acidosis?
ACE inhibitors can cause hyperkalemia and non-anion gap metabolic acidosis because they lower aldosterone. With hypoaldosteronism, the kidney decreases K+ secretion and decreases H+ secretion, producing a type 4 RTA physiology. That is why a patient on an ACE inhibitor can develop elevated potassium and metabolic acidosis.
What makes the kidney release renin?
Renin is released when the kidney senses low effective arterial blood volume through several signals. Juxtaglomerular cells increase renin release with decreased afferent arteriole pressure, decreased NaCl delivery to the macula densa via NKCC2 signaling, and increased sympathetic tone through beta-1 stimulation. These changes activate RAAS as a volume rescue pathway.
How do you tell true RAAS activation from RAAS blocked by an ACE inhibitor?
True RAAS activation usually shows increased renin, increased angiotensin II, and increased aldosterone, such as in renal artery stenosis, heart failure, cirrhosis, or diuretic-associated volume depletion. ACE inhibitor therapy breaks that pattern by preventing angiotensin II formation, so angiotensin II and aldosterone fall while renin rises as a compensatory response.
What does angiotensin II normally do in renal physiology?
Angiotensin II normally helps preserve perfusion and sodium balance in low-volume states. It constricts the efferent arteriole to help maintain GFR when renal perfusion is reduced, increases proximal tubule sodium reabsorption through the Na+/H+ exchanger, and stimulates aldosterone, ADH, and thirst to support effective arterial blood volume.