EGPA (eosinophilic granulomatosis with polyangiitis, formerly Churg-Strauss syndrome) is a necrotizing vasculitis of small and medium vessels that develops in people with adult-onset asthma, nasal polyps or sinusitis and blood eosinophilia, then shows itself with mononeuritis multiplex, purpura, transient lung infiltrates or myocarditis. Only 30–40% of patients are ANCA-positive, usually p-ANCA against myeloperoxidase (MPO), so a negative ANCA never excludes it, and heart involvement is the main cause of death. The mnemonic is the name itself: A-E-G-P-A.
The A-E-G-P-A mnemonic
| Letter | Hook | What to remember |
|---|---|---|
| A | Asthma (and the nose) | Adult-onset, often severe asthma in more than 95% of patients, usually with allergic rhinitis, nasal polyps or sinusitis; the vasculitis typically follows 3 to 9 years after the asthma starts |
| E | Eosinophils | Blood eosinophilia above 10% of white cells, eosinophil-rich tissue infiltrates, raised IgE in about 75% |
| G | Granulomas | Extravascular necrotizing granulomas, usually rich in eosinophils, alongside necrotizing vasculitis of small and medium vessels |
| P | Peripheral nerves and Purpura | Mononeuritis multiplex in about three-quarters of patients; purpura, or nodules and papules on extensor surfaces, in about half |
| A | ANCA, in only a minority | Positive in 30–40%: mostly MPO (p-ANCA, about 35%), rarely PR3 (about 5%) |
Picture it: a wheezing patient (asthma) covered in bright red granules (eosinophils), wearing purple socks (purpura), with one sock slipping off (foot drop from mononeuritis multiplex), holding a bottle labeled MPO that is only a third full (ANCA in a minority). When a stem gives you asthma and eosinophils and then adds a foot drop, purpura or heart failure, think EGPA.
Three phases, which can overlap
- Prodromal (allergic): asthma, allergic rhinitis and nasal polyps, sometimes for years.
- Eosinophilic: blood eosinophilia with eosinophilic infiltrates in organs such as the lungs.
- Vasculitic: necrotizing small- and medium-vessel vasculitis, the life-threatening phase, typically 3 to 9 years after asthma onset.
The phases do not have to follow one another in order.
Organ by organ
| Organ | Finding | How often or why it matters |
|---|---|---|
| Upper airway | Nasal polyps; sinusitis that is not destructive | Part of the prodrome; destructive disease suggests GPA instead |
| Lungs | Asthma; transient, patchy infiltrates; peripheral ground-glass opacities on CT that can migrate | Asthma in more than 95% |
| Peripheral nerves | Mononeuritis multiplex | About three-quarters of patients |
| Skin | Purpura from leukocytoclastic vasculitis; nodules and papules on extensor surfaces | About half |
| Heart | Myocarditis, endomyocardial fibrosis, coronary vasculitis, pericarditis | Main cause of death; every patient needs a baseline echocardiogram |
| GI tract | GI symptoms; mesenteric ischemia counts as severe disease | Up to a third |
| Kidneys | Renal involvement | About a quarter; less often than in GPA or MPA |
ANCA status shapes the picture. ANCA-positive patients lean toward vasculitic features: glomerulonephritis, mononeuritis, alveolar hemorrhage and biopsy-proven vasculitis. ANCA-negative patients lean toward eosinophilic features: myocarditis and eosinophilic lung infiltrates.
2022 ACR/EULAR classification criteria
Apply them only after a small- or medium-vessel vasculitis has been diagnosed and mimics excluded. A total of 6 or more points classifies the vasculitis as EGPA (sensitivity 85%, specificity 99% in the validation set). They classify patients who already carry a vasculitis diagnosis; they are not diagnostic criteria.
| Item | Points |
|---|---|
| Maximum blood eosinophil count /L | +5 |
| Obstructive airway disease | +3 |
| Nasal polyps | +3 |
| Extravascular eosinophilic-predominant inflammation on biopsy | +2 |
| Mononeuritis multiplex or motor neuropathy not due to radiculopathy | +1 |
| Positive cytoplasmic ANCA (c-ANCA) or anti-PR3 antibodies | −3 |
| Hematuria | −1 |
Memory line: eosinophils 5, airways 3, nose 3, biopsy 2, nerves 1; PR3 minus 3, blood in the urine minus 1. MPO-ANCA earns no points, because it is more common in microscopic polyangiitis and does not discriminate.
EGPA vs GPA vs microscopic polyangiitis
| Feature | EGPA (Churg-Strauss) | GPA (Wegener) | Microscopic polyangiitis |
|---|---|---|---|
| Asthma and eosinophilia | Yes: the defining clues | No | No |
| Granulomas | Eosinophil-rich necrotizing granulomas | Necrotizing granulomatous inflammation | None |
| Typical ANCA | 30–40% positive, mostly MPO (p-ANCA) | Most with active disease: PR3 (c-ANCA) | At least 70% positive, mostly MPO (p-ANCA) |
| Upper airway | Polyps and sinusitis, not destructive | Chronic sinusitis, septal perforation, saddle nose | Minimal |
| Lungs | Asthma, transient infiltrates | Nodules that cavitate, infiltrates, alveolar hemorrhage | Alveolar hemorrhage from capillaritis |
| Kidneys | About a quarter | Pauci-immune crescentic glomerulonephritis | Up to 90%: pauci-immune necrotizing glomerulonephritis |
Fast rule: in a patient with small- or medium-vessel vasculitis, asthma plus eosinophilia points to EGPA; an MPO-ANCA alone does not separate EGPA from MPA. The PR3 side of the family is covered in the GPA (Wegener granulomatosis) overview.
Workup
- CBC with differential for eosinophilia; IgE, C-reactive protein and ESR.
- ANCA (MPO and PR3), knowing most patients test negative.
- Urinalysis with sediment and creatinine to screen the kidneys.
- Chest imaging for transient patchy infiltrates.
- Echocardiogram in every patient at baseline.
- Biopsy of the most accessible affected tissue: necrotizing vasculitis, extravascular granulomas and tissue eosinophilia.
- Rule out other eosinophilic disorders: parasitic infection (including Strongyloides), drug reactions, acute and chronic eosinophilic pneumonia, allergic bronchopulmonary aspergillosis and hypereosinophilic syndrome.
Treatment: 2021 ACR/Vasculitis Foundation guideline
- Severe disease (organ- or life-threatening: alveolar hemorrhage, glomerulonephritis, CNS vasculitis, mononeuritis multiplex, cardiac involvement, mesenteric ischemia, limb or digit ischemia): IV pulse or high-dose oral glucocorticoids plus cyclophosphamide or rituximab, favored over mepolizumab.
- Nonsevere disease: glucocorticoids plus mepolizumab (anti-IL-5), favored over methotrexate, azathioprine or mycophenolate.
- Maintenance after cyclophosphamide: methotrexate, azathioprine or mycophenolate.
- Nonsevere relapse (asthma or sinonasal disease) on methotrexate, azathioprine or mycophenolate: add mepolizumab rather than switching drugs.
- Leukotriene receptor antagonists: continue them in newly diagnosed EGPA; later studies did not conclude that they cause the disease.
Two further points from the Merck Manual: cyclophosphamide is preferred for cardiac involvement, and benralizumab (an IL-5 receptor antibody) was noninferior to mepolizumab for remission. Asthma treatment itself is reviewed in the asthma Q-bank breakdown.
Exam traps
- A negative ANCA does not rule out EGPA; most patients are ANCA-negative.
- MPO-ANCA does not separate EGPA from MPA. Asthma and eosinophilia do.
- c-ANCA or anti-PR3 points away from EGPA (−3 points) and toward GPA.
- Destructive nasal disease (septal perforation, saddle nose) is GPA; EGPA's sinus disease is not destructive.
- Montelukast: older teaching blamed leukotriene antagonists for triggering EGPA. The 2021 guideline says a causal link was not established and that they are not contraindicated.
- Mononeuritis multiplex counts as severe disease, so the answer is glucocorticoids with cyclophosphamide or rituximab, not mepolizumab.
- The heart kills: chest pain, arrhythmia or heart failure in a patient with asthma and eosinophilia needs cardiac evaluation.
- Eosinophilia with lung infiltrates is not automatically EGPA: parasites, drug reactions, eosinophilic pneumonia, ABPA and hypereosinophilic syndrome are the look-alikes to exclude.
Worked example
Vignette. A 44-year-old woman has had asthma since age 38 and had nasal polyps removed last year; she uses an inhaled corticosteroid–LABA and montelukast. Over 3 weeks she has developed numbness over the top of the right foot with a right foot drop, then weakness of left wrist extension. There is palpable purpura on both shins. White cell count is 12,500/µL with 30% eosinophils (3,750/µL). Chest CT shows patchy peripheral ground-glass opacities that were absent a month ago. Urinalysis is normal, and MPO-ANCA and PR3-ANCA are negative. Skin biopsy shows small-vessel vasculitis with eosinophil-rich inflammation around the vessels; echocardiogram is normal. What is the diagnosis, and what is the best initial treatment?
Answer: EGPA with mononeuritis multiplex, which makes it severe: high-dose glucocorticoids plus cyclophosphamide or rituximab.
Reasoning: She scores 14 on the 2022 criteria: eosinophils (+5), obstructive airway disease (+3), nasal polyps (+3), extravascular eosinophilic inflammation (+2) and mononeuritis multiplex (+1). Her negative ANCA costs nothing.
- GPA would need destructive upper-airway disease, cavitating nodules or PR3-ANCA, and has no asthma or eosinophilia.
- Microscopic polyangiitis is ANCA-positive (usually MPO) in at least 70%, involves the kidneys in up to 90%, and lacks asthma, eosinophilia and granulomas.
- Hypereosinophilic syndrome is defined by persistent eosinophilia above 1,500/µL; her asthma, polyps and biopsy-proven vasculitis point to EGPA instead.
- Glucocorticoids plus mepolizumab is the guideline choice for nonsevere disease, and mononeuritis multiplex makes her disease severe.
- Stopping montelukast because it caused the vasculitis is wrong: the guideline conditionally recommends continuing it.
Key takeaways
- EGPA = asthma + eosinophilia + necrotizing small- and medium-vessel vasculitis with eosinophil-rich granulomas.
- A-E-G-P-A: Asthma, Eosinophils, Granulomas, Peripheral nerves and Purpura, ANCA in only 30–40% (mostly MPO).
- 2022 criteria: eosinophils ≥1 × 10⁹/L +5, obstructive airway disease +3, nasal polyps +3, extravascular eosinophils +2, mononeuropathy +1, PR3/c-ANCA −3, hematuria −1; 6 or more classifies.
- The heart is the main cause of death: echocardiogram for everyone.
- Treatment: severe disease gets glucocorticoids with cyclophosphamide or rituximab; nonsevere disease gets glucocorticoids with mepolizumab.
Sources
- Eosinophilic Granulomatosis With Polyangiitis (Churg-Strauss Syndrome) — StatPearls, NCBI Bookshelf
- Eosinophilic Granulomatosis with Polyangiitis (EGPA) — Merck Manual Professional Edition
- Grayson PC, et al. 2022 ACR/EULAR Classification Criteria for Eosinophilic Granulomatosis With Polyangiitis. Arthritis Rheumatol 2022;74:386-392 (full article hosted by the American College of Rheumatology)
- Chung SA, et al. 2021 ACR/Vasculitis Foundation Guideline for the Management of ANCA-Associated Vasculitis (full guideline hosted by the American College of Rheumatology)
- Granulomatosis with Polyangiitis (GPA) — Merck Manual Professional Edition
- Microscopic Polyangiitis (MPA) — Merck Manual Professional Edition
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
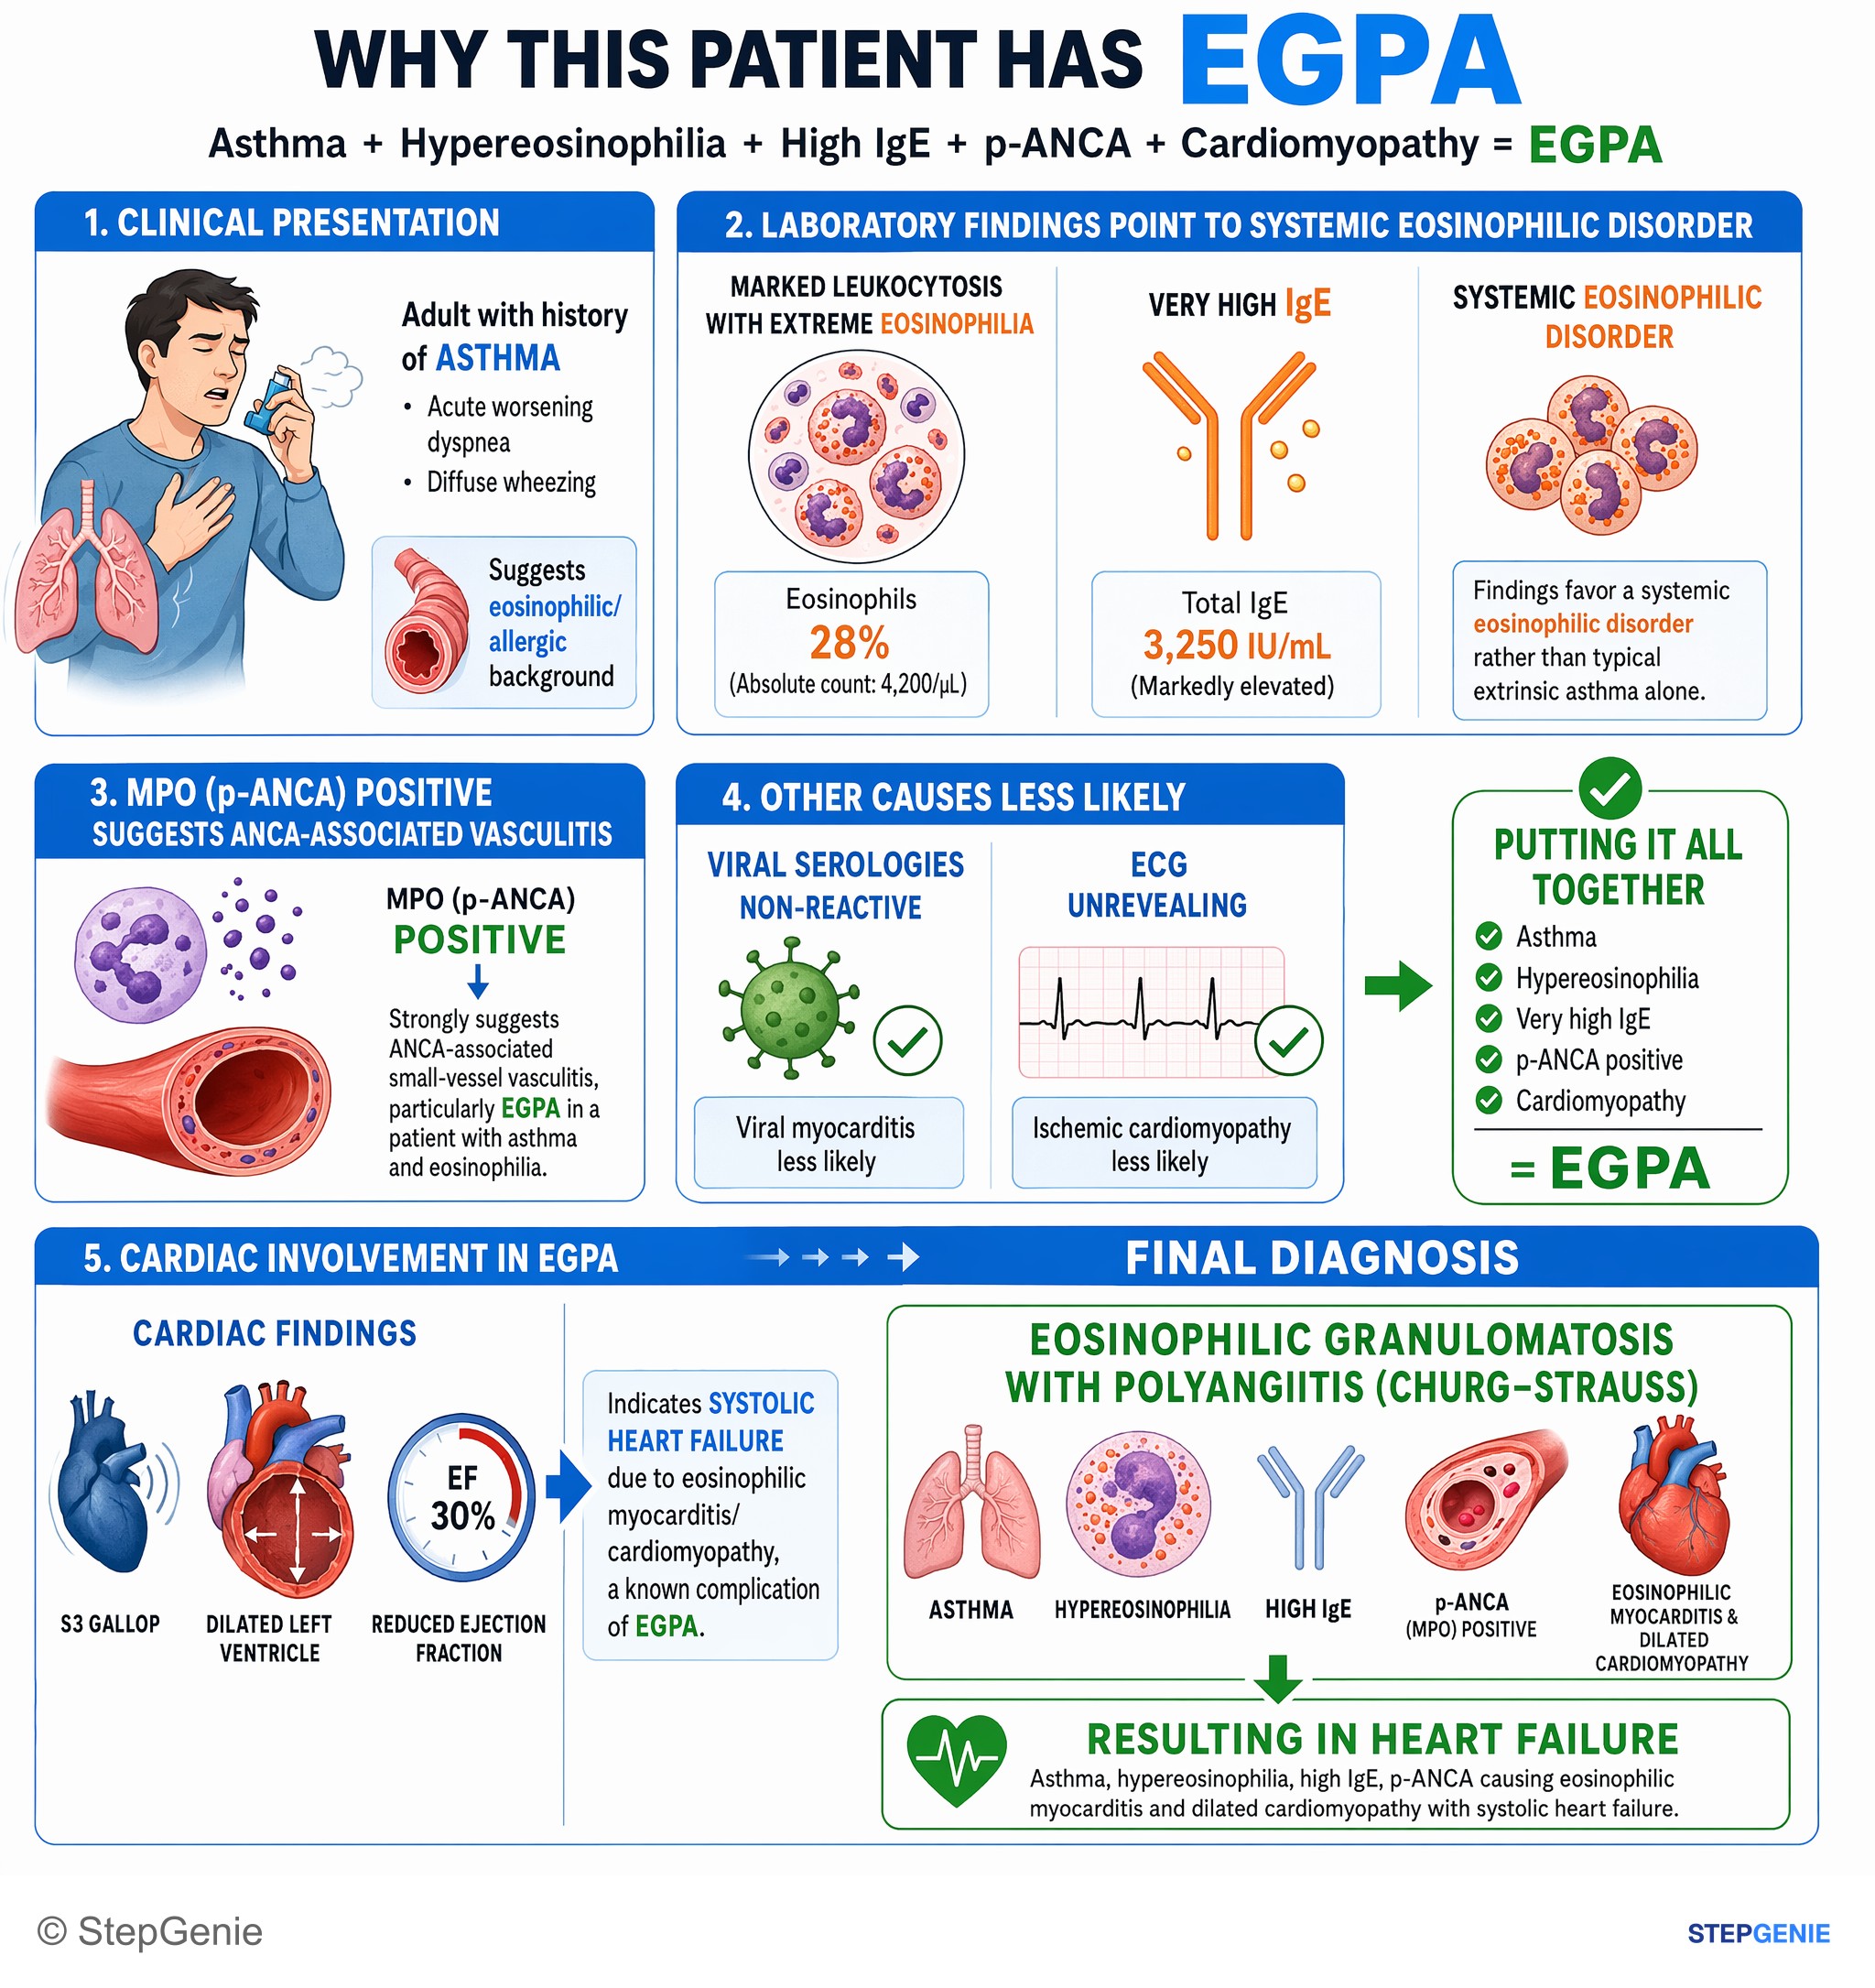
Eosinophilic granulomatosis with polyangiitis (Churg-Strauss): asthma, hypereosinophilia, high IgE, p-ANCA, causing eosinophilic…
USMLE Step 1Frequently Asked Questions
What is a good mnemonic for Churg-Strauss syndrome (EGPA)?
Use the name itself, A-E-G-P-A: Asthma (adult-onset, often with nasal polyps), Eosinophils (blood eosinophilia above 10%), Granulomas (eosinophil-rich necrotizing granulomas with small- and medium-vessel vasculitis), Peripheral nerves and Purpura (mononeuritis multiplex and skin lesions), and ANCA, which is positive in only 30–40% of patients and is usually MPO (p-ANCA).
Is EGPA p-ANCA or c-ANCA positive?
Only 30–40% of patients with EGPA are ANCA-positive: about 35% have p-ANCA against myeloperoxidase (MPO) and about 5% have c-ANCA against PR3. A negative ANCA does not exclude EGPA, and a positive c-ANCA or anti-PR3 subtracts 3 points in the 2022 classification criteria because it points toward GPA.
What are the 2022 ACR/EULAR classification criteria for EGPA?
After a small- or medium-vessel vasculitis is diagnosed and mimics are excluded, add the points: blood eosinophils of at least 1 × 10⁹/L (+5), obstructive airway disease (+3), nasal polyps (+3), extravascular eosinophilic-predominant inflammation (+2), mononeuritis multiplex or motor neuropathy (+1), positive c-ANCA or anti-PR3 (−3) and hematuria (−1). A score of 6 or more classifies the patient as having EGPA.
How is EGPA treated?
The 2021 ACR/Vasculitis Foundation guideline treats severe, organ- or life-threatening disease, including mononeuritis multiplex and cardiac involvement, with high-dose glucocorticoids plus cyclophosphamide or rituximab. Nonsevere disease is treated with glucocorticoids plus mepolizumab, an anti-IL-5 antibody. After cyclophosphamide induction, methotrexate, azathioprine or mycophenolate maintains remission, and mepolizumab can be added for a nonsevere relapse.
Does montelukast cause Churg-Strauss syndrome?
Concern arose after leukotriene receptor antagonists were introduced, and the question is still debated, but later retrospective studies did not conclude that they cause EGPA. The 2021 ACR/Vasculitis Foundation guideline conditionally recommends continuing leukotriene inhibitors in newly diagnosed EGPA and states that they are not contraindicated in patients with active asthma or sinonasal disease.