You’ve probably seen it in a Q-bank: a “young” patient with emphysema, minimal smoking history, and some weird liver clue. Alpha-1 antitrypsin (A1AT) deficiency is a classic Step diagnosis—but the real test is whether you can defend it against every distractor in the answer choices. Let’s do this the way the exam does: with a vignette, a single best answer, and a ruthless breakdown of why the wrong options are wrong.
Tag
Pulmonary > Obstructive Lung Disease
Clinical Vignette (Q-bank style)
A 34-year-old man comes to clinic for progressive shortness of breath and wheezing. He has had multiple “bronchitis” episodes over the past few years. He smoked briefly in college (3 pack-years total) and quit 10 years ago. He also reports intermittent right upper quadrant discomfort and fatigue. Family history is notable for a brother who needed a liver transplant in his 40s. Exam shows prolonged expiratory phase and mild scleral icterus. Pulmonary function testing demonstrates an obstructive pattern. A CT scan shows basilar-predominant emphysematous changes.
Which of the following is the most likely underlying mechanism?
A. Inherited defect leading to misfolded protein accumulation in hepatocytes
B. Cigarette smoke–induced inactivation of α1-antitrypsin leading to panacinar emphysema
C. Loss of elastic recoil due to centriacinar emphysema predominantly in the upper lobes
D. Bronchial smooth muscle hyperresponsiveness with reversible airflow obstruction
E. Chronic productive cough due to mucus gland hyperplasia (increased Reid index)
Step-Style Bottom Line
✅ Correct Answer: A. Inherited defect leading to misfolded protein accumulation in hepatocytes
Alpha-1 antitrypsin deficiency is an autosomal codominant disorder (classically PiZZ) that causes:
- Low A1AT in the lungs → unopposed neutrophil elastase → panacinar emphysema
- Misfolded A1AT trapped in hepatocytes → liver disease (neonatal jaundice, hepatitis, cirrhosis, hepatocellular carcinoma)
Why the vignette screams A1AT deficiency
- Young age with emphysema + minimal smoking
- Basilar-predominant emphysema on CT (panacinar, lower lobes)
- Liver clues (RUQ discomfort, scleral icterus, family member with liver transplant)
Key path concept
- Lung damage is from too little A1AT in alveoli.
- Liver damage is from too much misfolded A1AT stuck in hepatocytes.
High-yield phrasing you’ll see:
- “PAS-positive, diastase-resistant globules” in hepatocytes (accumulated A1AT)
- Panacinar emphysema worse at the bases
- Think early COPD in a nonsmoker + liver disease
Why Every Other Answer Choice Is Wrong (and What It’s Testing)
❌ B. Cigarette smoke–induced inactivation of α1-antitrypsin leading to panacinar emphysema
This option is sneaky because it contains a true concept: smoke oxidizes A1AT (especially methionine residues) → decreased elastase inhibition. But two issues:
- Smoking-related emphysema is classically centriacinar, not panacinar.
- The stem pushes inherited disease: early onset, minimal smoking, and liver involvement.
Testable takeaway
- Smoking can worsen emphysema in anyone, and it’s especially bad in A1AT deficiency, but it’s not the primary mechanism here.
❌ C. Loss of elastic recoil due to centriacinar emphysema predominantly in the upper lobes
This describes classic smoking-related COPD:
- Centriacinar (centrilobular) emphysema
- Predominantly upper lobes
- Strong smoking history typically present
In contrast, A1AT deficiency causes:
- Panacinar emphysema
- Predominantly lower lobes
Quick comparison table (high yield)
| Feature | Smoking-related emphysema | A1AT deficiency emphysema |
|---|---|---|
| Pattern | Centriacinar | Panacinar |
| Location | Upper lobes | Lower lobes |
| Typical patient | Older, heavy smoker | Younger, minimal smoking |
| Extra clue | Chronic bronchitis often coexists | Liver disease, family history |
❌ D. Bronchial smooth muscle hyperresponsiveness with reversible airflow obstruction
This is asthma.
Asthma can present with wheezing and obstruction, but Step questions usually give you some combo of:
- Atopy/allergies, eczema
- Symptoms worse at night/early morning
- Triggers (exercise, cold air)
- Reversibility on spirometry (improves with bronchodilator)
This vignette instead emphasizes:
- Emphysema on CT (not typical for asthma)
- Basilar changes
- Liver findings
USMLE reminder
- Asthma = reversible obstruction + eosinophils + Charcot-Leyden crystals/Curschmann spirals (classic path associations)
- COPD/emphysema = less reversible, structural destruction
❌ E. Chronic productive cough due to mucus gland hyperplasia (increased Reid index)
This is chronic bronchitis, defined clinically as:
- Productive cough ≥ 3 months/year for ≥ 2 consecutive years
Mechanism:
- Irritants (usually smoking) → mucus gland enlargement and goblet cell hyperplasia
- Increased Reid index (ratio of mucus gland layer thickness to total bronchial wall thickness)
Why it doesn’t fit:
- The vignette highlights emphysema (alveolar destruction), not mucus plugging
- Again: young, minimal smoking, and liver disease
Helpful association
- Chronic bronchitis is the COPD subtype associated with:
- cyanosis (“blue bloater”)
- polycythemia
- pulmonary hypertension and cor pulmonale
- frequent infections due to mucus plugging
“How They’ll Ask It” — Rapid-Fire High-Yield Facts
1) Genetics + mechanism
- Autosomal codominant
- Most common severe genotype: PiZZ
- Lung: low A1AT → ↑ elastase activity → alveolar wall destruction
- Liver: misfolded A1AT accumulates in ER of hepatocytes → hepatitis/cirrhosis/HCC
2) Imaging and anatomy
- Panacinar emphysema: uniform acinar enlargement/destruction
- Lower lobe predominance (bases)
3) Histology buzzword
- PAS-positive, diastase-resistant globules in hepatocytes
4) Labs you might be asked
- Low serum A1AT level
- Phenotyping/genotyping confirms (PiZZ, etc.)
5) Real-world management (Step-relevant, not Step-obsessive)
- Smoking cessation is huge (smoke accelerates disease)
- A1AT augmentation therapy can slow lung decline in selected patients
- Treat COPD as usual (bronchodilators, vaccines, pulmonary rehab)
- Liver transplant is definitive for end-stage liver disease
Test-Taking Strategy: How to Lock It In Under Time Pressure
When you see obstructive disease, ask three quick questions:
- Age + smoking history: “Too young for COPD?”
- CT distribution: upper vs lower lobe emphysema
- Extra-pulmonary clue: liver disease → think A1AT
If you hit young + basilar emphysema + liver issues, don’t overthink it.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
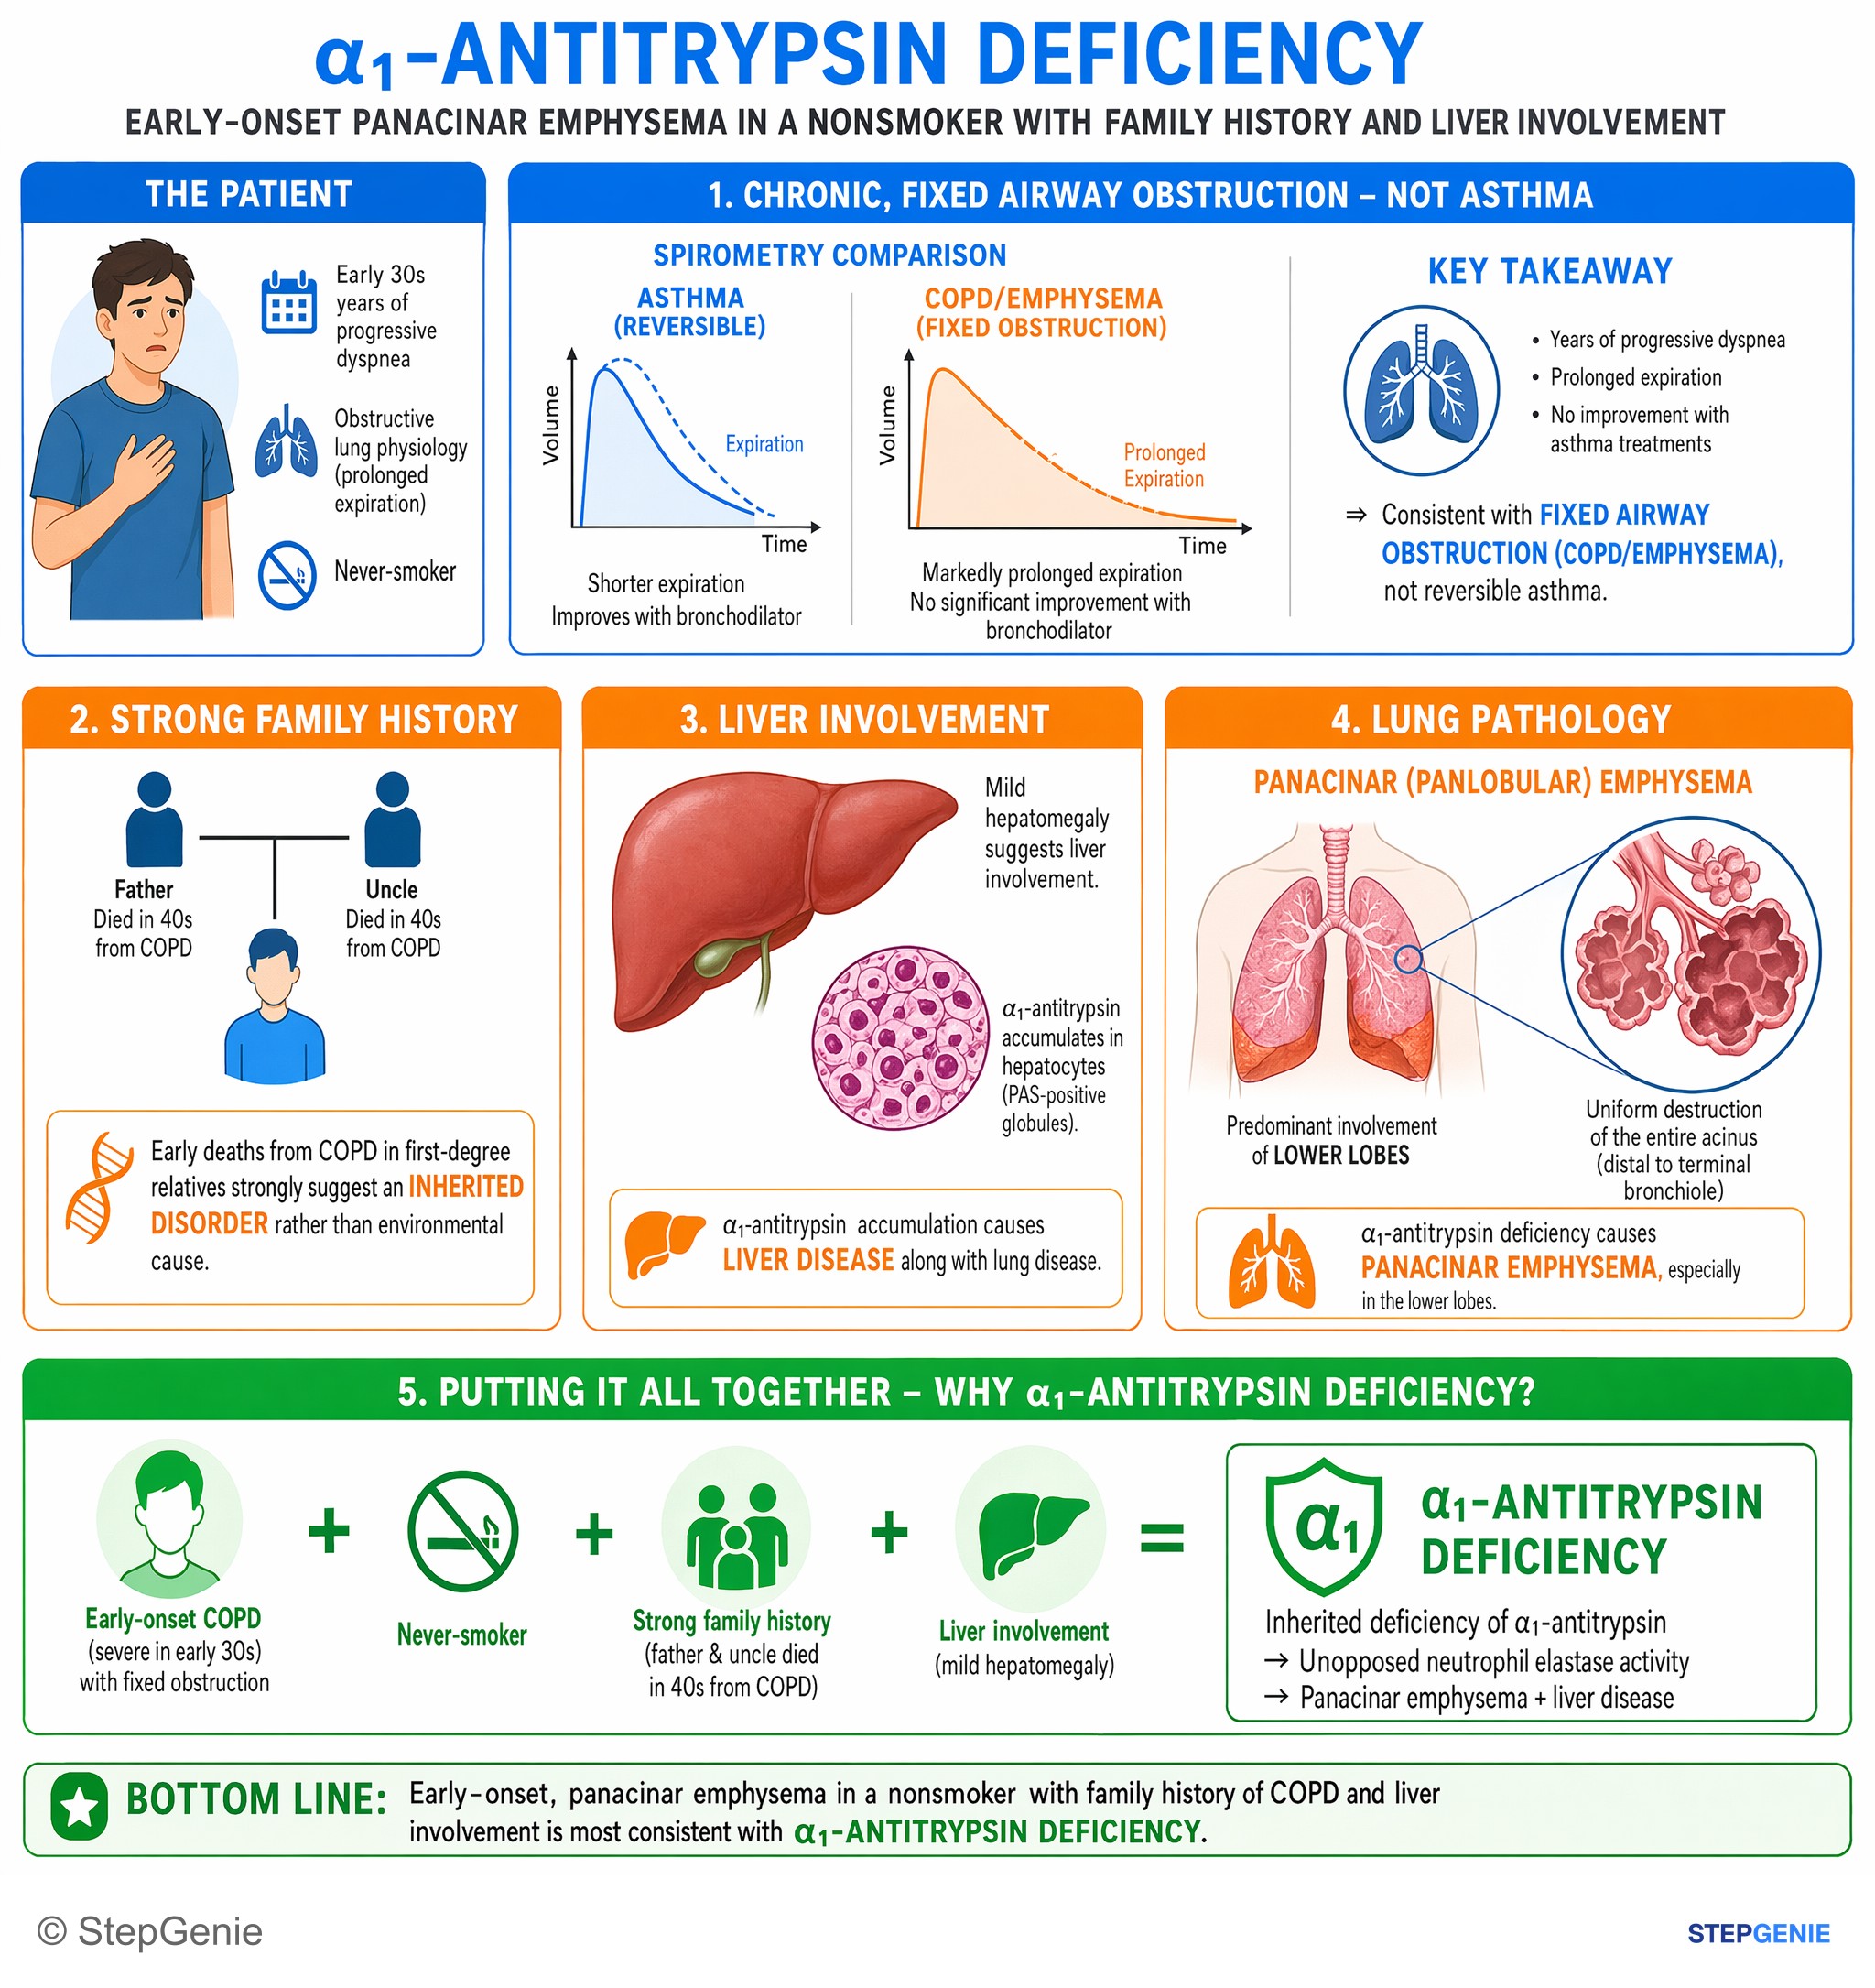
α1-antitrypsin deficiency → early-onset panacinar emphysema in a nonsmoker with family history of COPD and liver involvement.
USMLE Step 2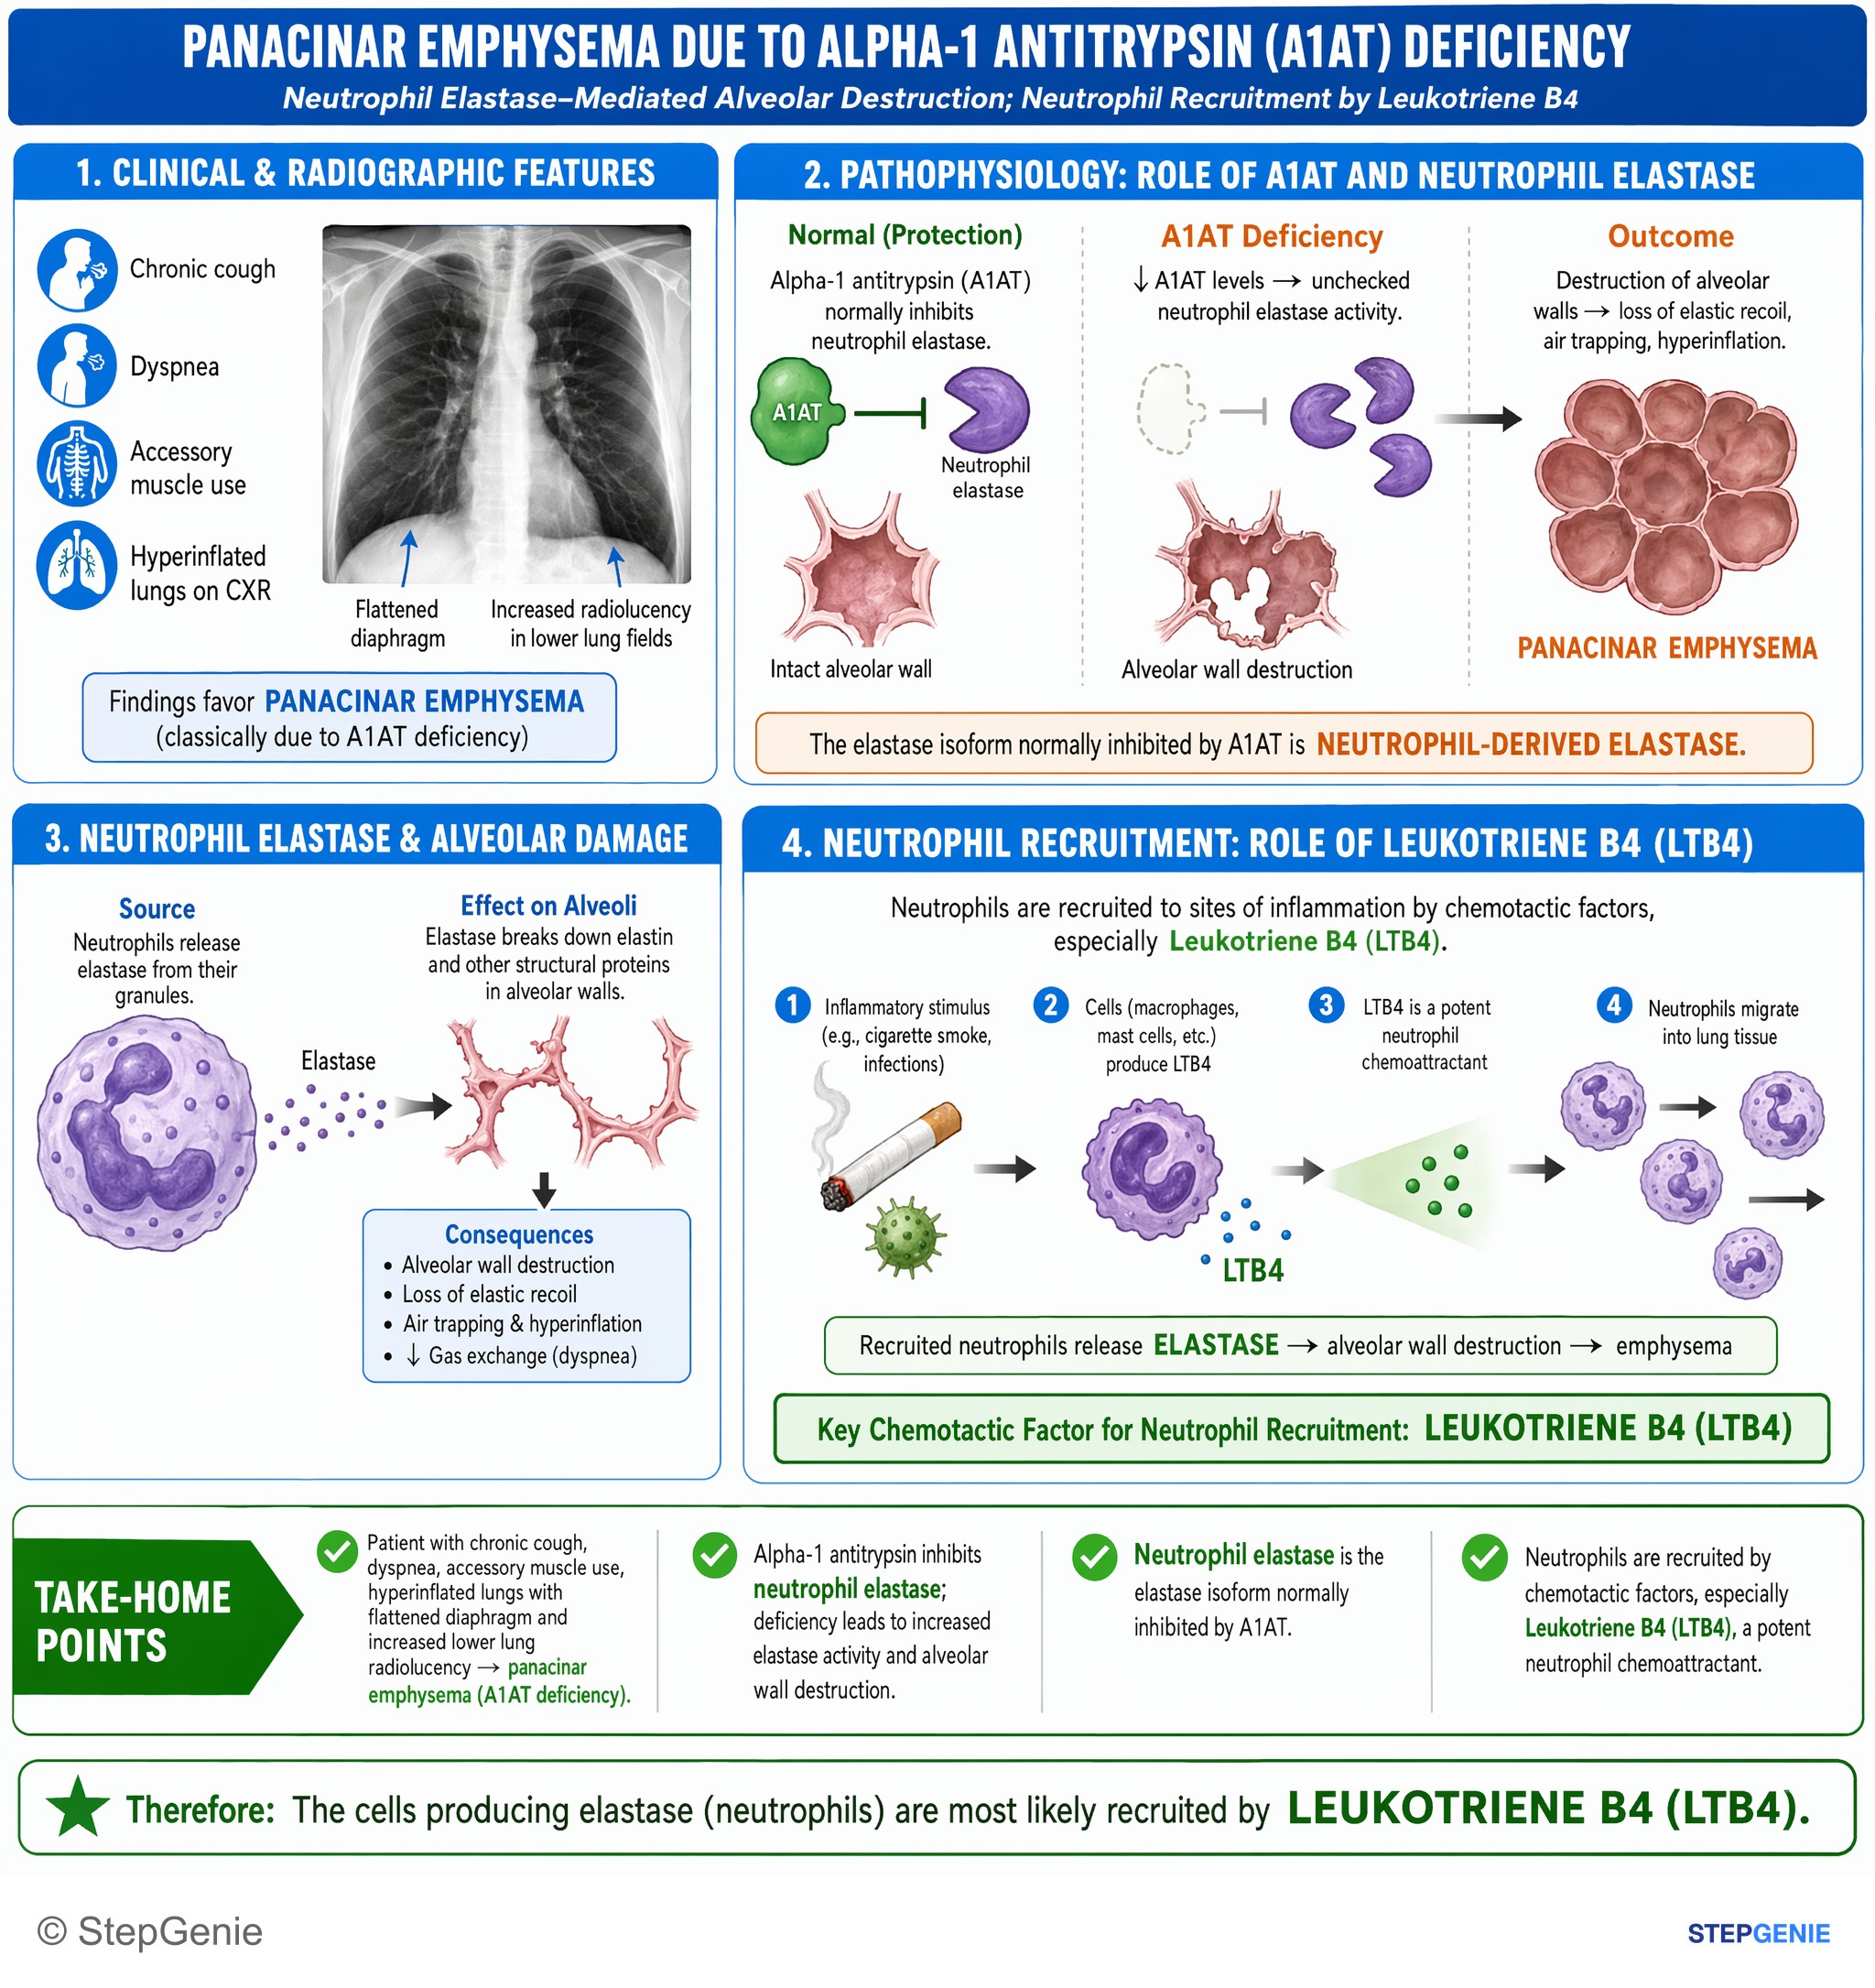
Panacinar emphysema due to A1AT deficiency involves neutrophil elastase–mediated destruction; LTB4 is a key neutrophil chemoattractant.
USMLE Step 1Frequently Asked Questions
Why does alpha-1 antitrypsin deficiency cause both emphysema and liver disease?
Alpha-1 antitrypsin deficiency causes emphysema because there is too little functional A1AT in the lungs and liver disease because misfolded A1AT accumulates in hepatocytes. Low A1AT leaves neutrophil elastase unopposed, leading to panacinar emphysema, while the trapped abnormal protein in the liver can cause hepatitis, cirrhosis, and hepatocellular carcinoma.
How do you tell alpha-1 antitrypsin deficiency emphysema from smoking-related emphysema on a vignette?
Alpha-1 antitrypsin deficiency emphysema is suggested by a younger patient with minimal smoking history, liver clues, and basilar-predominant panacinar emphysema. Smoking-related emphysema classically causes centriacinar emphysema in the upper lobes and usually occurs in an older heavy smoker. Family history of liver disease also points toward inherited A1AT deficiency rather than smoking alone.
Why isn’t cigarette smoke–induced inactivation of alpha-1 antitrypsin the best answer in this case?
It is not the best answer because the vignette points to inherited alpha-1 antitrypsin deficiency as the primary mechanism. Although cigarette smoke can oxidize A1AT and decrease elastase inhibition, smoking-related emphysema is classically centriacinar rather than panacinar. Early onset disease, minimal smoking exposure, and associated liver findings make inherited misfolded protein accumulation the better explanation.
How do you distinguish alpha-1 antitrypsin deficiency from asthma in an obstructive lung disease question?
Alpha-1 antitrypsin deficiency is favored when obstruction is accompanied by emphysema on CT, especially basilar changes, plus liver findings. Asthma is more associated with bronchial smooth muscle hyperresponsiveness, reversible airflow obstruction, atopy, nighttime symptoms, and triggers such as exercise or cold air. The presence of structural emphysematous destruction and hepatic clues argues against asthma.
What pathology clue is high-yield for alpha-1 antitrypsin deficiency on Step-style questions?
A classic pathology clue is PAS-positive, diastase-resistant globules in hepatocytes. This finding reflects accumulated misfolded alpha-1 antitrypsin trapped in liver cells. On exams, it often appears alongside early COPD in a nonsmoker, panacinar emphysema worse at the bases, and signs of liver disease such as jaundice, hepatitis, or cirrhosis.