COPD is one of those Step 1 topics that feels “easy” until you realize how many testable contrasts are packed into it: emphysema vs chronic bronchitis, A1AT deficiency, V/Q mismatching patterns, pulmonary function test (PFT) curves, and classic clinical vignettes. This post is your high-yield, mechanism-first walkthrough designed to help you predict the answer rather than memorize it.
Big Picture: What COPD Is (and Isn’t)
Chronic Obstructive Pulmonary Disease (COPD) is a progressive, not fully reversible airflow limitation due to airway inflammation/remodeling and/or alveolar destruction. It sits under the obstructive umbrella, meaning:
- FEV1 is decreased
- FEV1/FVC ratio is decreased (typically < 0.70)
- Air trapping → increased RV and often increased TLC
COPD vs Asthma (Step 1 shortcut)
- Asthma: reversible, episodic, eosinophils, atopy, large bronchodilator response.
- COPD: partially reversible or fixed, progressive, smoking/biomass exposure, chronic inflammation, less bronchodilator reversibility.
First Aid cross-reference: Pulmonary → Obstructive lung disease; COPD (emphysema, chronic bronchitis), A1AT deficiency, PFT patterns.
The Two Core Phenotypes: Emphysema vs Chronic Bronchitis
COPD often includes elements of both, but Step questions love the “classic” ends of the spectrum.
Quick Compare Table (High Yield)
| Feature | Emphysema | Chronic Bronchitis |
|---|---|---|
| Primary problem | Alveolar wall destruction → ↓ elastic recoil | Mucus hypersecretion + airway inflammation |
| Key pathology | Enlarged airspaces, loss of septa | Enlarged mucus glands, plugging |
| Defining clinical criterion | Not symptom-defined | Productive cough ≥ 3 months/year for ≥ 2 consecutive years |
| Classic patient | “Pink puffer” | “Blue bloater” |
| V/Q pattern (typical boards framing) | More dead space tendency (ventilation > perfusion) | More shunt-like tendency (perfusion > ventilation) |
| DLCO | Decreased (lost surface area) | Normal (alveoli intact) |
| ABG tendency | Later CO₂ retention | Earlier hypercapnia and hypoxemia |
| Imaging | Hyperinflation, bullae, ↓ vascular markings | Increased bronchovascular markings (“dirty chest”) |
| Complications | Spontaneous pneumothorax (blebs), cachexia | Pulm HTN, cor pulmonale, polycythemia |
Pathophysiology You Can Use to Answer Questions
Obstruction in COPD: “Hard to get air out”
Obstructive physiology is dominated by:
- Dynamic airway collapse during expiration
- Air trapping → ↑ RV, ↑ TLC (hyperinflation)
- Prolonged expiration, wheezing, decreased breath sounds
On PFT flow-volume loops: scooped-out expiratory limb.
Emphysema: Protease–Antiprotease Imbalance + Loss of Elastic Recoil
Core mechanism
Emphysema = destruction of alveolar walls → fewer alveolar septa:
- ↓ elastic recoil → small airways collapse on expiration
- ↓ diffusion surface area → ↓ DLCO
- ↑ compliance (floppy lungs) → hyperinflation
Smoking-induced emphysema (most common)
Smoking drives:
- Inflammatory cell recruitment (esp. neutrophils, macrophages)
- ↑ elastase and other proteases
- Oxidative stress → inactivates α1-antitrypsin (A1AT)
Location pattern (very testable)
- Centriacinar (centrilobular) emphysema
- Smokers
- Upper lobes predominance
First Aid hook: Smoking → centriacinar, upper lobes.
A1AT deficiency emphysema (genetics vignette favorite)
α1-antitrypsin normally inhibits neutrophil elastase. Deficiency → unchecked elastase → alveolar destruction.
- Panacinar (panlobular) emphysema
- Lower lobes predominance
- Often younger patient, minimal smoking history possible
Bonus association: Liver disease
Misfolded A1AT accumulates in hepatocytes → cirrhosis, hepatocellular carcinoma risk.
Clues in vignettes
- Young patient with emphysema
- Basilar-predominant disease
- Family history
- Concurrent liver disease
First Aid hook: A1AT deficiency → panacinar, lower lobes + liver disease.
Chronic Bronchitis: Mucus + Airway Remodeling → “Dirty Airways”
Definition (memorize it exactly)
Chronic bronchitis: productive cough for ≥ 3 months per year for ≥ 2 consecutive years.
Core mechanism
Long-term irritants (classically smoking) → airway inflammation:
- Mucous gland enlargement (↑ Reid index)
- Goblet cell hyperplasia → mucus plugs
- Airflow obstruction from narrowing + mucus
- Increased susceptibility to infection
Reid index (Step 1 favorite)
Reid index = thickness of mucous gland layer / thickness of bronchial wall
- Increased in chronic bronchitis due to gland hyperplasia.
Why “blue bloater”?
- Hypoventilation and V/Q mismatch → hypoxemia
- Chronic hypoxemia → pulmonary vasoconstriction → pulmonary HTN → cor pulmonale
- Hypoxemia → ↑ EPO → secondary polycythemia
First Aid hooks: Reid index; cor pulmonale; secondary polycythemia.
Clinical Presentation (How It Shows Up on Test Day)
Shared COPD features
- Progressive dyspnea
- Chronic cough ± sputum
- Wheezing, prolonged expiration
- Decreased breath sounds, barrel chest (esp. emphysema)
- Frequent exacerbations (often infectious triggers)
Emphysema-predominant clues
- Dyspnea > cough
- Thin/cachectic, pursed-lip breathing
- Hyperresonance, decreased breath sounds
- Bullae on imaging
- ↓ DLCO on PFTs
Chronic bronchitis-predominant clues
- Prominent chronic productive cough
- Cyanosis, edema (cor pulmonale)
- More frequent infections
- Normal DLCO
Diagnosis: PFTs, Imaging, and a Few High-Yield Labs
Pulmonary function tests (must-know patterns)
COPD is obstructive:
- FEV1 ↓
- FVC normal or ↓
- FEV1/FVC ↓
- TLC ↑
- RV ↑
Bronchodilator response: may improve a little, but does not normalize.
DLCO (board-friendly discriminator)
- Decreased DLCO → emphysema (destroyed alveolar-capillary surface area)
- Normal DLCO → chronic bronchitis (alveoli mostly intact)
Chest imaging
- Emphysema: hyperinflation, flattened diaphragms, bullae, ↓ vascular markings
- Chronic bronchitis: increased bronchovascular markings (“dirty chest”)
ABGs (pattern recognition)
- COPD can show chronic CO₂ retention later → respiratory acidosis with metabolic compensation (↑ HCO₃⁻).
- Chronic bronchitis tends toward earlier hypoxemia/hypercapnia than emphysema-predominant disease.
COPD Exacerbations (Step 2 crossover, still Step 1-relevant)
Common triggers:
- Viral URIs
- Bacterial infections (often H. influenzae, S. pneumoniae, Moraxella catarrhalis)
- Environmental pollutants
Typical vignette: increased dyspnea, increased sputum volume, increased sputum purulence.
Treatment: What You Actually Need to Know for USMLE
Core chronic management (conceptual ladder)
- Smoking cessation (biggest mortality benefit)
- Bronchodilators
- Short-acting (rescue): SABA (albuterol), SAMA (ipratropium)
- Long-acting (maintenance): LABA (salmeterol), LAMA (tiotropium)
- Inhaled corticosteroids (ICS) for frequent exacerbations / eosinophilic component (often combined with LABA)
- Pulmonary rehab
- Oxygen for chronic hypoxemia
- Selected patients: roflumilast (PDE-4 inhibitor), surgery (bullectomy, lung volume reduction), transplant
Oxygen therapy: the testable criterion
Long-term oxygen is indicated when:
- PaO₂ ≤ 55 mmHg or SaO₂ ≤ 88% (at rest), or
- PaO₂ 56–59 with evidence of pulmonary HTN, cor pulmonale, or polycythemia (often taught conceptually)
Managing acute exacerbations (high yield)
- Short-acting bronchodilators (SABA ± SAMA)
- Systemic corticosteroids
- Antibiotics if increased purulence/volume/dyspnea or severe illness
- Noninvasive ventilation (BiPAP) for hypercapnic respiratory failure (common Step 2 concept)
High-Yield Associations & “Classic” USMLE Traps
1) A1AT deficiency = lung + liver
- Panacinar emphysema, lower lobes
- Cirrhosis/HCC risk (misfolded protein accumulation)
2) DLCO distinguishes emphysema from most other obstructive diseases
- Emphysema: DLCO ↓
- Asthma/chronic bronchitis: DLCO usually normal or ↑ (asthma may be normal/↑)
3) Cor pulmonale linkage (often via chronic bronchitis phenotype)
Chronic hypoxemia → pulmonary vasoconstriction → pulmonary HTN → RV hypertrophy/failure.
4) Polycythemia
Hypoxemia → ↑ EPO → ↑ RBC mass.
5) Smoking and cancer overlap (don’t mix them up)
Smoking predisposes to both COPD and lung cancer, but COPD itself classically gives:
- Hyperinflation, wheeze, chronic cough/sputum Cancer vignettes lean toward:
- Weight loss, hemoptysis, focal mass, paraneoplastic syndromes
Rapid Review: Step-Style “If You See This, Think That”
- Upper lobe emphysema in smoker → centrilobular emphysema
- Lower lobe emphysema in younger patient + liver disease → A1AT deficiency (panacinar)
- Chronic productive cough for years → chronic bronchitis
- Reid index increased → chronic bronchitis
- DLCO decreased → emphysema
- Pulmonary HTN + cor pulmonale + cyanosis → often chronic bronchitis-predominant COPD
Mini Table: The “Pink Puffer” vs “Blue Bloater” Myth—Used Correctly
These are extremes; real patients often overlap. Still, boards use them as shorthand.
| Board phrase | What they’re really testing |
|---|---|
| “Pink puffer” | Emphysema physiology: hyperinflation, pursed-lip breathing, less sputum, ↓ DLCO |
| “Blue bloater” | Chronic bronchitis physiology: mucus plugging, hypoxemia early, cor pulmonale, polycythemia, normal DLCO |
Takeaway
If you anchor COPD to (1) obstruction, then separate the phenotypes by (2) alveolar destruction (emphysema, ↓ DLCO) vs (3) mucus/inflammation (chronic bronchitis, ↑ Reid index), most USMLE questions become pattern recognition with a mechanistic backbone.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
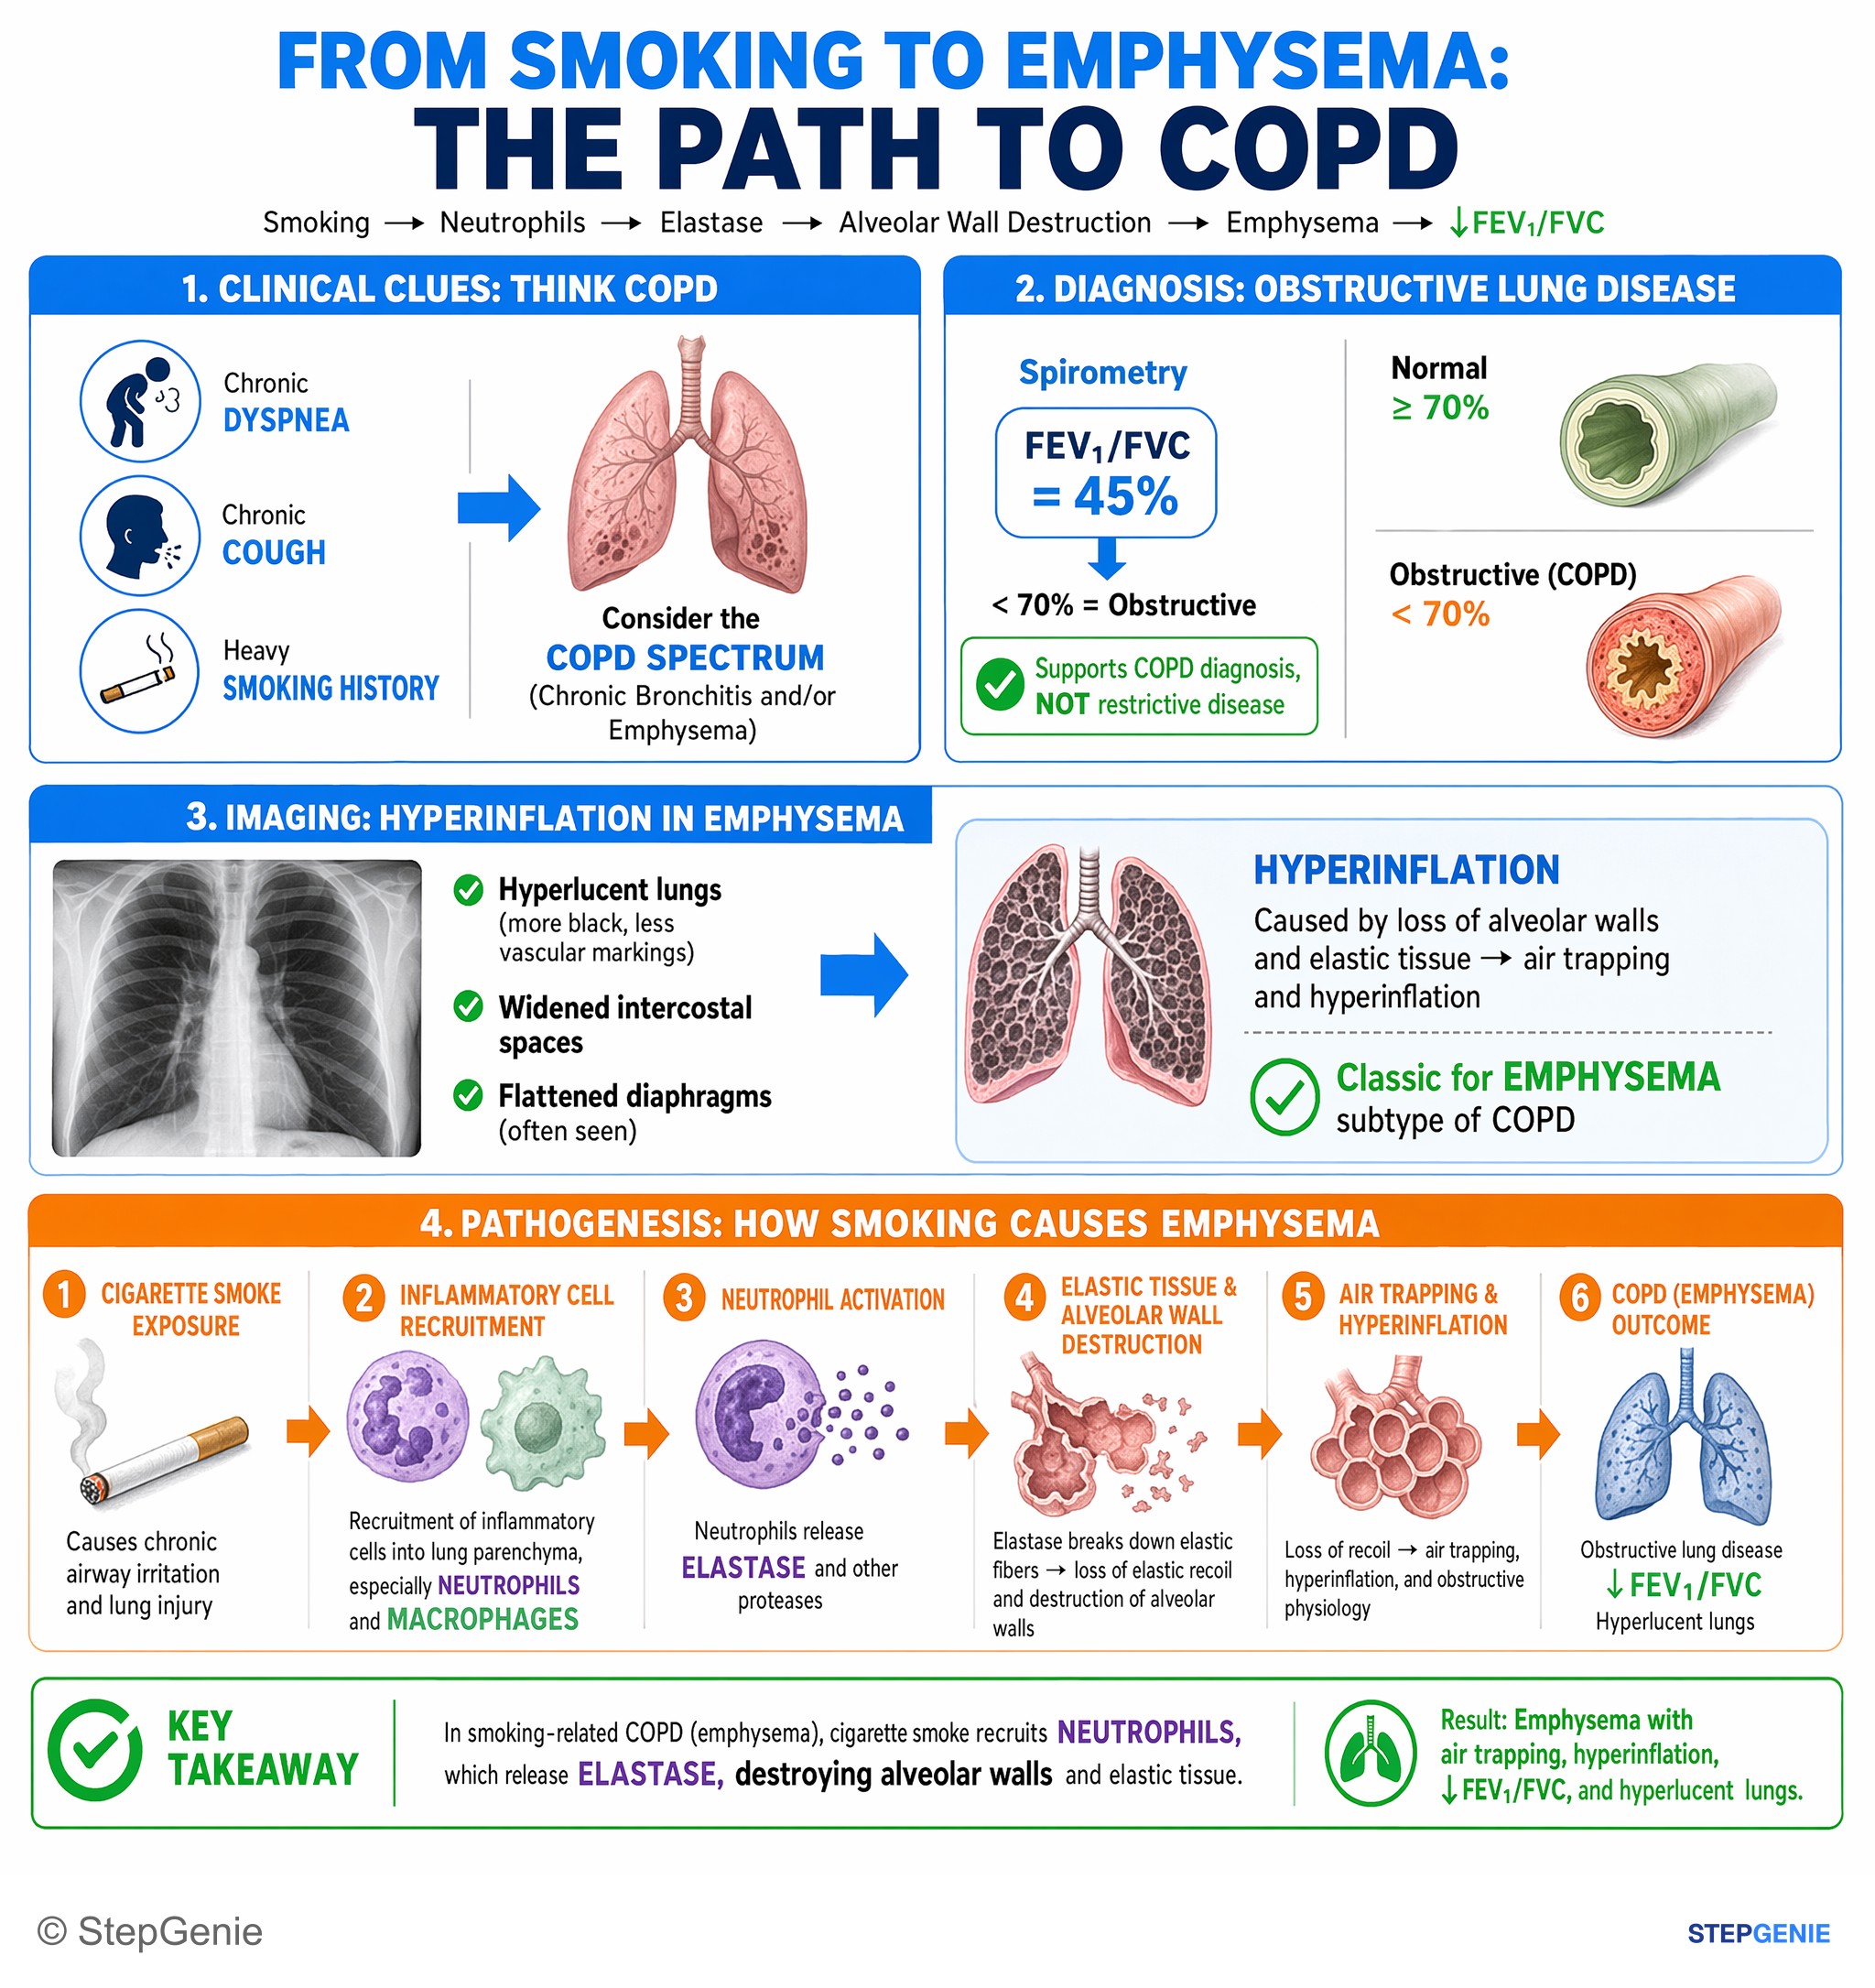
Emphysema due to smoking: cigarette smoke recruits neutrophils, which release elastase, destroying alveolar walls and causing COPD with…
USMLE Step 1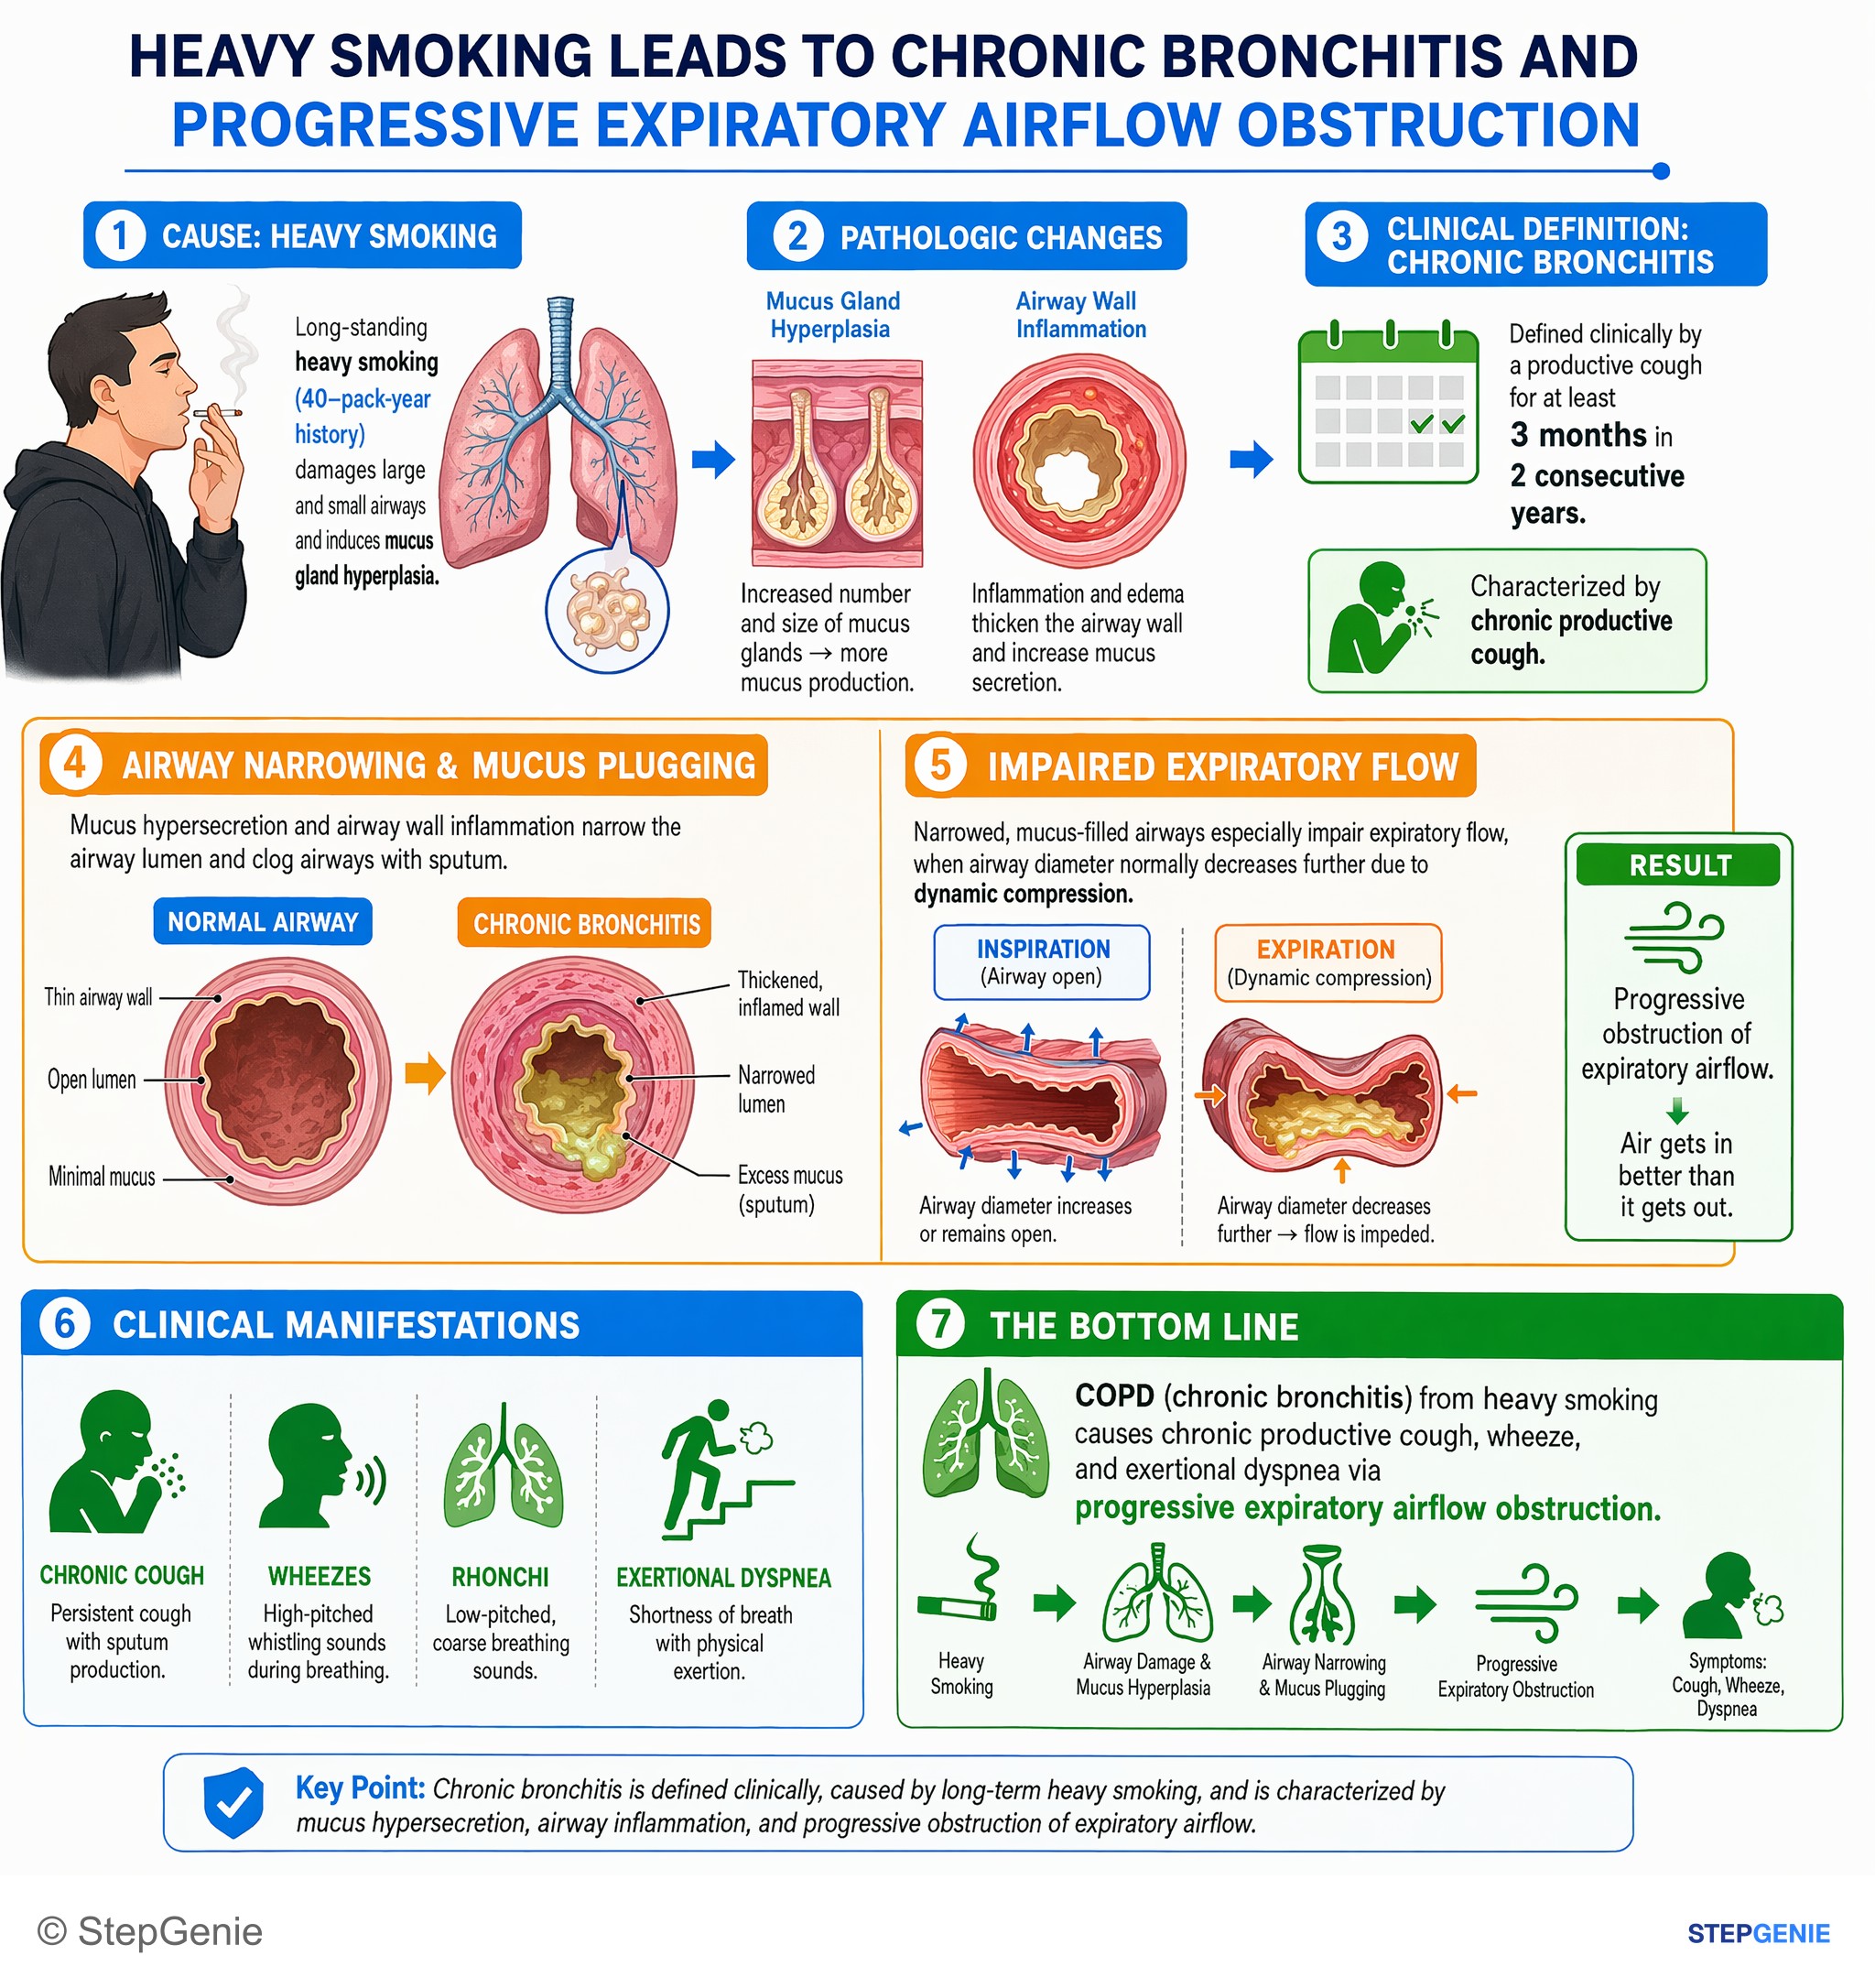
COPD (chronic bronchitis) from heavy smoking causes chronic productive cough, wheeze, and exertional dyspnea via progressive expiratory…
USMLE Step 1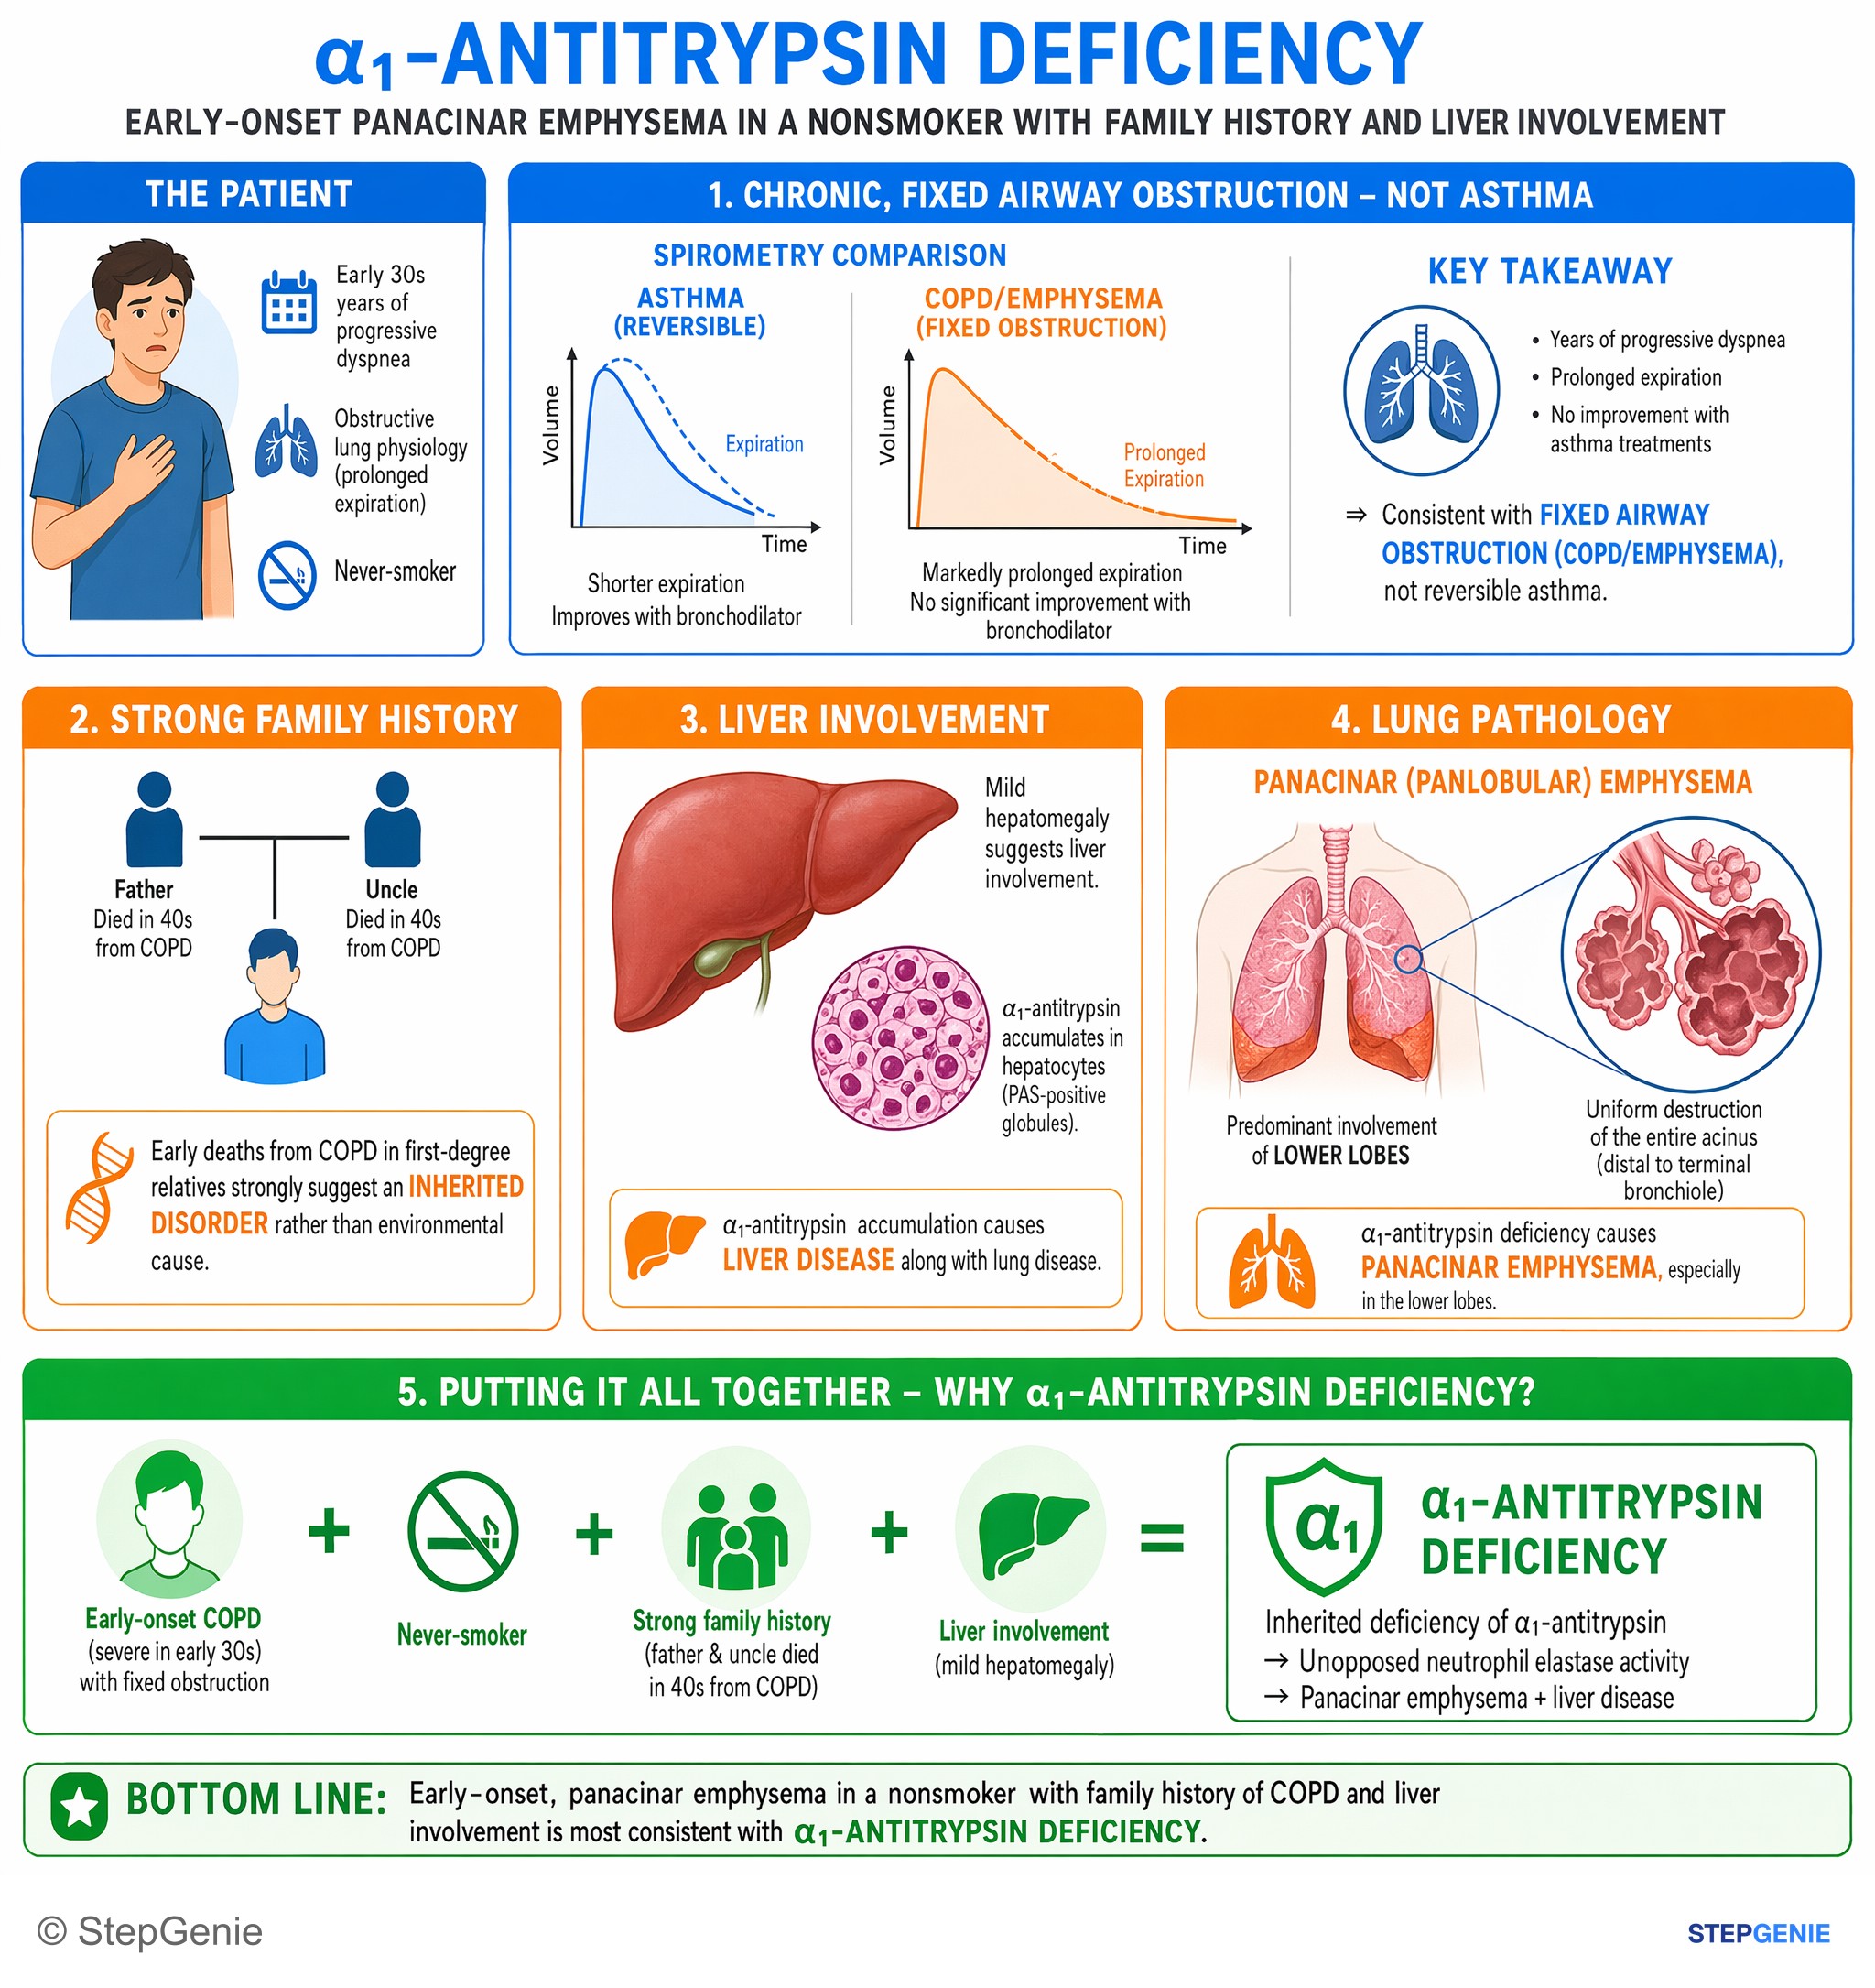
α1-antitrypsin deficiency → early-onset panacinar emphysema in a nonsmoker with family history of COPD and liver involvement.
USMLE Step 2Frequently Asked Questions
How do you tell emphysema from chronic bronchitis on PFTs and diffusion testing?
The key discriminator is DLCO: it is decreased in emphysema and normal in chronic bronchitis. Emphysema destroys alveolar walls, which reduces diffusion surface area and lowers DLCO. Chronic bronchitis mainly causes mucus hypersecretion and airway inflammation while the alveoli remain intact, so DLCO stays normal. Both still show an obstructive pattern with decreased FEV1, decreased FEV1/FVC, and air trapping.
Why does emphysema cause a decreased DLCO?
Emphysema lowers DLCO because it destroys alveolar walls and reduces the surface area available for gas diffusion. The loss of alveolar septa also decreases elastic recoil, which contributes to airway collapse during expiration and hyperinflation. On exams, a reduced DLCO points toward emphysema rather than chronic bronchitis because the alveoli themselves are damaged.
What are the classic Step 1 clues for alpha-1 antitrypsin deficiency emphysema?
Alpha-1 antitrypsin deficiency classically presents as panacinar emphysema with lower lobe predominance, often in a younger patient and sometimes with little smoking history. The mechanism is unchecked neutrophil elastase activity causing alveolar destruction because alpha-1 antitrypsin normally inhibits elastase. A strong clue is concurrent liver disease, since misfolded alpha-1 antitrypsin can accumulate in hepatocytes and lead to cirrhosis.
Why does chronic bronchitis lead to cor pulmonale and secondary polycythemia?
Chronic bronchitis causes hypoventilation and V/Q mismatch, which lead to chronic hypoxemia. Persistent hypoxemia triggers pulmonary vasoconstriction, causing pulmonary hypertension and eventually cor pulmonale. The same hypoxemia also increases erythropoietin production, leading to secondary polycythemia. This is why chronic bronchitis is associated with cyanosis, edema, and the classic “blue bloater” presentation.
How do you define chronic bronchitis for Step 1?
Chronic bronchitis is defined as a productive cough for at least 3 months per year for at least 2 consecutive years. This diagnosis reflects long-term airway irritation, usually from smoking, leading to mucous gland enlargement, goblet cell hyperplasia, and mucus plugging. A related Step 1 favorite is the increased Reid index, which reflects thickening of the mucous gland layer in the bronchial wall.