Compliance and elastance are inverses of each other. Compliance () is how much volume each unit of pressure buys, meaning how easily the lung inflates; elastance () is how much pressure each unit of volume costs, meaning stiffness and elastic recoil. Emphysema raises compliance and lowers elastance; fibrosis, ARDS, pulmonary edema and neonatal RDS do the reverse.
Compliance vs elastance side by side
| Feature | Compliance (C) | Elastance (E) |
|---|---|---|
| Formula | ||
| Units | mL/cm H₂O | cm H₂O/mL (or cm H₂O/L) |
| Plain meaning | Distensibility: how easily it fills | Stiffness: how hard it pushes back |
| On a volume–pressure curve | The slope; steeper = more compliant | The inverse of the slope; flatter = stiffer |
| Elastic recoil | Low when compliance is high | High when elastance is high |
| Classic disease with a high value | Emphysema | Pulmonary fibrosis, ARDS |
| Effect on FRC | High lung compliance → ↑ FRC | High lung elastance → ↓ FRC |
| Lung + chest wall (in series) |
Both lungs together normally have a compliance of about 200 mL/cm H₂O. The lungs and chest wall are stretched in series, so the whole respiratory system is stiffer (less compliant) than either part measured alone. That is where elastance earns its keep: elastances in series simply add, so a stiff chest wall and a stiff lung each add their own load.
Compliance vs elasticity: the word trap
In everyday speech "elastic" often means stretchy, which invites confusion. In respiratory physiology, elasticity means recoil (the tendency to spring back), and it is measured as elastance. An emphysematous lung is very stretchy (high compliance) precisely because it has lost its elasticity (low elastance). A useful picture: a new party balloon is hard to blow up and snaps back (high elastance); a worn-out balloon inflates easily and sags (high compliance).
| Term | Physiology meaning | Emphysema | Fibrosis |
|---|---|---|---|
| Compliance | Volume gained per unit pressure | High | Low |
| Elastance | Pressure needed per unit volume | Low | High |
| Elasticity / elastic recoil | Tendency to spring back | Lost | Increased |
| Distensibility | Same idea as compliance | High | Low |
Decide in 60 seconds: stiff, floppy or blocked?
- Picture the breath. Hard to inflate, small lung volumes → ↓ compliance, ↑ elastance. Easy to inflate but hard to empty (air trapping, barrel chest) → ↑ compliance, ↓ elastance.
- Name what changed in the tissue. Elastic fibers destroyed (emphysema) → compliance up. Excess collagen and scarring in the interstitium (fibrosis), fluid or protein in the alveoli (edema, ARDS) or collapsed alveoli (atelectasis, or surfactant deficiency in neonatal RDS) → compliance down.
- Locate the stiffness. Obesity and scoliosis stiffen the chest wall and lower respiratory-system compliance with a normal DLCO. Interstitial fibrosis stiffens the lung itself and lowers DLCO.
- Don't confuse resistance with compliance. Asthma and chronic bronchitis are airway-resistance problems; in obstructive disease, compliance is normal or increased. The obstructive disease with a big compliance change is emphysema.
- Predict the knock-on findings. ↑ compliance → ↓ recoil → air trapping with ↑ FRC, RV and TLC and a low FEV₁/FVC. ↓ compliance → ↑ recoil → ↓ TLC, FRC and RV, with FEV₁/FVC normal or ↑.
How common conditions shift compliance and elastance
| Condition | Lung compliance | Elastance / recoil | Volumes | Classic clue |
|---|---|---|---|---|
| Emphysema | ↑ | ↓ | ↑ FRC, RV, TLC | Barrel chest, ↓ FEV₁/FVC, ↓ DLCO |
| Normal aging | ↑ (chest wall compliance ↓) | ↓ (lung) | ↑ RV, FRC slightly ↑, ↓ VC; TLC unchanged | Lung and chest wall change in opposite directions with age |
| Pulmonary fibrosis | ↓ | ↑ | ↓ FRC, RV, TLC | Restrictive pattern: FEV₁/FVC normal or ↑, ↓ DLCO |
| ARDS | ↓↓ | ↑↑ | ↓ aerated lung | Bilateral opacities with hypoxemia (2024 global definition: P/F ≤300, or SpO₂/FiO₂ ≤315 when SpO₂ ≤97%) |
| Neonatal RDS | ↓ | ↑ | ↓ (atelectasis) | Surfactant deficiency with diffuse alveolar collapse |
| Pulmonary edema, atelectasis | ↓ | ↑ | ↓ | High plateau pressure on a ventilator |
| Obesity, scoliosis | Chest wall ↓ (lung ↓ too) | ↑ | ↓ FRC and ERV | Restrictive pattern with normal DLCO |
For the gas-exchange side of the same diseases, see dead space vs shunt and emphysema vs chronic bronchitis.
FRC: where two elastic forces cancel
Functional residual capacity (about 3 L in a healthy adult) is the volume at which the lung's inward recoil and the chest wall's outward recoil are in equilibrium. Change either elastance and the resting volume moves:
- Emphysema: the lung's inward recoil weakens, so the chest wall wins and FRC rises (air trapping, barrel chest).
- Fibrosis and other intrinsic restrictive disease: the lung recoils harder and TLC falls, so FRC falls.
- Obesity, pregnancy and lying supine or prone: thoracic volume falls and so does FRC; in pregnancy, RV and ERV fall, which predisposes to atelectasis.
Intrinsic vs extrinsic restriction: whose compliance fell?
Restrictive disease means a reduced TLC with an FEV₁/FVC ratio that is preserved or increased. The compliance lens tells you where the problem sits.
| Feature | Intrinsic (parenchymal) | Extrinsic (chest wall, neuromuscular, obesity, pleura) |
|---|---|---|
| Whose compliance is low | The lung's | The chest wall's (thoracic compliance); in neuromuscular disease the core problem is weak respiratory muscles rather than stiffness |
| Examples | Interstitial lung disease, idiopathic pulmonary fibrosis | Obesity, kyphoscoliosis, neuromuscular weakness, pleural disease |
| DLCO | Decreased (thickened alveolar septa) | Within the reference range |
| Respiratory-system compliance | Decreased | Decreased (lung and thorax are in series) |
Reading the pressure–volume curve
- Slope = compliance. A steep curve (emphysema) gains a lot of volume for little pressure; a flat curve (fibrosis, ARDS) gains little.
- Hysteresis. The inflation and deflation limbs differ: more pressure is needed to inflate the lungs than to deflate them. The curve is sometimes called the hysteresis curve for that reason.
- Specific compliance divides compliance by FRC. It corrects for lung size, so a small lung can have a low absolute compliance without its tissue being any stiffer.
- Static vs dynamic. Static compliance is measured with no airflow (an inspiratory pause, muscles relaxed), so it reflects elastic recoil alone. Dynamic compliance is measured during breathing and also reflects airway resistance, so it falls in bronchospasm even when the lung tissue is normal.
Surfactant, surface tension and the law of Laplace
Surface tension at the alveolar air–liquid interface adds to the lung's inward recoil. Surfactant (mainly dipalmitoylphosphatidylcholine with surfactant proteins and calcium, made by type II pneumocytes) lowers surface tension, which raises compliance and lowers elastance and keeps small alveoli open. By the law of Laplace, : for the same surface tension, the collapsing pressure is highest in the smallest alveoli, so lowering surface tension is what keeps small alveoli from collapsing.
- Transpulmonary pressure () is the ΔP in the lung-compliance equation. Stiff lungs need a bigger swing for the same tidal volume: a more negative intrapleural pressure when breathing spontaneously, or a higher plateau pressure on a ventilator.
- Neonatal RDS: without surfactant, surface tension stays high, alveoli collapse (atelectasis) and the lung becomes stiff.
The ventilator version (Step 2 CK and Step 3)
Peak airway pressure is the total pressure needed to push gas in: resistive pressure plus elastic pressure plus PEEP. An end-inspiratory hold of about 0.3–0.5 seconds stops flow, and the resulting plateau pressure minus PEEP is the elastic pressure. So:
- Static compliance , and elastance is its reciprocal.
- Resistive pressure = peak − plateau.
| Ventilator pattern | Meaning | Causes to name |
|---|---|---|
| High peak, normal plateau (large peak–plateau gap) | Resistance problem | Kinked or secretion-plugged endotracheal tube, bronchospasm, intraluminal mass |
| High peak and high plateau | Compliance problem (high elastance) | ARDS, pulmonary edema, fibrosis, lobar atelectasis, pneumothorax, large pleural effusion, mainstem intubation, obesity, ascites, pregnancy, circumferential burns |
| Expiratory flow that never reaches zero | Auto-PEEP (air trapping) | Asthma or COPD with too short an expiratory time, or very high minute ventilation |
Lung-protective ventilation in ARDS. Use low tidal volumes (6–8 mL/kg of ideal body weight to start, aiming for about 6) and keep plateau pressure at or below 30 cm H₂O. Driving pressure (plateau − PEEP, equal to ) matters too: in a pooled analysis of 3,562 patients from nine ARDS trials, each increase of about 7 cm H₂O in driving pressure was associated with higher mortality (relative risk 1.41), and the link held even when plateau pressure and tidal volume were "protective" (relative risk 1.36). The 2024 ATS guideline update suggests higher PEEP without lung recruitment maneuvers for moderate to severe ARDS and recommends against prolonged recruitment maneuvers. For auto-PEEP, lower the respiratory rate or shorten inspiratory time to lengthen expiration.
For the full syndrome (Berlin criteria vs the 2024 global definition, P/F ratio, histology), see ARDS.
The same idea outside the lung
Arteries obey the same rule: pulse pressure ≈ stroke volume ÷ arterial compliance. Aging stiffens large arteries (less elastin, more collagen, calcification), so compliance falls and pulse pressure widens.
How USMLE tests compliance and elastance
- Pick the disease from a curve: a steep pressure–volume slope means high compliance (emphysema, aging lung); a flat slope means low compliance (fibrosis, ARDS, neonatal RDS).
- Do the arithmetic: static compliance from tidal volume, plateau pressure and PEEP, then elastance as its reciprocal.
- Predict the resting volume: FRC up when lung recoil is lost, down when the lung or chest wall stiffens.
- Separate stiffness from obstruction: a high plateau pressure is a compliance problem; a large peak–plateau gap is a resistance problem.
- Explain surfactant: lower surface tension means higher compliance and stable small alveoli (Laplace).
- Decode the word "elastic": high elasticity means strong recoil and low compliance, never "stretchy."
Worked examples
Vignette 1. A 54-year-old woman with acute pancreatitis is intubated for ARDS. Volume-control settings: tidal volume 420 mL, PEEP 10 cm H₂O. Peak airway pressure is 35 cm H₂O and plateau pressure is 31 cm H₂O. What best describes her respiratory mechanics?
Answer: markedly decreased compliance (increased elastance) with near-normal airway resistance. Static compliance = 420 ÷ (31 − 10) = 20 mL/cm H₂O; elastance = 1/C = 0.05 cm H₂O/mL (50 cm H₂O/L).
One-line reasoning: the plateau (elastic) pressure is high while the peak–plateau gap is only 4 cm H₂O, so the problem is stiff, flooded, surfactant-poor alveoli rather than the airways. Her plateau pressure also exceeds 30 cm H₂O, so the tidal volume should come down.
Vignette 2. A ventilated patient with asthma suddenly has a peak pressure of 40 cm H₂O; plateau pressure is 15 cm H₂O and PEEP is 5 cm H₂O. Is the problem compliance or resistance?
Answer: Resistance. The resistive pressure (peak − plateau) is 25 cm H₂O, far above about 10, while the elastic pressure (15 − 5 = 10 cm H₂O) is not raised; think bronchospasm or a plugged or kinked tube.
Vignette 3. A 67-year-old man with progressive exertional dyspnea has a reduced TLC, an FEV₁/FVC ratio of 0.86 and a low DLCO. His obese brother has a similarly reduced TLC but a normal DLCO. Whose lung tissue is stiff?
Answer: The first patient's. Low TLC with a preserved ratio and a low DLCO means intrinsic (parenchymal) restriction such as pulmonary fibrosis: low lung compliance, high lung elastance. The brother's normal DLCO points to extrinsic restriction from a stiff chest wall and abdomen, with normal lung tissue.
Key takeaways
- Compliance = (ease of filling); elastance = = 1/C (stiffness and recoil). They always move in opposite directions.
- "Elastic" in physiology means recoil, so the high-compliance emphysematous lung has lost elasticity.
- Emphysema is the classic high-compliance, low-elastance lung: easy in, hard out, with ↑ FRC and air trapping.
- Fibrosis, ARDS, neonatal RDS, edema and atelectasis are low-compliance, high-elastance lungs: small volumes, rapid shallow breathing and high ventilator plateau pressures.
- Lung and chest wall act in series: elastances add, and the combined system is stiffer than either part.
- On a ventilator, a high plateau pressure means low compliance; a high peak with a normal plateau means high resistance; keep plateau ≤30 and watch driving pressure.
More respiratory physiology lives on the pulmonology topic hub.
Sources
- Physiology, Pulmonary Compliance (StatPearls, NCBI Bookshelf)
- Pulmonary Compliance, archived chapter (StatPearls, NCBI Bookshelf)
- Ventilator Management, archived chapter (StatPearls, NCBI Bookshelf)
- Overview of Mechanical Ventilation — Merck Manual Professional Edition
- Amato MBP, et al. Driving pressure and survival in the acute respiratory distress syndrome. N Engl J Med. 2015 (PubMed)
- Qadir N, et al. An Update on Management of Adult Patients with ARDS: An Official ATS Clinical Practice Guideline. Am J Respir Crit Care Med. 2024 (PubMed)
- Physiology, Functional Residual Capacity (StatPearls, NCBI Bookshelf)
- Restrictive Lung Disease (StatPearls, NCBI Bookshelf)
- Physiology, Residual Volume (StatPearls, NCBI Bookshelf)
- Diffusing Capacity of the Lungs for Carbon Monoxide (StatPearls, NCBI Bookshelf)
- Matthay MA, et al. A New Global Definition of Acute Respiratory Distress Syndrome. Am J Respir Crit Care Med. 2024 (PubMed)
- Physiology, Pulse Pressure (StatPearls, NCBI Bookshelf)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
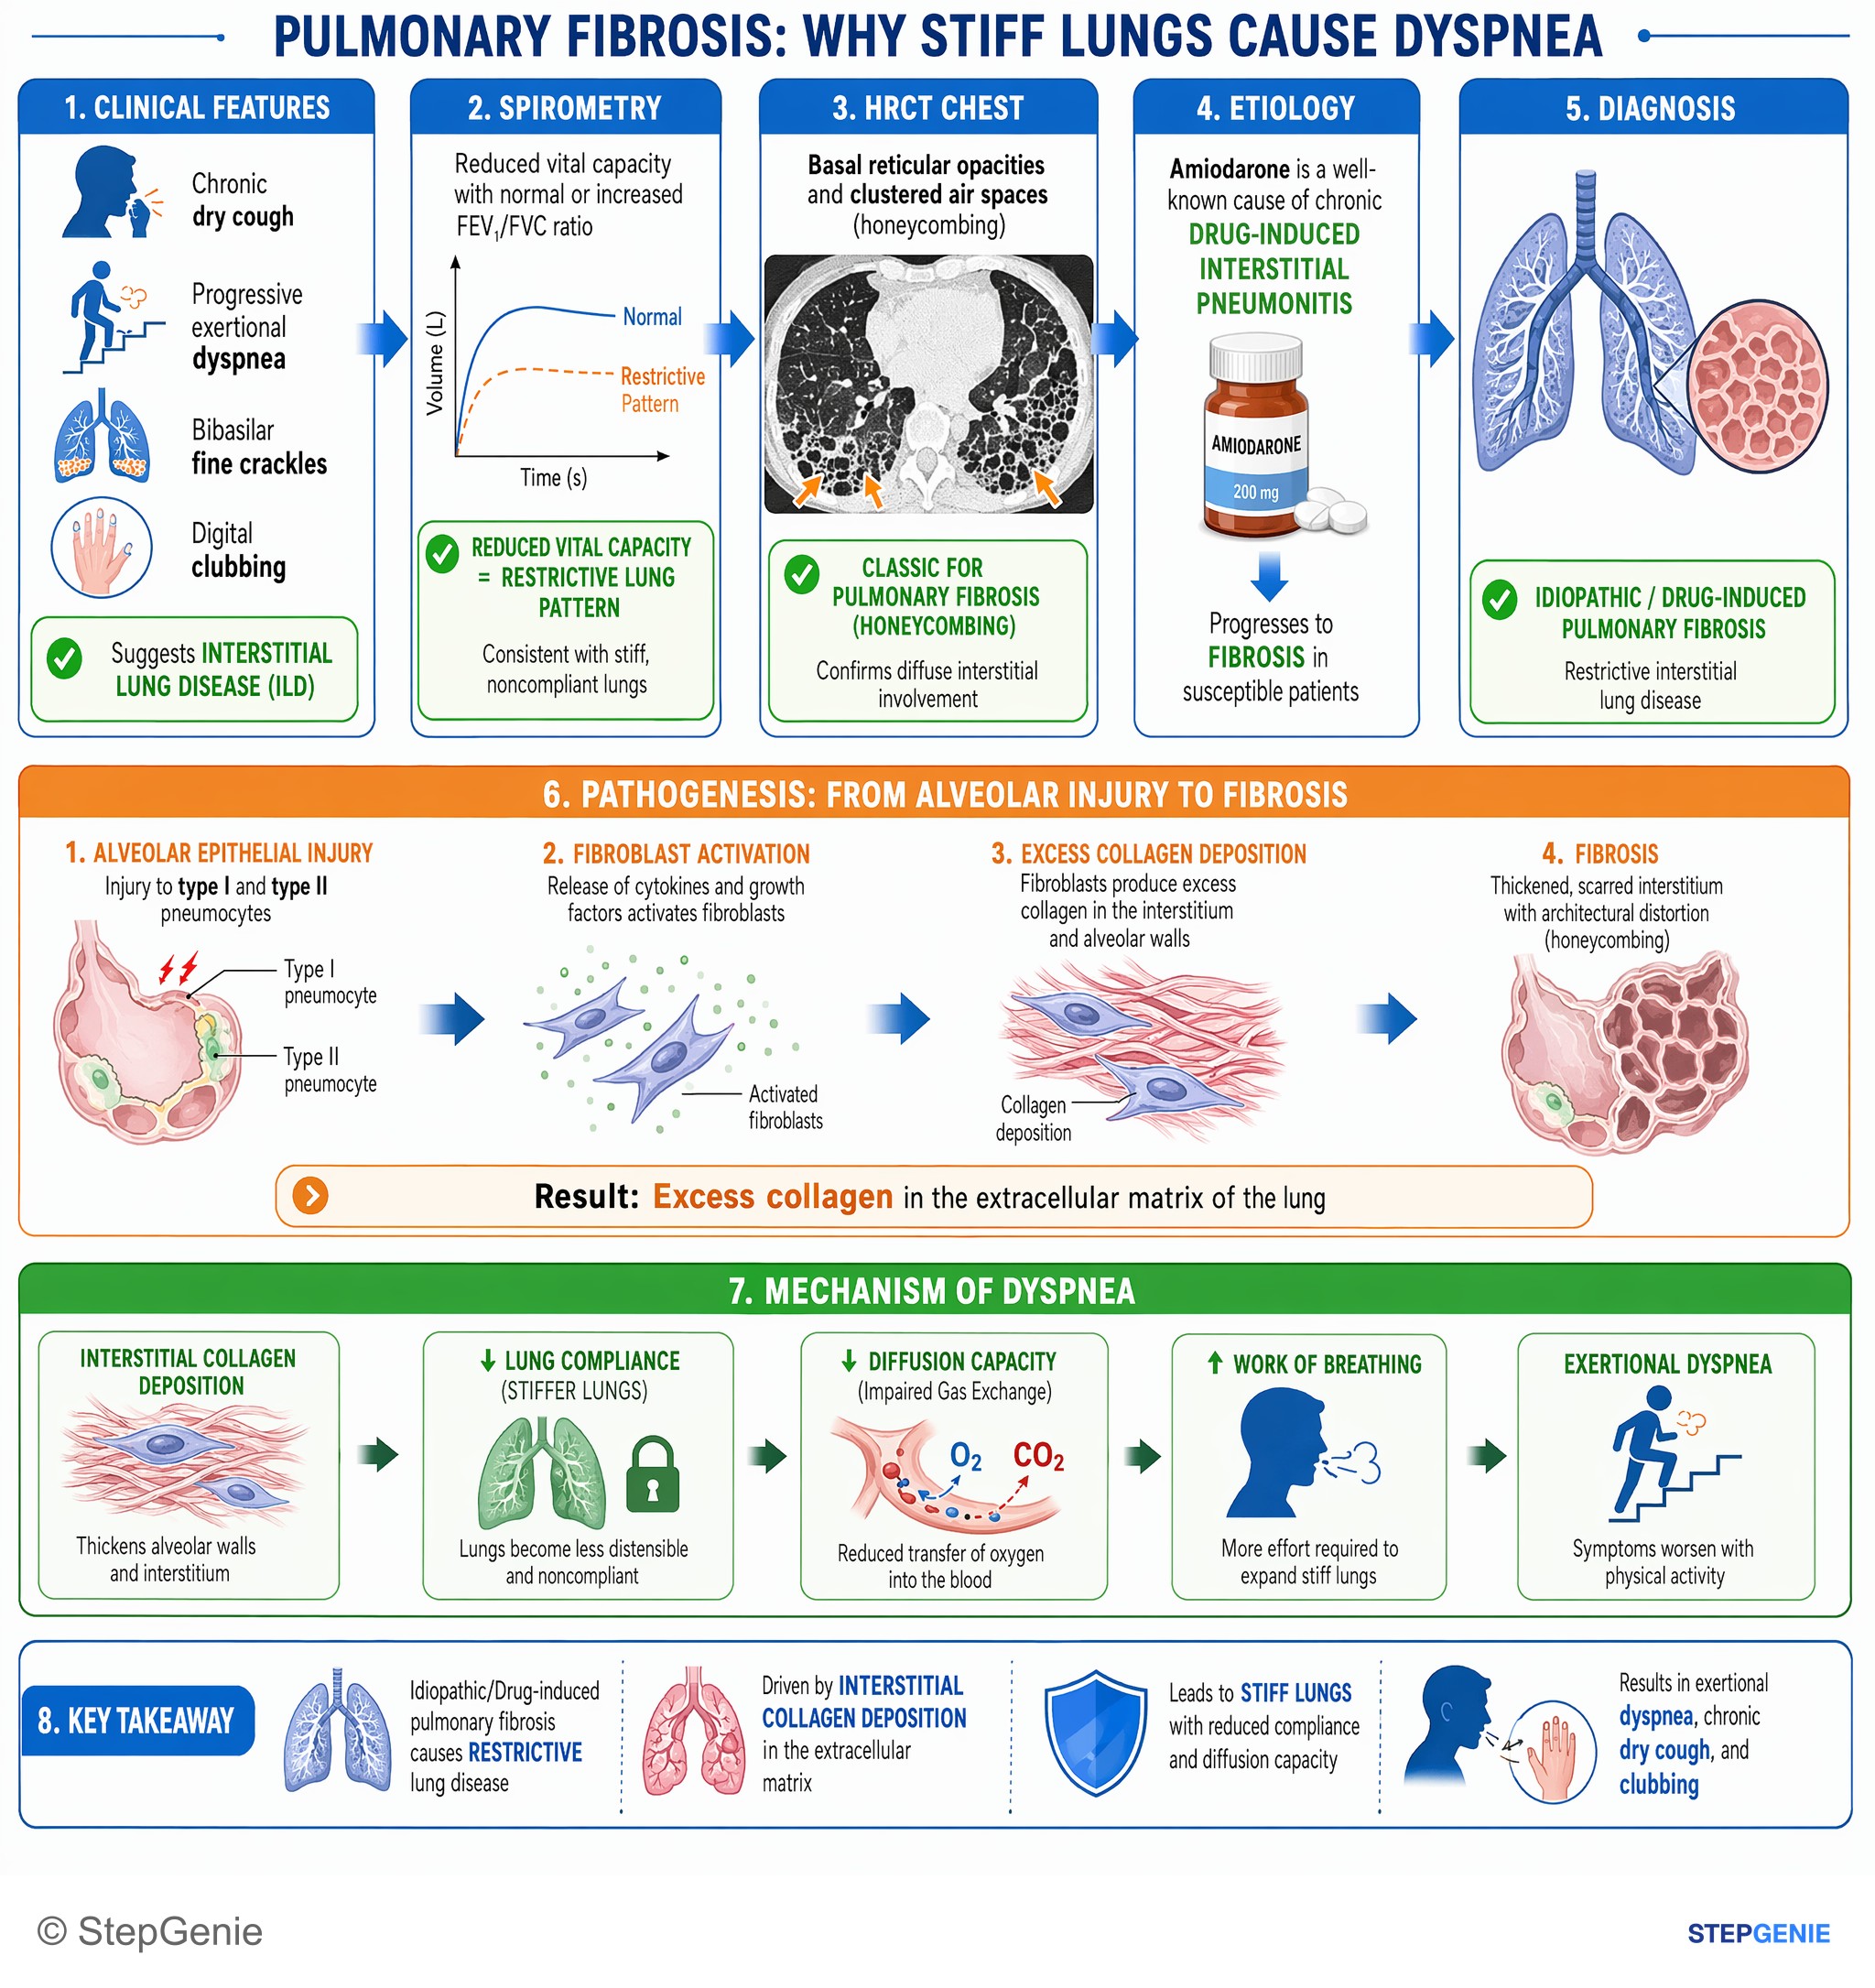
Idiopathic/Drug-induced pulmonary fibrosis causes restrictive lung disease from interstitial collagen deposition, leading to stiff lungs…
USMLE Step 1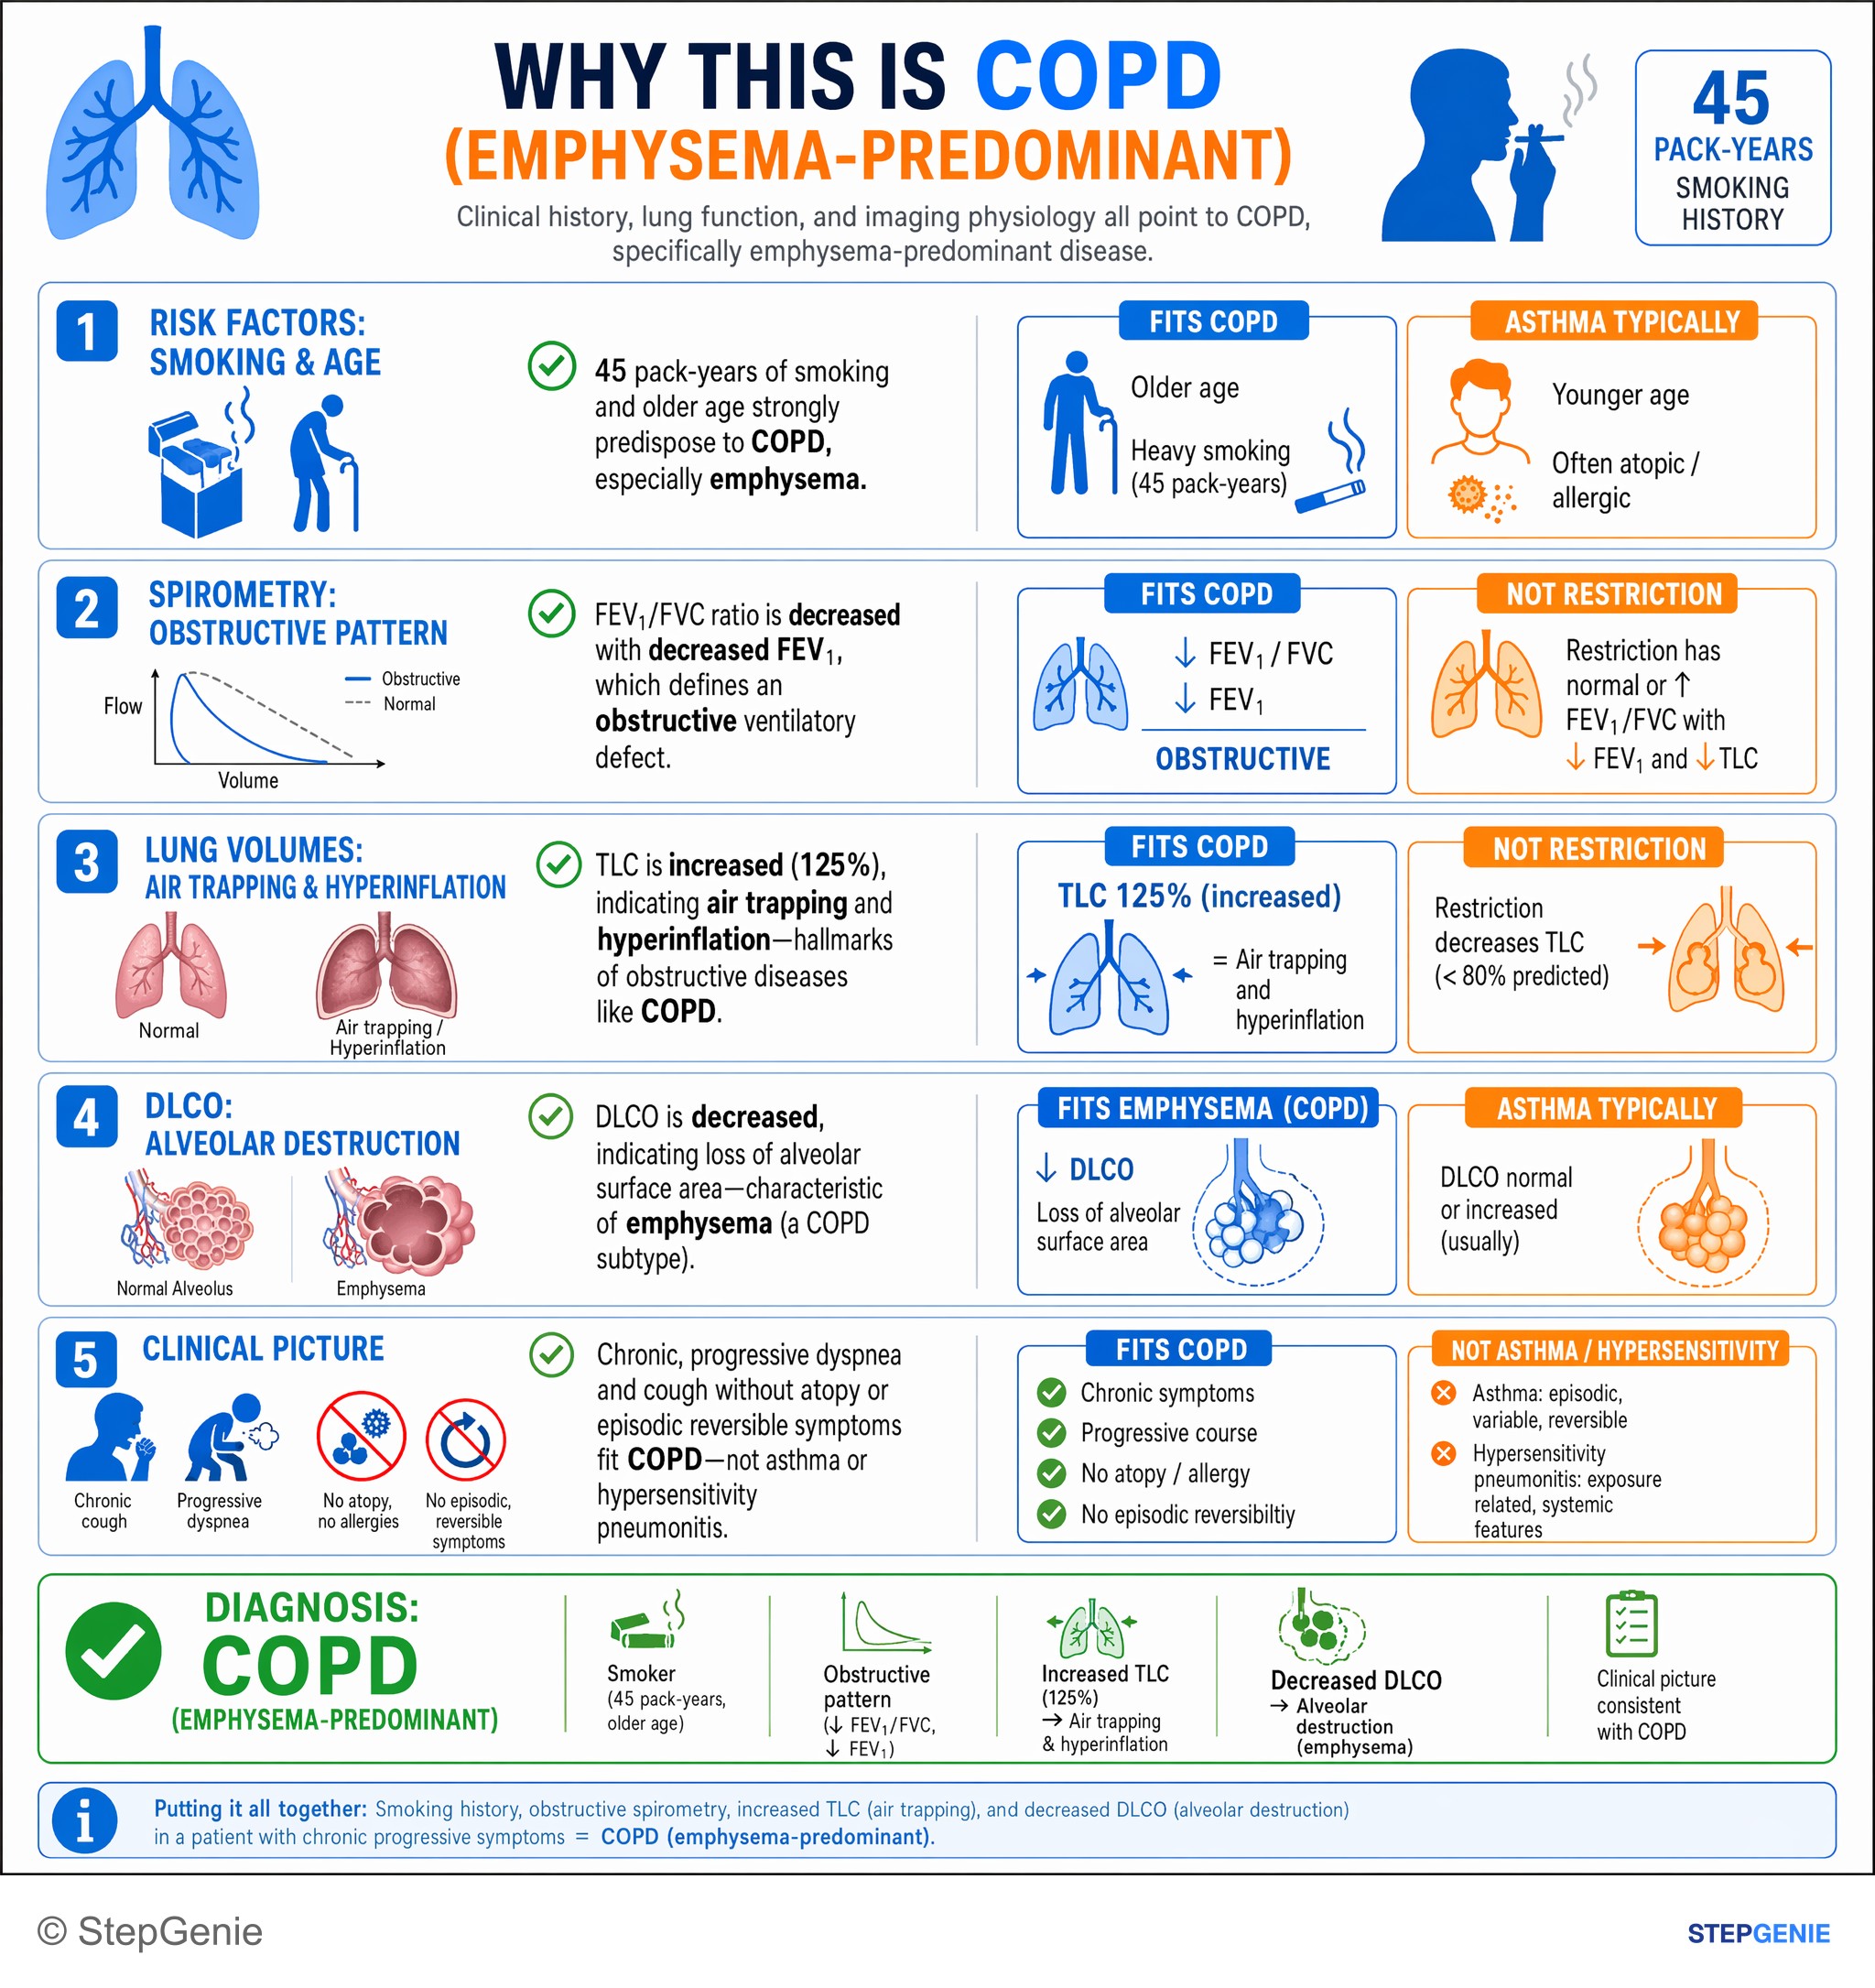
COPD (emphysema-predominant): smoker with obstructive pattern, increased TLC (air trapping), and decreased DLCO indicating parenchymal…
USMLE Step 2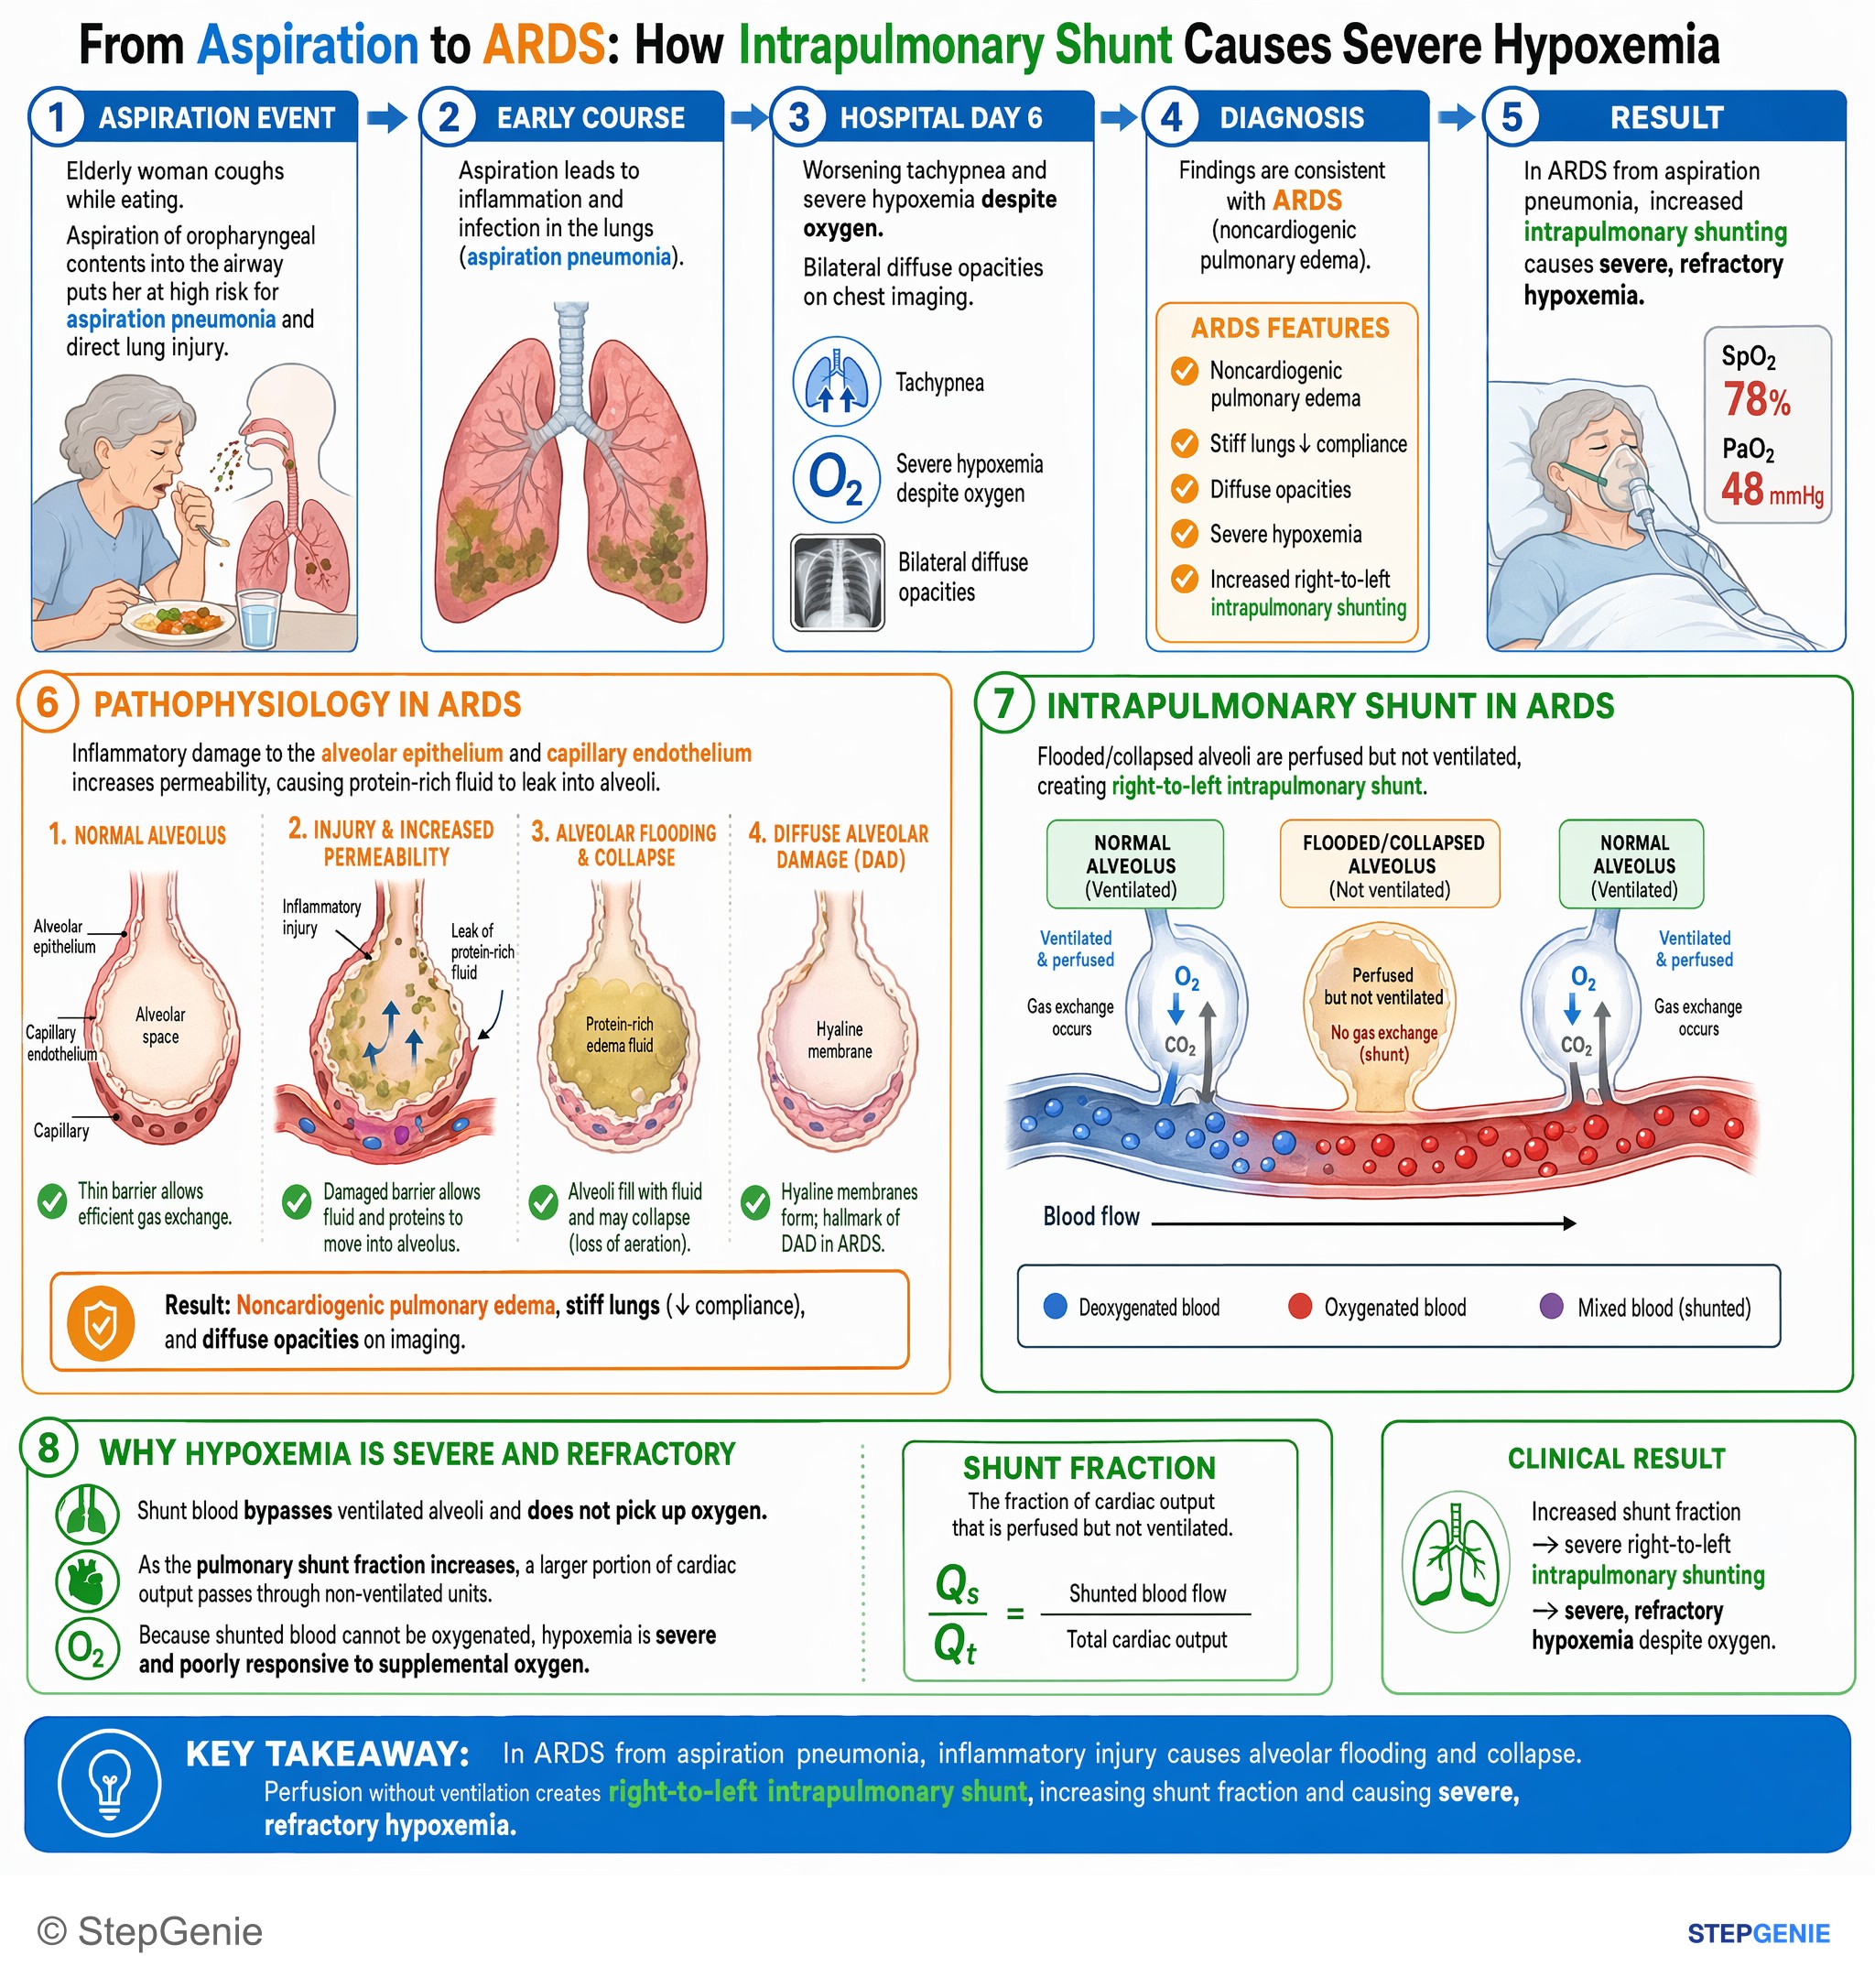
ARDS from aspiration pneumonia causes noncardiogenic pulmonary edema, stiff lungs, diffuse opacities, and severe hypoxemia due to…
USMLE Step 1Frequently Asked Questions
What is the difference between compliance and elastance?
Compliance is the change in volume per unit change in pressure (ΔV/ΔP), so it measures how easily the lung inflates. Elastance is its reciprocal (ΔP/ΔV), the pressure needed per unit of volume, so it measures stiffness and elastic recoil. They always move in opposite directions: emphysema raises compliance and lowers elastance, while pulmonary fibrosis, ARDS and neonatal respiratory distress syndrome lower compliance and raise elastance.
Is elastance the same as elasticity?
Essentially yes: elastance is how physiologists measure elasticity, as the pressure change needed per unit of volume change (ΔP/ΔV). A lung with high elastance is stiff and recoils strongly, as in pulmonary fibrosis. The trap is that "elastic" in everyday speech means stretchy, which is really compliance, so an emphysematous lung is highly compliant yet has lost its elasticity.
Does emphysema increase or decrease lung compliance?
Emphysema increases lung compliance. Destruction of alveolar walls removes elastic fibers, so the lung inflates with very little pressure but has weak elastic recoil (low elastance). That weak recoil lets small airways collapse during expiration, which traps air and raises the functional residual capacity.
How do you calculate static compliance on a ventilator?
Divide the tidal volume by the plateau pressure minus PEEP: for example, 500 mL ÷ (25 − 5) cm H₂O = 25 mL/cm H₂O. The plateau is measured during an end-inspiratory hold with no airflow, so the result reflects the elastic load of the lungs and chest wall rather than airway resistance. Dynamic compliance is measured while gas is flowing, so it also falls when airway resistance rises.
Why does surfactant increase lung compliance?
The thin fluid layer lining the alveoli has surface tension that pulls inward and adds to the lung's recoil. Surfactant, made by type II pneumocytes and composed mainly of dipalmitoylphosphatidylcholine, lowers that surface tension, so less pressure is needed for each milliliter of inflation, which is exactly what higher compliance means. Lower surface tension also reduces the collapsing pressure in small alveoli predicted by the law of Laplace (P = 2T/r).
What is normal lung compliance?
In a healthy adult, the two lungs together expand by roughly 200 mL for each 1 cm H₂O rise in transpulmonary pressure. The lungs and chest wall are stretched in series, so the whole respiratory system is less compliant than either the lungs or the chest wall measured alone. Stiff lungs in ARDS or fibrosis show up on a ventilator as a high plateau pressure for a given tidal volume.