Dead space is ventilation that takes no part in gas exchange: air in the conducting airways, or air reaching alveoli that get no blood flow (V/Q → ∞), so that part of each breath removes no CO₂. Pulmonary embolism (PE) is the classic cause. A shunt is perfusion without ventilation (V/Q = 0): blood flows past alveoli that get no air (pneumonia, ARDS, atelectasis) or bypasses them altogether (right-to-left cardiac shunts, pulmonary AVMs), so it reaches the systemic arteries still deoxygenated. The exam discriminator is 100% oxygen: shunt hypoxemia responds poorly, while hypoxemia from low-V/Q units, which accounts for most of the hypoxemia in PE, improves.
Dead space vs shunt at a glance
| Feature | Dead space | Shunt |
|---|---|---|
| Definition | Ventilated, not perfused ("wasted ventilation") | Perfused, not ventilated ("wasted blood flow") |
| V/Q ratio | Approaches infinity | Zero |
| Main problem | CO₂ removal: minute ventilation must rise | O₂ uptake: hypoxemia |
| Response to 100% O₂ | Hypoxemia, mostly from coexisting low-V/Q units, usually improves | PaO₂ rises little, and less as the shunt grows |
| A–a gradient | Often widened, but by the accompanying V/Q mismatch | Widened |
| PaCO₂ | Normal or low if ventilation can rise; high if it cannot | Usually normal or low |
| Capnography | End-tidal CO₂ falls; the PaCO₂–EtCO₂ gap widens | Not the key clue |
| Classic causes | PE, emphysema, sudden fall in cardiac output or blood pressure, excessive PEEP | Pneumonia, ARDS, atelectasis, pulmonary edema, right-to-left cardiac shunt, pulmonary AVM |
| What fixes it | Treat the cause (anticoagulation for PE, thrombolysis if unstable; restore cardiac output; avoid excess PEEP) | Reopen alveoli (treat the cause, PEEP, prone positioning when PaO₂/FiO₂ stays below 150); embolize a pulmonary AVM |
Types of dead space and shunt
| Type | What it is | Size or examples |
|---|---|---|
| Anatomic dead space | Gas in the conducting airways (nose to terminal bronchioles) | About 150 mL: roughly 2 mL/kg, or a third of a 500 mL breath |
| Alveolar dead space | Ventilated alveoli with no blood flow | Negligible in health; PE, low cardiac output or blood pressure, emphysema, overdistending PEEP |
| Physiologic dead space | Anatomic plus alveolar | Dead space fraction (VD/VT) about 0.3 in health |
| Anatomic shunt | Blood that bypasses the alveoli | Tetralogy of Fallot; Eisenmenger reversal of an ASD, VSD or PDA; patent foramen ovale when right atrial pressure exceeds left (large PE); pulmonary AVMs, often from hereditary hemorrhagic telangiectasia (HHT) |
| Intrapulmonary shunt | Blood passing alveoli that are filled or collapsed | Pneumonia, ARDS, pulmonary edema, atelectasis (mucus plug, foreign body) |
| Normal shunt | Bronchial veins into pulmonary veins; thebesian veins into the left ventricle | About 2–3% of cardiac output |
Physiologic dead space vs physiologic shunt. They are mirror images: physiologic dead space (anatomic plus alveolar) is wasted ventilation, measured from PaCO₂ and expired CO₂; shunt is wasted blood flow, measured from O₂ contents on 100% O₂. "Physiologic shunt" is used in two ways: for blood flowing past unventilated alveoli, as opposed to an anatomic shunt that bypasses them, and for the normal shunt of a few percent of cardiac output from bronchial and thebesian veins, or the whole shunt fraction calculated with the shunt equation. A shunt fraction calculated on room air also counts low-V/Q units, so it is better called venous admixture.
The V/Q spectrum from zero to infinity
The ventilation–perfusion ratio compares alveolar ventilation with capillary blood flow; for the whole lung it is about 0.8 (roughly 4 L/min of alveolar ventilation for 5 L/min of blood flow).
| V/Q | Unit | What leaves the unit | Typical setting |
|---|---|---|---|
| 0 | Shunt | Blood at mixed venous values (PO₂ about 40 mm Hg) | Lobar pneumonia, ARDS, atelectasis |
| Low | Low-V/Q unit | Blood with low PO₂ and high PCO₂ | Asthma, chronic bronchitis, over-perfused lung in PE |
| High | High-V/Q unit | Little blood, with high PO₂ and low PCO₂ | Emphysema, lung apex |
| Infinity | Alveolar dead space | No blood; gas stays at inspired values (PO₂ about 150, PCO₂ near 0) | Segment beyond an embolus |
In the upright lung, ventilation and perfusion both increase toward the base, but perfusion increases more, so V/Q is highest at the apex. Hypoxic pulmonary vasoconstriction, unique to the pulmonary circulation, diverts blood from poorly ventilated alveoli; supplemental O₂ can release it.
Why 100% oxygen cannot fix a shunt
Three facts explain why shunt hypoxemia resists oxygen:
- Shunted blood never meets the extra oxygen. It leaves the lung at mixed venous O₂ content however high the FiO₂.
- Blood from ventilated alveoli is already nearly saturated. Alveolar PO₂ rises from about 100 to 663 mm Hg, but on the flat top of the oxygen–hemoglobin dissociation curve that blood gains only a little O₂, mostly dissolved (0.003 mL/dL per mm Hg).
- Low-V/Q units are still ventilated. More O₂ raises their alveolar PO₂ too, so hypoxemia from asthma, COPD or PE improves.
Worked example: a 30% shunt. Hemoglobin is 15 g/dL (1.34 × 15 = 20.1 mL O₂/dL when fully saturated); mixed venous blood is 75% saturated at PO₂ 40 mm Hg (1.34 × 15 × 0.75 + 0.003 × 40 ≈ 15.2 mL/dL).
| O₂ content (mL/dL) | Room air | 100% O₂ |
|---|---|---|
| Blood from ventilated units (70%) | 98% saturated, PO₂ 100: 19.7 + 0.3 = 20.0 | Fully saturated, PO₂ 663: 20.1 + 2.0 = 22.1 |
| Shunted blood (30%) | 15.2 | 15.2 |
| Mixed arterial blood | 0.7 × 20.0 + 0.3 × 15.2 ≈ 18.6 | 0.7 × 22.1 + 0.3 × 15.2 ≈ 20.0 |
Arterial content rises only from about 18.6 to 20.0 mL/dL, still short of full saturation: on a standard dissociation curve, and assuming mixed venous content stays at 15.2, PaO₂ goes from roughly 60 to roughly 100 mm Hg, even though alveolar PO₂ in the ventilated units has risen to 663. Rearranged, the same mixing gives the shunt equation:
(Cc = end-capillary, Ca = arterial, Cv = mixed venous O₂ content.) A normal right-to-left shunt is under 5% of cardiac output; in ARDS, pneumonia and atelectasis it can exceed 50%, when even an FiO₂ of 1.0 does little.
- Hyperoxia test: after 10 minutes of 100% O₂, newborns with cyanotic heart disease usually cannot raise PaO₂ above about 100 mm Hg; with lung disease it generally rises further.
- Caveat: 100% O₂ can itself add shunt through absorption atelectasis of poorly ventilated units.
A–a gradient by mechanism
The A–a gradient (alveolar minus arterial PO₂) is normal when too little O₂ reaches the alveoli and widened when O₂ fails to get from alveoli into arterial blood:
On room air the gradient is under 10 mm Hg in young adults and rises with age (StatPearls estimates (age + 10)/4; another chapter uses age/4 + 4). It widens by about 5–7 mm Hg per 10% rise in FiO₂, so age-based normals apply only on room air.
| Mechanism | PaCO₂ | A–a gradient | 100% O₂ | Example |
|---|---|---|---|---|
| Low inspired PO₂ | Normal or low | Normal | Corrects | High altitude |
| Hypoventilation | High | Normal | Corrects | Opioid overdose, neuromuscular weakness |
| Low V/Q | Normal or low; high in severe COPD | Widened | Corrects | Asthma, COPD, PE |
| Diffusion limitation | Normal | Widened | Corrects, sometimes needing a high FiO₂; worse on exercise | Interstitial lung disease |
| Shunt | Normal or low | Widened | Little rise | ARDS, lobar pneumonia, atelectasis, right-to-left cardiac shunt |
Where dead space fits: a unit with no blood flow cannot desaturate blood. In PE, the gradient widens because blood diverted into over-perfused lung creates low-V/Q units and mixed venous PO₂ falls with cardiac output.
Bohr and Enghoff equations: measuring dead space
Dead-space gas contains essentially no CO₂, so it dilutes what the perfused alveoli exhale:
Bohr's original equation used mean alveolar PCO₂; Enghoff substituted arterial PCO₂, and this version (which StatPearls also calls the Bohr equation) gives physiologic dead space. Mnemonic: "Taco, Paco, Peco, Paco."
- Healthy adult: VT 500 mL, PaCO₂ 40, mixed expired PCO₂ 28 mm Hg. VD/VT = (40 − 28)/40 = 0.30, so VD = 150 mL. At 12 breaths/min, minute ventilation is 6.0 L/min and alveolar ventilation (500 − 150) × 12 = 4.2 L/min.
- Acute PE: VT 500 mL at 22 breaths/min, PaCO₂ 30, mixed expired PCO₂ 15 mm Hg. VD/VT = (30 − 15)/30 = 0.50, so VD = 250 mL. Of 11.0 L/min of minute ventilation, only (500 − 250) × 22 = 5.5 L/min reaches perfused alveoli; the patient holds PaCO₂ at 30 only by nearly doubling minute ventilation.
- Shunt inflates the Enghoff number: shunted blood lifts PaCO₂ above alveolar PCO₂, so in ARDS a high VD/VT reflects shunt and V/Q heterogeneity more than unperfused alveoli.
PaCO₂: dead space costs ventilation; shunt rarely raises CO₂
PaCO₂ is proportional to CO₂ production divided by alveolar ventilation, which equals minute ventilation × (1 − VD/VT). At constant CO₂ production, holding alveolar ventilation at 4.2 L/min takes 4.2/0.7 = 6.0 L/min of minute ventilation when VD/VT is 0.3, but 4.2/0.5 = 8.4 L/min when it is 0.5.
- More dead space usually means harder breathing, not hypercapnia. PaCO₂ climbs when ventilation cannot keep up: muscle fatigue, severe COPD, low tidal volumes on a ventilator.
- Rapid shallow breathing wastes more of each breath. At the same 7.5 L/min, 500 mL × 15 gives (500 − 150) × 15 = 5.25 L/min of alveolar ventilation; 250 mL × 30 gives only (250 − 150) × 30 = 3.0 L/min.
- Shunt rarely raises PaCO₂. Chemoreceptors drive extra ventilation of normal units, so PaCO₂ is usually normal or low; one review notes that hypercapnia is uncommon until the shunt reaches about 50%.
For reading the full blood gas, see how to approach acid–base questions.
Disease by disease
| Condition | Main mechanism | Response to O₂ | Clue |
|---|---|---|---|
| Pulmonary embolism | Dead space where vessels are occluded; hypoxemia mainly from low V/Q elsewhere and low mixed venous PO₂ (inert-gas data), little shunt | Usually improves | Acute dyspnea, tachycardia, hypocapnia, clear chest x-ray |
| Emphysema | High-V/Q units from capillary loss add dead space; hypoxemia, often mild, comes from V/Q mismatch, with little shunt | Improves | Hyperinflation; hypercapnia when severe |
| Lobar pneumonia | Shunt through filled alveoli | Poor if the shunt is large | Consolidation |
| ARDS | Shunt through flooded, collapsed alveoli, plus high dead space | Poor; improves with PEEP | Bilateral opacities, refractory hypoxemia |
| Atelectasis, mucus plug, foreign body | Shunt through collapsed alveoli | Poor until re-expanded | Common after general anesthesia |
| Right-to-left cardiac shunt | Anatomic shunt (tetralogy of Fallot, Eisenmenger syndrome) | Poor | Cyanosis, clubbing, erythrocytosis |
| Pulmonary AVM | Anatomic intrapulmonary shunt; found in 30–50% of people with HHT | Poor | Epistaxis, stroke or brain abscess from paradoxical embolism |
| Hepatopulmonary syndrome | Dilated intrapulmonary vessels: V/Q mismatch, impaired diffusion, some true shunt | Improves with diffuse precapillary dilatation (type I), poorly with larger arteriovenous channels (type II) | Liver disease, platypnea–orthodeoxia |
- Hepatopulmonary syndrome: liver disease or portal hypertension, an A–a gradient of at least 15 mm Hg on room air (above 20 after age 64) or PaO₂ below 80, and intrapulmonary vascular dilatation: contrast bubbles reach the left atrium on the fourth to sixth cardiac cycle (before the third suggests an intracardiac shunt). Orthodeoxia is a fall in PaO₂ of more than 5% or 4 mm Hg on moving upright. Liver transplantation is the only established treatment with a long-term survival benefit.
Ventilator and bedside pearls
- PEEP cuts both ways. It recruits collapsed alveoli and shrinks shunt, but too much overdistends alveoli, cuts their perfusion (more dead space) and lowers venous return. For the mechanics, see compliance vs elastance.
- Proning improves V/Q matching and reduces shunt. The 2017 ATS/ESICM/SCCM guideline strongly recommends it for more than 12 hours a day in severe ARDS; the 2023 ESICM guideline recommends sessions of 16 hours or more whenever PaO₂/FiO₂ stays below 150 on PEEP of at least 5 cm H₂O (Merck: moderate to severe ARDS). That threshold comes from PROSEVA, which called it "severe ARDS" even though the Berlin and 2024 global definitions grade a PaO₂/FiO₂ of 100–200 as moderate; in PROSEVA, 28-day mortality fell from 32.8% to 16.0%.
- Dead space predicts death in ARDS: in 179 intubated patients, the early dead space fraction averaged 0.58, and each 0.05 increase raised the odds of death by 45%.
- Capnography tracks dead space. The PaCO₂–EtCO₂ gap, normally about 3–5 mm Hg, widens as dead space rises. A sudden fall in end-tidal CO₂ signals less pulmonary blood flow (PE, severe hypotension, cardiac arrest) or a circuit or airway problem; during CPR, an abrupt rise suggests return of spontaneous circulation.
Classic exam traps
- PE is the "dead space" disease, but its hypoxemia comes mainly from low V/Q, so O₂ helps; the typical ABG shows hypocapnia, respiratory alkalosis and a widened A–a gradient.
- A normal A–a gradient does not exclude PE: in PIOPED, 11–14% of patients with angiographically proven PE had a gradient of 20 mm Hg or less.
- ARDS is the classic shunt, but it also raises dead space.
- A blocked bronchus causes shunt; narrowed airways cause low V/Q. A mucus plug or aspirated foreign body can collapse the lung beyond it (V/Q = 0); in asthma, narrowed airways still pass some air and collateral ventilation makes shunt uncommon, so O₂ helps.
Worked examples
Vignette 1. Five days after hip replacement, a 58-year-old woman develops sudden dyspnea and tachycardia. On room air: pH 7.48, PaCO₂ 30 mm Hg, PaO₂ 62 mm Hg; the chest x-ray is clear and end-tidal CO₂ is 18 mm Hg. On FiO₂ 0.5, PaO₂ rises to 160 mm Hg. What explains the low end-tidal CO₂?
Answer: Increased alveolar dead space from pulmonary embolism.
Reasoning: Ventilated but unperfused alveoli exhale CO₂-free gas that dilutes end-tidal CO₂, widening the PaCO₂–EtCO₂ gap to 12 mm Hg. Alveolar PO₂ is 0.21 × 713 − 30/0.8 ≈ 112 mm Hg, so the A–a gradient is about 50 mm Hg, far above the (58 + 10)/4 = 17 expected for her age. The brisk rise on oxygen points to low-V/Q units, not shunt.
Vignette 2. A 45-year-old man with severe pneumonia is intubated, and imaging shows bilateral opacities. On PEEP 8 cm H₂O and FiO₂ 0.6, PaO₂ is 64 mm Hg; FiO₂ 1.0 brings it only to 72 mm Hg. What is the mechanism, and what helps?
Answer: Intrapulmonary shunt through flooded and collapsed alveoli, as in ARDS: reopen alveoli with higher PEEP and, since PaO₂/FiO₂ is well below 150 (64/0.6 ≈ 107), prone positioning, rather than relying on more oxygen.
Reasoning: A 40-point rise in FiO₂ added only 8 mm Hg of PaO₂, the signature of shunt: blood crossing unventilated alveoli never sees the extra oxygen.
Key takeaways
- Dead space = ventilation without perfusion (V/Q → ∞; PE, emphysema, low cardiac output); shunt = perfusion without ventilation (V/Q = 0; pneumonia, ARDS, atelectasis, right-to-left shunts, pulmonary AVMs).
- Shunt hypoxemia responds poorly to 100% O₂; low V/Q, diffusion limitation, hypoventilation and low inspired PO₂ all respond.
- Dead space mainly costs ventilation: minute ventilation rises and end-tidal CO₂ falls; PaCO₂ rises only if breathing can't keep up.
More respiratory physiology lives on the pulmonology topic hub.
Sources
- Physiology, Lung Dead Space (StatPearls, NCBI Bookshelf)
- Anatomy, Anatomic Dead Space (StatPearls, NCBI Bookshelf)
- Hypoxia and Hypoxemia (StatPearls, NCBI Bookshelf)
- Alveolar Gas Equation (StatPearls, NCBI Bookshelf)
- Arterial Blood Gas Analysis (StatPearls, NCBI Bookshelf)
- Capnography (StatPearls, NCBI Bookshelf)
- Physiology, Oxygen Transport (StatPearls, NCBI Bookshelf)
- Acute Pulmonary Embolism (StatPearls, NCBI Bookshelf)
- Hepatopulmonary Syndrome (StatPearls, NCBI Bookshelf)
- Pulmonary Arteriovenous Malformation (StatPearls, NCBI Bookshelf)
- Eisenmenger Syndrome (StatPearls, NCBI Bookshelf)
- Cyanotic Heart Disease (StatPearls, NCBI Bookshelf)
- Atelectasis (StatPearls, NCBI Bookshelf)
- Positive End-Expiratory Pressure (StatPearls, NCBI Bookshelf)
- Oxygen Therapy (StatPearls, NCBI Bookshelf)
- Acute Hypoxemic Respiratory Failure (AHRF), Including Acute Respiratory Distress Syndrome (ARDS) — Merck Manual Professional Edition
- Petersson J, Glenny RW. Gas exchange and ventilation–perfusion relationships in the lung. Eur Respir J. 2014 (PubMed)
- Robertson HT. Dead space: the physiology of wasted ventilation. Eur Respir J. 2015 (PubMed)
- Sarkar M, et al. Mechanisms of hypoxemia. Lung India. 2017 (PMC)
- Santolicandro A, et al. Mechanisms of hypoxemia and hypocapnia in pulmonary embolism. Am J Respir Crit Care Med. 1995 (PubMed)
- Stein PD, et al. Alveolar-arterial oxygen gradient in the assessment of acute pulmonary embolism. Chest. 1995 (PubMed)
- Nuckton TJ, et al. Pulmonary dead-space fraction as a risk factor for death in the acute respiratory distress syndrome. N Engl J Med. 2002 (PubMed)
- Fan E, et al. An Official ATS/ESICM/SCCM Clinical Practice Guideline: Mechanical Ventilation in Adult Patients with ARDS. Am J Respir Crit Care Med. 2017 (PubMed)
- Guérin C, et al. Prone positioning in severe acute respiratory distress syndrome. N Engl J Med. 2013 (PubMed)
- Grasselli G, et al. ESICM guidelines on acute respiratory distress syndrome: definition, phenotyping and respiratory support strategies. Intensive Care Med. 2023 (PMC)
- Matthay MA, et al. A New Global Definition of Acute Respiratory Distress Syndrome. Am J Respir Crit Care Med. 2024 (PMC)
- Partial Pressure of Oxygen (StatPearls, NCBI Bookshelf)
- Platypnea (StatPearls, NCBI Bookshelf)
- Chronic Obstructive Pulmonary Disease (COPD) (StatPearls, NCBI Bookshelf)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
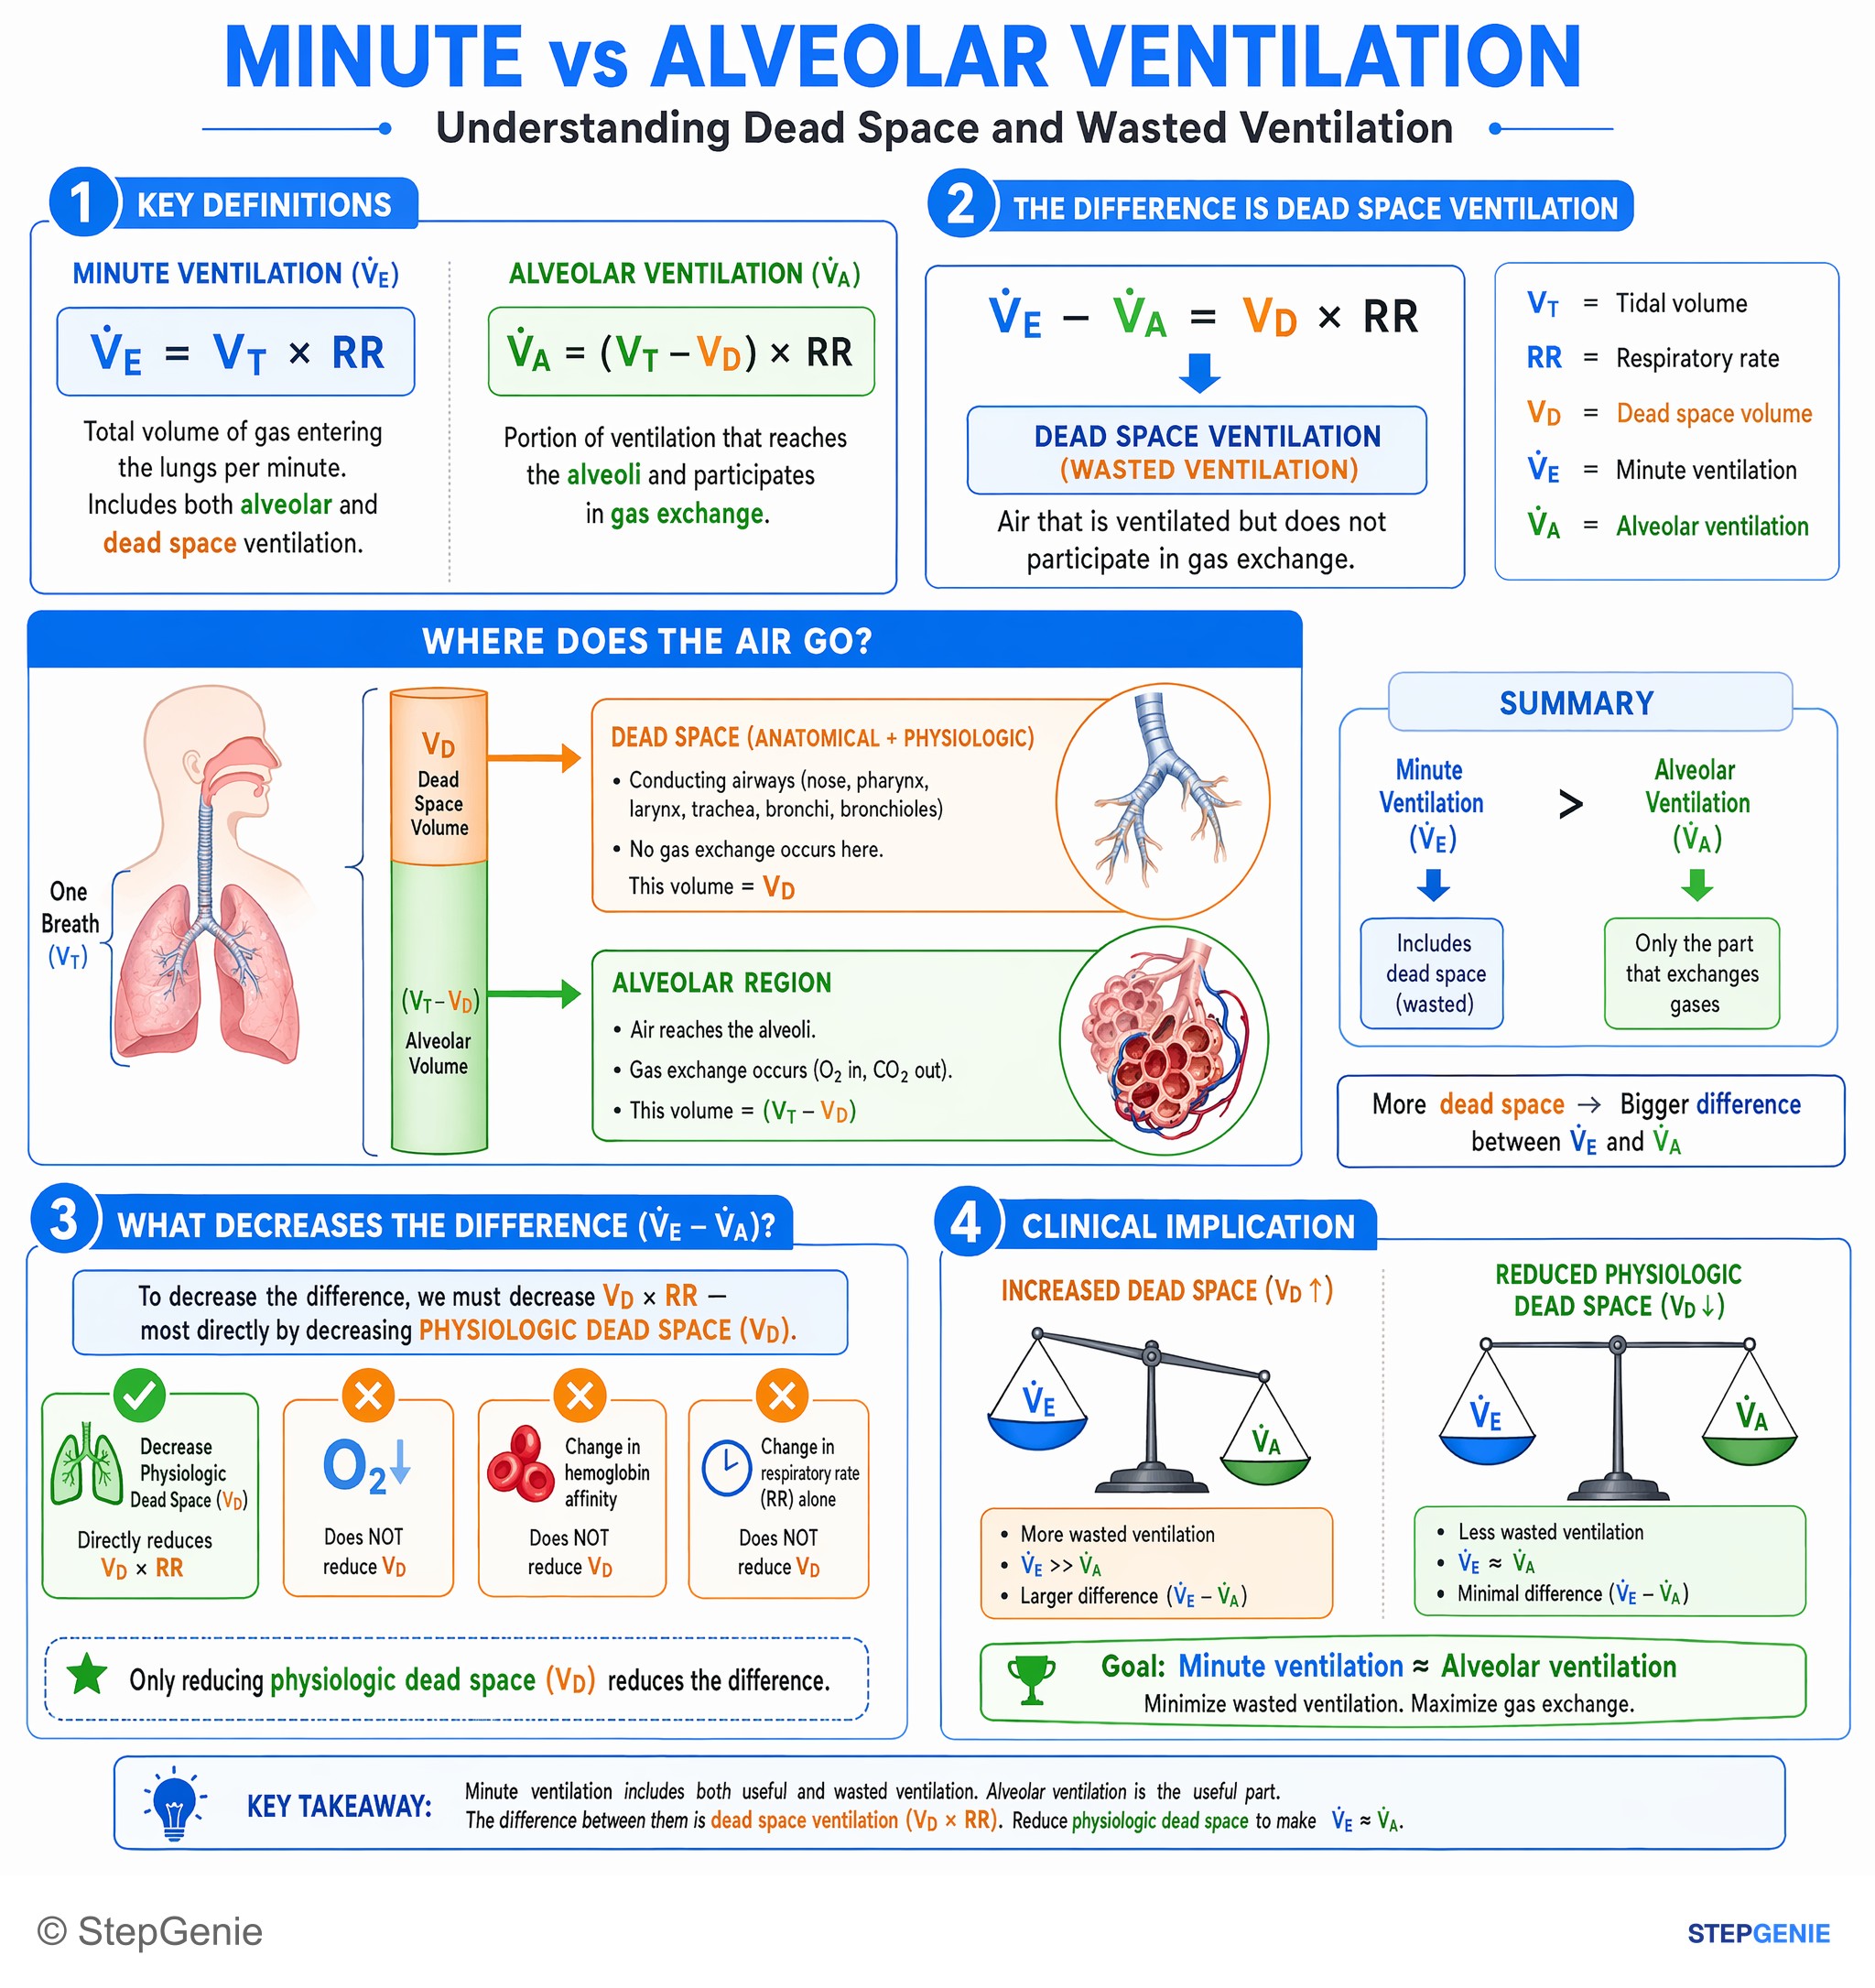
Increased dead space means more wasted ventilation; reducing physiologic dead space makes minute ventilation ≈ alveolar ventilation…
USMLE Step 1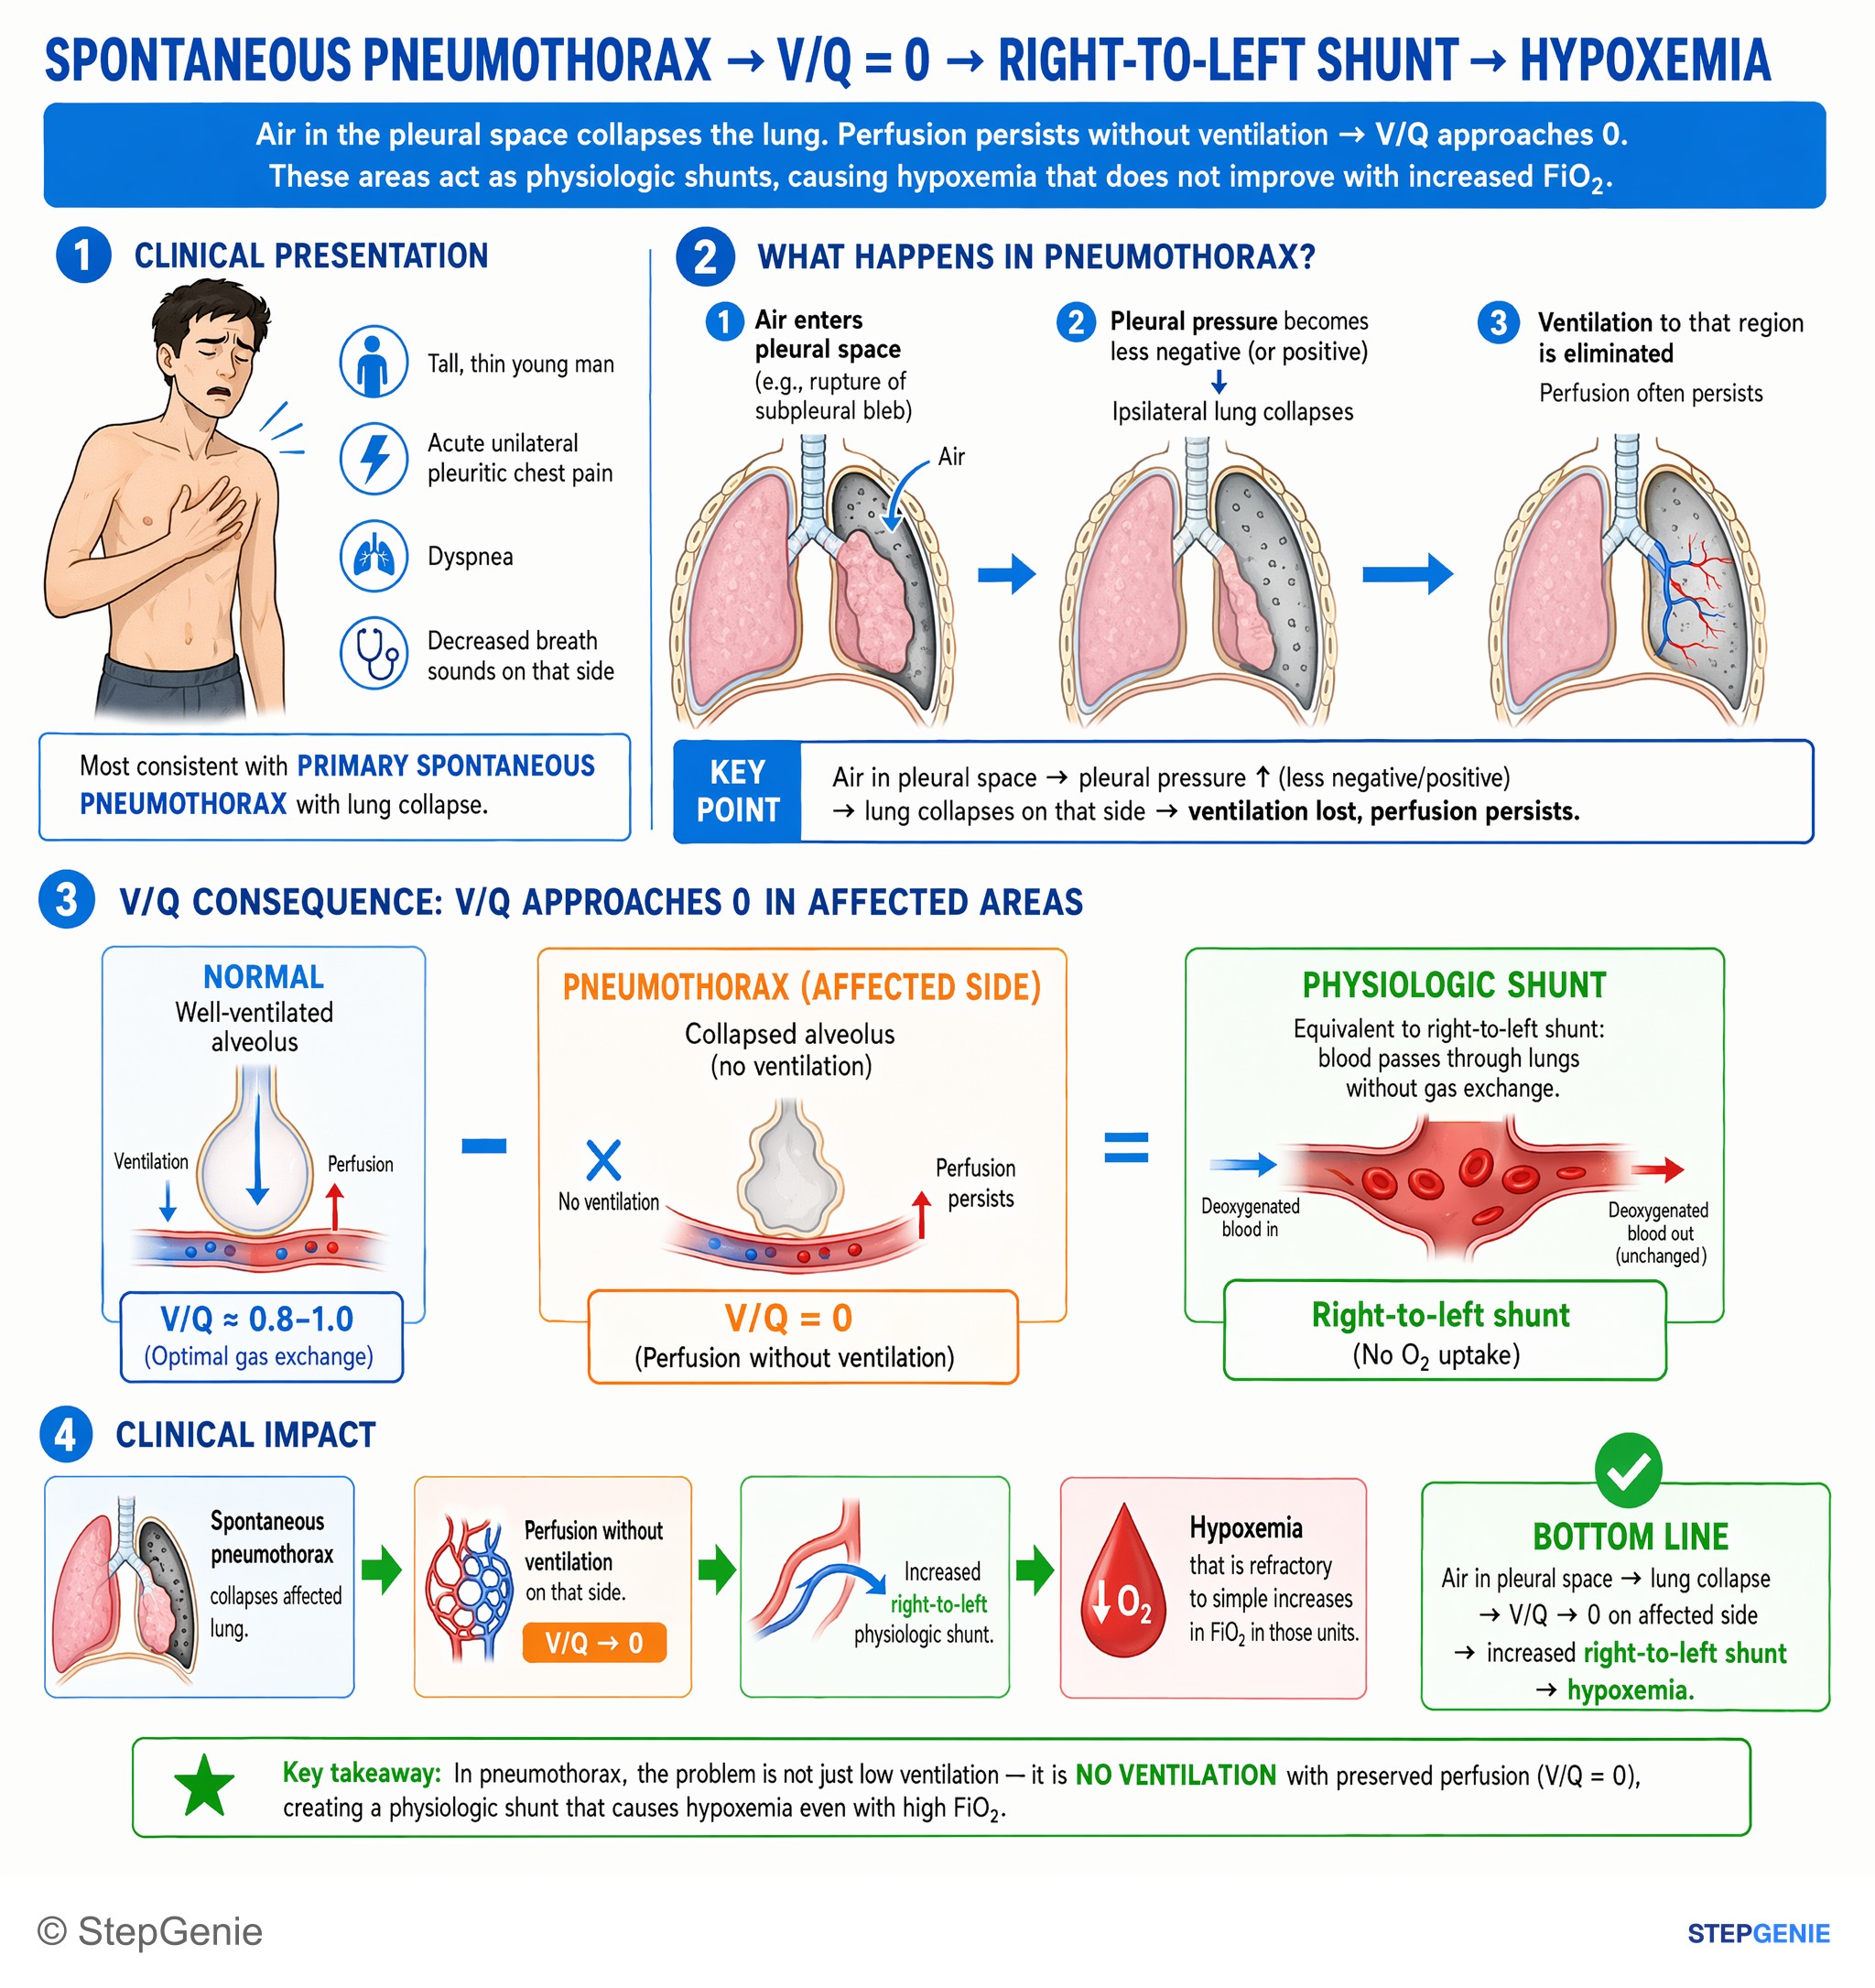
Spontaneous pneumothorax collapses affected lung, perfusion without ventilation → V/Q → 0 on that side → increased right-to-left…
USMLE Step 1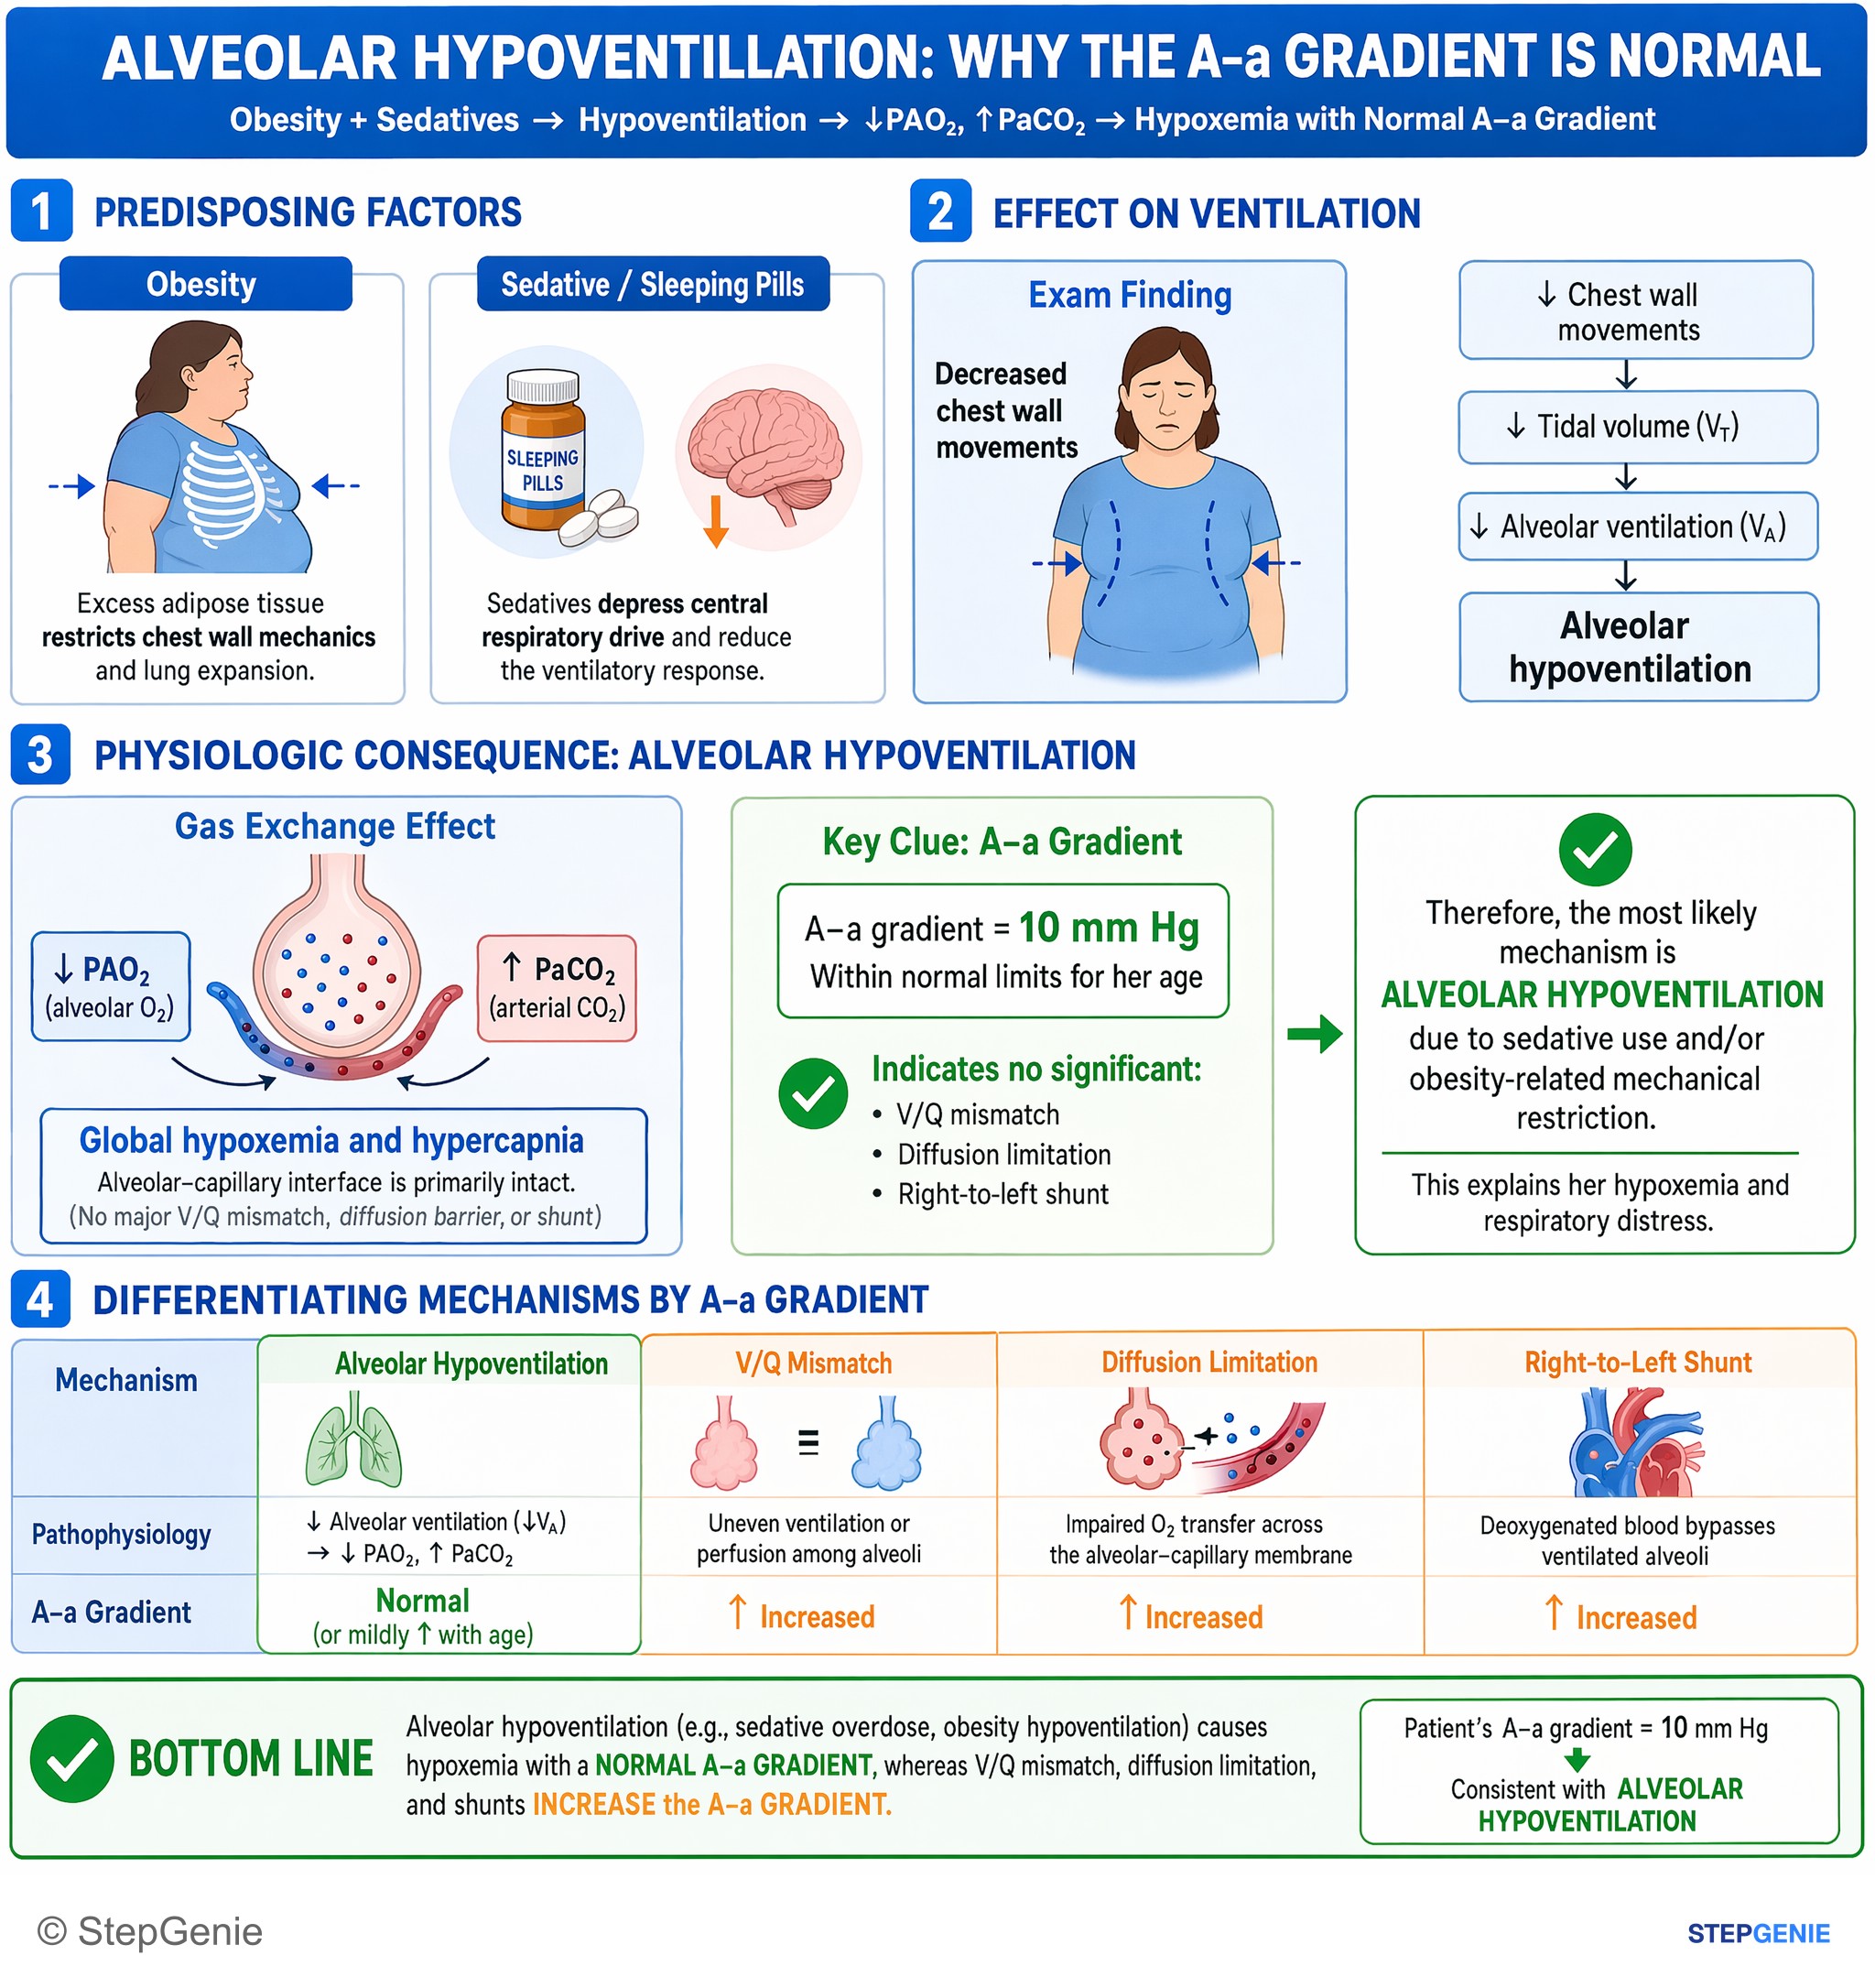
Alveolar hypoventilation (e.g., sedative overdose, obesity hypoventilation) causes hypoxemia with a normal A–a gradient; V/Q mismatch and…
USMLE Step 1Frequently Asked Questions
What is the difference between dead space and shunt?
Dead space is ventilation without perfusion: air in the conducting airways, or in alveoli with no blood flow, takes no part in gas exchange, so its V/Q ratio approaches infinity and the main cost is CO₂ removal. A shunt is perfusion without ventilation: blood passes unventilated alveoli or bypasses them, so V/Q is zero and the result is hypoxemia that responds poorly to supplemental oxygen. Pulmonary embolism is the classic dead-space disease; pneumonia and ARDS are classic shunts.
What is the difference between physiological shunt and physiological dead space?
Physiologic dead space is wasted ventilation: anatomic dead space in the conducting airways plus alveolar dead space in ventilated but unperfused alveoli. In health it is about 30% of each breath, and it is measured from arterial and mixed expired CO₂ with the Bohr–Enghoff equation. A physiologic shunt is wasted blood flow, but the term is used in two ways: blood flowing through alveoli that are perfused but not ventilated, as in pneumonia, atelectasis or ARDS, as opposed to an anatomic shunt that bypasses the alveoli; or the shunt fraction calculated with the shunt equation, which in health is a few percent of cardiac output from bronchial and thebesian veins.
Why doesn't 100% oxygen correct hypoxemia caused by a shunt?
Shunted blood never meets ventilated alveoli, so extra inspired oxygen cannot reach it, and it leaves the lungs at mixed venous oxygen content. Blood from ventilated alveoli is already nearly saturated, so it can carry only a little more oxygen, mostly dissolved. When the two streams mix, arterial PO₂ stays low, and the larger the shunt, the smaller the rise. Low-V/Q units still receive some fresh gas, so hypoxemia from V/Q mismatch improves with oxygen.
Is a pulmonary embolism dead space or shunt?
A pulmonary embolism creates alveolar dead space: ventilated lung beyond the clot loses its blood flow, which lowers end-tidal CO₂ and widens the gap between arterial and end-tidal CO₂. Its hypoxemia, however, comes mainly from V/Q mismatch, as blood diverted to the remaining lung creates low-V/Q units, plus a low mixed venous oxygen level. That is why PE hypoxemia usually improves with supplemental oxygen. A large PE can add a true shunt through a patent foramen ovale.
Is ARDS a shunt or a dead space problem?
Both, but shunt drives the hypoxemia. Flooded and collapsed alveoli stay perfused, so blood crosses them without picking up oxygen; the hypoxemia responds poorly to extra oxygen but improves when PEEP or prone positioning reopens alveoli. ARDS also raises the dead space fraction, partly through shunt and V/Q heterogeneity. In one study of 179 intubated patients, each 0.05 rise in the early dead space fraction raised the odds of death by 45%.
How do you calculate physiologic dead space with the Bohr equation?
Use VD/VT = (PaCO₂ − PECO₂)/PaCO₂, where PECO₂ is the PCO₂ of mixed expired gas; this arterial form is Enghoff's modification of Bohr's equation. With a tidal volume of 500 mL, a PaCO₂ of 40 mm Hg and a mixed expired PCO₂ of 28 mm Hg, VD/VT is (40 − 28)/40 = 0.30, so dead space is 150 mL, about the normal anatomic value. Higher values point to more alveolar dead space or V/Q mismatch, and shunt raises the result too.