Acute respiratory distress syndrome (ARDS) is an acute, diffuse, inflammatory lung injury that makes the alveolar-capillary barrier leak, flooding the alveoli with protein-rich, noncardiogenic edema. The Berlin definition requires onset within 1 week of a known insult, bilateral opacities not explained by effusions, collapse or nodules, respiratory failure not fully explained by heart failure or fluid overload, and a PaO2/FiO2 of 300 mm Hg or less on PEEP or CPAP of at least 5 cm H2O; the 2024 global definition keeps that core and adds high-flow oxygen, SpO2/FiO2 and lung ultrasound. The histology is diffuse alveolar damage with hyaline membranes, the physiology is shunt plus stiff lungs, and survival improves with low tidal volume ventilation (6 mL/kg predicted body weight, plateau pressure below 30 cm H2O) and prone positioning for more than 12 hours a day in severe ARDS.
ARDS definition: Berlin (2012) vs the 2024 global definition
| Criterion | Berlin definition (2012) | Global definition (2024) |
|---|---|---|
| Timing | Within 1 week of a known insult or new or worsening respiratory symptoms | Unchanged |
| Imaging | Bilateral opacities on chest x-ray or CT, not fully explained by effusions, lobar or lung collapse, or nodules | Same, or bilateral B lines and/or consolidations on lung ultrasound by a trained operator |
| Origin of edema | Not fully explained by heart failure or fluid overload; echocardiography if no risk factor is present | Triggered by a risk factor; not primarily cardiogenic edema, fluid overload or atelectasis, though ARDS can coexist with them |
| Oxygenation | PaO2/FiO2 ≤ 300 mm Hg on PEEP ≥ 5 cm H2O (CPAP ≥ 5 allowed for mild) | Intubated: same bands (PEEP ≥ 5) or SpO2/FiO2 equivalents. New nonintubated category: PaO2/FiO2 ≤ 300 or SpO2/FiO2 ≤ 315 on high-flow nasal oxygen ≥ 30 L/min or NIV/CPAP ≥ 5 cm H2O |
| Low-resource settings | Not covered | SpO2/FiO2 ≤ 315 with no PEEP or oxygen-flow requirement |
Severity bands (intubated patients; the PaO2/FiO2 cutoffs are the same in both definitions, and SpO2/FiO2 counts only when SpO2 is 97% or less, because the top of the oxygen-hemoglobin curve is flat):
| Severity | PaO2/FiO2 (mm Hg) | SpO2/FiO2 equivalent (global definition) |
|---|---|---|
| Mild | > 200 to ≤ 300 | > 235 to ≤ 315 |
| Moderate | > 100 to ≤ 200 | > 148 to ≤ 235 |
| Severe | ≤ 100 | ≤ 148 |
P/F ratio: . A PaO2 of 60 mm Hg on FiO2 0.5 gives 120: moderate ARDS if PEEP is at least 5 cm H2O. A PaO2 of 90 mm Hg on room air (FiO2 0.21) gives about 430.
Wedge pressure trap: the older American-European consensus definition required a pulmonary artery wedge pressure below about 18 mm Hg when it was measured. Berlin dropped it: pulmonary artery catheters are now rarely used (a large trial showed no benefit), and ARDS can coexist with high filling pressures. On exams, a normal wedge pressure still argues against cardiogenic edema.
Pathophysiology: leaky barrier to refractory hypoxemia
Insult → cytokines activate alveolar macrophages and recruit neutrophils → proteases, oxidants, leukotrienes and platelet-activating factor injure capillary endothelium and alveolar epithelium → protein-rich fluid and debris flood the airspaces → surfactant disruption and collapse, mostly in dependent lung zones → shunt, V/Q mismatch and pulmonary hypertension.
- Refractory hypoxemia = shunt. Flooded or collapsed alveoli admit no inspired gas, so blood crossing them stays at mixed venous oxygen content however high the FiO2. The A-a gradient widens and extra oxygen helps far less than in V/Q mismatch; see dead space vs shunt.
- Dead space rises too, impairing CO2 excretion and driving up minute ventilation. Higher dead space and lower compliance each independently predict death.
- Stiff, small lungs. Aerated lung shrinks to a "baby lung," so compliance falls (compliance vs elastance) and a normal-sized breath overdistends what is left.
- PEEP recruits collapsed alveoli and enlarges the aerated lung, so the FiO2 can come down.
Histology: diffuse alveolar damage and hyaline membranes
| Phase | Timing | Findings |
|---|---|---|
| Exudative | About the first 7 days | Interstitial and alveolar edema; hyaline membranes (eosinophilic, fibrin-rich layers lining alveoli, formed as leaked plasma protein polymerizes); neutrophils, hemorrhage, patchy atelectasis |
| Proliferative (fibroproliferative) | After the first week; can last more than 3 weeks in survivors | Type II pneumocyte hyperplasia re-lining the alveoli, fibroblast proliferation, interstitial fibrosis in some |
- "Diffuse alveolar damage with hyaline membranes" is the Step 1 phrase, but it is not required for diagnosis and is not always present in patients who meet the clinical criteria.
- Trap: neonatal RDS is a different disease: surfactant deficiency in preterm infants, with ground-glass lungs and air bronchograms; antenatal corticosteroids reduce its risk and severity.
Causes: direct vs indirect lung injury
Sepsis and pneumonia account for most cases.
| Direct (airspace side) | Indirect (bloodstream side) |
|---|---|
| Pneumonia (bacterial or viral) | Sepsis from a nonpulmonary source |
| Aspiration of gastric contents | Major trauma with prolonged shock; burns |
| Pulmonary contusion; nonfatal drowning | Acute pancreatitis |
| Smoke or irritant gas inhalation | Transfusion (TRALI); massive transfusion |
| Fat or amniotic fluid embolism | Drug overdose (aspirin, cocaine, opioids, tricyclics) |
TRALI vs TACO (timing from the CDC hemovigilance definitions):
| TRALI | TACO | |
|---|---|---|
| Mechanism | Donor anti-HLA or anti-granulocyte antibodies activate the recipient's neutrophils in the lung → capillary leak | Volume overload → hydrostatic edema |
| Onset | During or within 6 hours of transfusion | Within 12 hours |
| Left atrial hypertension | Absent by definition (no circulatory overload) | Present (circulatory overload); an elevated BNP or NT-proBNP supports it |
| At risk | Any recipient | Older adults; cardiac or renal insufficiency |
| Treatment | Supportive care; avoid diuretics | IV diuretic such as furosemide |
ARDS vs cardiogenic pulmonary edema
| Feature | ARDS | Cardiogenic pulmonary edema |
|---|---|---|
| Starling problem | ↑ capillary permeability | ↑ hydrostatic pressure from high LV filling pressure |
| Edema fluid | Protein-rich: edema-to-plasma protein ratio > 0.65 | Protein-poor: ratio < 0.65 |
| Stem clues | Sepsis, pneumonia, pancreatitis, trauma or transfusion | S3 or summation gallop, jugular venous distention, peripheral edema |
| Chest x-ray | Bilateral opacities, generally more peripheral | Perihilar "bat-wing" opacities, cardiomegaly, Kerley B lines, effusions |
| Wedge pressure | Classically normal (no longer a criterion) | High |
| BNP and echo | Echo may show a weak LV, but that is not specific (sepsis depresses contractility) | An elevated BNP suggests a cardiac cause; LV dysfunction |
| Treatment | Lung-protective ventilation, PEEP, proning | Oxygen, IV diuretic, vasodilators, noninvasive ventilation |
The edema mechanisms are compared in Starling forces, and the cardiac side in left vs right-sided heart failure.
Treatment: what improves survival
Treat the trigger first (antibiotics and source control for sepsis or pneumonia). Then:
| Intervention | What to do | Evidence |
|---|---|---|
| Low tidal volume | 6 mL/kg predicted body weight (range 4-8), plateau pressure < 30 cm H2O | Strong recommendation; the NHLBI ARDS Network trial (2000): 6 mL/kg beat 12 mL/kg for survival |
| PEEP | Recruit alveoli so FiO2 can fall; target SpO2 about 88-95% | ATS 2024: higher PEEP without recruitment maneuvers in moderate-severe ARDS (conditional); strong recommendation against prolonged high-pressure recruitment maneuvers |
| Prone positioning | > 12 hours a day in severe ARDS (Merck: at least 12 hours a day in moderate to severe ARDS) | ATS strong recommendation for severe ARDS (2017, restated 2024); PROSEVA (PaO2/FiO2 < 150, at least 16 hours a day) improved survival |
| Conservative fluids | Less fluid plus diuretics once shock has resolved | Fewer ventilator and ICU days; no survival difference |
| Selected patients | Corticosteroids; neuromuscular blockade in early severe ARDS; VV-ECMO in selected severe ARDS | Conditional ATS 2024 suggestions. Merck calls glucocorticoid data in ARDS inconclusive (dexamethasone is recommended in COVID-19) and prefers sedation to neuromuscular blockade |
| No mortality benefit | Inhaled nitric oxide (transient oxygenation gain), surfactant in adults, high-frequency oscillatory ventilation, pulmonary artery catheter | ATS/ESICM/SCCM 2017: strong recommendation against routine HFOV in moderate or severe ARDS |
Predicted body weight uses height and sex, because tidal volume is scaled to the size of a healthy lung, not to body fat:
- Men:
- Women:
- A 178 cm man: PBW about 73 kg, so 6 mL/kg is about 440 mL.
Why it works: big breaths overdistend the small aerated lung (volutrauma), and alveoli that open and close with every breath are injured too (atelectrauma). Low tidal volume limits the first, PEEP the second; proning makes ventilation more uniform. The trade-off is permissive hypercapnia, usually tolerated down to a pH of about 7.15.
Prognosis: 28-day mortality is about 30-35% (over 40% in severe ARDS), mostly from sepsis and multiorgan failure. Most survivors' lung function returns close to normal within 6-12 months, but weakness and cognitive problems often persist.
Practice question
A 52-year-old man with gallstone pancreatitis becomes progressively dyspneic on hospital day 2 and is intubated. Chest x-ray shows new bilateral patchy opacities with a normal heart size, and echocardiography shows normal left ventricular function. He is ventilated at 6 mL/kg predicted body weight with a plateau pressure of 28 cm H2O and PEEP of 14 cm H2O. On FiO2 0.8, his PaO2 is 64 mm Hg. Which of the following is most likely to improve his survival?
A. Prone positioning for more than 12 hours a day B. Increase tidal volume to 10 mL/kg to open collapsed alveoli C. Inhaled nitric oxide D. High-frequency oscillatory ventilation E. Pulmonary artery catheter to keep the wedge pressure below 18 mm Hg
Answer: A. His P/F ratio is : severe ARDS from an indirect injury (pancreatitis), with a normal echo arguing against a cardiac cause. He already has lung-protective settings, so prolonged prone positioning is the next survival-proven step.
- B: larger breaths overdistend the aerated lung; 6 mL/kg outperformed 12 mL/kg in the ARDS Network trial.
- C: inhaled nitric oxide can transiently improve oxygenation but has not reduced mortality.
- D: a high-frequency oscillation trial was stopped early for harm; guidelines strongly recommend against routine use.
- E: pulmonary artery catheters did not improve outcomes, and the diagnosis no longer depends on wedge pressure.
Key takeaways
- ARDS = within 1 week, bilateral opacities, not primarily cardiac, PaO2/FiO2 ≤ 300 on PEEP ≥ 5: mild 201-300, moderate 101-200, severe ≤ 100.
- The 2024 global definition adds nonintubated patients on high-flow oxygen ≥ 30 L/min, SpO2/FiO2 ≤ 315 (SpO2 ≤ 97%) and lung ultrasound.
- Leaky barrier → protein-rich edema → diffuse alveolar damage with hyaline membranes → type II pneumocyte hyperplasia.
- Hypoxemia is refractory because of shunt; compliance falls and dead space rises.
- Sepsis and pneumonia cause most cases; also aspiration, trauma, pancreatitis and transfusion (TRALI within 6 hours).
- Treat with 6 mL/kg predicted body weight, plateau < 30 cm H2O, PEEP and prone positioning > 12 h/day in severe ARDS; restrict fluids once shock resolves.
Sources
- Acute Hypoxemic Respiratory Failure (AHRF, ARDS) — Merck Manual Professional Edition (2026)
- Matthay MA, et al. A New Global Definition of Acute Respiratory Distress Syndrome — Am J Respir Crit Care Med (2024)
- Matthay MA, et al. Acute respiratory distress syndrome — Nature Reviews Disease Primers (2019), free full text on PMC
- Fan E, et al. ATS/ESICM/SCCM Guideline: Mechanical Ventilation in Adult Patients with ARDS — Am J Respir Crit Care Med (2017)
- Qadir N, et al. An Update on Management of Adult Patients with ARDS: ATS Clinical Practice Guideline — Am J Respir Crit Care Med (2024)
- Batah SS, Fabro AT. Pulmonary pathology of ARDS in COVID-19: a pathological review for clinicians — Respiratory Medicine (2021)
- NHSN Hemovigilance Module Protocol (TRALI and TACO definitions) — CDC (2026)
- Complications of Transfusion — Merck Manual Professional Edition (2026)
- Pulmonary Edema — Merck Manual Professional Edition (2025)
- Respiratory Distress Syndrome in Neonates — Merck Manual Professional Edition (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
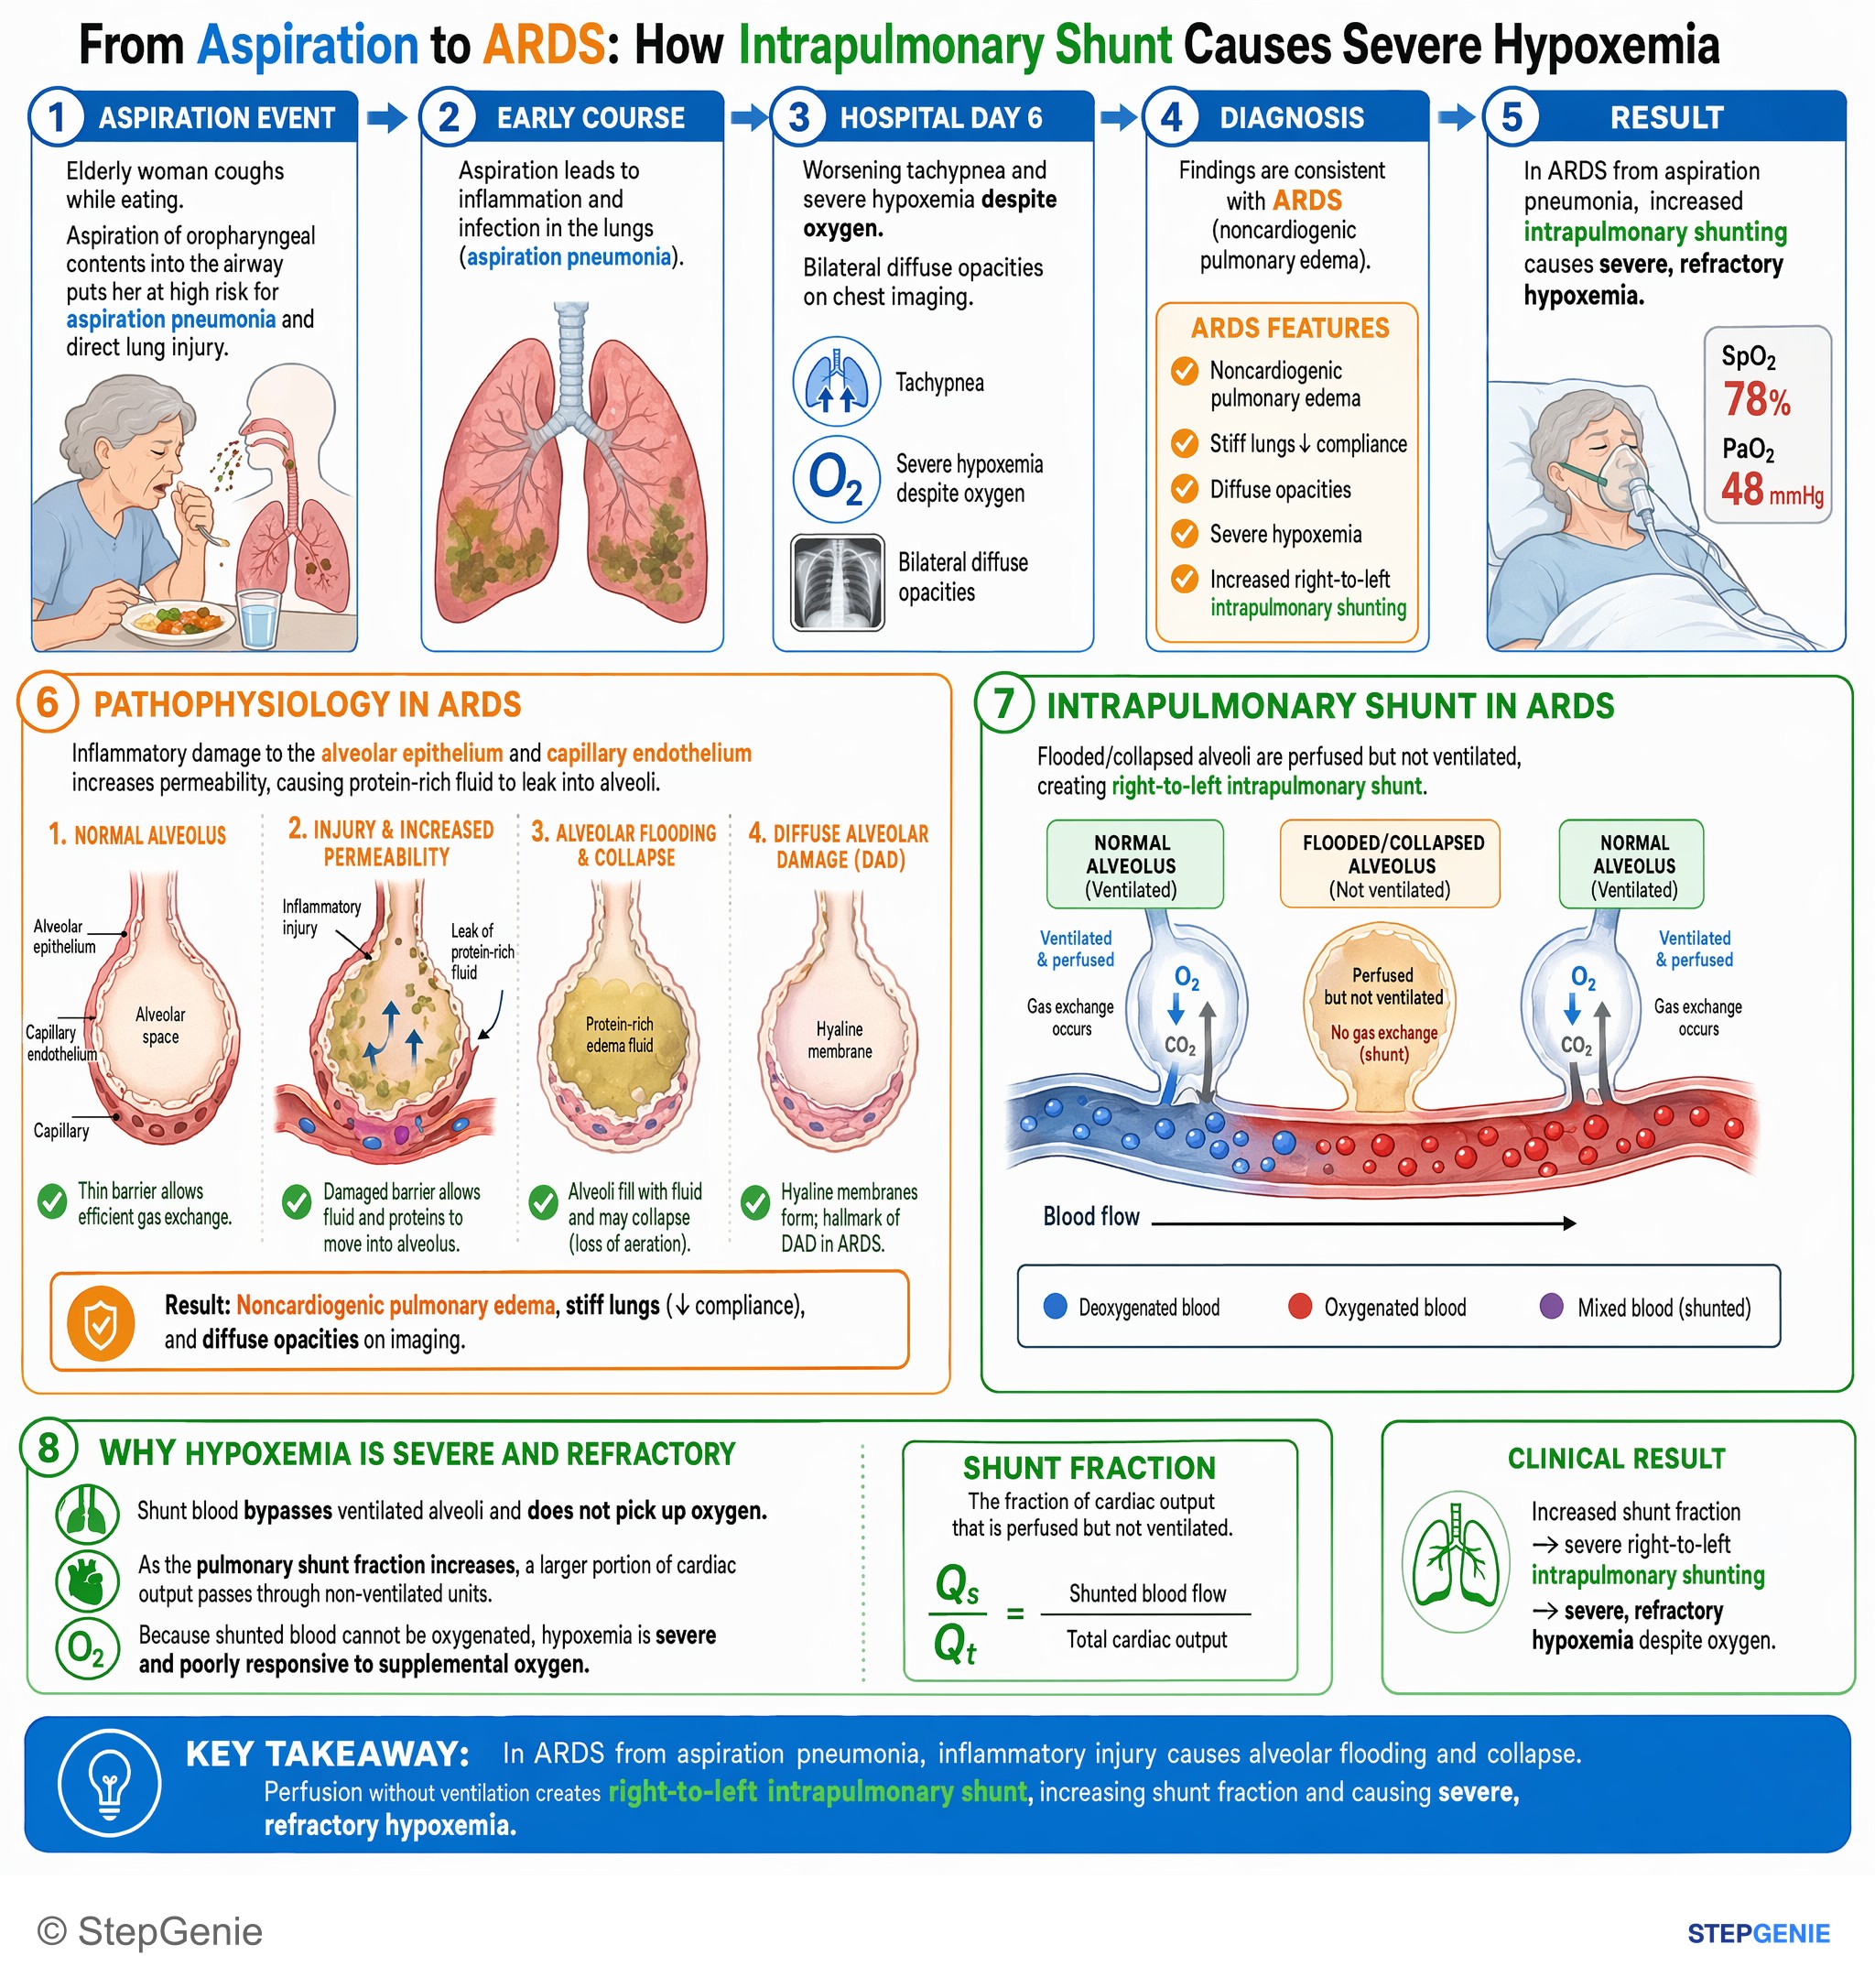
ARDS from aspiration pneumonia causes noncardiogenic pulmonary edema, stiff lungs, diffuse opacities, and severe hypoxemia due to…
USMLE Step 1Frequently Asked Questions
What are the Berlin criteria for ARDS?
The Berlin definition (2012) requires onset within 1 week of a known insult or new or worsening respiratory symptoms, bilateral opacities on chest x-ray or CT not fully explained by effusions, collapse or nodules, and respiratory failure not fully explained by heart failure or fluid overload. Severity is set by oxygenation on at least 5 cm H2O of PEEP or CPAP: a PaO2/FiO2 of 201-300 mm Hg is mild, 101-200 is moderate and 100 or less is severe.
What changed in the 2024 global definition of ARDS?
The global definition keeps the Berlin timing, imaging and noncardiac-origin criteria but widens who can be diagnosed. Patients on high-flow nasal oxygen of at least 30 L/min can meet criteria as nonintubated ARDS, an SpO2/FiO2 of 315 or less can stand in for the PaO2/FiO2 when the SpO2 is 97% or less, and lung ultrasound can show the bilateral changes. In resource-limited settings, neither PEEP nor a minimum oxygen flow is required.
How do you calculate the P/F ratio in ARDS?
Divide the arterial PaO2 in mm Hg by the FiO2 written as a fraction. A PaO2 of 60 mm Hg on 50% oxygen gives 60 / 0.5 = 120, which is moderate ARDS if the patient is on at least 5 cm H2O of PEEP. The lower the ratio, the worse the oxygenation; 100 or less is severe.
Why is ARDS ventilated with a tidal volume of 6 mL/kg?
ARDS leaves only a small aerated baby lung, so normal-sized breaths overdistend it and cause ventilator-induced lung injury. Guidelines recommend 4-8 mL/kg of predicted body weight, usually starting at 6 mL/kg, with a plateau pressure below 30 cm H2O, and the NHLBI ARDS Network trial found better survival with 6 than with 12 mL/kg. Predicted body weight comes from height and sex, not actual weight.
What is the histology of ARDS?
The classic pattern is diffuse alveolar damage. In the exudative phase, roughly the first week, the alveoli fill with protein-rich edema and are lined by eosinophilic, fibrin-rich hyaline membranes, with neutrophils and hemorrhage. A proliferative phase follows, with type II pneumocyte hyperplasia and, in some patients, interstitial fibrosis.
How do you tell ARDS from cardiogenic pulmonary edema?
ARDS is a permeability problem that follows a risk factor such as sepsis, pneumonia, aspiration, pancreatitis or trauma, and its edema fluid is protein-rich. Cardiogenic edema comes from high left-sided filling pressure, with clues such as an S3, jugular venous distention, cardiomegaly, a high BNP and a high wedge pressure. Echocardiography helps, but a weak ventricle does not exclude ARDS because sepsis can depress contractility.