Surfactant is one of those “small topic, huge yield” concepts that shows up everywhere: newborn respiratory distress, compliance curves, atelectasis, and even why small alveoli don’t collapse into oblivion. Here’s a quick-hit, shareable one-pager you can review in 2 minutes and recall on test day.
The one-liner (memorize this)
Surfactant (from type II pneumocytes) decreases surface tension → increases compliance → prevents alveolar collapse (esp at end-expiration) and reduces work of breathing.
What it is + where it comes from
Source
- Type II pneumocytes
- Cuboidal cells in alveoli
- Also responsible for alveolar repair/regeneration after injury
What it’s made of (high yield)
- Mostly phospholipids (classic: dipalmitoylphosphatidylcholine, DPPC / lecithin)
- Plus surfactant proteins (SP-A, SP-B, SP-C, SP-D)
When it starts (board-relevant timeline)
- Begins production around 20–24 weeks
- Ramps up significantly in the late 3rd trimester
- “Functionally sufficient” is often framed as ~34–36 weeks (varies by source/question stem wording)
The physiology you actually need (surface tension, compliance, and stability)
The key relationship: Laplace’s law
For an alveolus:
- = pressure needed to keep the alveolus open
- = surface tension
- = radius
Why this matters: small alveoli (low ) would require high to stay open—unless surfactant lowers .
High-yield consequences of surfactant
- ↓ Surface tension ()
- ↓ Collapsing pressure (prevents atelectasis)
- ↑ Lung compliance (easier to inflate)
- ↓ Work of breathing
- ↓ Tendency for fluid to transude into alveoli (helps keep alveoli “dry”)
The classic “small vs large alveoli” concept (common trap)
Without surfactant:
- Smaller alveoli have higher → tend to collapse into larger alveoli
With surfactant:
- Surfactant’s effect is stronger when alveoli are smaller (surfactant molecules become more concentrated as surface area shrinks)
- This stabilizes small alveoli and prevents collapse.
Visual/mnemonic device (quick recall)
“SOAP bubble lungs”
Imagine alveoli coated in soap:
- Soap lowers surface tension in bubbles → keeps tiny bubbles from popping
- Surfactant is the lung’s soap
Mnemonic: “SUrface ACTant” → ACTs on surface tension
- SUrfactant ↓ SUrface tension
Surfactant vs compliance: how to answer graph questions
Compliance is .
Surfactant increases compliance, so compared with normal:
- The lung inflates more for the same pressure
- On a pressure–volume curve, surfactant shifts the curve up/left (less pressure needed for a given volume)
Clinical correlations you’ll see on USMLE (high yield)
Neonatal Respiratory Distress Syndrome (NRDS)
Path: insufficient surfactant (usually prematurity)
Who: premature infants (especially <34 weeks)
Presentation:
- Respiratory distress shortly after birth
- Grunting, nasal flaring, retractions, tachypnea
CXR: classically ground-glass appearance + air bronchograms
Complications: atelectasis, hypoxemia, acidosis
Management (board style):
- Antenatal corticosteroids (e.g., betamethasone) → accelerate type II pneumocyte maturation → ↑ surfactant
- Exogenous surfactant for treatment
- Support with CPAP/ventilation as needed
Transient Tachypnea of the Newborn (TTN) (the “not surfactant” comparison)
- Due to delayed clearance of fetal lung fluid
- Often after C-section
- Usually self-limited within 1–2 days
Board tip: TTN is about fluid, NRDS is about surfactant.
ARDS (adult respiratory distress syndrome)
Surfactant becomes dysfunctional/inactivated due to diffuse alveolar damage → ↓ compliance (“stiff lungs”).
- Exudative phase: protein-rich edema + hyaline membranes
- Think sepsis, pancreatitis, aspiration, trauma, massive transfusion
Type II pneumocyte quick hits (often tested together)
- Type I pneumocytes: gas exchange, thin, cover most alveolar surface area
- Type II pneumocytes: surfactant + regeneration
- Alveolar macrophages (dust cells): phagocytose debris/RBCs (e.g., in CHF you can see hemosiderin-laden macrophages)
Super high-yield table: Surfactant facts at a glance
| Feature | High-yield answer |
|---|---|
| Produced by | Type II pneumocytes |
| Main function | ↓ surface tension → ↑ compliance → prevent atelectasis |
| Key equation | |
| Starts (roughly) | ~20–24 weeks, increases in 3rd trimester |
| Clinically sufficient | Often tested as ~34–36 weeks |
| Deficiency causes | NRDS |
| Antenatal boost | Corticosteroids |
| Treatment | Exogenous surfactant + respiratory support |
| ARDS effect | Surfactant dysfunction → ↓ compliance |
Rapid-fire exam bullets (the “last 30 seconds” review)
- Surfactant ↓ → ↓ needed to keep alveoli open
- Prevents small alveoli from collapsing into large ones
- Increases compliance → easier inflation → lower work of breathing
- NRDS: prematurity, ground-glass CXR, treat with steroids (prenatal) + surfactant (postnatal)
- ARDS: stiff lungs due to diffuse alveolar damage + surfactant dysfunction
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
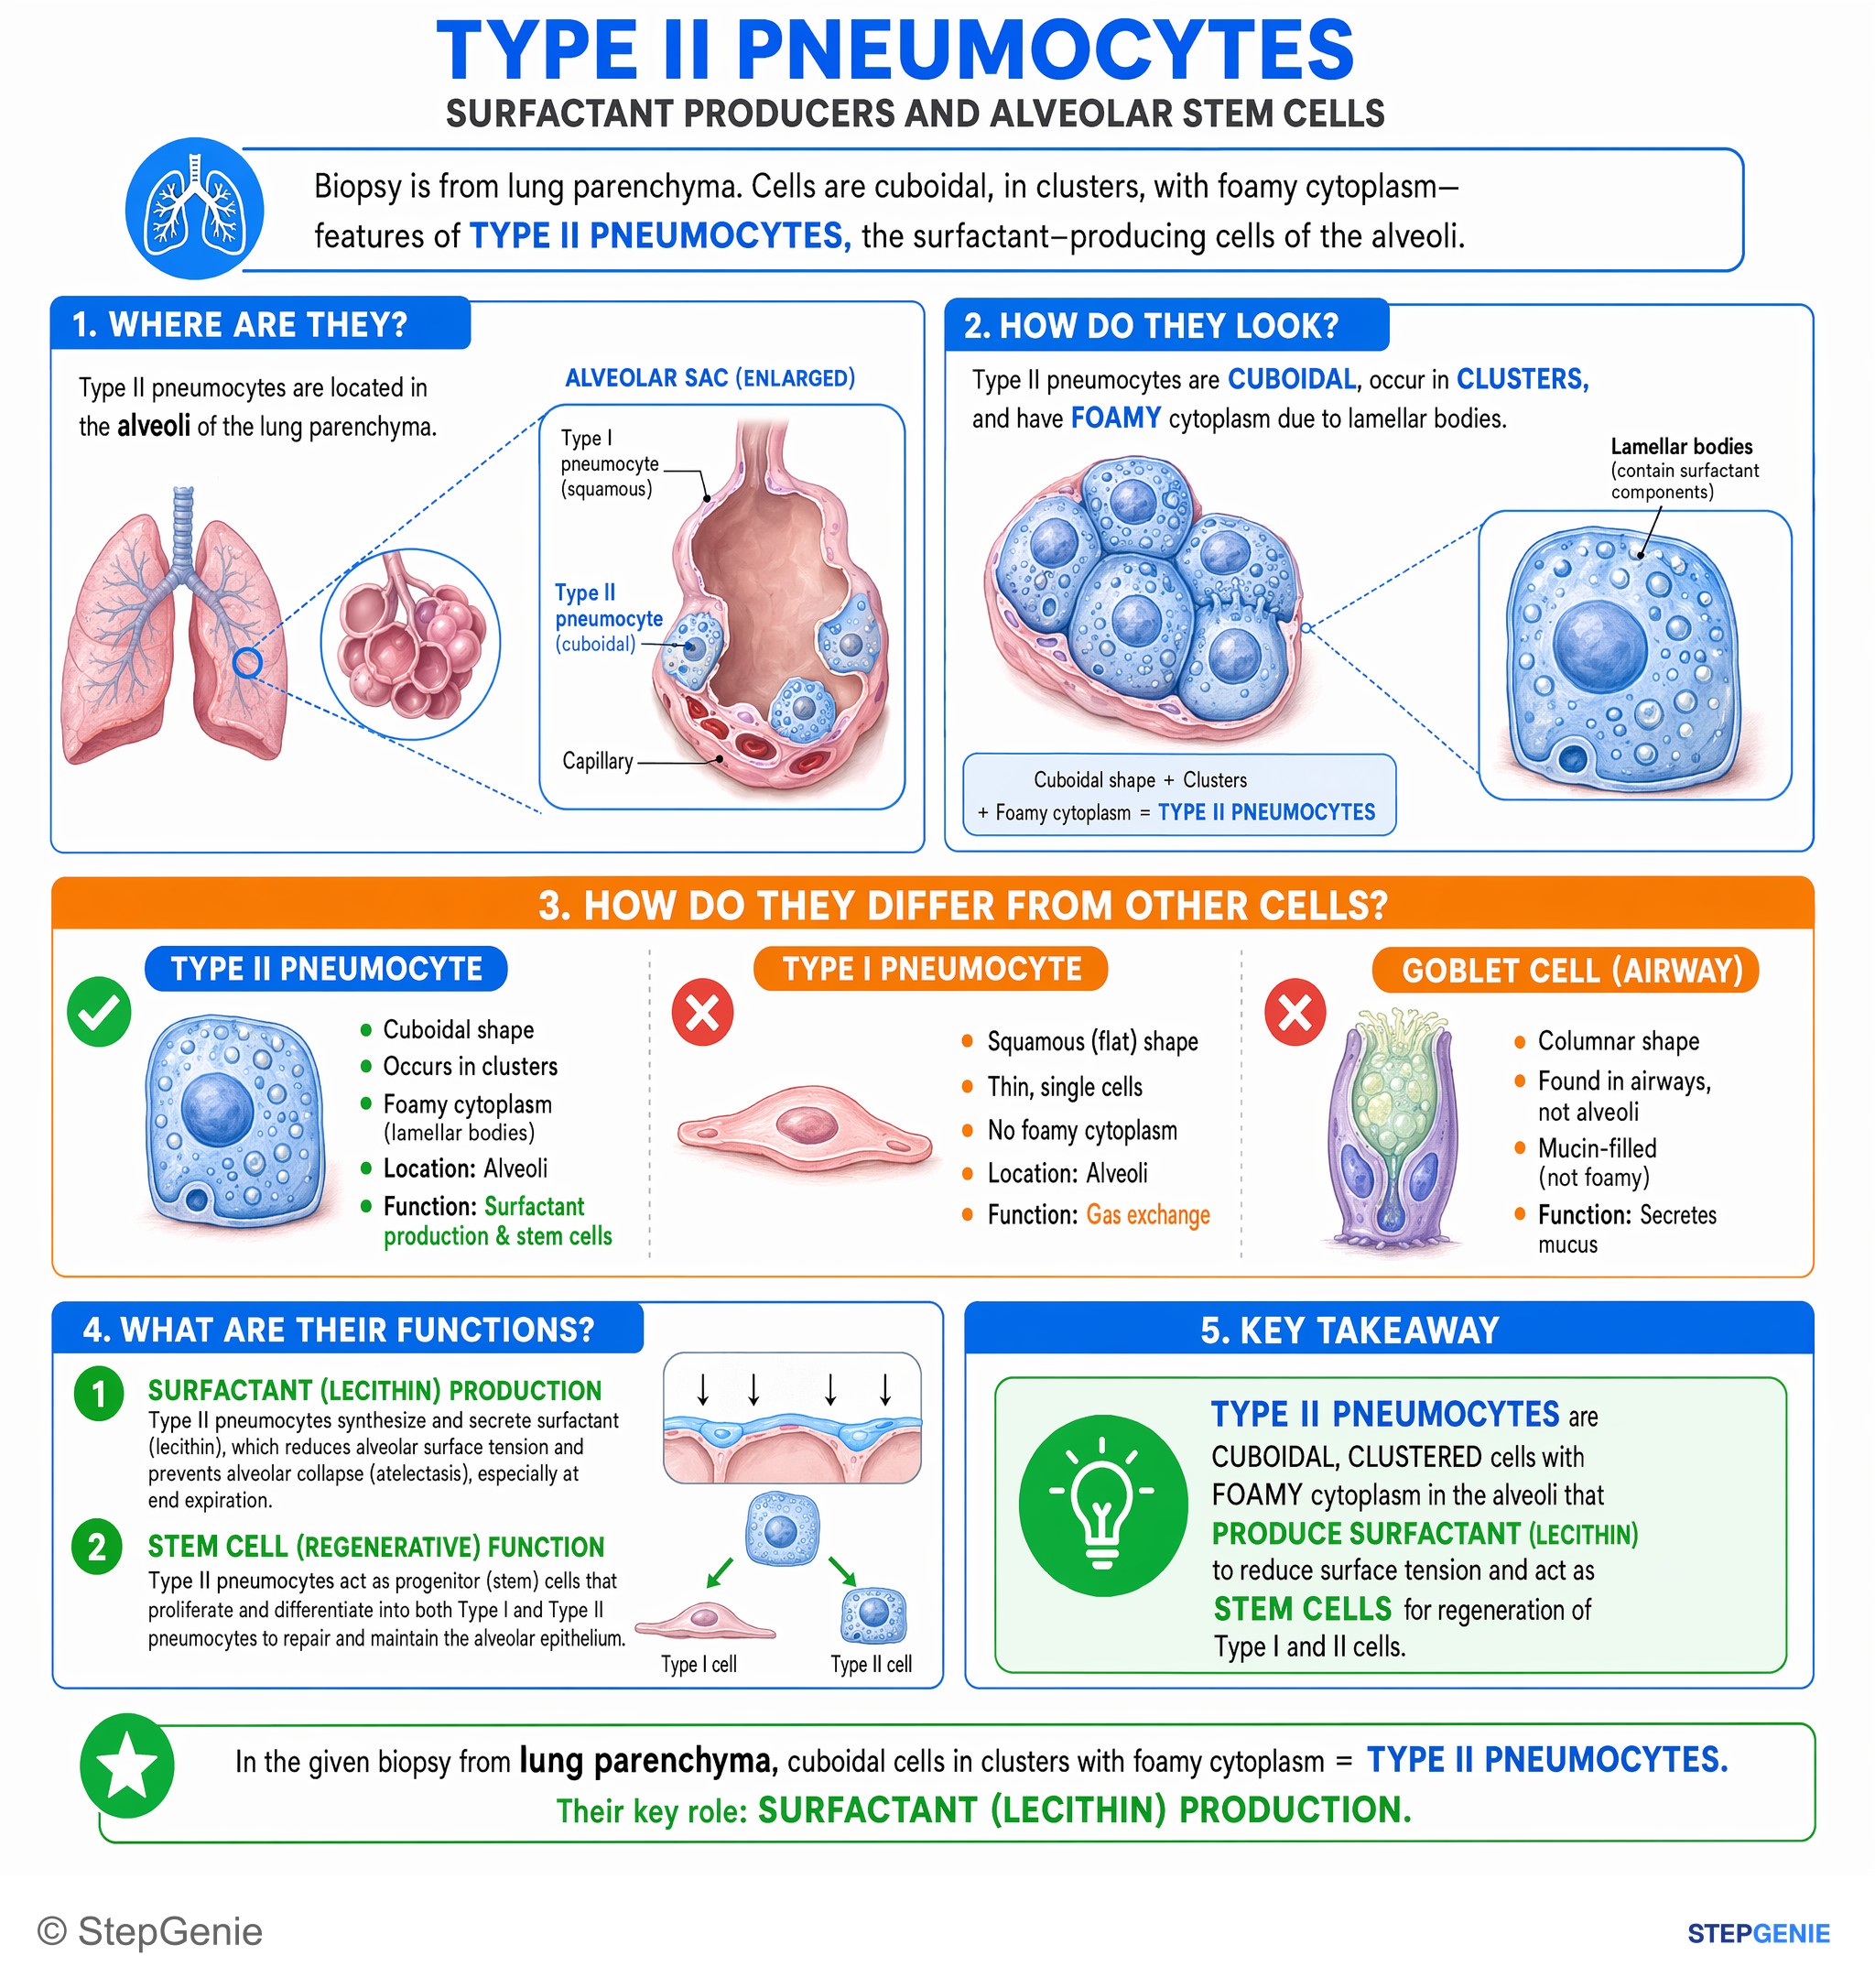
Type II pneumocytes are cuboidal cells with foamy cytoplasm that produce surfactant (lecithin) to reduce alveolar surface tension and…
USMLE Step 1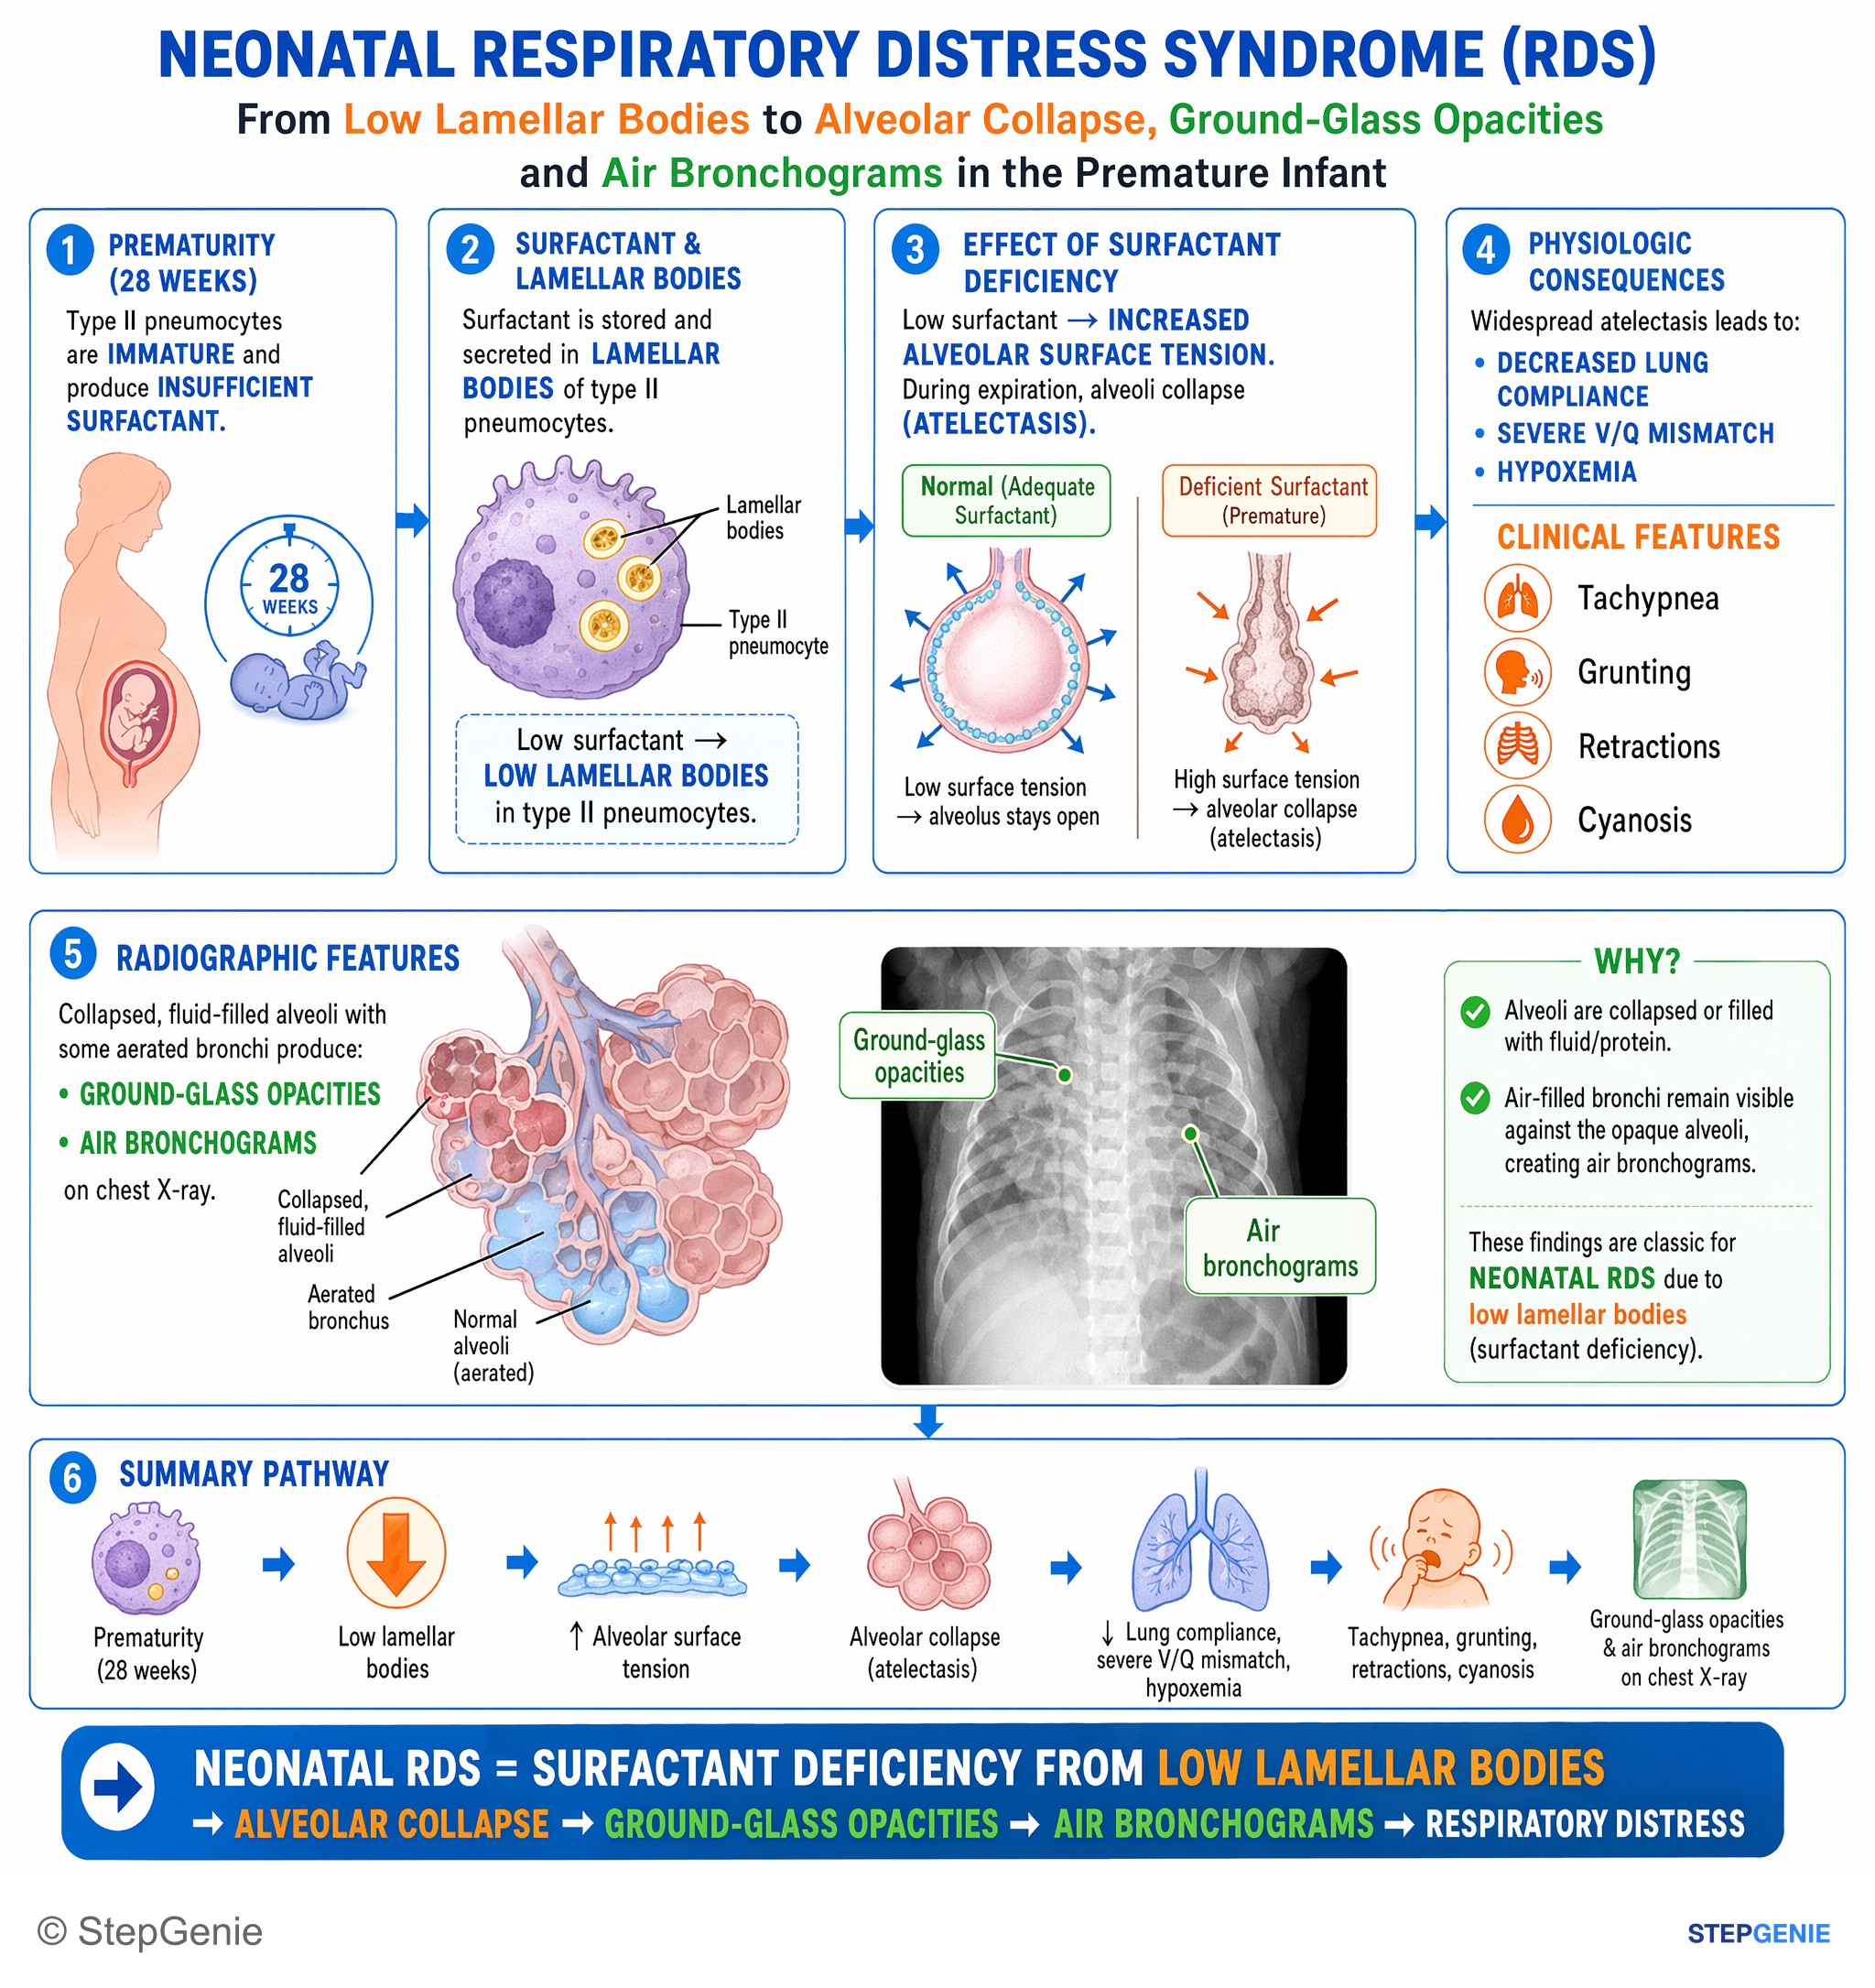
Neonatal respiratory distress syndrome from surfactant deficiency due to low lamellar bodies → alveolar collapse, ground-glass opacities…
USMLE Step 1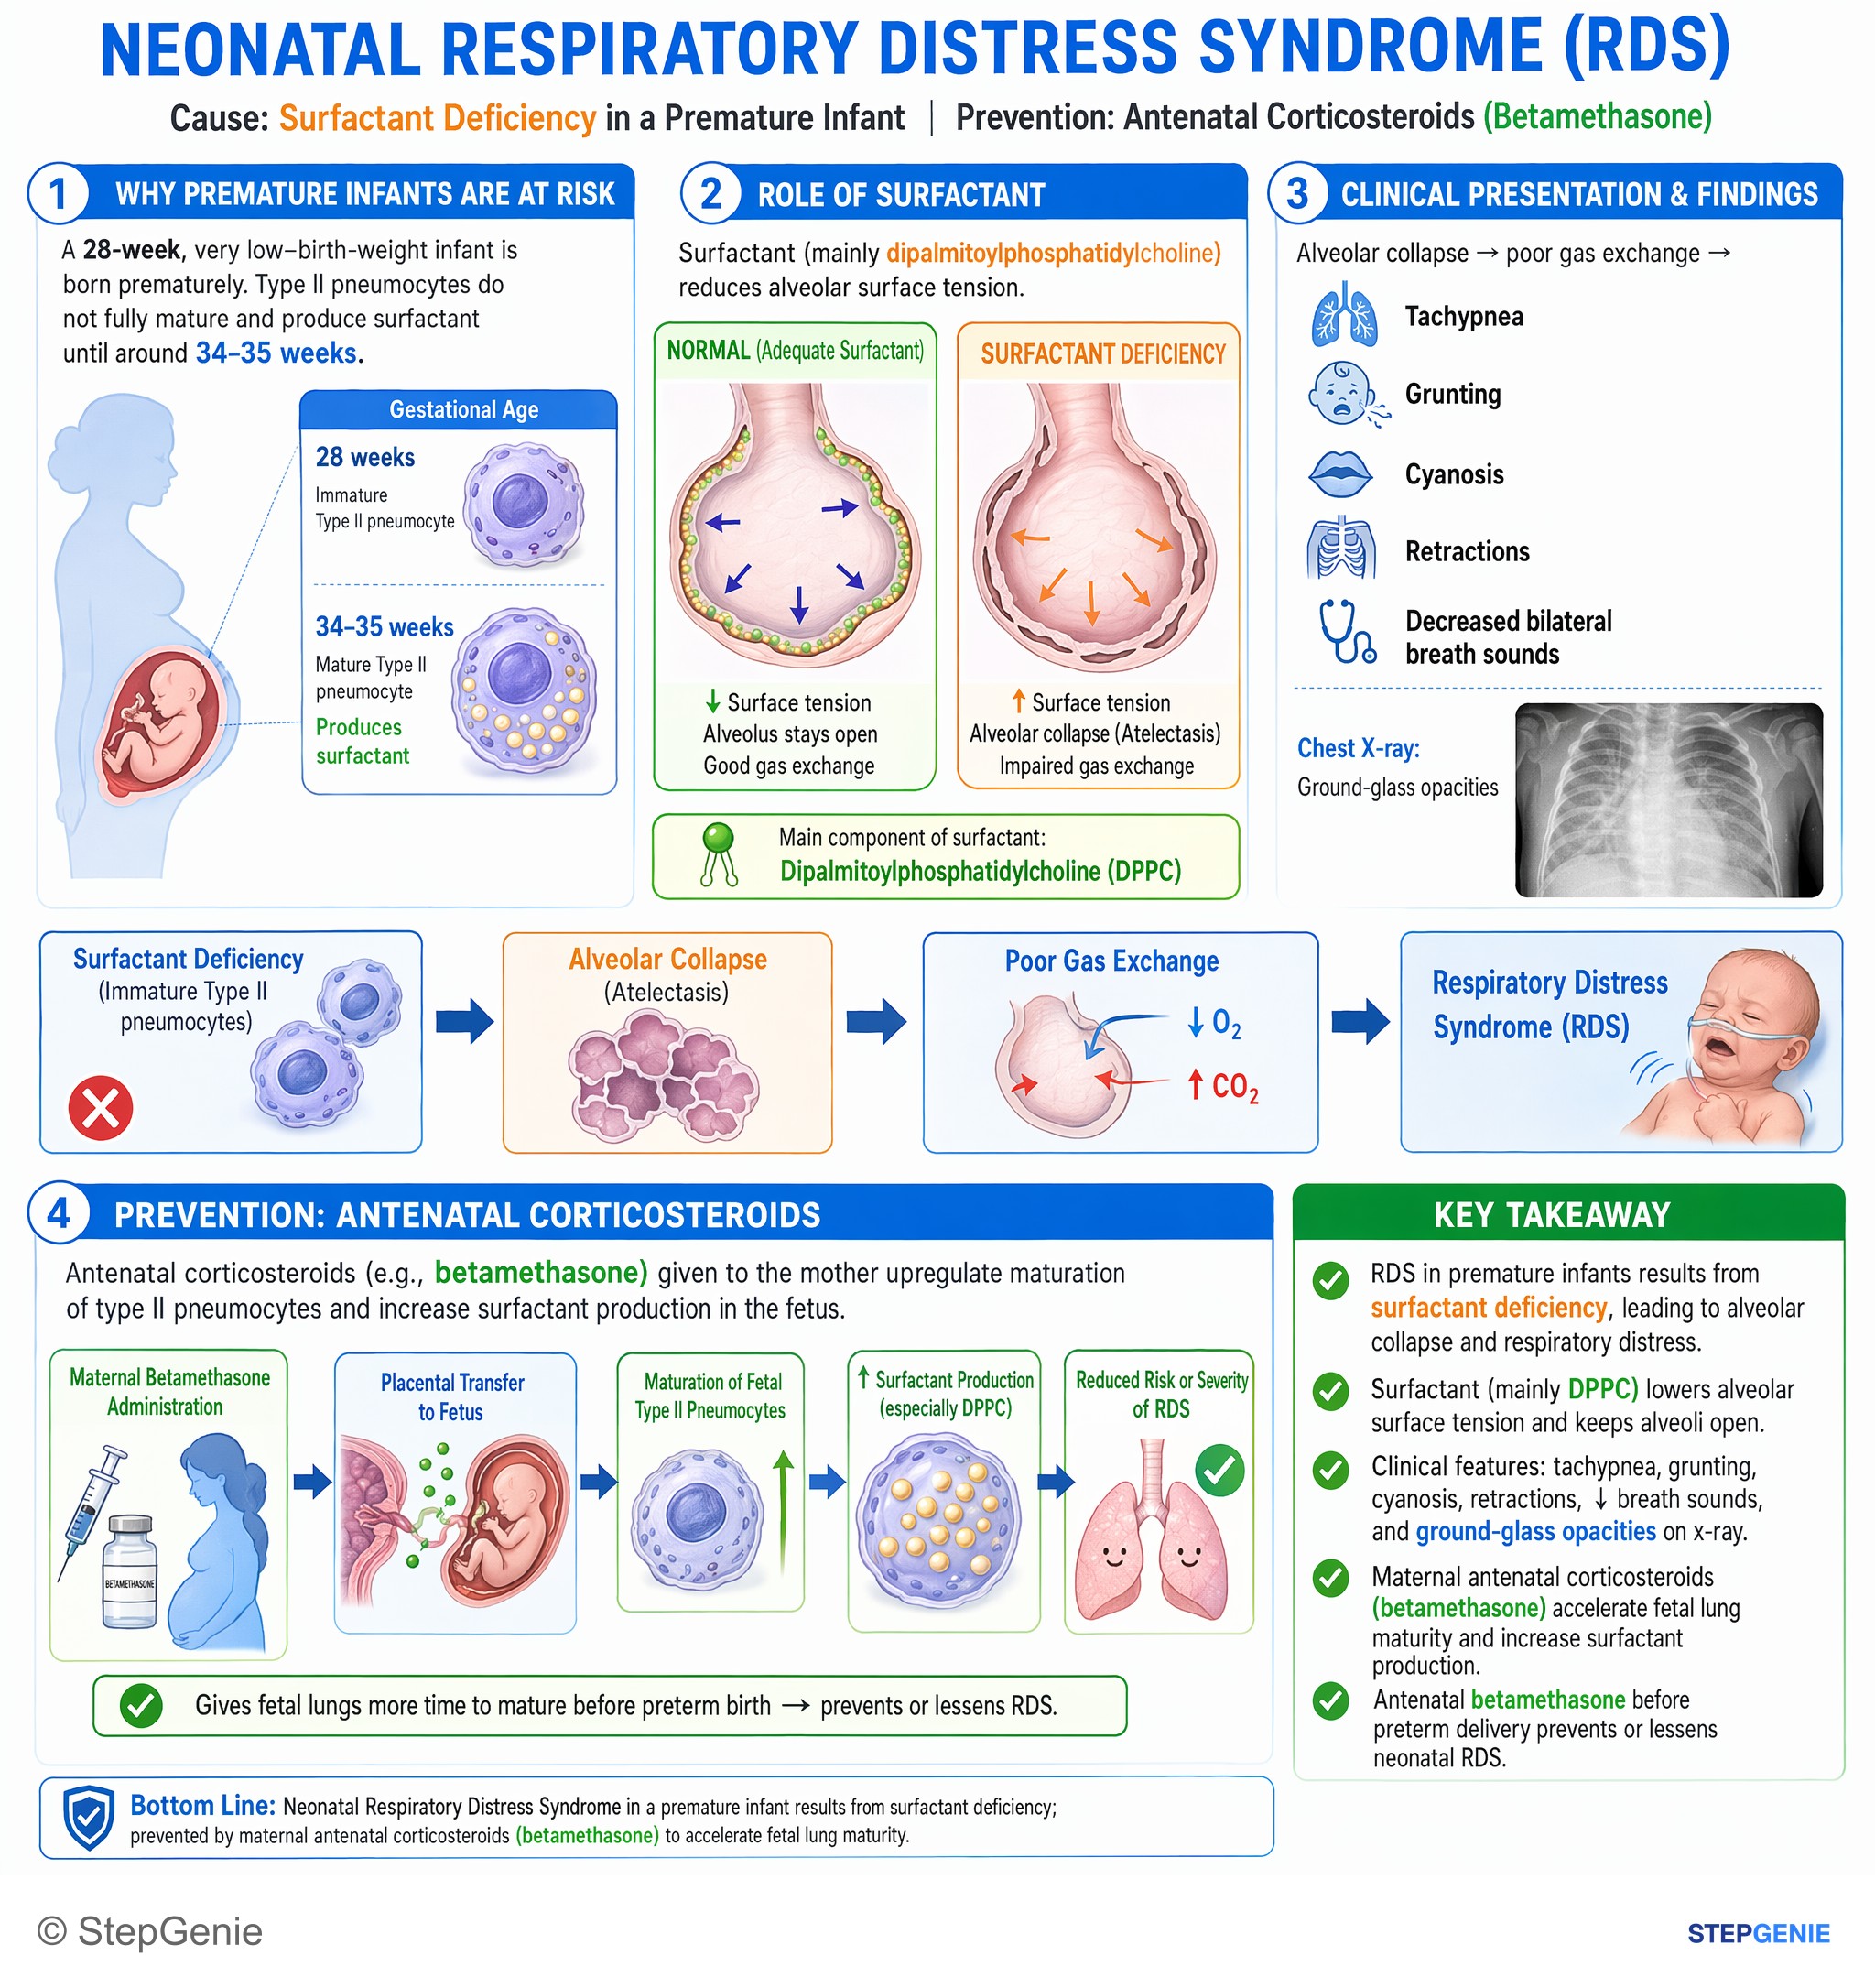
Neonatal respiratory distress syndrome in a premature infant results from surfactant deficiency; prevented by maternal antenatal…
USMLE Step 2Frequently Asked Questions
Why does surfactant prevent small alveoli from collapsing?
Surfactant prevents small alveoli from collapsing by lowering surface tension, which lowers the pressure needed to keep them open. By Laplace’s law, pressure equals 2T divided by radius, so small alveoli would otherwise need especially high pressure. Surfactant becomes more concentrated as alveoli get smaller, making its effect stronger there and stabilizing them instead of letting them collapse into larger alveoli.
How does surfactant affect lung compliance and work of breathing?
Surfactant increases lung compliance and reduces the work of breathing. Because it lowers alveolar surface tension, the lungs inflate more easily for a given pressure. On a pressure-volume curve, this means a higher or left-shifted curve, reflecting that less pressure is needed to achieve the same volume. The overall result is easier inflation and less effort required to breathe.
How do you tell neonatal respiratory distress syndrome from transient tachypnea of the newborn?
Neonatal respiratory distress syndrome is due to insufficient surfactant, whereas transient tachypnea of the newborn is due to delayed clearance of fetal lung fluid. NRDS classically occurs in premature infants and presents shortly after birth with respiratory distress, including grunting, nasal flaring, retractions, and tachypnea, with ground-glass opacities and air bronchograms on chest x-ray. TTN is often seen after C-section and is usually self-limited within 1 to 2 days.
What is the first-line board-style management for neonatal respiratory distress syndrome?
Board-style management of neonatal respiratory distress syndrome includes antenatal corticosteroids before birth, exogenous surfactant after birth, and respiratory support as needed. Corticosteroids such as betamethasone accelerate type II pneumocyte maturation and increase surfactant production. After delivery, affected infants may receive exogenous surfactant along with CPAP or ventilation depending on the severity of respiratory distress.
What do type II pneumocytes do besides make surfactant?
Type II pneumocytes make surfactant and also participate in alveolar repair and regeneration after injury. They are cuboidal alveolar cells and are commonly tested alongside type I pneumocytes, which handle gas exchange and cover most of the alveolar surface area. Remembering that type II cells are responsible for both surfactant production and regeneration helps distinguish their role from other alveolar cell types.