In a pneumoconiosis question, the exposure and the lung zone give the diagnosis: asbestos (construction trades, shipyards, insulation, brake work) causes lower-lobe fibrosis with pleural plaques, while silica and coal dust cause upper-lobe nodules. Each disease then has one classic follow-up: the greatest cancer risk in asbestosis is bronchogenic carcinoma, which is more common than mesothelioma and multiplied by smoking; silicosis raises the risk of tuberculosis; and rheumatoid nodules in a coal worker are Caplan syndrome. The vignette below tests all three.
The vignette
A 68-year-old man has had 2 years of progressive dyspnea on exertion and a dry cough. He worked for 30 years in shipbuilding, much of it handling insulation, and has a 30-pack-year smoking history. He has digital clubbing and bibasilar "Velcro-like" crackles. Chest CT shows reticular fibrosis predominantly in the peripheral lower lobes and bilateral pleural plaques. Pulmonary function tests show a reduced total lung capacity and a reduced DLCO.
This patient is at greatest risk for which of the following?
A. Bronchogenic carcinoma B. Malignant mesothelioma C. Reactivation tuberculosis D. Caplan syndrome E. Upper lobe–predominant eggshell calcification of hilar nodes
Step 1: name the disease
This is asbestosis, interstitial fibrosis caused by asbestos:
- Exposure: shipyards and insulation are classic asbestos jobs, along with insulators, pipefitters, electricians, roofers, drywall workers, boilermakers, auto brake mechanics and Navy personnel.
- Timing: disease usually appears 20–40 years after exposure.
- Clinical: slowly progressive exertional dyspnea, dry cough and bibasilar crackles; clubbing occurs in about a third (32–42%), so its absence does not exclude the diagnosis.
- Imaging: reticular fibrosis in the peripheral lower lobes, with or without pleural plaques and thickening.
- Physiology: restriction with a low DLCO; mild airflow obstruction can coexist.
Step 2: answer the question actually asked
Asbestos raises the risk of both lung cancer and mesothelioma, but lung cancer (bronchogenic carcinoma, usually non-small cell) is more common than mesothelioma, and asbestos and smoking act synergistically on lung cancer risk. Mesothelioma risk, by contrast, is independent of smoking.
Answer: A. Bronchogenic carcinoma.
Why each answer choice is right or wrong
A. Bronchogenic carcinoma (correct). It is the most common asbestos-related cancer, and this patient's smoking history multiplies the risk. Pleural plaques mark asbestos exposure; think lung cancer first, then mesothelioma.
B. Malignant mesothelioma (tempting, but not the greatest risk). Mesothelioma is a rare cancer of the mesothelium caused by asbestos in the great majority of cases, and up to 90% arise in the pleura. The latency is 30–50 years, amphibole fibers are more potent than serpentine (chrysotile) fibers, and smoking does not change the risk. Patients present with dyspnea, nonpleuritic chest pain and a pleural effusion, and a pleural biopsy is usually needed because fluid cytology is usually nondiagnostic. It would be the answer if the stem centered on a pleural effusion with nonpleuritic chest pain, or asked which tumor is most strongly tied to asbestos.
C. Reactivation tuberculosis (silicosis's complication). Silica impairs macrophage function, so silicosis raises the risk of TB and other mycobacterial infections. Latent TB infection should be treated in patients with silicosis, and silica-exposed workers are tested every year with a tuberculin skin test or interferon-gamma release assay. TB risk is also increased in coal workers' pneumoconiosis because coal dust contains silica. Nothing in this stem points to silica; the reactivation pattern itself is reviewed in the primary vs reactivation TB Q-bank breakdown.
D. Caplan syndrome (no rheumatoid arthritis, no nodules). Caplan syndrome, or rheumatoid pneumoconiosis, is multiple well-defined, mostly peripheral lung nodules in a patient with rheumatoid arthritis and inorganic dust exposure. It is traditionally tied to coal dust (coal miners have an increased risk of rheumatoid arthritis) but is also described with silica and asbestos, and the nodules must be told apart from cancer and infection. The stem would give rheumatoid arthritis and lung nodules, classically in a coal miner, not lower-lobe fibrosis with plaques.
E. Eggshell calcification of hilar nodes (silicosis's imaging sign). Chronic silicosis shows 1–3 mm nodules in the upper lobes, and calcified hilar and mediastinal nodes are common, occasionally in an eggshell pattern. This patient's disease is basal and pleural.
Pneumoconioses side by side
| Disease | Typical exposure | Lung zone | Buzzword finding | Classic follow-up |
|---|---|---|---|---|
| Asbestosis | Construction trades, shipyards and the Navy, insulation, boilermakers, brake mechanics, asbestos mining | Lower lobes, peripheral | Asbestos (ferruginous) bodies: golden-brown fibers coated with iron-containing protein; pleural plaques | Lung cancer (synergy with smoking), then mesothelioma |
| Silicosis | Mining, quarrying, stonecutting, sandblasting, foundries, glass and ceramics, engineered-stone countertops | Upper lobes | Silicotic nodules of whorled collagen with birefringent silica; eggshell-calcified hilar nodes | TB and other mycobacteria; lung cancer; rheumatoid arthritis, systemic sclerosis |
| Coal workers' pneumoconiosis | Coal mining: drilling, blasting and crushing coal | Upper lobes; progressive massive fibrosis in the upper posterior zones | Coal macules and nodules with surrounding emphysema | Progressive massive fibrosis, Caplan syndrome, COPD, TB |
| Berylliosis (chronic beryllium disease) | Aerospace, electronics, telecommunications, nuclear and defense industries, alloy production and machining | Upper zones, with hilar and mediastinal adenopathy | Granulomas indistinguishable from sarcoidosis | Beryllium lymphocyte proliferation test; remove from exposure, corticosteroids if symptomatic |
Memory aid: asbestos came down from the roof (insulation) but settles in the lung bases; silica and coal come up from the ground but settle in the upper lobes.
Details that separate the good answer from the best one
- Not every pneumoconiosis is purely restrictive. Asbestosis is the classic restrictive disease with a low DLCO. Silicosis and coal workers' pneumoconiosis can give obstructive, restrictive or mixed patterns, and coal dust causes COPD even in nonsmokers.
- Silicosis runs at three speeds. Chronic silicosis, the most common form, appears decades after exposure; accelerated silicosis appears 5–10 years after heavy exposure; acute silicosis (silicoproteinosis) follows intense exposure within weeks to a few years and mimics pulmonary alveolar proteinosis. Crystalline silica is also a Group 1 lung carcinogen (IARC).
- Black lung is back. Coal workers' pneumoconiosis, especially severe progressive disease, has resurged in the United States since the late 1990s, linked to greater silica exposure as miners cut through more rock to reach less accessible seams. NIOSH data show progressive massive fibrosis appearing more often in younger age groups, and a higher share of silica in the respirable dust of central Appalachian underground mines.
- Treatment is mostly prevention and support. There is no specific therapy for asbestosis or chronic silicosis: remove the worker from exposure, stop smoking, vaccinate against influenza, pneumococcus and COVID-19, give oxygen for hypoxemia, and consider lung transplantation for end-stage disease.
Exam traps
- "Greatest risk" vs "most specific": asbestos causes more lung cancer than mesothelioma, but mesothelioma is the tumor most tied to asbestos.
- Smoking multiplies asbestos-related lung cancer but does not change mesothelioma risk.
- Zone swap: lower lobes mean asbestos; upper lobes mean silica, coal or beryllium.
- Pleural plaques point to asbestos; eggshell nodes point to silica.
- Silica means test for latent TB, and coal dust carries some of the same risk because it contains silica.
- Sarcoid look-alike: sarcoid-like granulomas with hilar adenopathy in an aerospace or electronics worker is berylliosis.
- Caplan syndrome needs rheumatoid arthritis plus dust exposure, classically coal but also silica or asbestos, and its nodules can mimic cancer.
Worked example: the silica version
Vignette. A 34-year-old man has cut and polished engineered-quartz countertops for 7 years, often dry-cutting without respiratory protection. He has 6 months of exertional dyspnea and a dry cough. Chest CT shows many 1–3 mm nodules concentrated in the upper lobes and hilar lymph nodes with thin rims of calcification. Besides removing him from exposure, which of the following is most appropriate?
A. Interferon-gamma release assay B. Serum rheumatoid factor C. Beryllium lymphocyte proliferation test D. Pleural biopsy E. High-dose glucocorticoids
Answer: A. This is accelerated silicosis (5–10 years of heavy exposure) from engineered stone. Silica impairs macrophage function, so latent TB should be sought and treated.
- B: rheumatoid factor helps only when a coexisting rheumatic disease such as rheumatoid arthritis is suspected; silica raises that risk, but he has no joint symptoms.
- C: the beryllium test is for granulomatous disease in beryllium workers.
- D: pleural biopsy is the workup for mesothelioma, an asbestos disease that presents with dyspnea, chest pain and a pleural effusion.
- E: there is no proven specific treatment for chronic silicosis; glucocorticoids and whole-lung lavage have been tried in acute silicosis with unclear benefit.
Key takeaways
- Asbestosis: shipyards, insulation and construction; lower-lobe fibrosis with pleural plaques; clubbing in about a third; restrictive PFTs with a low DLCO.
- Asbestos cancers: lung cancer is more common and is multiplied by smoking; mesothelioma is rarer, has a 30–50 year latency and is unaffected by smoking.
- Silicosis: upper-lobe nodules, eggshell-calcified nodes, TB risk; accelerated disease in engineered-stone workers.
- Coal workers' pneumoconiosis: upper-lobe nodules, progressive massive fibrosis, Caplan syndrome; resurging in US miners.
- Berylliosis: sarcoid-like granulomas in aerospace and electronics workers; confirm with the beryllium lymphocyte proliferation test.
Sources
- Asbestosis — Merck Manual Professional Edition
- Asbestosis — StatPearls, NCBI Bookshelf
- Mesothelioma — Merck Manual Professional Edition
- Silicosis — Merck Manual Professional Edition
- Coal Worker Pneumoconiosis — Merck Manual Professional Edition
- Beryllium Disease — Merck Manual Professional Edition
- Pneumoconiosis — StatPearls, NCBI Bookshelf
- Caplan Syndrome — StatPearls, NCBI Bookshelf
- Konečný P, et al. Immunity to the Dual Threat of Silica Exposure and Mycobacterium tuberculosis — Frontiers in Immunology
- Modern Coal Miners Have Higher Death Rates From Lung Diseases Than Their Predecessors — NIOSH Science Bulletin, CDC
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
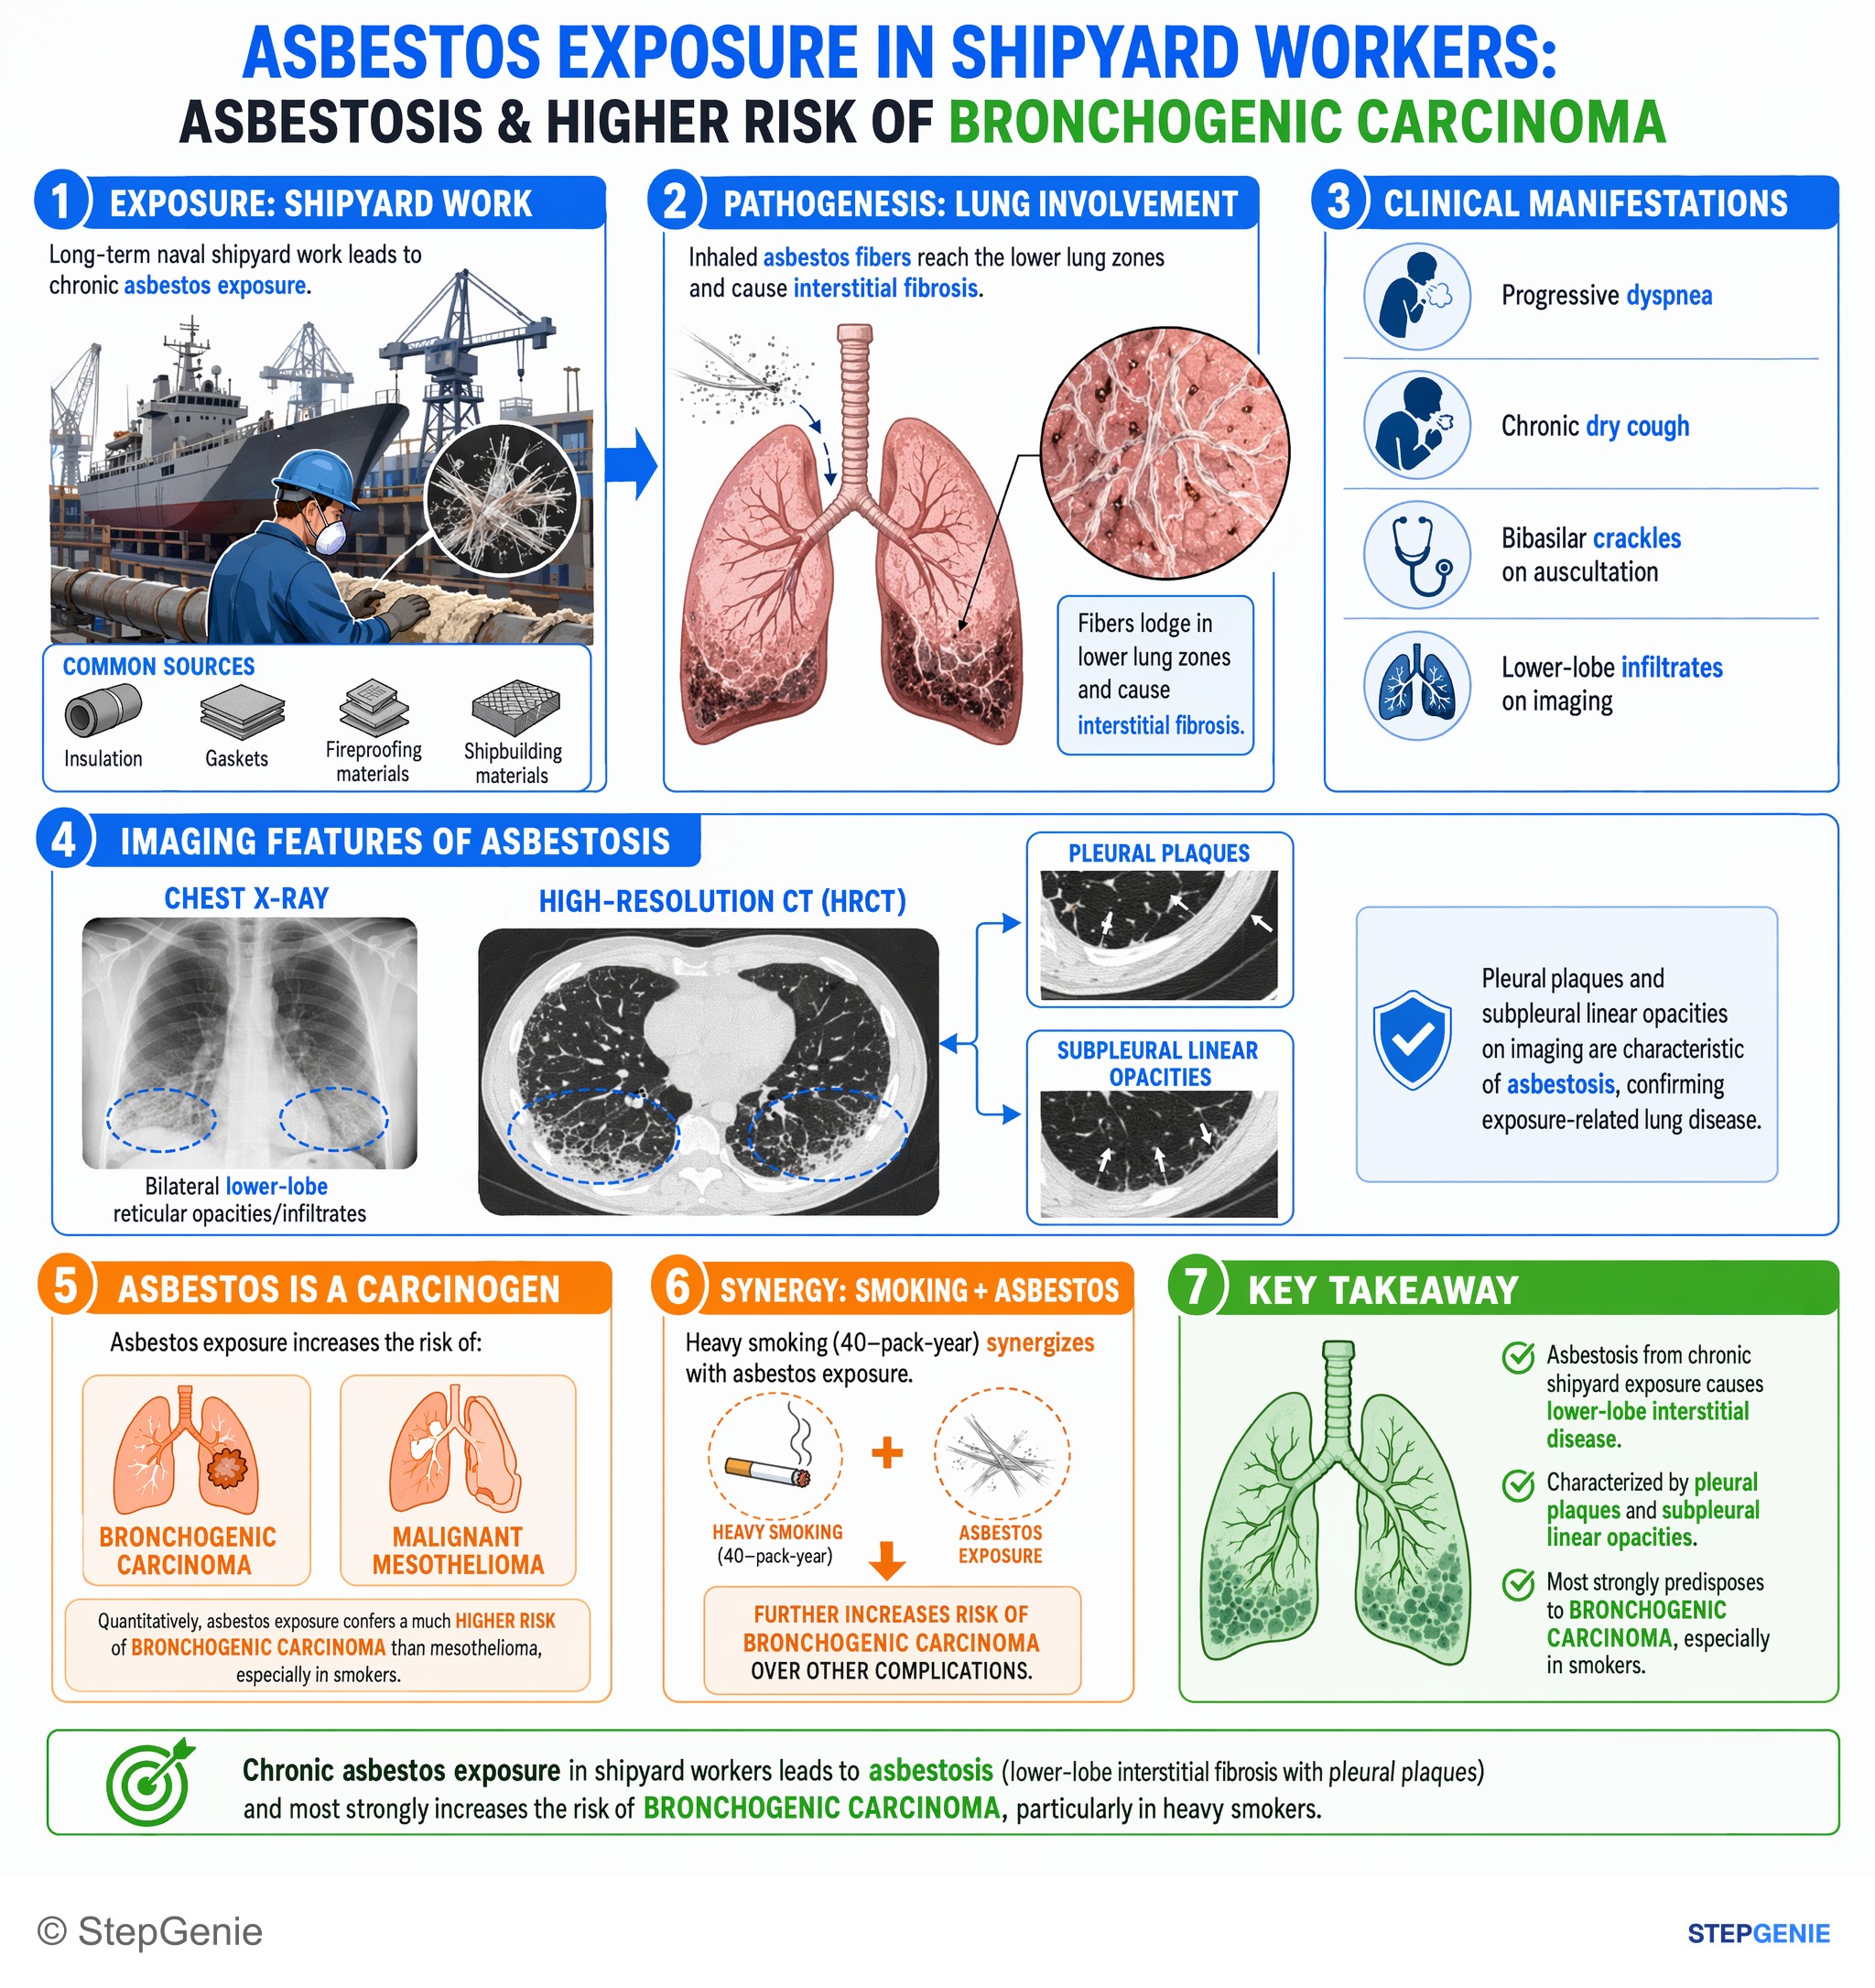
Asbestosis from chronic shipyard exposure causes lower-lobe interstitial disease with pleural plaques and most strongly predisposes to…
USMLE Step 1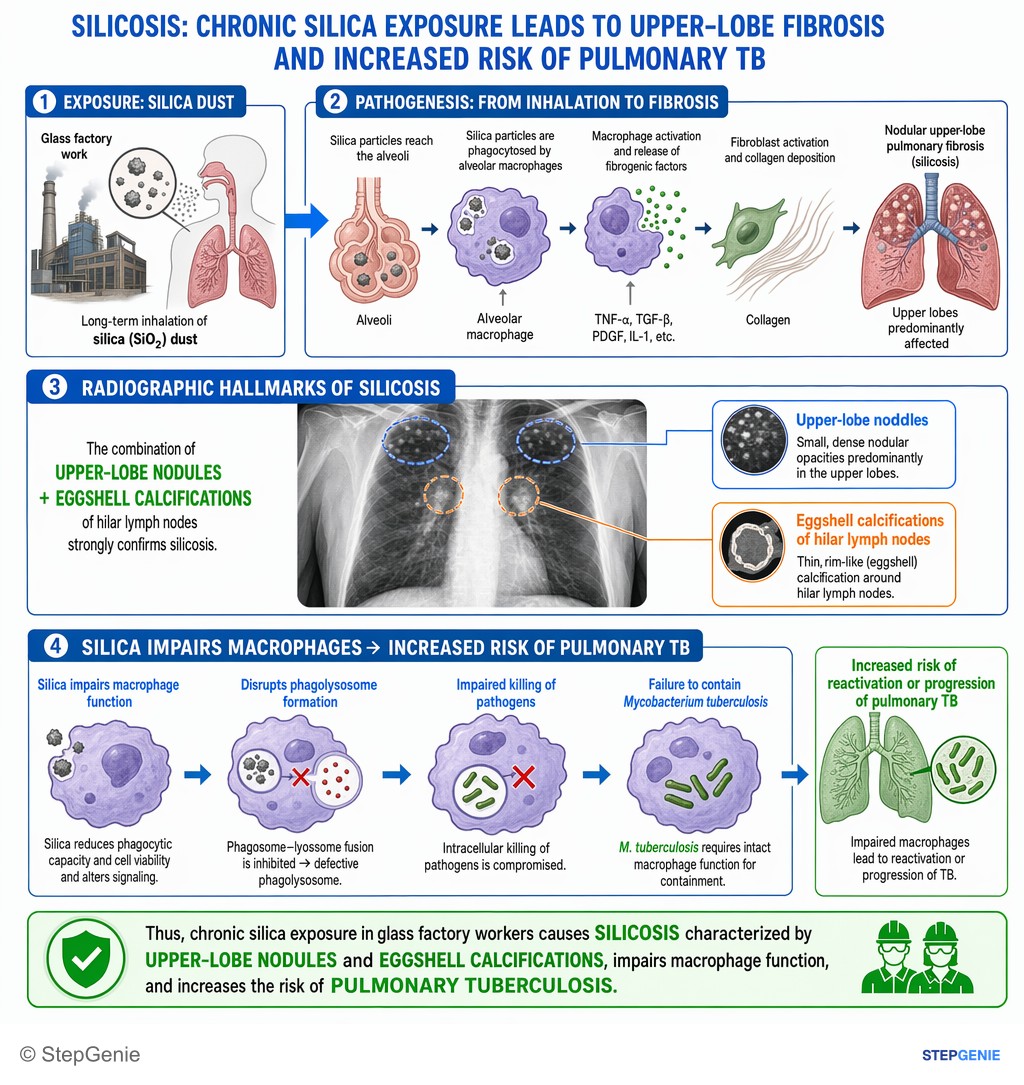
Silicosis from chronic silica exposure (glass factory) causes upper-lobe nodules, eggshell calcifications, and impairs macrophages…
USMLE Step 2Frequently Asked Questions
What cancer is a patient with asbestosis at greatest risk for?
Bronchogenic carcinoma. Asbestos raises the risk of both lung cancer and mesothelioma, but lung cancer, usually non-small cell, is more common, and asbestos and smoking act synergistically on its risk. Mesothelioma is the tumor most strongly tied to asbestos, yet it is rarer, appears 30–50 years after exposure and is not affected by smoking.
How do you tell asbestosis from silicosis on a USMLE question?
Start with the job and the lung zone. Asbestosis follows construction, shipyard, insulation or brake work and causes lower-lobe reticular fibrosis with pleural plaques. Silicosis follows mining, quarrying, stonecutting, sandblasting, foundry or engineered-stone work and causes upper-lobe nodules, often with calcified hilar nodes, occasionally in an eggshell pattern. The follow-up questions differ too: lung cancer for asbestos, tuberculosis for silica.
Why does silicosis increase the risk of tuberculosis?
Inhaled silica is taken up by alveolar macrophages and impairs their function, so patients with silicosis are more susceptible to tuberculosis and other mycobacterial infections. Silica-exposed workers are screened every year with a tuberculin skin test or interferon-gamma release assay, and latent TB infection is treated in patients with silicosis. Coal workers carry some of this risk because coal dust contains silica.
What is Caplan syndrome?
Caplan syndrome, also called rheumatoid pneumoconiosis, is the combination of rheumatoid arthritis, inorganic dust exposure and multiple well-defined, mostly peripheral lung nodules. It is traditionally tied to coal mining, and coal miners have an increased risk of rheumatoid arthritis, but it is also described after silica and asbestos exposure. The nodules can look like cancer or infection, so they must be distinguished from both.
Which pneumoconiosis looks like sarcoidosis?
Chronic beryllium disease (berylliosis). Beryllium triggers a cell-mediated hypersensitivity reaction that produces granulomas in the lungs and hilar or mediastinal lymph nodes that are indistinguishable from sarcoidosis. Exposure comes from aerospace, electronics, telecommunications, nuclear and defense work and alloy machining. The beryllium lymphocyte proliferation test detects sensitization, and treatment is removal from exposure plus corticosteroids when symptomatic.