Strongyloides is one of those parasites that USMLE loves because it breaks the usual rules: it can autoinfect, persist for decades, and then explode into hyperinfection the moment a patient gets steroids. If you can picture its “loop,” you’ll never miss the diagnosis again.
The 10-second visual hack (draw this in the margin)
The “∞ Steroid Loop” for Strongyloides
Imagine an infinity symbol () that keeps cycling:
- Left loop: Skin → larvae penetrate feet
- Cross: Lungs → larvae migrate up trachea
- Right loop: Gut → adults in small intestine
- Back to Skin/Gut: Autoinfection → larvae re-enter through intestinal mucosa or perianal skin
Now write “Steroids = Supercharger” above the .
One-liner: Strongyloides = “the autoinfecting nematode” that can persist silently, then cause hyperinfection with steroids.
Strongyloides in one table (high-yield snapshot)
| Feature | Strongyloides stercoralis |
|---|---|
| Organism type | Nematode (roundworm) |
| Infectious form | Filariform larvae in soil |
| Entry | Skin penetration (bare feet) |
| Migration | Blood → lungs → trachea → swallowed → small intestine |
| Key superpower | Autoinfection (unique board-favorite) |
| Classic lab clue | Eosinophilia (may disappear in hyperinfection) |
| Diagnosis | Larvae in stool (often intermittent), serology helpful |
| First-line treatment | Ivermectin |
| Big USMLE trigger | Steroids → hyperinfection/dissemination |
The USMLE story: Step-style pathogenesis (don’t mix this up)
1) Infection: “Feet → Lungs → Gut”
- Filariform larvae penetrate skin → bloodstream
- Reach lungs → can cause transient pneumonitis (Löffler-like symptoms)
- Crawl up trachea → swallowed
- Mature into adults in small intestine
2) Autoinfection: why it sticks around
Strongyloides can complete its cycle inside the host:
- Larvae can penetrate intestinal mucosa or perianal skin
- Reinfection happens without leaving the body → chronic infection for decades
Memory anchor: Most helminths need you to “leave the host.” Strongyloides says, “I’ll just loop forever.”
Clinical: what you’re supposed to recognize on exams
Classic clues (chronic infection)
- Intermittent abdominal pain, diarrhea
- Eosinophilia
- Urticarial rash
- “Larva currens”: rapidly migrating, pruritic, serpiginous rash (often perianal/trunk)
The scary clue: hyperinfection
Think: immunosuppression, especially glucocorticoids.
- Worsening pulmonary + GI symptoms
- Diffuse alveolar hemorrhage, respiratory failure
- Gram-negative bacteremia/meningitis can occur because larvae can carry gut flora across tissues
Step 2 pearl: If a patient from an endemic area is about to receive steroids (e.g., COPD flare, transplant, nephrotic syndrome), you screen/treat Strongyloides first.
Steroids = “turn off eosinophils, turn on disaster”
Two reasons steroids are a classic trigger:
- Immunosuppression allows massive larval proliferation → hyperinfection
- Eosinophilia may vanish, so a “normal eosinophil count” doesn’t rule it out in severe cases
Board pattern: “Starting prednisone” → then sudden GI + lung decline → think Strongyloides hyperinfection.
Diagnosis: what they’ll test you on
- Stool O&P can miss it (larvae shed intermittently)
- Serology is often used and can be more sensitive, especially in chronic infection
- In hyperinfection, larvae may be seen in sputum or other body fluids
Mini-mnemonic: Strongy = “stubborn stool sample” → may need repeat testing/serology.
Treatment: the money answer
Ivermectin is first-line
- Chronic uncomplicated infection: ivermectin
- Hyperinfection/disseminated disease: ivermectin + supportive care, often prolonged/confirmed clearance
Exam trap: Albendazole exists, but ivermectin is the go-to for Strongyloides.
Rapid-fire USMLE bullets (memorize these)
- Infectious form: filariform larvae
- Unique feature: autoinfection
- Rash: larva currens
- Complication: hyperinfection with steroids
- Complication clue: Gram-negative bacteremia (larvae translocate gut flora)
- Treatment: ivermectin
Final sticky mnemonic (shareable)
Write: “Strongy = Strong loop () + Steroids = Stronger”
Translation: autoinfection + steroids → hyperinfection.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
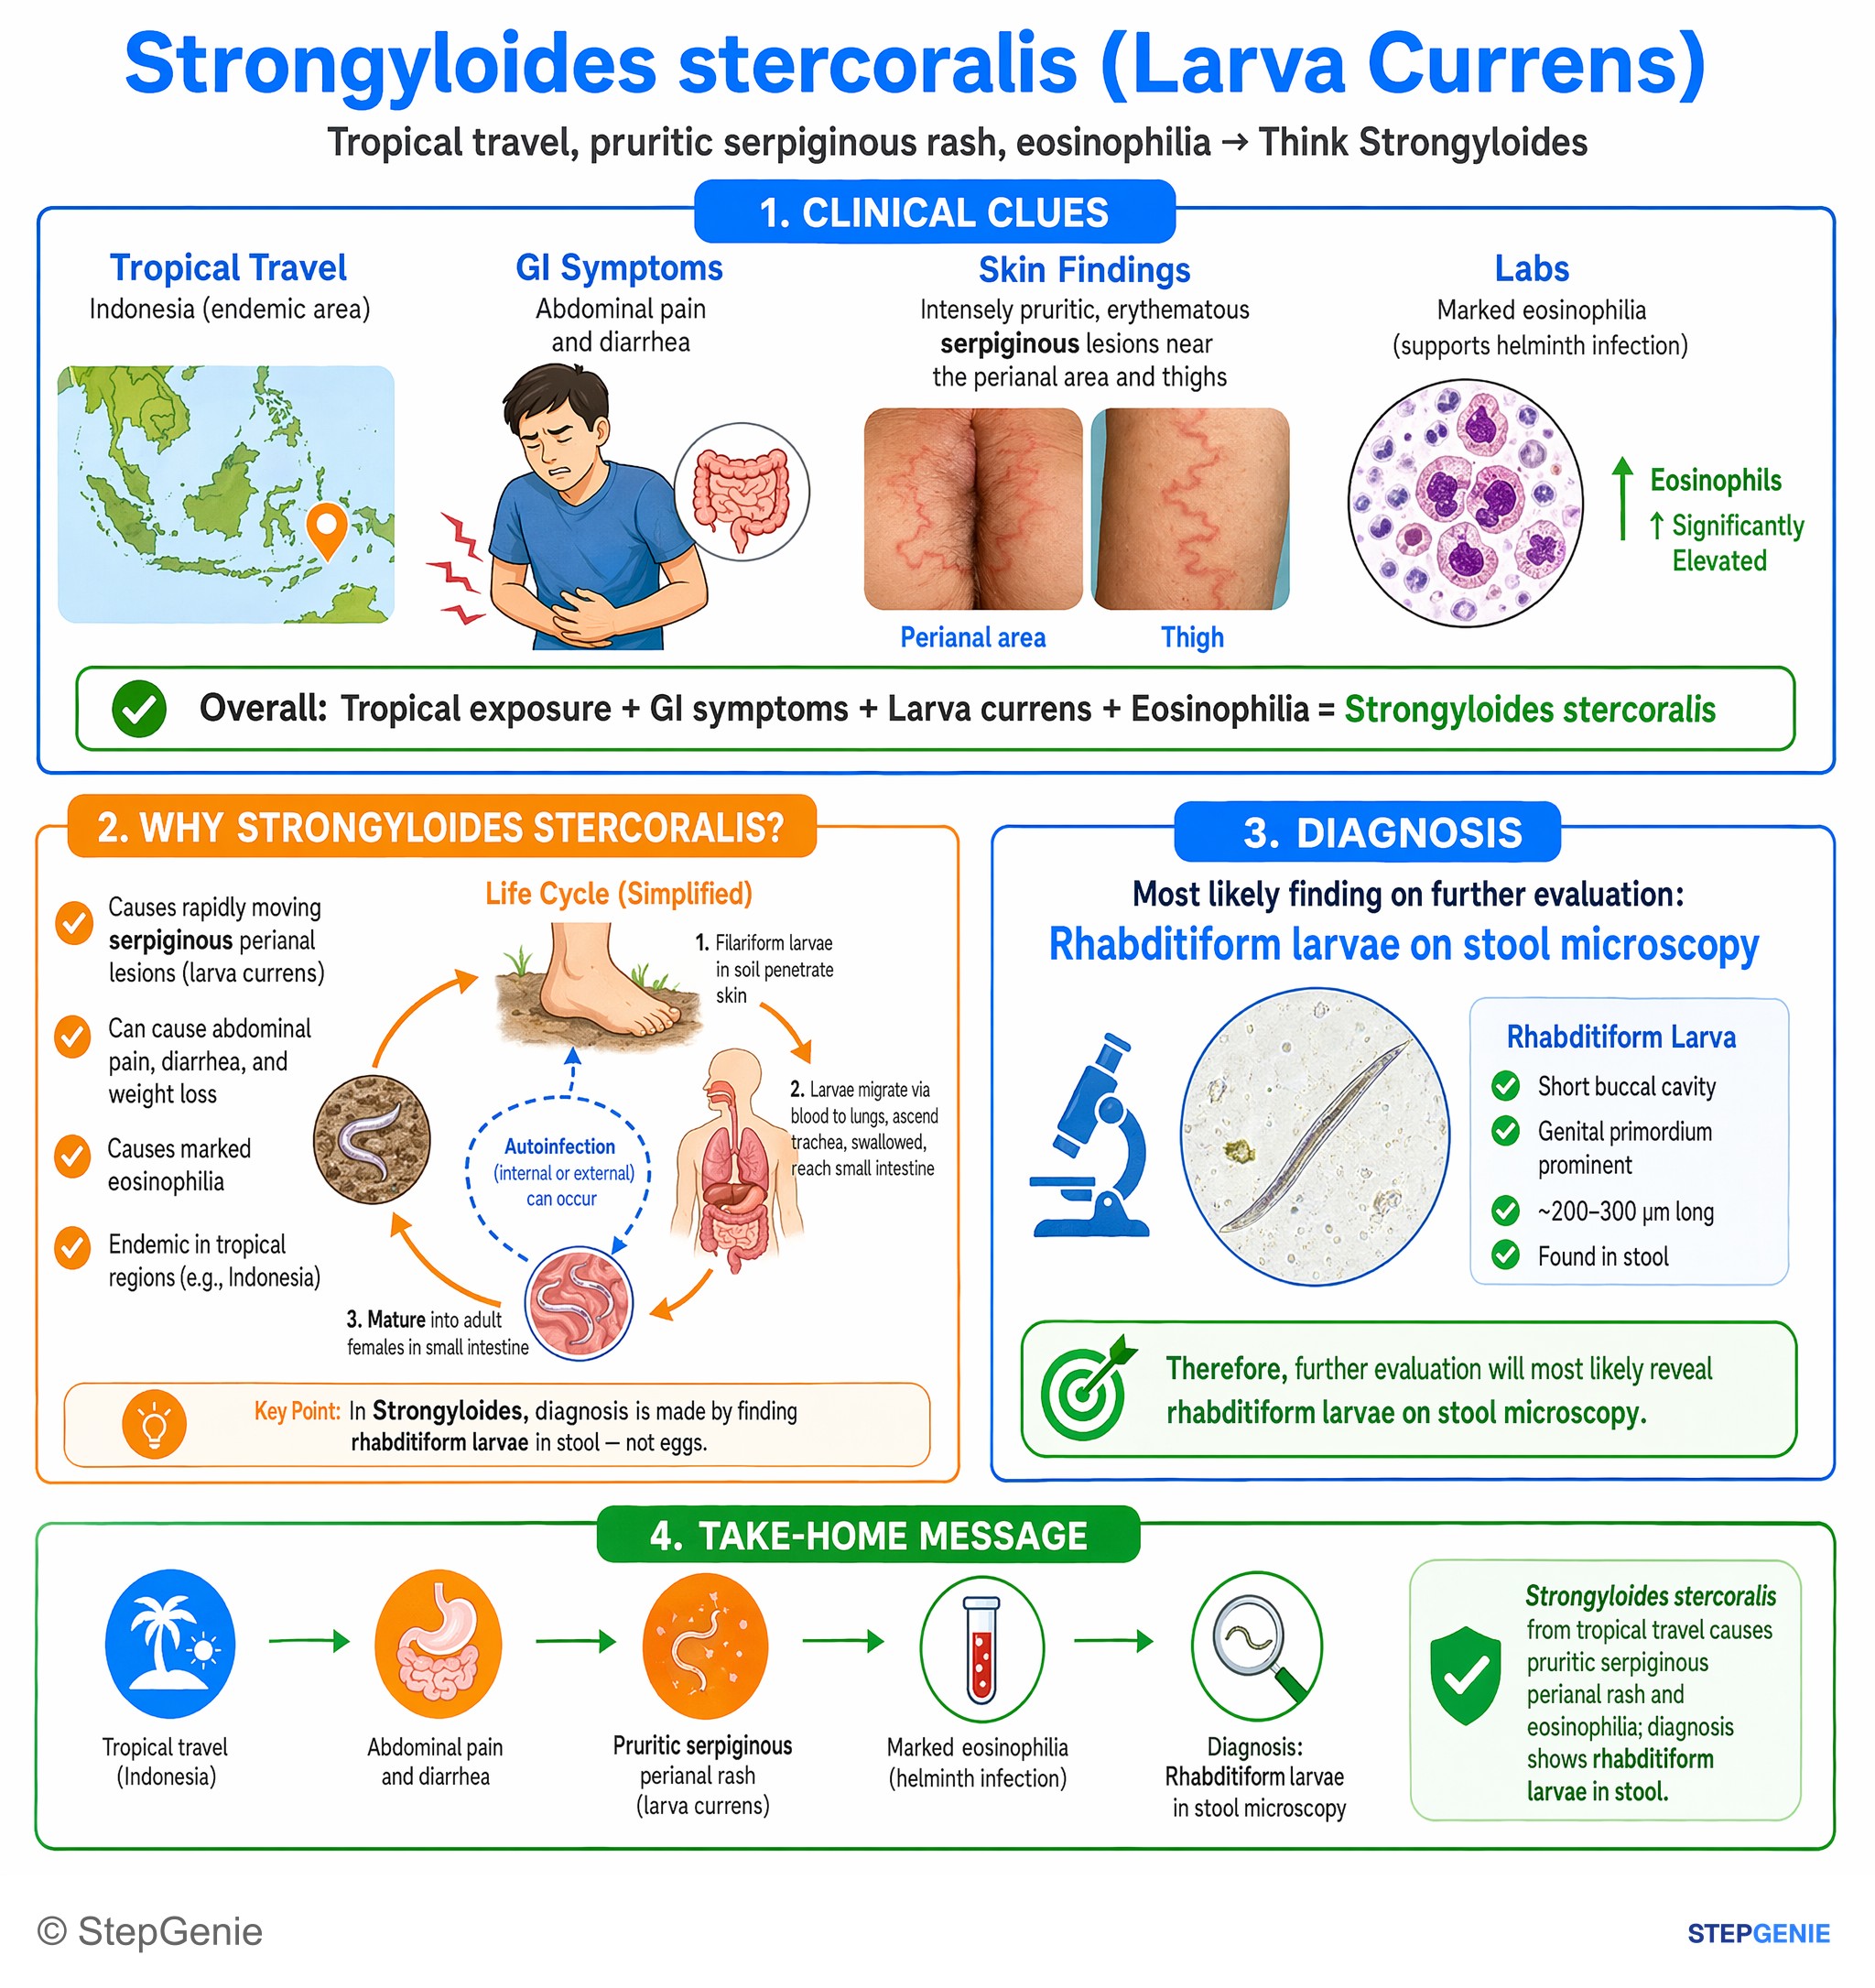
Strongyloides stercoralis from tropical travel causes pruritic serpiginous perianal rash and eosinophilia; diagnosis shows rhabditiform…
USMLE Step 1Frequently Asked Questions
Why do steroids trigger Strongyloides hyperinfection?
Steroids trigger Strongyloides hyperinfection because they suppress host defenses and let larvae proliferate massively. Strongyloides is unusual because it can autoinfect, meaning larvae re-enter through the intestinal mucosa or perianal skin and keep cycling inside the body for years. Glucocorticoids can turn that chronic loop into disseminated disease with worsening GI and pulmonary symptoms, and eosinophilia may even disappear during severe infection.
How does Strongyloides infect the body and complete its life cycle?
Strongyloides enters by skin penetration, typically through the feet, and then follows a lungs-to-gut migration. The infectious form is the filariform larva in soil, which penetrates skin, travels through the bloodstream to the lungs, migrates up the trachea, is swallowed, and matures in the small intestine. Its key feature is autoinfection, where larvae re-enter through intestinal mucosa or perianal skin and continue the cycle inside the host.
What is the classic rash clue for Strongyloides on exams?
The classic rash clue is larva currens, a rapidly migrating, pruritic, serpiginous rash, often involving the perianal area or trunk. Strongyloides can also cause an urticarial rash in chronic infection. This skin finding fits the parasite’s ability to autoinfect by re-entering through perianal skin or intestinal mucosa, which is one reason the infection can persist for decades.
How is Strongyloides diagnosed if the stool test is negative?
A negative stool test does not exclude Strongyloides because larvae are shed intermittently. Stool ova and parasite testing can miss the infection, so repeat testing may be needed, and serology is often helpful and may be more sensitive in chronic infection. In hyperinfection, larvae may also be found in sputum or other body fluids, which is a major diagnostic clue in severe disease.
What is the first-line treatment for Strongyloides?
Ivermectin is the first-line treatment for Strongyloides. It is the go-to therapy for chronic uncomplicated infection, and hyperinfection or disseminated disease is treated with ivermectin plus supportive care, often with prolonged therapy until clearance is confirmed. An exam trap is thinking of albendazole first, but the key board answer for Strongyloides is ivermectin.