Viral pneumonia is lung infection by a respiratory virus; viruses cause up to 30% of community-acquired pneumonia (CAP). The common causes are influenza, RSV, human metapneumovirus (hMPV), parainfluenza, rhinovirus, adenovirus and SARS-CoV-2, while CMV, varicella and measles hit immunocompromised or unvaccinated hosts. The highest-yield trap is secondary bacterial pneumonia after influenza (S. pneumoniae, S. aureus including MRSA, group A strep). Influenza gets oseltamivir as soon as possible, even after 48 hours in hospitalized patients; most other respiratory viruses get supportive care, and RSV is now preventable with an infant antibody (nirsevimab or clesrovimab), a maternal vaccine or an adult vaccine.
The mnemonic: VIP MARCH
Picture a VIP motorcade marching down the trachea. The influenza limousine leads, RSV pushes a baby stroller, adenovirus wears army fatigues, a CMV float carries a transplant cooler, and the hantavirus car has a mouse on the dashboard.
| Letter | Virus | Who / setting | Signature clue | Treat / prevent |
|---|---|---|---|---|
| V | Varicella-zoster virus | Adults, neonates and immunocompromised patients with chickenpox | Pneumonia is the classic complication of adult chickenpox | IV acyclovir; varicella vaccine |
| I | Influenza A and B | Anyone in flu season; worst in high-risk groups | Abrupt fever, chills, myalgia, headache; then the bacterial superinfection trap | Oseltamivir; annual vaccine |
| P | Parainfluenza (HPIV 1-4) | Infants, young children, immunocompromised | HPIV-1 and -2 cause croup; HPIV-3 causes bronchiolitis and pneumonia (spring, early summer) | Supportive; no antiviral |
| M | Metapneumovirus and Measles | hMPV: young children, older adults; measles: unvaccinated | hMPV is the RSV look-alike (late winter, spring); bronchopneumonia is a common measles complication | Supportive; vitamin A for children hospitalized with measles; MMR |
| A | Adenovirus | Military recruits, children, immunocompromised | Respiratory illness; other types cause conjunctivitis, cystitis or gastroenteritis; survives many disinfectants | Supportive; oral type 4 and 7 vaccine for the military only |
| R | RSV (and rhinovirus) | RSV: infants, older adults and immunocompromised people | Bronchiolitis; apnea and irritability in very young infants | Supportive; infant antibody, maternal or adult vaccine |
| C | Coronavirus (SARS-CoV-2) and CMV | COVID-19: older or immunocompromised; CMV: transplant recipients | COVID: bilateral peripheral ground-glass on CT; CMV: "owl's eye" inclusions | COVID: antivirals, dexamethasone if severe; CMV: ganciclovir |
| H | Hantavirus | Contact with deer mouse urine, droppings or saliva | Flu-like illness, then pulmonary edema and shock | Supportive care, ECMO |
Sort the parade by host: infants and toddlers get RSV, hMPV and parainfluenza; healthy adults in winter get influenza, SARS-CoV-2, RSV and rhinovirus; transplant recipients get CMV (in advanced HIV, CMV mainly causes retinitis); the unvaccinated get measles and varicella; and rodent exposure points to hantavirus.
How viral pneumonia looks, and how it differs from bacteria
Viruses inflame the alveolar walls and interstitium rather than filling alveoli with neutrophils, so imaging tends to show interstitial or diffuse infiltrates; severe disease progresses to ARDS. Merck puts it this way for influenza: primary viral pneumonia gives focal or diffuse interstitial infiltrates or ARDS, while secondary bacterial pneumonia is more often lobar or segmental.
| Viral pneumonia | Typical bacterial (e.g., S. pneumoniae) | Atypical bacterial (Mycoplasma, Legionella) | |
|---|---|---|---|
| Story | Season or outbreak, URI prodrome, myalgias | Abrupt fever, rigors, productive cough | Gradual dry cough, exposure clue, extrapulmonary signs |
| X-ray | Interstitial or diffuse, often bilateral | Lobar or segmental consolidation | Patchy bronchopneumonia |
| Key test | Rapid molecular (PCR) panel | Sputum Gram stain and culture, blood cultures | NAAT; Legionella urine antigen |
| Drugs | Virus-specific (oseltamivir, ganciclovir, acyclovir) or none | Beta-lactam | Macrolide, doxycycline or fluoroquinolone |
The atypical bacteria and the animal-borne look-alikes have their own page: the atypical pneumonia visual hack.
The influenza trap: secondary bacterial pneumonia
- The story: fever and cough persist or come back after the flu seemed to be resolving, now with a lobar or segmental consolidation.
- The bugs (CDC): S. pneumoniae, S. aureus including MRSA, and S. pyogenes (group A strep). Bacterial coinfection raises mortality about 3-fold in patients hospitalized with influenza (Merck). Review the staph toxins and MRSA in the S. aureus comparison table.
- Other complications: primary viral pneumonia, ARDS, myocarditis and pericarditis, encephalopathy or encephalitis, sepsis and multiorgan failure.
- Antibiotics with a positive flu test: ATS/IDSA (2019) recommends standard CAP antibiotics for patients with clinical and radiographic pneumonia who test positive for influenza. The 2025 ATS update extends this to any respiratory virus for outpatients with comorbidities and for inpatients, but suggests no antibiotics for outpatients without comorbidities; IDSA did not endorse that update because it favors deciding case by case for comorbid outpatients and nonsevere inpatients.
- Steroids: the 2025 ATS update suggests corticosteroids in severe CAP but excludes influenza pneumonia; in contrast, dexamethasone is the cornerstone of treatment for severe COVID-19 (IDSA).
Diagnosis: what to order
- Influenza: when flu is circulating, ATS/IDSA recommends testing CAP patients with a rapid influenza molecular assay.
- Multiplex NAAT (PCR) panels test one nasopharyngeal swab for many respiratory viruses at once, and most also detect M. pneumoniae (CDC).
- Procalcitonin doesn't decide whether to start antibiotics for CAP (ATS/IDSA 2019).
- CMV: PCR for CMV DNA; tissue histology is the gold standard for invasive disease.
- Hantavirus: IgM ELISA or PCR.
Treatment and prevention by virus
| Virus | Treatment | Prevention |
|---|---|---|
| Influenza | Oseltamivir as soon as possible for hospitalized patients, severe or progressive illness and high-risk outpatients; it still helps inpatients after 48 hours. Zanamivir, peramivir or baloxavir are outpatient options but not routinely recommended for inpatients | Annual vaccine for all eligible people |
| RSV | Supportive (oxygen, fluids, ventilation if needed) | Infant antibody (nirsevimab or clesrovimab), maternal Abrysvo at 32-36 weeks, or a single adult vaccine dose; US eligibility was under litigation in 2026 (see below) |
| SARS-CoV-2 | High-risk outpatients: nirmatrelvir-ritonavir (within 5 days) or remdesivir (within 7 days), molnupiravir as backup; severe disease: dexamethasone | COVID-19 vaccines |
| CMV | Valganciclovir or IV ganciclovir first line; foscarnet or cidofovir second line; maribavir for refractory or resistant disease | Letermovir prophylaxis in some transplant recipients |
| Varicella | IV acyclovir | Varicella vaccine |
| Measles | Supportive; vitamin A for hospitalized children | MMR |
| hMPV, parainfluenza, adenovirus | Supportive; no specific antiviral | No vaccine for hMPV or parainfluenza; adenovirus vaccine for the military only |
| Hantavirus | Supportive; ECMO for cardiopulmonary collapse | Avoid rodent droppings |
RSV prevention: products and US status (October 2026)
- Infant antibodies (passive immunity, not vaccines): nirsevimab (Beyfortus, approved 2023) and clesrovimab (Enflonsia, approved 2025; one 105 mg IM dose) are long-acting monoclonal antibodies against the RSV fusion (F) protein. Both are licensed for infants born during or entering their first RSV season; nirsevimab is also licensed for children up to 24 months who remain vulnerable through a second season. Palivizumab is no longer available after December 31, 2025 (CDC).
- Maternal vaccine: Abrysvo is the only RSV vaccine licensed in pregnancy, given at 32-36 weeks' gestation to protect the baby from birth through 6 months.
- Adult vaccines: Arexvy, Abrysvo and mResvia are licensed for adults 60 or older and adults 18-59 at increased risk; RSV vaccine is a single dose, not an annual shot.
- Who should get them is under litigation: in January 2026 a revised federal childhood schedule moved infant RSV antibodies from all infants to "certain high-risk groups". On March 16, 2026, a federal court in Massachusetts (AAP v. Kennedy) stayed that schedule and the vaccine-recommendation changes made after June 11, 2025, including the reconstituted ACIP's votes; the government appealed to the First Circuit, and the stay was still in effect in September 2026. The Congressional Research Service says the nirsevimab recommendation and the April 2025 adult recommendation remain in effect, but that it is unclear whether the June 2025 clesrovimab recommendation does.
- What CDC's pages say now: the infant page (last updated August 2025) recommends one infant antibody for infants under 8 months entering their first season unless the mother received Abrysvo at least 14 days before birth (most babies need only one of the two), plus nirsevimab for some high-risk children aged 8-19 months; the adult page (February 2026) recommends one dose for everyone 75 or older and for adults 50-74 at increased risk. Check CDC's current RSV guidance before relying on eligibility details. More RSV virology is in RSV for Step 1.
How USMLE tests it
- Hospitalized flu patient on day 4 of symptoms: still give oseltamivir; the 48-hour window applies to healthy outpatients.
- Amantadine or rimantadine is a wrong answer: high resistance among circulating influenza A viruses.
- Mechanisms: oseltamivir, zanamivir and peramivir inhibit neuraminidase (virions can't be released); baloxavir inhibits the cap-dependent endonuclease (blocks viral RNA transcription). Drift and shift are in the influenza antigenic drift vs shift cheat sheet.
- Taxonomy: RSV and hMPV are now Pneumoviridae; parainfluenza stays in Paramyxoviridae (older texts lump them together as paramyxoviruses).
- Barking cough in a toddler: parainfluenza croup. Infant bronchiolitis: RSV.
- Transplant recipient with diffuse infiltrates and owl's eye inclusions: CMV, treat with ganciclovir. Compare the other herpesviruses in the herpesvirus guide.
- Military recruit with pneumonia and conjunctivitis: adenovirus; more in the adenovirus question breakdown.
Practice question
A 70-year-old woman with COPD has had fever, myalgias and cough for 4 days. She is short of breath, with an oxygen saturation of 89% on room air. Chest X-ray shows bilateral interstitial infiltrates. A nasopharyngeal rapid molecular test is positive for influenza A. She is admitted, and ceftriaxone plus azithromycin are started for community-acquired pneumonia. Which is the most appropriate antiviral management?
A. No antiviral, because symptoms began more than 48 hours ago B. Oral oseltamivir now C. Oral amantadine D. Inhaled zanamivir E. A single dose of oral baloxavir
Answer: B. CDC recommends antiviral treatment as soon as possible for any hospitalized patient with influenza, and treatment still helps hospitalized and severely ill patients when started after 48 hours. Oseltamivir is the recommended drug for inpatients. ATS/IDSA also recommends it for influenza-positive CAP regardless of illness duration, alongside standard antibiotics because of possible bacterial coinfection.
- A: the 48-hour cut-off applies to otherwise healthy outpatients; hospitalized patients are treated regardless.
- C: adamantanes are not recommended because circulating influenza A viruses are highly resistant.
- D: inhaled zanamivir is not routinely recommended for hospitalized patients, and CDC advises against it in asthma or COPD because of bronchospasm.
- E: baloxavir is not routinely recommended for hospitalized patients because there is too little evidence of benefit.
Key takeaways
- VIP MARCH: Varicella, Influenza, Parainfluenza, Metapneumovirus and Measles, Adenovirus, RSV and Rhinovirus, Coronavirus and CMV, Hantavirus.
- Viral = interstitial or diffuse infiltrates; bacterial superinfection = lobar or segmental consolidation, classically after influenza.
- Post-flu bacteria: S. pneumoniae, S. aureus (including MRSA), S. pyogenes.
- Oseltamivir for every hospitalized flu patient, even after 48 hours; no adamantanes.
- RSV prevention: infant antibodies (nirsevimab, clesrovimab), Abrysvo at 32-36 weeks of pregnancy and single-dose adult vaccines; US eligibility rules were under litigation in 2026, so check CDC.
- Positive viral test: ATS 2025 suggests skipping antibiotics only in outpatients without comorbidities; IDSA, which did not endorse that update, favors case-by-case decisions.
Sources
- Community-Acquired Pneumonia — Merck Manual Professional Edition (2026)
- Influenza — Merck Manual Professional Edition (2026)
- Influenza Antiviral Medications: Summary for Clinicians — CDC (2026)
- Clinical Signs and Symptoms of Influenza — CDC (2026)
- Diagnosis and Treatment of Adults with Community-acquired Pneumonia: Executive Summary — ATS/IDSA (2019)
- Diagnosis and Management of Community-acquired Pneumonia: An Official ATS Clinical Practice Guideline — American Journal of Respiratory and Critical Care Medicine (2025)
- IDSA Position Statement: Why IDSA Did Not Endorse the Community-Acquired Pneumonia Guidelines 2025 Update — Clinical Infectious Diseases (2026)
- RSV Immunization Guidance for Infants and Young Children — CDC (2025)
- RSV Vaccine Guidance for Adults — CDC (2026)
- Changes to CDC Vaccine Recommendations in 2025 and 2026 — Congressional Research Service, via EveryCRSReport (2026)
- ENFLONSIA (clesrovimab-cfor) Injection: Prescribing Information — DailyMed, National Library of Medicine (2025)
- Cytomegalovirus (CMV) Infection — Merck Manual Professional Edition (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
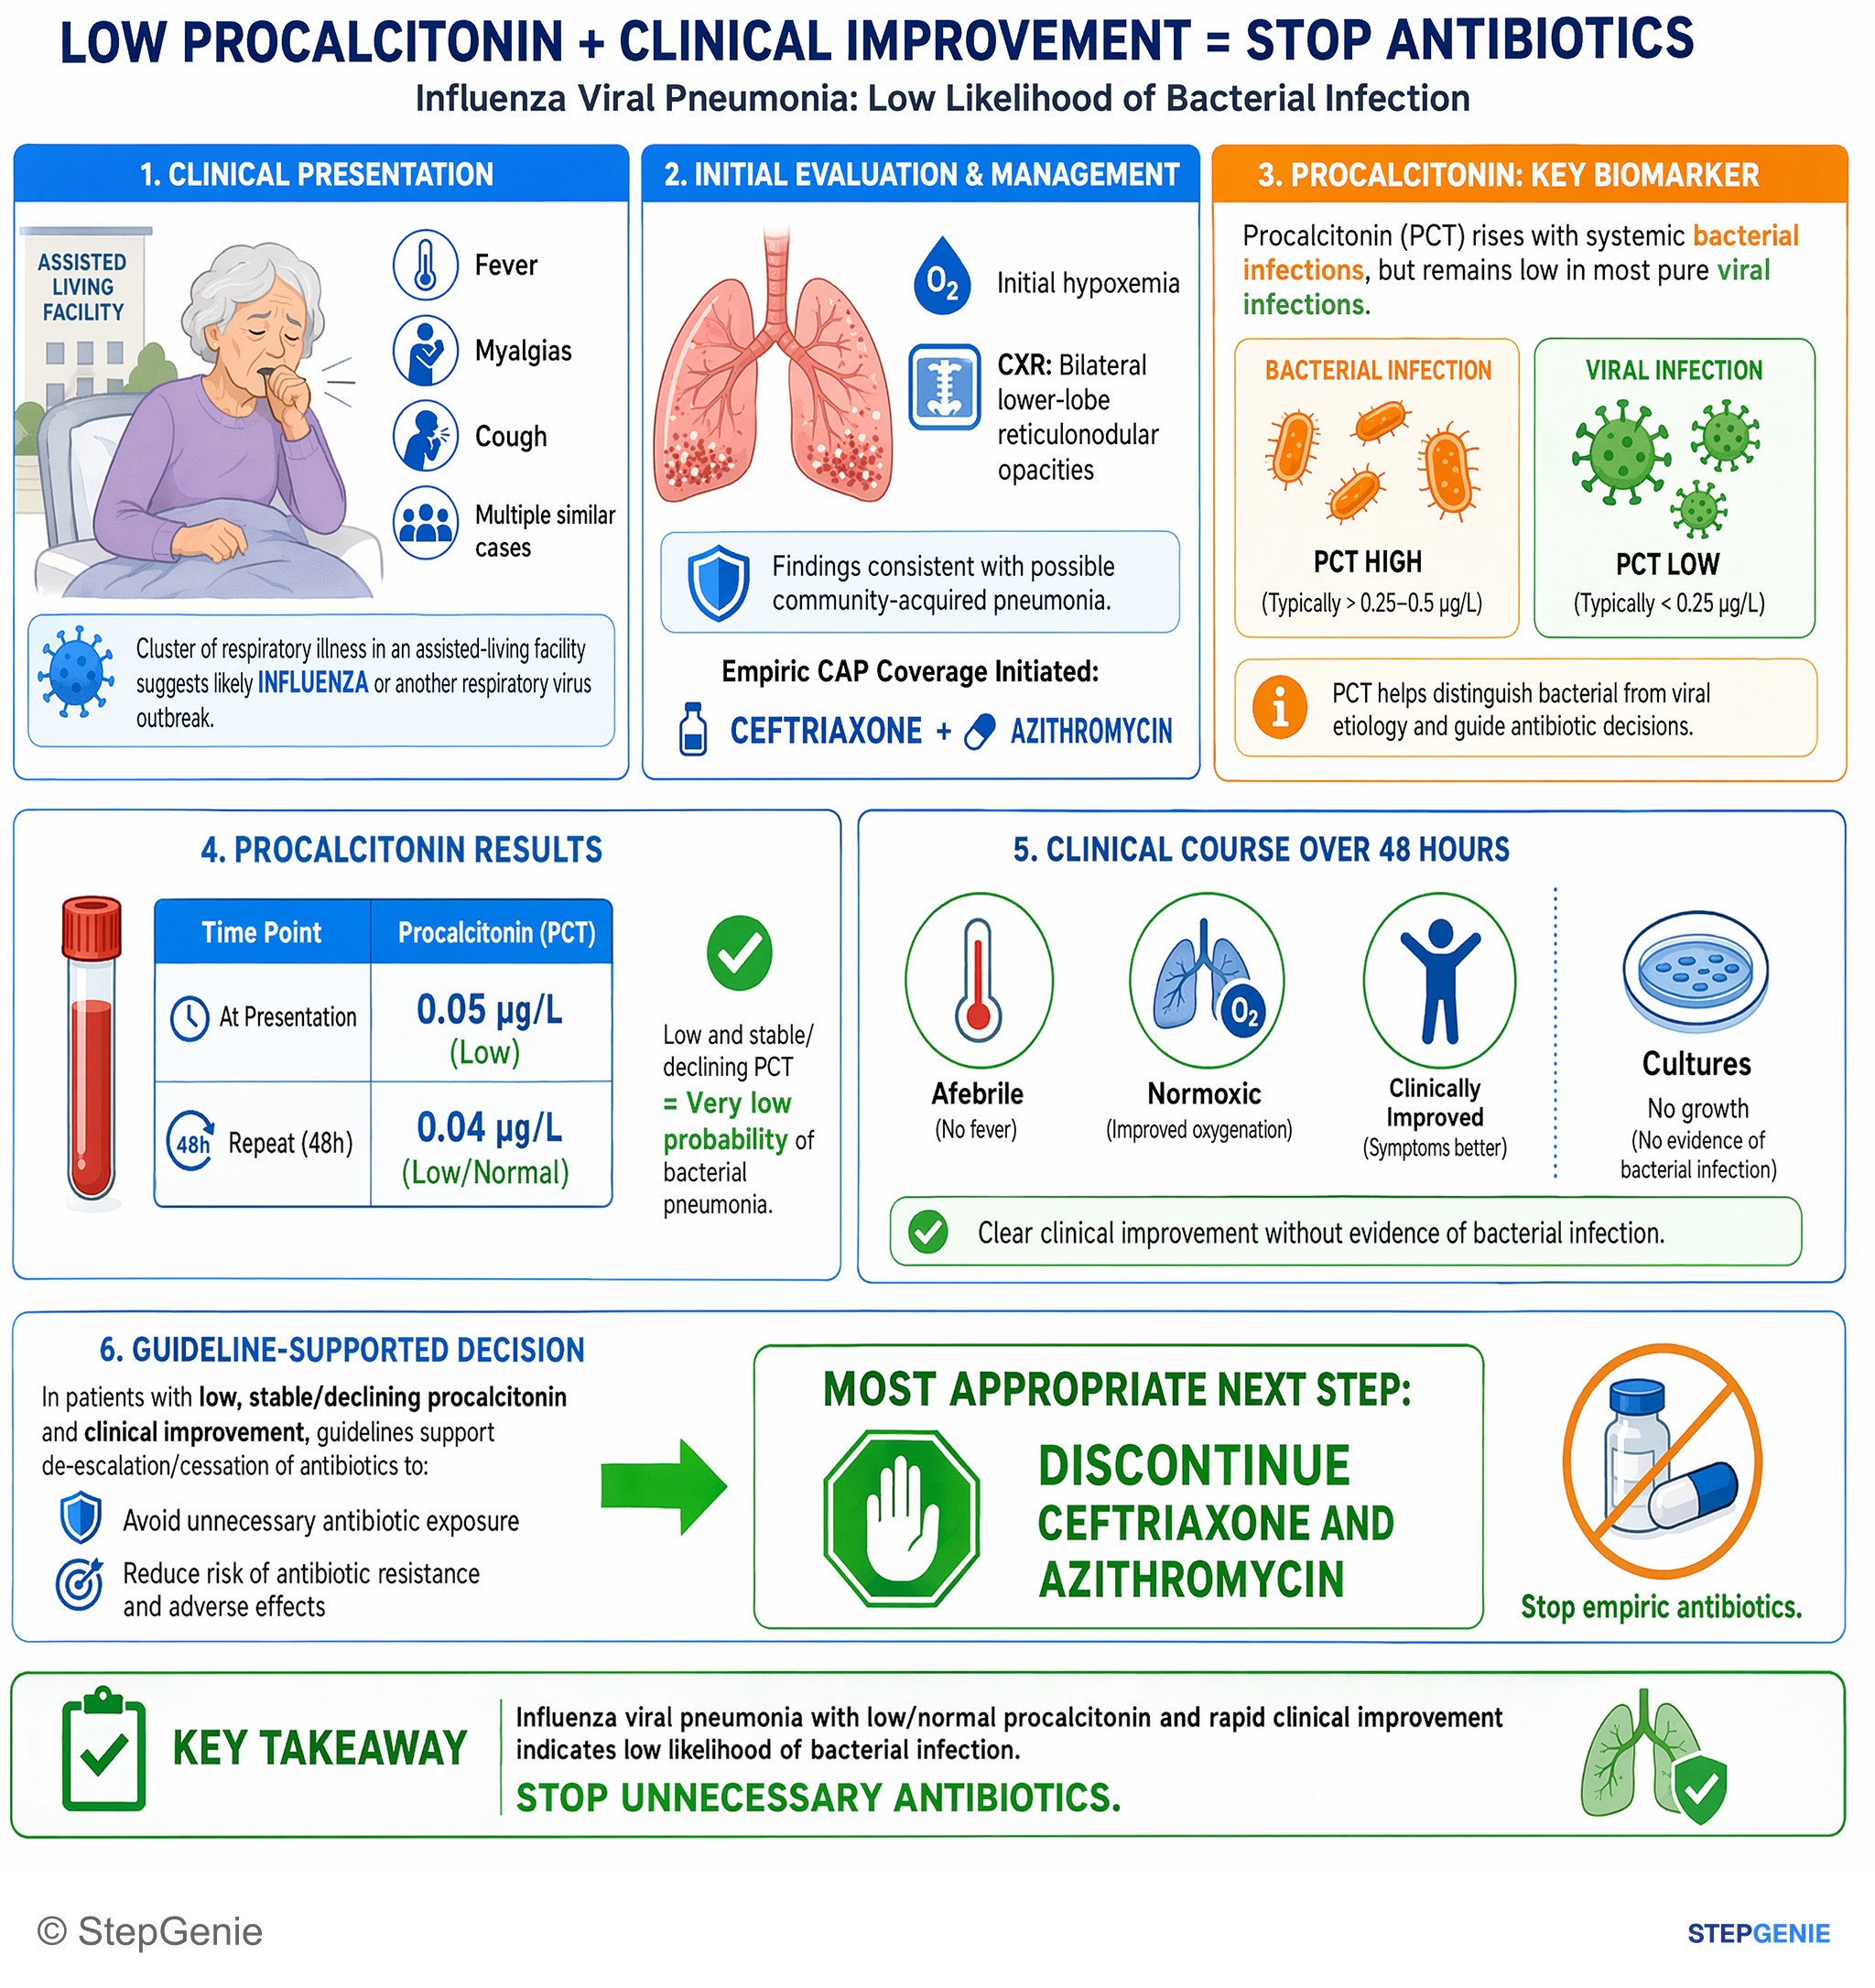
Influenza viral pneumonia with low/normal procalcitonin and rapid clinical improvement indicates low likelihood of bacterial infection…
USMLE Step 2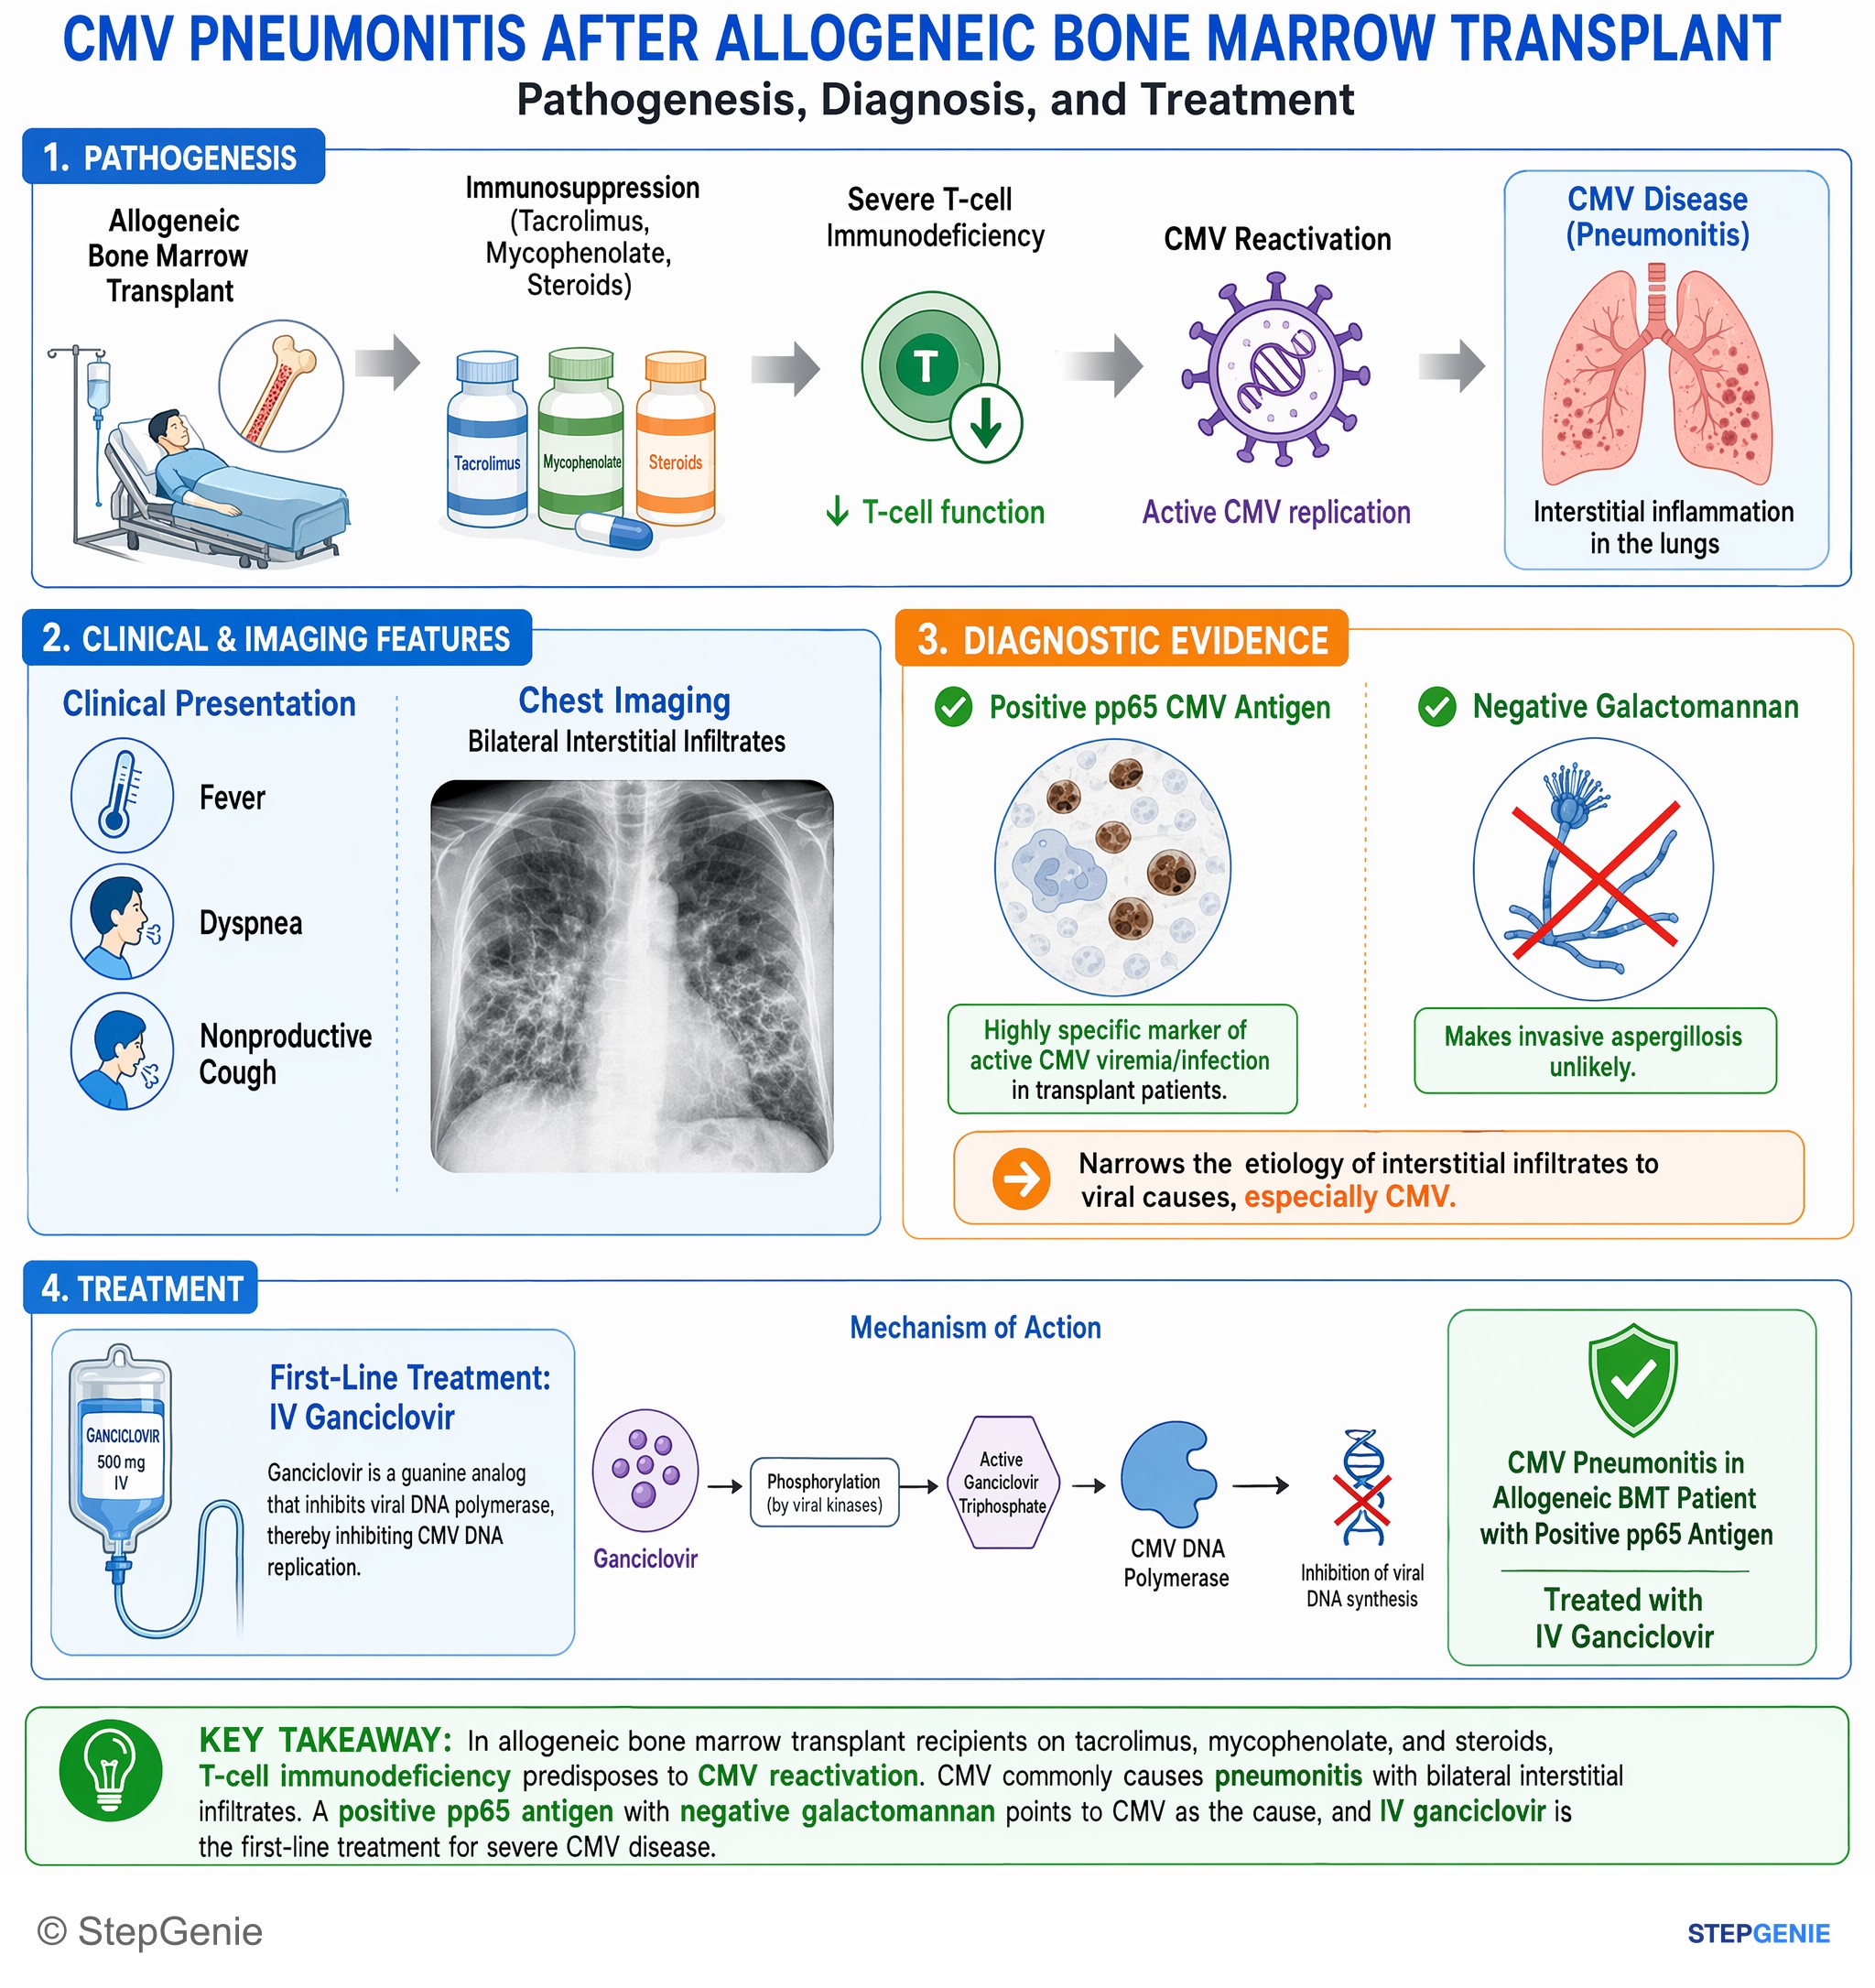
CMV pneumonitis in an allogeneic bone marrow transplant patient with positive pp65 antigen is treated with IV ganciclovir.
USMLE Step 2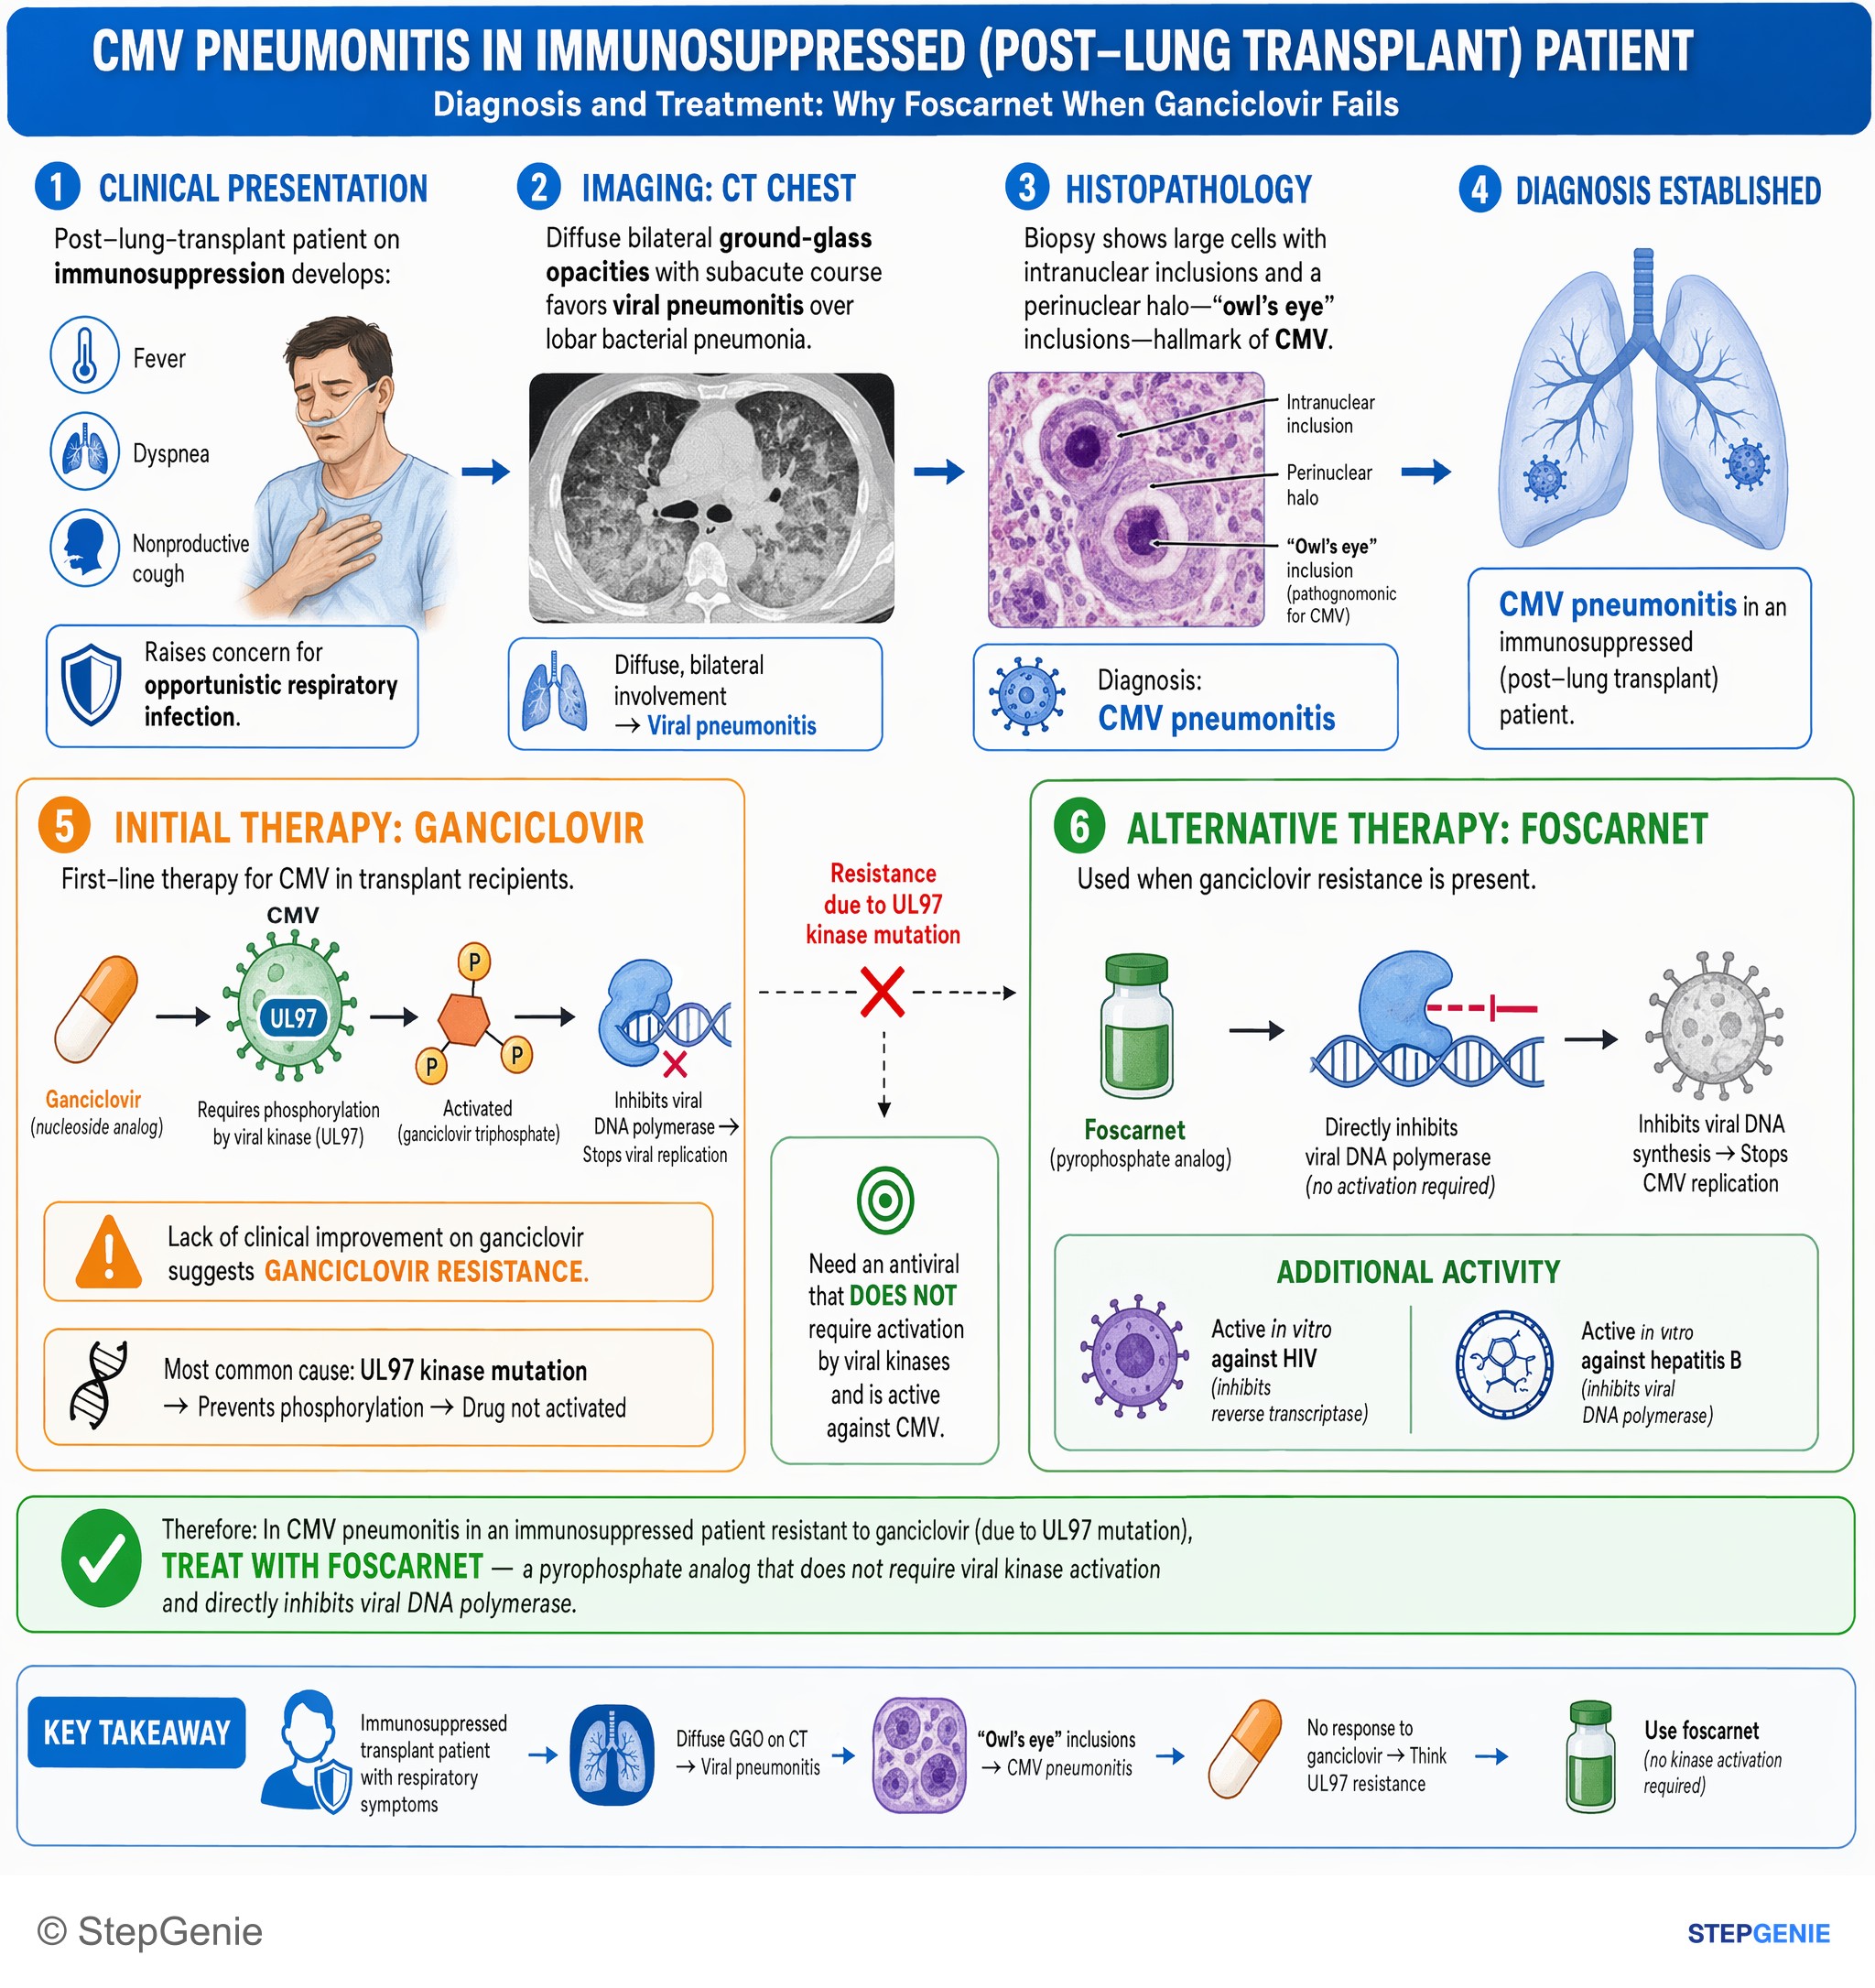
CMV pneumonitis in immunosuppressed patient resistant to ganciclovir → treat with foscarnet, a pyrophosphate analog that does not require…
USMLE Step 1Frequently Asked Questions
What are the most common causes of viral pneumonia?
Viruses cause up to 30 percent of community-acquired pneumonia. The common community causes are influenza, respiratory syncytial virus (RSV), human metapneumovirus, parainfluenza viruses, rhinovirus, adenovirus and coronaviruses, including SARS-CoV-2. In immunocompromised patients, especially transplant recipients, cytomegalovirus (CMV) becomes important, and varicella and measles cause pneumonia mainly in unvaccinated or immunocompromised people. Hantavirus causes a severe pulmonary syndrome after contact with deer mouse urine, droppings or saliva.
What is a good mnemonic for the causes of viral pneumonia?
VIP MARCH: picture a VIP motorcade marching down the trachea. V is varicella-zoster virus, I is influenza, P is parainfluenza, M is metapneumovirus and measles, A is adenovirus, R is RSV and rhinovirus, C is coronavirus (SARS-CoV-2) and cytomegalovirus, and H is hantavirus. Each letter carries one clue: croup for parainfluenza, infant bronchiolitis for RSV, military recruits for adenovirus, transplant recipients for CMV and deer mouse droppings for hantavirus.
How do you tell viral pneumonia from bacterial pneumonia?
Viral pneumonia inflames the alveolar walls and interstitium, so the chest X-ray usually shows interstitial or diffuse, often bilateral, infiltrates, while typical bacterial pneumonia more often causes lobar or segmental consolidation. A rapid molecular test or multiplex PCR panel on a nasopharyngeal swab identifies the virus. Because bacterial coinfection cannot be excluded, the 2025 ATS guideline suggests antibiotics for patients with pneumonia and a positive viral test unless they are otherwise healthy outpatients, while IDSA prefers case-by-case decisions. Procalcitonin does not decide whether to start them.
What bacteria cause secondary pneumonia after influenza?
The classic organisms are Streptococcus pneumoniae, Staphylococcus aureus, including MRSA, and Streptococcus pyogenes (group A strep). The typical story is a patient whose flu seemed to be resolving who then develops recurrent or persistent fever and cough with a new lobar or segmental consolidation. Bacterial coinfection raises the risk of death about threefold in patients hospitalized with influenza, so these patients need antibiotics in addition to an influenza antiviral such as oseltamivir.
Should hospitalized patients with influenza get oseltamivir after 48 hours of symptoms?
Yes. CDC recommends antiviral treatment as soon as possible for every hospitalized patient with suspected or confirmed influenza, and treatment still has clinical benefit in hospitalized and severely ill patients when it is started more than 48 hours after symptoms begin. Oral or enteric oseltamivir is the recommended drug for inpatients. Inhaled zanamivir, intravenous peramivir and oral baloxavir are not routinely recommended for hospitalized patients, and amantadine and rimantadine are not recommended because of resistance.
How is RSV prevented in infants and older adults?
Three kinds of products exist. Infants can receive a long-acting monoclonal antibody against the RSV F protein, nirsevimab (Beyfortus) or clesrovimab (Enflonsia), both licensed for babies born during or entering their first RSV season. Pregnant women can receive the Abrysvo vaccine at 32 to 36 weeks to protect the baby for its first 6 months. Older and high-risk adults can receive a single dose of Arexvy, Abrysvo or mResvia. As of October 2026, US recommendations on who should receive these products were tied up in federal litigation, so check CDC's current guidance.