You’re doing a q-bank block on asthma and it feels like every question is “wheeze + cough = pick albuterol”… until the test writers start slipping in distractors that are almost right. This post breaks down a classic Step-style asthma vignette the way you should review it: pick the best answer and learn why the other options are wrong (or right in a different scenario).
Tag: Pulmonary > Obstructive Lung Disease
The Vignette (USMLE-Style)
A 19-year-old woman comes to clinic for episodic shortness of breath and chest tightness for the past year. Symptoms are worse at night and with exercise. She has allergic rhinitis and eczema. Exam is normal between episodes. Spirometry shows:
- FEV/FVC: decreased
- FEV: 70% predicted
- After inhaled bronchodilator: FEV increases by 18%
Which of the following is the most appropriate long-term therapy?
A. Inhaled albuterol as needed
B. Inhaled ipratropium
C. Inhaled corticosteroid daily
D. Oral prednisone daily
E. Montelukast monotherapy
F. Omalizumab
G. Inhaled salmeterol monotherapy
H. Propranolol
Step 1: Identify the Core Diagnosis
This is asthma based on:
- Episodic symptoms with triggers (nighttime, exercise)
- Atopy (eczema, allergic rhinitis)
- Obstructive pattern on spirometry (low FEV/FVC)
- Reversibility: FEV increase 12% and 200 mL after bronchodilator strongly supports asthma (the stem gives 18%)
Pathophysiology in One Pass (High-Yield)
Asthma is due to airway hyperresponsiveness and reversible airflow obstruction from:
- Bronchoconstriction (acute)
- Mucus hypersecretion
- Airway edema/inflammation
- Airway remodeling (chronic): subepithelial fibrosis, smooth muscle hypertrophy → can make obstruction less reversible over time
Immunology buzzwords (Step 1 favorites):
- Th2 skew → IL-4 (IgE class switching), IL-5 (eosinophils), IL-13 (mucus)
- Eosinophils, mast cells
- Curschmann spirals and Charcot–Leyden crystals (eosinophil-derived) can show up in sputum
Step 2: Pick the Best Answer (and Why)
✅ Correct Answer: C. Inhaled corticosteroid daily
Her spirometry suggests asthma, and her symptoms are not described as “rare” or “only occasional.” With an FEV around 70% predicted and nighttime symptoms implied, she fits at least persistent asthma. For persistent asthma, daily inhaled corticosteroids (ICS) are the foundation of long-term control.
Why ICS are the cornerstone
- They reduce airway inflammation
- Decrease mucus production
- Decrease airway hyperresponsiveness
- Reduce exacerbations and improve lung function over time
Mechanism (Step 1 version):
- Glucocorticoid receptor activation → altered gene transcription → ↓ inflammatory cytokines, ↓ eosinophils, ↓ vascular permeability
Classic adverse effects
- Oropharyngeal candidiasis, dysphonia
- Mitigation: spacer + rinse mouth after use
Step 3: Why Every Distractor Is There (and When It Would Be Right)
Below is the real value: learning the “if/then” logic behind wrong answers.
A. Inhaled albuterol as needed (SABA)
Why it’s tempting: it treats symptoms quickly.
Why it’s wrong here: SABA is rescue, not controller. For persistent asthma, you need an anti-inflammatory controller (ICS).
When it’s correct:
- Intermittent asthma (symptoms <2 days/week, nighttime <2/month, normal FEV between episodes)
- Also used before exercise for exercise-induced bronchoconstriction
High-yield mechanism: agonist → ↑ cAMP → bronchodilation
Toxicity: tremor, tachycardia, hypokalemia
B. Inhaled ipratropium (SAMA)
Why it’s tempting: bronchodilator, used in obstructive lung disease.
Why it’s wrong: ipratropium is not first-line controller for asthma.
When it’s correct:
- COPD maintenance (more classic)
- Acute asthma exacerbation adjunct with SABA in the ED (especially moderate–severe)
Mechanism: muscarinic (M3) antagonism → ↓ bronchoconstriction
Side effects: dry mouth, urinary retention (minimal systemic absorption inhaled)
D. Oral prednisone daily
Why it’s tempting: steroids treat asthma inflammation.
Why it’s wrong: chronic oral steroids have major systemic toxicity and are reserved for severe, refractory asthma when other therapies fail.
When it’s correct:
- Acute exacerbation (short course of systemic steroids)
- Severe persistent asthma not controlled on maximal inhaled therapy (specialist territory)
Classic chronic steroid toxicities: osteoporosis, diabetes, adrenal suppression, cataracts, glaucoma, skin thinning, proximal myopathy
E. Montelukast monotherapy
Why it’s tempting: asthma + atopy; leukotrienes are involved.
Why it’s wrong: leukotriene receptor antagonists are generally adjuncts, and ICS are preferred first-line for persistent asthma.
When it’s correct (or reasonable):
- Aspirin-exacerbated respiratory disease (AERD): asthma + nasal polyps + aspirin sensitivity
- Exercise-induced bronchoconstriction prophylaxis
- Patients who can’t/won’t use ICS (less effective)
Mechanism: blocks CysLT receptor → ↓ leukotriene-mediated bronchoconstriction and mucus
High-yield adverse effect: neuropsychiatric symptoms (boxed warning; know the association)
F. Omalizumab
Why it’s tempting: “allergic asthma” clues (eczema, rhinitis).
Why it’s wrong: it’s for moderate–severe persistent allergic asthma not controlled on standard therapy (ICS ± LABA), typically with elevated IgE and sensitization.
When it’s correct:
- Allergic asthma with frequent symptoms/exacerbations despite optimized controller therapy
Mechanism: anti-IgE monoclonal antibody → decreases free IgE and downstream mast cell activation
Risk: anaphylaxis (rare but tested)
G. Inhaled salmeterol monotherapy (LABA alone)
Why it’s tempting: long-acting bronchodilation sounds like “long-term control.”
Why it’s wrong (very high-yield): LABA monotherapy increases asthma-related deaths. LABAs must be paired with an ICS in asthma.
When it’s correct:
- COPD can use LABA alone
- Asthma: only as add-on therapy to ICS when not controlled
Mechanism: agonist bronchodilation (long-acting)
H. Propranolol
Why it’s tempting: sometimes q-banks test drug-induced bronchospasm.
Why it’s wrong: nonselective -blockers ( blockade) can precipitate bronchospasm and blunt response to albuterol.
When it’s relevant:
- A patient with asthma worsening after starting a nonselective -blocker (propranolol, nadolol, timolol eye drops can also do it)
- If a -blocker is required, use -selective agents (metoprolol, atenolol) cautiously
Rapid-Fire High-Yield Table: Asthma Meds by Job
| Medication/Class | Role in Asthma | Key Point USMLE Loves |
|---|---|---|
| SABA (albuterol) | Rescue | Acute relief; pre-exercise |
| ICS (fluticasone, budesonide) | Controller #1 | Decreases inflammation; rinse mouth |
| LABA (salmeterol, formoterol) | Controller add-on | Never alone in asthma |
| LAMA/SAMA (tiotropium/ipratropium) | COPD mainstay; asthma adjunct | Ipratropium helps in acute exacerbations |
| Leukotriene modifiers (montelukast, zafirlukast) | Adjunct/alternative | AERD + exercise; neuropsychiatric effects |
| Systemic steroids | Exacerbations; severe refractory control | Huge side-effect burden long-term |
| Omalizumab | Severe allergic asthma | Anti-IgE; anaphylaxis risk |
How This Shows Up on Step Questions
1) “Reversible obstruction” clue
If they give spirometry with bronchodilator response, mentally lock in:
- Obstructive baseline + reversibility → asthma
2) Symptoms drive step-up therapy
They’ll force you to choose between:
- “Just use albuterol” vs “start ICS”
- The trick: persistent symptoms = controller therapy
3) Monotherapy traps
- LABA alone in asthma = no
- Oral prednisone daily for routine control = no
- Montelukast alone = usually not first-line
Takeaway: The One-Sentence Rule
If the vignette suggests persistent asthma, the best long-term answer is almost always daily inhaled corticosteroids, and most distractors are either rescue meds, adjuncts, or for severe refractory disease.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
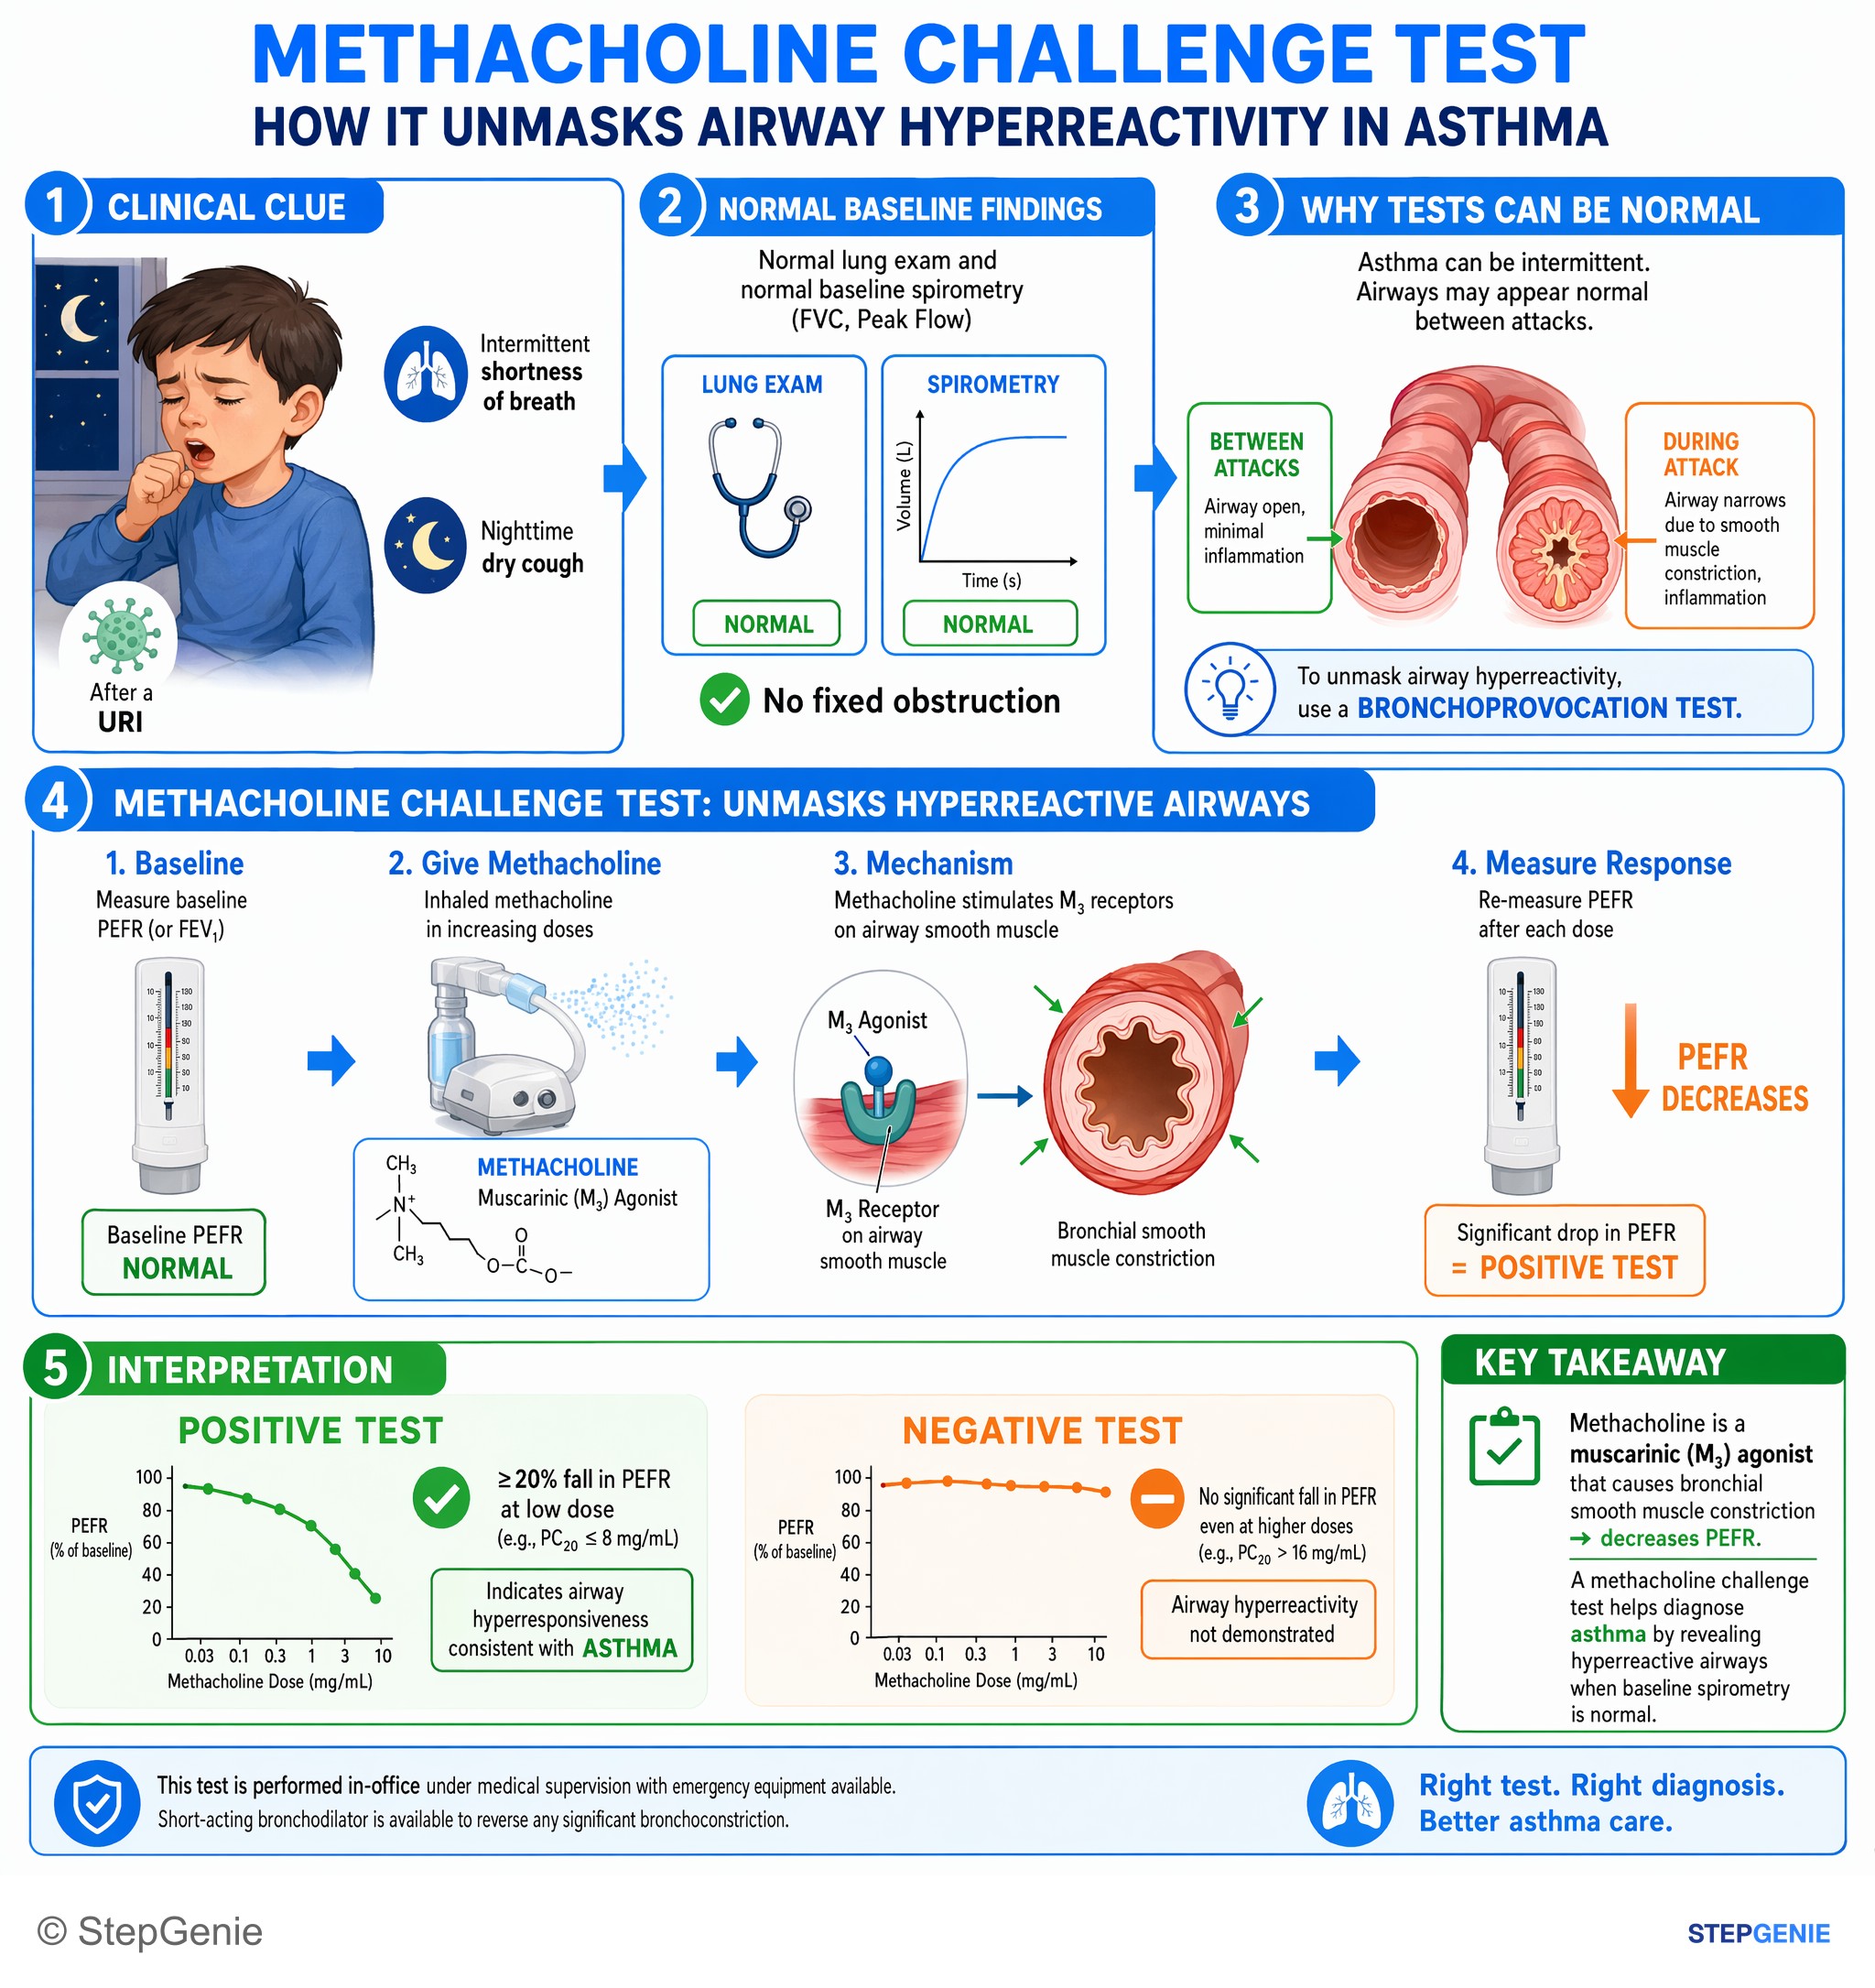
Asthma diagnosis uses methacholine challenge: muscarinic agonist causes bronchoconstriction → ↓PEFR in hyperreactive (asthmatic) airways…
USMLE Step 1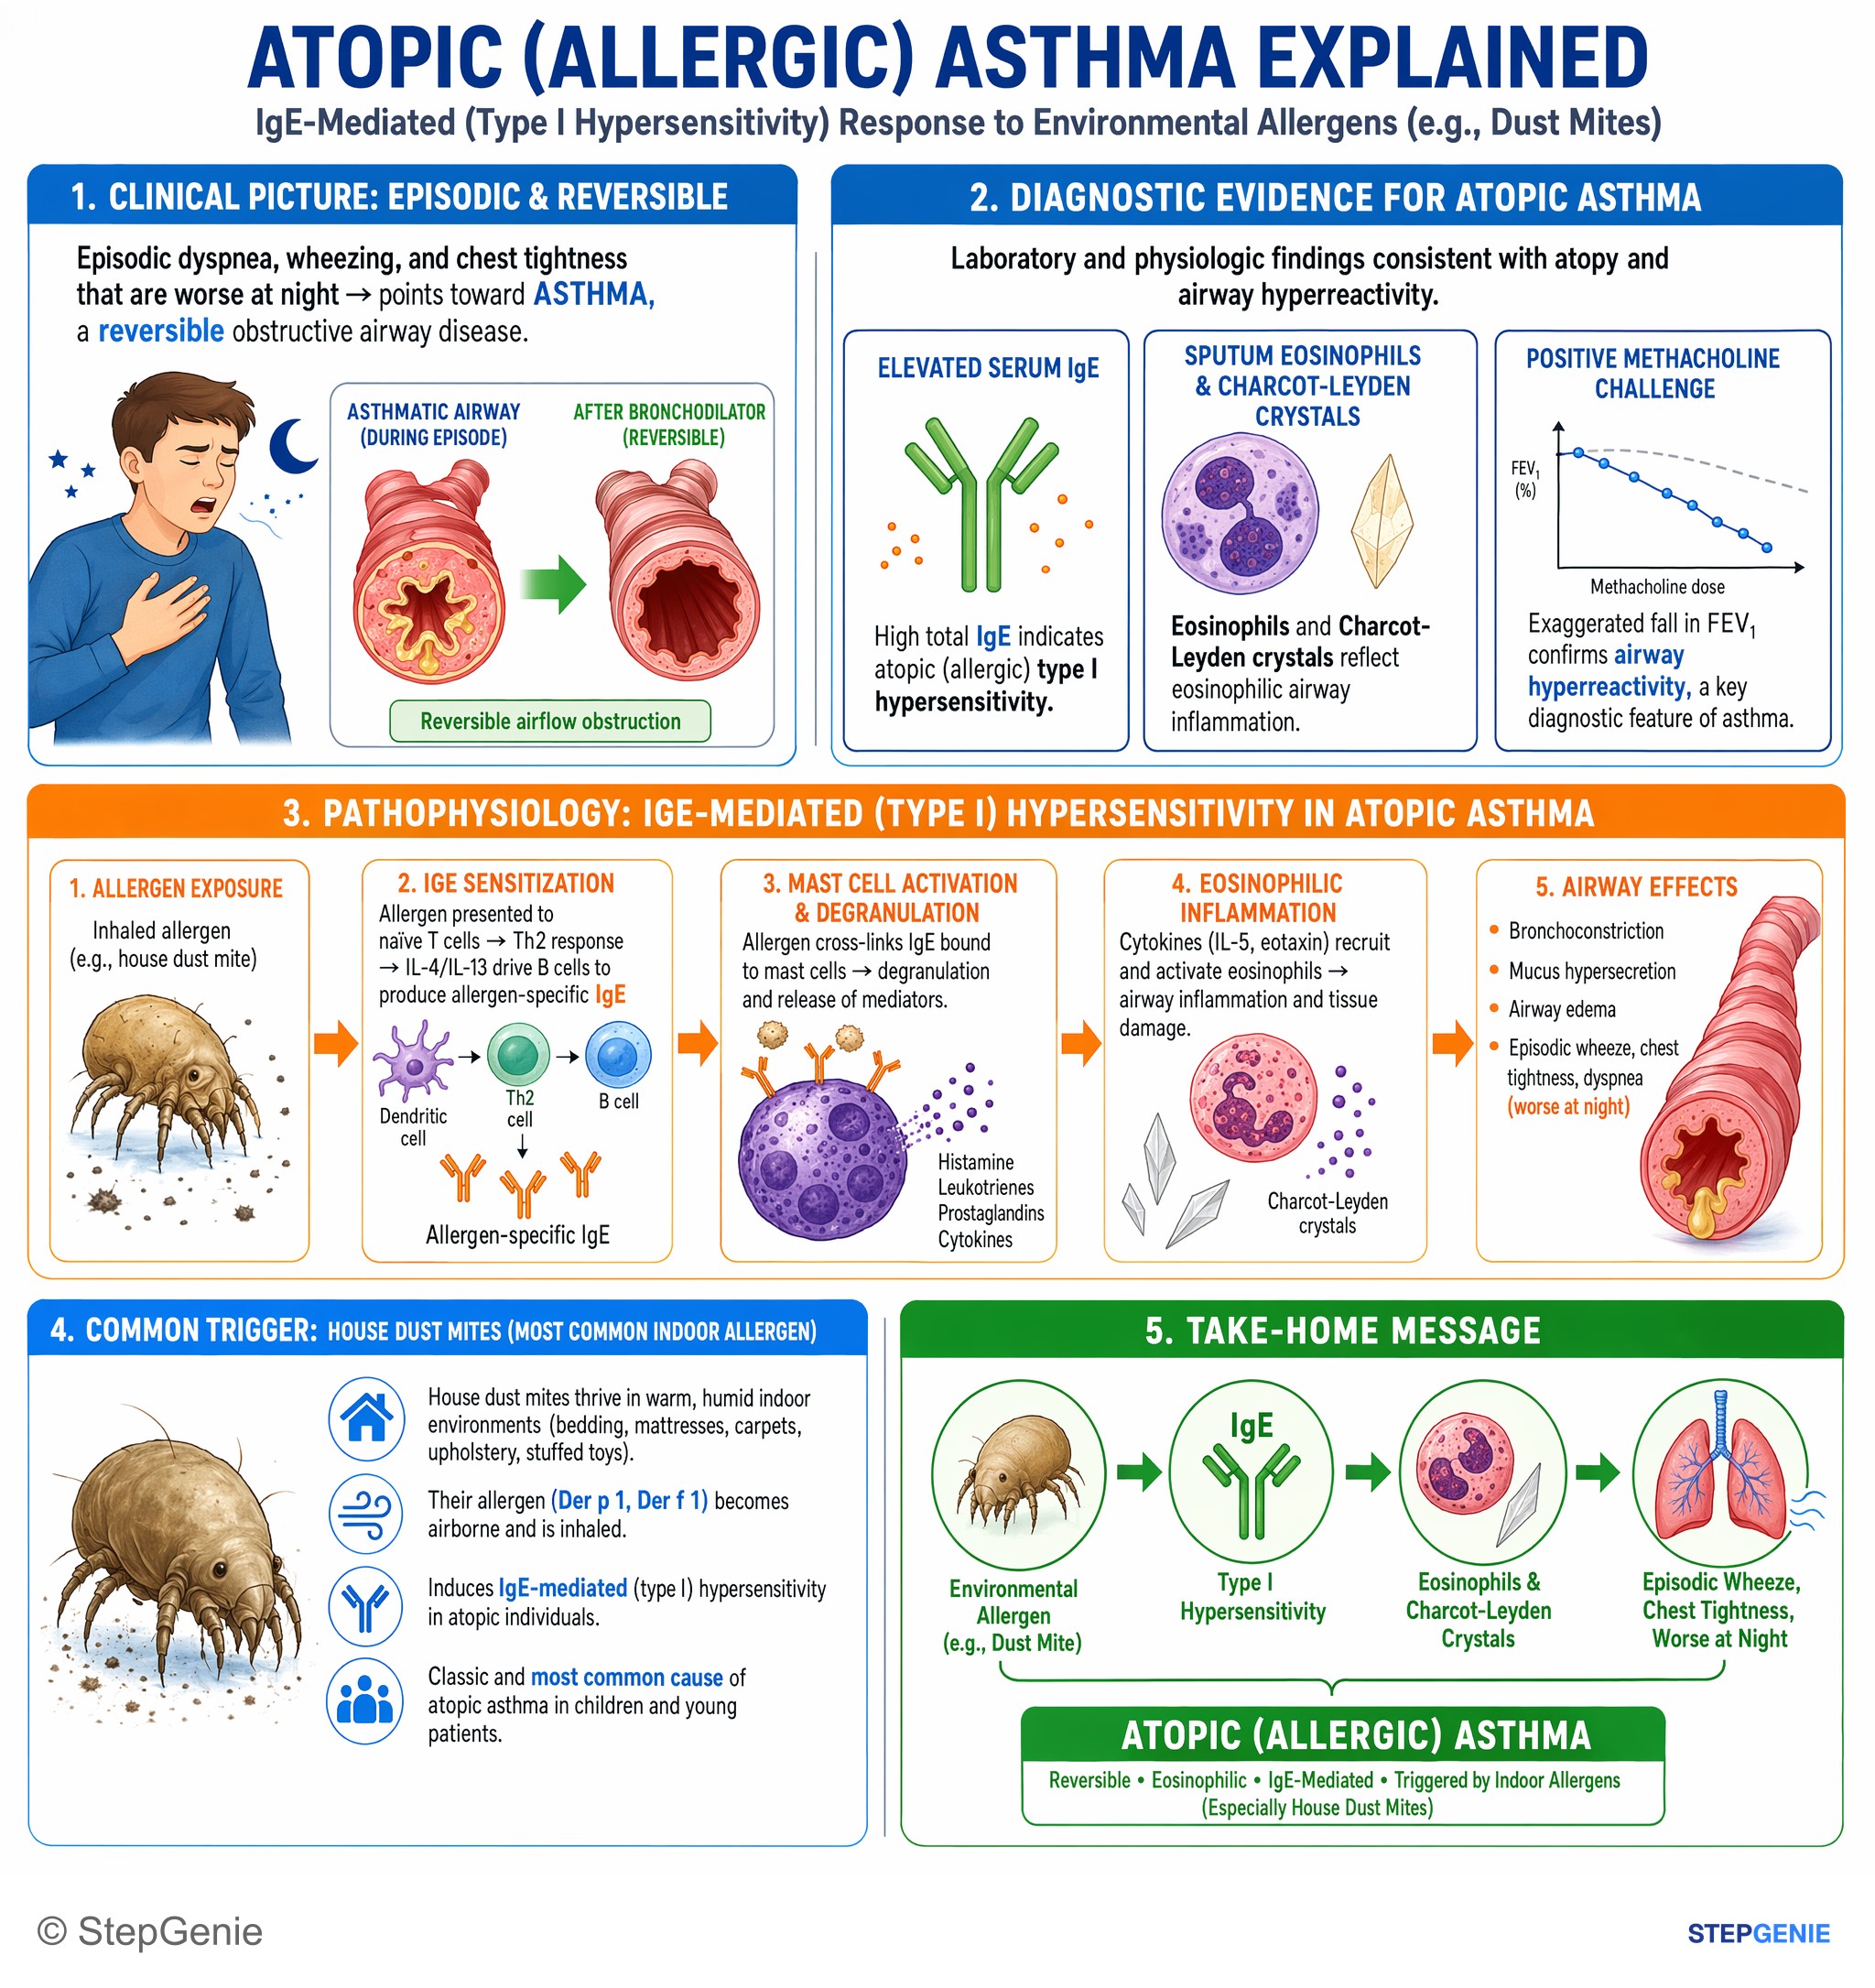
Allergic (atopic) asthma from environmental allergens (e.g., dust mites) → type I hypersensitivity with IgE, eosinophils, Charcot-Leyden…
USMLE Step 1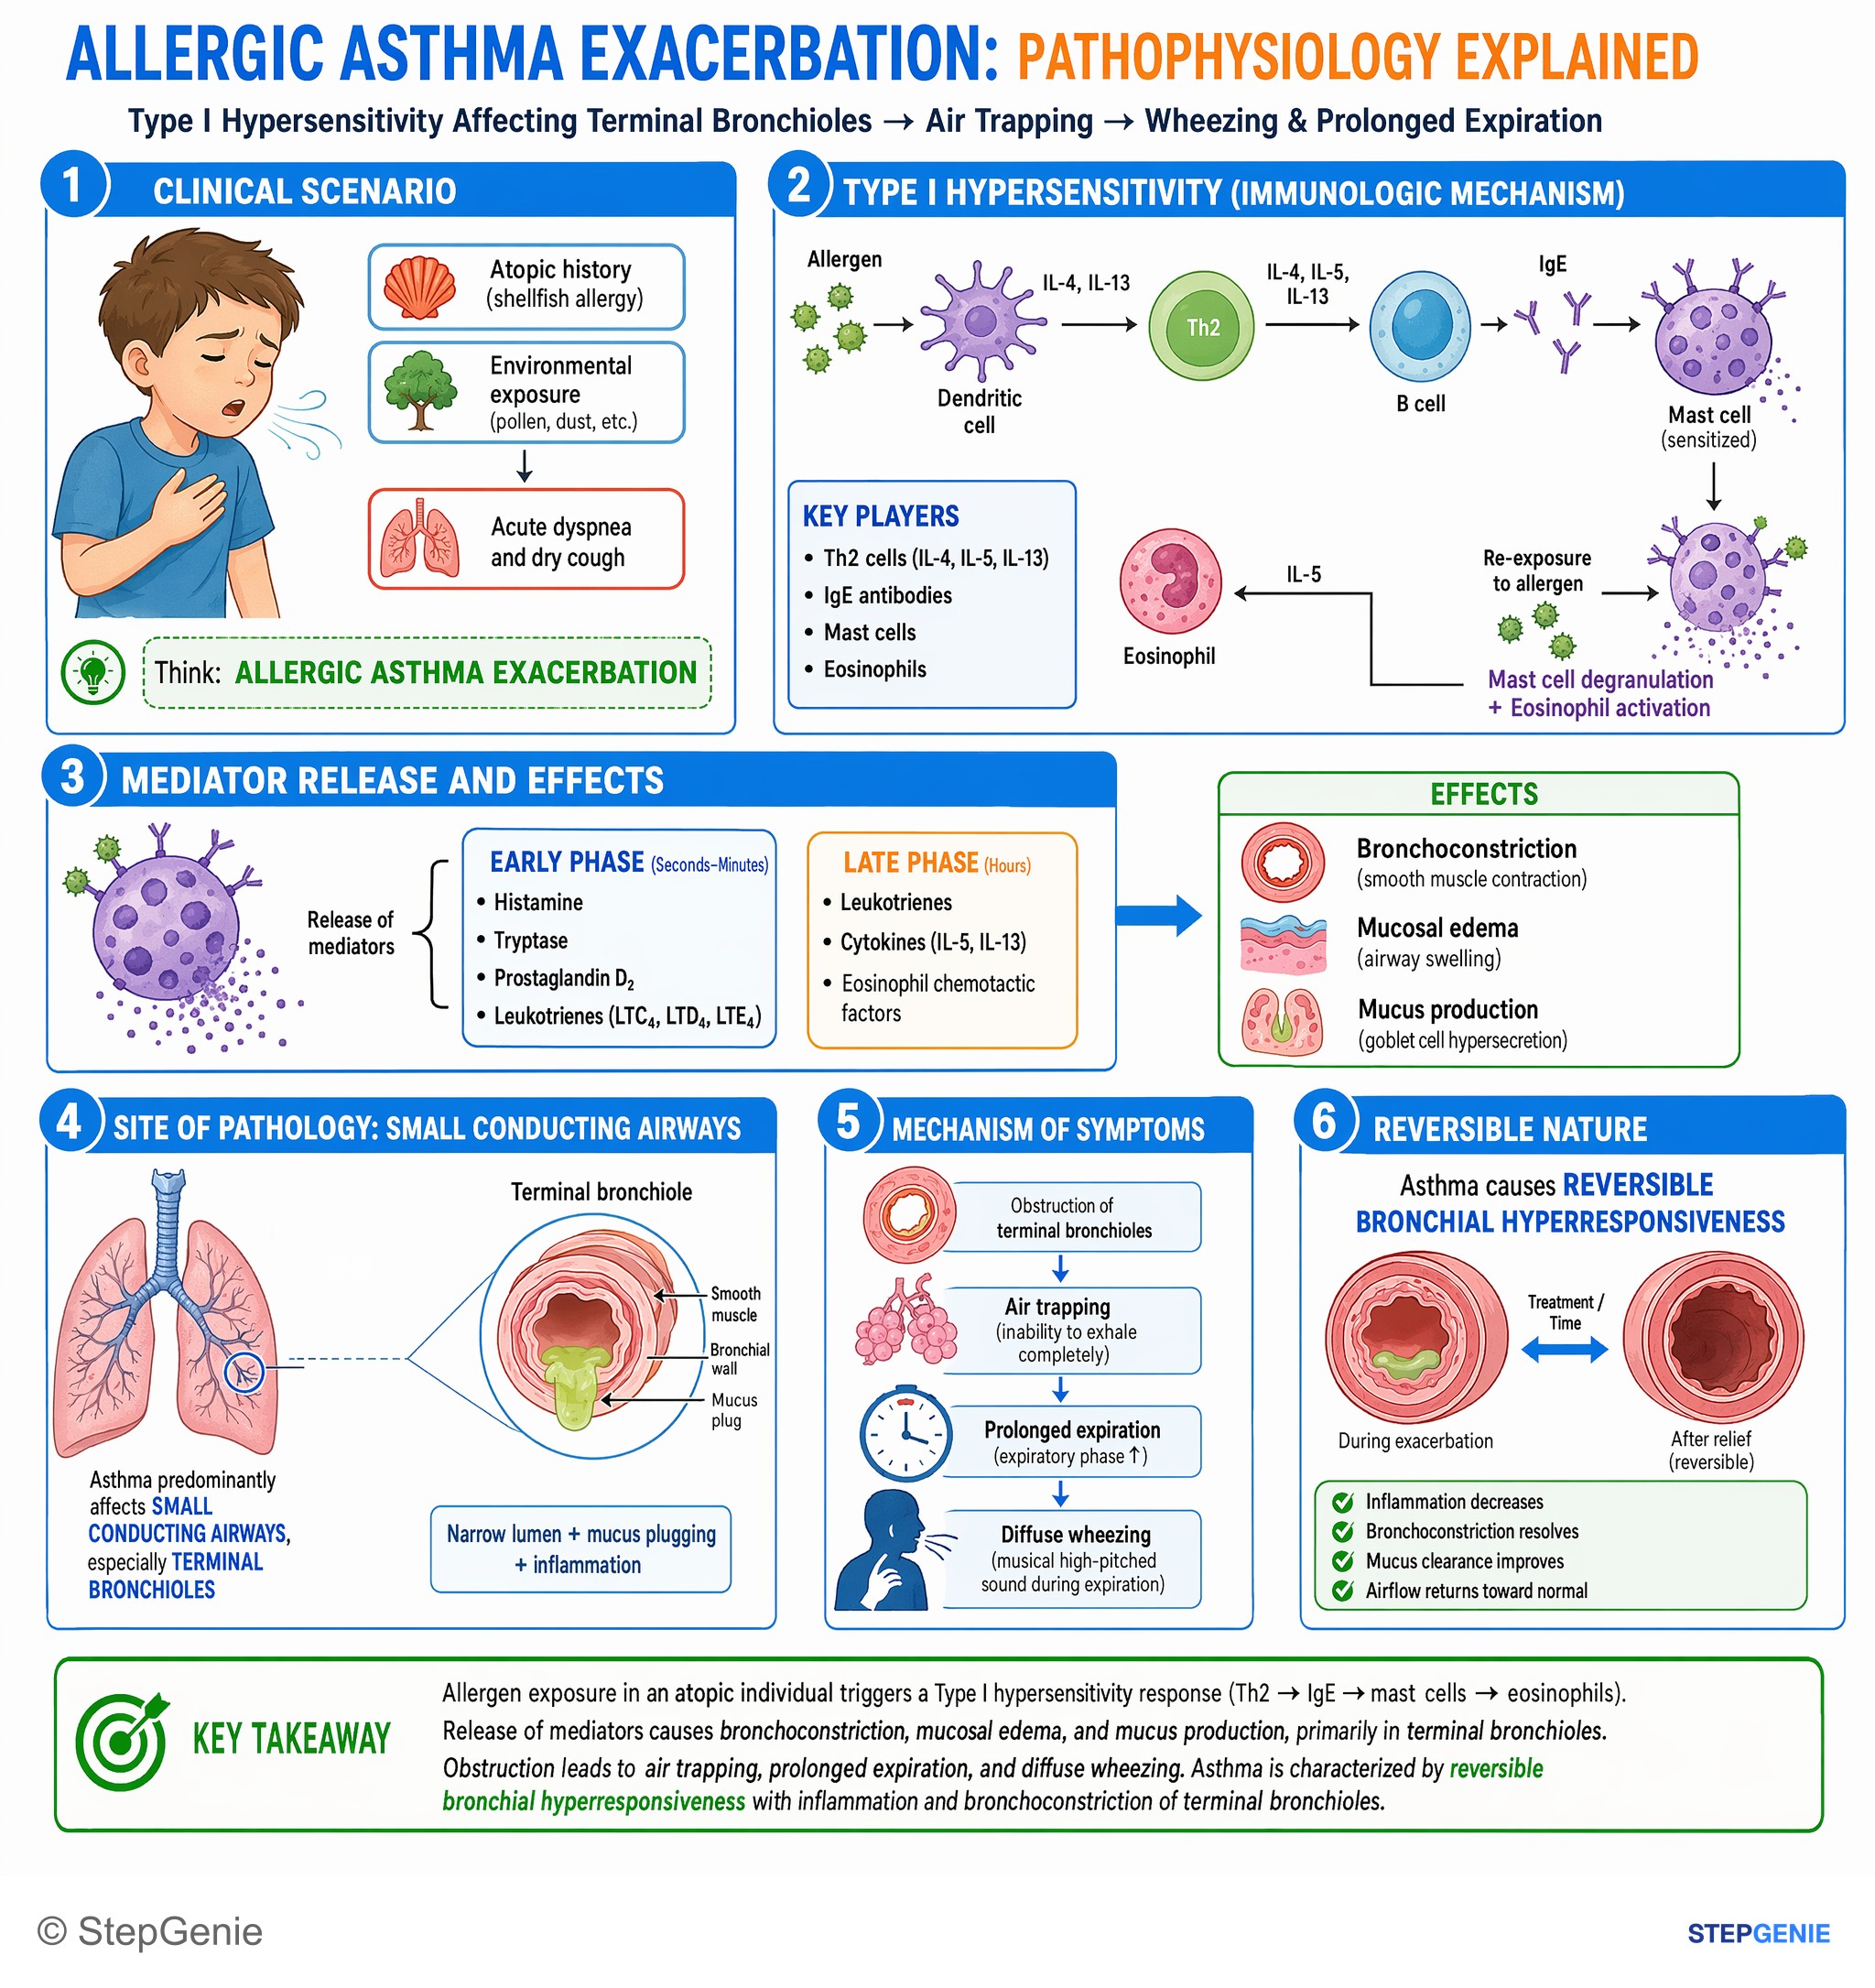
Asthma causes reversible bronchial hyperresponsiveness with inflammation and bronchoconstriction of terminal bronchioles, producing…
USMLE Step 1Frequently Asked Questions
How do you know this vignette is asthma and not just nonspecific wheezing?
This vignette supports asthma because it shows episodic shortness of breath and chest tightness with classic triggers like nighttime symptoms and exercise, plus atopy from eczema and allergic rhinitis. Spirometry shows an obstructive pattern with a decreased FEV1/FVC, and the diagnosis is strongly supported by reversibility after bronchodilator, with FEV1 increasing by 18%, which meets the bronchodilator response clue for asthma.
What is the most appropriate long-term treatment for persistent asthma in this kind of question?
Daily inhaled corticosteroids are the best long-term therapy for persistent asthma in this scenario. The patient has asthma with FEV1 around 70% predicted and symptoms suggesting at least persistent disease, so she needs a controller, not just a reliever. Inhaled corticosteroids are the foundation of long-term control because they reduce airway inflammation, decrease mucus production, lower airway hyperresponsiveness, and reduce exacerbations over time.
Why isn’t albuterol alone the right answer for this asthma patient?
Albuterol alone is not the right choice because it is a rescue medication, not a controller for persistent asthma. It quickly relieves symptoms through beta-2 agonism that increases cAMP and causes bronchodilation, but it does not address the underlying airway inflammation. As-needed albuterol fits intermittent asthma or use before exercise, whereas persistent asthma requires an anti-inflammatory controller such as daily inhaled corticosteroids.
Why are inhaled corticosteroids the cornerstone of asthma treatment?
Inhaled corticosteroids are the cornerstone because they target the inflammatory component of asthma, not just bronchospasm. Through glucocorticoid receptor activation, they alter gene transcription to decrease inflammatory cytokines, eosinophils, and vascular permeability. This leads to less airway inflammation, less mucus production, reduced airway hyperresponsiveness, and fewer exacerbations, which is why they are the foundation of long-term control in persistent asthma.
What pathophysiology details are high-yield for asthma on Step-style questions?
High-yield asthma pathophysiology includes airway hyperresponsiveness and reversible airflow obstruction caused by bronchoconstriction, mucus hypersecretion, airway edema and inflammation, and chronic airway remodeling. The immunology clues are a Th2-skewed response with IL-4 driving IgE class switching, IL-5 recruiting eosinophils, and IL-13 increasing mucus. Eosinophils and mast cells are central, and sputum may show Curschmann spirals and Charcot-Leyden crystals.