Granulomatosis with polyangiitis (GPA), formerly Wegener granulomatosis, is a necrotizing granulomatous vasculitis of small and medium vessels that classically strikes the upper airway, the lungs and the kidneys, and most patients with active generalized disease have c-ANCA directed against proteinase 3 (PR3-ANCA). The exam picture is bloody nasal crusting, sinusitis or a saddle nose + nodules or cavities in the lungs (or hemoptysis) + hematuria with RBC casts, confirmed by biopsy showing necrotizing granulomatous inflammation or pauci-immune necrotizing crescentic glomerulonephritis. Current guidelines (ACR 2021, EULAR 2022, KDIGO 2024) induce remission with glucocorticoids plus rituximab or cyclophosphamide, taper steroids faster than in the past, and maintain remission with rituximab (azathioprine or methotrexate as alternatives).
The one-liner and the name
- Definition: necrotizing granulomatous inflammation + small- and medium-vessel vasculitis + focal necrotizing glomerulonephritis, with or without crescents (Merck). It is one of the three ANCA-associated vasculitides, with microscopic polyangiitis (MPA) and eosinophilic GPA (EGPA).
- Why the name changed: in 2011 the ACR, EULAR and the American Society of Nephrology proposed "granulomatosis with polyangiitis" after it emerged that Friedrich Wegener had joined the Nazi paramilitary SA in 1932 and kept Nazi affiliations through World War II. Both names still appear in question stems.
- Who gets it: usually middle-aged adults (Merck gives a mean onset age of 40), most often people of European ancestry, although any age or ethnic group can be affected. With treatment, about 80% of patients reach complete remission, but about half of them later relapse (Merck).
Pathophysiology in one chain
Primed neutrophil → PR3 moves to its surface → PR3-ANCA binds and activates it → degranulation, oxidants and neutrophil extracellular traps (NETs) → necrosis of small-vessel walls. NETs and complement (C5a) amplify neutrophil activation, and abnormal T-cell and dendritic-cell responses drive granuloma formation and help B cells make more ANCA.
- "Pauci-immune" means little or no immunoglobulin or complement in the vessel wall or glomerulus on immunofluorescence. That separates ANCA vasculitis from anti-GBM disease (linear IgG) and immune complex disease (granular deposits).
- c-ANCA vs PR3-ANCA: c-ANCA is a cytoplasmic immunofluorescence pattern; PR3-ANCA is the antigen-specific result. In GPA they usually coincide.
The classic triad (ELK) and beyond
| Site | How often | What you see |
|---|---|---|
| ENT (upper airway) | 80–100% | Sinus pain, bloody or purulent discharge, epistaxis, thick crusts, ulcers, septal perforation, saddle nose, otitis media, hearing loss; subglottic stenosis (hoarseness, laryngeal pain, dyspnea) |
| Lungs | 62–90% | Single or multiple nodules, with or without cavitation, infiltrates; diffuse alveolar hemorrhage (dyspnea, bilateral infiltrates, falling hemoglobin, with or without hemoptysis) |
| Kidneys | 70–85% during the course | Hematuria, RBC casts, proteinuria, rising creatinine; can be rapidly progressive GN |
| Eyes | 50–60% | Scleritis, conjunctivitis, uveitis, nasolacrimal duct obstruction, orbital pseudotumor with proptosis |
| Peripheral nerves | 11–44% | Mononeuritis multiplex (ischemic neuropathy) |
| Skin and joints | Variable | Palpable purpura, nodules, ulcers, livedo; arthralgias, myalgias |
Frequencies are from a 2024 Frontiers in Medicine review. The kidneys may join late: some patients start with upper and lower respiratory disease and develop glomerulonephritis afterward, so keep checking the urine. Granulomas as a pattern are compared in the granulomatous inflammation table.
Diagnosis: what to order and what it means
- Urinalysis and creatinine in everyone: hematuria, dysmorphic RBCs, RBC casts and proteinuria signal glomerulonephritis.
- ANCA: test for both PR3- and MPO-ANCA with antigen-specific immunoassays as the primary method (EULAR 2022). PR3-ANCA is positive in roughly three-quarters of patients (pooled sensitivity about 74%) and in most with active disease; a negative test does not exclude GPA. Merck notes a positive ANCA has a positive predictive value of only about 50%, so test when pretest probability is at least moderately high.
- Imaging: non-contrast chest CT for everyone suspected, because a chest radiograph can miss nodules and cavities; sinus CT shows mucosal thickening, opacification or septal perforation.
- Biopsy: "a positive biopsy is strongly supportive" (EULAR). A kidney biopsy showing pauci-immune necrotizing crescentic GN strongly supports the diagnosis; lung tissue is most likely to show the characteristic findings; nasal biopsy is usually nonspecific. The histologic triad (necrosis, granulomatous inflammation, vasculitis) is rarely complete in one specimen.
- Exclude infection: a positive ANCA with a cavitary lesion still needs cultures and stains for tuberculosis and fungi.
The 2022 ACR/EULAR classification criteria are built to select uniform groups for research, not to diagnose, and apply only after small- or medium-vessel vasculitis is diagnosed and mimics are excluded. They still show which clues weigh most:
| Item | Points |
|---|---|
| c-ANCA or PR3-ANCA positive | +5 |
| Bloody nasal discharge, nasal crusting or sinonasal congestion | +3 |
| Cartilaginous involvement; pulmonary nodules, mass or cavitation; granuloma or giant cells on biopsy | +2 each |
| Conductive or sensorineural hearing loss; sinus inflammation or consolidation on imaging; pauci-immune GN | +1 each |
| p-ANCA or MPO-ANCA positive | −1 |
| Blood eosinophils ≥1 × 10⁹/L | −4 |
A total of ≥5 classifies GPA (sensitivity 93%, specificity 94% in validation).
GPA vs the look-alikes
| Feature | GPA | Microscopic polyangiitis | EGPA (Churg-Strauss) | Anti-GBM disease |
|---|---|---|---|---|
| Antibody | PR3-ANCA (c-ANCA) | MPO-ANCA (p-ANCA), at least 70% | ANCA in 30–40%, mostly MPO | Anti-GBM (α3 chain of type IV collagen); some patients are also ANCA positive |
| Granulomas | Yes, necrotizing | No | Yes, with eosinophils | No |
| Upper airway | Destructive (septal perforation, saddle nose) | Minimal or none | Allergic rhinitis, nasal polyps, non-destructive sinusitis | None |
| Lungs | Nodules, cavities, alveolar hemorrhage | Alveolar hemorrhage, no cavities | Asthma, transient infiltrates | Alveolar hemorrhage |
| Kidney immunofluorescence | Pauci-immune | Pauci-immune | Pauci-immune when GN occurs | Linear IgG |
| Extra clue | Subglottic stenosis, orbital pseudotumor | Kidney involvement in up to 90% | Eosinophilia, mononeuritis multiplex, myocarditis | Smoking or hydrocarbon exposure |
The eosinophilic cousin has its own EGPA mnemonic and criteria, and the three immunofluorescence patterns of crescentic GN are in the rapidly progressive GN guide.
Treatment: current induction and maintenance
| Step | What current guidelines say |
|---|---|
| Induction, organ- or life-threatening disease (GN, alveolar hemorrhage, mononeuritis multiplex, CNS, cardiac or mesenteric disease) | Glucocorticoids + rituximab or cyclophosphamide. ACR 2021 conditionally prefers rituximab; EULAR and KDIGO prefer rituximab for relapses |
| Glucocorticoid dose | Reduced-dose regimens (ACR, KDIGO). EULAR: start 50–75 mg/day prednisolone equivalent by weight and taper to 5 mg/day by 4–5 months. IV pulses or a high-dose oral start are both acceptable (ACR) |
| Non-organ-threatening GPA (e.g., sinus disease alone) | ACR 2021: methotrexate + glucocorticoids; EULAR 2022: rituximab + glucocorticoids, with methotrexate or mycophenolate as alternatives |
| Plasma exchange | Not routine. EULAR and KDIGO: consider if creatinine is >3.4 mg/dL (300 µmol/L); KDIGO also for dialysis, rapidly rising creatinine, or alveolar hemorrhage with hypoxemia. ACR 2021 recommends against routine use |
| Maintenance | Rituximab preferred (ACR: over methotrexate or azathioprine); azathioprine or methotrexate are alternatives. Duration: 24–48 months after remission of new-onset disease (EULAR); 18 months to 4 years (KDIGO) |
| Prophylaxis | Trimethoprim-sulfamethoxazole against Pneumocystis with rituximab or cyclophosphamide (ACR, EULAR); the rituximab label advises it during treatment and for at least 6 months after the last infusion |
| ANCA titers | Do not adjust therapy on ANCA titers alone (ACR); a rising titer by itself does not mean a flare |
Avacopan update (2026). This oral complement C5a-receptor antagonist entered EULAR 2022 and KDIGO 2024 as a way to cut glucocorticoid exposure. In 2026 regulators challenged the pivotal ADVOCATE trial behind its approval, and the New England Journal of Medicine retracted the trial's 2021 report in June 2026. In April 2026 FDA's drug center proposed withdrawing US approval, stating that study personnel had manipulated the pivotal study's results and citing serious drug-induced liver injury, including fatal vanishing bile duct syndrome (the subject of a March 2026 FDA safety communication). In the EU, EMA concluded that the trial had been conducted in breach of good clinical practice, and the marketing authorization was revoked in August 2026. Amgen has requested a hearing, and FDA had issued no final decision as of October 2026; FDA's statement (last updated July 2026) says the drug stays on the US market until the company withdraws it or the FDA Commissioner orders its removal. For exam questions, the standard answer remains glucocorticoids plus rituximab or cyclophosphamide.
Drug toxicities worth knowing
| Drug | Mechanism | High-yield toxicity |
|---|---|---|
| Rituximab | Anti-CD20 antibody, depletes B cells | Boxed warnings: fatal infusion reactions, severe mucocutaneous reactions, hepatitis B reactivation (screen first), PML |
| Cyclophosphamide | Alkylating agent | Hemorrhagic cystitis (hydration; mesna), urinary tract cancer and other malignancies, myelosuppression and infection, infertility, fetal harm |
| Glucocorticoids | Broad anti-inflammatory | Infection, hyperglycemia, bone loss; the reason for faster tapers |
| Methotrexate, azathioprine | Antimetabolites | Myelosuppression and liver toxicity (azathioprine is riskier with TPMT or NUDT15 deficiency); methotrexate is teratogenic and renally excreted |
Merck adds that when cyclophosphamide is used for induction, it is typically replaced after 3–6 months to limit its toxicity. Pneumocystis itself is reviewed in the Pneumocystis jirovecii guide.
How it shows up on the exam
Vignette. A 49-year-old man has had 4 months of nasal congestion with bloody crusts despite two courses of antibiotics. For 2 weeks he has had a cough with blood-streaked sputum and ankle swelling. His nasal bridge has collapsed. Blood pressure is 152/94 mm Hg. Creatinine is 2.6 mg/dL (1.0 mg/dL 6 months ago); urinalysis shows blood, protein and RBC casts. Chest CT shows multiple bilateral nodules, several cavitated. Kidney biopsy shows necrotizing crescentic glomerulonephritis with scant immunoglobulin and complement on immunofluorescence.
Which serologic finding is most likely?
- A. Antibodies against proteinase 3
- B. Antibodies against myeloperoxidase
- C. Antibodies against the α3 chain of type IV collagen
- D. Anti-dsDNA antibodies with low C3 and C4
- E. Elevated antistreptolysin O titer with low C3
Answer: A. Destructive nasal disease, cavitating nodules and pauci-immune crescentic GN add up to GPA, which is linked to PR3-ANCA (c-ANCA).
- B (MPO-ANCA): typical of MPA and EGPA; MPA usually spares the upper airway and lacks cavitating nodules.
- C (anti-GBM): causes pulmonary hemorrhage plus GN, but with linear IgG on immunofluorescence, not pauci-immune staining, and no destructive nasal disease.
- D (lupus nephritis): an immune complex GN with granular deposits and low complement.
- E (post-streptococcal GN): also immune complex disease with low C3, following a throat or skin infection.
Next step? High-dose glucocorticoids plus rituximab (or cyclophosphamide), with trimethoprim-sulfamethoxazole prophylaxis. Glucocorticoids alone are inadequate for organ-threatening disease, methotrexate is for non-organ-threatening disease, and plasma exchange is not routine (it is considered mainly for creatinine >3.4 mg/dL, dialysis, a rapidly rising creatinine or alveolar hemorrhage with hypoxemia).
Key takeaways
- ELK: ENT + lung + kidney disease in one patient means GPA until proven otherwise.
- PR3-ANCA (c-ANCA) for GPA; MPO-ANCA (p-ANCA) for MPA and EGPA; test by antigen-specific immunoassay, and remember the modest positive predictive value.
- Biopsy: necrotizing granulomatous inflammation and vasculitis; kidney shows pauci-immune necrotizing crescentic GN.
- Destructive nose, cavitating nodules, subglottic stenosis separate GPA from MPA; asthma and eosinophils mean EGPA; linear IgG means anti-GBM.
- Treatment: glucocorticoids + rituximab (or cyclophosphamide) for induction, reduced-dose steroid tapers, rituximab maintenance for roughly 2–4 years, and Pneumocystis prophylaxis.
Sources
- Granulomatosis With Polyangiitis (GPA) — Merck Manual Professional Edition
- Chung SA, et al. 2021 American College of Rheumatology/Vasculitis Foundation Guideline for the Management of ANCA-Associated Vasculitis — Arthritis & Rheumatology (2021)
- Hellmich B, et al. EULAR recommendations for the management of ANCA-associated vasculitis: 2022 update — Annals of the Rheumatic Diseases (2024; author manuscript)
- KDIGO 2024 Clinical Practice Guideline for the Management of ANCA-Associated Vasculitis: Top 10 Takeaways — KDIGO (2024)
- Robson JC, et al. 2022 ACR/EULAR Classification Criteria for Granulomatosis with Polyangiitis — Annals of the Rheumatic Diseases (2022)
- Potentas-Policewicz M, Fijolek J. Granulomatosis with polyangiitis: clinical characteristics and updates in diagnosis — Frontiers in Medicine (2024)
- Microscopic Polyangiitis (MPA) — Merck Manual Professional Edition
- Eosinophilic Granulomatosis With Polyangiitis (EGPA) — Merck Manual Professional Edition
- RITUXAN (rituximab) Prescribing Information — DailyMed
- Nazi Taint Sparks Proposed Name Change for Wegener's Granulomatosis — MDedge (2011)
- CDER proposes to withdraw approval of TAVNEOS — U.S. Food and Drug Administration (2026)
- Tavneos: referral (marketing authorisation revoked) — European Medicines Agency (2026)
- Retraction: Jayne DRW et al. Avacopan for the Treatment of ANCA-Associated Vasculitis — New England Journal of Medicine (2026)
- TAVNEOS: update for prescribers on the FDA hearing request — Amgen (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
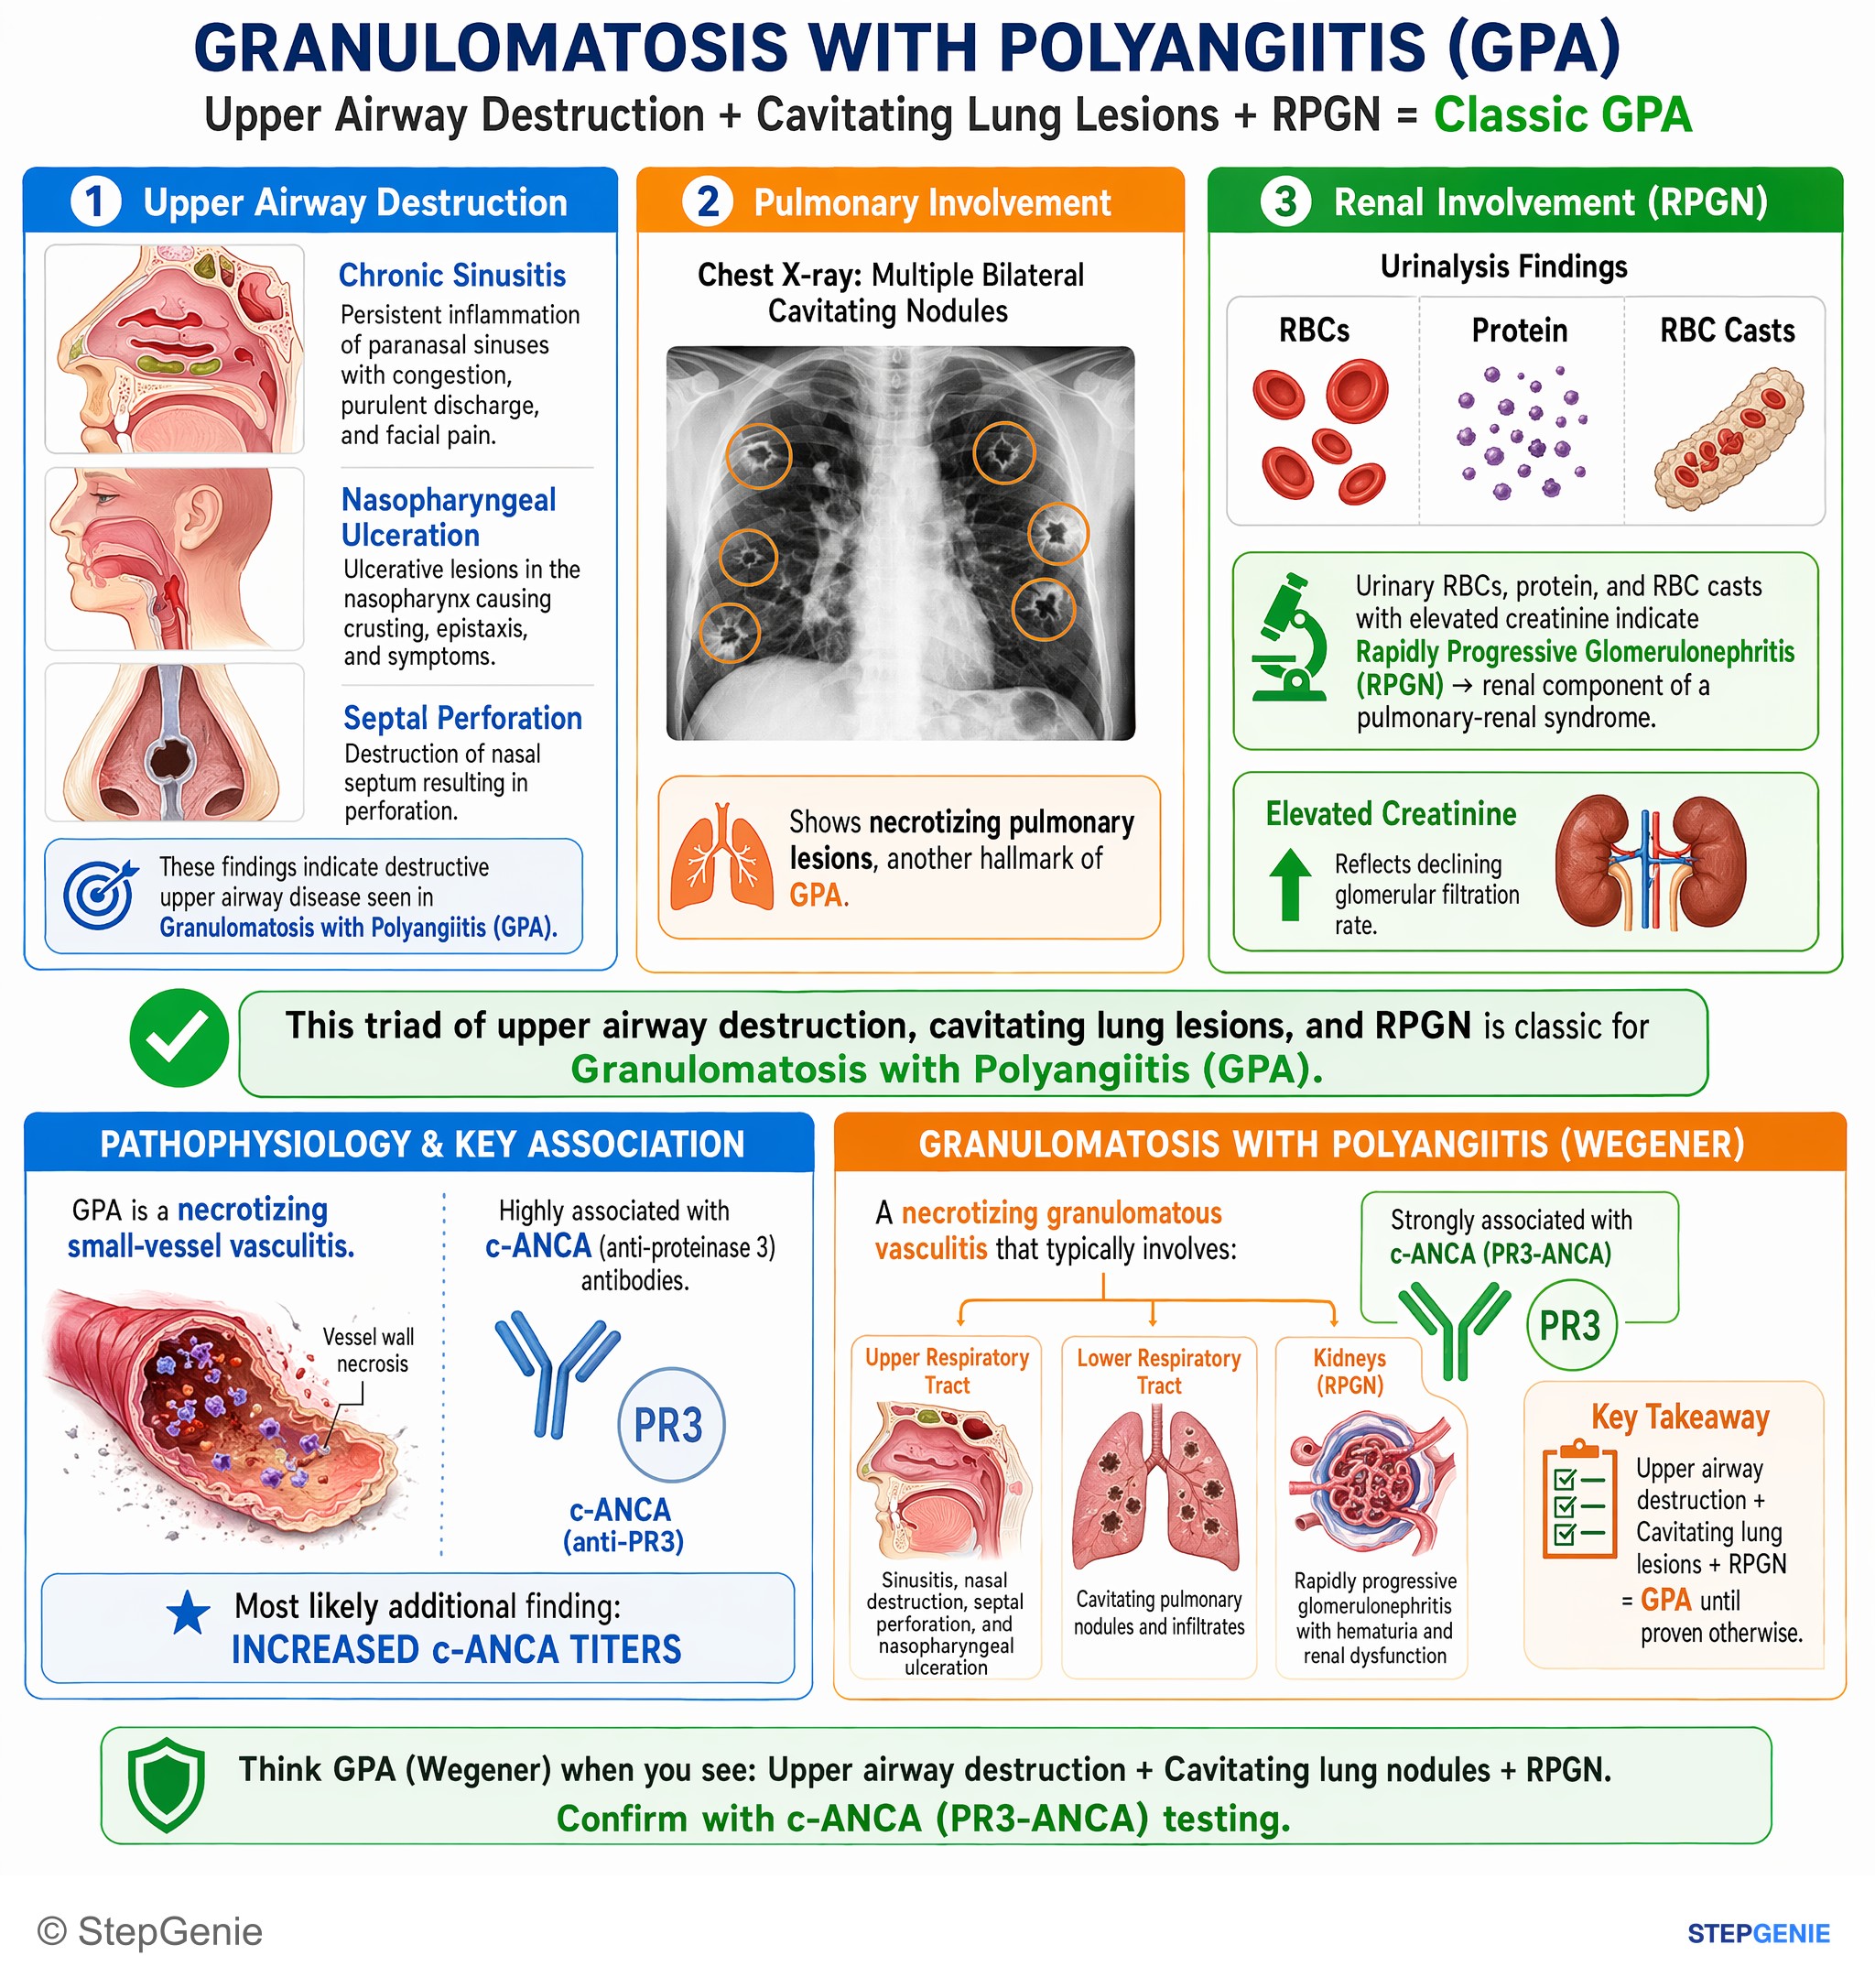
Granulomatosis with polyangiitis (Wegener): necrotizing granulomatous vasculitis of upper/lower respiratory tract plus RPGN; strongly…
USMLE Step 1Frequently Asked Questions
What is the classic triad of granulomatosis with polyangiitis?
The classic triad is upper airway, lung and kidney disease. Typical findings are bloody nasal crusting, sinusitis, septal perforation or a saddle nose; lung nodules that may cavitate, or diffuse alveolar hemorrhage; and glomerulonephritis with hematuria and RBC casts. Not every patient has all three at once, and the kidneys can become involved after the respiratory disease.
What antibody is associated with GPA?
GPA is most strongly associated with antineutrophil cytoplasmic antibodies against proteinase 3 (PR3-ANCA), which usually produce a cytoplasmic (c-ANCA) immunofluorescence pattern. Roughly three-quarters of patients are PR3-ANCA positive (pooled sensitivity about 74%), and most patients with active disease are positive. Guidelines recommend testing for both PR3- and MPO-ANCA with antigen-specific immunoassays, and a positive result has only a modest positive predictive value and does not rule out infection.
Why was Wegener's granulomatosis renamed?
In 2011 the American College of Rheumatology, EULAR and the American Society of Nephrology recommended the name granulomatosis with polyangiitis. The change followed evidence that Friedrich Wegener, the pathologist the disease was named after, had joined the Nazi SA in 1932 and kept Nazi affiliations through World War II. The new name describes the disease itself: granulomatous inflammation plus vasculitis of many small vessels.
How is GPA different from microscopic polyangiitis?
Both are ANCA-associated, pauci-immune small-vessel vasculitides that can cause glomerulonephritis and alveolar hemorrhage. GPA has necrotizing granulomas, destructive upper airway disease such as septal perforation and saddle nose, and nodular or cavitating lung lesions, and it is usually PR3-ANCA positive. Microscopic polyangiitis lacks granulomas, usually spares the upper airway and is usually MPO-ANCA (p-ANCA) positive.
What is the treatment for GPA?
For organ- or life-threatening disease, ACR, EULAR and KDIGO guidance is glucocorticoids plus rituximab or cyclophosphamide, with reduced-dose glucocorticoid tapers, and rituximab is often preferred. After remission, maintenance with rituximab, or azathioprine or methotrexate, continues for roughly 18 months to 4 years. Patients receiving rituximab or cyclophosphamide also take trimethoprim-sulfamethoxazole to prevent Pneumocystis pneumonia. Plasma exchange is reserved for selected patients, such as those with severe kidney failure.
What does a kidney biopsy show in GPA?
It typically shows pauci-immune necrotizing glomerulonephritis, often with crescents; pauci-immune means little or no immunoglobulin or complement on immunofluorescence. That separates ANCA vasculitis from anti-GBM disease, which shows linear IgG, and from immune complex diseases such as lupus nephritis and post-streptococcal glomerulonephritis, which show granular deposits. Lung biopsy is the most likely to show the characteristic granulomatous inflammation, while nasal biopsies are often nonspecific.