The lungs hold four volumes, stacked from top to bottom: inspiratory reserve volume (IRV), tidal volume (TV), expiratory reserve volume (ERV) and residual volume (RV). Every capacity is a sum of two or more of them: inspiratory capacity (IC = IRV + TV), functional residual capacity (FRC = ERV + RV), vital capacity (VC = IRV + TV + ERV) and total lung capacity (TLC = all four). Spirometry can't measure RV or anything that contains it (FRC and TLC); those need helium dilution, nitrogen washout or body plethysmography, the gold standard. Obstruction traps air (RV, FRC and often TLC rise); restriction shrinks the lung and is defined by a TLC below the lower limit of normal.
The acronym: "I Tidy Every Room"
Read the volume stack from top to bottom: IRV, TV, ERV, RV. Then let pieces of the phrase build each capacity:
| Piece of the phrase | Volumes added | Capacity |
|---|---|---|
| "I Tidy" | IRV + TV | Inspiratory capacity (IC) |
| "Every Room" | ERV + RV | Functional residual capacity (FRC) |
| "I Tidy Every" | IRV + TV + ERV | Vital capacity (VC) |
| "I Tidy Every Room" | IRV + TV + ERV + RV | Total lung capacity (TLC) |
The rule that wins points: the spirometer never gets into the Room. Anything that contains RV (RV itself, FRC and TLC) can't be measured by spirometry, because air that never leaves the lungs never reaches the spirometer.
The four volumes
| Letter | Volume | What it is | Typical adult value | Spirometry? |
|---|---|---|---|---|
| I | Inspiratory reserve volume (IRV) | Extra air you can inhale after a normal breath in | Varies | Yes |
| T | Tidal volume (TV) | Air moved in one quiet breath | About 500 mL (men), 400 mL (women); about 7 mL/kg ideal body weight | Yes |
| E | Expiratory reserve volume (ERV) | Extra air you can exhale after a normal breath out | Varies | Yes |
| R | Residual volume (RV) | Air left after a maximal exhalation; keeps alveoli open between breaths | About 1-1.2 L | No |
The four capacities
| Capacity | Formula | What it is | Typical adult value | Spirometry? |
|---|---|---|---|---|
| IC | IRV + TV | Deepest breath in, starting from the end of a quiet exhalation | Varies | Yes |
| FRC | ERV + RV | Air left after a normal, passive exhalation | About 3 L | No |
| VC | IRV + TV + ERV (= TLC − RV) | Most air you can exhale after a maximal inhalation; FVC if exhaled as fast as possible | 3-5 L | Yes |
| TLC | IRV + TV + ERV + RV (= VC + RV = IC + FRC) | All the air in the lungs after a maximal inhalation | About 6 L | No |
Values are approximate and vary with height, sex, age, body size and, for FRC, posture (StatPearls); men tend to have a larger TLC than women, and tall people a larger TLC than short people. Remember the definition: a capacity is always two or more volumes added together.
How each one is measured
Spirometry records TV during quiet breathing and IRV, ERV, IC and VC with deeper maneuvers, along with FEV1 and FVC (interpretation in the FEV1/FVC ratio cheat sheet). It cannot measure RV.
To get into the Room, the lab measures FRC by one of the methods below, then does arithmetic: RV = FRC − ERV and TLC = FRC + IC (or RV + VC).
| Method | How it works | The catch |
|---|---|---|
| Helium dilution (closed circuit) | Breathe from a spirometer holding a known helium concentration until it equilibrates; conservation of mass gives | Measures only gas that communicates with open airways, so it underestimates volumes in obstruction |
| Nitrogen washout (open circuit) | Breathe 100% oxygen and collect the exhaled nitrogen until it stays below 1.5% for 3 consecutive breaths; all the nitrogen washed out came from the FRC | Same problem: underestimates in obstruction; a simpler, easier test than plethysmography |
| Body plethysmography | Sit in a sealed box and make breathing efforts; Boyle's law () turns the pressure changes into thoracic gas volume | Gold standard; counts trapped gas too (can overestimate in severe obstruction) |
CT imaging can also estimate lung volumes. Why the catch matters: in severe airflow obstruction, gas-dilution TLC can be lower than the true value by as much as 3 L, because helium and nitrogen never reach gas trapped in poorly ventilated or non-communicating airspaces (ERS/ATS 2022).
FRC: the lung's resting point
- FRC is the volume where the lung's inward elastic recoil and the chest wall's outward recoil are equal, which is why a quiet exhalation passively ends there (see compliance vs elastance).
- Pulmonary vascular resistance is lowest at FRC, and FRC is the oxygen reservoir that keeps gas exchange going between breaths.
- FRC rises with emphysema (lost elastic recoil), age and upright posture.
- FRC falls when lying supine and with obesity, pregnancy and pulmonary fibrosis. When FRC drops below closing capacity, small airways close, causing atelectasis and shunt.
Dead space: why not all of the tidal volume counts
- Of a 500-mL tidal breath, about 150 mL fills the anatomic dead space, so only about 350 mL reaches the respiratory zone.
- Alveolar ventilation = respiratory rate × (TV − dead space), so rapid, shallow breathing wastes a bigger share of each breath. More in dead space vs shunt.
Obstructive vs restrictive: what happens to the volumes
| Measure | Obstructive (COPD, asthma) | Restrictive (fibrosis, chest wall, neuromuscular, severe obesity) |
|---|---|---|
| Defined by | FEV1/FVC below the lower limit of normal; GOLD uses post-bronchodilator FEV1/FVC <0.7 for COPD | TLC below the lower limit of normal (5th percentile) |
| TLC | Normal or ↑ (hyperinflation) | ↓ |
| RV | ↑ (air trapping) | ↓ in lung parenchymal disease; can stay relatively high (↑ RV/TLC) in neuromuscular or chest wall disease |
| FRC | ↑ | ↓ |
| VC/FVC | Normal or slightly ↓ | ↓ |
| FEV1/FVC | ↓ | Normal |
- Obstruction (COPD, asthma, emphysema; see the COPD question): airway and parenchymal changes trap air, so RV, FRC and the RV/TLC ratio rise. An RV or RV/TLC above the 95th percentile suggests hyperinflation or air trapping.
- Restriction from the lung itself (idiopathic pulmonary fibrosis, pneumoconioses) or from outside it (kyphoscoliosis, pectus excavatum, myasthenia gravis, ALS): TLC is low by definition. In most restrictive disease FEV1, FVC and TLC fall in roughly the same proportion ("simple restriction"), FRC and RV fall too, and the ratio stays normal. When the patient can't empty the lungs (neuromuscular disease, chest wall restriction), FVC falls out of proportion to TLC because RV stays disproportionately high ("complex restriction", ERS/ATS 2022).
- Obesity first lowers ERV and FRC (significantly at a BMI >30). Most obese patients still have lung volumes in the normal range, and TLC is usually not reduced until BMI >40; then it gives a restrictive pattern, which weight loss can reverse.
- Trap: a low FVC with a normal ratio only suggests restriction. It goes with a low TLC less than half the time, so measure lung volumes before calling it restrictive (ERS/ATS 2022).
- Mixed disorder: a low TLC plus a low FEV1/FVC means obstruction and restriction together.
Practice question
A 67-year-old man with severe emphysema has pulmonary function testing. Post-bronchodilator FEV1/FVC is 0.41. Total lung capacity measured by helium dilution is 5.6 L; total lung capacity measured by body plethysmography the same morning is 7.9 L. Which of the following best explains the difference?
A. Helium mixes only with gas in airspaces that communicate with open airways B. Helium diffuses across the alveolar-capillary membrane into the blood C. Helium dilution measures vital capacity, not residual volume D. Air trapping lowers the residual volume measured by plethysmography E. A coexisting restrictive process shrinks the plethysmographic volume
Answer: A. Gas-dilution methods measure only communicating gas. In emphysema, air trapped in poorly ventilated, non-communicating airspaces (bullae) never equilibrates with the helium, so helium dilution underestimates TLC, by as much as 3 L in severe obstruction. Plethysmography compresses all the gas in the thorax, trapped or not, which is why it is the gold standard here.
- B: helium is used precisely because it is a non-absorbable, inert gas that stays in the airspaces rather than crossing into the blood. Carbon monoxide, which is taken up by the blood, is the gas used to measure diffusing capacity (DLCO); in that test an inert tracer gas is added only to measure alveolar volume.
- C: helium dilution measures FRC, which includes RV; the lab then calculates RV = FRC − ERV and TLC = FRC + IC.
- D: air trapping raises RV, which is exactly why the plethysmographic volume is higher.
- E: restriction lowers TLC by every method; it cannot make plethysmography read higher than helium dilution.
How USMLE tests it
| If the question asks... | Answer |
|---|---|
| Which volumes can't spirometry measure? | RV, FRC and TLC (anything with RV in it) |
| Which capacity equals ERV + RV? | FRC ("Every Room") |
| Lung and chest wall recoil balance; PVR is lowest | FRC |
| Plethysmography TLC much higher than helium TLC | Gas trapped behind obstructed airways (emphysema, bullae) |
| Patient lies supine, is obese or is pregnant | FRC falls |
| Why is FRC high in emphysema? | Loss of elastic recoil |
| Alveolar ventilation | Respiratory rate × (TV − dead space) |
Key takeaways
- I Tidy Every Room = IRV, TV, ERV, RV from top to bottom. "I Tidy" = IC, "Every Room" = FRC, "I Tidy Every" = VC, the whole phrase = TLC.
- Spirometry can't get into the Room: RV, FRC and TLC need helium dilution, nitrogen washout or body plethysmography (gold standard); then RV = FRC − ERV and TLC = FRC + IC.
- Gas dilution underestimates lung volumes in obstruction because it misses trapped gas.
- Typical adult values: TV about 500 mL, RV about 1-1.2 L, FRC about 3 L, VC 3-5 L, TLC about 6 L.
- FRC = where lung and chest wall recoil balance; lowest PVR; falls when supine and with obesity or pregnancy.
- Obstructive: ↓ FEV1/FVC, ↑ RV, FRC and RV/TLC, TLC normal or ↑. Restrictive: ↓ TLC (the defining finding), ↓ FRC and usually RV (RV can stay high with neuromuscular weakness), normal ratio.
Sources
- Physiology, Lung Capacity — StatPearls, NCBI Bookshelf (2023)
- Physiology, Functional Residual Capacity — StatPearls, NCBI Bookshelf (2022)
- Physiology, Residual Volume — StatPearls, NCBI Bookshelf (2023)
- Physiology, Tidal Volume — StatPearls, NCBI Bookshelf (2023)
- Vital Capacity — StatPearls, NCBI Bookshelf (2023)
- ERS/ATS technical standard on interpretive strategies for routine lung function tests — European Respiratory Journal (2022)
- Pocket Guide to COPD Diagnosis, Management and Prevention: 2026 Report — Global Initiative for Chronic Obstructive Lung Disease (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
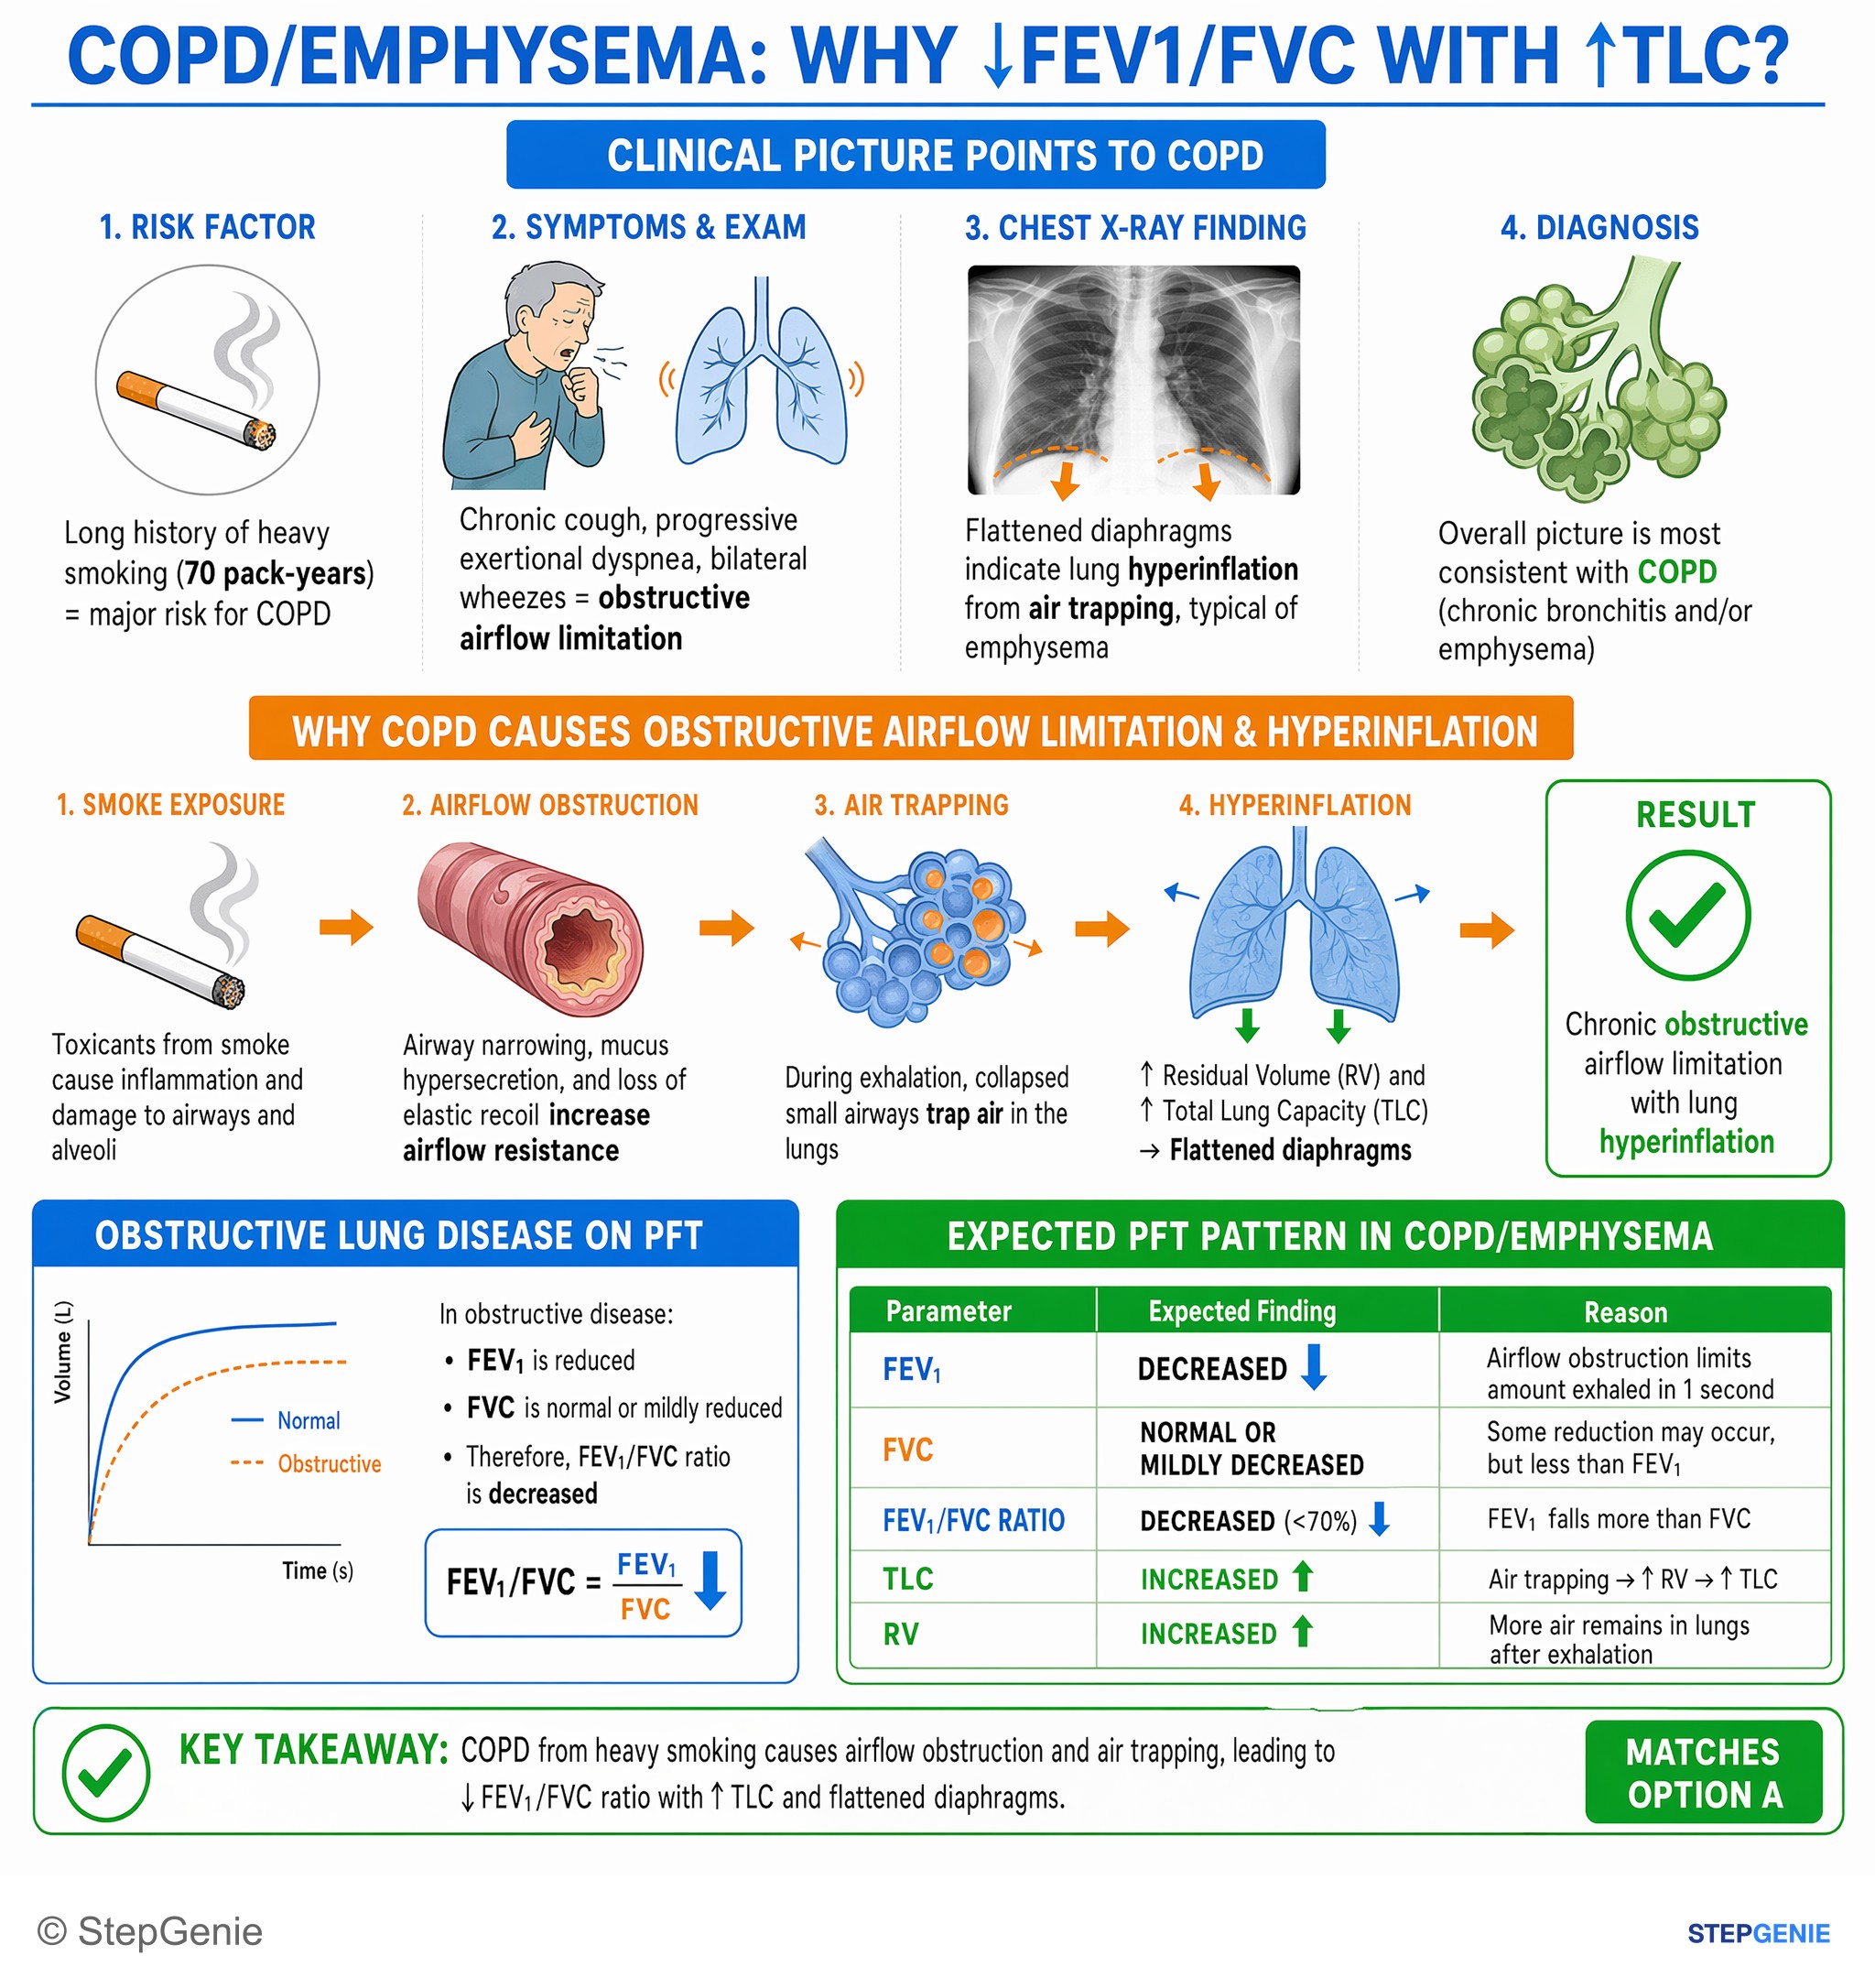
COPD/emphysema from heavy smoking causes obstructive pattern: ↓FEV1/FVC with air trapping → increased TLC and flattened diaphragms.
USMLE Step 1Frequently Asked Questions
What are the 4 lung volumes and 4 lung capacities?
The four lung volumes, from top to bottom, are inspiratory reserve volume, tidal volume, expiratory reserve volume and residual volume. The four capacities are sums of these: inspiratory capacity equals IRV plus TV, functional residual capacity equals ERV plus RV, vital capacity equals IRV plus TV plus ERV, and total lung capacity equals all four volumes. The phrase I Tidy Every Room lists the volumes in order and builds each capacity.
Which lung volumes cannot be measured by spirometry?
Spirometry cannot measure residual volume or any capacity that contains it, so RV, functional residual capacity and total lung capacity all need another method. The lab measures FRC by helium dilution, nitrogen washout or body plethysmography, then calculates RV as FRC minus ERV and TLC as FRC plus inspiratory capacity. Spirometry does measure tidal volume, IRV, ERV, inspiratory capacity and vital capacity.
What is the difference between helium dilution and body plethysmography?
In helium dilution the patient breathes a known concentration of helium until it equilibrates, and the degree of dilution gives FRC. It only measures gas in airspaces that communicate with open airways, so it underestimates lung volumes when air is trapped, as in severe COPD. Body plethysmography uses Boyle's law in a sealed box to measure all the gas in the thorax, including trapped gas, and is the gold standard.
What are normal lung volumes in adults?
Typical adult values are approximate: tidal volume about 500 mL in men and 400 mL in women, residual volume about 1 to 1.2 liters, functional residual capacity about 3 liters, vital capacity 3 to 5 liters and total lung capacity about 6 liters. Predicted values depend on height, sex, age and body size, so pulmonary function reports compare each result with the patient's own lower limit of normal.
What is functional residual capacity and what changes it?
Functional residual capacity is the air left in the lungs after a normal, passive exhalation, equal to expiratory reserve volume plus residual volume. It is the point where the lung's inward recoil and the chest wall's outward recoil balance, and pulmonary vascular resistance is lowest there. FRC increases with emphysema, age and upright posture, and decreases when lying supine and with obesity, pregnancy and pulmonary fibrosis.
How do lung volumes change in obstructive vs restrictive lung disease?
In obstructive disease such as COPD, air trapping raises residual volume, FRC and the RV/TLC ratio, total lung capacity is normal or increased, and the FEV1/FVC ratio is low. In restrictive disease, total lung capacity is below the lower limit of normal by definition; usually FRC and residual volume fall and FEV1 and FVC drop together, so the ratio stays normal, although residual volume can stay relatively high in neuromuscular or chest wall disease. A low FVC alone does not prove restriction.