Corynebacterium diphtheriae is an aerobic, gram-positive, club-shaped rod that causes diphtheria only when it carries the tox gene, delivered by a lysogenic β-phage; the toxin's A fragment ADP-ribosylates elongation factor 2 (EF-2) and shuts down protein synthesis. In the throat it makes a gray, adherent pseudomembrane that bleeds when scraped, often with a "bull neck"; absorbed toxin causes myocarditis (typically days 10-14) and neuropathy (palatal weakness, then peripheral neuropathy in weeks 3-6). Treat on clinical suspicion with diphtheria antitoxin (obtained from CDC) plus erythromycin or penicillin, and prevent it with the toxoid in DTaP, Tdap and Td.
Quick ID: the organism
| Feature | C. diphtheriae |
|---|---|
| Gram stain and shape | Gram-positive, club-shaped, nonmotile, noncapsulated rod |
| Arrangement | Palisades or V and L shapes (the "Chinese letters" of exam lore) |
| Granules | Metachromatic (polymetaphosphate) granules, bluish-purple with methylene blue |
| Catalase | Positive |
| Culture | Loeffler medium (brings out the granules) plus selective tellurite media such as Tinsdale: gray-black colonies on tellurite, black colonies with halos on Tinsdale |
| Toxin test | Elek immunodiffusion test (done only at CDC in the US) |
| Virulence | tox gene on a β-prophage (lysogenic conversion); toxin is made when iron is scarce |
| Spread and incubation | Mostly person to person by respiratory droplets; incubation 2-5 days (range 1-10) |
| Vaccine | Toxoid: formaldehyde-inactivated toxin that stays antigenic |
Where it sits among the other gram-positive rods is mapped in the gram-positive vs gram-negative table.
How the toxin works
- Lysogenic conversion: the toxin gene, tox, rides on a family of corynebacteriophages, the β-phage being the best studied. Only toxigenic strains cause classic diphtheria with myocarditis and neuropathy; nontoxigenic strains can still cause exudative pharyngitis, from mild to severe.
- Iron switch: when iron is scarce, iron comes off the repressor DtxR, so tox is derepressed and toxin is secreted at maximal rates.
- A-B toxin: fragment B (C-terminal) carries the receptor-binding and membrane-translocation domains; fragment A (N-terminal, 21 kDa) is the enzyme. It transfers ADP-ribose from NAD+ onto EF-2, the factor ribosomes need to translocate along mRNA, so protein synthesis stops and the cell dies.
- Same mechanism, different bug: Pseudomonas aeruginosa exotoxin A also ADP-ribosylates EF-2, a mechanism described as identical to diphtheria toxin fragment A (Pseudomonas clues and mimics).
- Classic mnemonic, ABCDEFG = ADP-ribosylation, β-prophage, Corynebacterium Diphtheriae, Elongation Factor 2, Granules.
Clinical presentation
- Respiratory diphtheria starts gradually: mild fever, sore throat, difficulty swallowing, malaise, poor appetite and hoarseness. The pseudomembrane appears within 2-3 days over the tonsils, pharynx, larynx or nares and can extend into the trachea. It is dirty gray, tough, fibrinous and so adherent that removing it causes bleeding.
- Bull neck: marked swelling of the submandibular area and neck with lymphadenopathy.
- Laryngeal spread threatens the airway: respiratory insufficiency from obstruction is one of the major complications.
- Cutaneous diphtheria: a scaling rash or ulcers with clearly demarcated edges and a membrane, slow to heal. US cutaneous isolates have usually been nontoxigenic, though imported toxigenic cases have been reported.
- Mortality: 5-10% overall, and up to 20% in children younger than 5 and adults older than 40. Most complications, including death, come from the toxin.
Complications timeline
| Complication | Usual timing | What you see |
|---|---|---|
| Airway obstruction | Early, as the membrane spreads | Stridor, respiratory distress |
| Myocarditis | By days 10-14 (Merck); can be early or weeks later (Pink Book) | Abnormal rhythms; can be fatal |
| Cranial neuropathy | From the first week (Merck); soft-palate paralysis most often in week 3 (Pink Book) | Nasal voice, nasal regurgitation, trouble swallowing |
| Peripheral neuropathy | Weeks 3-6 (Merck); eye, limb and diaphragm paralysis after week 5 (Pink Book) | Can be mistaken for Guillain-Barré syndrome |
| Kidney | Severe disease | Acute kidney failure |
Diagnosis
- Treat first. CDC: begin presumptive therapy quickly, before confirmatory results are available. The diagnosis is clinical.
- Specimens: swabs of the nares and oropharynx, taken from beneath the membrane (or a piece of the membrane itself).
- Culture on a selective tellurite-containing medium separates C. diphtheriae and C. ulcerans from other corynebacteria. Gram stain shows gram-positive club-shaped rods, and methylene blue shows the metachromatic granules.
- Prove toxin production with the Elek test, an immunodiffusion assay in which an antitoxin-soaked strip in the agar forms a precipitin line with secreted toxin. PCR for the tox gene is not enough: CDC notes that most US C. diphtheriae carrying tox don't express it.
- Report it: health departments investigate every suspected case and trace close contacts.
Treatment (CDC, 2026)
| Step | What to do |
|---|---|
| Diphtheria antitoxin (DAT) | Recommended for respiratory diphtheria, given promptly on suspicion. It neutralizes circulating toxin but not toxin already fixed to tissues, so delay costs heart and nerves. DAT is equine, so sensitivity testing comes first; Merck gives 20,000-100,000 units IM or IV, scaled to site, severity and duration. Usually not needed for cutaneous disease |
| Getting DAT | Not made in the US; CDC releases it under an expanded-access investigational new drug (EA-IND) protocol. The treating physician calls the state health department, then the CDC Emergency Operations Center (770-488-7100) |
| Antibiotics | CDC: only erythromycin or penicillin is recommended, with attention to high penicillin resistance reported in several regions. Merck gives 14-day courses (and also lists azithromycin). Patients are usually no longer contagious 48 hours after antibiotics start |
| Isolation | Droplet precautions (contact precautions for skin disease) until antibiotics are finished and two cultures taken 24 hours apart after therapy are negative |
| Supportive care | Airway first; recovery is slow, and patients with myocarditis must avoid exertion |
| Vaccinate | Give a diphtheria toxoid vaccine during convalescence if not up to date: infection doesn't always confer immunity |
Close contacts
- Quarantine and monitor for 7-10 days after the last exposure.
- Take nasal and throat cultures.
- Give prophylaxis: a single IM dose of benzathine penicillin G (600,000 units under age 6; 1.2 million units at 6 or older) or 7-10 days of oral erythromycin. CDC prefers the IM dose when adherence is a concern.
- Vaccinate anyone not up to date, and give another dose if the last diphtheria-containing vaccine was more than 5 years ago.
Prevention: DTaP, Tdap and Td
| Vaccine | Who | Current CDC schedule |
|---|---|---|
| DTaP | Children younger than 7 | 5 doses: 2, 4 and 6 months, 15-18 months, 4-6 years |
| Tdap | Adolescents; pregnancy | 1 dose at 11-12 years; 1 dose in every pregnancy, preferably early in weeks 27-36 |
| Td or Tdap | Adults | Every 10 years |
Uppercase letters mean full-strength components and lowercase mean reduced amounts, so the "d" in Tdap and Td is a smaller diphtheria toxoid dose. After the primary series more than 95% of recipients reach the protective antitoxin level (above 0.1 IU/mL). The pertussis side of these vaccines is covered in Bordetella pertussis.
How USMLE tests diphtheria
| Look-alike | Its clues | Why it isn't diphtheria |
|---|---|---|
| Strep pharyngitis (GAS) | Fever, tonsillar exudate, tender anterior nodes, sandpaper rash | Patchy exudate, not a tightly adherent membrane that bleeds when scraped; no toxin myocarditis or neuropathy |
| Infectious mononucleosis (EBV) | Exudative pharyngitis, posterior (and anterior) cervical nodes, splenomegaly in about half, heterophile antibodies | No adherent membrane that bleeds |
| Epiglottitis (H. influenzae type b) | Drooling, tripod position, muffled voice | Gram-negative coccobacillus; swollen epiglottis, not a membrane |
| Pertussis | Paroxysmal cough, whoop, post-tussive vomiting | No membrane |
Traps:
- Antibiotics stop toxin production and spread but don't neutralize circulating toxin: the answer is antitoxin plus antibiotic, given before culture results.
- A positive tox PCR doesn't prove a toxigenic strain; the Elek test does.
- Recovered patients still need the vaccine.
- Toxin mechanism questions: EF-2 for diphtheria toxin and Pseudomonas exotoxin A.
Practice question
A 7-year-old boy who recently arrived in the US with no vaccination records has 3 days of low-grade fever, malaise, sore throat and difficulty swallowing. His neck is diffusely swollen, with tender submandibular lymph nodes. A gray membrane covers both tonsils and the posterior pharynx, and it bleeds when the examiner tries to lift its edge with a swab. He has no stridor. A Gram stain of material from beneath the membrane shows gram-positive, club-shaped rods. Which is the most appropriate next step?
A. Request diphtheria antitoxin through the health department and CDC, and start erythromycin or penicillin now B. Send cultures and an Elek test, and treat only if toxin production is confirmed C. Start penicillin alone, since antibiotics clear both the organism and its toxin D. Give a dose of diphtheria toxoid-containing vaccine now as treatment E. Send a rapid strep test and start amoxicillin
Answer: A. An adherent gray pseudomembrane that bleeds, a bull neck and no record of vaccination mean respiratory diphtheria. CDC and the Pink Book call for antitoxin and antibiotics without waiting for laboratory confirmation, with droplet precautions and a report to the health department. Antitoxin only neutralizes toxin that hasn't yet bound to tissue, which is why speed protects the heart (myocarditis, typically days 10-14) and nerves.
- B: waiting for the Elek test, which only CDC performs in the US, lets toxin fix to tissues.
- C: antibiotics stop toxin production and transmission, but only antitoxin neutralizes the toxin already circulating.
- D: the toxoid is given during convalescence because infection doesn't always confer immunity; it doesn't treat active disease. (At age 7 he would get Tdap or Td, since DTaP is for children younger than 7.)
- E: strep causes a patchy exudate, not an adherent membrane that bleeds when lifted, and group A strep is a gram-positive coccus in chains, not a club-shaped rod; delaying antitoxin is dangerous.
Key takeaways
- Gram-positive club-shaped rod, palisades/V-L shapes, metachromatic granules, catalase-positive; Loeffler medium and selective tellurite media (Tinsdale).
- β-prophage tox gene (lysogenic conversion); toxin made under low iron (DtxR).
- A-B toxin; fragment A ADP-ribosylates EF-2 with NAD+, like Pseudomonas exotoxin A.
- Gray adherent pseudomembrane that bleeds, bull neck; then myocarditis (days 10-14) and neuropathy (palate first, then peripheral at weeks 3-6).
- Elek test proves toxin; a tox PCR alone doesn't.
- Antitoxin (from CDC, EA-IND) plus erythromycin or penicillin, on suspicion; two negative cultures 24 hours apart end isolation.
- Contacts: cultures, benzathine penicillin G once or erythromycin 7-10 days, and a booster if their last dose was more than 5 years ago.
- DTaP at 2, 4, 6, 15-18 months and 4-6 years; Tdap at 11-12 and in every pregnancy; Td or Tdap every 10 years.
Sources
- Clinical Guidance for Diphtheria — CDC (2026)
- Clinical Features of Diphtheria — CDC (2026)
- Diphtheria Antitoxin — CDC (2026)
- Laboratory Testing for Diphtheria — CDC (2026)
- Diphtheria Vaccine Recommendations — CDC (2026)
- Chapter 7: Diphtheria — CDC Pink Book (2024)
- Pertussis Vaccination Recommendations — CDC (2025)
- Diphtheria — Merck Manual Professional Edition (2026)
- Diphtheria — StatPearls, NCBI Bookshelf (2024)
- Corynebacterium Diphtheriae — Medical Microbiology, 4th ed., NCBI Bookshelf (1996)
- Pseudomonas — Medical Microbiology, 4th ed., NCBI Bookshelf (1996)
- Acute Pharyngitis — StatPearls, NCBI Bookshelf (2024)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
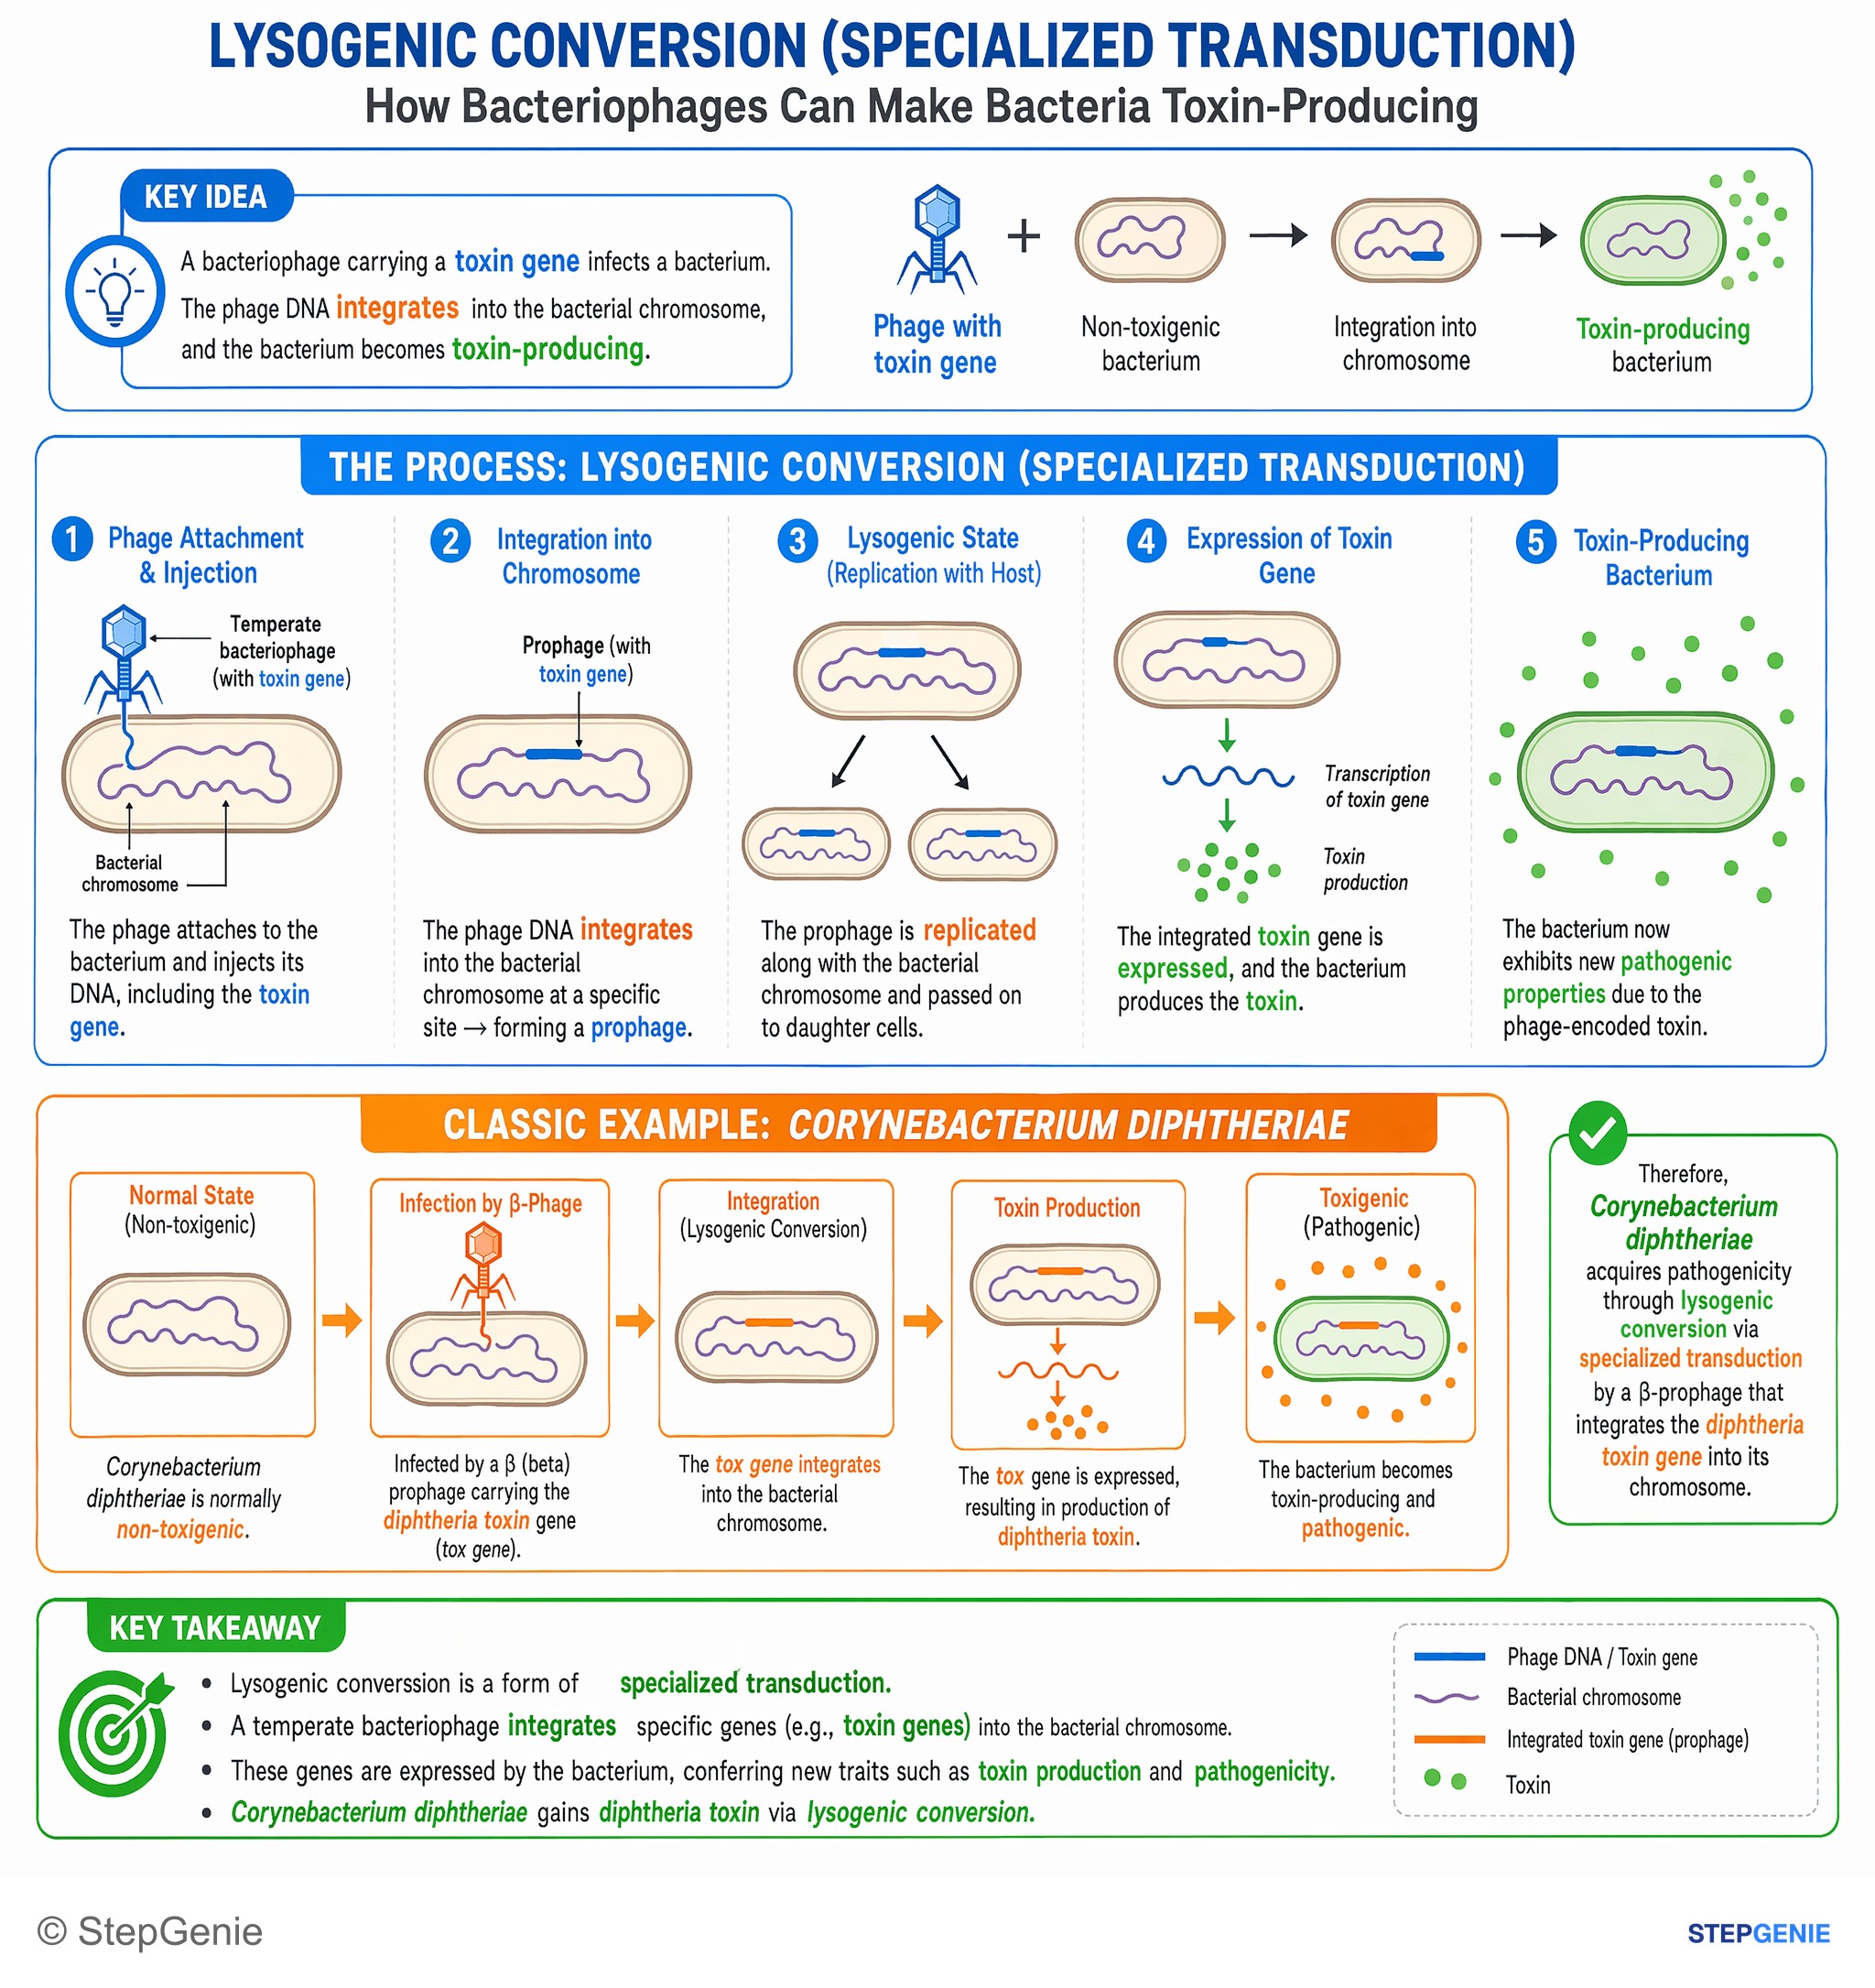
Corynebacterium diphtheriae gains diphtheria toxin via lysogenic conversion (specialized transduction by temperate bacteriophage…
USMLE Step 1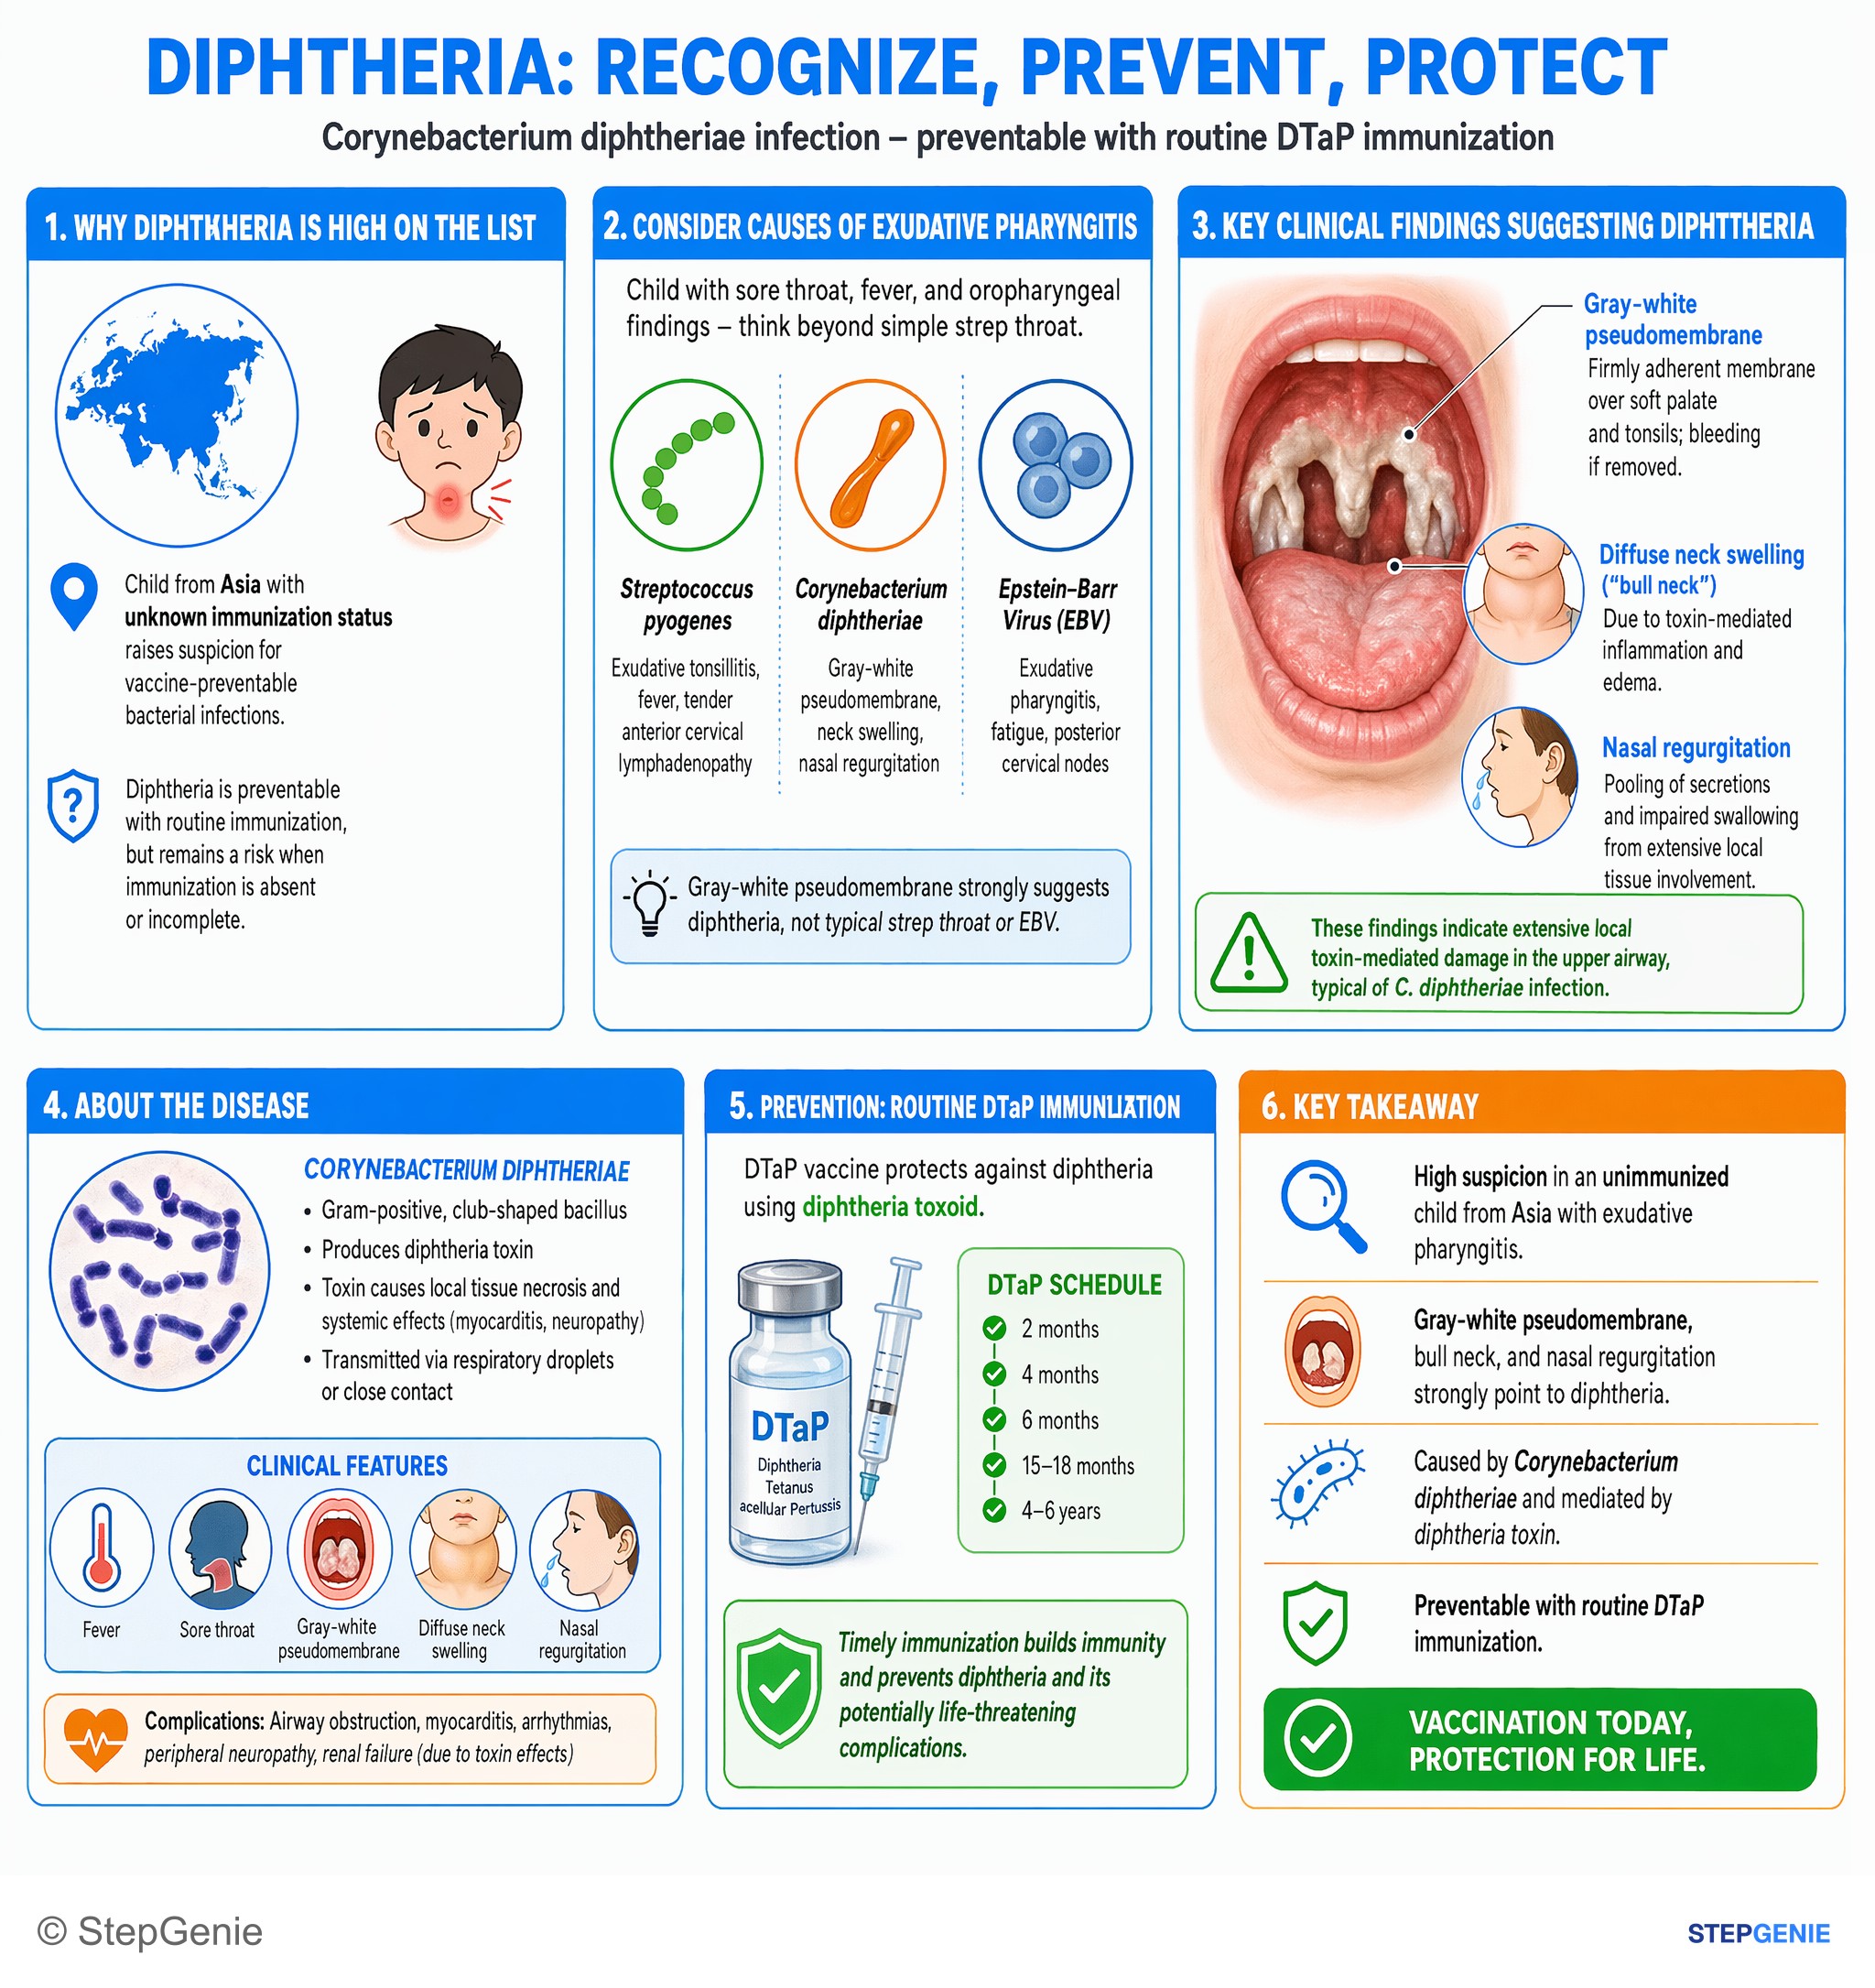
Diphtheria due to Corynebacterium diphtheriae causes gray pseudomembranes, neck swelling, nasal regurgitation; preventable with routine…
USMLE Step 1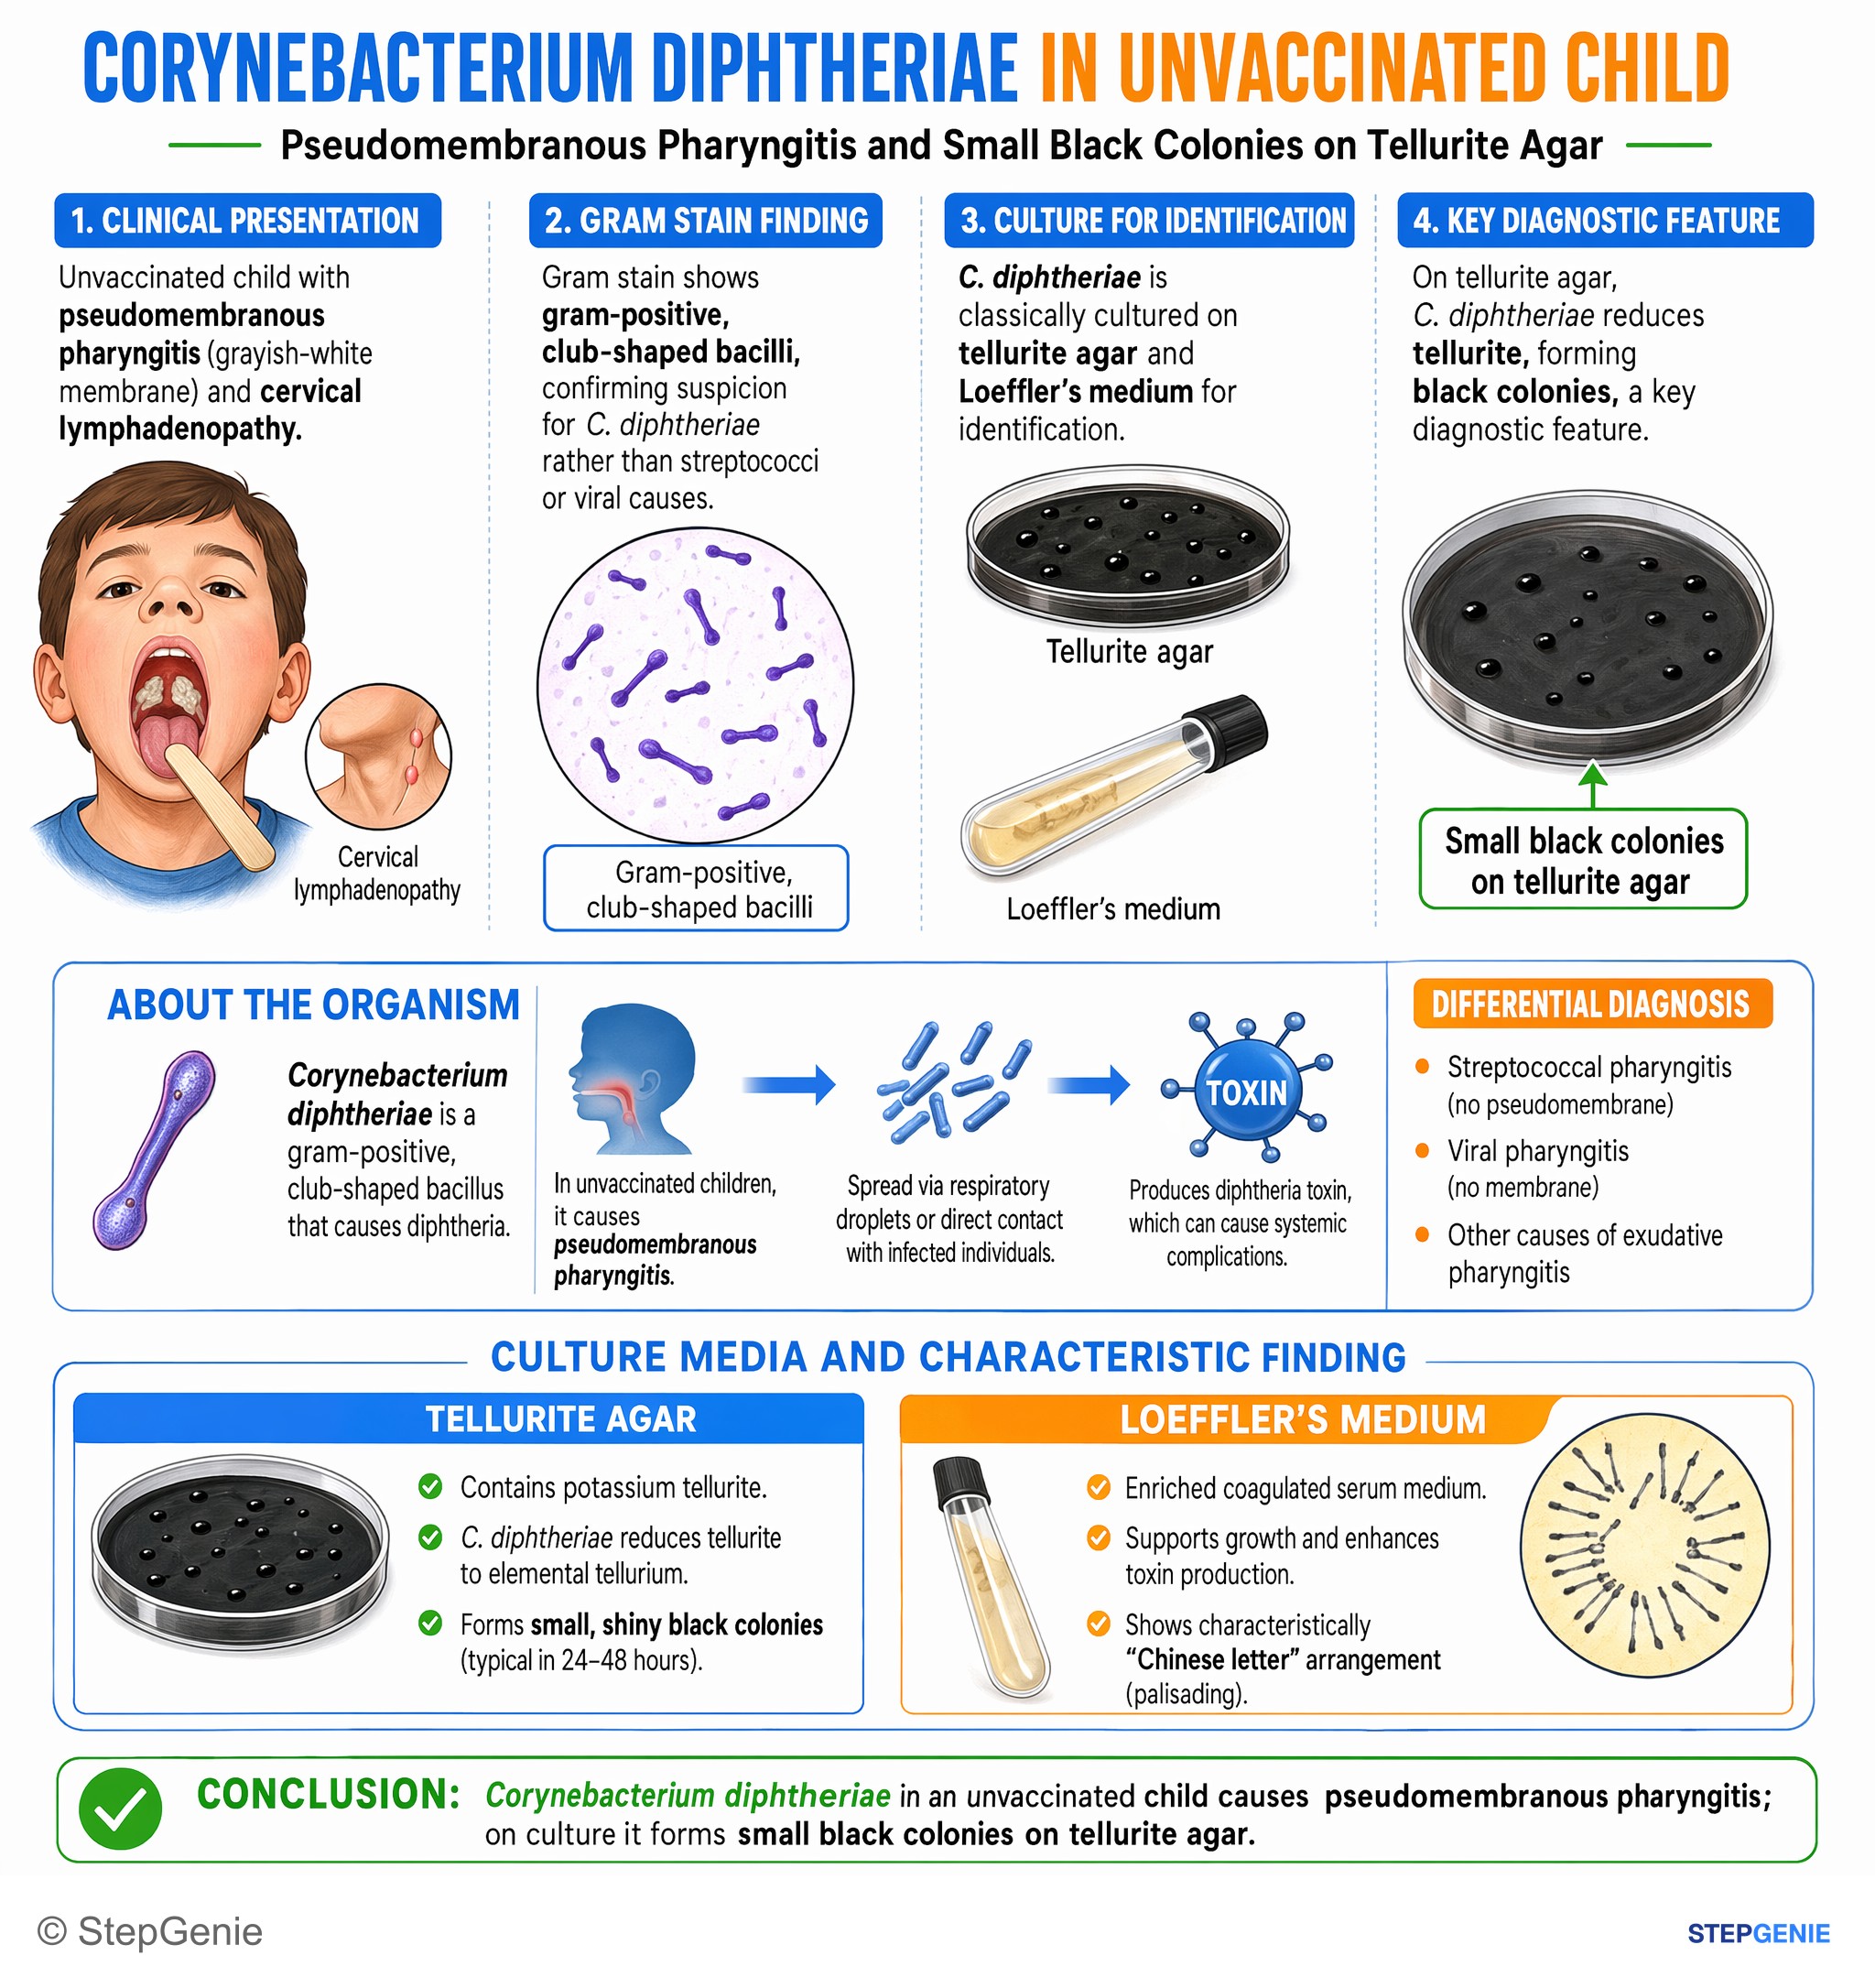
Corynebacterium diphtheriae in an unvaccinated child causes pseudomembranous pharyngitis; on culture it forms small black colonies on…
USMLE Step 1Frequently Asked Questions
What is the mechanism of diphtheria toxin?
Diphtheria toxin is an A-B exotoxin. The B fragment binds the host cell and moves the toxin across the membrane, and the A fragment transfers ADP-ribose from NAD+ onto elongation factor 2 (EF-2), so protein synthesis stops and the cell dies. The toxin gene is carried by a lysogenic beta-phage and is switched on when iron is scarce. Pseudomonas exotoxin A works the same way.
How is diphtheria diagnosed?
Diphtheria is a clinical diagnosis, and treatment starts before results return. Swabs are taken from the nose and throat, ideally from beneath the membrane, and cultured on Loeffler medium and selective tellurite media such as Tinsdale. Gram stain shows gram-positive club-shaped rods, and methylene blue shows metachromatic granules. Toxin production is confirmed with the Elek immunodiffusion test, which only CDC performs in the US; a positive PCR for the tox gene alone does not prove the strain makes toxin.
What is the treatment for diphtheria?
Suspected respiratory diphtheria is treated right away with diphtheria antitoxin plus an antibiotic, without waiting for lab confirmation. In the US the antitoxin is obtained from CDC through the state health department under an expanded-access protocol. CDC recommends only erythromycin or penicillin. Droplet precautions continue until antibiotics are finished and two cultures taken 24 hours apart are negative, and patients are vaccinated during recovery because infection does not always give immunity.
What are the complications of diphtheria and when do they happen?
Airway obstruction can occur early as the membrane spreads to the larynx. Myocarditis typically appears around days 10 to 14 but can come earlier or weeks later, causing abnormal heart rhythms that can be fatal. Cranial neuropathy, such as soft-palate paralysis, is most common around the third week, and peripheral neuropathy follows in weeks 3 to 6. Overall case fatality is 5 to 10 percent, and up to 20 percent in young children and adults over 40.
How are close contacts of a diphtheria patient managed?
The health department identifies close contacts, who are quarantined and monitored for 7 to 10 days after their last exposure. They have nasal and throat cultures and receive antibiotic prophylaxis: a single intramuscular dose of benzathine penicillin G or a 7 to 10 day course of oral erythromycin. Anyone not up to date with diphtheria vaccine is vaccinated, and contacts whose last dose was more than 5 years ago get another dose.
What is the current diphtheria vaccine schedule?
Diphtheria vaccines contain toxoid, an inactivated toxin. CDC recommends five doses of DTaP at 2, 4 and 6 months, 15 to 18 months, and 4 to 6 years, then one dose of Tdap at 11 to 12 years. Tdap is also given in every pregnancy, preferably early in weeks 27 to 36. Adults get Td or Tdap every 10 years. The lowercase d in Tdap and Td means a reduced amount of diphtheria toxoid.