Listeria monocytogenes is one of those Step 1 bugs that’s deceptively “small” on the page but shows up everywhere in questions—pregnancy, neonatal sepsis, meningitis in the elderly, and “why ampicillin?” moments. If you can recognize its risk groups, intracellular lifestyle, and classic lab clues, you’ll pick up a lot of easy points.
Quick ID: What is Listeria monocytogenes?
Listeria monocytogenes is a Gram-positive rod (coccobacillus) that is:
- Facultative intracellular
- Motile (classic “tumbling motility”)
- Catalase-positive
- Beta-hemolytic
- Often associated with unpasteurized dairy and deli meats
High-yield “one-liner”
Listeria = Gram+ rod that causes meningitis/sepsis in neonates, pregnant patients, elderly, and immunocompromised; treated with ampicillin.
Where it lives + how you get it (Epidemiology)
Common sources (very testable)
- Unpasteurized milk/soft cheeses (e.g., queso fresco, brie)
- Deli meats/hot dogs, refrigerated ready-to-eat foods
- Can grow at cold temperatures → survives and multiplies in the fridge
High-risk populations (memorize this list)
- Pregnant patients (often mild illness in mom → severe fetal/neonatal disease)
- Neonates
- Elderly
- Immunocompromised (e.g., transplant, steroids, malignancy)
Pathophysiology: why Listeria is a “favorite” organism
Listeria’s Step 1 magic is its intracellular survival and cell-to-cell spread.
Key virulence factors
- Internalins: help invasion into epithelial cells
- Listeriolysin O: allows escape from phagolysosome (think “pore-forming toxin”)
- Actin polymerization: forms actin rockets → spreads cell-to-cell
Intracellular spread = immune implications
Because it’s intracellular, control relies heavily on:
- Cell-mediated immunity (T cells, macrophage activation)
- Patients with impaired cellular immunity are at higher risk
Classic USMLE mechanism summary
- Invades GI tract after ingestion
- Enters macrophages/epithelial cells
- Escapes phagolysosome via listeriolysin O
- Uses actin to push into adjacent cells
- Disseminates → bloodstream → crosses placenta and/or blood-brain barrier
Clinical presentations (what it looks like on questions)
1) Pregnancy-associated listeriosis
Mom: often mild, flu-like illness (fever, myalgias), sometimes GI symptoms
Fetus/newborn: can be severe
Complications:
- Spontaneous abortion
- Stillbirth
- Preterm labor
- Neonatal sepsis/meningitis
Step clue: “Pregnant patient + soft cheese + fever” → think Listeria.
2) Neonatal infection: early vs late (know the split)
| Syndrome | Timing | Typical features | Mechanism |
|---|---|---|---|
| Early-onset disease | 0–6 days | Sepsis, pneumonia, diffuse rash | Often transplacental |
| Late-onset disease | 7–28 days | Meningitis, irritability, poor feeding | Often acquired during/after birth |
Granulomatosis infantiseptica (very HY buzzword): disseminated neonatal listeriosis with granulomas/abscesses and severe sepsis.
3) Meningitis in elderly/immunocompromised
Listeria is a major cause of meningitis in:
- Older adults
- Immunocompromised
- Sometimes pregnant patients
Step clue: “Elderly with meningitis; CSF suggests bacterial meningitis; add ampicillin” → covering Listeria.
4) Gastroenteritis (less “sexy” but real)
In immunocompetent hosts, Listeria can cause:
- Febrile gastroenteritis (diarrhea, fever) after contaminated food outbreaks
Diagnosis: how questions expect you to confirm it
Lab ID features (high-yield)
- Gram stain: Gram-positive rods (may appear as coccobacilli)
- Culture: beta-hemolytic
- Motility: “tumbling motility” at room temperature
- Catalase-positive (helps differentiate from many streptococci)
Clinical diagnosis shortcuts
Often, Step questions don’t require definitive culture—recognize based on:
- Risk group + food exposure + meningitis/sepsis
- Need for ampicillin coverage in meningitis
Treatment (Step 1/2 essentials)
First-line therapy
- Ampicillin (or penicillin G) is the backbone
- Often combined with gentamicin for synergy in severe disease (especially invasive infections)
If penicillin allergy (common question twist)
- TMP-SMX is a classic alternative
Meningitis empiric therapy tie-in (super HY)
In suspected bacterial meningitis:
- Neonates and older adults/immunocompromised require empiric coverage for Listeria → ampicillin is added.
High-yield associations & “buzz phrases”
Must-know associations
- Unpasteurized dairy / deli meats
- Grows in the cold (refrigeration doesn’t protect you)
- Facultative intracellular
- Actin rockets
- Listeriolysin O
- Transplacental spread → neonatal sepsis/meningitis
- Meningitis in elderly → add ampicillin
Rapid “differentiate from other Gram+ rods”
| Organism | Key clue | Major disease | Treatment pearl |
|---|---|---|---|
| Listeria | Tumbling motility, cold growth, intracellular | Neonatal sepsis/meningitis, meningitis in elderly | Ampicillin (± gentamicin) |
| Corynebacterium diphtheriae | Pseudomembrane, bull neck, toxin | Pharyngitis, myocarditis, neuropathy | Erythromycin + antitoxin |
| Bacillus anthracis | “Medusa head” colonies, black eschar, inhalational disease | Anthrax | Ciprofloxacin/doxycycline |
| Clostridium tetani/botulinum/perfringens/difficile | Anaerobic, spore-formers | Tetanus/botulism/gas gangrene/C. diff colitis | Varies; often antitoxin + antibiotics |
First Aid cross-references (where it “lives” in FA)
You’ll typically see Listeria emphasized in First Aid under:
- Gram-positive bacilli (Listeria listed with distinguishing features like tumbling motility)
- Meningitis—empiric treatment by age group (ampicillin added for Listeria coverage)
- TORCH/intrauterine infections concepts (especially transplacental infection → neonatal disease)
Tip: When you review FA tables, annotate Listeria with: “pregnant + soft cheese,” “elderly meningitis add ampicillin,” and “actin rockets.” Those are the recurring question stems.
USMLE-style checkpoints (self-test)
If you can answer these quickly, you’re in great shape:
- Pregnant patient with fever after eating unpasteurized cheese → most likely organism? Listeria
- Elderly patient with bacterial meningitis—what antibiotic must be included empirically? Ampicillin
- Intracellular Gram+ rod with actin-based cell-to-cell spread → virulence mechanism? Actin polymerization; listeriolysin O for phagolysosome escape
- Why does refrigeration not prevent infection? Listeria grows at cold temperatures
- Alternative in penicillin allergy? TMP-SMX
Take-home summary (what to memorize)
- Who: Pregnant, neonates, elderly, immunocompromised
- Where from: Unpasteurized dairy, deli meats, grows in cold
- How it causes disease: Facultative intracellular, listeriolysin O, actin rockets
- What it causes: Neonatal sepsis/meningitis, meningitis in elderly, pregnancy complications
- Treat: Ampicillin (± gentamicin); TMP-SMX if allergic
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
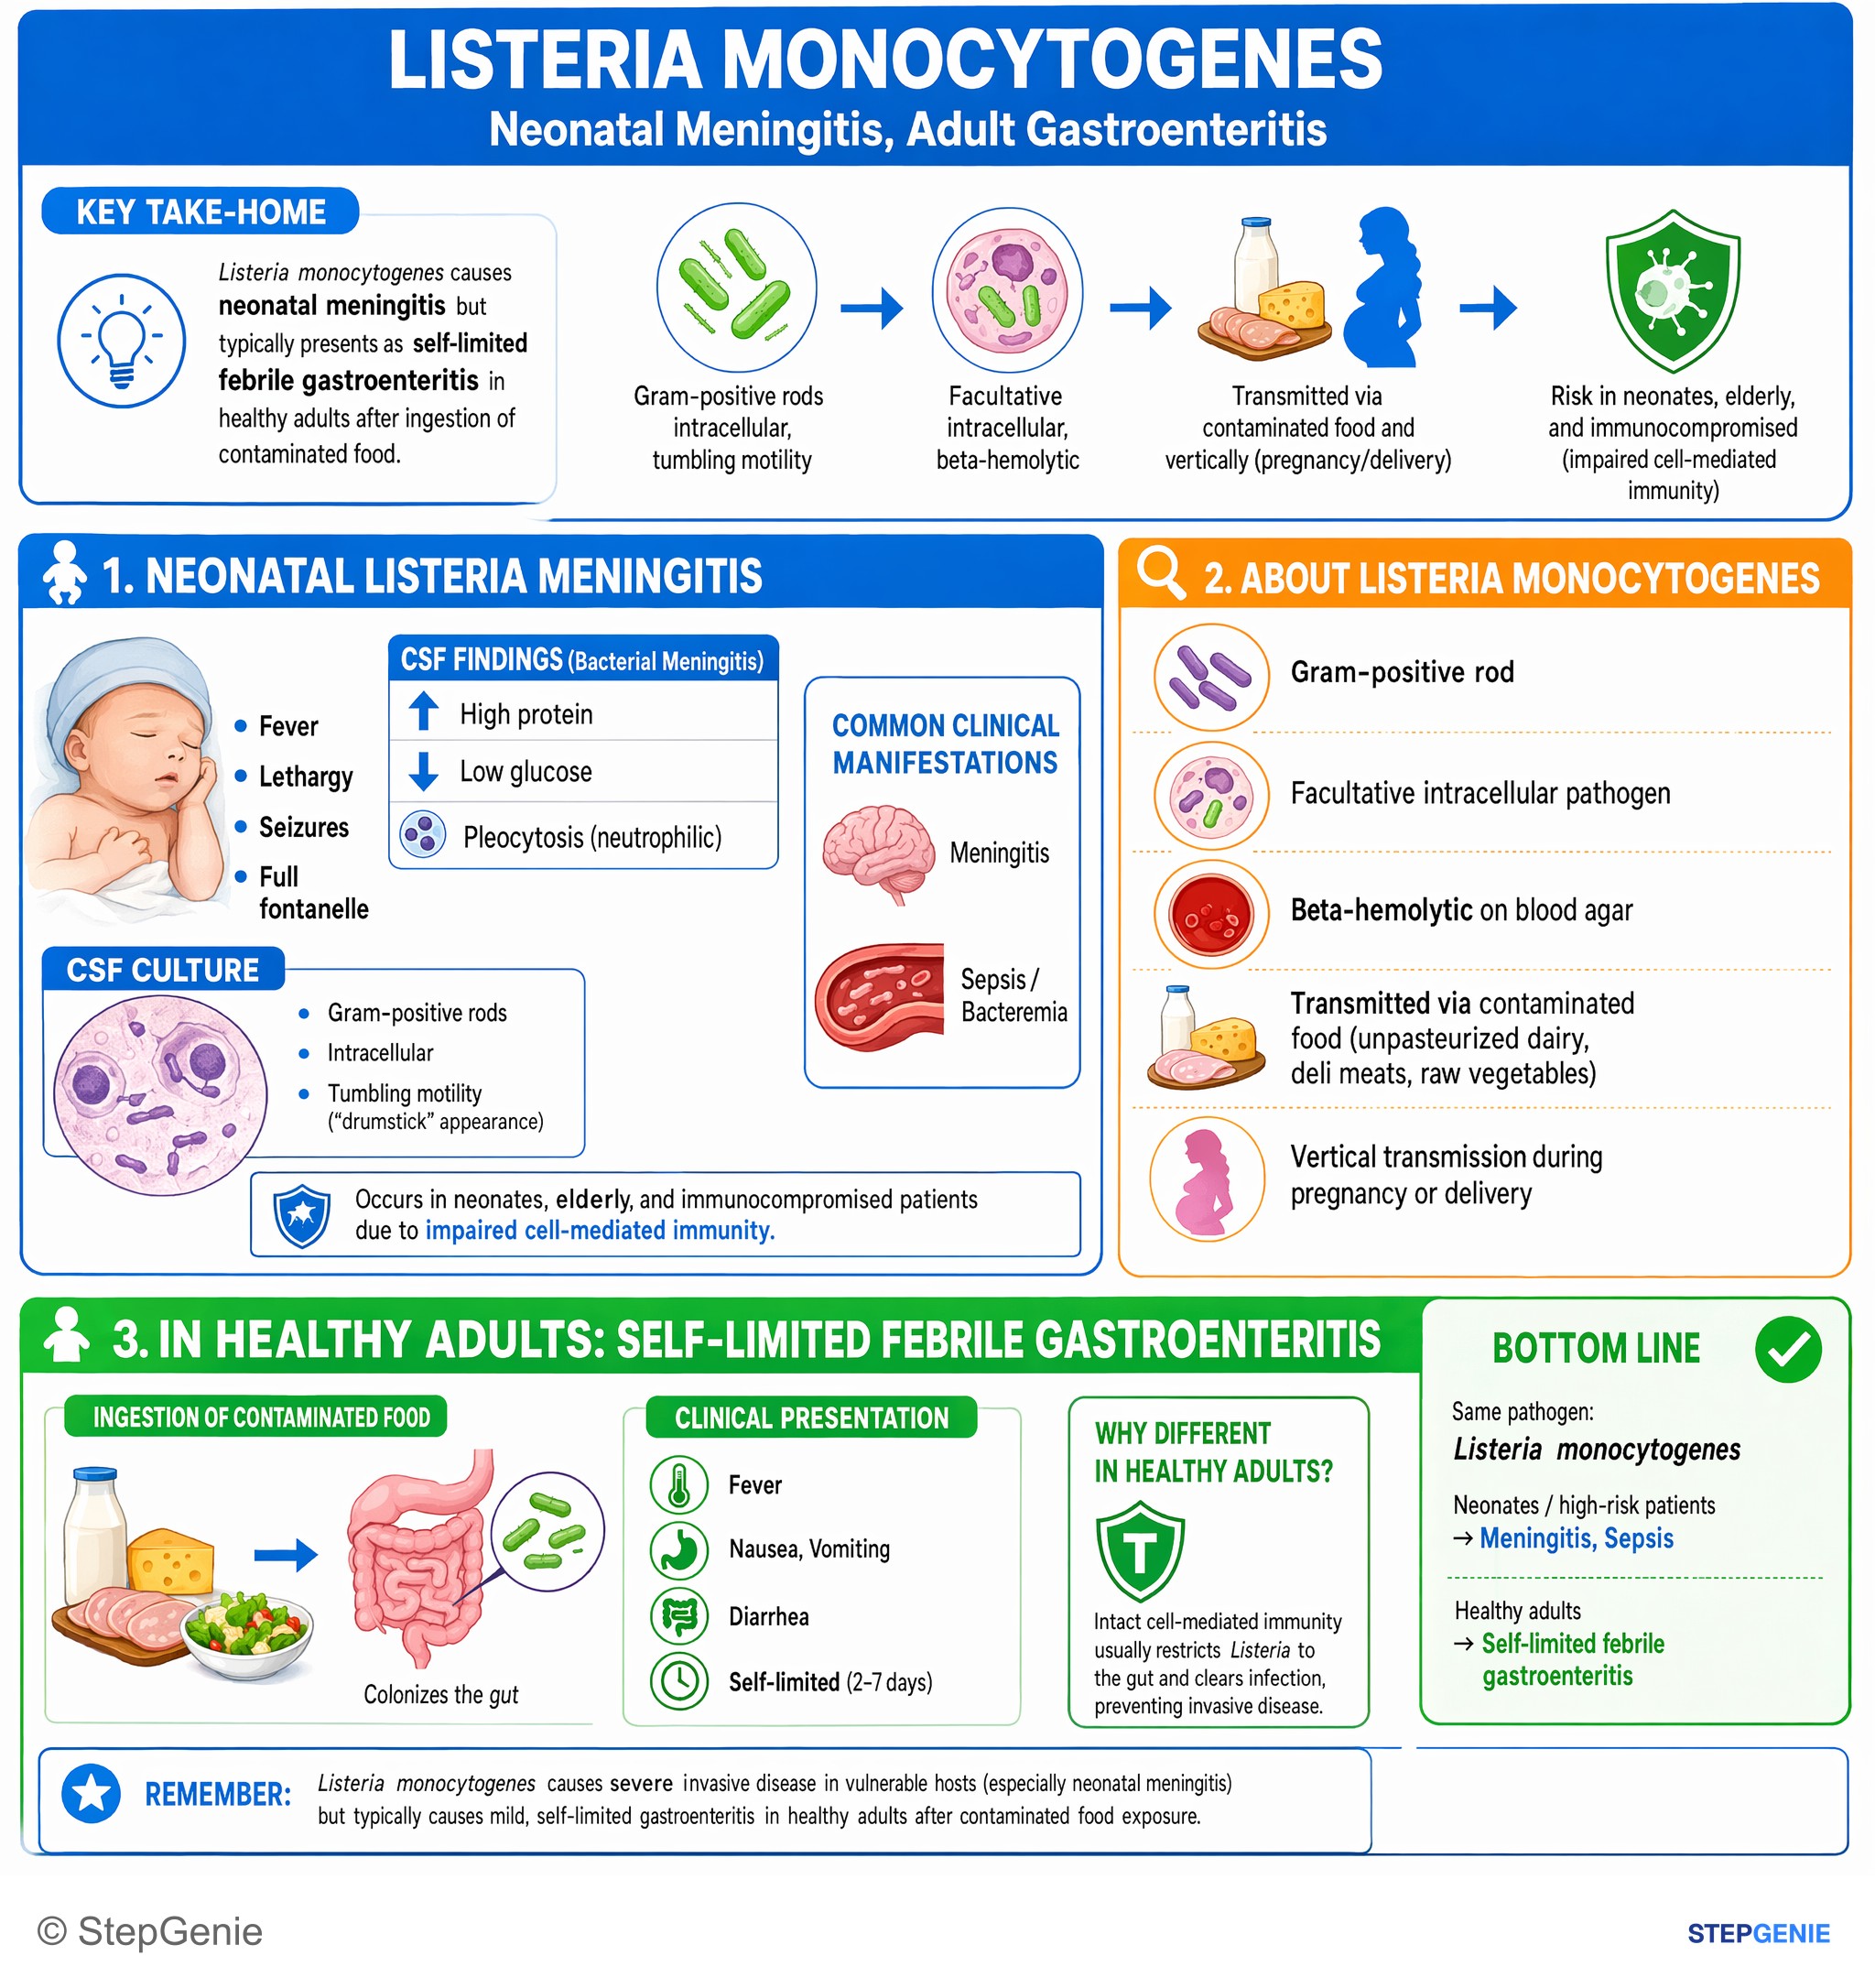
Listeria monocytogenes causes neonatal meningitis but typically presents as self-limited febrile gastroenteritis in healthy adults after…
USMLE Step 1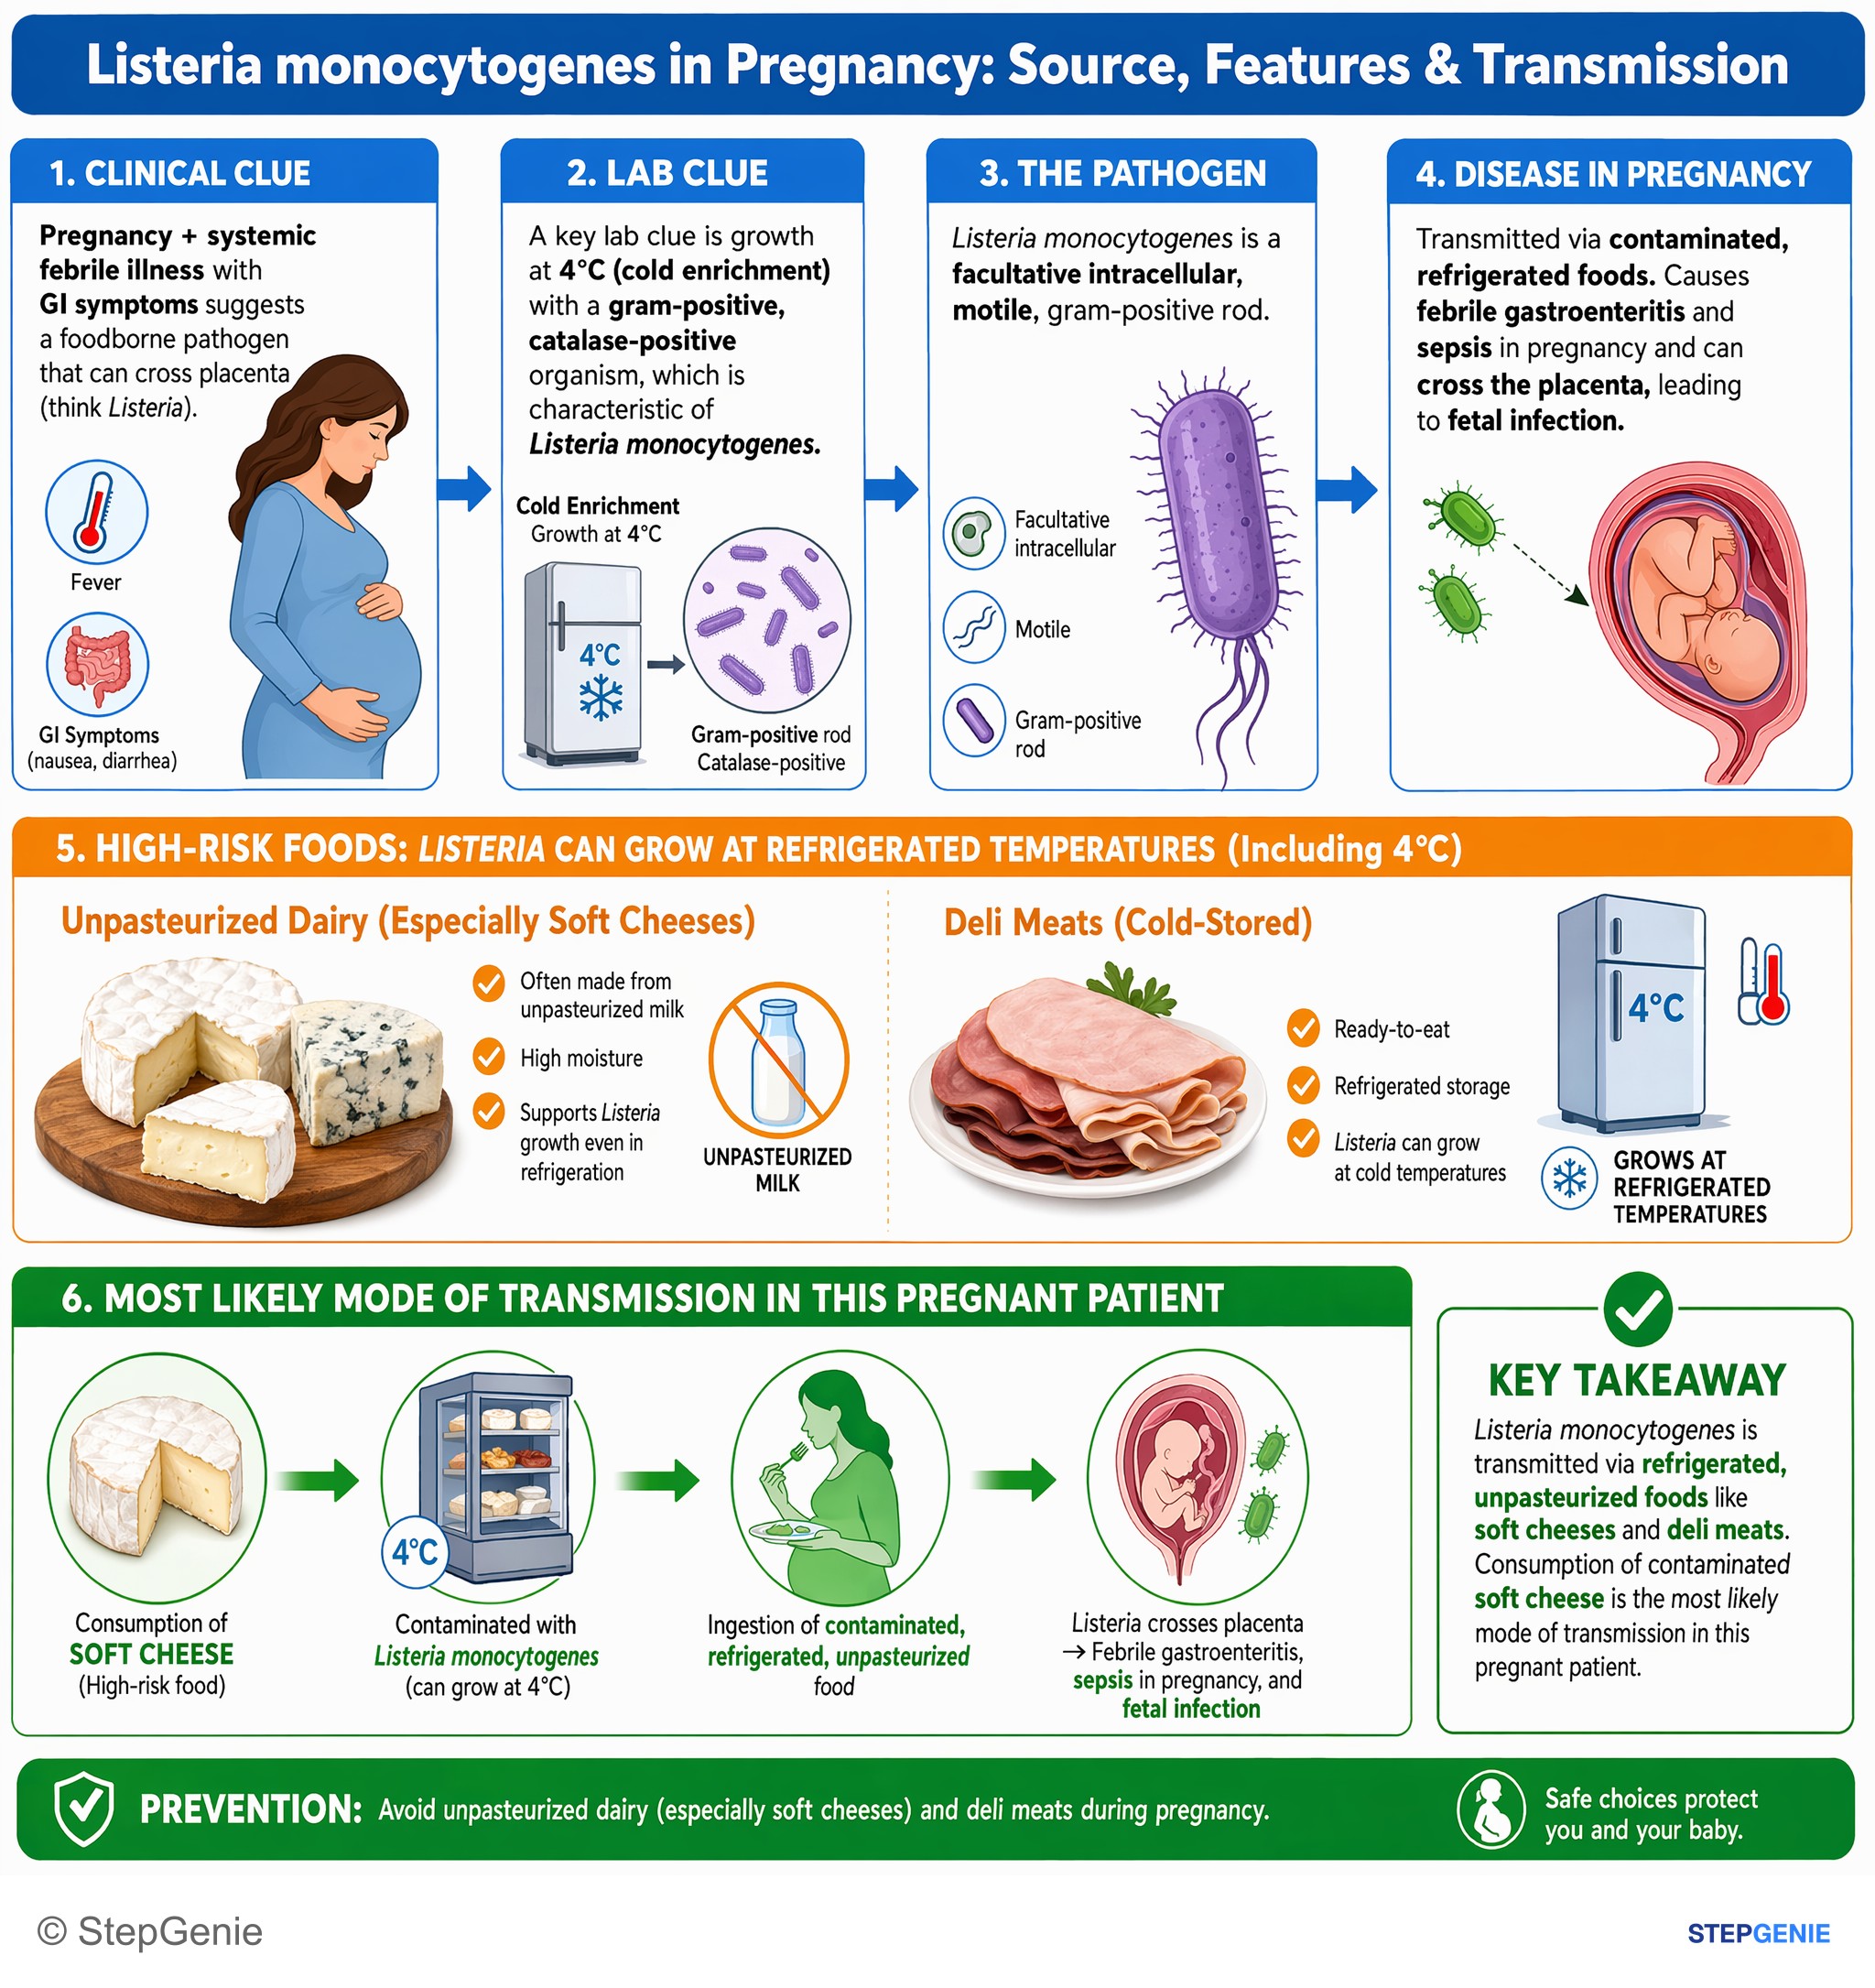
Listeria monocytogenes causes febrile gastroenteritis and sepsis in pregnancy; transmitted via refrigerated, unpasteurized foods like soft…
USMLE Step 1Frequently Asked Questions
Why does Listeria cause severe disease in pregnant patients, neonates, the elderly, and immunocompromised patients?
Listeria causes severe disease in these groups because it is a facultative intracellular organism that depends on cell-mediated immunity for control. It invades epithelial cells and macrophages, escapes the phagolysosome with listeriolysin O, and spreads cell-to-cell using actin polymerization. That intracellular lifestyle makes patients with impaired cellular immunity especially vulnerable, and it also allows dissemination to the bloodstream, placenta, and central nervous system.
How do you recognize Listeria monocytogenes on a Step 1 question stem?
The classic recognition pattern is a Gram-positive rod with tumbling motility, beta-hemolysis, catalase positivity, and exposure to unpasteurized dairy or deli meats. Question stems often pair those clues with a high-risk patient, such as a pregnant patient with fever after soft cheese, a neonate with sepsis or meningitis, or an elderly patient with meningitis who needs ampicillin coverage.
What is the first-line treatment for Listeria monocytogenes?
Ampicillin is the first-line treatment for Listeria monocytogenes. Penicillin G is also used, and gentamicin is often added for synergy in severe invasive disease. A common testing point is meningitis empiric therapy, where neonates, older adults, and immunocompromised patients need ampicillin added specifically to cover Listeria. If there is a penicillin allergy, TMP-SMX is a classic alternative.
How do you tell Listeria apart from other Gram-positive rods?
Listeria is distinguished by tumbling motility, growth at cold temperatures, and an intracellular lifestyle. It is a Gram-positive coccobacillus that is also beta-hemolytic and catalase-positive. Those features help separate it from Corynebacterium diphtheriae, which is associated with pseudomembrane and toxin-mediated disease, Bacillus anthracis, which causes anthrax, and Clostridium species, which are anaerobic spore-formers.
What neonatal infections does Listeria cause, and how do early-onset and late-onset disease differ?
Listeria causes neonatal sepsis and meningitis, and the timing helps distinguish the presentation. Early-onset disease occurs in the first 0 to 6 days and usually presents with sepsis, pneumonia, and a diffuse rash, often from transplacental transmission. Late-onset disease occurs from 7 to 28 days and more often presents as meningitis with irritability and poor feeding, typically acquired during or after birth.