Leishmania is an obligate intracellular protozoan spread by the bite of female phlebotomine sand flies: the fly injects flagellated promastigotes, macrophages engulf them, and they become small amastigotes (Leishman-Donovan bodies) that multiply inside macrophages. It causes three syndromes: a painless skin ulcer with raised borders (cutaneous), destruction of the nose and mouth years later (mucosal, mainly L. braziliensis), and visceral leishmaniasis, or kala-azar (L. donovani, L. infantum), with fever, weight loss, a large spleen, pancytopenia and hypergammaglobulinemia. In the US, liposomal amphotericin B is FDA-approved for visceral disease, and oral miltefosine is approved for selected species, including L. donovani visceral disease (it is contraindicated in pregnancy). Sodium stibogluconate, the classic exam answer, is a pentavalent antimonial that is not FDA-approved or commercially available in the US.
Promastigote vs amastigote: the life cycle
| Feature | Promastigote | Amastigote |
|---|---|---|
| Shape | Elongate and slender, about 10-12 µm, with a long flagellum at the front end | Ovoid, 1-5 µm long by 1-2 µm wide, with a nucleus and a kinetoplast; no long flagellum |
| Where it lives | Sand fly gut and proboscis | Inside macrophages and other mononuclear phagocytes in human tissue |
| Role | Infective form injected by the bite | Tissue and diagnostic form: the "LD bodies" seen on Giemsa stain |
- An infected female sand fly takes a blood meal and injects promastigotes into the skin.
- Macrophages phagocytose them, and inside the macrophage they transform into amastigotes.
- Amastigotes multiply and infect more mononuclear phagocytes, either staying in the skin (cutaneous disease) or spreading to the reticuloendothelial organs: spleen, liver, bone marrow and lymph nodes (visceral disease).
- A sand fly feeding on an infected host ingests infected cells; the amastigotes turn back into promastigotes in the fly's gut and migrate to its proboscis.
Vectors: Phlebotomus in the Old World and Lutzomyia in the New World. Reservoirs vary by species: dogs and other canines, rodents, and, for L. donovani in the Indian subcontinent, humans. Visceral disease can also spread congenitally and through blood transfusion, organ transplantation and shared needles.
Immunology link. An intracellular parasite has to be cleared by cell-mediated immunity, and the clinical clues show it: visceral leishmaniasis is an opportunistic infection in advanced HIV, with frequent relapse; the leishmanin skin test is positive in cutaneous and mucosal disease but negative in active visceral disease; and diffuse cutaneous leishmaniasis, with widespread nodules resembling lepromatous leprosy, reflects cell-mediated anergy. Review the T-cell arms in Th1 vs Th2 responses.
The three syndromes
| Cutaneous | Mucosal | Visceral (kala-azar) | |
|---|---|---|---|
| Classic species | Old World: L. major, L. tropica, L. aethiopica. New World: L. mexicana complex and Viannia species | Viannia subgenus, mainly L. braziliensis (also L. panamensis, L. guyanensis) | L. donovani and L. infantum (also called L. chagasi in Latin America) |
| Timing | Weeks to months after the bite, sometimes later | Usually years (even decades) after the skin lesion | Incubation of weeks to months |
| Hallmark | Papule or nodular plaque that becomes a painless ulcer with a raised border and central crater ("volcano") on exposed skin | Nasal stuffiness, nosebleeds and discharge, then destruction of the nasal septum, palate and pharynx ("espundia"); laryngeal disease can be fatal | Fever, weight loss, night sweats, hepatosplenomegaly (especially the spleen), pancytopenia, high total protein with low albumin (hypergammaglobulinemia) |
| Where acquired | About 95% in the Americas, the Mediterranean basin, the Middle East and central Asia (cases in US troops from Iraq and Afghanistan) | Over 90% of cases in Bolivia, Brazil, Ethiopia and Peru | Most cases in Brazil, East Africa and India (South Asia); also the Mediterranean basin |
| Without treatment | Usually heals over months to years, leaving an atrophic scar | Progressive and mutilating | Fatal in over 95% of cases |
Extra visceral clues:
- Skin darkening (hyperpigmentation) may be seen in people infected in India and Bangladesh.
- Post-kala-azar dermal leishmaniasis (PKDL) is a macular, papular or nodular rash, usually on the face, upper arms and trunk, that typically appears 6 months to a year or more after apparently successful treatment (sometimes earlier). It occurs mainly in East Africa and South Asia, where L. donovani is the cause, and people with PKDL are considered a potential source of infection.
- HIV coinfection raises the risk of relapse and treatment failure.
- Pancytopenia has many non-infectious causes, so the travel history is what points to kala-azar; for the marrow-failure side of the differential, see the aplastic anemia flowchart.
Diagnosis
- Microscopy: Giemsa-stained tissue shows amastigotes inside macrophages, each with a nucleus and a kinetoplast. Species cannot be told apart by appearance.
- Visceral disease specimens: bone marrow aspirate is the preferred first sample because it is safer, though less sensitive (52-85%). Splenic aspirate has the highest yield (93-99%) but carries a bleeding risk and is not recommended in North America. Lymph node aspirates yield 52-58%.
- Cutaneous disease: skin biopsy or swab of the lesion; PCR is the most sensitive method and identifies the species, which matters because species differ in mucosal risk and drug response.
- PCR vs culture: cultures can take weeks to turn positive, so treatment often starts on the basis of microscopy or PCR.
- Serology: an rK39 rapid test supports visceral disease but is not a stand-alone test; serology is not recommended for cutaneous disease because the available assays are neither sensitive nor specific for it.
Treatment
| Syndrome | Main options |
|---|---|
| Visceral | Liposomal amphotericin B (FDA-approved; for immunocompetent patients 3 mg/kg IV daily on days 1-5, 14 and 21, total 21 mg/kg). Oral miltefosine for L. donovani (approved for this species; guidelines recommend it for disease acquired in South Asia). Pentavalent antimonials (20 mg/kg/day of antimony for 28 days) are a guideline option only where available and where antimony resistance is low; resistance is common in South Asia |
| Cutaneous, simple | Many lesions heal on their own; local therapy: cryotherapy, thermotherapy, topical paromomycin, intralesional antimony |
| Cutaneous, complex or Viannia | Systemic therapy for L. braziliensis and related species with mucosal risk, or for multiple, large or disfiguring lesions: liposomal amphotericin B, miltefosine (approved for L. braziliensis, L. panamensis, L. guyanensis) or amphotericin B deoxycholate |
| Mucosal | Systemic therapy: liposomal amphotericin B or miltefosine (approved for L. braziliensis), though data are limited; amphotericin B deoxycholate is an alternative |
Drug pearls:
- Miltefosine carries a boxed warning for embryo-fetal toxicity and is contraindicated in pregnancy (and in Sjögren-Larsson syndrome); pregnancy status is checked before starting, and patients who could become pregnant need effective contraception during treatment and for 5 months after the last dose. Breastfeeding is avoided for the same period. It is approved for patients aged 12 or older who weigh at least 30 kg, given for 28 days with food.
- Pentavalent antimonials (sodium stibogluconate, meglumine antimoniate) cause nausea, vomiting, malaise, raised amylase and liver enzymes, and cardiotoxicity (arrhythmias, heart failure). In the US they are not commercially available; meglumine antimoniate can be obtained only under an individual investigational protocol.
How USMLE tests Leishmania: look-alikes and traps
| Look-alike | What overlaps | How to tell them apart |
|---|---|---|
| Trypanosoma cruzi (Chagas) | Its tissue amastigotes look identical to Leishmania amastigotes | Triatomine (kissing) bug feces; trypomastigotes in blood; chagoma or Romaña sign acutely; dilated cardiomyopathy, megaesophagus, megacolon years later |
| Histoplasma capsulatum | Yeasts of the same size (1-5 µm) inside macrophages on Giemsa stain; disseminated disease causes hepatosplenomegaly and marrow involvement | Dimorphic fungus (a yeast, so no kinetoplast); bird or bat droppings and caves; Ohio and Mississippi River valleys; disseminates with impaired T-cell immunity; urine antigen. See Histoplasma tips |
| Plasmodium (malaria) | Fever and splenomegaly in a returning traveler | Female Anopheles mosquito; parasites inside red blood cells on thick and thin blood smears. See Plasmodium species |
| Sporothrix | Painless skin bump after outdoor exposure | Fungus from rose thorns, sphagnum moss, hay or cat scratches; new bumps spread up the arm from the inoculation site; itraconazole is the treatment of choice |
Traps to remember:
- Promastigote = in the fly (infective form); amastigote = in human macrophages (diagnostic form).
- The vector is the sand fly, not the mosquito, tick, kissing bug or tsetse fly.
- Big spleen + pancytopenia + high globulins after time in South Asia, East Africa, Brazil or the Mediterranean is visceral leishmaniasis until proven otherwise.
- Nasal septum destruction in someone who had a healed skin ulcer from Latin America is mucosal L. braziliensis, and it needs systemic treatment.
- Kinetoplast separates Leishmania from Histoplasma; geography, vector and blood trypomastigotes separate it from T. cruzi.
- In HIV, visceral leishmaniasis behaves as an opportunistic infection; see the CD4 count and opportunistic infections table.
Practice question
A 41-year-old engineer returns to the US after 18 months in rural India. He has had 3 months of intermittent fever, night sweats and a 9-kg weight loss, and his family says his skin has darkened. The spleen is palpable 12 cm below the costal margin and the liver is enlarged. Hemoglobin is 8.2 g/dL, leukocytes 2,100/mm³ and platelets 61,000/mm³; total protein is high and albumin low. An HIV test is negative. A bone marrow aspirate shows macrophages packed with small oval organisms, each with a nucleus and a separate small kinetoplast. Which of the following is the most appropriate treatment?
A. Benznidazole B. Itraconazole C. Liposomal amphotericin B D. Primaquine E. Splenectomy
Answer: C, liposomal amphotericin B. Fever, wasting, marked splenomegaly, pancytopenia, high globulins and skin darkening after living in India, plus amastigotes with kinetoplasts in marrow macrophages, is visceral leishmaniasis (kala-azar) from L. donovani. Liposomal amphotericin B is FDA-approved for it (3 mg/kg on days 1-5, 14 and 21 in immunocompetent patients); without treatment, visceral disease is almost always fatal.
- A (benznidazole) treats T. cruzi (Chagas disease). Its tissue amastigotes look identical, but Chagas is spread by triatomine (kissing) bugs and leads to cardiomyopathy and megaviscera, not kala-azar after living in India.
- B (itraconazole) treats mild-to-moderate histoplasmosis and sporotrichosis. Histoplasma yeasts are the same size, but a fungus has no kinetoplast, and disseminated histoplasmosis mainly affects people with impaired T-cell immunity (HIV, transplant, immunosuppressants).
- D (primaquine) clears the dormant liver hypnozoites of P. vivax and P. ovale malaria. Malaria parasites sit inside red blood cells, not inside marrow macrophages.
- E (splenectomy) treats neither the infection in the marrow and liver nor the parasite itself; this patient needs an antiparasitic drug.
Key takeaways
- Sand fly (Phlebotomus, Lutzomyia) injects promastigotes; amastigotes with a nucleus and kinetoplast live inside macrophages (LD bodies).
- Cutaneous: painless ulcer with raised borders that heals with a scar. Mucosal: L. braziliensis, nasal septum and palate destruction years later.
- Visceral (kala-azar): L. donovani or L. infantum; fever, weight loss, hepatosplenomegaly, pancytopenia, hypergammaglobulinemia, hyperpigmentation in India and Bangladesh; PKDL after treatment.
- Diagnosis: amastigotes on Giemsa stain; bone marrow first, spleen highest yield; PCR identifies the species; rK39 supports but doesn't confirm.
- Treatment: liposomal amphotericin B for visceral disease; miltefosine is oral but teratogenic; antimonials are the classic exam answer but are unavailable commercially in the US.
- Look-alikes: T. cruzi amastigotes look identical; Histoplasma is a fungus without a kinetoplast.
Sources
- Clinical Overview of Leishmaniasis — CDC (2024)
- Clinical Care of Leishmaniasis — CDC (2024)
- DPDx: Leishmaniasis — CDC (2024)
- Leishmaniasis — CDC Yellow Book 2026
- Leishmaniasis — Merck Manual Professional Edition (2026)
- Leishmaniasis Fact Sheet — World Health Organization (2023)
- Diagnosis and Treatment of Leishmaniasis: ASTMH/IDSA Clinical Practice Guidelines — Infectious Diseases Society of America (2016)
- IMPAVIDO (miltefosine) capsule label — DailyMed (2026)
- DPDx: American Trypanosomiasis — CDC (2021)
- Histoplasmosis — Merck Manual Professional Edition (2025)
- Sporotrichosis — Merck Manual Professional Edition (2025)
- Treatment of Uncomplicated Malaria — CDC (2026)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
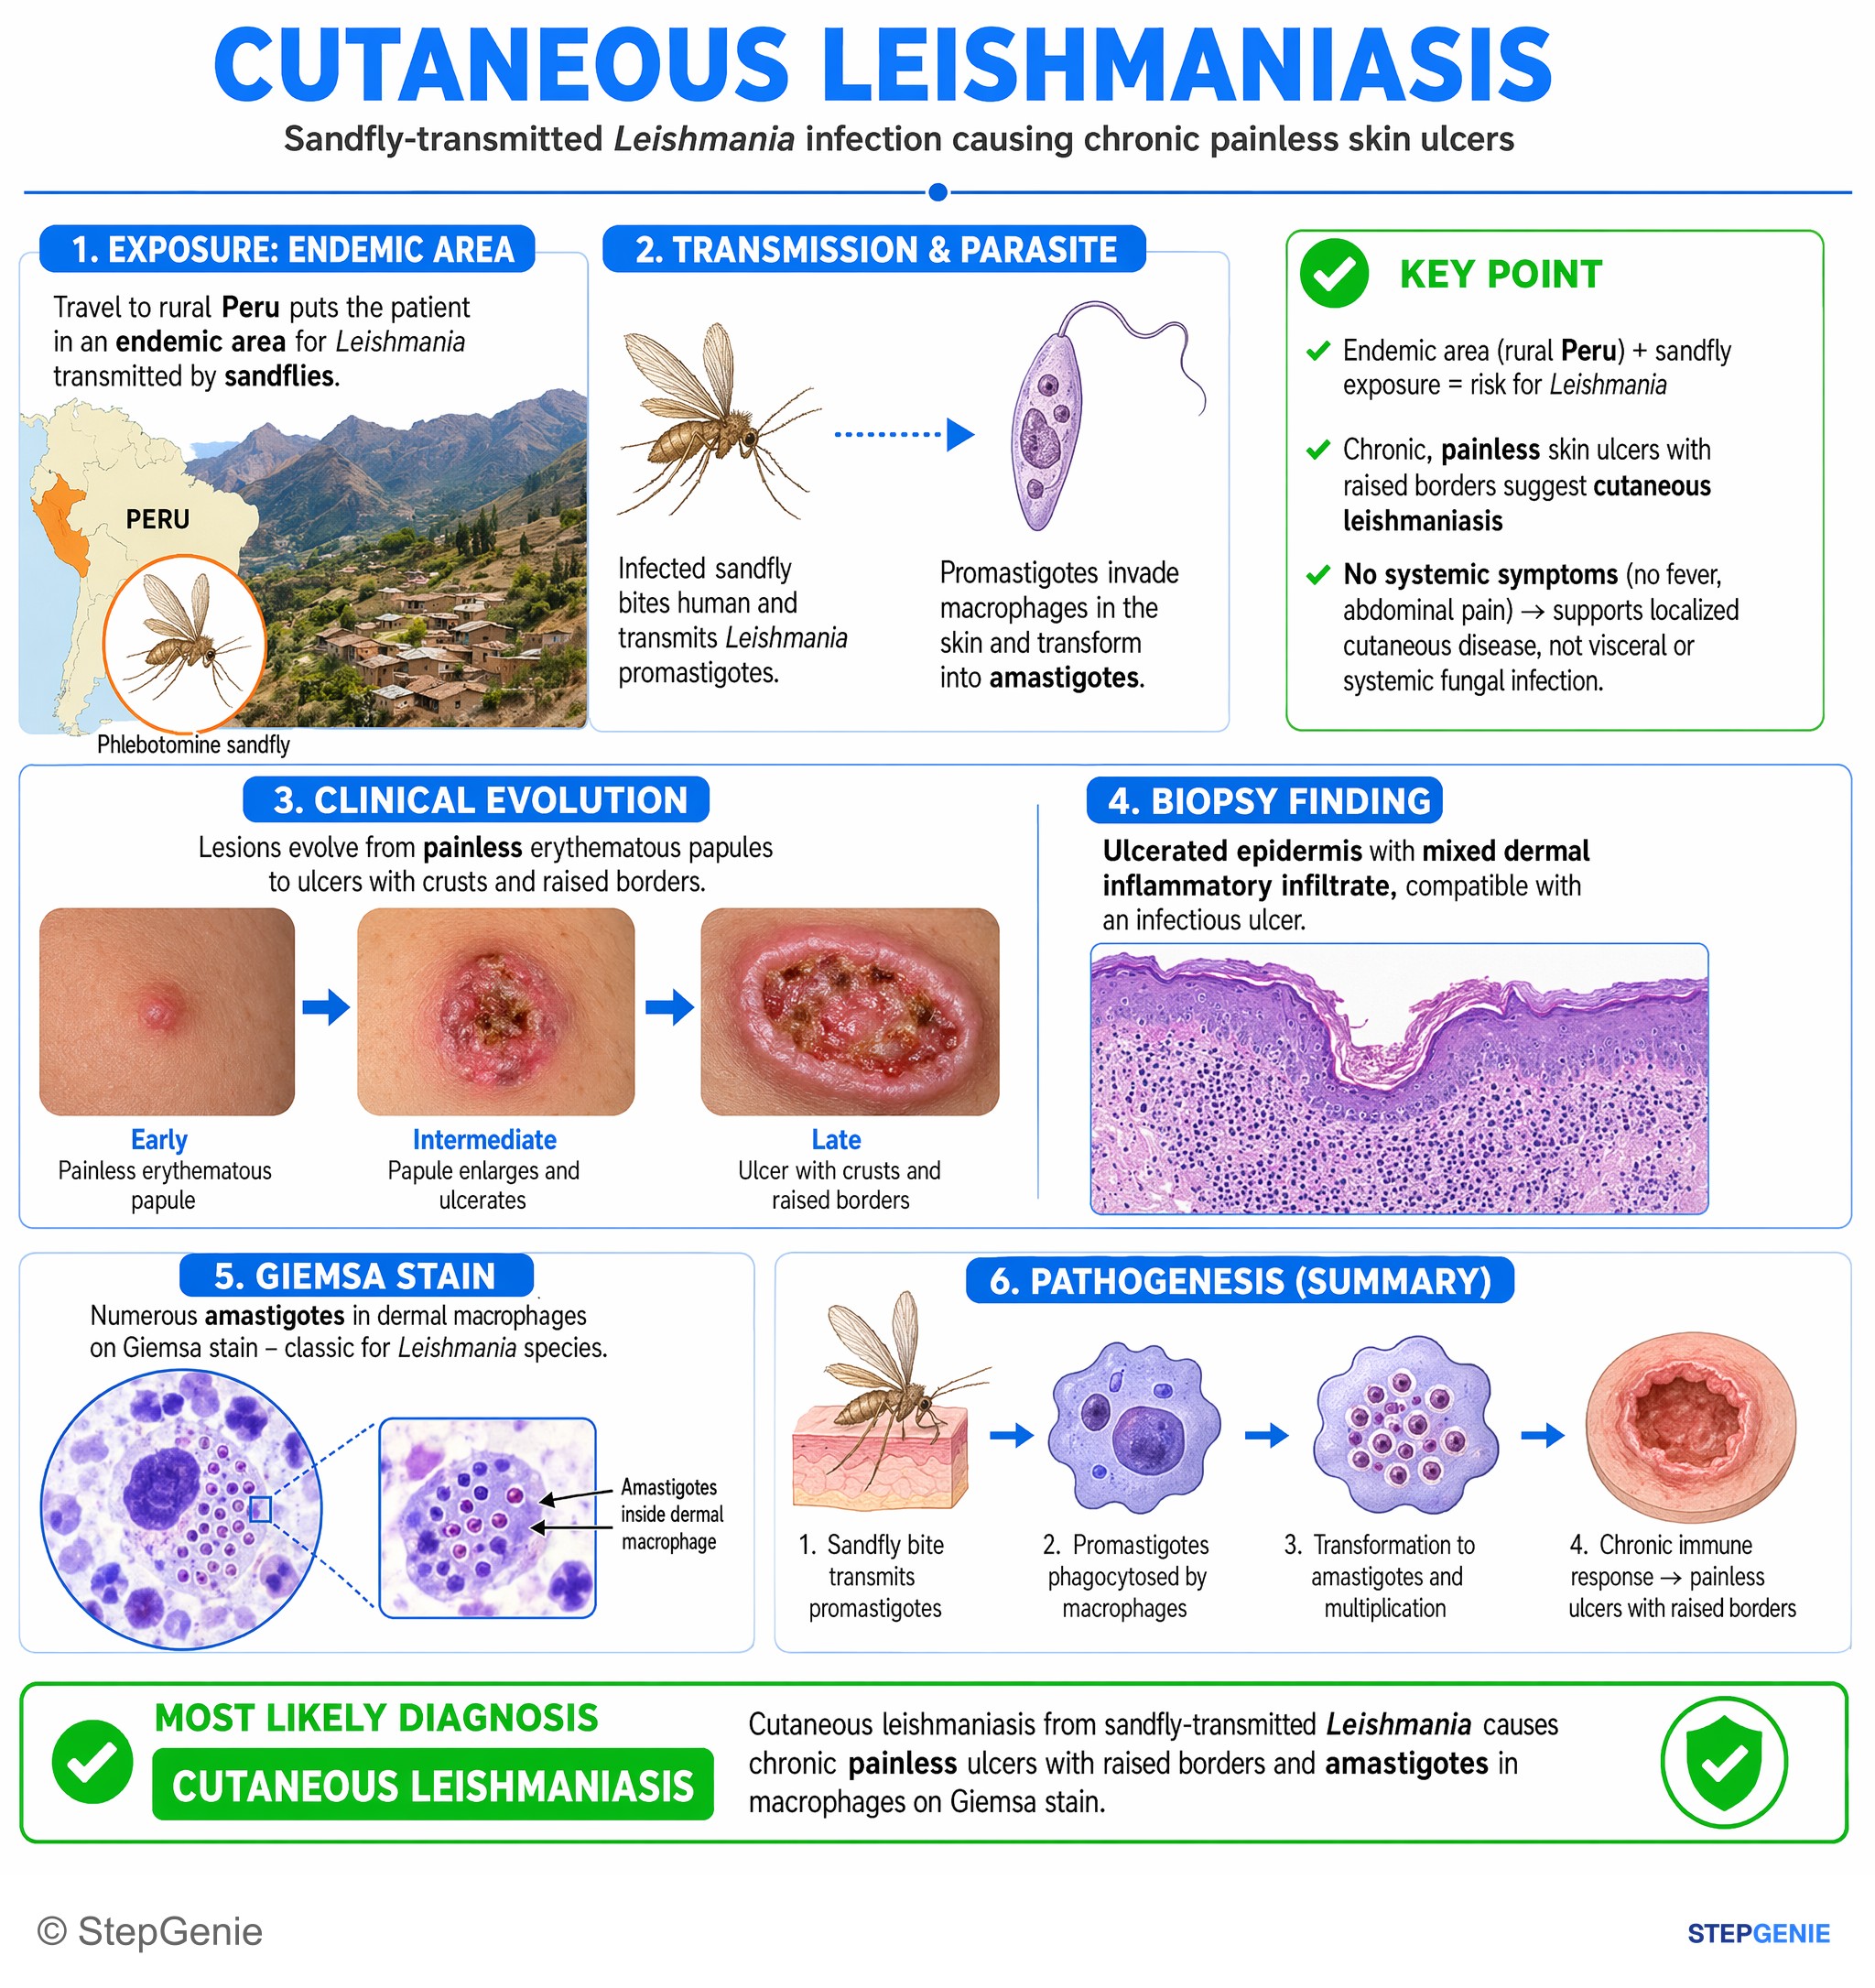
Cutaneous leishmaniasis from sandfly-transmitted Leishmania causes chronic painless ulcers with raised borders and amastigotes in…
USMLE Step 2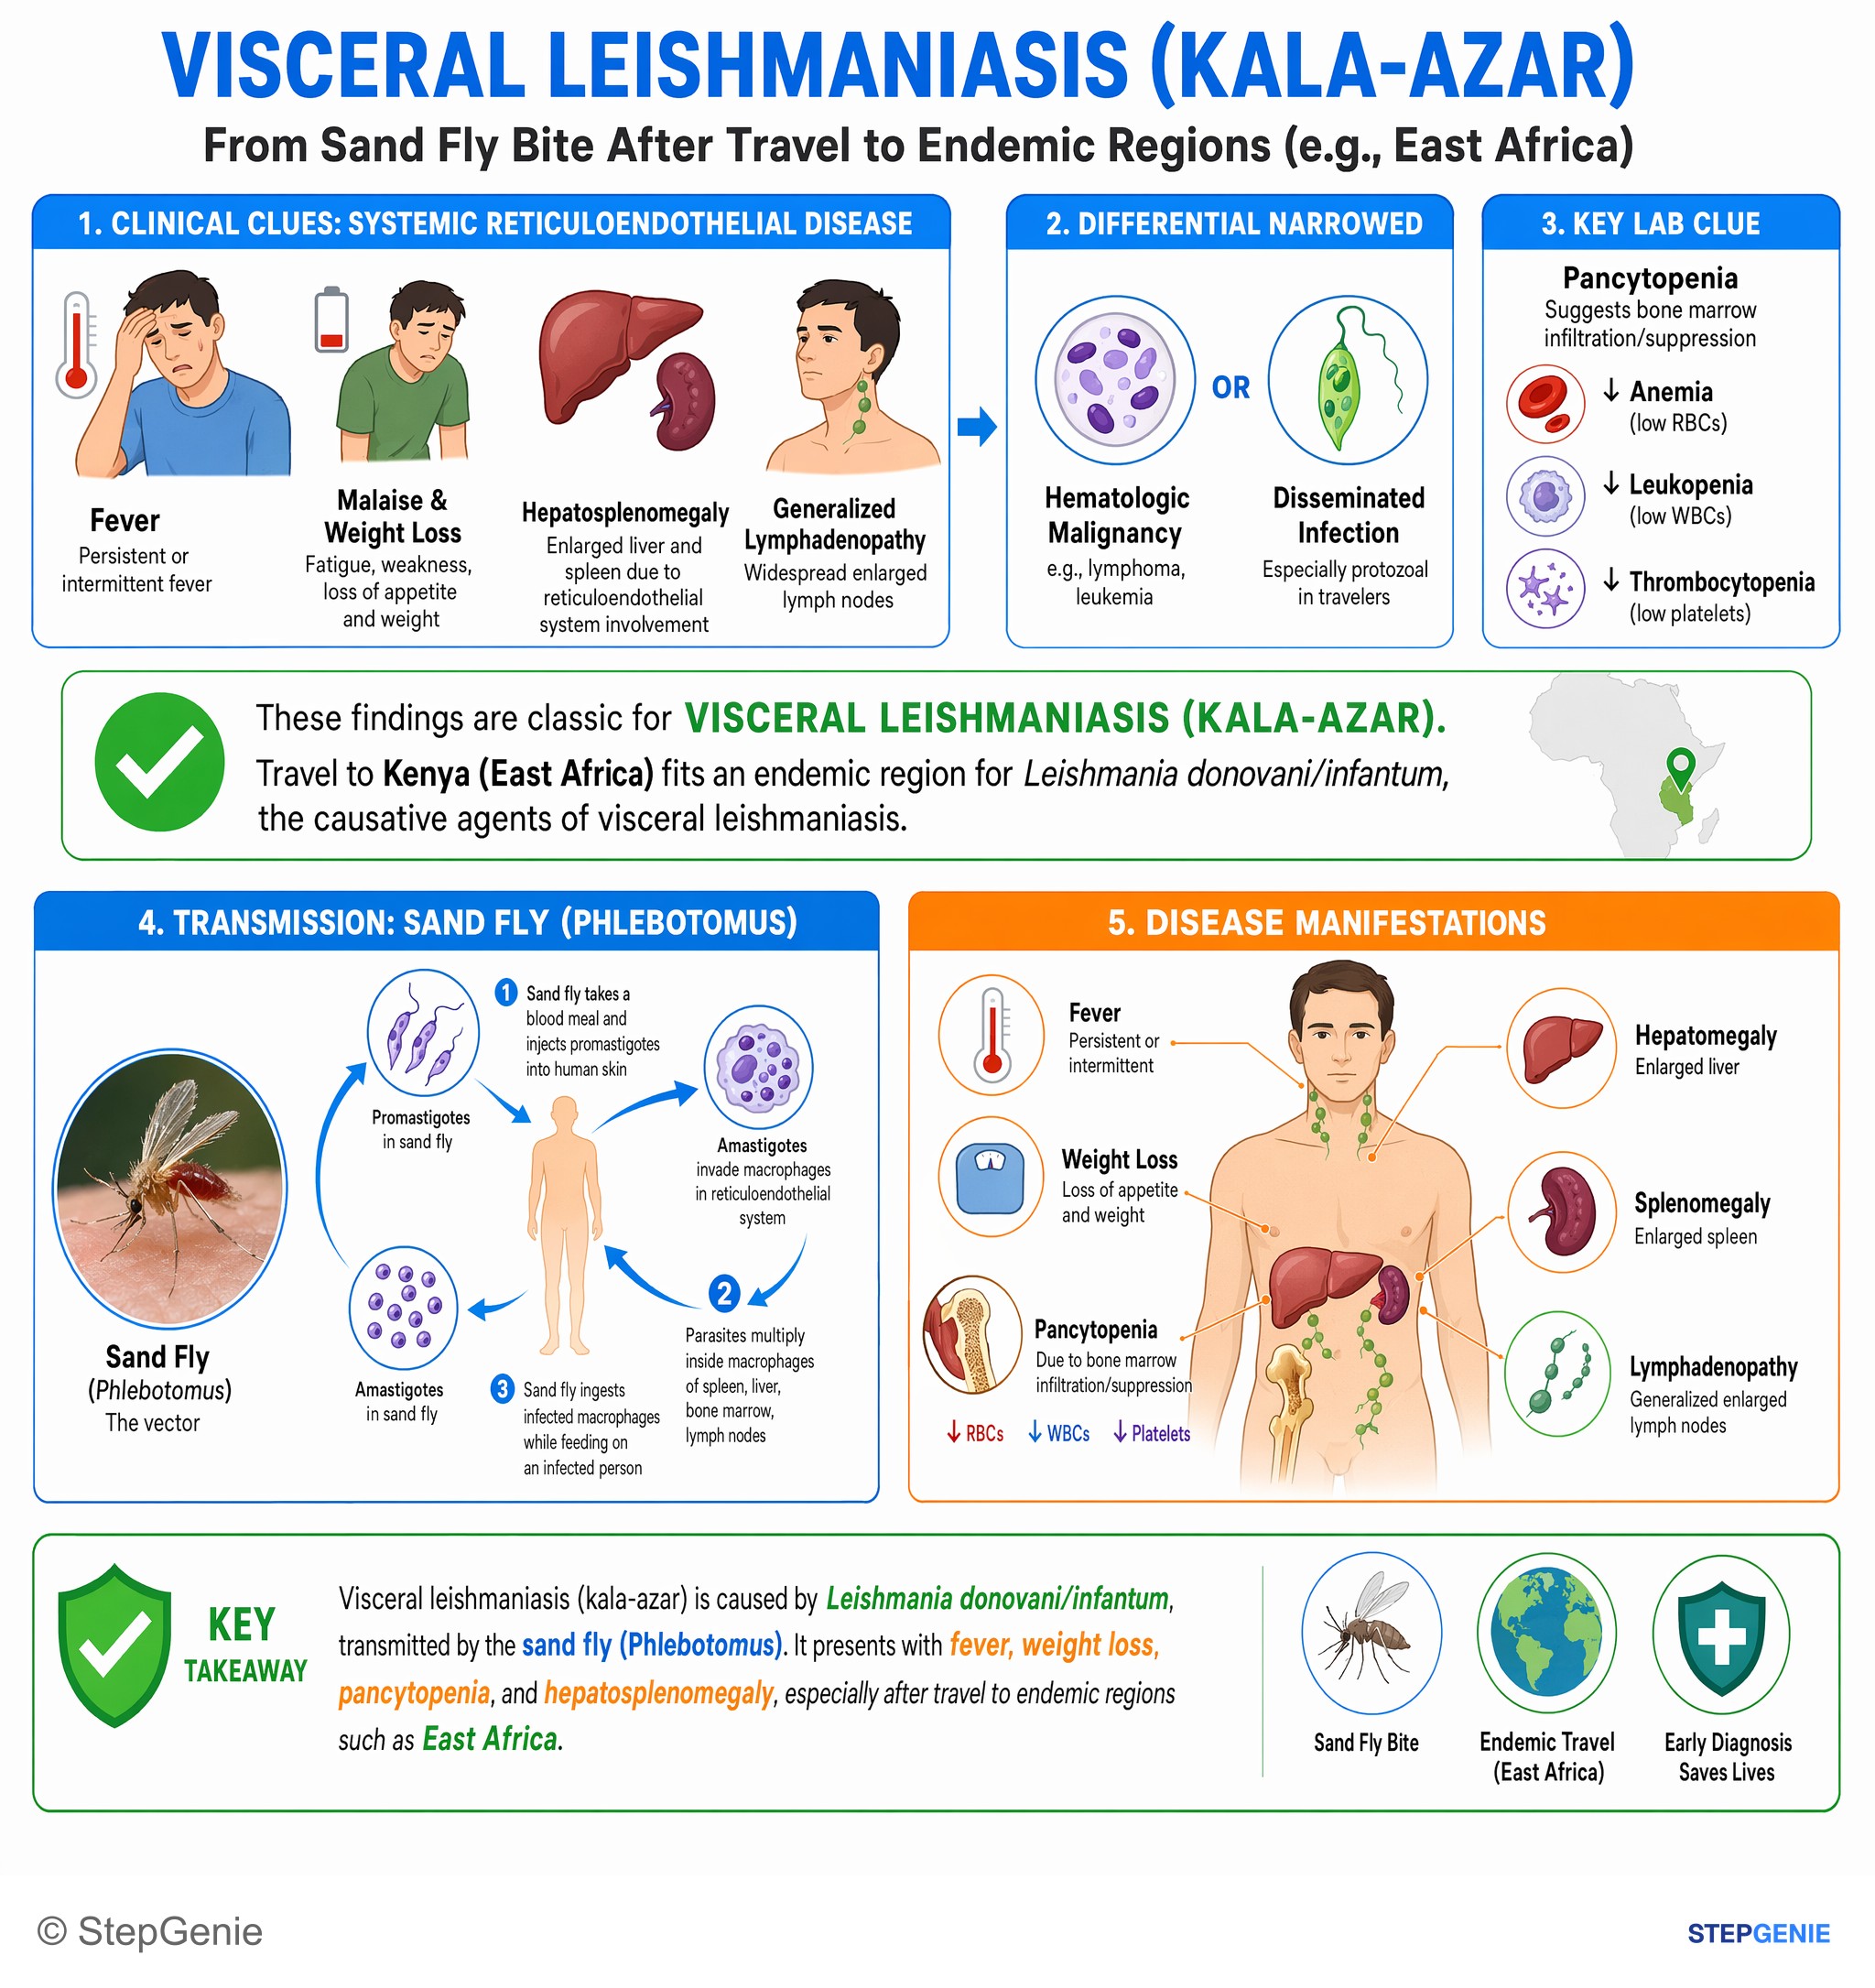
Visceral leishmaniasis (kala-azar) from sand fly bite causes fever, weight loss, pancytopenia, and hepatosplenomegaly after travel to…
USMLE Step 1Frequently Asked Questions
What is the difference between the promastigote and amastigote forms of Leishmania?
The promastigote is the elongated, flagellated form, about 10 to 12 micrometers long, that lives in the sand fly's gut and is injected into the skin when the fly bites. In the human host, macrophages engulf promastigotes, which turn into amastigotes: small ovoid forms 1 to 5 micrometers long, each with a nucleus and a kinetoplast and no long flagellum. Amastigotes multiply inside macrophages and are the form seen on Giemsa-stained tissue, called Leishman-Donovan bodies.
What are the three types of leishmaniasis?
Cutaneous leishmaniasis, the most common form, is a painless skin ulcer with raised borders that appears weeks to months after a sand fly bite and heals with a scar. Mucosal leishmaniasis, mainly from Leishmania braziliensis in Latin America, destroys the nose, palate and throat, usually years after the skin lesion. Visceral leishmaniasis, or kala-azar, from L. donovani or L. infantum, causes fever, weight loss, hepatosplenomegaly, pancytopenia and hypergammaglobulinemia and is fatal in over 95% of untreated cases.
What are the symptoms of kala-azar?
Kala-azar, or visceral leishmaniasis, develops weeks to months after infection with fever, night sweats, weight loss and an enlarged liver and especially spleen. Blood tests show pancytopenia (anemia, low white cells and low platelets), with high total protein, low albumin and hypergammaglobulinemia. Skin darkening may be seen in people infected in India and Bangladesh. More than 95% of untreated cases are fatal, and some patients develop post-kala-azar dermal leishmaniasis months to years after treatment.
How is visceral leishmaniasis diagnosed?
The diagnosis is made by finding Leishmania amastigotes or their DNA in tissue. Bone marrow aspirate is the preferred first specimen because it is safer, with a sensitivity of about 52 to 85 percent; splenic aspirate has the highest yield, 93 to 99 percent, but risks bleeding and is not recommended in North America. Giemsa stain shows amastigotes with a nucleus and kinetoplast inside macrophages, PCR identifies the species, and an rK39 rapid test supports but does not confirm the diagnosis.
What is the treatment for leishmaniasis?
Treatment depends on the syndrome and species. In the US, visceral leishmaniasis is treated with liposomal amphotericin B, which is FDA-approved; oral miltefosine is approved for L. donovani and some cutaneous and mucosal species but is contraindicated in pregnancy. Simple cutaneous lesions can be treated locally, for example with cryotherapy, heat or topical paromomycin, while L. braziliensis infections and complex lesions need systemic therapy. Pentavalent antimonials such as sodium stibogluconate are classic exam answers but are not commercially available in the US.
How do you tell Leishmania from Histoplasma or Trypanosoma cruzi?
All three can appear as small organisms inside host cells. Histoplasma capsulatum is a fungus whose 1 to 5 micrometer yeasts sit inside macrophages, but it has no kinetoplast and is linked to bird or bat droppings in the Ohio and Mississippi River valleys. Trypanosoma cruzi amastigotes look identical to Leishmania amastigotes, so the clues are its triatomine bug vector, trypomastigotes in the blood and late cardiomyopathy, megaesophagus or megacolon.