Th1 and Th2 responses are the two classic helper T-cell programs, and they are the core of what immunologists call type 1 and type 2 immunity. A Th1 response is switched on by IL-12 (with IFN-γ), runs on the transcription factor T-bet and secretes IFN-γ, which activates macrophages for cell-mediated immunity against intracellular microbes; its fingerprints are granulomas and delayed (type IV) hypersensitivity. A Th2 response is switched on by IL-4, runs on GATA3 and secretes IL-4, IL-5 and IL-13, which drive IgE, eosinophils and mast-cell responses against helminths; its fingerprints are allergy, asthma and eosinophilia. Each program restrains the other, so one side usually dominates.
Th1 vs Th2 at a glance
| Feature | Th1 (type 1) | Th2 (type 2) |
|---|---|---|
| Induced by | IL-12 from dendritic cells and macrophages, plus IFN-γ (early from NK cells) | IL-4 (from mast cells, NKT cells and Th2 cells themselves) |
| Signaling and master transcription factor | IL-12 via STAT4; IFN-γ via STAT1, which induces T-bet | IL-4 via STAT6; GATA3 |
| Signature cytokines | IFN-γ, IL-2, TNF, lymphotoxin | IL-4, IL-5, IL-13, IL-10 |
| Main effector cells | Activated (M1) macrophages, CD8 cytotoxic T cells, NK cells | B cells switching to IgE, eosinophils, mast cells, basophils, M2 macrophages |
| Kind of immunity | Cell-mediated | Humoral and allergic |
| Classic targets | Intracellular pathogens such as viruses and mycobacteria | Helminths |
| Tissue signature | Granulomas | Eosinophilia, high IgE |
| Hypersensitivity link | Type IV (delayed, T-cell mediated) | Type I (IgE-mediated, within an hour) |
| Leprosy pole | Tuberculoid | Lepromatous |
| How it restrains the other | IFN-γ antagonizes IL-4 and inhibits Th2 proliferation | IL-4 lowers IL-12 production; IL-10 inhibits Th1 differentiation |
How a naive CD4 T cell picks a side
The choice is made while a naive (Th0) CD4 T cell is being activated by an antigen-presenting cell, and it depends on the cytokines around it.
- Th1: dendritic cells and macrophages release IL-12, which signals through STAT4 and also makes NK cells secrete IFN-γ. IFN-γ signals through STAT1 to induce T-bet, and T-bet raises the IL-12 receptor β2 chain, so the cell responds even more to IL-12: a feed-forward loop.
- Th2: IL-4 signals through STAT6, and the transcription factor GATA3 drives Th2 differentiation and Th2-cell growth. Th2 cells then make more IL-4 (positive feedback), and GATA3 also restrains Th1 differentiation.
What each response does
Th1 (type 1):
- IFN-γ turns macrophages into strongly microbicidal, "classically activated" (M1) cells that secrete TNF; it also raises MHC class I and II expression and activates NK cells.
- IL-2 drives T-cell proliferation, including CD8 cytotoxic T cells, and enhances NK-cell killing.
- When antigen persists, macrophages, epithelioid cells and lymphocytes organize into granulomas, with CD4 T cells playing a key role; this is how the body contains Mycobacterium tuberculosis.
Th2 (type 2):
- IL-4 and IL-13 switch B cells to IgE. IgE arms mast cells and basophils through the high-affinity receptor FcεRI, and cross-linking by antigen triggers degranulation: type I hypersensitivity.
- IL-5 drives eosinophil proliferation (and IgA switching); eosinophils release major basic protein, which is toxic to parasites.
- IL-4 and IL-13 also produce "alternatively activated" (M2) macrophages, which resolve inflammation and remodel tissue.
Cross-inhibition: why one side wins
Th1 and Th2 cells can, to a degree, down-regulate each other. IFN-γ antagonizes IL-4 and inhibits Th2 proliferation. IL-4 lowers IL-12 production, and IL-10 (from Th2 cells, regulatory T cells and macrophages) reduces IL-12 and MHC class II on antigen-presenting cells, so Th1 differentiation stalls. The hygiene hypothesis rests on this balance: early-childhood exposure to infections and bacterial endotoxin may shift responses toward Th1 and suppress Th2-driven allergy. Real responses often involve other subsets as well, such as Th17 and regulatory T cells, so treat the split as a way to predict the dominant pattern.
Classic infections and diseases
| Condition | Dominant response | What the stem shows |
|---|---|---|
| Tuberculoid leprosy | Th1: IL-2 and IFN-γ in lesions | Strong cell-mediated immunity; a few numb skin lesions; bacilli rarely seen; granulomas of epithelioid (M1) macrophages |
| Lepromatous leprosy | Th2: IL-4, IL-5 and IL-10 in lesions | Poor cell-mediated immunity; many symmetric lesions; high bacillary load; foamy (M2) macrophages; lost eyebrows |
| Tuberculosis | Th1 | Granulomas; the tuberculin skin test is read at 48–72 hours; IGRAs measure IFN-γ release; TNF inhibitors and glucocorticoids can reactivate latent infection |
| Mendelian susceptibility to mycobacterial disease | Broken IL-12/IFN-γ axis | Defects in the IFN-γ receptor, IL-12 or the IL-12 receptor cause mycobacterial infections (see this IL-12 receptor deficiency case) |
| Sarcoidosis | Cell-mediated | Noncaseating granulomas; a BAL CD4:CD8 ratio above 3.5 suggests the diagnosis |
| Contact dermatitis (poison ivy) | Type IV (T-cell mediated) | Delayed rash where the antigen touched the skin (see the type IV hypersensitivity breakdown) |
| Helminth infection | Th2 | Eosinophilia (above 500/µL) and high IgE |
| Allergic asthma and atopy | Th2, type I | IgE, eosinophils, symptoms within an hour of exposure (see the type I hypersensitivity breakdown) |
Severe asthma biologics map straight onto type 2 immunity: omalizumab (anti-IgE), mepolizumab and reslizumab (anti-IL-5), benralizumab (anti-IL-5 receptor), dupilumab (blocks IL-4 receptor α, and so both IL-4 and IL-13) and tezepelumab (anti-TSLP).
Where Th17 and Treg fit
- Th17 cells (transcription factor RORγt) make IL-17, IL-21 and IL-22 and defend against extracellular bacteria and fungi; IL-17 induces cytokines such as IL-8 and G-CSF that mobilize neutrophils. In autosomal dominant hyper-IgE (Job) syndrome, STAT3 mutations impair Th17 differentiation, and patients have recurrent staphylococcal abscesses, severe itchy dermatitis, eosinophilia and IgE above 2,000 IU/mL (see the Job syndrome flowchart).
- Regulatory T cells (FOXP3) secrete TGF-β, IL-10 and IL-35 and suppress excessive responses, curbing allergic and autoimmune activity.
Exam traps
- Type 1/type 2 immunity is not Gell–Coombs type I/II hypersensitivity. Type I hypersensitivity is a type 2 (Th2, IgE) reaction, and the Th1 link is type IV. Types II and III are antibody-mediated (cytotoxic and immune complex) reactions, not Th1/Th2 labels.
- IL-10 belongs to the Th2 and regulatory side: it suppresses Th1, so don't pick it as a Th1 cytokine.
- IFN-γ is not only a Th1 product: NK cells and CD8 (Tc1) cells make it too, and early NK-cell IFN-γ helps start Th1 polarization.
- Know the Th2 cytokines apart: IL-4 induces Th2 cells and IgE; IL-5 drives eosinophils; IL-13 also switches to IgE and signals through the IL-4 receptor α chain, which is why dupilumab blocks both.
- Lepromatous leprosy is not "no immune response": antibodies dominate, but without strong cell-mediated immunity the bacilli multiply.
- Eosinophilia: in the United States, allergic or atopic disease is the most common cause; in a traveler or immigrant, think helminths.
- Tuberculin skin test: read induration at 48–72 hours; an IGRA measures IFN-γ and is not affected by BCG vaccination.
Worked example
Vignette. A 32-year-old man who emigrated from a region where leprosy is endemic has had a single lesion on his forearm for a year: a centrally hypopigmented macule with a sharp, raised border. The lesion is numb to light touch and temperature. Skin biopsy shows granulomas of epithelioid macrophages, and acid-fast staining finds no bacilli. Which cytokine pattern most likely predominates in the lesion?
- A. IL-4, IL-5 and IL-10
- B. IL-2 and IFN-γ
- C. IL-17 and IL-22
- D. TGF-β and IL-10 from FOXP3+ cells
- E. IgE-triggered histamine release from mast cells
Answer: B. A single numb, sharply bordered lesion with epithelioid granulomas and no visible bacilli is tuberculoid leprosy, the Th1 pole, and IL-2 and IFN-γ dominate its lesions.
Why the distractors are wrong:
- A is the lepromatous (Th2) profile, which goes with many symmetric lesions, foamy macrophages and a high bacillary load.
- C is Th17, aimed at extracellular bacteria and fungi.
- D is the regulatory T-cell profile, which suppresses immune responses rather than activating macrophages.
- E is type I hypersensitivity, an IgE reaction that develops within an hour, not a chronic granuloma.
Key takeaways
- Th1: IL-12 (STAT4) and IFN-γ (STAT1, which induces T-bet) → IFN-γ → macrophage activation, granulomas, type IV hypersensitivity; intracellular microbes; tuberculoid leprosy.
- Th2: IL-4 (STAT6) and GATA3 → IL-4, IL-5, IL-13 → IgE, eosinophils, mast cells, type I hypersensitivity; helminths, asthma; lepromatous leprosy.
- Cross-inhibition: IFN-γ restrains Th2; IL-4 and IL-10 restrain Th1.
- Th17 (RORγt, IL-17) handles extracellular bacteria and fungi; Treg (FOXP3, IL-10, TGF-β) keeps responses in check.
Sources
- Cellular Components of the Immune System — Merck Manual Professional Edition
- Molecular Components of the Immune System — Merck Manual Professional Edition
- Lee GR. Molecular Mechanisms of T Helper Cell Differentiation and Functional Specialization. Immune Network, 2023
- Afkarian M, et al. T-bet is a STAT1-induced regulator of IL-12R expression in naïve CD4+ T cells. Nature Immunology, 2002
- Overview of Allergic and Atopic Disorders — Merck Manual Professional Edition
- Leprosy — Merck Manual Professional Edition
- Zhang F, Mi Z, Liu H. Advances in the Immunology and Genetics of Leprosy. Frontiers in Immunology, 2020
- Tuberculosis (TB) — Merck Manual Professional Edition
- Overview of Immunodeficiency Disorders — Merck Manual Professional Edition
- Sarcoidosis — Merck Manual Professional Edition
- Hyper-IgE Syndrome — Merck Manual Professional Edition
- Pharmacologic Treatment of Asthma — Merck Manual Professional Edition
- CINQAIR (reslizumab) prescribing information — U.S. Food and Drug Administration
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
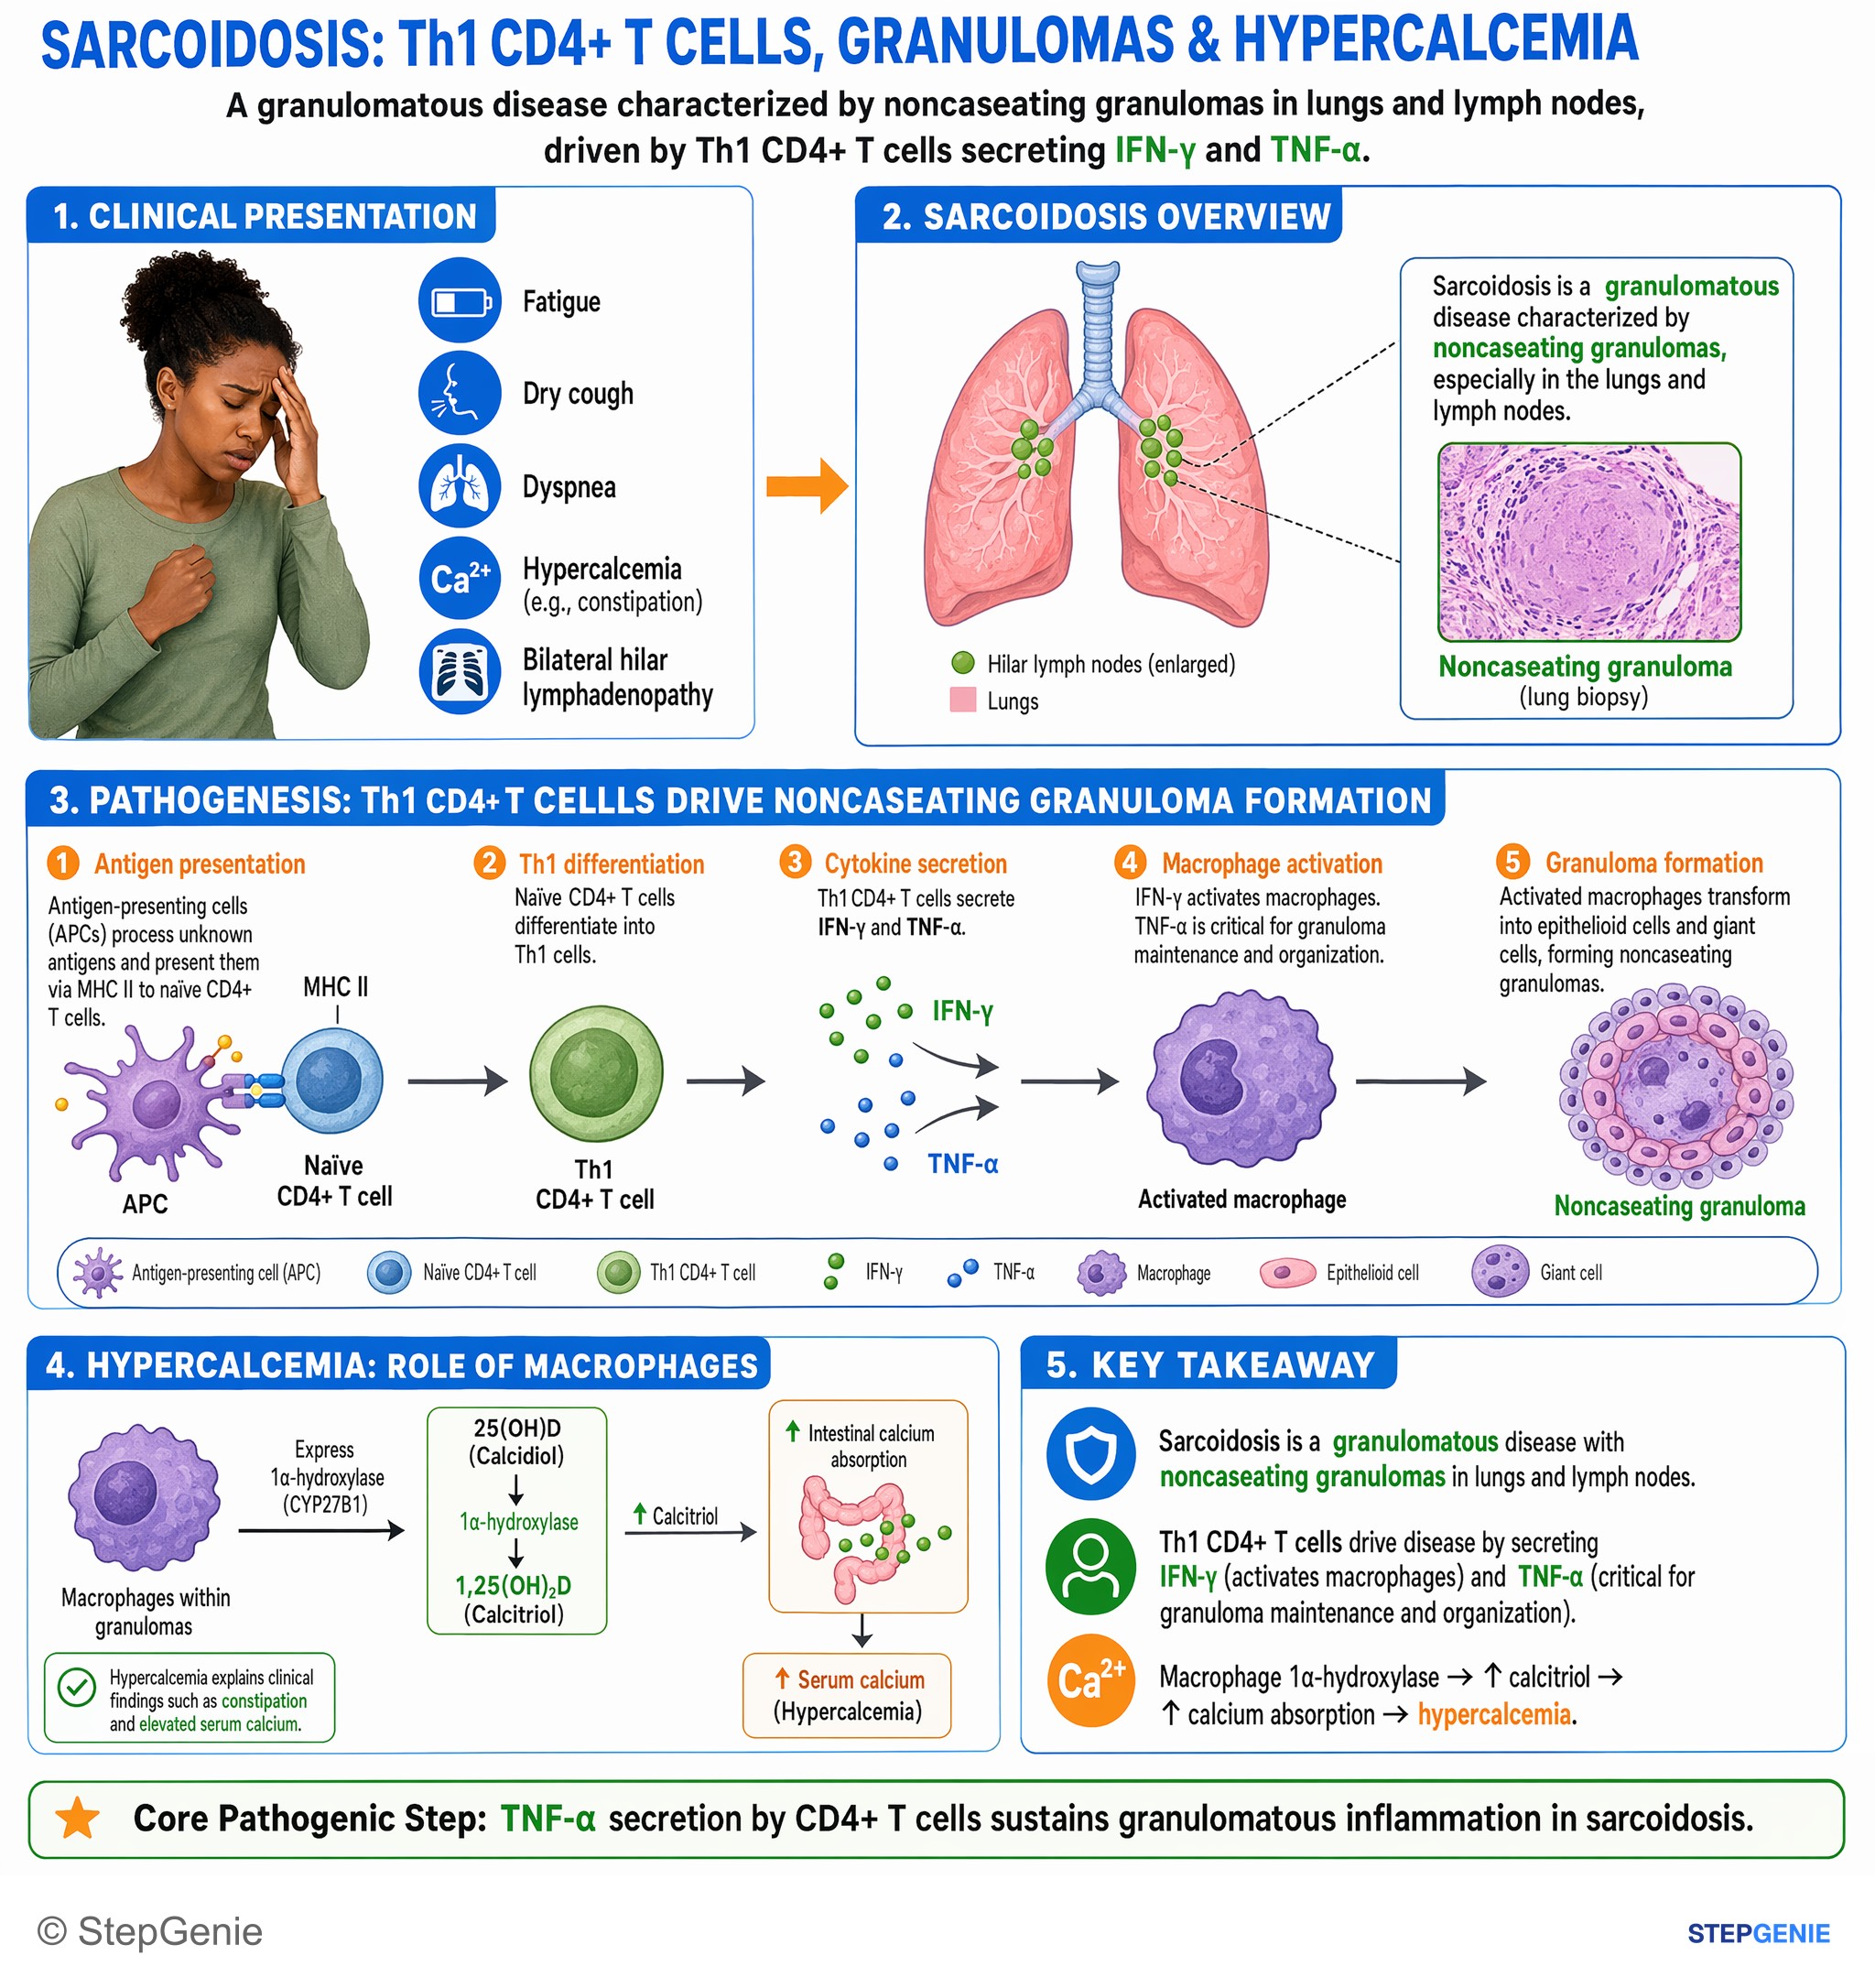
Sarcoidosis: noncaseating granulomas driven by Th1 CD4+ T cells secreting IFN-γ and TNF-α, causing hypercalcemia and bilateral hilar…
USMLE Step 1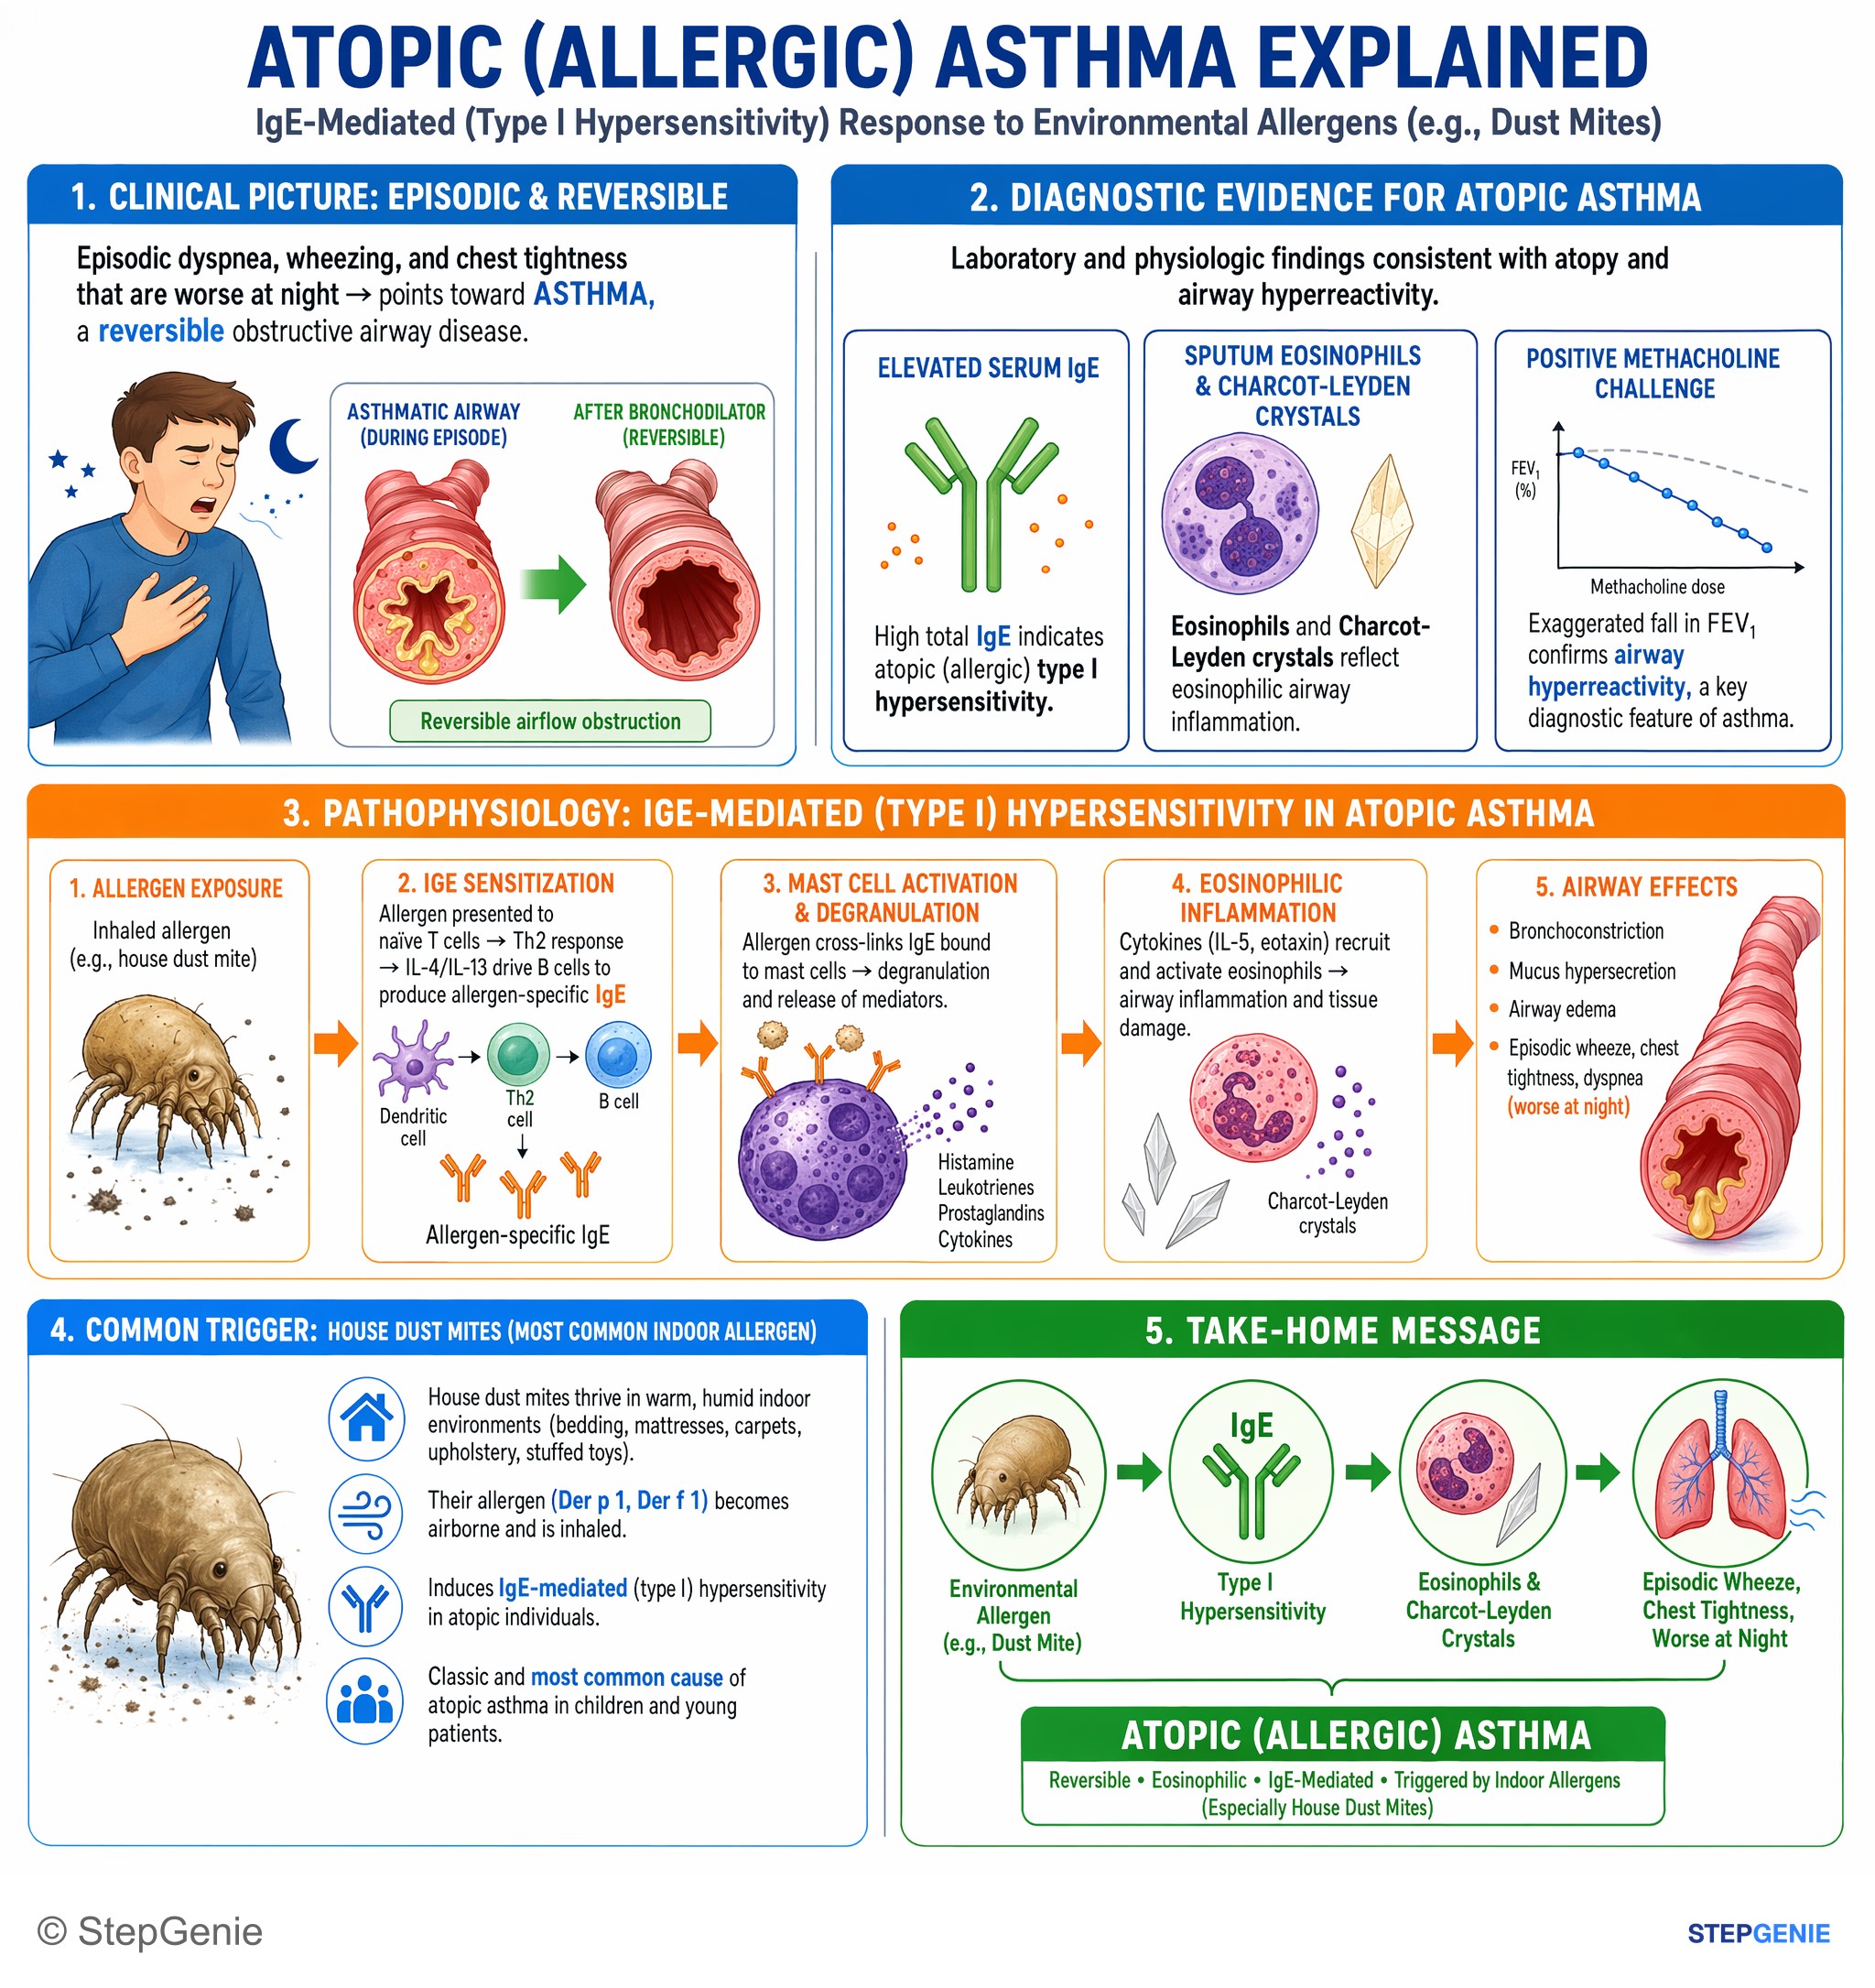
Allergic (atopic) asthma from environmental allergens (e.g., dust mites) → type I hypersensitivity with IgE, eosinophils, Charcot-Leyden…
USMLE Step 1Frequently Asked Questions
Is type 1 immunity the same as type I hypersensitivity?
No. Type 1 and type 2 immunity name the Th1 and Th2 programs, together with the NK, CD8 and other cells that make the same cytokines. The Gell–Coombs types I to IV classify tissue-damaging hypersensitivity reactions. The overlap runs crosswise: type I hypersensitivity is IgE-mediated and belongs to type 2 (Th2) immunity, while Th1 cells drive type IV delayed hypersensitivity, such as a positive tuberculin skin test or poison ivy dermatitis.
Which transcription factors define Th1, Th2, Th17 and regulatory T cells?
T-bet defines Th1 cells, GATA3 defines Th2 cells, RORγt defines Th17 cells and FOXP3 defines regulatory T cells. IFN-γ signaling through STAT1 induces T-bet, which raises the IL-12 receptor, while IL-4 signaling through STAT6 drives Th2 differentiation. Each subset is then recognized by its signature cytokines: IFN-γ for Th1; IL-4, IL-5 and IL-13 for Th2; IL-17 for Th17; and TGF-β, IL-10 and IL-35 for regulatory T cells.
Why is tuberculoid leprosy Th1 and lepromatous leprosy Th2?
The clinical form follows the host response. Tuberculoid lesions are rich in IL-2 and IFN-γ: strong cell-mediated immunity turns macrophages into epithelioid cells that form granulomas and limits disease to a few numb lesions with few bacilli. Lepromatous lesions are rich in IL-4, IL-5 and IL-10: cell-mediated immunity is poor and antibody responses dominate, so the bacillary load is high, foamy macrophages fill the lesions, and the lesions are many and symmetric.
How do Th1 and Th2 cells suppress each other?
Mostly through cytokines. IFN-γ from Th1 cells antagonizes IL-4 and inhibits Th2 proliferation. IL-4 from Th2 cells lowers IL-12 production by antigen-presenting cells, and IL-10 reduces IL-12 and MHC class II expression, so fewer naive cells become Th1; GATA3 also restrains Th1 differentiation. This cross-regulation is why established responses tend to polarize, and it underlies the hygiene hypothesis of allergy.
What do IL-4, IL-5 and IL-13 each do?
IL-4 induces Th2 differentiation and switches B cells to IgE. IL-13 also promotes IgE switching and, with IL-4, generates alternatively activated (M2) macrophages. IL-5 drives eosinophil proliferation and IgA switching. Asthma biologics follow the same map: dupilumab blocks the IL-4 receptor alpha chain and so inhibits both IL-4 and IL-13, while mepolizumab and reslizumab block IL-5 and benralizumab binds its receptor.