Histoplasma capsulatum is a thermally dimorphic fungus: a mold in soil enriched with bird or bat droppings, and a tiny yeast at body temperature that hides inside macrophages. Inhaled spores cause histoplasmosis, which is silent or a self-limited flu-like pneumonia in most people but becomes progressive disseminated disease (fever, hepatosplenomegaly, pancytopenia, oral ulcers) when cell-mediated immunity is impaired, as in advanced HIV or TNF-α inhibitor therapy. The classic US hot spot is the Ohio and Mississippi River valleys, though CDC says the fungus is likely present nationwide. Urine and serum antigen is the key rapid test in disseminated disease. IDSA's 2025-2026 update uses itraconazole when mild-to-moderate acute pulmonary disease needs treatment and liposomal amphotericin B, then itraconazole, for severe disease.
Histoplasma at a glance
| Feature | High-yield fact |
|---|---|
| Organism | H. capsulatum var. capsulatum (near-worldwide) and var. duboisii (Africa) |
| Forms | Mold in nature and in culture at room temperature; small oval yeast (about 2-4 µm) at 37 °C |
| Habitat | Soil contaminated with bird or bat droppings |
| Route | Inhaled microconidia after the soil is disturbed; not spread person to person, or between people and pets |
Memory hook: "Histo hides." It hides inside macrophages, and it hides in bat caves and bird roosts along the big rivers.
Tip 1: Read the exposure (and don't over-trust the map)
- Stem triggers: spelunking or a bat cave, cleaning a chicken coop, construction or landscaping. Severity depends on host immunity and the intensity of exposure (CDC).
- Geography: classically the central and eastern US, especially the Ohio and Mississippi River valleys (also Central and South America, Africa, Asia and Australia). But CDC says "Histoplasma distribution is likely nationwide," and some outbreaks occurred where it was not expected. Exam stems still use the river valleys.
- Who disseminates: people with HIV/AIDS, transplant recipients, people on immunosuppressive drugs, infants and adults 55 or older (CDC). IDSA rates as high risk advanced or untreated HIV (CD4 below 200/mm³), prednisone 20 mg/day or more for at least 2 weeks and autoimmune disease treated with biologics, especially those that impair T-cell function and granuloma formation (TNF-α inhibitors and IL-12/23 blockers are frequently reported).
- TNF-α inhibitors carry an FDA boxed warning: histoplasmosis may present as disseminated rather than localized disease, antigen and antibody tests may be negative despite active infection, and empiric antifungals should be considered if an at-risk patient develops severe systemic illness.
Tip 2: Think "tiny yeast inside macrophages," then pick the right test
- In tissue: small, oval, narrow-based budding yeasts, often inside macrophages or histiocytes (StatPearls).
| Test | What it tells you | Watch out for |
|---|---|---|
| Antigen (EIA), urine and serum | Urine antigen may be the most sensitive noninvasive test (CDC). In disseminated disease: urine positive in more than 90%, serum in about 80%; testing both raises the yield (Merck). Also tracks response | Cross-reacts with Blastomyces and other endemic fungi; may be negative in some patients on TNF inhibitors |
| Culture (blood, BAL, bone marrow, tissue) | Confirms the diagnosis; most useful in severe disease | Takes up to 6 weeks; warn the lab, because culturing Histoplasma is a biohazard |
| Histopathology or smear | Fast when positive: yeasts inside macrophages; in advanced HIV even on Wright- or Giemsa-stained blood or buffy coat (Merck) | Low sensitivity |
| Serology (immunodiffusion H and M bands, complement fixation) | Shows antibodies once they form | Antibodies take 2-6 weeks; immunodiffusion about 80% sensitive, complement fixation more sensitive but less specific; less useful early and in immunosuppressed patients |
Tip 3: Match the host to the syndrome
| Syndrome | Typical patient | Findings |
|---|---|---|
| Asymptomatic infection | Most exposed people | Nothing, or calcified nodules and nodes within several years |
| Acute pulmonary | Healthy host; heavier exposure means worse illness | Fever, cough, chest pain, headache and myalgias 3-17 days after exposure; hilar or mediastinal adenopathy; usually resolves within 2 weeks |
| Chronic cavitary | Underlying lung disease such as COPD, often in smokers | Apical cavities that resemble cavitary TB; worsening cough and dyspnea; does not disseminate |
| Progressive disseminated | Impaired cell-mediated immunity | Fever, weight loss, fatigue; hepatosplenomegaly, lymphadenopathy, marrow involvement with pancytopenia, oral or GI ulcers; meningitis or focal brain lesions |
| Mediastinal | Follows mediastinal node infection | Lymphadenitis, mediastinal granuloma, fibrosing mediastinitis, broncholithiasis |
- Disseminated disease, the details. In HIV, a CD4 count below 150/mm³ raises the risk of symptomatic illness (NIH). The course is usually subacute with vague symptoms; oral mucosal lesions are frequent; adrenal infection is rare but can cause Addison disease. Advanced HIV can bring severe pneumonia with hypoxia, hypotension, confusion, coagulopathy or rhabdomyolysis. Untreated, mortality is high (Merck).
- Immune reactions with acute disease: arthritis or arthralgias in about 5% of symptomatic patients, pericarditis in about 6%, and sometimes erythema nodosum or multiforme, more often in women (StatPearls).
- Mediastinal complications: nodes and granulomas can compress neighbors or form fistulas (StatPearls); a calcified node eroding into a bronchus (broncholithiasis) often causes hemoptysis (IDSA 2007); rare fibrosing mediastinitis is an intense fibrotic process causing superior vena cava syndrome, tracheal narrowing or pulmonary artery or vein obstruction (Merck).
Treatment: the 2025-2026 IDSA update
IDSA is updating its 2007 guideline in parts: Part 1 (March 2025) covers nodules and mild-to-moderate acute pulmonary disease; Part 2, a consensus statement (16 September 2026), covers initial therapy of severe disease (hospitalization for severe acute pulmonary or disseminated histoplasmosis). Other rows follow IDSA 2007 and NIH.
| Situation | Management |
|---|---|
| Asymptomatic nodule (histoplasmoma) | No routine antifungal; in moderate- or high-risk immunocompromised patients, monitor closely or consider treatment |
| Mild acute pulmonary, immunocompetent | No routine antifungal; consider it if illness is prolonged, infiltrates progress or hilar or mediastinal nodes enlarge |
| Moderate acute pulmonary, immunocompetent | Treat or observe, weighing severity, duration and drug harms; if treating, itraconazole 200 mg three times daily for 3 days, then 200 mg twice daily for 6-12 weeks |
| Mild or moderate acute pulmonary, immunocompromised | Itraconazole if at moderate to high risk of dissemination |
| Severe (hospitalized: severe acute pulmonary or disseminated) | Liposomal amphotericin B 3 mg/kg IV daily (5 mg/kg for CNS disease), historically 7-14 days (4-6 weeks for CNS), then itraconazole after clinical improvement |
| Disseminated, total course | Itraconazole to complete at least 12 months; mild-to-moderate disease can get itraconazole alone (IDSA 2007, NIH; IDSA 2026 allows it for chronic, low-risk presentations) |
| Chronic cavitary | Itraconazole for at least 1 year; some experts give 18-24 months (IDSA 2007) |
| Mediastinal lymphadenitis or granuloma | Usually no treatment; itraconazole for prolonged or significant symptoms (IDSA 2007) |
| Fibrosing mediastinitis | Antifungals not recommended (unless it cannot be told from mediastinal granuloma); stents for selected pulmonary vessel obstruction (IDSA 2007) |
| Advanced HIV | Stop itraconazole only after more than 1 year of azole therapy, with negative fungal blood cultures, serum or urine antigen below the level of quantification, undetectable viral load on stable ART, and CD4 ≥150/mm³ with at least 6 months of ART (NIH) |
| Pregnancy | If treatment is needed, avoid azoles in the first trimester when possible; use liposomal amphotericin B (IDSA 2025) |
- Itraconazole pearls (NIH, Merck): capsules need food and stomach acid (SUBA-itraconazole absorbs better), so check blood levels; boxed warning for heart failure; many drug interactions. Fluconazole is less effective.
- Mechanisms (StatPearls): azoles inhibit fungal 14α-demethylase (ergosterol synthesis); amphotericin B binds ergosterol and forms membrane channels, causing nephrotoxicity, hypokalemia and hypomagnesemia, less with lipid formulations.
Endemic mycoses: comparison table
| Fungus | Where | Exposure | Tissue form | Classic picture | Treatment |
|---|---|---|---|---|---|
| Histoplasma | Ohio and Mississippi River valleys; likely nationwide; worldwide | Bird or bat droppings, caves | Small (2-4 µm) oval yeasts inside macrophages | Hilar nodes, calcified granulomas; disseminates in AIDS | Itraconazole; liposomal amphotericin B if severe |
| Blastomyces | Ohio and Mississippi River valleys, northern Midwest, upstate New York, southern Canada | Moist soil with decaying organic matter near waterways | Large (15-20 µm) yeasts with broad-based buds | Pneumonia plus verrucous skin lesions, bone, prostate | Itraconazole for 6-12 months; amphotericin B if severe or CNS |
| Coccidioides | Desert Southwest (Arizona, California's Central Valley), northern Mexico, Central and South America | Dust carrying arthroconidia | Spherules (20-80 µm) full of endospores, not a yeast | Pneumonia with erythema nodosum; spread to skin, bone, meninges | Fluconazole or itraconazole; amphotericin B if severe |
| Paracoccidioides | South and Central America, especially Brazil | Rural farm work, mostly adult men | Yeast with multiple buds ("pilot's wheel") | Mucocutaneous ulcers around the mouth and nose, lymphadenitis, lung fibrosis | Itraconazole or TMP-SMX; amphotericin B if severe |
How USMLE tests it
- Histo vs TB: both cause granulomas, hilar nodes, calcifications and apical cavities, but histoplasmosis is not contagious and shows yeasts in macrophages, not acid-fast bacilli (compare primary vs reactivation TB).
- Histo vs Blasto: same river valleys, but Blastomyces is a large broad-based budder that favors skin and bone (see the Blastomyces Q-bank breakdown); the two cross-react on antigen tests.
- Histo vs Cryptococcus: both come from bird droppings, but Cryptococcus (pigeons) is an encapsulated yeast whose signature disease is meningitis (Cryptococcus mnemonic).
- AIDS with fever, pancytopenia, hepatosplenomegaly and oral ulcers suggests disseminated histoplasmosis (CD4 count and opportunistic infection table); adrenal involvement can add Addison disease.
- "Mold in the cold, yeast in the heat" fits Histoplasma, Blastomyces, Paracoccidioides and Sporothrix (rose thorns; inoculated, not inhaled); Coccidioides forms spherules in tissue instead.
Practice question
A 46-year-old man from Kentucky with Crohn disease has received infliximab for 2 years. He has 3 weeks of fever, night sweats, a 5-kg weight loss and a painful ulcer on his tongue. Temperature is 39.1°C (102.4°F), blood pressure 86/50 mm Hg despite IV fluids and oxygen saturation 88% on room air. He has hepatosplenomegaly. Hemoglobin is 8.9 g/dL, leukocyte count 2,400/mm³ and platelet count 61,000/mm³. Chest radiograph shows diffuse small nodules. Bone marrow biopsy shows granulomas and macrophages packed with small oval yeasts. Which is the most appropriate initial treatment?
A. Oral fluconazole B. Oral itraconazole alone C. Intravenous liposomal amphotericin B D. Isoniazid, rifampin, pyrazinamide and ethambutol E. Stop infliximab and observe without antifungal therapy
Answer: C. Shock, hypoxemia and pancytopenia on a TNF-α inhibitor, with yeasts inside marrow macrophages, mean severe progressive disseminated histoplasmosis. IDSA's 2026 consensus statement starts amphotericin B (liposomal preferred, 3 mg/kg daily), then switches to itraconazole once he improves, for at least 12 months in total (IDSA 2007, NIH).
- A: fluconazole is less effective against Histoplasma, and no oral azole is initial therapy for severe disease.
- B: itraconazole suits mild-to-moderate disease and step-down therapy, not shock and hypoxemia.
- D: marrow granulomas can suggest TB, but these organisms are yeasts in macrophages, not acid-fast bacilli.
- E: stopping the immunosuppressant does not treat the infection; untreated disseminated histoplasmosis has a high mortality.
Key takeaways
- Thermally dimorphic: mold in soil, tiny yeasts inside macrophages ("Histo hides").
- Bird or bat droppings; Ohio and Mississippi River valleys (CDC: likely nationwide); not contagious.
- Usually silent or a self-limited pneumonia; healed foci calcify. Chronic cavitary disease mimics TB; fibrosing mediastinitis can obstruct the SVC, pulmonary vessels or airways.
- Disseminated disease (advanced HIV, TNF-α inhibitors, transplant, high-dose steroids): fever, hepatosplenomegaly, pancytopenia, oral ulcers.
- Urine plus serum antigen is the best rapid test (cross-reacts with Blastomyces); culture takes up to 6 weeks.
- Itraconazole for mild-to-moderate disease that needs treatment; liposomal amphotericin B, then itraconazole, for severe disease; at least 12 months in total for disseminated disease; avoid azoles in the first trimester.
Sources
- Clinical Overview of Histoplasmosis — CDC (2024)
- How People Get Histoplasmosis — CDC (2024)
- Histoplasmosis in Adults, Children, and Pregnant Individuals: Guideline Update, Part 1 (2025) and Part 2 Consensus Statement (2026) — Infectious Diseases Society of America
- Clinical Practice Guidelines for the Management of Patients with Histoplasmosis: 2007 Update — Clinical Infectious Diseases (2007)
- Histoplasmosis: Adult and Adolescent Opportunistic Infection Guidelines — NIH ClinicalInfo.HIV.gov (updated 2024, reviewed 2026)
- Histoplasmosis — Merck Manual Professional Edition (2025)
- Histoplasmosis — StatPearls, NCBI Bookshelf (2026)
- HUMIRA (adalimumab) Prescribing Information, Boxed Warning — DailyMed, National Library of Medicine (2025)
- Amphotericin B — StatPearls, NCBI Bookshelf (2024)
- Blastomycosis — Merck Manual Professional Edition (2025)
- Coccidioidomycosis — Merck Manual Professional Edition (2025)
- Paracoccidioidomycosis — Merck Manual Professional Edition (2025)
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
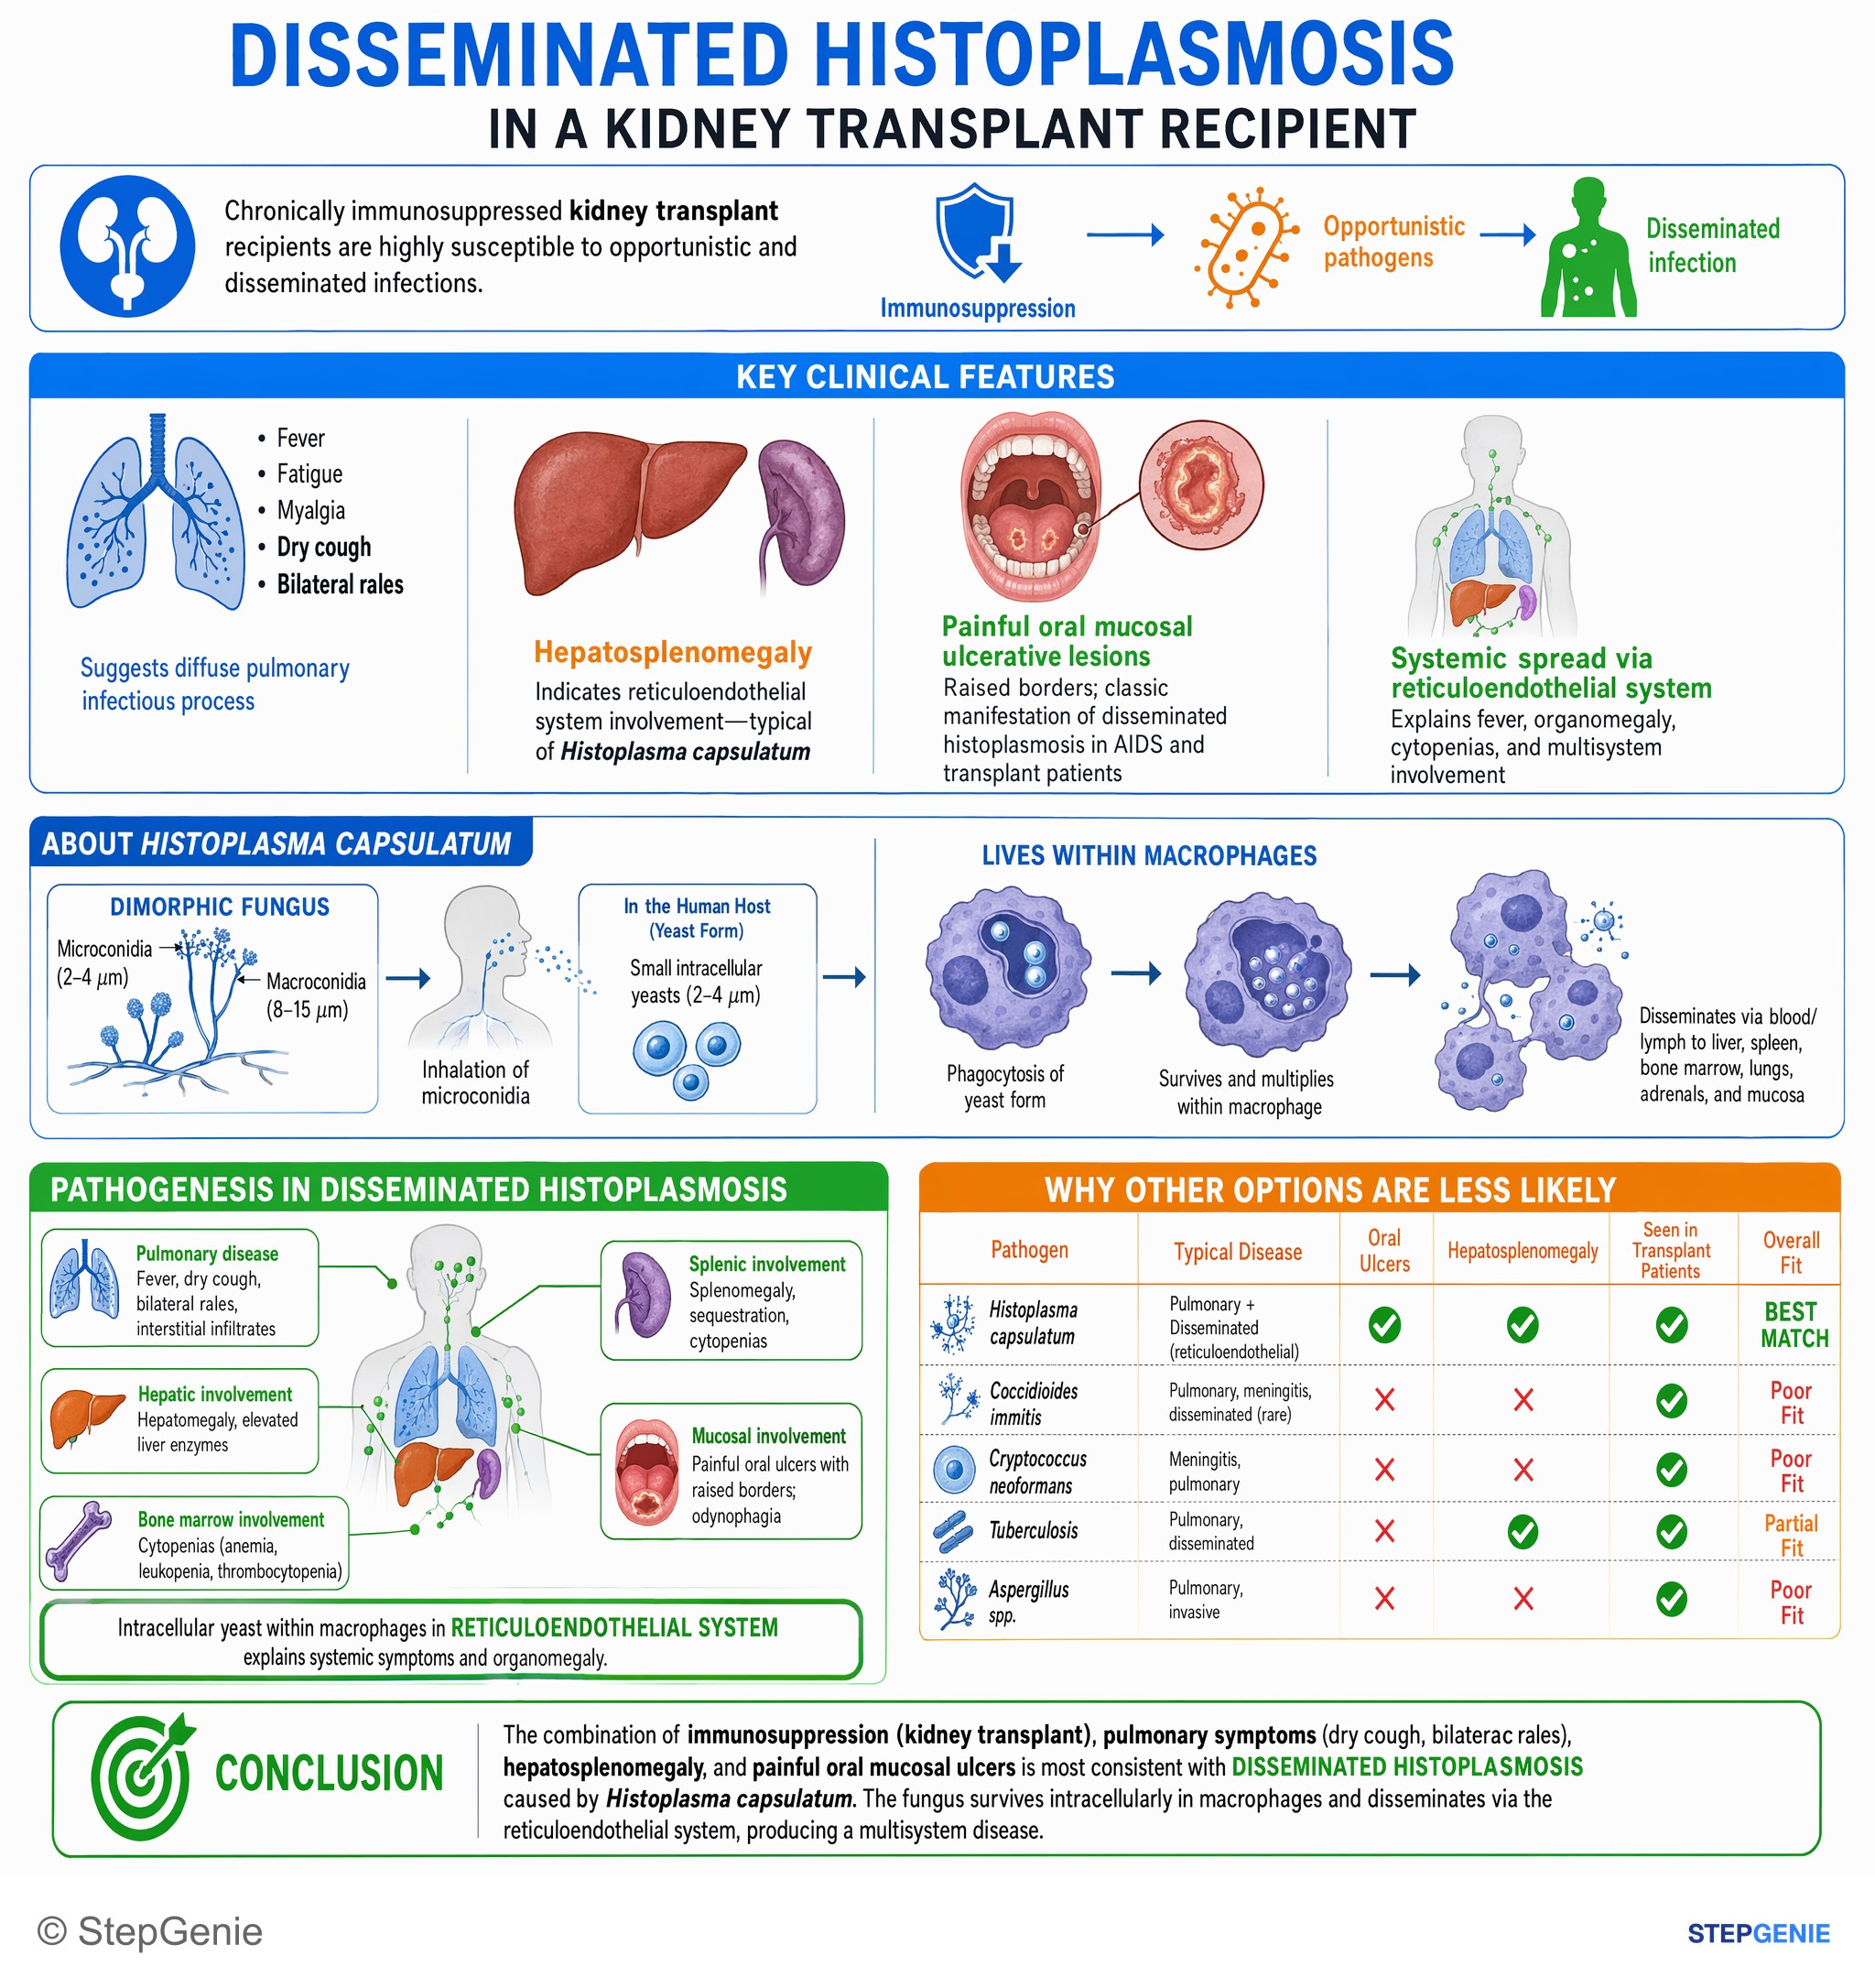
Disseminated histoplasmosis in an immunosuppressed transplant patient causes pulmonary disease, hepatosplenomegaly, and painful oral…
USMLE Step 2Frequently Asked Questions
Where is Histoplasma capsulatum found?
Histoplasma capsulatum lives in soil contaminated with bird or bat droppings, so caves, chicken coops, construction and landscaping are classic exposures. In the United States it is concentrated in the central and eastern states, especially the Ohio and Mississippi River valleys, but CDC now says its distribution is likely nationwide, and outbreaks have occurred where it was not expected. It is also found in Central and South America, Africa, Asia and Australia. It does not spread from person to person.
What does Histoplasma look like under the microscope?
Histoplasma is thermally dimorphic: it grows as a mold in soil and in culture at room temperature, and as a small oval yeast, about 2 to 4 micrometers across, at body temperature. In tissue the yeasts are typically found inside macrophages, which is the classic exam clue. Blastomyces is a much larger yeast with broad-based buds, and Coccidioides forms large spherules filled with endospores rather than yeasts.
What are the signs of disseminated histoplasmosis?
Progressive disseminated histoplasmosis occurs mainly in people with impaired cell-mediated immunity, such as advanced HIV (risk rises once the CD4 count falls below 150 per cubic millimeter), TNF-alpha inhibitor therapy, transplant immunosuppression or high-dose corticosteroids, and also in infants and older adults. It causes fever, weight loss and fatigue with hepatosplenomegaly, lymphadenopathy, pancytopenia from bone marrow involvement, and oral or gastrointestinal ulcers. Adrenal involvement can rarely cause Addison disease. Untreated, it has a high mortality.
What is the best test for histoplasmosis?
Histoplasma antigen testing by enzyme immunoassay on urine and serum is the key rapid test, especially in disseminated disease, where urine antigen is positive in more than 90 percent of patients and serum antigen in about 80 percent. It cross-reacts with Blastomyces. Culture confirms the diagnosis but can take up to 6 weeks, histopathology is fast but insensitive, and antibodies take 2 to 6 weeks to appear, so serology is less useful early or in immunosuppressed patients.
How is histoplasmosis treated?
Most mild acute pulmonary infections resolve without antifungals. Under IDSA's 2025 guideline update, moderate acute pulmonary disease may be treated or observed, and immunocompromised patients at moderate to high risk of dissemination are generally treated, with itraconazole 200 mg three times daily for 3 days and then twice daily for 6 to 12 weeks. IDSA's 2026 consensus statement starts severe disease with liposomal amphotericin B, followed by itraconazole; disseminated disease is treated for at least 12 months in total. Azoles are avoided in the first trimester of pregnancy when possible.
How is histoplasmosis different from tuberculosis?
Both cause granulomatous lung disease with hilar adenopathy, calcified nodes and apical cavities, and chronic cavitary histoplasmosis can closely resemble cavitary tuberculosis. The differences: Histoplasma is a fungus acquired from soil with bird or bat droppings and is not spread from person to person, its tissue form is small yeasts inside macrophages rather than acid-fast bacilli, it is diagnosed with antigen tests and fungal culture, and it is treated with itraconazole or amphotericin B rather than antituberculous drugs.