Five Plasmodium species infect humans, and most exam questions turn on three contrasts. P. falciparum is the dangerous one: it invades red cells of every age, sticks to small-vessel walls and causes cerebral malaria, and its smear shows multiple delicate rings and banana-shaped gametocytes. P. vivax and P. ovale relapse from dormant liver hypnozoites, while P. malariae causes a 72-hour (quartan) fever and nephrotic syndrome. Every patient needs a blood-stage drug (artemether-lumefantrine for chloroquine-resistant falciparum, IV artesunate for severe malaria), and vivax or ovale also needs primaquine or tafenoquine to clear hypnozoites, but only after G6PD testing.
Tip 1: Give each species one signature
| Species | Red cells it infects | Classic fever cycle | Signature fact |
|---|---|---|---|
| P. falciparum | All ages, so parasitemia can climb very high | Irregular | Severe malaria: cerebral malaria, severe anemia, ARDS, kidney injury |
| P. vivax | Reticulocytes; invasion needs the Duffy antigen | Every 48 hours (tertian) | Relapse from hypnozoites; rare splenic rupture |
| P. ovale | Reticulocytes | Every 48 hours (tertian) | Relapse from hypnozoites; oval, sometimes fimbriated red cells |
| P. malariae | Older red cells | Every 72 hours (quartan) | Low-level infection that can persist for decades; immune complex nephrotic syndrome |
| P. knowlesi | — | Every 24 hours | Macaque malaria of Southeast Asia, especially Malaysia; parasitemia rises fast and can be fatal |
The one-line version: falciparum kills, vivax and ovale come back, malariae hits the kidney. The 48- and 72-hour rhythms appear only once an infection is established, and falciparum is usually irregular, so questions lean more on the smear, the complication and the treatment than on fever timing.
Two host traits are favorite genetics tie-ins. Sickle cell trait (HbAS) protects against severe falciparum malaria, which helps explain why the HbS allele is common where falciparum is endemic (see the sickle cell disease cheat sheet). Lack of the Duffy blood group gives most sub-Saharan African populations resistance to P. vivax, although rare vivax infections in Duffy-negative people have been documented.
Tip 2: Read the smear like a board question
Giemsa-stained blood smears remain the standard test. The thick smear examines more blood, so it is more sensitive for finding parasites; the thin smear identifies the species and measures percent parasitemia. One negative set does not rule malaria out: CDC advises repeating smears every 12–24 hours for a total of three sets. A negative rapid antigen test does not rule malaria out either, so microscopy is always ordered alongside it.
| Species | Infected red cell | Forms to recognize |
|---|---|---|
| P. falciparum | Normal size | Several delicate rings in one cell, appliqué (accolé) rings on the cell edge, crescent ("banana") gametocytes, Maurer clefts; mature trophozoites and schizonts are seldom seen because they sequester in vessels |
| P. vivax | Enlarged 1.5–2 times, may be distorted | Large amoeboid trophozoites, fine Schüffner dots |
| P. ovale | Normal to slightly enlarged, oval, sometimes fimbriated | Compact trophozoites; Schüffner dots may be seen |
| P. malariae | Normal or small | Band-form trophozoites, rosette schizonts, coarse dark-brown pigment |
| P. knowlesi | — | Early rings resemble falciparum; older forms resemble malariae |
Babesia is the classic look-alike. It also produces ring forms inside red cells, but the stem adds a tick bite in the Northeast or Midwest of the United States and often an asplenic, immunosuppressed or older patient. The smear shows pleomorphic rings and tetrads (the "Maltese cross") and, unlike malaria, no hemozoin pigment.
Tip 3: Treat by stage: blood stage for everyone, liver stage for vivax and ovale
The blood-stage drug stops symptoms and complications. The liver-stage drug, needed only for vivax and ovale, kills hypnozoites so the infection cannot relapse. The table follows current CDC guidance for the United States.
| Situation | Treatment | Exam point |
|---|---|---|
| Uncomplicated falciparum or unknown species acquired where parasites are chloroquine resistant (most of the world) | Artemether-lumefantrine is preferred; atovaquone-proguanil is second line | Falciparum, knowlesi and unknown species are hospitalized at first because they can worsen fast |
| Uncomplicated falciparum from a chloroquine-sensitive area (Central America west of the Panama Canal, Haiti, Dominican Republic) | Chloroquine or hydroxychloroquine | Chloroquine blocks polymerization of heme into hemozoin, so toxic free heme builds up inside the parasite |
| P. vivax or P. ovale | Chloroquine (except vivax from Papua New Guinea or Indonesia, where chloroquine resistance is common) plus primaquine for 14 days or single-dose tafenoquine | Quantitative G6PD test first; tafenoquine only if G6PD is normal and the patient is at least 16 |
| P. malariae or P. knowlesi, confirmed | Chloroquine or hydroxychloroquine | No hypnozoites, so no liver-stage drug |
| Severe malaria, any species | IV artesunate at 0, 12 and 24 hours, then a full oral course such as artemether-lumefantrine | Check for delayed hemolysis weekly for 4 weeks after artesunate |
Two safety rules are tested again and again:
- G6PD before primaquine or tafenoquine. Both drugs can cause hemolysis in G6PD deficiency, so G6PD activity is measured before either is given. The mechanism and the other classic triggers are in the G6PD deficiency overview.
- Neither drug in pregnancy. Primaquine and tafenoquine are contraindicated because of the risk of fetal hemolysis. Pregnant patients with vivax or ovale take weekly chloroquine for the rest of the pregnancy, and anti-relapse therapy is considered after delivery if G6PD activity is normal.
Older question banks list IV quinidine for severe malaria. It has not been available in the United States since April 2019, when IV artesunate became the first-line US treatment. Quinine, still an oral option, aggravates malarial hypoglycemia by driving insulin release.
The life cycle in one pass
- A female Anopheles mosquito injects sporozoites, which head to the liver.
- In hepatocytes they mature into liver schizonts that release merozoites. This stage causes no symptoms; the incubation period is usually 7–30 days, shortest with falciparum and longest with malariae.
- In P. vivax and P. ovale, some liver forms stay dormant as hypnozoites and can reactivate months later, up to about 2 years after infection.
- Merozoites invade red cells and cycle through ring, trophozoite and schizont; rupture of infected cells releases new merozoites and brings fever, chills and hemolysis.
- Some parasites become gametocytes, the sexual forms a feeding mosquito takes up to complete the cycle.
Relapse vs recrudescence. A relapse comes from hypnozoites and happens only with vivax and ovale. Recrudescence is the return of blood-stage parasites that were never cleared (inadequate or poorly absorbed treatment, poor adherence, drug resistance) and can happen with any species. P. malariae can smolder at low levels for decades without any liver reservoir, so a late recurrence is not a reason to give primaquine.
Why falciparum kills: sequestration and severe malaria
Falciparum-infected red cells display PfEMP1, which makes them stick to endothelium and form rosettes with uninfected cells. The cells sequester in the small vessels of the brain, lungs, kidneys and placenta, causing tissue hypoxia. That explains cerebral malaria (a diffuse, symmetric encephalopathy with seizures and coma), ARDS, acute kidney injury, acidosis, and placental malaria with low birth weight and miscarriage. Blackwater fever is massive intravascular hemolysis with dark urine (hemoglobinuria) and kidney failure, classically described in repeated falciparum infections treated with quinine.
CDC defines severe malaria as any one of the following and recommends IV artesunate for every species:
- Impaired consciousness or coma, prostration, seizures
- Severe anemia (hemoglobin below 7 g/dL)
- Acute kidney injury, pulmonary edema or ARDS, shock
- Acidosis, jaundice, hypoglycemia, abnormal bleeding or DIC
- Parasite density of 5% or more (the WHO uses a higher cutoff of 10%)
Exam traps
- No fever rhythm does not mean no malaria. Falciparum is irregular, and periodicity appears only in established infection. A febrile traveler from an endemic area needs smears.
- One negative smear is not enough. Repeat every 12–24 hours for three sets, and always pair a rapid test with microscopy.
- Vivax or ovale treated with chloroquine alone relapses weeks to months later. The missing drug is primaquine or tafenoquine.
- Primaquine without a G6PD test is the classic hemolysis setup; in pregnancy, use weekly chloroquine instead.
- A P. malariae recurrence years later is recrudescence, not relapse, because malariae forms no hypnozoites.
- "IV quinidine" is an outdated answer; IV artesunate is first-line for severe malaria.
- Ring forms after a tick bite in New England suggest babesiosis, not malaria.
Worked example
Vignette. A 29-year-old woman has fever and shaking chills every other day. Five months ago she returned from 6 weeks in India, where she took no malaria prophylaxis, and 3 months ago she had a similar illness that resolved with chloroquine alone. A thin smear shows enlarged red cells with fine stippling (Schüffner dots) and large amoeboid trophozoites. Her pregnancy test is negative. Along with chloroquine, what must be done before giving the drug that prevents another recurrence?
Answer: A quantitative G6PD test, then primaquine for 14 days (or single-dose tafenoquine if G6PD activity is normal).
Reasoning: Enlarged red cells, Schüffner dots and a 48-hour fever point to P. vivax. Her recurrence came from liver hypnozoites that chloroquine never touched, so she needs a liver-stage drug, and both options can cause severe hemolysis in G6PD deficiency. Chloroquine still works for the blood stage because the infection came from India, not Papua New Guinea or Indonesia.
Key takeaways
- Five species infect humans; P. falciparum causes severe malaria because it infects red cells of all ages and sequesters through PfEMP1.
- Falciparum smear: multiple delicate rings, appliqué forms, banana gametocytes, normal-sized red cells.
- Vivax and ovale: reticulocytes, Schüffner dots, 48-hour fever, hypnozoites and relapse; add primaquine or tafenoquine after a G6PD test, never in pregnancy.
- Malariae: 72-hour fever, band forms, nephrotic syndrome, decades-long low-level infection without hypnozoites.
- Treatment: artemether-lumefantrine for uncomplicated chloroquine-resistant falciparum, chloroquine where parasites are sensitive, IV artesunate for any severe malaria, including parasitemia of 5% or more.
- Diagnosis: thick smear to detect, thin smear to identify the species; repeat three times before ruling malaria out.
Sources
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
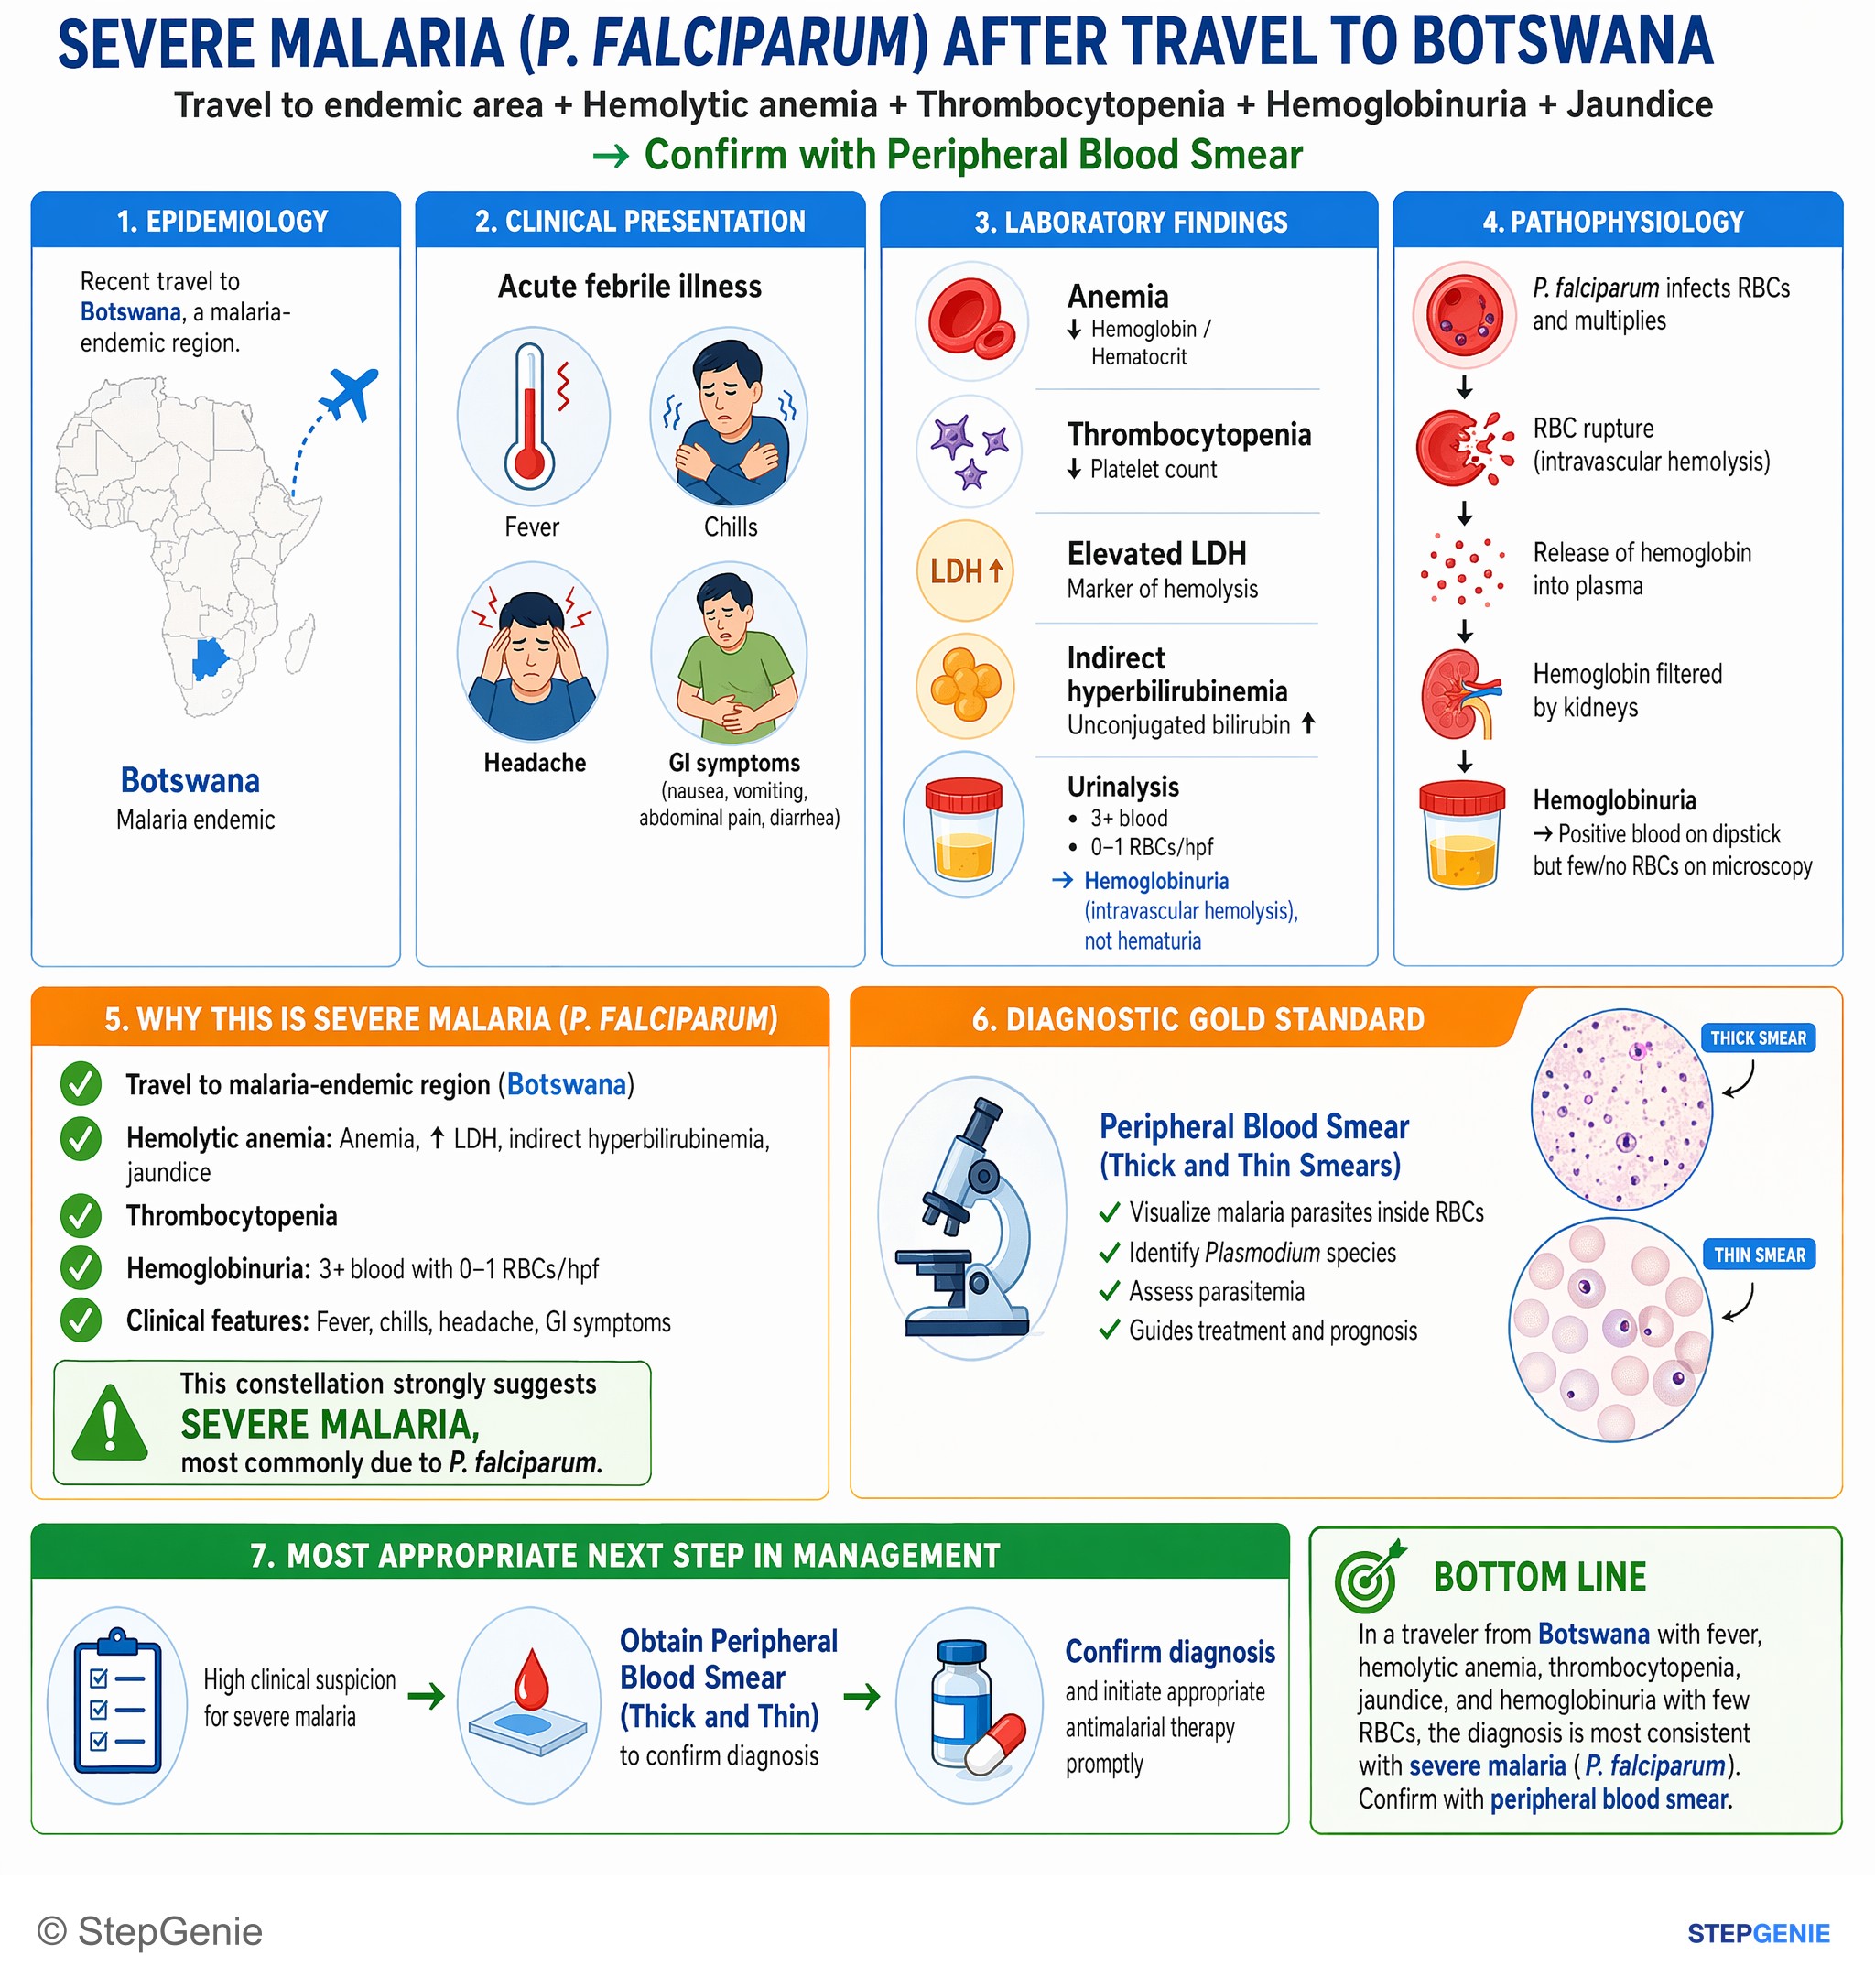
Severe malaria after travel to Botswana: fever, hemolytic anemia, thrombocytopenia, jaundice, hemoglobinuria with few RBCs → confirm with…
USMLE Step 2Frequently Asked Questions
Which Plasmodium species cause relapsing malaria?
Plasmodium vivax and Plasmodium ovale cause relapsing malaria because some of their liver-stage parasites stay dormant as hypnozoites and can reactivate months later, up to about 2 years after infection. Treating the blood stage alone does not touch hypnozoites, so these patients also need primaquine or tafenoquine after G6PD testing. P. falciparum and P. malariae form no hypnozoites, although P. malariae can persist at low levels in the blood for decades.
Why is Plasmodium falciparum the most dangerous malaria species?
P. falciparum infects red blood cells of all ages, so parasitemia can climb very high. Infected cells express PfEMP1, stick to endothelium and sequester in the small vessels of the brain, lungs, kidneys and placenta, causing cerebral malaria, ARDS, kidney injury, acidosis and severe anemia. Severe falciparum malaria is treated with IV artesunate.
How do you tell Plasmodium species apart on a blood smear?
The thin smear identifies the species. P. falciparum shows several delicate rings in normal-sized red cells, appliqué forms and banana-shaped gametocytes; P. vivax enlarges the red cell and shows Schüffner dots; P. ovale gives oval, sometimes fimbriated cells; and P. malariae shows band-form trophozoites and rosette schizonts. The thick smear is more sensitive for detecting parasites but is not the one used to identify the species.
Why do you need a G6PD test before primaquine?
Primaquine and tafenoquine, the drugs that kill vivax and ovale hypnozoites, can cause hemolysis in people with G6PD deficiency. CDC advises quantitative G6PD testing before either drug, and tafenoquine is given only when G6PD activity is normal. Both drugs are avoided in pregnancy, so pregnant patients take weekly chloroquine for the rest of the pregnancy instead.
What is the treatment for severe malaria?
IV artesunate is first-line for severe malaria of any species, given at 0, 12 and 24 hours and followed by a full oral course such as artemether-lumefantrine. CDC defines severe malaria as any one of a list of findings, such as impaired consciousness, seizures, severe anemia, kidney injury, ARDS, shock, acidosis or hypoglycemia, or a parasitemia of 5% or more. IV quinidine, the older answer, has not been available in the United States since 2019.