You’ve probably noticed that H. pylori questions are rarely just “what bug is this?” They’re usually testing a chain: risk factors → symptoms → pathophys → diagnostics → complications → treatment. The fastest way to boost your score is to treat every answer choice like a mini-flashcard: why it’s right, why the others are wrong, and what clue would’ve made them right.
The Vignette (Classic USMLE Style)
A 46-year-old man presents with burning epigastric pain that improves with meals but returns a few hours later. He has nausea and a history of intermittent NSAID use. No weight loss. Stool is guaiac-positive. Endoscopy shows a duodenal ulcer. A urea breath test is positive.
Question: Which virulence factor most directly contributes to this organism’s ability to colonize the stomach?
Answer choices
A. Coagulase
B. Urease
C. Heat-labile enterotoxin (LT)
D. Shiga toxin
E. Capsule composed of D-glutamate
Step-by-Step: What’s Being Tested?
The stem screams duodenal ulcer + positive urea breath test → Helicobacter pylori.
Key vignette clues:
- Duodenal ulcer (classically improves with meals)
- Urea breath test positive (strongly points to urease-producing organisms)
- Occult blood (ulcer complication)
- Age and intermittent symptoms (common presentation)
Correct Answer: B. Urease
Why urease matters (mechanism + test relevance)
H. pylori is a Gram-negative, curved/spiral-shaped, microaerophilic rod that colonizes the gastric antrum.
- Urease converts urea into ammonia () and carbon dioxide ():
- The ammonia buffers gastric acid, creating a more hospitable microenvironment around the bacteria.
- This enzyme is the basis of:
- Urea breath test (detects labeled in exhaled air)
- Rapid urease test on biopsy (CLO test)
High-yield extras you should attach to this concept
H. pylori clinical associations:
- Chronic gastritis (often antral-predominant early)
- Peptic ulcer disease (especially duodenal)
- Gastric adenocarcinoma
- MALT lymphoma (extranodal marginal zone lymphoma)
Virulence factors beyond urease:
- Flagella → motility through mucus
- Adhesins → attach to epithelium
- CagA (type IV secretion system) → inflammation, ↑ cancer risk
- VacA → epithelial injury, ulceration
Treatment (Step 2 favorite):
- Bismuth quadruple therapy (common first-line in many settings):
PPI + bismuth + tetracycline + metronidazole - Alternative (where appropriate): PPI + clarithromycin + amoxicillin/metronidazole (resistance patterns matter)
Test-of-cure:
- Use urea breath test or stool antigen (not serology)
- Test after stopping PPI ~2 weeks and antibiotics/bismuth ~4 weeks (common exam pearl)
Distractor Breakdown: Why Each Wrong Choice Was Tempting (and How to Recognize It)
A. Coagulase
Why it’s wrong: Coagulase is a Staphylococcus aureus virulence factor (Gram-positive cocci in clusters), not a Gram-negative spiral rod.
What would’ve made it right:
- Skin/soft tissue infection, abscesses (“pus”)
- Pneumonia post-influenza
- Endocarditis in IVDU
- Rapid latex agglutination for clumping factor/protein A, etc.
High-yield tie-in: Coagulase helps S. aureus form fibrin clots → immune evasion.
C. Heat-labile enterotoxin (LT)
Why it’s wrong: LT is produced by ETEC (enterotoxigenic E. coli), causing watery traveler’s diarrhea, not ulcers.
Mechanism you’re supposed to know:
- LT activates adenylate cyclase → ↑ → ↑ chloride secretion → watery diarrhea
(Similar mechanism to cholera toxin)
What would’ve made it right:
- Recent travel, watery diarrhea, no blood or fever
- Often self-limited; supportive care
D. Shiga toxin
Why it’s wrong: Shiga toxin points to EHEC (E. coli O157:H7) or Shigella, causing bloody diarrhea and risk of HUS—not gastric colonization and ulcers.
Mechanism (classic USMLE):
- Shiga(-like) toxin inactivates 60S ribosomal subunit by removing adenine from rRNA → inhibits protein synthesis
What would’ve made it right:
- Bloody diarrhea after undercooked beef/unpasteurized products (EHEC)
- HUS triad: hemolytic anemia, thrombocytopenia, AKI
- Typically low/no fever in EHEC (helps separate from invasive causes)
E. Capsule composed of D-glutamate
Why it’s wrong: That capsule is basically a neon sign for Bacillus anthracis (Gram-positive spore-forming rod), not H. pylori.
What would’ve made it right:
- Painless black eschar (cutaneous anthrax)
- Widened mediastinum (inhalational anthrax)
- Exposure to animal hides/wool (“woolsorter’s disease”)
High-yield micro distinction: Anthrax capsule = poly-D-glutamate (unusual because many capsules are polysaccharide).
Quick Comparison Table (High-Yield Sorting)
| Answer Choice | Organism Classically Linked | Toxin/Factor | Typical Presentation |
|---|---|---|---|
| Coagulase | Staph aureus | Coagulase | Abscesses, endocarditis, post-flu pneumonia |
| Urease | H. pylori | Urease | Duodenal ulcer, chronic gastritis, + urea breath test |
| LT toxin | ETEC | ↑ | Watery traveler’s diarrhea |
| Shiga toxin | EHEC / Shigella | Inhibits 60S | Bloody diarrhea ± HUS |
| D-glutamate capsule | B. anthracis | Capsule | Eschar, mediastinitis |
USMLE “Clue-to-Conclusion” Pattern for H. pylori
When you see any combination of:
- Duodenal ulcer (pain improves with meals)
- Chronic gastritis
- Iron deficiency anemia (chronic blood loss)
- Positive urea breath test/stool antigen
- MALT lymphoma history
Think:
- Colonization strategy → urease + flagella
- Mucosal injury → inflammation (CagA/VacA), altered somatostatin/gastrin balance
- Complications → ulcer, cancer, lymphoma
- Treat and confirm eradication → appropriate regimen + test-of-cure
Takeaway: How to Use Distractors to Study Faster
In a good Q-bank question, distractors are not random—they’re curated to test whether you can:
- Match virulence factor → organism
- Match organism → clinical syndrome
- Use one or two stem clues to eliminate whole categories fast
For H. pylori, the highest-yield anchor is urease—because it’s both how it survives and how we test for it.
Visual explanations from the StepGenie QBank
Infographics StepGenie drew to explain questions in its own QBank, matched to this article's topic. Each caption is the takeaway of the question it explains.
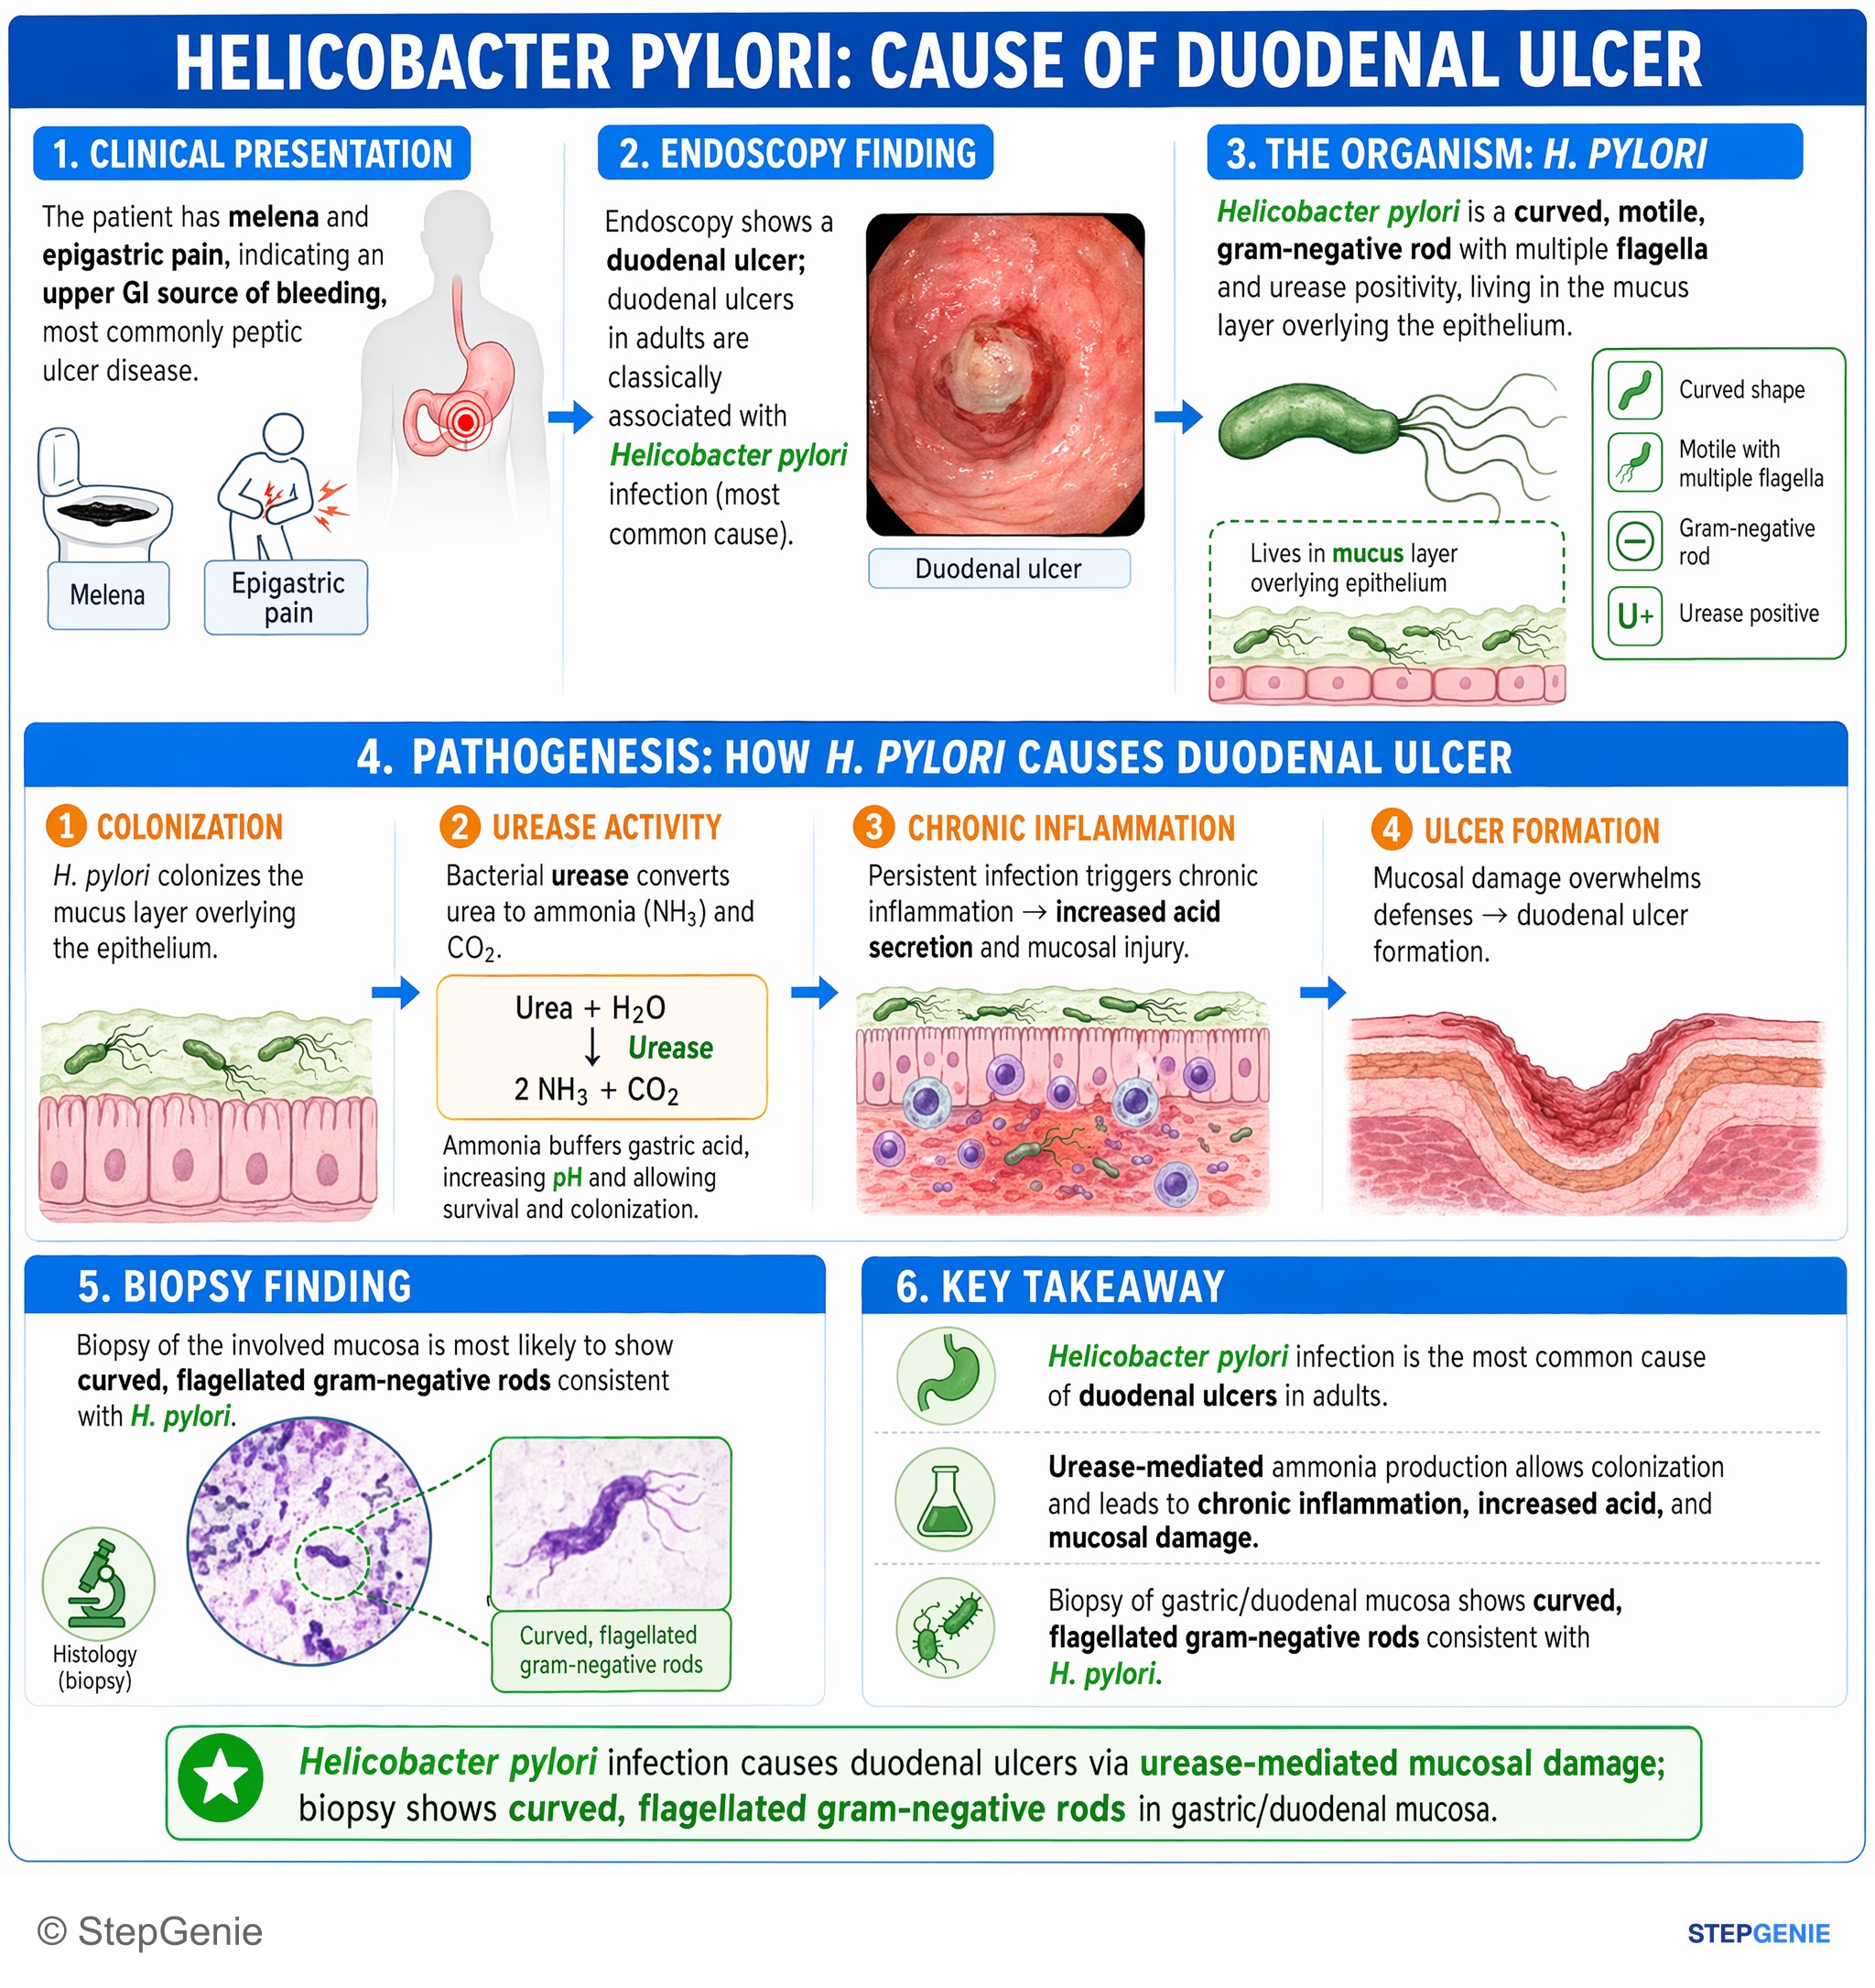
Helicobacter pylori infection causes duodenal ulcers via urease-mediated mucosal damage; biopsy shows curved, flagellated gram-negative…
USMLE Step 1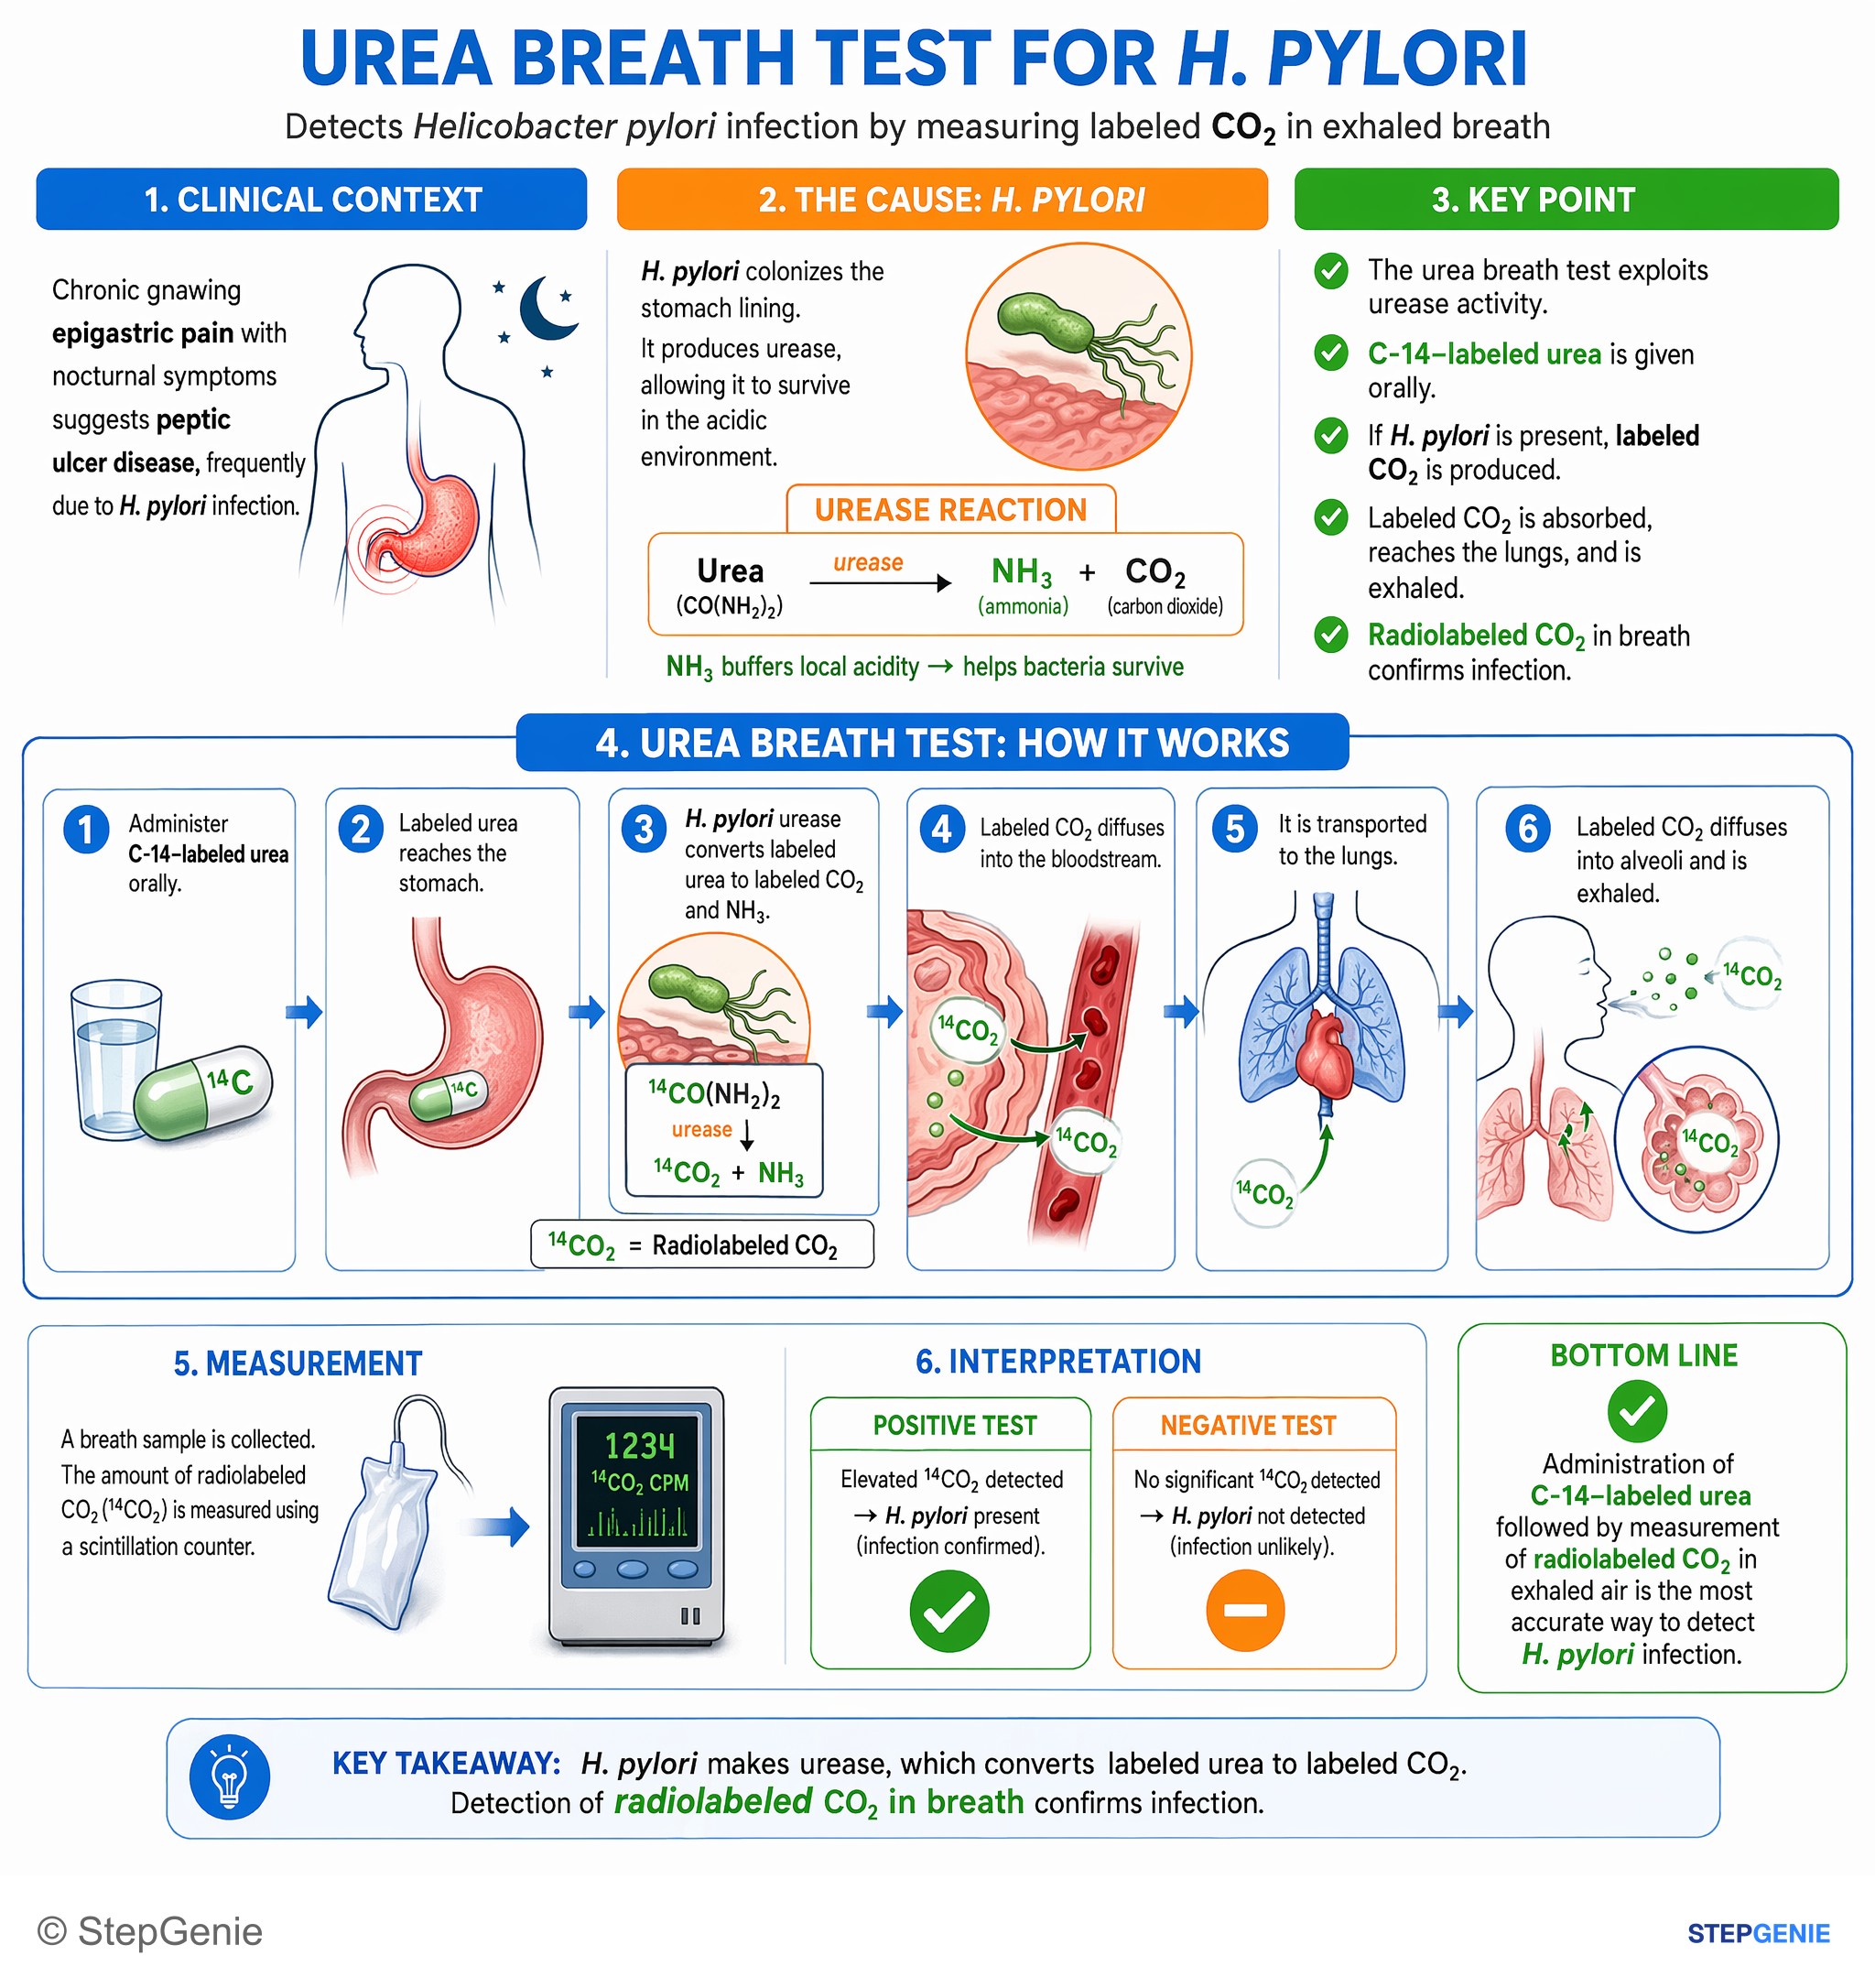
Helicobacter pylori makes urease, which converts labeled urea to labeled CO₂; detection of radiolabeled CO₂ in breath confirms infection.
USMLE Step 1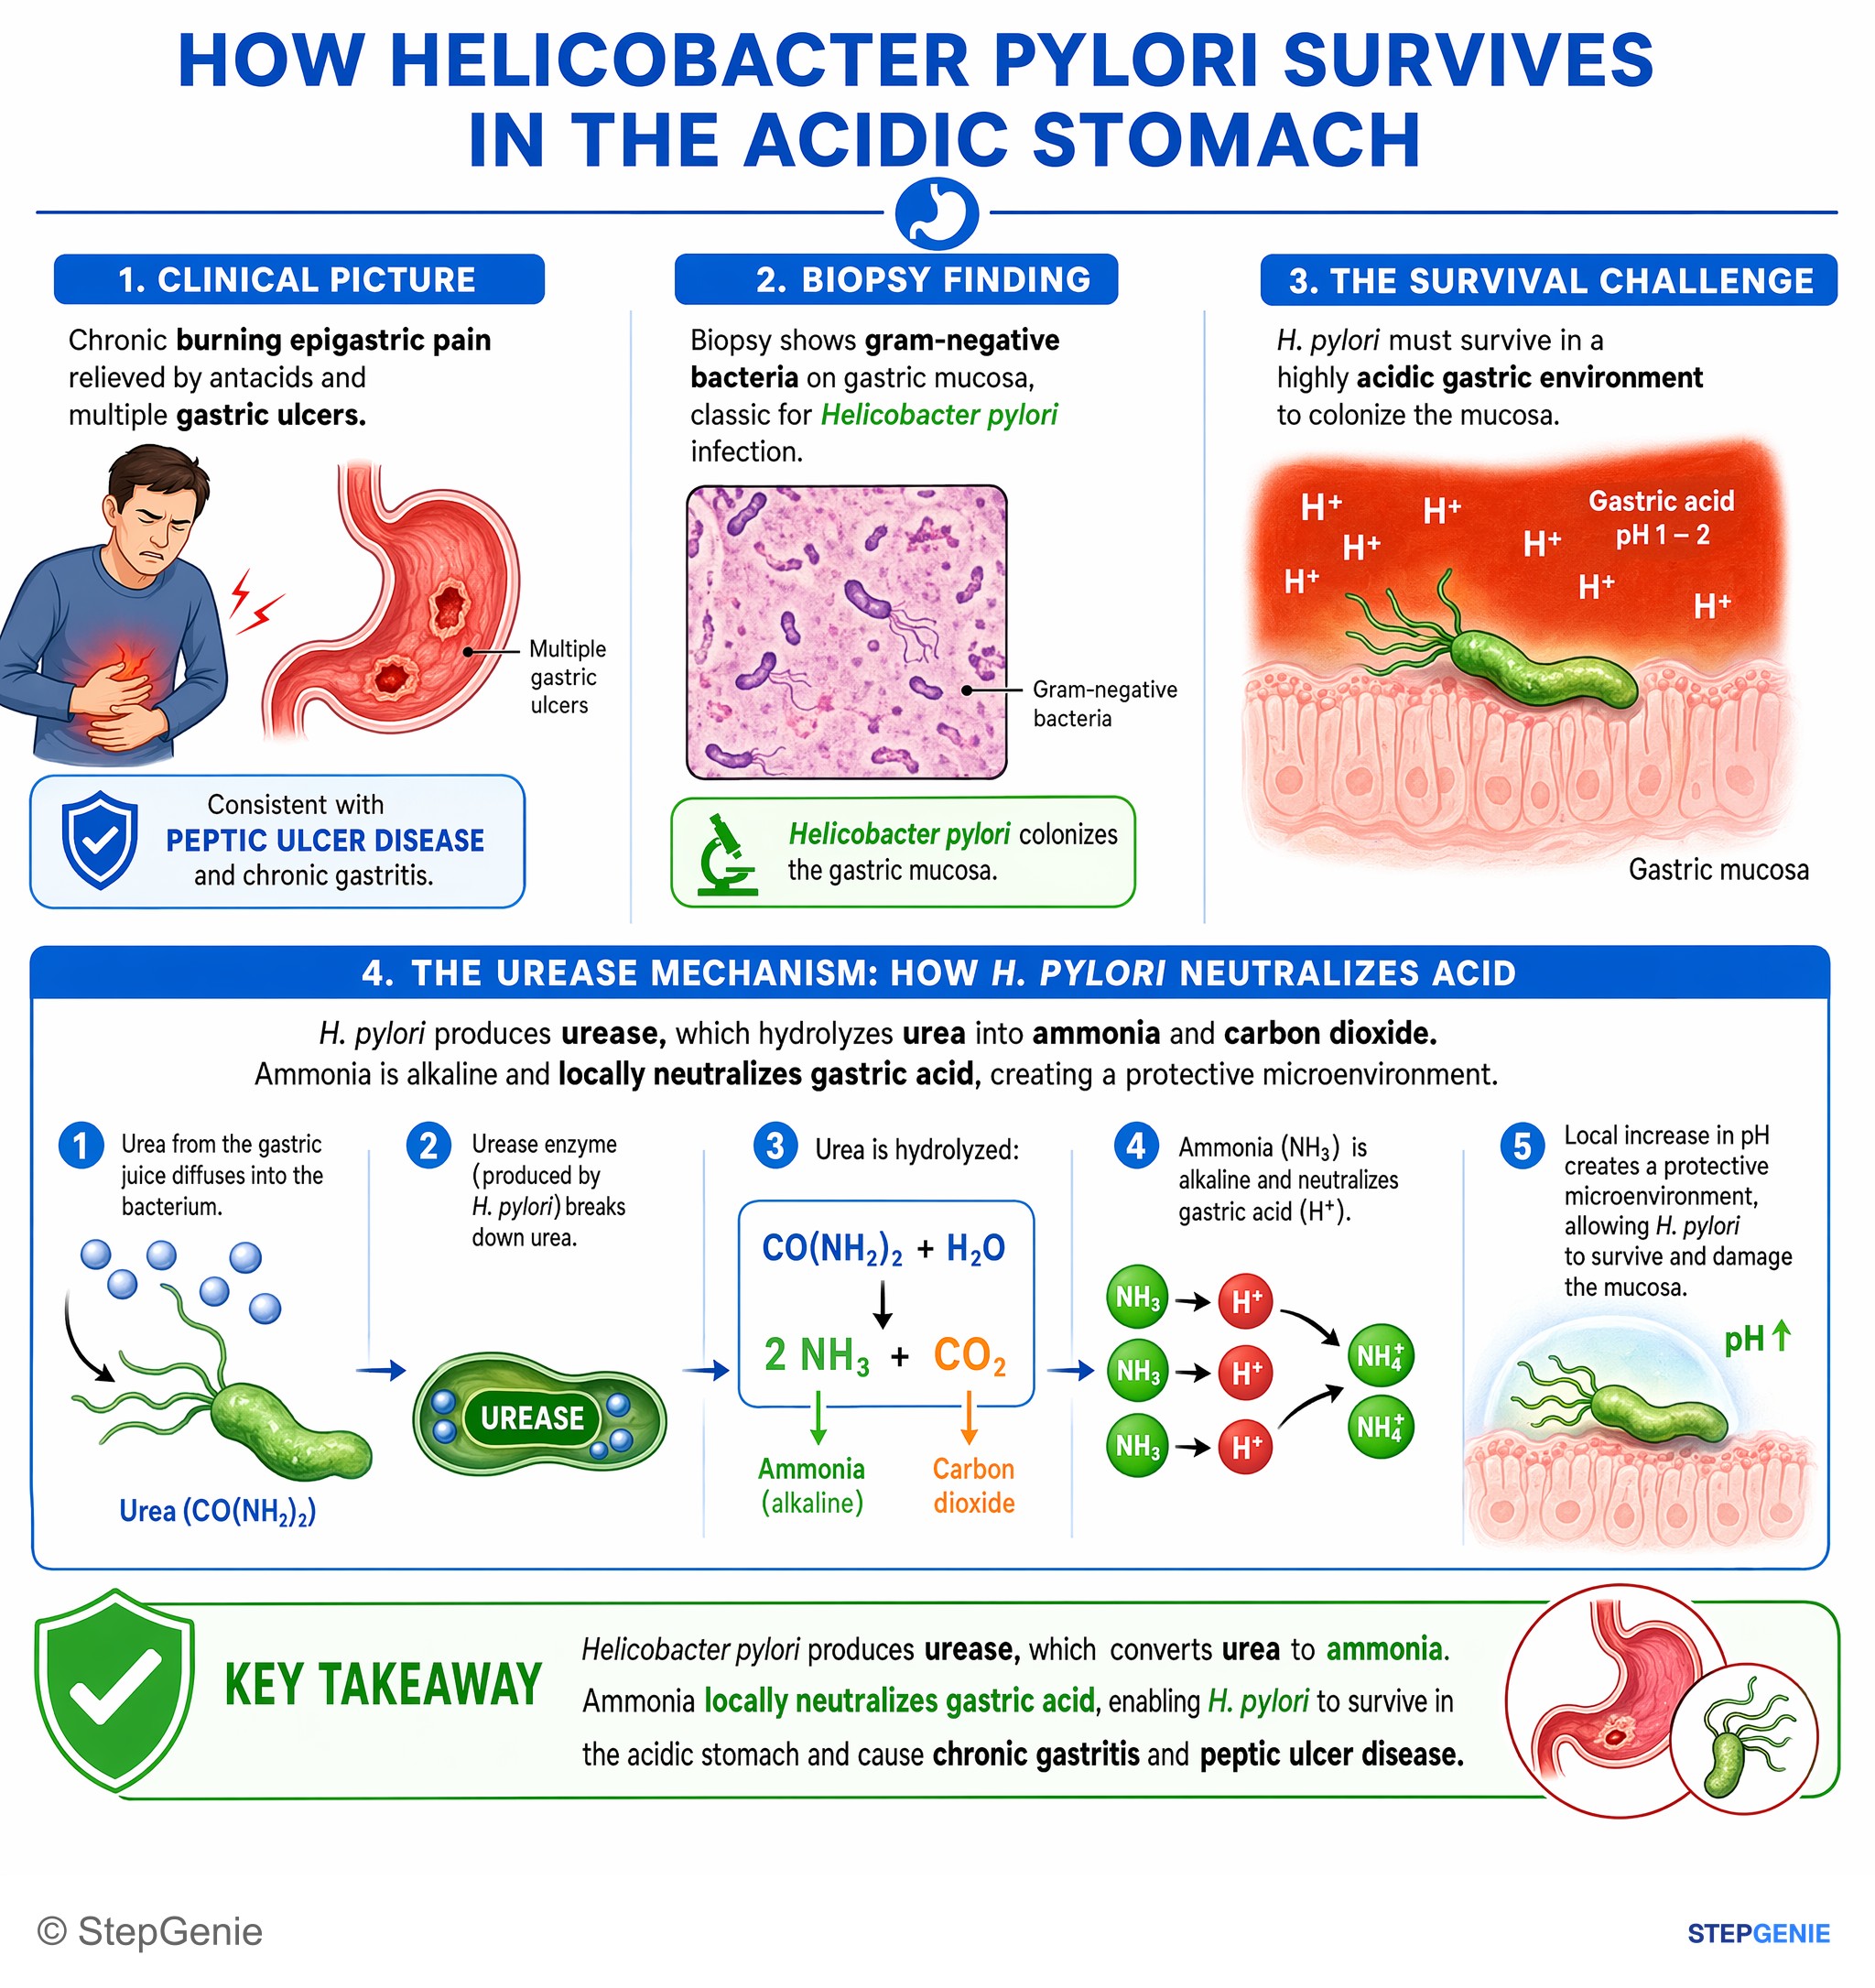
Helicobacter pylori produces urease, which converts urea to ammonia, locally neutralizing gastric acid and enabling survival in the acidic…
USMLE Step 1Frequently Asked Questions
Why does Helicobacter pylori use urease to colonize the stomach?
Helicobacter pylori colonizes the stomach by producing urease, which converts urea into ammonia and carbon dioxide. The ammonia buffers gastric acid, creating a more hospitable microenvironment around the bacteria. This acid-neutralizing effect helps a Gram-negative, curved, microaerophilic rod survive in the gastric antrum and is a key reason urease is the organism’s classic colonization factor.
How does a urea breath test identify Helicobacter pylori?
A urea breath test identifies Helicobacter pylori by detecting carbon dioxide generated from bacterial urease activity. H. pylori breaks down urea into ammonia and carbon dioxide, and the labeled carbon dioxide is then measured in exhaled air. Because the test relies on urease production, a positive result strongly points to this urease-producing organism in the right clinical setting.
What clues in a vignette point to Helicobacter pylori causing a duodenal ulcer?
The classic clues are burning epigastric pain that improves with meals, a duodenal ulcer on endoscopy, and a positive urea breath test. Nausea and guaiac-positive stool also support the diagnosis, with occult blood reflecting an ulcer complication. Together, these findings fit Helicobacter pylori, which is strongly associated with duodenal ulcers and chronic gastritis.
How do you tell Helicobacter pylori from ETEC or EHEC on a microbiology question?
Helicobacter pylori points to ulcers and a positive urea breath test, whereas ETEC causes watery traveler’s diarrhea and EHEC causes bloody diarrhea with possible HUS. ETEC’s heat-labile toxin increases cAMP, while Shiga-like toxin from EHEC inhibits the 60S ribosomal subunit. Those diarrheal toxin patterns do not explain gastric colonization or duodenal ulcer disease, which instead suggests H. pylori urease.
What is the first-line treatment and test-of-cure approach for Helicobacter pylori?
A common first-line treatment is bismuth quadruple therapy: a proton pump inhibitor, bismuth, tetracycline, and metronidazole. An alternative in appropriate settings is a proton pump inhibitor with clarithromycin plus amoxicillin or metronidazole. To confirm eradication, use a urea breath test or stool antigen rather than serology, after stopping PPIs for about 2 weeks and antibiotics or bismuth for about 4 weeks.